Vitamin C and Immune Defense
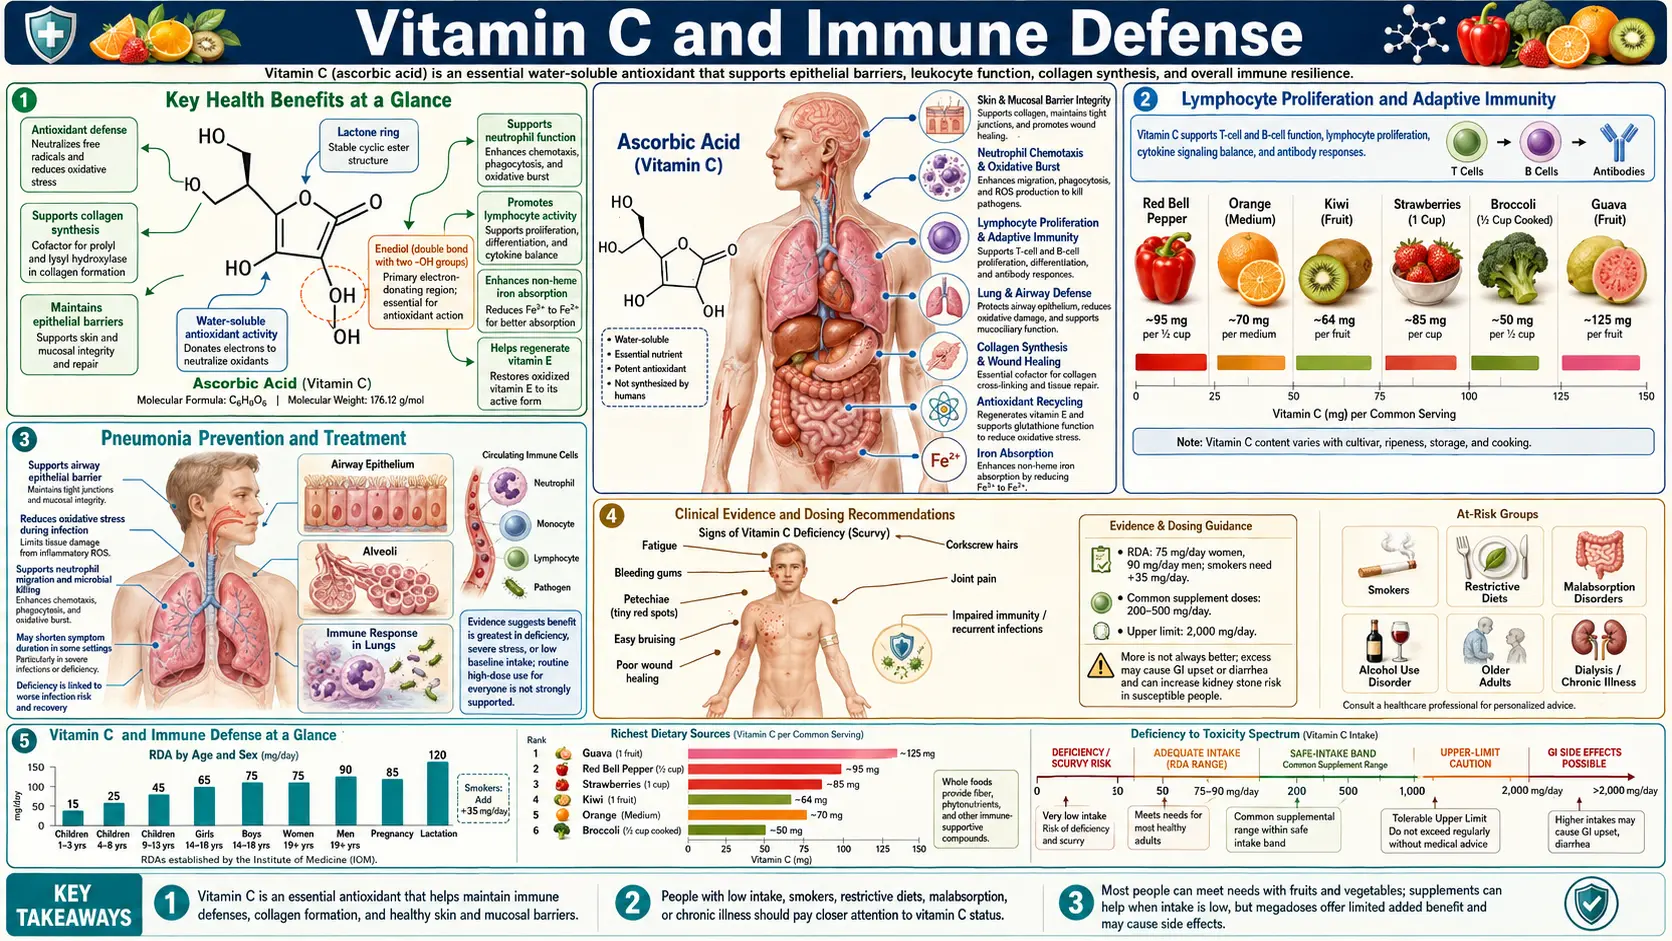
Vitamin C (ascorbic acid) is one of the most extensively studied nutrients in the context of immune function, and it occupies an almost unique position: immune cells concentrate ascorbate at levels 10 to 100 times higher than plasma, reflecting how much they depend on it. Both innate defenses (neutrophils, macrophages, natural killer (NK) cells, antimicrobial peptides, type I interferons) and adaptive responses (T and B lymphocytes, antibody production, epigenetic TET-enzyme regulation) require adequate vitamin C status to perform optimally. This article reviews the cellular mechanisms, the high-quality Cochrane evidence on the common cold, the pneumonia-prevention trials, the mixed picture from intravenous-vitamin-C sepsis research, and the evidence-based dosing for healthy and at-risk populations.
Interactive Visualization Vitamin C, Collagen & Why Sailors Fell Apart Zip three protein chains into the strongest rope in biology — then take the vitamin C away and watch the helix unravel, and old healed scars split back open. Launch →Table of Contents
- Key Health Benefits at a Glance
- Neutrophil Function
- Macrophage Activation
- Natural Killer Cell Enhancement
- Lymphocyte Proliferation and Adaptive Immunity
- Cathelicidin, Antimicrobial Peptides, and Interferons
- Common Cold: Meta-Analysis Results
- Pneumonia Prevention and Treatment
- Sepsis and Critical Care: Intravenous Vitamin C Protocols
- High-Dose Vitamin C Research
- The Linus Pauling Legacy
- Clinical Evidence and Dosing Recommendations
- Key Research Papers
- Connections
- Featured Videos
Key Health Benefits at a Glance
Before the detailed mechanisms, the following is a high-level summary of the evidence-backed immune benefits of adequate vitamin C status. Each bullet is developed below, and supporting studies are linked in the Key Research Papers section.
- Concentrates in immune cells – Neutrophils, lymphocytes, and monocytes accumulate vitamin C at 10–100 times plasma levels, highlighting its central role in immune defense.
- Boosts neutrophil function – Ascorbate enhances chemotaxis, phagocytosis, oxidative burst, and apoptotic clearance, reducing collateral tissue damage at infection sites.
- Supports natural killer cell cytotoxicity – Supplementation has been shown to enhance natural killer cell killing of virus-infected and transformed cells in clinical studies.
- Supports lymphocyte biology and epigenetics – Vitamin C is a cofactor for the TET DNA-demethylation enzymes, shaping T-cell differentiation and memory formation.
- Shortens common colds – The Cochrane meta-analysis (Hemilä & Chalker, 2013) documented 8% shorter colds in adults and 14% shorter in children with regular supplementation; cold incidence is cut roughly in half in people under severe physical stress.
- Lowered pneumonia in three small older trials – Three controlled trials in military recruits and boys at a wartime boarding school (37 pneumonia cases among 2,335 people) each found an 80% or greater reduction in pneumonia; the 2013 Cochrane review judged this evidence too weak to support preventive use in the general population.
- Works with vitamin D on antimicrobial peptides – Ascorbate synergizes with vitamin D to upregulate cathelicidin (LL-37), a peptide that directly kills bacteria, fungi, and enveloped viruses.
- Enhances type I interferon production – Vitamin C supports IFN-alpha and IFN-beta output, amplifying the antiviral state in neighboring cells.
- Runs critically low in sepsis – Septic patients exhibit scorbutic plasma levels. Intravenous (IV) vitamin C has been tested in large randomized trials: VITAMINS and VICTAS found no benefit, LOVIT found a higher risk of death or persistent organ dysfunction, and the 2021 Surviving Sepsis Campaign guideline suggests against intravenous vitamin C in sepsis or septic shock.
- Supports mucosal barrier immunity – Ascorbate supports beta-defensin production by respiratory and gastrointestinal epithelium, reinforcing the first line of defense.
Neutrophil Function
Neutrophils are the first responders of the innate immune system, and vitamin C plays an essential role in multiple aspects of their function.
- Chemotaxis – Vitamin C enhances the directed migration of neutrophils toward sites of infection. Studies demonstrate that ascorbate-replete neutrophils exhibit significantly improved chemotactic movement compared to vitamin C-deficient cells. The nutrient supports cytoskeletal reorganization required for cell motility through its effects on microtubule assembly and actin polymerization.
- Phagocytosis – The engulfment and internalization of pathogens by neutrophils is augmented in the presence of adequate vitamin C. Ascorbate enhances recognition of opsonized bacteria and facilitates the membrane remodeling necessary for phagosome formation. Vitamin C-deficient individuals show measurably reduced phagocytic capacity.
- Oxidative Burst – During the respiratory burst, neutrophils generate reactive oxygen species (ROS) to kill ingested microorganisms. Vitamin C supports the reduced nicotinamide adenine dinucleotide phosphate (NADPH) oxidase enzyme complex responsible for superoxide production. Simultaneously, ascorbate protects the neutrophil itself from oxidative self-damage through its antioxidant properties, thereby extending neutrophil lifespan and functional capacity.
- Neutrophil Extracellular Traps (NETs) – Emerging research suggests that vitamin C may modulate the formation of NETs, web-like structures of DNA and antimicrobial proteins that neutrophils release to trap and kill extracellular pathogens.
- Apoptosis and Clearance – Vitamin C promotes timely apoptosis of spent neutrophils and enhances their clearance by macrophages (efferocytosis), a process critical for resolving inflammation and preventing tissue damage at infection sites.
What the randomized trials show: a 2019 systematic review of 16 randomized controlled trials (Liugan and Carr) found effects of vitamin C on neutrophil function in 44% of them. Two of the three trials that measured neutrophil movement (chemotaxis) found improvement, both after intravenous vitamin C in patients. The authors noted that the studies were very heterogeneous, with different groups of people and different doses.
Macrophage Activation
Macrophages serve as both phagocytic defenders and orchestrators of immune responses. Vitamin C influences macrophage function through several mechanisms.
- Enhanced Phagocytic Activity – Ascorbate-loaded macrophages demonstrate greater capacity to engulf and destroy bacteria, fungi, and cellular debris. Vitamin C supports the generation of phagolysosomal killing mechanisms.
- Cytokine Production – Vitamin C modulates macrophage cytokine output, promoting the release of pro-inflammatory mediators during active infection while supporting the transition to anti-inflammatory signaling during the resolution phase. This dual role helps prevent excessive inflammation while maintaining pathogen clearance.
- M1/M2 Polarization – Research indicates that vitamin C may influence macrophage polarization, supporting the pro-inflammatory M1 phenotype during acute infection and facilitating the shift to the tissue-repair M2 phenotype during recovery.
Natural Killer Cell Enhancement
Natural killer (NK) cells provide rapid cytotoxic responses against virus-infected cells and tumor cells. Vitamin C supports natural killer cell function in several ways.
- Cytotoxic Activity – Supplementation with vitamin C has been shown to enhance natural killer cell cytolytic activity by 20 to 50% in some clinical studies. Ascorbate supports the production and release of perforin and granzymes, the primary effector molecules of natural killer cell killing.
- Natural killer Cell Proliferation – Vitamin C promotes the expansion of natural killer cell populations during immune challenge, ensuring adequate numbers of these critical effector cells are available during viral infections.
- Recognition of Targets – Adequate vitamin C status supports the expression of activating receptors on the natural killer cell surface, improving the ability to detect and respond to abnormal cells.
Lymphocyte Proliferation and Adaptive Immunity
The adaptive immune system, comprising T cells and B cells, also depends on vitamin C for optimal function.
- T Cell Proliferation – Vitamin C is required for robust clonal expansion of T lymphocytes following antigen recognition. In vitro studies show that ascorbate enhances mitogen-stimulated T cell proliferation by supporting the metabolic demands of rapidly dividing cells.
- T Cell Differentiation – Vitamin C influences epigenetic regulation through its role as a cofactor for ten-eleven translocation (TET) enzymes, which catalyze DNA demethylation. This activity is important for proper T cell maturation and differentiation into effector and memory subsets.
- B Cell Function and Antibody Production – Adequate ascorbate status supports B cell maturation and immunoglobulin synthesis. Vitamin C-deficient animals produce lower antibody titers in response to immunization.
Cathelicidin, Antimicrobial Peptides, and Interferons
- Cathelicidin (LL-37) – Vitamin C works synergistically with vitamin D to upregulate the expression of cathelicidin, a potent antimicrobial peptide produced by neutrophils, macrophages, and epithelial cells. LL-37 directly kills bacteria, fungi, and enveloped viruses by disrupting their membranes, and also serves as a chemoattractant for immune cells.
- Defensins – Ascorbate supports the production of beta-defensins by epithelial barrier cells, contributing to mucosal immunity in the respiratory and gastrointestinal tracts.
- Interferon Production – Vitamin C enhances the synthesis of type I interferons (IFN-alpha and IFN-beta), which are critical for antiviral defense. Interferons induce an antiviral state in neighboring cells by upregulating hundreds of interferon-stimulated genes (ISGs) that inhibit viral replication at multiple stages. Cell culture studies demonstrate increased interferon output from ascorbate-treated leukocytes exposed to viral stimuli.
Common Cold: Meta-Analysis Results
The relationship between vitamin C and the common cold has been studied in numerous randomized controlled trials. The Cochrane Collaboration meta-analysis by Hemilä and Chalker (2013) provides the most comprehensive summary.
- Incidence – Regular supplementation with 200 mg or more of vitamin C daily did not reduce the incidence of colds in the general population (general-community trials with 10,708 people; risk ratio 0.97). However, in individuals under heavy physical stress (marathon runners, soldiers in subarctic environments, skiers), regular vitamin C supplementation reduced cold incidence by approximately 50% (five trials with 598 people; risk ratio 0.48).
- Duration – Consistent supplementation reduced cold duration by 8% in adults and 14% in children; in children, 1 to 2 g a day shortened colds by 18%. This translates to roughly half a day shorter illness for adults and a full day shorter for children.
- Severity – Several trials reported reduced symptom severity scores in the supplemented groups, with less time confined to bed or absent from work or school.
- Therapeutic Use – In the seven comparisons of vitamin C taken after cold symptoms begin (3,249 cold episodes), the Cochrane review saw no consistent effect on the duration or severity of colds. A 2017 review by Hemilä notes that two controlled trials found a dose-response for cold duration with up to 6 to 8 g a day, and suggests that some negative treatment trials may be explained by lower doses of 3 to 4 g a day.
Pneumonia Prevention and Treatment
- Prevention – Three controlled trials (two in military recruits, one in boys at a UK boarding school during World War II) found that vitamin C supplementation (200 mg to 2 g daily) reduced pneumonia incidence by 80% or more in the supplemented groups. The 2013 Cochrane review (Hemilä and Louhiala) notes that these trials recorded only 37 pneumonia cases among 2,335 people, that only one was satisfactorily randomized, double-blind and placebo-controlled, and that the evidence is too weak to support preventive use of vitamin C in the general population.
- Treatment – Observational data and limited trial evidence suggest that vitamin C supplementation in hospitalized pneumonia patients may reduce duration of illness and improve outcomes, particularly when baseline vitamin C levels are low.
- Elderly Populations – In older adults already in hospital with pneumonia in the UK, one placebo-controlled trial found lower mortality and less severe illness with vitamin C, but the benefit was restricted to the most ill patients.
- 2024 Meta-Analysis – A 2024 meta-analysis of six randomized trials in adults treated for community-acquired pneumonia found a non-significant trend toward fewer deaths with vitamin C (risk ratio 0.51, 95% confidence interval 0.24 to 1.09, p = 0.052); the authors called the findings inconclusive.
Sepsis and Critical Care: Intravenous Vitamin C Protocols
The use of intravenous vitamin C in critically ill patients has generated significant clinical interest.
- Rationale – Critically ill patients, especially those with sepsis, exhibit dramatically depleted plasma vitamin C levels, often reaching scorbutic concentrations below 11 micromol/L. This depletion correlates with organ dysfunction and mortality. Intravenous administration bypasses the saturable intestinal absorption that limits oral dosing.
- Marik Protocol – Dr. Paul Marik’s combination protocol using intravenous vitamin C (1.5 g every 6 hours), hydrocortisone, and thiamine generated initial excitement with a 2017 retrospective before-after study: 47 treated patients were compared with 47 patients treated in the same intensive care unit during the preceding 7 months, with hospital deaths of 8.5% vs 40.4%. It was not a randomized trial. The randomized controlled trials that followed found no benefit: VITAMINS (2020; 216 patients with septic shock) found no difference from hydrocortisone alone in time alive and free of vasopressors, and VICTAS (2021; 501 patients) found no difference from placebo in ventilator- and vasopressor-free days.
- LOVIT Trial – The LOVIT trial (2022; 872 adults with sepsis on vasopressors in intensive care) found that intravenous vitamin C, 50 mg/kg every 6 hours for up to 96 hours, led to a higher risk of death or persistent organ dysfunction at 28 days than placebo (44.5% vs 38.5%).
- 2021 Surviving Sepsis Campaign Guideline – The 2021 Surviving Sepsis Campaign guideline, published before LOVIT, already suggests against using intravenous vitamin C for adults with sepsis or septic shock (weak recommendation, low-quality evidence); its pooled analysis of seven randomized trials (416 critically ill patients) found that vitamin C did not reduce deaths compared with usual care (risk ratio 0.79, 95% confidence interval 0.57 to 1.1).
- Ongoing Research – Research continues into dosing, patient selection and timing. A 2026 meta-analysis of 14 randomized trials (1,958 patients) found lower 28-day mortality with intravenous vitamin C overall (risk ratio 0.70), but the benefit came from single-center studies and was not confirmed in low-risk-of-bias multicenter trials.
High-Dose Vitamin C Research
- Pharmacokinetics – Oral vitamin C absorption is saturable, with bioavailability dropping from nearly 100% at low doses to below 50% at doses exceeding 1 gram. Padayatty and colleagues (Ann Intern Med 2004) measured a peak plasma level of 134.8 micromol/L after 1.25 g by mouth versus 885 micromol/L after the same dose intravenously; their model predicted peaks of 220 micromol/L for the maximum tolerated oral dose (3 g every 4 hours) versus 13,400 micromol/L for a 50 g intravenous dose.
- Pro-Oxidant Activity – At the very high plasma concentrations achievable only through intravenous administration, vitamin C can generate hydrogen peroxide in the extracellular space. This pro-oxidant effect is selectively toxic to certain cancer cells while normal cells are protected by catalase activity. This mechanism underlies research into high-dose intravenous vitamin C as an adjunctive cancer therapy.
- Safety Considerations – High-dose intravenous vitamin C is generally well tolerated but is contraindicated in patients with glucose-6-phosphate dehydrogenase (G6PD) deficiency due to the risk of hemolytic anemia. High-dose intravenous vitamin C can falsely raise some finger-stick glucose meter readings, and in people with kidney disease it has been linked to oxalate kidney damage (oxalate nephropathy).
The Linus Pauling Legacy
Nobel laureate Linus Pauling brought vitamin C into mainstream consciousness with his 1970 book Vitamin C and the Common Cold. Pauling advocated for gram-dose supplementation, far exceeding the Recommended Dietary Allowance (RDA), based on evolutionary arguments (most mammals synthesize their own vitamin C) and emerging clinical data. While some of Pauling’s more expansive claims were not fully validated by subsequent research, his advocacy catalyzed decades of productive scientific investigation. Modern immunology has largely confirmed that vitamin C plays a far more significant role in immune defense than was appreciated before Pauling’s work, even if the optimal supplemental doses remain debated.
Clinical Evidence and Dosing Recommendations
- Recommended Dietary Allowance vs. Optimal Intake – The current Recommended Dietary Allowance for vitamin C (75 mg for women, 90 mg for men) is designed to prevent scurvy with a margin of safety. However, immune cell saturation requires higher intakes. Research by Levine and colleagues (PNAS 1996) in seven healthy volunteers found that circulating immune cells were saturated at 100 mg daily and that 200 mg daily lies just past the steep part of the plasma curve (plasma was completely saturated only at 1,000 mg daily); the authors proposed 200 mg daily, obtainable from fruits and vegetables.
- During Infection – Metabolic demand for vitamin C increases dramatically during active infection. Some experts recommend 1 to 2 grams daily during acute illness, divided into multiple doses to maximize absorption.
- At-Risk Populations – Smokers require an additional 35 mg daily due to increased oxidative stress. The elderly, individuals under physical stress, and those with chronic illness may also benefit from higher intakes.
- Upper Limit – The tolerable upper intake level is set at 2 grams daily for adults, primarily based on the risk of gastrointestinal discomfort and diarrhea at higher doses. Serious adverse effects from oral vitamin C are rare.
- Food Sources – The richest dietary sources include bell peppers, citrus fruits, kiwi, strawberries, broccoli, Brussels sprouts, and tomatoes. Five servings of fruits and vegetables daily typically provide 200 mg or more of vitamin C.
This content is provided for informational purposes only and does not constitute medical advice. In the Levine 1996 study, urine oxalate and urate rose at 1,000 mg of vitamin C a day compared with lower doses, which matters for people with a history of kidney stones; high-dose intravenous vitamin C can break down red blood cells in glucose-6-phosphate dehydrogenase deficiency; and in chronic kidney disease high doses have been linked to oxalate kidney damage. The adult upper limit for oral vitamin C is 2 g a day.
Key Research Papers
The following are landmark and frequently cited research papers underpinning the claims on this page. Links resolve to the publisher DOI or PubMed record.
Pharmacokinetics
- Levine M, Conry-Cantilena C, Wang Y, et al. Vitamin C pharmacokinetics in healthy volunteers: evidence for a recommended dietary allowance. PNAS. 1996;93(8):3704-3709. — doi:10.1073/pnas.93.8.3704
- Padayatty SJ, Sun H, Wang Y, et al. Vitamin C pharmacokinetics: implications for oral and intravenous use. Annals of Internal Medicine. 2004;140(7):533-537. — doi:10.7326/0003-4819-140-7-200404060-00010
Immune Function — Mechanism and Review
- Carr AC, Maggini S. Vitamin C and immune function. Nutrients. 2017;9(11):1211. — doi:10.3390/nu9111211
- Liugan M, Carr AC. Vitamin C and neutrophil function: findings from randomized controlled trials. Nutrients. 2019;11(9):2102. — PubMed PMID: 31487891
- PubMed: Vitamin C and NK cell cytotoxicity (topic search)
- PubMed — Vitamin C, TET enzymes, and T-cell epigenetics (topic search)Search PubMed
Common Cold
- Hemilä H, Chalker E. Vitamin C for preventing and treating the common cold. Cochrane Database of Systematic Reviews. 2013;(1):CD000980. — doi:10.1002/14651858.CD000980.pub4
- Quidel S, Gómez E, Bravo-Soto G, Ortigoza Á. What are the effects of vitamin C on the duration and severity of the common cold? (Vitamin C taken during a cold had minimal or no impact on its duration.) Medwave. 2018;18(6):e7261. — PubMed PMID: 30339136
- Hemilä H. Vitamin C and infections. Nutrients. 2017;9(4):339. — PubMed PMID: 28353648
Pneumonia and Respiratory Infection
- Hemilä H, Louhiala P. Vitamin C for preventing and treating pneumonia. Cochrane Database of Systematic Reviews. 2013;(8):CD005532. — PubMed PMID: 23925826
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Scientific Reports. 2024;14(1):11846. — PubMed PMID: 38783029
- PubMed: Vitamin C and pneumonia prevention trials (topic search)
- PubMed: Vitamin C and respiratory infection in the elderly (topic search)
Sepsis and Critical Care
- Marik PE, Khangoora V, Rivera R, et al. Hydrocortisone, vitamin C, and thiamine for the treatment of severe sepsis and septic shock: a retrospective before-after study. Chest. 2017;151(6):1229-1238. — PubMed PMID: 27940189
- Fujii T, Luethi N, Young PJ, et al. Effect of vitamin C, hydrocortisone, and thiamine vs hydrocortisone alone on time alive and free of vasopressor support among patients with septic shock: the VITAMINS randomized clinical trial. JAMA. 2020;323(5):423-431. — PubMed PMID: 31950979
- Sevransky JE, Rothman RE, Hager DN, et al. Effect of vitamin C, thiamine, and hydrocortisone on ventilator- and vasopressor-free days in patients with sepsis: the VICTAS randomized clinical trial. JAMA. 2021;325(8):742-750. — PubMed PMID: 33620405
- Lamontagne F, Masse MH, Menard J, et al. Intravenous vitamin C in adults with sepsis in the intensive care unit. New England Journal of Medicine. 2022;386(25):2387-2398. — PubMed PMID: 35704292
- Evans L, Rhodes A, Alhazzani W, et al. Surviving sepsis campaign: international guidelines for management of sepsis and septic shock 2021. Intensive Care Medicine. 2021;47(11):1181-1247. — PubMed PMID: 34599691
- Cai B, Xiao Q, Xia Y, et al. Intravenous vitamin C as micronutrient therapy in patients with sepsis or septic shock: an updated systematic review and meta-analysis of randomized controlled trials. Frontiers in Nutrition. 2026;13:1905726. — PubMed PMID: 42761050
- PubMed: HAT protocol (hydrocortisone, ascorbic acid, thiamine) and sepsis (topic search)
- PubMed: LOVIT trial and high-dose IV vitamin C in sepsis (topic search)
- PubMed: VITAMINS trial and vitamin C in septic shock (topic search)
Antimicrobial Peptides and Interferons
- PubMed: Vitamin C, cathelicidin, and antimicrobial peptides (topic search)
- PubMed: Ascorbate and type I interferon antiviral defense (topic search)
External Authoritative Resources
- NIH Office of Dietary Supplements — Vitamin C Fact Sheet for Health Professionals
- Linus Pauling Institute — Micronutrient Information Center: Vitamin C
- Harvard T.H. Chan School of Public Health — The Nutrition Source: Vitamin C
- PubMed — Vitamin C and immune function systematic reviews (topic search)Search PubMed