⚠ Evidence warning: Clinical trials or other evidence do not support the claim that properly fitted hearing aids clinically reduce tinnitus distress in about 60-70 percent of tinnitus patients with hearing loss. This page keeps it as a report of what people, websites or other media say.
Tinnitus — Sound Therapy and Habituation
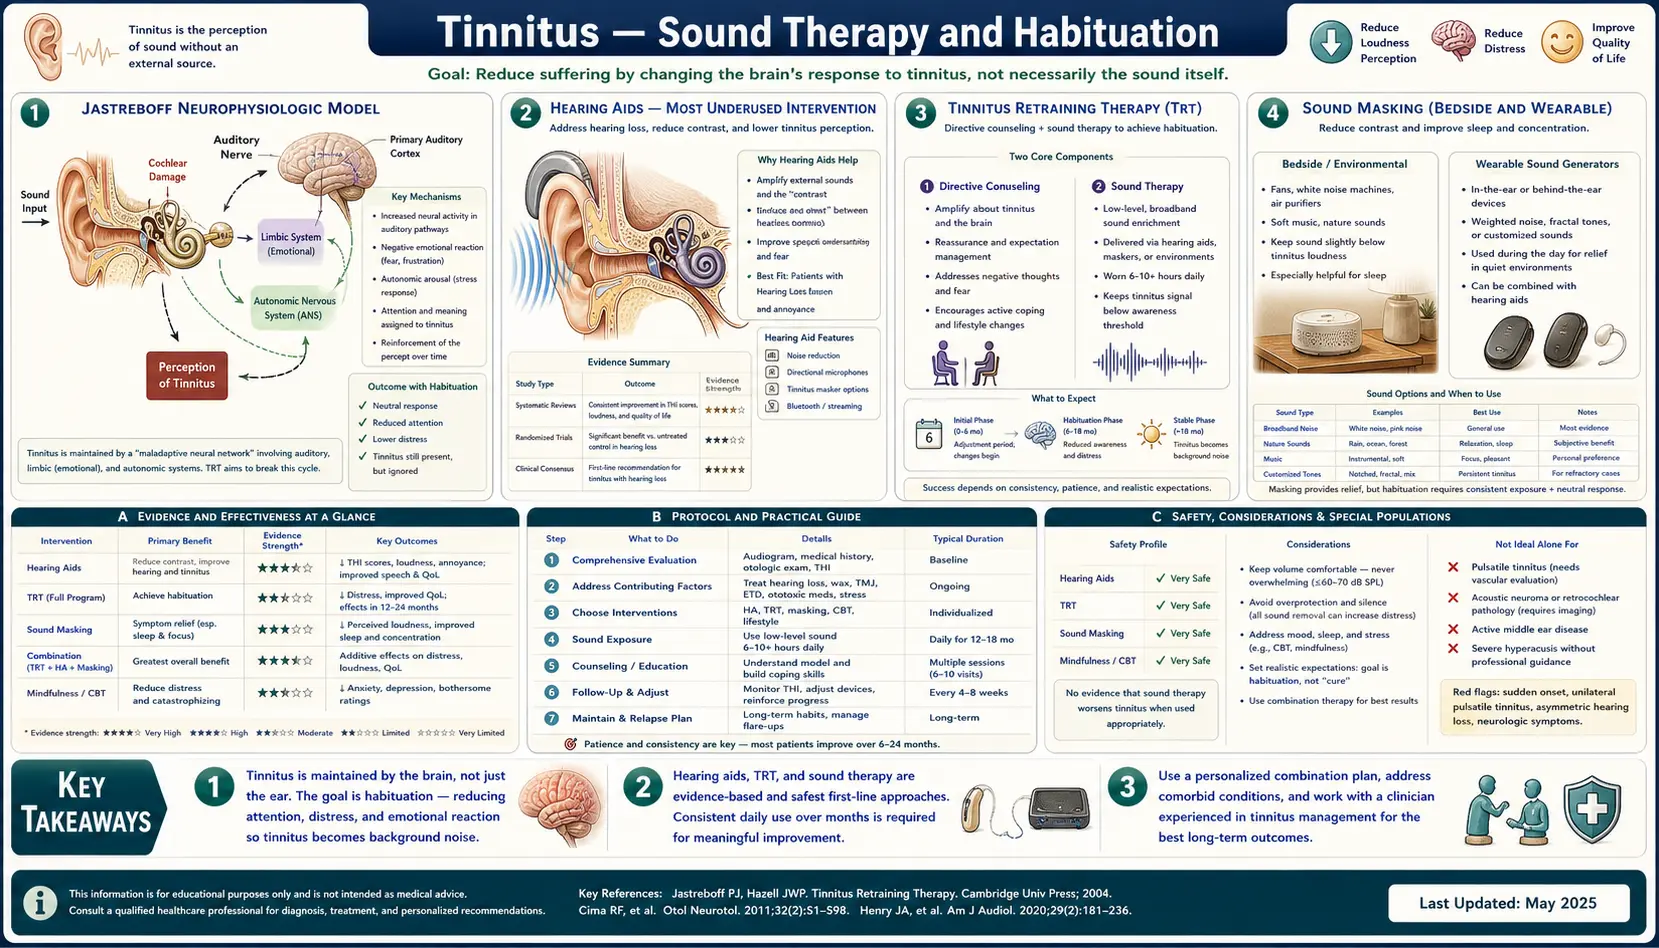
No drug has ever been U.S. Food and Drug Administration-approved for tinnitus. The interventions with the largest documented effect sizes in randomized trials and Cochrane reviews are not pharmacologic at all — they are sound-based and behavioral. Hearing-aid amplification, Tinnitus Retraining Therapy, sound masking, notched-music therapy, and cognitive-behavioral therapy each address a distinct component of the tinnitus experience. Their combination addresses the central neural plasticity that generates the phantom percept, the limbic-prefrontal filtering circuit that determines how distressing it feels, and the comorbid hearing loss that drives much of the underlying cortical hypersensitivity. This page walks through each modality, the Jastreboff neurophysiologic model that explains why they work, the American Academy of Otolaryngology–Head and Neck Surgery Foundation (AAO-HNS) guideline recommendations, and the order in which guidelines and trials describe these approaches.
Table of Contents
- The Jastreboff Neurophysiologic Model
- Hearing Aids — The Most Underused Intervention
- Tinnitus Retraining Therapy (TRT)
- Sound Masking (Bedside and Wearable)
- Notched-Music Therapy — Targeted Cortical Reorganization
- Cognitive-Behavioral Therapy (CBT)
- Bimodal Neuromodulation (Sound + Tongue Stimulation)
- The AAO-HNS Clinical Practice Guidelines (2014 and 2026)
- How Guidelines and Trials Order These Approaches
- Approaches the Research Does Not Support
- Key Research Papers
- Connections
- Featured Videos
The Jastreboff Neurophysiologic Model
Pawel Jastreboff's 1990 paper in Neuroscience Research reframed tinnitus from an "ear problem" to a "brain problem," and that conceptual shift is the foundation of every sound-and-behavior intervention now in clinical use. The neurophysiologic model has three core claims:
- The phantom signal originates in the central auditory pathway, not in the cochlea, even when the inciting event was peripheral (noise injury, ototoxin, presbycusis). The cochlear damage triggers central plasticity; the plasticity then generates the phantom percept regardless of ongoing peripheral activity.
- The distress generated by tinnitus is a function of limbic-system involvement, not of the perceived loudness of the phantom signal itself. Two patients with identical audiometric tinnitus matching can have radically different functional impact — one is barely bothered, the other suicidal — depending on how much limbic activation the phantom signal generates and how the prefrontal cortex evaluates its threat significance.
- Habituation, not suppression, is the therapeutic target. The phantom signal cannot reliably be eliminated. The achievable goal is to retrain the limbic-prefrontal circuit to demote the phantom signal to background noise — to learn to ignore it the way one learns to ignore the steady hum of a refrigerator or a fan. Healthy humans habituate to thousands of irrelevant background signals every day; the tinnitus patient's limbic system has failed to do so for this particular signal, and the therapeutic task is to re-establish that habituation.
This model produces immediate clinical predictions that have been borne out:
- Sound therapy works not by drowning out the tinnitus but by providing competing stimuli that the limbic system can learn to filter alongside the phantom signal
- Counseling about the benign nature of the signal directly reduces limbic activation by removing the threat interpretation
- Stress, anxiety, and depression worsen tinnitus because they impair the prefrontal filtering circuit
- Restoring hearing through amplification reduces central gain and the underlying drive for the phantom signal
- Most patients improve substantially over 12–18 months with appropriate intervention, even when the peripheral driver of the tinnitus cannot be reversed
Hearing Aids — The Most Underused Intervention
Approximately 80% of chronic tinnitus patients have some degree of sensorineural hearing loss on audiometry, and the frequency profile of the hearing loss typically matches the perceived pitch of the tinnitus. Hearing-aid amplification — treating the underlying hearing loss — is the single most underused effective intervention in tinnitus management.
The mechanism is straightforward in the Schaette-McAlpine central-gain model. The deafferented auditory cortex turns up its gain to compensate for reduced peripheral input from the damaged frequency region; the upregulated central gain amplifies spontaneous neural activity into the phantom signal. Hearing aids restore afferent input at the deafferented frequencies, allowing the central gain to normalize downward, and the phantom signal becomes quieter and easier to ignore.
What the trials show, and what is not known: the 2018 Cochrane review of sound therapy (Sereda et al.; 8 studies, 590 participants) found no trial that compared hearing aids, sound generators or combination devices with no device, a placebo or education alone, so it found no evidence that any of them does better than those. In the trials that compared devices with each other, people using hearing aids, sound generators or combination devices each had a clinically meaningful drop in tinnitus symptom scores on questionnaires such as the Tinnitus Handicap Inventory (THI), with no difference between device types (low-quality evidence). None of the studies assessed side effects. In the Searchfield 2017 review and subsequent meta-analyses, properly-fit hearing aids produced clinically meaningful reduction in tinnitus distress (on validated questionnaires such as the Tinnitus Handicap Inventory) in approximately 60–70% of tinnitus patients with concurrent hearing loss. Modern "combination devices" (hearing aids with integrated tinnitus-masking sound generators) provide both amplification of environmental sound and a customizable low-level masking signal at the tinnitus pitch.
The 2014 US guideline recommends a hearing-aid evaluation for people with persistent, bothersome tinnitus and documented hearing loss, and the 2026 update recommends it for people with hearing difficulties and persistent, bothersome tinnitus. Insurance coverage of hearing aids has improved substantially in the US with the U.S. Food and Drug Administration (FDA) over-the-counter hearing-aid rule (2022) allowing direct purchase for mild-to-moderate loss at much lower price points than the historical $5,000–$7,000 audiologist-channel devices.
Tinnitus Retraining Therapy (TRT)
Tinnitus Retraining Therapy is the structured clinical program built around the Jastreboff model. It has two components delivered in parallel over 12–24 months:
- Directive counseling — structured education about the neurophysiology of tinnitus, the benign nature of the signal, the habituation mechanism, and the expected timecourse. The goal is to defuse the threat interpretation that drives limbic activation. This typically involves 3–5 sessions with a TRT-trained audiologist or otolaryngologist over the first three months.
- Sound enrichment — bilateral wearable sound generators (or hearing aids with sound-generator capability) producing low-level broadband noise just below the tinnitus loudness, worn 6–8 hours per day for 12–24 months. The noise is set at the "mixing point" where it is perceptible but does not mask the tinnitus completely — the goal is to provide a continuous background of competing auditory input for the limbic system to habituate to alongside the phantom signal.
The Henry 2006 clinical trial compared TRT with tinnitus masking in 123 military veterans, who were placed into the two groups in an alternating manner (not by randomization) and treated at 0, 3, 6, 12 and 18 months. Both groups improved on the tinnitus questionnaires; the improvement with TRT was significantly greater than with masking, most strongly in patients who began with a "very big" tinnitus problem, and more modest in those who began with a "moderate" problem. The intervention is intensive (typical course is 12–24 months) but the durability of benefit is substantially better than most pharmacologic approaches.
Sound Masking (Bedside and Wearable)
Sound masking is simpler than TRT — it does not require structured counseling or a specific device protocol. The principle is to provide environmental sound that reduces the perceived loudness of the tinnitus by providing competing auditory input.
The most common forms:
- Bedside sound machines — white noise, pink noise, ocean waves, rain, or fan sounds at low level throughout the sleep period. Tinnitus is most distressing at night when ambient sound drops and the phantom signal stands out against silence. A bedside masking sound reduces sleep-onset latency and night-waking frequency in most tinnitus patients with insomnia.
- Wearable sound generators — behind-the-ear or in-ear devices providing continuous low-level broadband noise during waking hours. Similar to TRT sound generators but without the formal counseling protocol.
- Smartphone-based masking apps — the modern accessible alternative; many free or low-cost apps provide customizable masking sounds. Quality varies; clinical research has been limited.
- Environmental sound enrichment — keeping a low-volume radio or background music on throughout the day; opening windows for outdoor sound; using a soft-running fan or air purifier. This costs nothing; sound enrichment is listed as an option ("clinicians may recommend") in the 2026 US guideline.
The Cochrane reviews are cautious. Hobson 2012 (6 trials, 553 participants) saw no significant change in tinnitus loudness or overall severity with sound therapy compared with other approaches such as education, relaxation, counselling or tinnitus retraining; the authors concluded that the limited data failed to show strong evidence that sound therapy works, that this absence of conclusive evidence is not evidence that it does not work, and that no side effects were reported. Sereda 2018 (8 studies, 590 participants) found no usable data comparing sound devices with no device, placebo or education alone. The evidence for any single device or sound type being superior to others is weak — patient preference and adherence are the dominant factors in outcomes.
Notched-Music Therapy — Targeted Cortical Reorganization
Notched-music therapy is a newer, mechanism-targeted intervention developed by Okamoto and colleagues at the University of Münster. The therapy is based on the observation that the auditory cortex demonstrates use-dependent reorganization — the cortical regions corresponding to frequently-heard frequencies expand at the expense of regions corresponding to rarely-heard frequencies. The notched-music protocol exploits this plasticity in reverse:
- The patient's individual tinnitus pitch is measured precisely with audiometric matching
- The patient's preferred music is digitally filtered to remove a one-octave-wide band of frequencies centered on the tinnitus pitch (the "notch")
- The patient listens to the notched music 1–2 hours per day for several months
- The deprivation of input at the tinnitus frequency, combined with normal input at adjacent frequencies, drives lateral-inhibition-mediated reorganization of the auditory cortex that reduces representation of the tinnitus frequency and reduces the phantom signal
In a small trial of 16 patients, Okamoto et al. (2010) found that after 12 months of regular listening, the 8 patients whose music was notched at their own tinnitus frequency had significantly lower tinnitus loudness, and lower evoked activity in the auditory-cortex areas matching the tinnitus frequency (measured by magnetoencephalography), than 8 patients who received an analogous placebo notched-music treatment.
The intervention is appealing because it is targeted, evidence-supported, and can be delivered through inexpensive smartphone apps. Several commercial implementations now exist. The main limitation is the requirement for precise tinnitus-pitch measurement to set the notch correctly, and the relatively long treatment duration needed to see meaningful effect.
Cognitive-Behavioral Therapy (CBT)
Cognitive-behavioral therapy is the behavioral treatment that both the 2014 and 2026 US guidelines recommend for persistent, bothersome tinnitus. The 2020 Cochrane review (Fuller et al.) of 28 studies totaling 2,733 participants found that, compared with no treatment or a waiting list, cognitive behavioral therapy (CBT) may reduce the impact of tinnitus on quality of life at the end of treatment (low certainty): a score about 10.91 points lower on the 0–100 Tinnitus Handicap Inventory, where the smallest change that matters to patients is estimated at 7 points. Compared with audiological care, CBT probably reduces that impact (moderate certainty; 5.65 points lower; 3 studies, 444 participants). CBT may slightly reduce depression. There was no evidence at 6 or 12 months after treatment, and serious adverse effects appeared to be rare.
Cognitive behavioral therapy does not aim to reduce the loudness or character of the phantom signal — that target is unrealistic. Instead, cognitive behavioral therapy targets the cognitive and emotional response to the signal:
- Cognitive restructuring — identifying and challenging catastrophic thoughts about tinnitus ("I will never have a moment of peace again," "I cannot live with this"), replacing them with more accurate appraisals ("This is a benign signal that fluctuates and that most people learn to ignore over time")
- Behavioral activation — restoring engagement with previously enjoyable activities that the patient may have abandoned because of tinnitus-related distress
- Relaxation and stress-reduction training — progressive muscle relaxation, diaphragmatic breathing, mindfulness; these directly reduce the limbic activation that amplifies tinnitus perception
- Sleep-hygiene optimization — addressing the bidirectional relationship between tinnitus and insomnia
- Attention-modification training — structured exercises that practice shifting attention away from the tinnitus signal
Cognitive behavioral therapy is delivered in 6–12 weekly sessions, individually or in group format. Internet-delivered cognitive behavioral therapy for tinnitus (iCBT) has shown effect sizes comparable to face-to-face cognitive behavioral therapy in several randomized trials, making it accessible to patients who cannot easily access a tinnitus-experienced therapist.
Bimodal Neuromodulation (Sound + Tongue Stimulation)
Bimodal neuromodulation is the most promising emerging intervention. The Conlon et al. (2020) Science Translational Medicine trial of a bimodal tongue-and-sound stimulation device tested a paired-stimulation paradigm in which patients received synchronized auditory tones (matched to their tinnitus frequency) plus mild electrical stimulation of the tongue surface for 60 minutes daily over 12 weeks. The pairing exploits cross-modal cortical plasticity to drive directed reorganization of the dorsal cochlear nucleus and auditory cortex.
Results in this randomized, double-blinded, exploratory study of 326 adults with chronic tinnitus, split into three arms with different stimulation settings:
- Tinnitus symptom severity fell significantly by the end of treatment in all arms (Tinnitus Handicap Inventory effect size, Cohen's d, −0.87 to −0.92)
- Improvements continued for 12 months after treatment for specific stimulation settings
- Compliance and satisfaction were high, and there were no treatment-related serious adverse events
The later pivotal trial (TENT-A3, Boedts et al. 2024) had 112 people use sound alone for 6 weeks and then sound plus tongue stimulation for 6 weeks, each person serving as their own control. A "responder" improved by more than 7 points on the Tinnitus Handicap Inventory. In people with moderate or more severe tinnitus, 58.6% responded during the combined stage compared with 43.2% with sound alone; this advantage was not seen in the full group across all severity levels. There were no device-related serious adverse events, and the authors report that these results led to the U.S. Food and Drug Administration De Novo decision for the device.
The device received U.S. Food and Drug Administration De Novo authorization in 2023 for tinnitus treatment and is commercially available, though insurance coverage in the US is still developing. Cost is approximately $4,000–$5,000 for the device and protocol. The 2026 US guideline lists bimodal neuromodulation as an option ("clinicians may offer"). Other bimodal devices using different cross-modal pairings (auditory + cervical stimulation, auditory + transcranial stimulation) are in development.
The AAO-HNS Clinical Practice Guidelines (2014 and 2026)
The 2014 Tunkel et al. clinical practice guideline of the American Academy of Otolaryngology–Head and Neck Surgery Foundation (AAO-HNS) covers adults with tinnitus that is bothersome and has lasted 6 months or longer. Its grades, as its summary states them:
- Strong recommendation: Distinguish bothersome from non-bothersome tinnitus
- Strong recommendation against: Imaging of the head and neck to evaluate tinnitus that is not in one ear only, is not pulsatile, and comes without focal neurologic abnormalities or asymmetric hearing loss
- Recommendation: A targeted history and physical examination; a prompt, comprehensive hearing (audiologic) exam when tinnitus is in one ear, has lasted 6 months or more, or comes with hearing difficulty; education about management strategies; a hearing-aid evaluation for persistent, bothersome tinnitus with documented hearing loss; and cognitive-behavioral therapy for persistent, bothersome tinnitus
- Recommendation against: Antidepressants, anticonvulsants, anxiolytics or intratympanic (injected into the ear) medications for routine treatment; Ginkgo biloba, melatonin, zinc or other dietary supplements; and transcranial magnetic stimulation for routine treatment
- Option: An initial comprehensive hearing exam for everyone with tinnitus, and sound therapy for persistent, bothersome tinnitus
- No recommendation: Acupuncture
The guideline was updated once, in October 2026 (Adams et al., "Clinical Practice Guideline: Tinnitus Update"). Its key action statements:
- Strong recommendation: Distinguish bothersome from non-bothersome tinnitus; ask about risks of self-harm in a person with bothersome tinnitus; no brain imaging (neuroradiologic imaging) to evaluate the tinnitus unless specific concerning features are present
- Recommendation: A targeted history and physical examination; a comprehensive hearing evaluation for people with tinnitus; education about the natural history, effects and management of tinnitus; a hearing-aid evaluation for people with hearing difficulties and persistent, bothersome tinnitus; referral for cochlear-implant evaluation when hearing criteria are met; cognitive-behavioral therapy; and assessing and documenting the outcomes of treatment
- Recommendation against: Routine antidepressants, anticonvulsants, anxiolytics or intratympanic medications with tinnitus as the primary reason; dietary supplements with tinnitus as the primary reason; and repetitive transcranial magnetic stimulation (rTMS)
- Option: Asking about somatosensory features (such as jaw or neck involvement); sound enrichment; and bimodal neuromodulation
Tinnitus Retraining Therapy is not among the key action statements in the summary of either guideline. No drug is recommended for tinnitus itself. Benzodiazepines, selective serotonin reuptake inhibitors (SSRIs), gabapentin, and other drugs are sometimes prescribed, and both guidelines recommend against routine antidepressants, anticonvulsants and anxiolytics with tinnitus as the target. Where these drugs are used, it is for the anxiety, depression, and insomnia that often accompany severe tinnitus, not the phantom signal itself.
How Guidelines and Trials Order These Approaches
The guidelines and trials above do not set a month-by-month plan, but they describe a broad order, from evaluation to the less-tested options:
- Evaluation — the 2026 guideline recommends a targeted history and physical examination and a comprehensive hearing evaluation, asks clinicians to enquire about risks of self-harm, and recommends against brain imaging unless specific concerning features are present. Nutrient status is covered on the nutrient deep-dive and modifiable triggers on the causes and triggers page. Bedside sound for sleep and directive counseling about the benign nature of tinnitus and the habituation process are usually part of the start.
- Education, hearing and sound — education about tinnitus is a recommendation; a hearing-aid evaluation is recommended when there is hearing difficulty (the U.S. Food and Drug Administration over-the-counter (OTC) hearing-aid pathway makes a 30-day trial low-cost); sound enrichment during the day is an option
- Cognitive behavioral therapy — recommended by both guidelines, delivered face to face or as internet-delivered CBT (iCBT) over 6–12 sessions
- Structured sound programs — Tinnitus Retraining Therapy with a trained audiologist, or notched-music therapy as an alternative sound-based approach, are used when distress persists; their trials are described above
- Later options — bimodal neuromodulation (a tongue-and-sound stimulation device) is an option in the 2026 guideline. Drugs such as nortriptyline, selective serotonin reuptake inhibitors (SSRIs) and gabapentin are sometimes prescribed for the depression, anxiety or poor sleep that accompanies tinnitus; both guidelines recommend against routine antidepressants, anticonvulsants and anxiolytics with tinnitus itself as the target. Sound enrichment and cognitive behavioral therapy stay in place throughout.
- Beyond 12 months — substantial habituation is described in most patients regardless of specific intervention; the natural history of tinnitus is toward gradual improvement in distress (even when loudness does not change) over 18–24 months with consistent management
Approaches the Research Does Not Support
- Telling a patient that "nothing can be done" — this is inaccurate and clinically harmful. Even patients who do not respond to specific interventions habituate substantially over time with appropriate framing and support.
- Long-term benzodiazepines — while clonazepam acutely reduces tinnitus perception in some patients, chronic use produces dependence, cognitive impairment, and rebound worsening of tinnitus on attempted discontinuation. Anxiolytics are among the drugs both US guidelines recommend against for routine tinnitus treatment.
- Seeking silence — patients often cope with tinnitus by avoiding loud environments and seeking silence; this worsens the tinnitus by reducing the competing auditory input the limbic system needs for habituation. Environmental sound enrichment is the alternative, listed as an option in the 2026 guideline.
- Repeated scans for stable tinnitus in both ears — repeated magnetic resonance imaging and extensive vestibular testing in a patient with symmetric audiometric tinnitus is rarely productive and reinforces the threat interpretation; both guidelines strongly recommend against imaging unless warning features are present (tinnitus in one ear only, pulsatile tinnitus, focal neurologic signs or asymmetric hearing loss in the 2014 version)
- Experimental devices and supplements without evidence — the tinnitus marketplace is full of expensive devices and supplements with little or no evidence base; both guidelines recommend against dietary supplements for tinnitus, and the AAO-HNS guidelines and the American Tinnitus Association (ATA) set out the evidence-grounded options
Key Research Papers
- Jastreboff PJ (1990). Phantom auditory perception (tinnitus): mechanisms of generation and perception. Neuroscience Research 8(4):221-54 — PubMed PMID: 2175858
- Jastreboff PJ, Hazell JW (1993). A neurophysiological approach to tinnitus: clinical implications. British Journal of Audiology — PubMed PMID: 8339063
- Tunkel DE et al. (2014). Clinical practice guideline: tinnitus. Otolaryngol Head Neck Surg — PubMed PMID: 25273878
- Adams ME, Cramer JD, Tunkel DE, Lee VS, et al. (2026). Clinical Practice Guideline: Tinnitus Update. Otolaryngol Head Neck Surg 175 Suppl 1:S1-S62 — PubMed PMID: 42861423
- Fuller T, Cima R, Langguth B, Mazurek B, Vlaeyen JW, Hoare DJ (2020). Cognitive behavioural therapy for tinnitus. Cochrane Database Syst Rev 1:CD012614 — PubMed PMID: 31912887
- Sereda M et al. (2018). Sound therapy (using amplification devices and/or sound generators) for tinnitus. Cochrane Database — PubMed PMID: 30589445
- Hobson J, Chisholm E, El Refaie A (2012). Sound therapy (masking) in the management of tinnitus in adults. Cochrane Database Syst Rev 11:CD006371 — PubMed PMID: 23152235
- Okamoto H et al. (2010). Listening to tailor-made notched music reduces tinnitus loudness and tinnitus-related auditory cortex activity. PNAS — PubMed PMID: 20080545
- Conlon B et al. (2020). Bimodal neuromodulation combining sound and tongue stimulation reduces tinnitus symptoms in a large randomized clinical study. Science Translational Medicine — PubMed PMID: 33028707
- Boedts M, Buechner A, Khoo SG, Gjaltema W, et al. (2024). Combining sound with tongue stimulation for the treatment of tinnitus: a multi-site single-arm controlled pivotal trial. Nature Communications 15(1):6806 — PubMed PMID: 39160146
- Hoare DJ, Searchfield GD, El Refaie A, Henry JA (2014). Sound therapy for tinnitus management: practicable options. J Am Acad Audiol 25(1):62-75 — PubMed PMID: 24622861
- Searchfield GD, Durai M, Linford T (2017). A State-of-the-Art Review: Personalization of Tinnitus Sound Therapy. Frontiers in Psychology 8:1599 — PubMed PMID: 28970812
- Hesser H et al. (2011). A systematic review and meta-analysis of randomized controlled trials of CBT for tinnitus distress. Clinical Psychology Review — PubMed PMID: 21237544
- Henry JA, Schechter MA, Zaugg TL, Griest S, et al. (2006). Outcomes of clinical trial: tinnitus masking versus tinnitus retraining therapy. J Am Acad Audiol 17(2):104-32 — PubMed PMID: 16640064
PubMed Topic Searches
Connections
- All Remedies
- Tinnitus Hub
- Benefits Deep-Dive Hub
- Causes and Triggers
- Nutrient Status (B12, Mg, Zn)
- N-Acetylcysteine and Antioxidants
- Ginkgo Biloba for Tinnitus
- Glycine for Tinnitus
- Taurine for Tinnitus
- Neurology
- Anxiety
- Depression
- Insomnia
- Meditation
- Ginkgo Biloba
- Tinnitus — the ENT clinical overview, including the hearing loss and audiometry findings that decide whether hearing aids or masking come first.