Tinnitus — N-acetyl-cysteine and Antioxidants
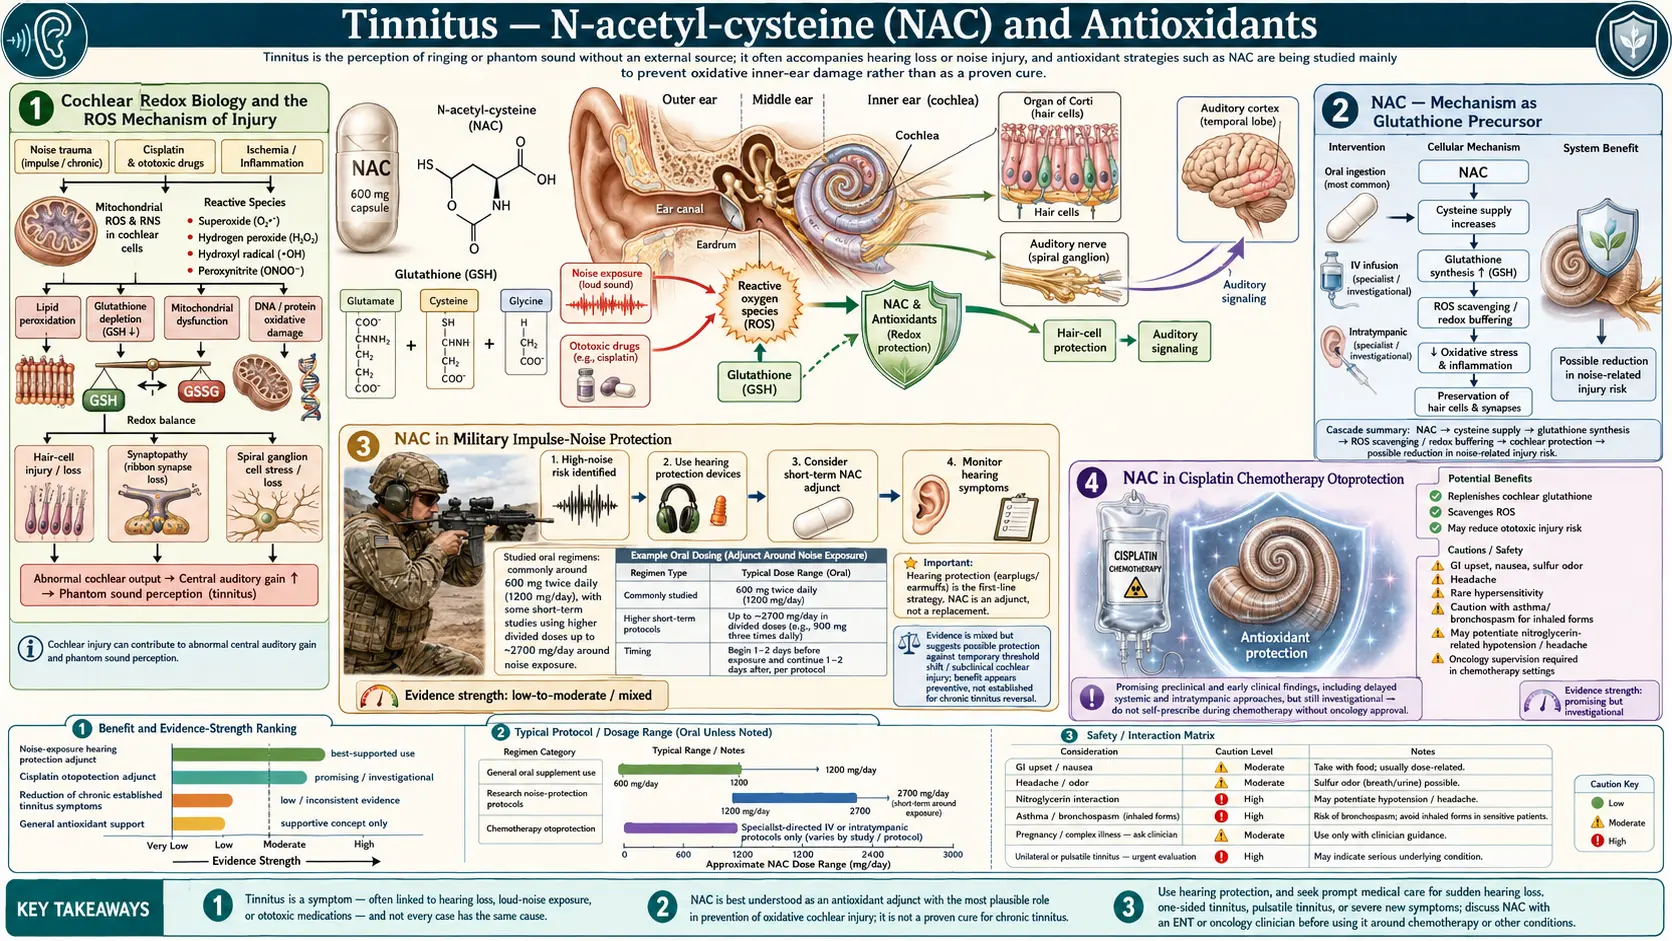
The single best-characterized molecular mechanism of cochlear injury — the mechanism that links noise overexposure, ototoxic chemotherapy, aminoglycoside antibiotics, and ischemic insults — is reactive oxygen species (ROS) generation in the cochlear hair cells. The mitochondrial reactive oxygen species burst overwhelms the cochlea's antioxidant defenses (Cu/Zn superoxide dismutase, glutathione peroxidase, catalase), depletes intracellular glutathione, triggers apoptotic cell death, and produces both immediate hearing loss and the persistent central plasticity that generates chronic tinnitus. N-acetylcysteine (NAC), a direct glutathione precursor, is the most extensively studied otoprotectant in this pathway. Adjunct agents — alpha-lipoic acid, coenzyme Q10, vitamin E, and idebenone — have supporting mechanistic rationale and progressively smaller evidence bases. This page covers the redox biology, the N-acetylcysteine clinical trials in military impulse-noise protection and cisplatin chemotherapy, the Ginkgo biloba Cochrane verdict, and the evidence-grounded protocols for prophylaxis and adjunct use.
Table of Contents
- Cochlear Redox Biology and the Reactive Oxygen Species Mechanism of Injury
- N-Acetylcysteine — Mechanism as Glutathione Precursor
- N-Acetylcysteine in Military Impulse-Noise Protection
- N-Acetylcysteine in Cisplatin Chemotherapy Otoprotection
- N-Acetylcysteine for Established Chronic Tinnitus
- Adjunct Antioxidants (Alpha-Lipoic Acid, Coenzyme Q10, Vitamin E, Idebenone)
- Ginkgo Biloba — The Cochrane Verdict
- Dosing Protocols Used in Practice
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Cochlear Redox Biology and the Reactive Oxygen Species Mechanism of Injury
The cochlea is metabolically the busiest tissue in the body per gram of weight. The stria vascularis maintains the +80 mV endocochlear potential against a steep ionic gradient using continuous adenosine triphosphate (ATP) hydrolysis by Na+/K+-ATPase pumps. The outer hair cells perform mechanical-electrical-mechanical transduction with submillisecond precision, requiring sustained mitochondrial output. This metabolic intensity generates a constant baseline flux of reactive oxygen species — superoxide, hydrogen peroxide, hydroxyl radical — that under normal conditions is detoxified by the cochlear antioxidant defense system: Cu/Zn superoxide dismutase, manganese superoxide dismutase, glutathione peroxidase, catalase, and the small-molecule antioxidants glutathione, vitamin E, vitamin C, and coenzyme Q10.
Acoustic overexposure dramatically increases reactive oxygen species generation through several mechanisms:
- Excessive glutamate release at the inner-hair-cell/spiral-ganglion synapse, producing postsynaptic N-methyl-D-aspartate-receptor calcium overload and mitochondrial dysfunction
- Increased metabolic demand on outer hair cells already operating near maximum capacity
- Ischemia-reperfusion injury as cochlear blood flow transiently drops during the acoustic event and then restores
- Mechanical disruption of hair-cell stereocilia, triggering apoptotic pathways
The reactive oxygen species surge overwhelms the cochlear antioxidant defenses, depletes intracellular glutathione (often to 30–50% of baseline), and initiates apoptotic cascades that produce hair-cell death over the following 1–14 days post-exposure. This delayed cell death is the rationale for post-exposure antioxidant intervention — the damage is not all "done" at the moment of acoustic overexposure; the reactive oxygen species-driven apoptotic cascade can be partially interrupted by restoring antioxidant capacity in the hours and days afterward.
Cisplatin ototoxicity follows an analogous mechanism. Cisplatin selectively accumulates in cochlear hair cells, binds to mitochondrial DNA, induces mitochondrial dysfunction and reactive oxygen species generation, depletes glutathione, and triggers apoptosis. The clinical dose-limiting toxicity of cisplatin chemotherapy is often hearing loss, particularly in pediatric oncology patients. Aminoglycoside antibiotics (gentamicin, tobramycin, amikacin, neomycin) produce ototoxicity through a similar reactive oxygen species-mediated apoptotic mechanism, often persisting weeks after drug discontinuation.
N-Acetylcysteine — Mechanism as Glutathione Precursor
N-acetylcysteine is the N-acetylated derivative of the amino acid L-cysteine. It is the standard antidote for acetaminophen overdose (where it replenishes hepatic glutathione consumed by acetaminophen's reactive metabolite NAPQI), a U.S. Food and Drug Administration-approved mucolytic in pulmonary medicine, and the most extensively studied otoprotectant in pre-clinical and clinical noise-injury research.
N-acetylcysteine's relevant mechanisms in cochlear protection:
- Direct antioxidant activity — the free sulfhydryl group of N-acetylcysteine scavenges reactive oxygen species, particularly hydroxyl radical and hypochlorous acid
- Glutathione precursor — N-acetylcysteine provides cysteine for de novo glutathione synthesis (cysteine is the rate-limiting amino acid in glutathione synthesis); restoring cochlear glutathione restores the cell's primary antioxidant defense
- Direct binding of platinum compounds — N-acetylcysteine's sulfhydryl group directly binds cisplatin, reducing the free drug available to enter cochlear hair cells; this is the mechanism behind the otoprotectant effect in chemotherapy
- Mitochondrial protection — N-acetylcysteine reduces mitochondrial calcium overload and prevents the opening of the mitochondrial permeability transition pore that triggers apoptosis
- Anti-inflammatory effects — N-acetylcysteine inhibits NF-kB activation and downstream inflammatory cytokine production in cochlear tissues
See the N-acetylcysteine main page for comprehensive mechanism and dosing information across all clinical applications.
N-Acetylcysteine in Military Impulse-Noise Protection
The most rigorous evidence for N-acetylcysteine otoprotection comes from military and occupational research on impulse-noise exposure. The US military has a strong operational interest in protecting service members' hearing — tinnitus is the most common service-connected disability in the VA system and noise-induced hearing loss accounts for a substantial fraction of military health spending.
Lin et al. (2010) ran a double-blind crossover trial in 53 male workers exposed to occupational noise (88–89 dB): each took N-acetylcysteine 1200 mg/day for 14 days and placebo for 14 days, in random order, separated by a 2-week washout. N-acetylcysteine significantly reduced noise-induced temporary threshold shift, and the effect was significant only in workers carrying null genotypes of both the GSTM1 and GSTT1 detoxification genes. While this trial was small, the effect was consistent with the larger pre-clinical animal-model literature.
Kopke et al. (2007) reviewed the effect of N-acetylcysteine in a variety of animal models of acute acoustic trauma and its likely mechanisms, noting that noise deafness remains a frequent battlefield injury in the US military, and mentioned early clinical trials. Doosti et al. (2014) randomized 48 textile workers to N-acetylcysteine 1200 mg/day, ginseng 200 mg/day or no supplement for 14 days and found reduced temporary threshold shift with both supplements, more so with N-acetylcysteine.
In civilian settings, the protocol described for predictable high-intensity noise exposure (a concert, fireworks display, firearm training, motorcycle ride, chainsaw use) is N-acetylcysteine 1200–2400 mg taken 1–2 hours before exposure and continued for several days afterward; the two worker trials above used 1200 mg/day for 14 days. Hearing protection (foam earplugs, custom-molded plugs, or muffs) is the main protective measure, and N-acetylcysteine is described as an add-on where hearing protection cannot eliminate exposure entirely.
N-Acetylcysteine in Cisplatin Chemotherapy Otoprotection
Cisplatin ototoxicity is a major clinical problem in pediatric oncology and adult head-and-neck cancer treatment. Up to 60% of pediatric patients treated with cisplatin develop permanent hearing loss; the cumulative dose-limiting toxicity is often hearing rather than nephrotoxicity. Several otoprotection strategies have been investigated:
- Intravenous (IV) N-acetylcysteine — systemic N-acetylcysteine given alongside cisplatin can bind circulating drug and reduce cochlear exposure, but it also reduces tumor exposure to cisplatin (which is the entire point of the chemotherapy), limiting clinical utility
- Transtympanic (intratympanic) N-acetylcysteine injection — N-acetylcysteine injected into the middle ear diffuses through the round-window membrane to reach the cochlea locally, providing high local concentration without systemic exposure that would protect the tumor. Riga et al. (2013) infused 10% N-acetylcysteine through the eardrum into one ear of 20 patients receiving cisplatin, using the other ear as the control; the untreated ears lost hearing at 8000 Hz while the treated ears did not, a significant difference at that frequency. The authors call the method feasible and promising and say additional studies are required. This approach has the strongest rationale.
- Sodium thiosulfate — U.S. Food and Drug Administration-approved otoprotectant for pediatric cisplatin-induced ototoxicity, works through similar sulfhydryl-binding mechanism. Has the advantage of more extensive trial data and regulatory approval.
- Amifostine — thiol-based otoprotectant approved for radiation-induced xerostomia, with some cisplatin-otoprotection data but limited clinical adoption
The clinical relevance for tinnitus: otoprotection options exist for patients receiving cisplatin or other ototoxic chemotherapy. Pre-treatment audiometry and serial monitoring during therapy allow early detection of threshold shift and adjustment of chemotherapy regimen when possible.
N-Acetylcysteine for Established Chronic Tinnitus
The use of N-acetylcysteine for established chronic tinnitus — as opposed to acute otoprotection — has a thinner evidence base. The challenge is that the central plasticity generating chronic tinnitus is largely independent of ongoing reactive oxygen species injury; the original peripheral cochlear damage may have occurred years prior, and antioxidant intervention cannot reverse the cortical reorganization that now sustains the phantom percept.
However, two scenarios are described in which N-acetylcysteine is tried in established tinnitus:
- Ongoing low-grade noise exposure — if the patient continues to experience occupational or recreational noise above protective thresholds, ongoing reactive oxygen species injury may continue to drive worsening tinnitus, and N-acetylcysteine may slow progression in addition to (not as a substitute for) hearing protection
- Sudden sensorineural hearing loss (SSNHL) with associated tinnitus — high-dose systemic N-acetylcysteine alongside high-dose oral or intratympanic steroids has shown some benefit in observational series for acute SSNHL, particularly in the first 1–2 weeks after onset. The mechanism is reduction of ongoing oxidative inflammation in the cochlea.
For unequivocally chronic tinnitus (greater than six months duration, stable, with no ongoing exposure), N-acetylcysteine is unlikely to produce meaningful symptomatic benefit; the sound-therapy and habituation interventions have better-established evidence bases. N-acetylcysteine supplementation does have other systemic benefits (glutathione support, mucolytic effects, neuroprotection) that may justify its use for those indications independently.
Adjunct Antioxidants (Alpha-Lipoic Acid, Coenzyme Q10, Vitamin E, Idebenone)
Several adjunct antioxidants have been investigated for cochlear protection with progressively weaker evidence bases:
- Alpha-lipoic acid (ALA) — a small endogenous antioxidant active in both lipid and aqueous phases. Animal models show cochlear protection comparable to N-acetylcysteine. Human trial data in tinnitus are limited but several small studies suggest modest benefit. Typical dose: 600 mg/day. The alpha-lipoic acid evidence is strongest in diabetic peripheral neuropathy; whether it translates to cochlear nerve protection in humans is less clear.
- Coenzyme Q10 — mitochondrial-membrane antioxidant essential for electron-transport-chain function. Animal models of noise-induced hearing loss show protection. One small uncontrolled pilot trial in chronic tinnitus (Khan et al. 2007, 20 patients, 16 weeks) found no overall effect on tinnitus scores; in a subgroup of 7 patients with low starting blood coenzyme Q10 whose levels rose, tinnitus scores fell. Typical dose: 100–200 mg/day ubiquinol form (better-absorbed than ubiquinone). May be particularly relevant in older patients (coenzyme Q10 (CoQ10) production declines with age) and those on statin therapy (statins deplete coenzyme Q10).
- Vitamin E (mixed tocopherols) — the principal lipid-phase antioxidant in cellular membranes including the hair-cell membrane. Le Prell's "ACE-Mg" combination (vitamins A, C, E plus magnesium) showed additive cochlear protection in animal models of noise injury. Typical dose: 400 international units (IU) mixed tocopherols.
- Idebenone — a synthetic coenzyme Q10 analog with better blood-brain-barrier penetration, used for Leber's hereditary optic neuropathy and investigated for cochlear protection.
- Resveratrol and curcumin — polyphenols with broad antioxidant and anti-inflammatory effects; pre-clinical evidence for cochlear protection but limited human trial data
- Melatonin — antioxidant and sleep-regulator; small trials suggest modest benefit for tinnitus-associated insomnia, with antioxidant action in the cochlea as a plausible adjunct mechanism. Typical dose: 3–5 mg at bedtime.
The "antioxidant stack" practitioners describe for tinnitus prevention or adjunct therapy is: N-acetylcysteine 1200–2400 mg/day, alpha-lipoic acid 600 mg/day, coenzyme Q10 100–200 mg/day (ubiquinol), mixed tocopherols 400 international units/day, with the underlying minerals (magnesium, zinc) addressed separately per the nutrient-status deep-dive.
Ginkgo Biloba — The Cochrane Verdict
Ginkgo biloba leaf extract (standardized as EGb 761 in most clinical trials) has been the most commercially-promoted herbal intervention for tinnitus for several decades. The mechanistic rationale is plausible — ginkgolides and bilobalides have antioxidant and vasoactive properties, improving cochlear microcirculation and reducing oxidative injury in animal models. However, the Hilton, Zimmermann and Hunt 2013 Cochrane review included four randomized controlled trials totaling over 1,500 participants and found no evidence that ginkgo biloba is effective in patients whose primary complaint is tinnitus.
The negative Cochrane verdict has several important caveats:
- The trials studied unselected chronic tinnitus populations, mixing many distinct etiologies. Patient-level meta-analysis stratifying by tinnitus subtype was not possible.
- Several positive trials of ginkgo in specific tinnitus subtypes (acute tinnitus less than three months duration; tinnitus with vascular or microcirculatory etiology; tinnitus in patients with cognitive complaints) exist but did not meet Cochrane inclusion criteria
- EGb 761 has established cognitive and vascular benefits independent of tinnitus that may justify its use for those indications in older patients
- The safety profile of EGb 761 at standard doses (120–240 mg/day standardized extract) is favorable except for bleeding risk in patients on anticoagulants
On the Cochrane evidence, ginkgo biloba is not supported as routine tinnitus therapy. Some people still try a 3–6 month course of standardized EGb 761 extract at 120 mg twice daily, particularly when there are additional reasons (mild cognitive complaints, peripheral vascular disease). See the Ginkgo Biloba main page for comprehensive discussion. Also see Ginkgo Biloba for Tinnitus for tinnitus-specific clinical use.
Dosing Protocols Used in Practice
These are the protocols described in practice; the worker trials cited on this page used N-acetylcysteine 1200 mg/day for 14 days.
N-acetylcysteine for predictable noise exposure (concert, range day, fireworks):
- 1200 mg PO two hours before exposure
- 1200 mg PO immediately after exposure
- 1200 mg PO twice daily for 2–3 days post-exposure
- Combined with appropriate hearing protection (foam plugs or earmuffs, not as a substitute)
N-acetylcysteine for sudden sensorineural hearing loss with acute tinnitus (adjunct to steroid therapy):
- 1200 mg PO twice daily for 14 days, starting as early as possible after onset (ideally within 72 hours)
- Coordinated with oral or intratympanic steroid therapy per ENT
- Alongside urgent audiology and ENT evaluation, which is standard for sudden hearing loss
Cisplatin chemotherapy otoprotection:
- Coordinated by the oncology team and ENT
- Intratympanic N-acetylcysteine injection prior to each cisplatin cycle is the protocol with the strongest mechanistic rationale
- Sodium thiosulfate is U.S. Food and Drug Administration-approved for pediatric cisplatin otoprotection
- Pre-treatment audiometry and serial monitoring throughout chemotherapy course
Chronic antioxidant maintenance described for people prone to tinnitus (occupational noise exposure, prior noise-induced hearing loss):
- N-acetylcysteine 600–1200 mg/day
- Alpha-lipoic acid 600 mg/day
- Coenzyme Q10 ubiquinol 100 mg/day
- Mixed tocopherols 400 international units/day
- Plus the foundational interventions (hearing protection, audiometric monitoring, nutrient repletion)
Cautions and Drug Interactions
- N-acetylcysteine and nitroglycerin — N-acetylcysteine potentiates nitroglycerin's vasodilator effect and can produce severe hypotension and headache, a known risk for people on nitrates
- N-acetylcysteine and asthma — oral N-acetylcysteine is well-tolerated; nebulized N-acetylcysteine can rarely trigger bronchospasm in asthmatics
- N-acetylcysteine gastric upset — sulfur-containing compounds may produce nausea and a transient sulfur odor; taking with food reduces this
- Ginkgo biloba and bleeding — potent inhibitor of platelet-activating factor; combined with warfarin, DOACs, aspirin, or nonsteroidal anti-inflammatory drugs (NSAIDs) raises bleeding risk substantially. Stopping it 2 weeks before scheduled surgery is the usual surgical guidance.
- Alpha-lipoic acid and diabetes — mild glucose-lowering effect, which adds to that of insulin or a sulfonylurea
- Coenzyme Q10 and warfarin — coenzyme Q10 can reduce warfarin's anticoagulant effect (similar structural homology to vitamin K); starting or stopping coenzyme Q10 can shift the international normalized ratio (INR) in people on warfarin
- High-dose vitamin E and bleeding — doses above 400 international units/day mildly inhibit platelet aggregation; combined with anticoagulants may increase bleeding risk
- Antioxidant excess during cancer chemotherapy — theoretical concern that systemic antioxidants may reduce tumor cell killing by reactive oxygen species-generating chemotherapy and radiation.
Key Research Papers
- Kopke RD, Jackson RL, Coleman JK et al. (2007). NAC for noise: from the bench top to the clinic. Hearing Research, 226(1-2):114-25 — PubMed PMID: 17184943
- Lin CY et al. (2010). N-acetyl-cysteine against noise-induced temporary threshold shift in male workers. Hearing Research — PubMed PMID: 20638463
- Riga MG et al. (2013). Transtympanic injections of N-acetylcysteine for the prevention of cisplatin-induced ototoxicity: a feasible method with promising efficacy. American Journal of Clinical Oncology, 36(1):1-6 — PubMed PMID: 22134515
- Le Prell CG et al. (2007). Free radical scavengers vitamins A, C, and E plus magnesium reduce noise trauma. Free Radical Biology and Medicine — Search PubMed
- Henderson D et al. (2006). The role of oxidative stress in noise-induced hearing loss. Ear and Hearing — Search PubMed
- Choi CH, Chen K, Vasquez-Weldon A et al. (2008). Effectiveness of 4-hydroxy phenyl N-tert-butylnitrone (4-OHPBN) alone and in combination with other antioxidant drugs in the treatment of acute acoustic trauma in chinchilla. Free Radical Biology and Medicine, 44(9):1772-84 — PubMed PMID: 18328271
- Doosti A et al. (2014). Comparison of the effects of N-acetyl-cysteine and ginseng in prevention of noise induced hearing loss in male textile workers. Noise and Health, 16(71):223-7 — PubMed PMID: 25033789
- Hilton MP, Zimmermann EF, Hunt WT (2013). Ginkgo biloba for tinnitus. Cochrane Database of Systematic Reviews, (3):CD003852 — PubMed PMID: 23543524
- Khan M, Gross J, Haupt H et al. (2007). A pilot clinical trial of the effects of coenzyme Q10 on chronic tinnitus aurium. Otolaryngology–Head and Neck Surgery, 136(1):72-7 — PubMed PMID: 17210337
PubMed Topic Searches
Connections
- All Remedies
- Tinnitus Hub
- Benefits Deep-Dive Hub
- Causes and Triggers
- Nutrient Status (B12, Mg, Zn)
- Sound Therapy and Habituation
- N-Acetyl-Cysteine
- Glutathione
- Alpha-Lipoic Acid
- Coenzyme Q10
- Vitamin E
- Ginkgo Biloba
- Ginkgo Biloba for Tinnitus
- Glycine for Tinnitus
- Taurine for Tinnitus
- Tinnitus — the ENT clinical overview, including the ototoxic exposures that make antioxidant otoprotection worth timing correctly.