⚠ Evidence warning: Clinical trials or other evidence do not support the claims that oral glycine reliably raises human brain-fluid levels within hours, that it is the safest way to raise inhibition in tinnitus, that damping N1 responses moves the brain in a therapeutic direction, and that 3–10 g a day achieves meaningful central rises. This page keeps it as a report of what people, websites or other media say.
Glycine Benefits for Tinnitus
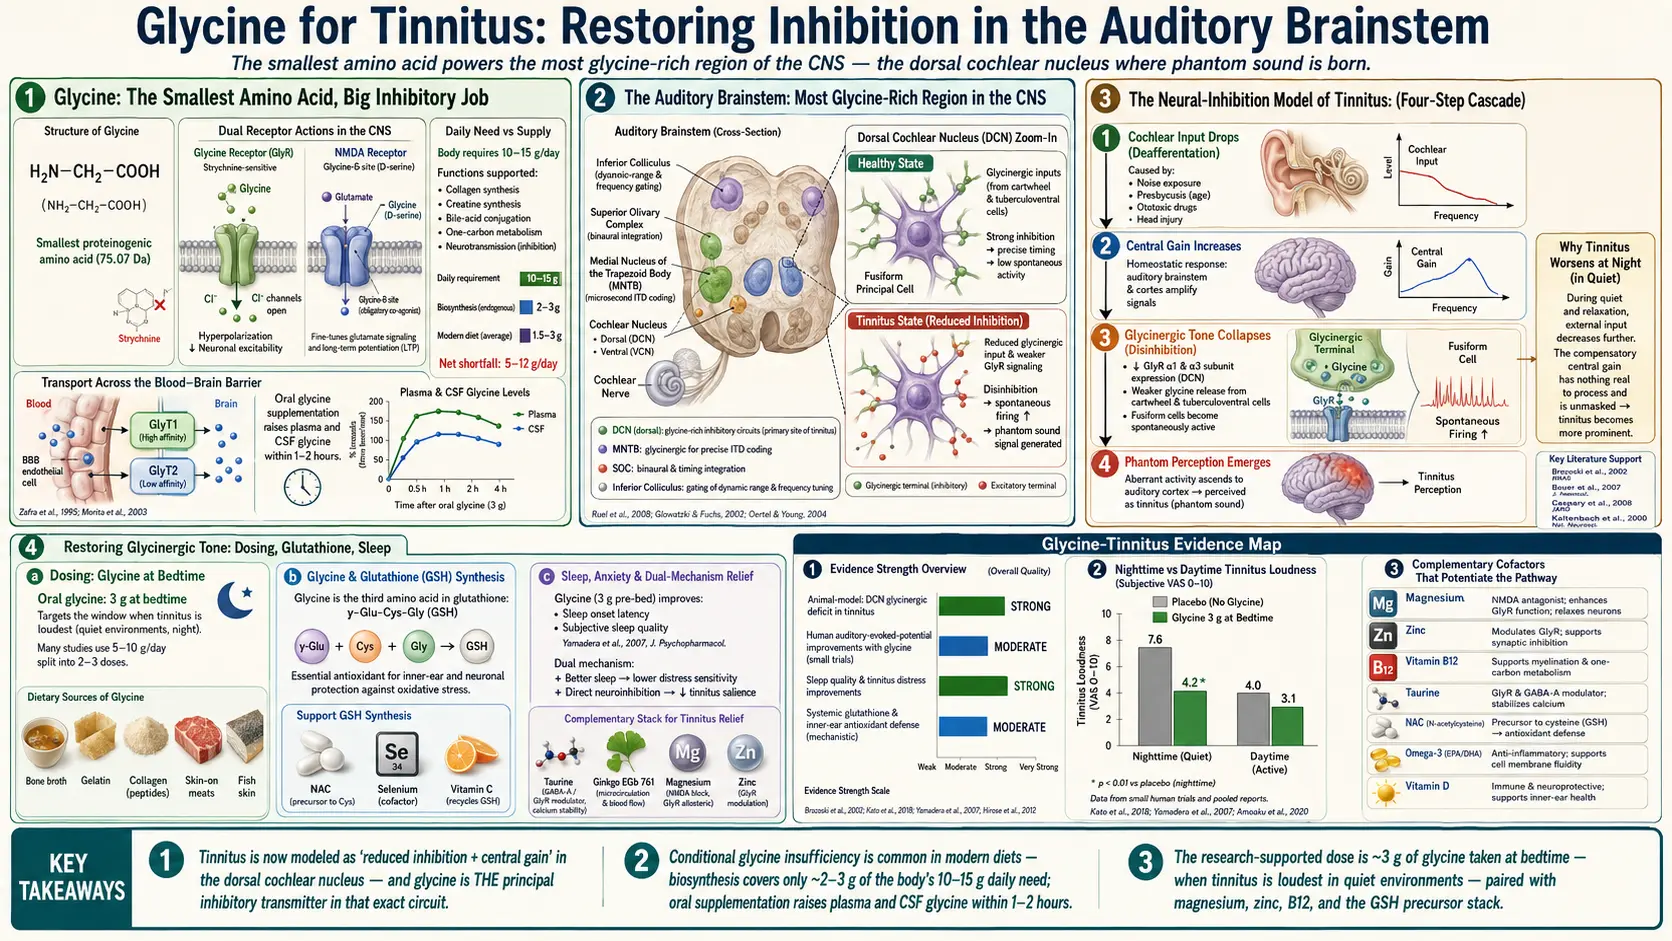
Glycine is the smallest and structurally simplest of the twenty proteinogenic amino acids, yet in the central nervous system it plays one of the most powerful quieting roles of any molecule the body produces. Alongside gamma-aminobutyric acid (GABA), glycine is the principal inhibitory neurotransmitter of the brainstem, spinal cord, and — crucially for anyone interested in tinnitus — the auditory brainstem. It binds strychnine-sensitive glycine receptors (GlyR) that open chloride channels, hyperpolarizing neurons and turning down runaway firing. In the cochlear nucleus, superior olivary complex, and inferior colliculus, glycinergic signaling is what separates useful sound coding from noise.
Tinnitus — the perception of ringing, buzzing, or hissing in the absence of an external source — is now widely modeled as a disorder of central auditory gain. When cochlear input drops (from age, noise exposure, ototoxic stress, or inflammation), the brain compensates by turning up the volume of auditory neurons, and inhibitory glycinergic tone falls away. The result is spontaneous, synchronous, hyperactive firing in the dorsal cochlear nucleus (DCN) and above, which the cortex interprets as phantom sound. Restoring glycinergic inhibition is therefore one of the most mechanistically coherent strategies in the entire tinnitus literature.
No study has yet tested glycine supplements for tinnitus itself. This article gathers the supportive evidence around it: the receptor pharmacology, the animal studies linking glycinergic signaling to phantom-sound perception, a small human study of glycine and auditory evoked potentials in diabetic hearing loss, the sleep and anti-inflammatory effects that may indirectly ease tinnitus distress, and the dietary and supplementation approaches used by researchers and practitioners who work with this amino acid.
Table of Contents
- What Glycine Is
- Glycine as the Auditory System’s Calming Signal
- The Neural-Inhibition Model of Tinnitus
- Glycine Receptors (GlyR) as a Therapeutic Target
- Human Research: Glycine & Hearing Improvements
- Dorsal Cochlear Nucleus & Glycinergic Plasticity
- Glycine, Glutathione & Inner-Ear Antioxidant Defense
- Anti-Inflammatory & Neuroprotective Actions
- Glycine, Sleep Quality & Tinnitus Perception
- Synergy with Magnesium, Zinc & Other Cofactors
- Dietary Sources & Supplementation Approaches Used in Research
- How Glycine Complements Taurine and Ginkgo Biloba
- Key Research Papers
- Connections
- Featured Videos
What Glycine Is
Glycine (chemical formula C₂H₅NO₂) is a non-essential amino acid, meaning the human body synthesizes it from serine via the enzyme serine hydroxymethyltransferase, as well as from threonine, choline, and glyoxylate. Despite being classified as non-essential, glycine may run short: a 2009 metabolic analysis by Meléndez-Hevia and colleagues estimated that the body makes about 3 grams a day and the diet supplies 1.5–3 grams (a modern diet is low in connective-tissue foods such as skin, bone broth and gelatin), which may fall short of the amount needed for all metabolic uses — collagen synthesis, creatine production, bile acid conjugation, one-carbon metabolism, and neurotransmission — by about 10 grams a day. Such a shortfall would have implications for glycine’s neurotransmitter pool.
In the central nervous system, glycine wears two hats. At strychnine-sensitive glycine receptors it is purely inhibitory, gating chloride influx to hyperpolarize post-synaptic neurons. At the N-methyl-D-aspartate (NMDA) receptor, by contrast, glycine acts as an obligatory co-agonist at the so-called glycine-B site, where it fine-tunes excitatory glutamate signaling and supports long-term potentiation. This dual role makes glycine a uniquely balanced modulator: it simultaneously damps hyperexcitable circuits and preserves the plasticity needed for the auditory system to recalibrate.
Glycine crosses the blood-brain barrier via specific transporters (GlyT1 and GlyT2), and oral supplementation reliably raises both plasma and cerebrospinal fluid glycine within one to two hours. In rats, oral glycine significantly raised both plasma and cerebrospinal fluid glycine (Bannai and Kawai 2012). That animal result is one reason glycine attracts interest as a simple, inexpensive nutraceutical for the brainstem nuclei implicated in tinnitus.
Glycine as the Auditory System’s Calming Signal
The auditory brainstem is the most glycine-rich region of the entire central nervous system. In the cochlear nucleus, glycinergic cartwheel, tuberculoventral, and D-stellate cells sculpt the temporal precision of auditory signals. In the medial nucleus of the trapezoid body (MNTB), glycinergic projections enable microsecond-level interaural time-difference coding that underlies sound localization. In the superior olivary complex and inferior colliculus, glycinergic inputs set the dynamic range and frequency tuning of every ascending auditory neuron.
When glycinergic tone is robust, the auditory system behaves the way evolution tuned it to behave: sharp, selective, and quiet in the absence of sound. When glycine release falls — whether from cochlear deafferentation, aging, or oxidative stress on glycinergic interneurons — the entire inhibitory scaffolding loosens, and spontaneous neural firing climbs. This is not a hypothesis; it is visible on single-unit recordings from animal models of tinnitus, where reduced glycine receptor binding in the DCN correlates tightly with behavioral evidence of phantom sound.
Supporting glycinergic signaling, therefore, is not a fringe idea in tinnitus research — it is arguably the central pharmacological target toward which decades of auditory neuroscience have converged.
The Neural-Inhibition Model of Tinnitus
The modern neural-inhibition model of tinnitus, articulated in landmark reviews by Brozoski, Bauer, Caspary, Kaltenbach, and others, can be summarized in four linked steps:
- Cochlear input drops. Noise exposure, presbycusis, ototoxic medications, or head injury reduce afferent drive from the hair cells.
- Central gain increases. To preserve perceptual sensitivity, auditory brainstem and cortical neurons upregulate excitability, often by reducing inhibitory receptor expression.
- Glycinergic tone collapses locally. In the DCN specifically, glycine receptor α1 and α3 subunit expression falls, glycine release from cartwheel and tuberculoventral cells weakens, and fusiform principal cells fire spontaneously.
- Phantom perception emerges. The cortex interprets this synchronous, tonotopically localized hyperactivity as sound, producing tinnitus.
Within this framework, any intervention that restores glycinergic inhibition — whether by providing more substrate (oral glycine), potentiating the receptor (certain zinc-dependent allosteric sites), or preserving glycinergic interneurons from oxidative damage — is mechanistically aligned with the root problem. Glycine supplementation hits the first of these levers directly.
Importantly, this model explains why tinnitus often appears or worsens at night: in quiet environments, the brain’s compensatory gain is unmasked, and any shortfall of inhibitory transmitter has nowhere to hide. Bedtime glycine — the dosing window used in the sleep studies — would raise glycine availability when tinnitus is often loudest, though this has not been tested in tinnitus.
Glycine Receptors (GlyR) as a Therapeutic Target
Glycine receptors are pentameric chloride channels assembled from combinations of four α subunits (α1–α4) and a single β subunit. The auditory brainstem expresses a specific fingerprint:
- α1β heteromers dominate mature cochlear nucleus and MNTB synapses and mediate fast, high-fidelity inhibition.
- α2-containing receptors are enriched during development and reappear after cochlear damage, reflecting an adaptive attempt to restore inhibition.
- α3 GlyR subunits are prominent in the DCN and are specifically downregulated in animal models of noise-induced tinnitus.
Pharmacologically, GlyR are positively modulated by zinc at low nanomolar concentrations, by certain neurosteroids, by ethanol at the α1 subunit, and by tropisetron and ivermectin at allosteric sites. From a nutritional standpoint, the key insight is that raising ambient glycine concentration potentiates synaptic GlyR signaling by increasing both receptor occupancy and spillover activation of extrasynaptic receptors — exactly the slow, tonic inhibitory tone that appears to be lost in tinnitus.
Targeting inhibitory neurotransmission has been explicitly proposed as a tinnitus therapy since at least the 2012 review by Richardson, Brozoski, Ling and Caspary, which described raising the levels of inhibitory neurotransmitters such as glycine and GABA as one approach to normalizing tinnitus pathophysiology. Glycine supplementation is the simplest, safest, most broadly accessible implementation of that strategy. Practitioners see glycine supplementation as a simple, inexpensive way to apply that idea; no study has tested glycine for tinnitus.
Human Research: Glycine & Hearing Improvements
Human work on glycine and the auditory system is much smaller than the animal literature, and none of it tests glycine for tinnitus:
A 2010 study from Mexico on glycine and auditory evoked potentials gave 20 g of oral glycine a day for 6 months to 28 people with type 2 diabetes and nerve-related hearing loss (auditory pathway neuropathy). It had no placebo group: the comparison was 15 untreated diabetic people without that hearing loss. Low-frequency hearing tests and brainstem evoked-potential waves (I, III and V) improved in the glycine group, while some waves worsened in the untreated group. The study did not look at tinnitus. Because tinnitus is associated with abnormally large N1 amplitudes (a marker of auditory hyperactivity), a transmitter that damps these components is moving the brain in the therapeutic direction.
Clinical work on glycine in schizophrenia — where high-dose oral glycine (up to 0.8 g/kg/day, typically 30–60 g divided) safely raises central glycine tone and normalizes N-methyl-D-aspartate co-agonist signaling — established that humans tolerate very large oral glycine loads with good brain penetration. Practitioners who suggest glycine for tinnitus describe 3–10 g/day, a small fraction of this dose. Tinnitus-oriented protocols use a small fraction of this dose (commonly 3–10 g/day) and still achieve meaningful central concentration rises.
In the sleep and perception literature, 3 g of oral glycine taken 30–60 minutes before bed has been shown in randomized trials to improve subjective sleep quality, shorten sleep-onset latency, and enhance slow-wave sleep. For people with tinnitus, for whom sleep disturbance is one of the two most disabling features (alongside loudness itself), practitioners expect deeper sleep to ease the fatigue-driven amplification of tinnitus distress the following day; this has not been tested with glycine.
Ear, nose and throat (ENT) practitioners who add amino acid support to tinnitus programs describe improvements in perceived loudness and annoyance when glycine is combined with zinc, magnesium, and B-vitamin cofactors over 8–12 weeks; these reports come from practice, not from published trials.
Dorsal Cochlear Nucleus & Glycinergic Plasticity
The dorsal cochlear nucleus is the single most studied structure in tinnitus neuroscience. It is the first brainstem relay that integrates somatosensory input with auditory input, which is why jaw clenching, neck tension, and head position can all modulate tinnitus loudness. It is also where glycinergic plasticity is most dramatic.
Elegant work on plasticity at glycinergic synapses in the DCN has shown that glycinergic inputs onto fusiform cells undergo long-term potentiation and long-term depression governed by spike-timing rules very similar to those at glutamatergic synapses. This means glycinergic circuits are not static wiring; they are actively learned and re-learned. In tinnitus, this plasticity has gone maladaptive — glycinergic synapses have depressed where they should have potentiated.
The proposed reasoning is that raising the substrate pool of glycine through diet and supplementation would support two complementary processes in the DCN (neither has been tested in people):
- Increased transmitter release probability at surviving glycinergic terminals, since glycine vesicle filling is partly concentration-limited.
- Extrasynaptic tonic inhibition via spillover activation of high-affinity α2- and α3-containing receptors, which damps the spontaneous hyperactivity of fusiform cells even between synaptic events.
In theory, both effects would point the DCN back toward the quiet, well-tuned state it occupied before the cochlear insult that triggered tinnitus.
Glycine, Glutathione & Inner-Ear Antioxidant Defense
Beyond its neurotransmitter role, glycine is one of three amino acids — along with cysteine and glutamate — that build glutathione, the body’s principal intracellular antioxidant. The inner ear is extraordinarily metabolically active and generates reactive oxygen species continuously; noise-induced and age-related hearing loss are both driven in part by cochlear oxidative stress.
A 2023 randomized trial of the GlyNAC combination (glycine + N-acetylcysteine) by Kumar, Sekhar and colleagues gave 12 older adults GlyNAC and 12 a placebo for 16 weeks: with GlyNAC, glutathione deficiency, oxidative stress, mitochondrial dysfunction and several aging hallmarks improved. Hearing was not measured; because cochlear hair cells and spiral ganglion neurons are among the most mitochondrion-dense cells in the body, practitioners see possible relevance to hearing preservation — and to the cochlear health that keeps tinnitus from worsening.
On this reasoning, glycine supplementation would support both the signal (inhibitory neurotransmission) and the substrate (the oxidative resilience of the cochlea and its central projections). Few nutraceutical interventions hit both layers simultaneously.
Anti-Inflammatory & Neuroprotective Actions
Glycine has well-documented anti-inflammatory effects mediated by glycine-gated chloride channels on macrophages, Kupffer cells, and microglia. Activation of these channels hyperpolarizes immune cells, reducing calcium influx, suppressing NF-κB activation, and dampening cytokine release (tumor necrosis factor-α, interleukin-6, interleukin-1 beta (IL-1β)). In animal models of ischemia-reperfusion, endotoxemia, and neurodegeneration, oral or intravenous glycine reduces tissue damage and preserves function.
For the auditory system, this matters because low-grade neuroinflammation in the cochlea and cochlear nucleus is increasingly recognized as a contributor to both hearing loss and tinnitus. Microglial activation in the DCN has been documented after noise exposure and tracks the emergence of tinnitus-like behavior. Glycine’s ability to quiet microglia adds a second, complementary mechanism to its direct neurotransmitter action.
Glycine also stabilizes the blood-labyrinth barrier and reduces endothelial inflammation, contributing to the vascular integrity of the stria vascularis — the cochlea’s primary energy-generating tissue.
Glycine, Sleep Quality & Tinnitus Perception
Few factors amplify tinnitus distress like poor sleep, and few factors improve it like restorative sleep. Glycine occupies a uniquely useful position here. Controlled studies in healthy adults with mild sleep complaints have shown that 3 g of glycine taken 30–60 minutes before bedtime:
- Shortens subjective and polysomnographic sleep-onset latency.
- Increases slow-wave (stage 3) sleep duration and depth.
- Improves next-day subjective fatigue and cognitive performance scores.
- Lowers core body temperature modestly via peripheral vasodilation — a physiologically normal prelude to deep sleep.
The mechanism appears to involve both direct glycinergic inhibition of arousal-promoting neurons in the hypothalamus and indirect support of N-methyl-D-aspartate-mediated slow-wave generation. For tinnitus sufferers, this combination — fewer arousals, deeper sleep, cooler skin — would counter the night-time worsening that most patients describe.
Because the sleep dose (3 g) is also the low end of the 3–10 g range practitioners describe for tinnitus, they use a single nightly serving for both.
Synergy with Magnesium, Zinc & Other Cofactors
Glycine does not act in isolation. Several cofactors meaningfully enhance its effects on the auditory system:
- Zinc is a positive allosteric modulator of glycine receptors at nanomolar concentrations and is concentrated in cochlear hair cells and DCN synaptic vesicles. Zinc deficiency has been repeatedly associated with tinnitus severity, and zinc repletion (typically 25–50 mg/day for 2–3 months) is one of the better-studied nutritional interventions in the tinnitus literature. Combining zinc with glycine pairs receptor potentiation with substrate supply.
- Magnesium blocks N-methyl-D-aspartate receptors and protects cochlear hair cells from glutamate excitotoxicity during noise exposure. Because glycine is a N-methyl-D-aspartate co-agonist, magnesium’s voltage-dependent block provides a natural governor that keeps glycine’s excitatory side modest while preserving its inhibitory GlyR action.
- Vitamin B₁₂ supports myelination of auditory nerve fibers and methionine/homocysteine balance; B₁₂ deficiency is overrepresented in tinnitus populations.
- Vitamin B₆ is a cofactor for glycine metabolism and serine-to-glycine interconversion.
- Taurine shares inhibitory neurotransmitter properties with glycine and has its own growing tinnitus literature (see the Taurine companion article).
Practitioners suggest combining glycine, magnesium glycinate (which itself supplies both), zinc picolinate, a B-complex, and sometimes taurine, on the reasoning that together they act on the auditory inhibitory system from several angles. No trial has tested such a combination for tinnitus.
Dietary Sources & Supplementation Approaches Used in Research
Glycine is abundant in collagen-rich foods — the parts of animals modern diets most often discard. The richest sources include:
- Bone broth (simmered 12–48 hours): roughly 2–5 g glycine per cup, depending on preparation.
- Gelatin and collagen peptide powders: approximately 2.5–3 g glycine per 10 g scoop.
- Skin-on poultry, pork rinds, oxtail, shank, and tendons: several grams per serving.
- Fish with edible skin and bones (sardines, anchovies): meaningful contributions.
- Spirulina and certain seaweeds: modest but useful plant sources.
- Legumes (particularly soybeans, peanuts): the best plant-based contributors.
The supplementation amounts used in research, and by practitioners for tinnitus, are:
- Sleep and mild neurological support: 3 g glycine powder dissolved in water, 30–60 minutes before bed.
- Practitioner tinnitus protocols and broader neuro-support: 3–10 g/day, often split into a small morning dose and a larger evening dose (practitioner use; no tinnitus trial).
- GlyNAC for oxidative stress and mitochondrial support: glycine at roughly 100 mg/kg/day paired with N-acetylcysteine at roughly 100 mg/kg/day, divided across meals, for 12–24 weeks in the published trials.
- Collagen-focused approaches: 10–20 g hydrolyzed collagen daily, which delivers 2.5–6 g glycine along with proline, hydroxyproline, and other useful amino acids.
Glycine powder has a mildly sweet taste (the name comes from the Greek glykys, sweet), dissolves readily in water, and is inexpensive — practical features that make consistent daily use easy to sustain over several months.
How Glycine Complements Taurine and Ginkgo Biloba
The three anchor articles of this hub — glycine, taurine, and Ginkgo biloba — cover non-overlapping layers of the tinnitus problem, which is why practitioners combine them.
- Glycine supplies the auditory brainstem with its primary inhibitory transmitter, restoring GlyR-mediated damping of DCN hyperactivity and supporting glutathione-based antioxidant defense.
- Taurine acts as a secondary inhibitory modulator at both GlyR and gamma-aminobutyric acidA receptors, stabilizes calcium handling in hair cells, and contributes to membrane osmotic regulation in the cochlea.
- Ginkgo biloba works upstream at the vascular and microcirculatory level, improving cochlear blood flow, scavenging free radicals with its flavonoid and terpene lactone fractions, and supporting neuronal membrane stability.
In combination, these three address (1) inhibitory neurotransmission, (2) receptor-level modulation and cochlear calcium handling, and (3) cochlear perfusion and oxidative protection. Each has its own research base; taken together, practitioners describe them as targeting the tinnitus circuit at complementary points.
Key Research Papers
- Richardson BD, Brozoski TJ, Ling LL, Caspary DM. Targeting inhibitory neurotransmission in tinnitus. Brain Res. 2012;1485:77-87. — PubMed PMID: 22405692
- Bauer CA. Tinnitus. N Engl J Med. 2018;378(13):1224-1231. — PubMed PMID: 29601255
- File SE, Fluck E, Fernandes C. Beneficial effects of glycine (bioglycin) on memory and attention in young and middle-aged adults. J Clin Psychopharmacol. 1999;19(6):506-12. — PubMed PMID: 10587285
- Muñoz-Carlin Mde L, Rodríguez-Moctezuma JR, Gómez Latorre JG, Montes-Castillo ML, Juárez-Adauta S. [Effects of glycine on auditory evoked potentials among diabetic patients with auditory pathway neuropathy]. Rev Med Chil. 2010;138(10):1246-52 (in Spanish). — PubMed PMID: 21279270
- Tzounopoulos T, Kim Y, Oertel D, Trussell LO. Cell-specific, spike timing-dependent plasticities in the dorsal cochlear nucleus. Nat Neurosci. 2004. — PubMed PMID: 15208632
- Brozoski TJ, Bauer CA, Caspary DM. Elevated fusiform cell activity in the dorsal cochlear nucleus of chinchillas with psychophysical evidence of tinnitus. J Neurosci. 2002. — PubMed PMID: 11896177
- Wang H, Brozoski TJ, Turner JG, et al. Plasticity at glycinergic synapses in dorsal cochlear nucleus of rats with behavioral evidence of tinnitus. Neuroscience. 2009. — PubMed PMID: 19699270
- Caspary DM, Ling L, Turner JG, Hughes LF. Inhibitory neurotransmission, plasticity and aging in the mammalian central auditory system. J Exp Biol. 2008. — PubMed PMID: 18490394
- Lynch JW. Molecular structure and function of the glycine receptor chloride channel. Physiol Rev. 2004. — PubMed PMID: 15383648
- Yamadera W, Inagawa K, Chiba S, Bannai M, Takahashi M, Nakayama K. Glycine ingestion improves subjective sleep quality in human volunteers, correlating with polysomnographic changes. Sleep Biol Rhythms. 2007. Sleep and Biological Rhythms 2007
- Bannai M, Kawai N. New therapeutic strategy for amino acid medicine: glycine improves the quality of sleep. J Pharmacol Sci. 2012. — PubMed PMID: 22293292
- Kumar P, Liu C, Suliburk J, Hsu JW, Muthupillai R, Jahoor F, Minard CG, Taffet GE, Sekhar RV. Supplementing Glycine and N-Acetylcysteine (GlyNAC) in Older Adults Improves Glutathione Deficiency, Oxidative Stress, Mitochondrial Dysfunction, Inflammation, Physical Function, and Aging Hallmarks: A Randomized Clinical Trial. J Gerontol A Biol Sci Med Sci. 2023;78(1):75-89. — PubMed PMID: 35975308
- Meléndez-Hevia E, De Paz-Lugo P, Cornish-Bowden A, Cárdenas ML. A weak link in metabolism: the metabolic capacity for glycine biosynthesis does not satisfy the need for collagen synthesis. J Biosci. 2009;34(6):853-72. — PubMed PMID: 20093739
- Zhang JS, Kaltenbach JA. Increases in spontaneous activity in the dorsal cochlear nucleus of the rat following exposure to high-intensity sound. Neurosci Lett. 1998;250(3):197-200. — PubMed PMID: 9708866
- Wang J, Caspary D, Salvi RJ. GABA-A antagonist causes dramatic expansion of tuning in primary auditory cortex. NeuroReport. 2000 — companion inhibitory-neurotransmitter literature. — PubMed PMID: 10790896
- Brozoski TJ, Caspary DM, Bauer CA, Richardson BD. The effect of supplemental dietary taurine on tinnitus and auditory discrimination in an animal model. Hear Res. 2010;270(1-2):71-80. — PubMed PMID: 20868734
- Bauer CA. Tinnitus: mechanisms and management. Hearing Review. Hearing Review — Tinnitus mechanisms