Tinnitus Causes and Triggers
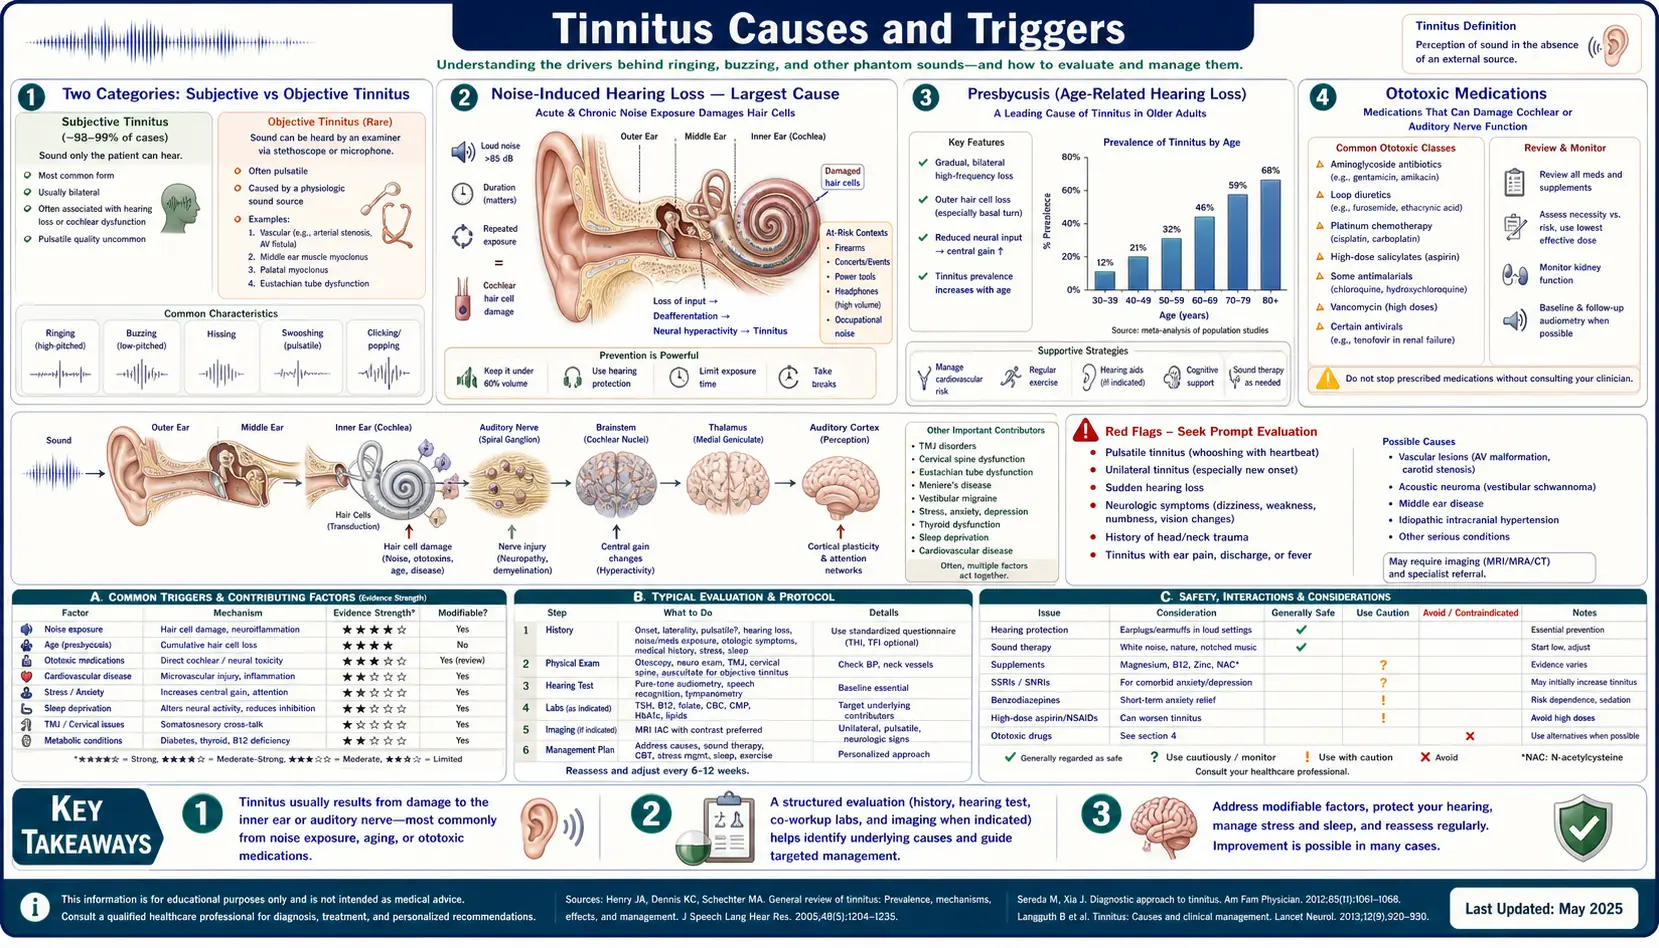
Tinnitus has no single cause — it is a final-common-pathway symptom of dozens of distinct upstream insults, ranging from peripheral cochlear hair-cell damage to central auditory-cortex maladaptive plasticity to vascular, muscular, and joint pathology in the head and neck. Identifying which upstream cause is dominant in any individual patient determines which interventions will be effective. This page walks through the major mechanistic categories with prevalence figures, the validated trigger inventory that fluctuates symptom severity, and the practical assessment that distinguishes treatable peripheral causes from intractable central tinnitus.
Table of Contents
- Two Categories: Subjective vs Objective Tinnitus
- Noise-Induced Hearing Loss — The Largest Cause
- Presbycusis (Age-Related Hearing Loss)
- Ototoxic Medications
- Otologic Conditions (Meniere's, Otosclerosis, Schwannoma)
- Somatic Tinnitus (Jaw Joint, Cervical Spine, Whiplash)
- Pulsatile and Vascular Tinnitus
- Central Auditory Plasticity — The Phantom-Limb Analogy
- The Modifiable Trigger Inventory
- Practical Assessment for the New Tinnitus Patient
- Key Research Papers
- Connections
- Featured Videos
Two Categories: Subjective vs Objective Tinnitus
The first clinical distinction is between subjective tinnitus (heard only by the patient, generated by neural activity without external sound) and objective tinnitus (a real acoustic phenomenon that can sometimes be heard by an examining clinician with a stethoscope placed over the ear). Subjective tinnitus accounts for greater than 99% of cases. Objective tinnitus, while rare, is more often treatable because it has a definable acoustic generator — vascular turbulence, palatal myoclonus, stapedial muscle spasm, eustachian tube dysfunction — that can sometimes be eliminated.
The clinical question on first encounter is therefore: does the patient's tinnitus have any character suggesting an objective generator? Pulsatile tinnitus that tracks the heartbeat strongly suggests a vascular cause (worth pursuing imaging). Tinnitus with a clicking or thumping quality that the examiner can detect suggests palatal myoclonus or stapedial myoclonus. Pure tonal or high-frequency hissing tinnitus is almost always subjective and the workup focuses on identifying the peripheral cochlear or central cause.
Noise-Induced Hearing Loss — The Largest Cause
Acoustic overexposure is by far the most common identifiable cause of subjective tinnitus, accounting for an estimated 40–50% of cases in adult civilian populations and a substantially higher fraction in military veterans (tinnitus is the most common service-connected disability in the US Department of Veterans Affairs system).
The mechanism is mechanical and biochemical injury to the outer hair cells of the cochlea, the most vulnerable structures in the inner ear. Acoustic overexposure produces a sudden glutamate excitotoxic surge at the inner-hair-cell synapse, mitochondrial calcium overload, reactive oxygen species generation, and ultimately apoptotic and necrotic death of outer hair cells — particularly in the basal (high-frequency) region of the cochlea. The classic noise notch on audiometry at 4 kHz reflects this anatomic pattern.
The relationship between noise exposure and tinnitus is not linear. A single severe acoustic event (a gunshot, an explosion, a rock concert) can produce immediate and permanent tinnitus. Repetitive moderate exposure (workplace noise, regular concert attendance, prolonged use of in-ear headphones at high volume) produces cumulative damage that emerges as tinnitus and hearing loss after years of exposure. The "temporary threshold shift" that follows acute exposure — the ringing and muffled hearing that resolves over hours to days after a loud event — was historically considered harmless but is now understood to produce cochlear synaptopathy (hidden hearing loss) even when audiogram thresholds return to normal.
Presbycusis (Age-Related Hearing Loss)
Presbycusis is the gradual high-frequency sensorineural hearing loss that occurs with aging, driven by progressive loss of outer hair cells, stria vascularis atrophy, and degeneration of spiral ganglion neurons. It is the second-most-common identifiable cause of tinnitus and dominates the etiology in patients over 60.
The pattern of hearing loss in presbycusis — gradual rolloff above 2–4 kHz — matches the frequency at which most patients perceive their tinnitus. This is not coincidence. The Schaette and McAlpine "central gain" model proposes that the central auditory cortex compensates for reduced afferent input from a damaged cochlea by turning up its own gain, much like a hearing aid amplifying a weak signal. The upregulated central gain amplifies spontaneous neural activity into a perceived tone — the phantom signal of tinnitus — centered at the frequencies where peripheral input is most attenuated.
The 2014 American Academy of Otolaryngology–Head and Neck Surgery (AAO-HNS) tinnitus guideline states that clinicians may obtain a full hearing test (comprehensive audiologic examination) for anyone with tinnitus, and should obtain a prompt one when the tinnitus is in one ear, has lasted 6 months or longer, or comes with hearing difficulty. The frequencies of the patient's tinnitus typically correspond to the frequencies of their hearing loss, and amplification with appropriately fit hearing aids reduces the central gain and often the perceived tinnitus loudness as a side effect of the primary hearing-loss treatment. See the sound therapy page for the role of hearing aids in tinnitus management.
Ototoxic Medications
Several drug classes are well-documented to cause tinnitus and hearing loss through direct cochlear toxicity. The major offenders:
- Salicylates (aspirin) — at high doses (greater than 4 g/day), aspirin produces dose-dependent reversible tinnitus through cochlear COX inhibition and outer-hair-cell electromotility changes. Tinnitus resolves within 24–72 hours of dose reduction. The threshold dose for symptoms varies considerably; some patients develop tinnitus on standard analgesic doses.
- Aminoglycoside antibiotics — gentamicin, tobramycin, amikacin, neomycin, and streptomycin produce ototoxicity through cochlear and vestibular hair-cell death, often permanent. Risk is greatest with prolonged intravenous (IV) therapy, renal impairment, and pre-existing hearing loss. Genetic susceptibility (mitochondrial A1555G mutation) produces severe permanent hearing loss after a single dose in affected individuals.
- Loop diuretics — furosemide, bumetanide, and ethacrynic acid cause usually-reversible tinnitus through disruption of the stria vascularis sodium-potassium ATPase, particularly at high intravenous doses and in patients with renal insufficiency.
- Platinum-based chemotherapy — cisplatin produces dose-dependent, often permanent, ototoxicity and tinnitus through outer-hair-cell reactive oxygen species (ROS) injury. Carboplatin is somewhat less ototoxic at standard doses. This is the setting in which N-acetylcysteine (NAC) and other antioxidants are most actively investigated as otoprotectants (see the N-acetylcysteine deep-dive).
- Quinine and chloroquine — quinine produces dose-dependent reversible tinnitus (the syndrome called "cinchonism"). The antimalarial chloroquine is similar.
- Nonsteroidal anti-inflammatory drugs (NSAIDs) — ibuprofen, naproxen, and indomethacin can produce tinnitus through a salicylate-like mechanism, generally reversible.
Stopping an ototoxic medication when possible — or switching to a non-ototoxic alternative — can resolve drug-induced tinnitus entirely. A prescribed antibiotic or chemotherapy drug is not stopped on one's own, because the infection or cancer it treats carries its own danger; new ringing or hearing loss during aminoglycoside, cisplatin, or high-dose intravenous loop-diuretic treatment is a sign of ear damage that the treating team needs to know about the same day.
Otologic Conditions (Meniere's, Otosclerosis, Schwannoma)
Several specific otologic diseases produce tinnitus as a primary feature:
- Meniere's disease — an idiopathic disorder of endolymphatic hydrops producing the classic triad of fluctuating low-frequency hearing loss, episodic vertigo, and roaring or low-pitched tinnitus. The tinnitus quality is characteristic and distinguishes Meniere's from most other causes. Sodium restriction, diuretics, and intratympanic steroid or gentamicin injection are standard management.
- Otosclerosis — abnormal bony remodeling fixing the stapes footplate, producing conductive hearing loss and often tinnitus, frequently in younger adults (peak onset 20–40). Stapedectomy surgery resolves the conductive loss and often the tinnitus.
- Vestibular schwannoma (acoustic neuroma) — a benign tumor of Schwann cells on the vestibular branch of cranial nerve VIII, presenting with unilateral hearing loss, tinnitus, and sometimes vertigo. For this reason, tinnitus in one ear — especially with hearing loss on the same side — is commonly investigated with magnetic resonance imaging (MRI) to rule out schwannoma; the 2014 AAO-HNS guideline recommends against imaging only for tinnitus that does not localize to one ear, is nonpulsatile, and comes without focal neurologic abnormalities or asymmetric hearing loss. Most are slow-growing and managed with observation, but a missed schwannoma growing into the cerebellopontine angle can be catastrophic.
- Eustachian tube dysfunction — chronic middle-ear pressure dysregulation produces a sensation of fullness and often low-pitched fluctuating tinnitus. Nasal steroid sprays, Valsalva maneuvers, and (in selected cases) balloon dilation of the eustachian tube address the underlying pathology.
- Cerumen impaction — the simplest and most embarrassingly missed cause. Removing impacted wax can resolve tinnitus in a small but real fraction of cases. An ear examination with an otoscope is part of the standard first tinnitus visit.
Somatic Tinnitus (Jaw Joint, Cervical Spine, Whiplash)
Somatic tinnitus is a distinct subtype in which the phantom percept is modulated by movement or pressure of the head, neck, or jaw. The underlying mechanism is convergence of somatosensory input from the trigeminal nerve and upper-cervical dorsal-root ganglia onto the dorsal cochlear nucleus — the first central relay of the auditory pathway. Aberrant somatosensory signaling from temporomandibular joint (TMJ, the jaw joint) dysfunction or cervical-spine pathology biases dorsal-cochlear-nucleus activity and generates a phantom auditory signal.
Clinical features that suggest somatic tinnitus:
- Tinnitus modulated by jaw clenching, chewing, or neck rotation
- Co-existing TMJ pain, clicking, or limited mouth opening
- Co-existing cervical pain or limited neck range of motion
- History of whiplash, cervical-spine surgery, or chronic posture-related neck strain
- Normal or near-normal audiogram
Treatment of the underlying somatic dysfunction — physical therapy for cervical spine and posture, dental management of TMJ dysfunction, occlusal splints, trigger-point injections — can produce substantial tinnitus improvement in this subset. The Levine model (1999) of somatic tinnitus is the seminal description of the mechanism.
Pulsatile and Vascular Tinnitus
Pulsatile tinnitus — a rhythmic sound that tracks the heartbeat — is a distinct subtype that almost always has an identifiable vascular cause. Unlike most tinnitus, pulsatile tinnitus warrants prompt imaging workup because some causes are surgically correctable and a few are life-threatening.
The differential includes:
- Atherosclerotic carotid disease — turbulent flow through a stenotic carotid artery produces audible bruit transmitted to the inner ear
- Dural arteriovenous fistula — an abnormal connection between meningeal arteries and dural venous sinuses, producing turbulent flow audible to the patient. Endovascular treatment is curative.
- Glomus tumor (paraganglioma) — a vascular tumor of the middle ear or jugular bulb producing pulsatile tinnitus, conductive hearing loss, and a characteristic reddish mass behind the tympanic membrane
- Sigmoid sinus diverticulum or dehiscence — an anatomic variant producing turbulent venous flow audible in the adjacent inner ear, often correctable surgically
- Idiopathic intracranial hypertension — elevated cerebrospinal fluid (CSF) pressure produces venous turbulence and pulsatile tinnitus, especially in young overweight women; treatable with weight loss and acetazolamide
- Severe anemia or hyperthyroidism — high-output states with increased cardiac output produce audible vascular flow even in the absence of structural pathology
The standard workup for pulsatile tinnitus is MR angiography of the head and neck, with computed tomography (CT) venography if a venous cause is suspected. Carotid duplex ultrasound screens for atherosclerotic stenosis. Audiometry, complete blood count, and thyroid-stimulating hormone (TSH) are also part of the standard workup.
Central Auditory Plasticity — The Phantom-Limb Analogy
The most important conceptual advance in tinnitus neuroscience in the last 30 years is the recognition that chronic tinnitus is not generated in the ear but in the brain. The Jastreboff neurophysiologic model (1990) and the Eggermont central-gain model (2004) frame tinnitus as a phantom percept analogous to phantom-limb pain in amputees — the central nervous system continues to perceive a signal in the absence of the peripheral generator that originally produced it.
The neuroplastic mechanism: when cochlear hair cells in a specific frequency region are lost (from noise, aging, or ototoxin), the central auditory cortex receives less afferent input from those frequencies. Through Hebbian plasticity, neurons in the deafferented region of cortex expand their receptive fields to encompass adjacent frequencies and increase their spontaneous firing rate. This spontaneous activity, in the absence of acoustic input, is interpreted by higher cortical areas as a real sound — the phantom tone of tinnitus.
This central-plasticity model explains several otherwise puzzling clinical observations:
- Why surgical destruction of the cochlea (rare cochleotomy procedures) does not abolish tinnitus — the phantom signal is now generated centrally, not peripherally
- Why the perceived pitch of tinnitus matches the frequency of the audiometric hearing loss — the deafferented cortical region is what generates the phantom signal
- Why amplification (hearing aids) reduces tinnitus — restoring afferent input to the deafferented cortical region reduces the maladaptive plasticity
- Why sound therapy and notched-music therapy can reduce tinnitus — targeted acoustic input to the affected frequencies reverses the cortical reorganization
- Why severe stress, sleep deprivation, and limbic activation worsen tinnitus — the prefrontal-limbic filtering circuit that normally suppresses irrelevant background signals is impaired by these states
The Modifiable Trigger Inventory
Once tinnitus is established, its perceived loudness and intrusiveness fluctuate considerably in response to identifiable triggers. A systematic trigger inventory, with a one-month elimination trial of each suspected trigger, is the method used to identify which apply to a given person:
- Caffeine — coffee, tea, energy drinks, and caffeinated soda; the test is 30 days without it, then reintroduction
- Sodium — particularly relevant in Meniere's-type tinnitus; elimination plans set a target of less than 2 g sodium/day
- Alcohol — especially red wine and beer; often produces acute worsening within hours of consumption
- Nicotine — cigarettes, e-cigarettes, and nicotine pouches; vasoconstriction reduces cochlear blood flow
- Sleep deprivation — the single most consistent modulator; less than 7 hours sleep predictably worsens next-day tinnitus
- Stress — through limbic activation and impaired prefrontal filtering; relaxation training, meditation, and cognitive behavioral therapy (CBT) directly address this
- Loud-noise exposure — even brief exposure to concerts, power tools, or fireworks can trigger weeks of increased tinnitus; hearing protection (earplugs or earmuffs) reduces the sound reaching the inner ear
- Aspartame and monosodium glutamate (MSG) — reported by some patients, though formal trial evidence is limited
- Specific medications — see the ototoxic medications section above; even non-ototoxic drugs sometimes worsen tinnitus idiosyncratically
- Dehydration — elimination plans set at least 2 L water/day; dehydration concentrates blood and may alter cochlear microcirculation
Practical Assessment for the New Tinnitus Patient
Tinnitus that arrives together with sudden hearing loss in one ear is treated as urgent by hospitals: the 2019 AAO-HNS sudden hearing loss guideline describes sudden hearing loss as a symptom that often prompts an urgent or emergency visit, frequently accompanied by tinnitus or vertigo, and states that prompt recognition and management may improve hearing recovery.
A typical first-visit workup for new tinnitus includes:
- History — onset, duration, laterality, character (tonal, hissing, pulsatile, clicking), modulating factors (jaw, neck movement, head position), associated symptoms (hearing loss, vertigo, otalgia, fullness), occupational and recreational noise exposure, complete medication list, family history of hearing loss
- Otoscopic examination — rule out cerumen impaction, tympanic-membrane perforation, middle-ear effusion, visible mass
- Audiometry — pure-tone air and bone conduction, speech audiometry, tympanometry; ideally extending to 8 kHz
- Tinnitus matching — pitch and loudness matching using audiometric tones, validated questionnaires (Tinnitus Handicap Inventory, Tinnitus Functional Index) to quantify distress baseline
- Laboratory studies — serum B12, ferritin, magnesium, zinc, thyroid-stimulating hormone, basic metabolic panel, complete blood count; see the nutrient-status deep-dive
- Magnetic resonance imaging — used for tinnitus in one ear (to rule out vestibular schwannoma) and for pulsatile tinnitus (magnetic resonance angiography); the 2014 AAO-HNS guideline recommends against imaging for tinnitus that does not localize to one ear, is nonpulsatile, and has no focal neurologic abnormalities or asymmetric hearing loss
- Jaw-joint (TMJ) and cervical examination — particularly if tinnitus modulates with jaw or neck movement
- Specialty referral — otolaryngology for any structural finding; neurology for pulsatile or refractory cases; psychology for prominent distress component
Key Research Papers
- Jastreboff PJ (1990). Phantom auditory perception (tinnitus): mechanisms of generation and perception. Neuroscience Research 8(4):221-254. — PubMed PMID: 2175858
- Bauer CA (2018). Tinnitus. N Engl J Med 378(13):1224-1231. — PubMed PMID: 29601255
- Schaette R, McAlpine D (2011). Tinnitus with a normal audiogram: physiological evidence for hidden hearing loss. Journal of Neuroscience — PubMed PMID: 21940438
- Levine RA (1999). Somatic (craniocervical) tinnitus and the dorsal cochlear nucleus hypothesis. American Journal of Otolaryngology — PubMed PMID: 10609479
- Tunkel DE et al. (2014). Clinical practice guideline: tinnitus. Otolaryngol Head Neck Surg — PubMed PMID: 25273878
- Langguth B, Kreuzer PM, Kleinjung T, De Ridder D (2013). Tinnitus: causes and clinical management. Lancet Neurology 12(9):920-930. — PubMed PMID: 23948178
- Baguley D, McFerran D, Hall D (2013). Tinnitus. Lancet — PubMed PMID: 23827090
- Henry JA et al. (2005). General review of tinnitus: prevalence, mechanisms, effects, and management. J Speech Lang Hear Res — PubMed PMID: 16411806
- Bhatt JM et al. (2016). Prevalence, severity, exposures, and treatment patterns of tinnitus in the US. JAMA Otolaryngol — PubMed PMID: 27441392
- Eggermont JJ, Roberts LE (2004). The neuroscience of tinnitus. Trends in Neurosciences — PubMed PMID: 15474168
- Bisht M, Bist SS (2011). Ototoxicity: the hidden menace. Indian J Otolaryngol — PubMed PMID: 22754805
- Chandrasekhar SS, Tsai Do BS, Schwartz SR, et al. (2019). Clinical Practice Guideline: Sudden Hearing Loss (Update) Executive Summary. Otolaryngol Head Neck Surg 161(2):195-210. — PubMed PMID: 31369349
PubMed Topic Searches
Connections
- All Remedies
- Tinnitus Hub
- Benefits Deep-Dive Hub
- Nutrient Status (B12, Mg, Zn)
- Sound Therapy and Habituation
- N-Acetylcysteine and Antioxidants
- Ginkgo Biloba for Tinnitus
- Glycine for Tinnitus
- Taurine for Tinnitus
- Neurology
- Vitamin B12
- Magnesium
- Zinc
- N-Acetyl-Cysteine
- Ginkgo Biloba
- Tinnitus — the ENT clinical overview: diagnosis, audiometric workup, and the full differential behind these causes.
- Covered in depth on its own page: Hearing Loss