⚠ Evidence warning: Clinical trials or other evidence do not support the claims that chromium reduces carbohydrate cravings through brain insulin signaling and improves blood sugar and cholesterol. This page keeps it as a report of what people, websites or other media say.
Chromium — Benefits Deep Dive
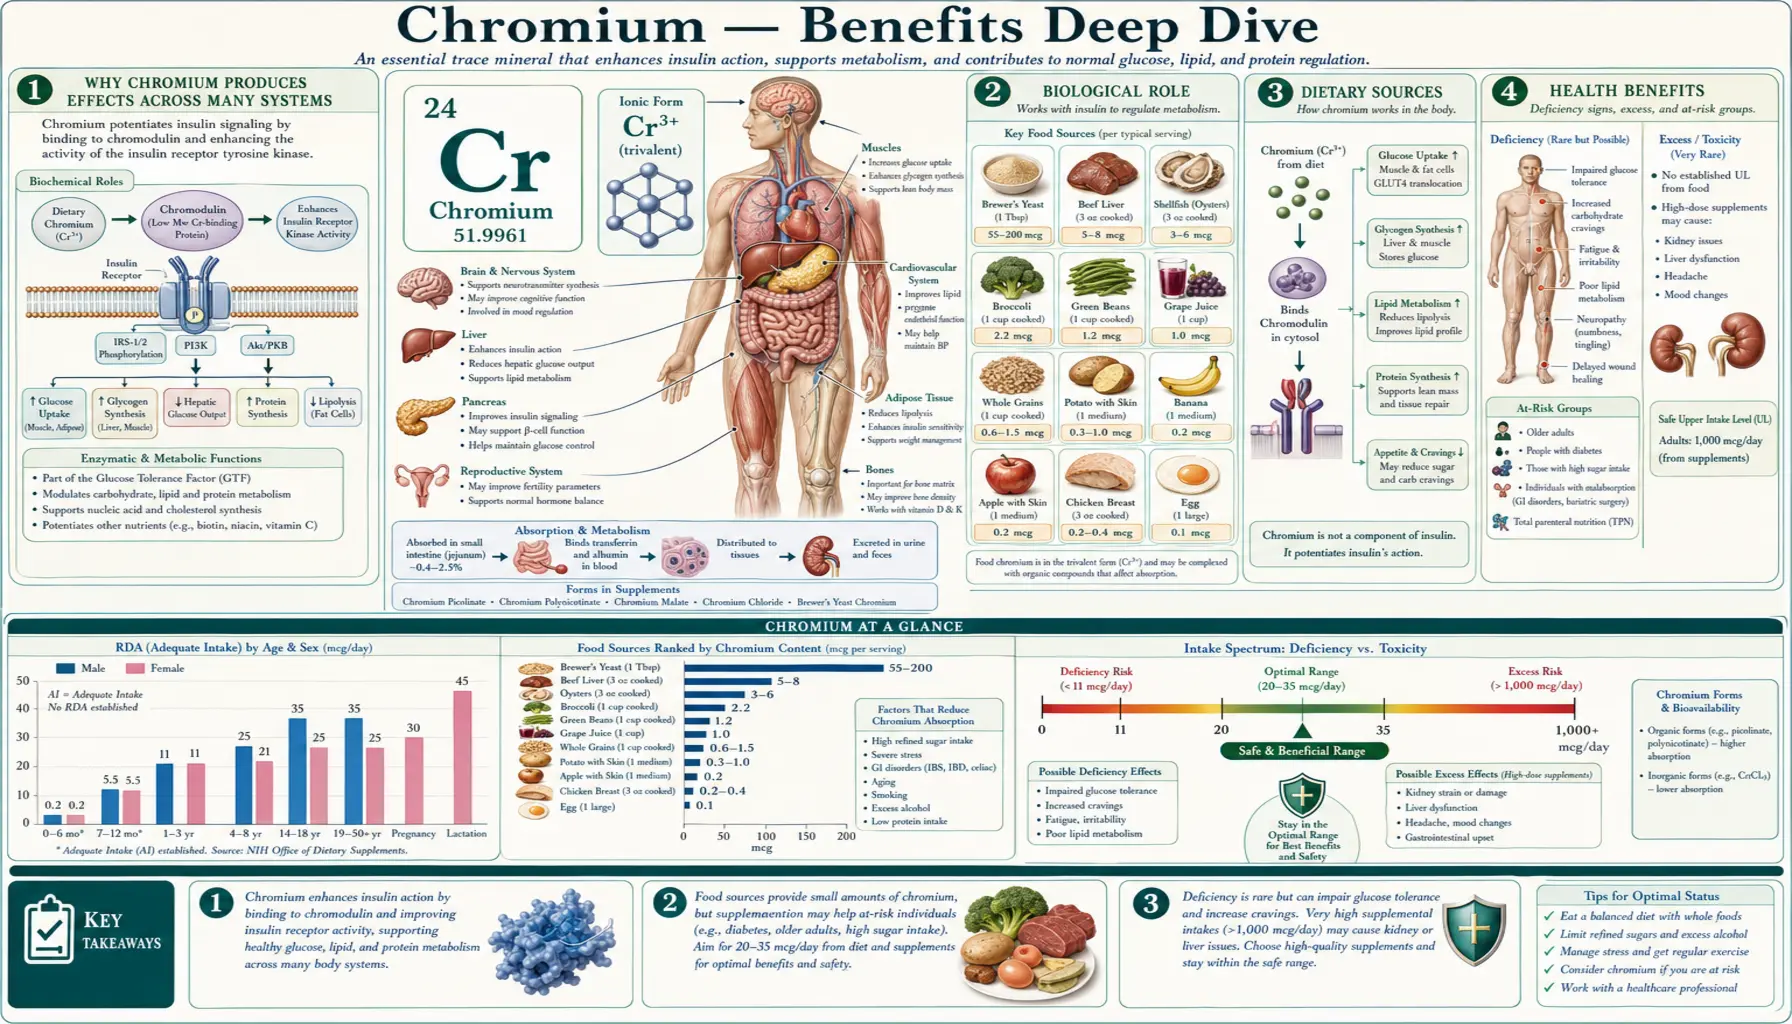
Chromium is the single trace mineral most directly tied to insulin signaling. The leading proposal is that every clinical effect ascribed to chromium — glycemic control in type 2 diabetes, lipid panel improvement, modest reductions in body fat, suppression of carbohydrate cravings — flows downstream from one molecular event: the oligopeptide chromodulin (low-molecular-weight chromium-binding substance, LMWCr) loading four trivalent chromium ions and binding to the activated insulin receptor, amplifying its tyrosine kinase activity by up to eight-fold in vitro (measured in rat fat-cell membrane fragments). A 2019 review states that the molecular mode of action "has failed to be elucidated". The four benefit pages below explore the conditions where chromium produces the largest clinical effect — the glycemic axis in established type 2 diabetes, the receptor-level mechanism of insulin sensitization that underlies every other benefit, the secondary downstream effects on the lipid panel, and the weight-management literature that emerged from the 1990s chromium picolinate boom and that practitioners now describe as a modest adjunct for carbohydrate-craving-driven overconsumption.
Deep-Dive Articles
Blood Sugar Regulation
The clinical translation of chromium biology — fasting glucose, hemoglobin A1c (HbA1c), postprandial glucose excursions, and the meta-analytic evidence in type 2 diabetes. The Anderson 1997 Beijing trial (after 4 months, hemoglobin A1c was 6.6% on 1,000 mcg/day chromium picolinate against 8.5% on placebo), Balk's 2007 Diabetes Care meta-analysis, the chromium-free total parenteral nutrition (intravenous feeding) deficiency case reports long cited as establishing essentiality, which a 2017 review disputes, and the emerging evidence in gestational diabetes and polycystic ovary syndrome (PCOS).
Read the deep dive →Insulin Sensitivity
The molecular mechanism that underlies every other chromium benefit. Chromodulin structure (four Cr3+ ions on a four-amino-acid peptide), the insulin-receptor tyrosine kinase amplification cycle, IRS-1/PI3K/Akt/AS160 downstream signaling, GLUT4 translocation in skeletal muscle and adipose tissue, transferrin-mediated delivery of chromium to insulin-responsive cells, and the bioavailability differences between chromium picolinate, polynicotinate, chloride, and histidinate.
Read the deep dive →Lipid Profile
How insulin sensitization produces coordinated improvement across the lipid panel. The Press 1990 trial (28 volunteers, 200 micrograms a day, 42-day crossover; the classic chromium-and-lipids citation), the mechanism through hepatic very-low-density lipoprotein (VLDL) secretion and ApoB-100 suppression, low-density lipoprotein-receptor upregulation, lipoprotein lipase activation, and the downstream effects on triglycerides, total and low-density lipoprotein (LDL) cholesterol, and high-density lipoprotein (HDL). Practitioners describe chromium as an add-on to statin therapy and lifestyle modification.
Read the deep dive →Weight Management
The legitimate clinical evidence extracted from the 1990s chromium-picolinate marketing boom. Kaats's hydrostatic-weighing body-composition trials, Volpe's tightly-controlled 2001 dual-energy X-ray absorptiometry study (44 women, 400 micrograms a day for 12 weeks, no significant change in body composition), Davidson's 2003 pilot trial in atypical depression (15 patients, 70% versus 0% responders), the Docherty 2005 follow-up in 113 patients (no difference on the main depression measures, with carbohydrate craving better on single scale items in the evaluable group and in a high-craving subgroup), the serotonergic and noradrenergic mechanism, supplement quality and reformulation concerns, and the role practitioners describe for chromium as a modest adjunct in carbohydrate-craving-driven overconsumption in the glucagon-like peptide-1 (GLP-1)-agonist era.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why Chromium Produces Effects Across Many Systems
- Research Papers: Blood Sugar Regulation
- Research Papers: Insulin Sensitivity
- Research Papers: Lipid Profile
- Research Papers: Weight Management
- Research Papers: Cross-Cutting (Mechanism, Status, Safety)
- External Authoritative Resources
- Connections
- Featured Videos
Why Chromium Produces Effects Across Many Systems
Most trace minerals participate in one principal class of enzyme reaction (zinc in metalloenzymes, iron in heme/iron-sulfur cluster electron transport, copper in oxidase reactions, selenium in selenocysteine-containing antioxidant enzymes). Chromium is unusual because it operates through one fundamentally upstream mechanism that produces clinical effects across many seemingly unrelated organ systems. The proposed mechanism is simple to state and far-reaching in consequence: trivalent chromium loads onto the oligopeptide chromodulin (low-molecular-weight chromium-binding substance, LMWCr), holo-chromodulin binds the activated insulin receptor, and insulin signaling is amplified by up to eight-fold in vitro.
Three categories of clinical effect flow from this single upstream amplification:
- Glycemic effects — amplified insulin signaling at skeletal muscle and adipose tissue increases GLUT4 translocation to the plasma membrane and accelerates glucose disposal from the bloodstream. The downstream clinical signature is reduced fasting glucose, reduced hemoglobin A1c, and reduced postprandial glucose excursions. The strongest evidence is in patients with established type 2 diabetes with poor baseline control — this is the territory of the Blood Sugar Regulation deep-dive and the mechanism-focused Insulin Sensitivity deep-dive.
- Lipid effects — amplified insulin signaling at hepatocytes suppresses very-low-density lipoprotein secretion (reducing circulating triglycerides), upregulates the low-density lipoprotein receptor (accelerating low-density lipoprotein clearance), and modestly suppresses HMG-CoA reductase (modestly reducing cholesterol synthesis). Amplified signaling at adipocytes suppresses inappropriate lipolysis (reducing free fatty acid flux), which secondarily reduces hepatic very-low-density lipoprotein substrate. The proposed downstream clinical signature is reduced triglycerides, modest low-density lipoprotein reduction, modest high-density lipoprotein elevation, and overall improvement in the atherogenic dyslipidemia of insulin resistance — the subject of the Lipid Profile deep-dive. A 2021 meta-analysis of 24 trials in type 2 diabetes found triglycerides down 6.54 mg/dl, total cholesterol down 7.77 mg/dl and high-density lipoprotein up 2.23 mg/dl, with no significant effect on low-density lipoprotein (−8.54 mg/dl, −19.58 to 2.49), and said the effects were small and may not reach clinical importance. A 2007 systematic review reported improved blood sugar in type 2 diabetes but not lipids.
- Central nervous system effects — amplified insulin signaling in the brain modulates serotonergic and noradrenergic neurotransmission, with downstream effects on appetite regulation (particularly carbohydrate craving) and mood (particularly atypical depression). The downstream clinical signature is reduced carbohydrate craving, reduced caloric intake from snacking, and modest mood improvement in subjects with atypical-depression carbohydrate-craving phenotype. This is the territory of the Weight Management deep-dive and Davidson's 2003 atypical-depression trial, a 15-patient pilot that reported depression response; the craving data come from the larger Docherty 2005 trial.
The same single mechanism (chromodulin-mediated insulin-receptor amplification) thus produces three distinct categories of clinical effect because insulin itself is a master hormone with effects on glucose disposal, lipid handling, and neuroendocrine regulation. Anything that potentiates insulin signaling therefore produces a constellation of effects matching insulin's own constellation of physiological roles.
This integrative framework also explains a recurring pattern in the clinical literature: chromium's benefits are clearest in subjects with documented insulin resistance and weakest in metabolically healthy individuals. Amplifying an already-adequate insulin signal produces minimal additional benefit; amplifying a resistant signal that is failing produces measurable downstream effects across all three categories.
How much of this holds in people is disputed, and the numbers are small:
- Blood sugar — A 2007 review of 41 studies, almost half of poor quality, found hemoglobin A1c down 0.6% and fasting glucose down 1.0 mmol/l in type 2 diabetes, no benefit in people without diabetes, and larger effects more common in poor-quality studies. A 2015 meta-analysis (14 trials, 875 people, 8 to 24 weeks) found no significant effect on hemoglobin A1c from chromium yeast, brewer's yeast or chromium picolinate. A 2014 meta-analysis with a different effect measure (16 studies, 809 people) found a non-significant effect size of 0.02 on fasting glucose. A 2016 review found hemoglobin A1c fell by 0.5% or more in 5 of 14 trials and concluded there is "little rationale to recommend" chromium for blood sugar control in type 2 diabetes.
- Weight — A 2013 meta-analysis of 11 trials found 0.50 kg more weight loss than placebo, and says "the clinical relevance is uncertain". A 2013 Cochrane review found 1.1 kg after 12 to 16 weeks, an effect it calls "of debatable clinical relevance".
- Essential status — A 2017 review by the researcher who described chromodulin's effect on the insulin receptor concluded that chromium "currently can only be considered pharmacologically active and not an essential element". His 2019 update concluded that supplementation "cannot currently be recommended in humans or farm animals".
- Regulators — The US Food and Drug Administration reviewed chromium picolinate and allowed one qualified health claim, on insulin resistance, concluding that the relationship is "highly uncertain".
The therapeutic complications are correspondingly limited but real. Chromium can potentiate the glucose-lowering effect of insulin and oral antidiabetic drugs, creating hypoglycemia risk if introduced without dose adjustment. The trivalent form (Cr3+) used in supplements is nutritionally safe at standard doses; the hexavalent form (Cr6+) is an industrial toxicant and known carcinogen with no nutritional role — the European Food Safety Authority said in 2010 that specifications for chromium picolinate need to keep chromium(VI) as low as possible, and that added chromium was not of concern provided total chromium stays within 250 micrograms a day. Chromium picolinate has been linked to isolated case reports of renal injury: kidney failure reported five months after a six-week course of 600 mcg/day, kidney failure with liver dysfunction and hemolysis at 1,200–2,400 mcg/day for 4 to 5 months, and reversible acute kidney failure in a 24-year-old man after two weeks on a chromium picolinate-containing supplement. Doses of 200–1,000 mcg/day (the standard therapeutic range) were tested in reviewed trials lasting up to 24 weeks; those reviews hold no long-term data.
Research Papers: Blood Sugar Regulation
- Anderson RA, Cheng N, Bryden NA, Polansky MM, Cheng N, Chi J, Feng J (1997). Elevated intakes of supplemental chromium improve glucose and insulin variables in individuals with type 2 diabetes (the Beijing trial). Diabetes 46(11):1786-1791. — PubMed PMID: 9356027
- Anderson RA (1998). Chromium, glucose intolerance and diabetes. Journal of the American College of Nutrition 17(6):548-555. — DOI: 10.1080/07315724.1998.10718802. — doi:10.1080/07315724.1998.10718802
- Balk EM, Tatsioni A, Lichtenstein AH, Lau J, Pittas AG (2007). Effect of chromium supplementation on glucose metabolism and lipids: a systematic review of randomized controlled trials. Diabetes Care 30(8):2154-2163. — DOI: 10.2337/dc06-0996. — doi:10.2337/dc06-0996
- Yin RV, Phung OJ (2015). Effect of chromium supplementation on glycated hemoglobin and fasting plasma glucose in patients with diabetes mellitus. Nutrition Journal 14:14. — PubMed PMID: 25971249
- Jeejeebhoy KN, Chu RC, Marliss EB, Greenberg GR, Bruce-Robertson A (1977). Chromium deficiency, glucose intolerance, and neuropathy reversed by chromium supplementation, in a patient receiving long-term total parenteral nutrition. American Journal of Clinical Nutrition 30(4):531-538. — PubMed PMID: 192066
- Cefalu WT, Hu FB (2004). Role of chromium in human health and in diabetes. Diabetes Care 27(11):2741-2751. — PubMed PMID: 15505017
- Suksomboon N, Poolsup N, Yuwanakorn A (2014). Systematic review and meta-analysis of the efficacy and safety of chromium supplementation in diabetes. Journal of Clinical Pharmacy and Therapeutics 39(3):292-306. — PubMed PMID: 24635480
- Heshmati J, Omani-Samani R, Vesali S, Maroufizadeh S, Rezaeinejad M, Razavi M, Sepidarkish M (2018). The effects of supplementation with chromium on insulin resistance indices in women with polycystic ovarian syndrome: a systematic review and meta-analysis of randomized clinical trials. Hormone and Metabolic Research 50(03):193-200. — PubMed PMID: 29523006
- Lamson DW, Plaza SM (2002). The safety and efficacy of high-dose chromium. Alternative Medicine Review 7(3):218-235. — PubMed PMID: 12126463
- Costello RB, Dwyer JT, Bailey RL (2016). Chromium supplements for glycemic control in type 2 diabetes: limited evidence of effectiveness. Nutrition Reviews 74(7):455-468. — PubMed PMID: 27261273
Research Papers: Insulin Sensitivity
- Vincent JB (2000). The biochemistry of chromium. Journal of Nutrition 130(4):715-718. — PubMed PMID: 10736319
- Davis CM, Vincent JB (1997). Chromium oligopeptide activates insulin receptor tyrosine kinase activity. Biochemistry 36(15):4382-4385. — PubMed PMID: 9109644
- Yamamoto A, Wada O, Suzuki H (1988). Purification and properties of biologically active chromium complex from bovine colostrum. Journal of Nutrition 118(1):39-45. — PubMed PMID: 3275760
- Mertz W (1993). Chromium in human nutrition: a review. Journal of Nutrition 123(4):626-633. — PubMed PMID: 8463863
- Vincent JB (2017). New evidence against chromium as an essential trace element. Journal of Nutrition 147(12):2212-2219. — PubMed PMID: 29021369
- Hua Y, Clark S, Ren J, Sreejayan N (2012). Molecular mechanisms of chromium in alleviating insulin resistance. Journal of Nutritional Biochemistry 23(4):313-319. — PubMed PMID: 22423897
- Anderson RA, Polansky MM, Bryden NA, Patterson KY, Veillon C, Glinsmann WH (1983). Effects of chromium supplementation on urinary Cr excretion of human subjects and correlation of Cr excretion with selected clinical parameters. Journal of Nutrition 113(2):276-281. — PubMed PMID: 6822901
- EFSA NDA Panel (2014). Scientific Opinion on Dietary Reference Values for chromium. EFSA Journal 12(10):3845. — PubMed PMID: 42087961
- Bailey CH (2014). Improved meta-analytic methods show no effect of chromium supplements on fasting glucose. Biological Trace Element Research 157(1):1-8. — PubMed PMID: 24293356
- Anderson RA (2003). Chromium and insulin resistance. Nutrition Research Reviews 16(2):267-275. — PubMed PMID: 19087394
Research Papers: Lipid Profile
- Press RI, Geller J, Evans GW (1990). The effect of chromium picolinate on serum cholesterol and apolipoprotein fractions in human subjects. Western Journal of Medicine 152(1):41-45. — PubMed PMID: 2408233
- Abraham AS, Brooks BA, Eylath U (1992). The effects of chromium supplementation on serum glucose and lipids in patients with and without non-insulin-dependent diabetes. Metabolism 41(7):768-771. — PubMed PMID: 1619996
- Riales R, Albrink MJ (1981). Effect of chromium chloride supplementation on glucose tolerance and serum lipids including high-density lipoprotein of adult men. American Journal of Clinical Nutrition 34(12):2670-2678. — PubMed PMID: 7032273
- Asbaghi O, Naeini F, Ashtary-Larky D, Moradi S, Zakeri N, Eslampour E, Kelishadi MR, Naeini AA (2021). Effects of chromium supplementation on lipid profile in patients with type 2 diabetes: a systematic review and dose-response meta-analysis of randomized controlled trials. Journal of Trace Elements in Medicine and Biology 66:126741. — PubMed PMID: 33813266
- Cheng N, Zhu X, Shi H, et al. (1999). Follow-up survey of people in China with type 2 diabetes mellitus consuming supplemental chromium. Journal of Trace Elements in Experimental Medicine 12(2):55-60. — doi:10.1002/(sici)1520-670x(1999)12:2<55::aid-jtra2>3.0.co;2-g
- Ngala RA, Awe MA, Nsiah P (2018). The effects of plasma chromium on lipid profile, glucose metabolism and cardiovascular risk in type 2 diabetes mellitus. A case - control study. PLoS ONE 13(7):e0197977. — PubMed PMID: 29975702
- Ginsberg HN, Zhang YL, Hernandez-Ono A (2005). Regulation of plasma triglycerides in insulin resistance and diabetes. Archives of Medical Research 36(3):232-240. — PubMed PMID: 15925013
- Lai MH (2008). Antioxidant effects and insulin resistance improvement of chromium combined with vitamin C and E supplementation for type 2 diabetes mellitus. Journal of Clinical Biochemistry and Nutrition 43(3):191-198. — PubMed PMID: 19015754
- Wang ZQ, Cefalu WT (2010). Current concepts about chromium supplementation in type 2 diabetes and insulin resistance. Current Diabetes Reports 10(2):145-151. — PubMed PMID: 20425574
- Vrtovec M, Vrtovec B, Briski A, Kocijancic A, Anderson RA, Radovancevic B (2005). Chromium supplementation shortens QTc interval duration in patients with type 2 diabetes mellitus. American Heart Journal 149(4):632-636. — PubMed PMID: 15990745
Research Papers: Weight Management
- Kaats GR, Blum K, Fisher JA, Adelman JA (1996). Effects of chromium picolinate supplementation on body composition: a randomized, double-masked, placebo-controlled study. Current Therapeutic Research 57(10):747-756. — doi:10.1016/s0011-393x(96)80080-4
- Kaats GR, Blum K, Pullin D, Keith SC, Wood R (1998). A randomized, double-masked, placebo-controlled study of the effects of chromium picolinate supplementation on body composition: a replication and extension of a previous study. Current Therapeutic Research 59(6):379-388. — doi:10.1016/s0011-393x(98)85040-6
- Volpe SL, Huang HW, Larpadisorn K, Lesser II (2001). Effect of chromium supplementation and exercise on body composition, resting metabolic rate and selected biochemical parameters in moderately obese women following an exercise program. Journal of the American College of Nutrition 20(4):293-306. — PubMed PMID: 11506057
- Davidson JR, Abraham K, Connor KM, McLeod MN (2003). Effectiveness of chromium in atypical depression: a placebo-controlled trial. Biological Psychiatry 53(3):261-264. — PubMed PMID: 12559660
- Docherty JP, Sack DA, Roffman M, Finch M, Komorowski JR (2005). A double-blind, placebo-controlled, exploratory trial of chromium picolinate in atypical depression: effect on carbohydrate craving. Journal of Psychiatric Practice 11(5):302-314. — PubMed PMID: 16184071
- Onakpoya I, Posadzki P, Ernst E (2013). Chromium supplementation in overweight and obesity: a systematic review and meta-analysis of randomized clinical trials. Obesity Reviews 14(6):496-507. — PubMed PMID: 23495911
- Tian H, Guo X, Wang X, He Z, Sun R, Ge S, Zhang Z (2013). Chromium picolinate supplementation for overweight or obese adults. Cochrane Database of Systematic Reviews (11):CD010063. — PubMed PMID: 24293292
- Anton SD, Morrison CD, Cefalu WT, Martin CK, Coulon S, Geiselman P, Han H, White CL, Williamson DA (2008). Effects of chromium picolinate on food intake and satiety. Diabetes Technology and Therapeutics 10(5):405-412. — PubMed PMID: 18715218
- Lukaski HC, Bolonchuk WW, Siders WA, Milne DB (1996). Chromium supplementation and resistance training: effects on body composition, strength, and trace element status of men. American Journal of Clinical Nutrition 63(6):954-965. — PubMed PMID: 8644693
- Wani S, Weskamp C, Marple J, Spry L (2006). Acute tubular necrosis associated with chromium picolinate-containing dietary supplement. Annals of Pharmacotherapy 40(3):563-566. — PubMed PMID: 16492795
Research Papers: Cross-Cutting (Mechanism, Status, Safety)
- Anderson RA, Polansky MM, Bryden NA, Bhathena SJ, Canary JJ (1987). Effects of supplemental chromium on patients with symptoms of reactive hypoglycemia. Metabolism 36(4):351-355. — PubMed PMID: 3550373
- Stearns DM, Wise JP Sr, Patierno SR, Wetterhahn KE (1995). Chromium(III) picolinate produces chromosome damage in Chinese hamster ovary cells. FASEB Journal 9(15):1643-1648. — PubMed PMID: 8529845
- NIH Office of Dietary Supplements (2024). Chromium fact sheet for health professionals. — NIH ODS Chromium
- Anderson RA, Bryden NA, Polansky MM (1992). Dietary chromium intake. Freely chosen diets, institutional diet, and individual foods. Biological Trace Element Research 32:117-121. — PubMed PMID: 1375047
- Krejpcio Z (2001). Essentiality of chromium for human nutrition and health. Polish Journal of Environmental Studies 10(6):399-404. — PubMed
- Krol E, Krejpcio Z (2010). Chromium(III) propionate complex supplementation improves carbohydrate metabolism in insulin-resistance rat model. Food and Chemical Toxicology 48(10):2791-2796. — PubMed PMID: 20633590
- Komorowski JR, Greenberg D, Juturu V (2008). Chromium picolinate does not produce chromosome damage. Toxicology in Vitro 22(3):819-826. — PubMed PMID: 18261879
- Hummel M, Standl E, Schnell O (2007). Chromium in metabolic and cardiovascular disease. Hormone and Metabolic Research 39(10):743-751. — PubMed PMID: 17952838
- Pittler MH, Stevinson C, Ernst E (2003). Chromium picolinate for reducing body weight: meta-analysis of randomized trials. International Journal of Obesity 27(4):522-529. — PubMed PMID: 12664086
- Vincent JB (2019). Effects of chromium supplementation on body composition, human and animal health, and insulin and glucose metabolism. Current Opinion in Clinical Nutrition and Metabolic Care 22(6):483-489. — PubMed PMID: 31577642
- Trumbo PR, Ellwood KC (2006). Chromium picolinate intake and risk of type 2 diabetes: an evidence-based review by the United States Food and Drug Administration. Nutrition Reviews 64(8):357-363. — PubMed PMID: 16958312
- Wasser WG, Feldman NS, D'Agati VD (1997). Chronic renal failure after ingestion of over-the-counter chromium picolinate. Annals of Internal Medicine 126(5):410. — PubMed PMID: 9054292
- Cerulli J, Grabe DW, Gauthier I, Malone M, McGoldrick MD (1998). Chromium picolinate toxicity. Annals of Pharmacotherapy 32(4):428-431. — PubMed PMID: 9562138
- EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS) (2010). Scientific Opinion on the safety of chromium picolinate as a source of chromium added for nutritional purposes to foodstuff for particular nutritional uses and to foods intended for the general population. EFSA Journal 8(12):1883. — PubMed PMID: 42004120
External Authoritative Resources
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Chromium Fact Sheet (Health Professionals) — the single most up-to-date authoritative summary of chromium evidence in the United States
- Linus Pauling Institute — Chromium Micronutrient Information Center — comprehensive scientific summary maintained at Oregon State
- European Food Safety Authority (EFSA) — Scientific Opinion on Dietary Reference Values for Chromium (2014) — the controversial European position questioning chromium's essentiality, worth reading in dialogue with the U.S. National Institutes of Health and Linus Pauling Institute summaries
- MedlinePlus — Chromium
- PubMed — All chromium picolinate human clinical trials
Connections
- All Minerals
- Chromium (Main Page)
- Chromium for Blood Sugar Regulation
- Chromium for Insulin Sensitivity
- Chromium for Lipid Profile
- Chromium for Weight Management
- Magnesium
- Zinc
- Manganese
- Iron (Transferrin Sharing)
- Insulin Resistance
- Type 2 Diabetes
- Metabolic Syndrome
- Polycystic Ovary Syndrome
- Obesity
- Gestational Diabetes
- Cardiovascular Disease
- Berberine
- Blood Sugar
- Fasting
- Cinnamon
- Vitamin B3 / Niacin
- Hemoglobin A1C
- Fasting Insulin
- Deficiency
- Toxicity
- History