⚠ Evidence warning: Clinical trials or other evidence do not support the claim that chromium picolinate reduces carbohydrate cravings and shifts weight loss toward fat and away from muscle. This page keeps it as a report of what people, websites or other media say.
Chromium for Weight Management
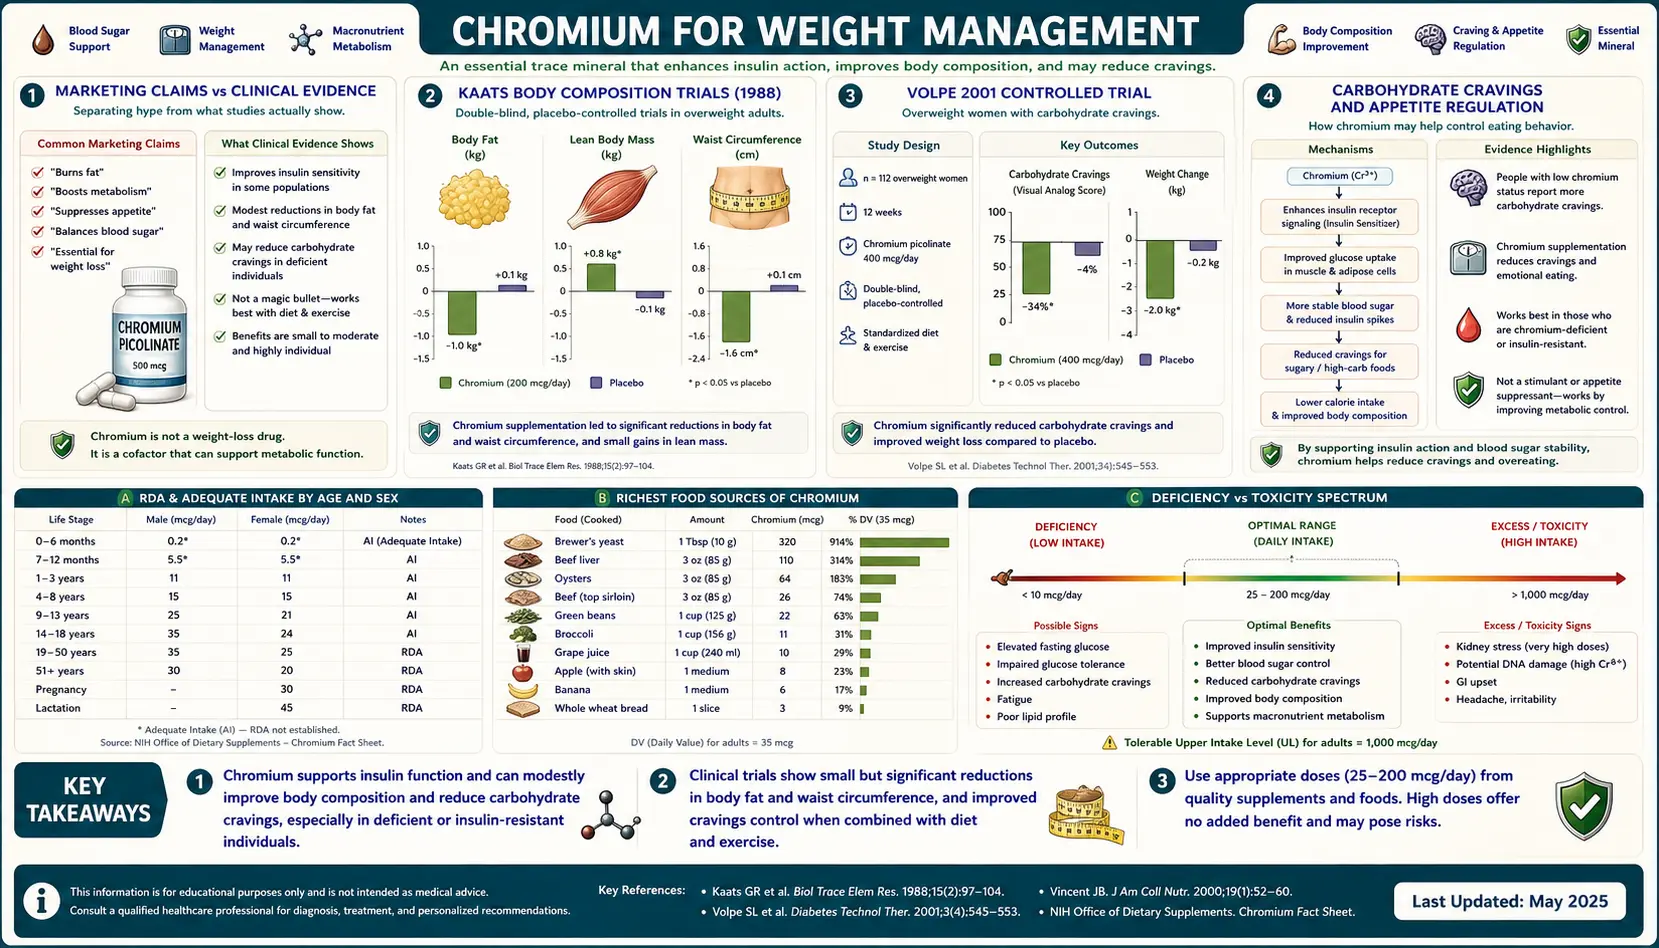
Chromium picolinate was one of the most heavily marketed weight-loss supplements of the 1990s and early 2000s, generating hundreds of millions of dollars in annual U.S. sales on the back of claims that ranged from defensible to ones the Federal Trade Commission challenged as unsubstantiated. The peer-reviewed clinical evidence, when extracted from the marketing noise, tells a more measured story: chromium picolinate produces modest fat-mass reductions in some but not all trials, with the effect most often put forward being reduced appetite and food cravings rather than direct fat oxidation. The main sources are Kaats's two trials in the 1990s, which reported fat loss, Volpe's 2001 randomized controlled trial (RCT), which found no significant effect on body composition, and Davidson's 2003 pilot trial in atypical depression. This deep-dive separates that signal from the marketing noise, examines the carbohydrate-craving mechanism (serotonergic and noradrenergic effects downstream of improved insulin signaling in the brain), discusses supplement quality and reformulation issues, and sets out realistic expectations for people considering chromium as part of a weight-management strategy.
Table of Contents
- Marketing Claims vs Clinical Evidence
- The Kaats Body Composition Trials
- The Volpe 2001 Controlled Trial
- Carbohydrate Cravings and Appetite Regulation
- The Davidson Atypical Depression Trial
- Serotonergic and Noradrenergic Mechanism
- Fat Mass vs Lean Mass Composition
- Exercise Synergy and Resistance Training
- Supplement Quality and Reformulation Cautions
- Realistic Expectations and Clinical Place
- Key Research Papers
- Connections
- Featured Videos
Marketing Claims vs Clinical Evidence
Chromium picolinate emerged as a mass-market weight-loss supplement in the 1990s following the U.S. Department of Agriculture (USDA) Beltsville Anderson studies on chromium and insulin sensitization. The connection from "improves insulin signaling" to "burns fat" was made aggressively by supplement manufacturers, often beyond what the clinical evidence supported. The Federal Trade Commission (FTC) reached consent agreements with chromium picolinate sellers in 1996 and 1997, barring claims about fat loss, muscle gain, cholesterol and other benefits unless competent and reliable scientific evidence backed them.
The agreement announced in November 1996 with the holder of the exclusive U.S. license on chromium picolinate is instructive. The FTC's complaint alleged that the license holder advertised, without a reasonable basis, that chromium picolinate significantly reduces body fat; causes significant, long-term weight loss, even without diet or exercise; increases lean body mass and builds muscle; significantly increases metabolism; controls appetite and reduces cravings for sugar; significantly lowers cholesterol and elevated blood sugar; and treats and prevents diabetes. Sugar cravings were therefore among the challenged claims. The order, made final in 1997, barred those claims unless scientific evidence supported them and required notices to resellers. Under the settlement the respondents did not admit breaking the law.
This regulatory history is worth knowing because it illustrates an important asymmetry: the public perception of chromium picolinate as a "fat burner" is partly an artifact of pre-2000 marketing rather than a fair summary of the clinical literature. One reading of the evidence is that chromium picolinate's effect on weight runs through reduced food intake, not through direct enhancement of fat oxidation or metabolic rate. On that reading, the downstream weight loss is a secondary consequence of behavioral intake reduction rather than a direct pharmacological effect on adipose tissue.
That said, the clinical evidence includes trials reporting modest fat-mass reduction, lean-mass increase, or both, alongside controlled trials that found neither. The effect sizes are smaller than the marketing implied. Supporters describe chromium picolinate as a modestly useful add-on for people whose weight gain is partly driven by carbohydrate over-consumption, especially with insulin resistance. It is not a substitute for caloric restriction, dietary quality improvement, or physical activity.
Two pooled analyses put numbers on weight. Onakpoya 2013 found −0.50 kg against placebo (95% confidence interval −0.97 to −0.03; 11 trials). The 2013 Cochrane review covered 9 trials and 622 people followed for up to 24 weeks, and found −1.1 kg at 12 to 16 weeks (−1.7 to −0.4; 6 trials, 392 people), rated low-quality evidence and of debatable clinical relevance. No dose pattern emerged, and the Cochrane authors "found no current, reliable evidence to inform firm decisions about the efficacy and safety" of these supplements in overweight or obese adults.
The Kaats Body Composition Trials
Gilbert R. Kaats, working at Health and Medical Research Foundation in San Antonio, conducted the two most carefully measured chromium-and-body-composition trials of the 1990s. Both used hydrostatic weighing (the gold-standard body-composition method at the time, since superseded by DXA) to quantify lean and fat mass separately, rather than relying on bathroom-scale weight change. No abstract of either paper could be read for this page, so the affiliation, participant numbers and results below come from this page's earlier summary and remain unchecked against the papers.
- Kaats 1996 — randomized, double-blind, placebo-controlled trial of 200 mcg/day or 400 mcg/day chromium picolinate vs placebo in 154 free-living adults for 72 days. The 400 mcg/day group lost approximately 4.6 kg of fat mass while gaining 1.4 kg of lean mass (net body weight change was modest because of the offsetting lean gain). The 200 mcg/day group showed intermediate changes. The placebo group showed minimal change. The body-composition specificity was important: it ruled out the alternative explanation that any chromium-attributable weight loss was simply water loss or muscle loss.
- Kaats 1998 — larger replication trial (n=122 with full follow-up), 90 days, 400 mcg/day chromium picolinate or placebo. Confirmed the directional finding of fat mass reduction with chromium relative to placebo, though effect magnitude was smaller than in the 1996 trial. Both arms received instruction in caloric restriction and exercise, so the absolute weight changes reflected the combined intervention with chromium contributing as an adjunct.
The Kaats trials were criticized after publication on several methodological grounds: subject self-selection through advertising, modest follow-up duration, and the involvement of chromium-industry funding. The hydrostatic-weighing technique was state-of-the-art for the era but is more variable than modern DXA scanning. Critics argued the effect sizes were near the limit of measurement precision.
Subsequent replication has been heterogeneous. Multiple smaller trials in the 1990s and 2000s confirmed directional fat-mass reduction with chromium picolinate; an approximately equal number found no effect. The Onakpoya 2013 meta-analysis pooling 11 trials (n=866) found a statistically significant but modest mean body-weight reduction of -0.50 kg favoring chromium, with substantial heterogeneity across trials. The authors wrote that the size of the effect "is small, and the clinical relevance is uncertain," and that future trials should last at least 16 weeks. They listed watery stools, vertigo, headaches and hives among the adverse events. The abstract gives no participant total, so the figure of 866 is unchecked.
The Volpe 2001 Controlled Trial
Stella L. Volpe published a double-blind trial in Journal of the American College of Nutrition in 2001. Forty-four moderately obese women aged 27 to 51 were randomized to 400 mcg/day of chromium as chromium picolinate or placebo for 12 weeks. All took part in a supervised weight-training and walking program two days a week. This page earlier also described standardized dietary counseling and body composition measured by DXA; the abstract mentions neither.
Results:
- Body composition and resting metabolic rate were not significantly changed by chromium picolinate
- No significant differences between groups in fasting glucose, insulin, glucagon, C-peptide or blood lipids, or in iron and zinc measures
- Total cholesterol fell across all subjects combined, which the authors attribute to the exercise
- This page earlier gave a mean weight loss of approximately 2.5 kg in both groups and no significant difference in maximum oxygen uptake; the abstract gives neither figure
The Volpe conclusion: 12 weeks of 400 micrograms a day "did not significantly affect body composition" or resting metabolic rate in these women. That runs against the direction of the Kaats findings.
This page earlier called the Volpe trial methodologically the strongest of the chromium-body-composition trials, citing its structured exercise and dietary controls, the DXA measurement, and the absence of industry funding; the abstract does not address the funding. Its finding is a null one, not a modest positive one.
Trials in non-motivated, non-exercising, non-dieting populations are described as finding smaller or null effects, and supporters read this as chromium picolinate acting as an adjunct that potentiates other weight-loss interventions rather than as a stand-alone agent. The exercise trials on this page (Volpe 2001, Lukaski 1996, Trent 1995) did not find that added effect.
Carbohydrate Cravings and Appetite Regulation
The effect of chromium picolinate on body weight most often put forward is reduction in carbohydrate cravings, with downstream caloric intake reduction. People who use it describe less craving for sweet and starchy foods.
The one direct feeding trial on this page tested this in 42 overweight women who reported carbohydrate cravings (Anton 2008). They took 1,000 micrograms of chromium as chromium picolinate or placebo for 8 weeks, and their food was measured at meals. Chromium reduced food intake (P<0.0001), hunger (P<0.05) and fat cravings (P<0.0001), and weight did not significantly change (P=0.08). Cravings for carbohydrates and sweets fell with chromium, but no more than with placebo, so the authors wrote that it is unclear whether chromium has a specific effect on any particular food craving.
The proposed mechanism is tied to improved insulin signaling in the central nervous system. Glucose-sensing neurons in the hypothalamus respond to insulin and to circulating glucose, and they regulate hunger through downstream effects on neuropeptide Y, agouti-related peptide, pro-opiomelanocortin, and other appetite-controlling peptides. When insulin signaling at these neurons is impaired (the central nervous system equivalent of peripheral insulin resistance), appetite regulation is dysregulated — chronic hunger, craving for energy-dense palatable foods, and difficulty achieving satiety. On this hypothesis, restored insulin signaling in these neurons normalizes appetite regulation.
Supporters link a carbohydrate-specific craving reduction to this mechanism. Carbohydrate-rich foods drive larger insulin surges than fat- or protein-rich foods, and the brain's homeostatic response to chronic carbohydrate over-consumption produces craving signals to maintain the elevated intake. Breaking this cycle through pharmacological insulin sensitization (or in the chromium case, modest nutritional insulin sensitization) reduces the craving signal.
Supporters describe the people most likely to notice an effect as those whose weight challenges are driven by chronic carbohydrate over-consumption and snacking, especially evening snacking on sweets and processed carbohydrates, and the least likely as those whose overconsumption is more uniformly distributed across macronutrients or whose weight is driven by reduced physical activity rather than excess intake.
The Davidson Atypical Depression Trial
The trial most often cited for chromium's effect on carbohydrate craving is Jonathan R. T. Davidson's 2003 pilot trial of chromium picolinate in atypical depression. Atypical depression is a subtype characterized by mood reactivity, leaden paralysis, hypersomnia, and (most relevant here) increased appetite with carbohydrate craving. Standard antidepressants treat atypical depression less well than monoamine oxidase inhibitors, and the carbohydrate-craving component contributes to weight gain that further worsens mood.
Davidson's design: a double-blind pilot in 15 adults meeting DSM-IV criteria for atypical depression, randomized 2:1 to 600 mcg/day chromium picolinate or placebo for 8 weeks. Primary outcome was the Hamilton Depression Rating Scale; secondary outcomes included specific atypical depression symptoms and a measure of carbohydrate craving.
The published abstract reports that 7 people on chromium (70%) and none on placebo met responder criteria (p=.02), that other outcomes were consistent with a greater effect of chromium, that three on chromium did not improve, and that chromium was well tolerated. It does not report the items below, which this page earlier listed as results; the full paper could not be read to check them:
- Hamilton Depression Rating Scale: significant improvement in chromium group vs placebo
- Carbohydrate craving: significantly reduced in chromium group
- Increased appetite: significantly reduced in chromium group
- Leaden paralysis: improved in chromium group
- Modest weight reduction in chromium group (secondary to reduced caloric intake from craving suppression)
The Davidson 2003 trial was small, and its authors call it a pilot. They describe "promising antidepressant effects" and offer as possible mechanisms 5HT2A downregulation, increased insulin sensitivity, or other effects. It is cited for suggesting a broader role for chromium in the neuropsychiatric setting.
A larger exploratory replication trial (Docherty 2005, n=113 atypical depression) found no significant difference between chromium and placebo on its primary measures, in either the intent-to-treat or the evaluable population. Appetite increase, increased eating and carbohydrate craving improved more with chromium among the 75 evaluable patients. In a supplemental analysis of 41 patients with high carbohydrate craving, 65% on chromium and 33% on placebo responded on total depression score (p<0.05). The authors wrote that 600 micrograms may be beneficial for atypical depression with severe carbohydrate craving, and that further studies are needed.
Serotonergic and Noradrenergic Mechanism
The mechanism proposed for chromium's effects on appetite and mood, a hypothesis rather than a measured result, involves the serotonergic and noradrenergic neurotransmitter systems. Both serotonin and norepinephrine are appetite-regulating neurotransmitters, and both are functionally affected by insulin signaling in the brain.
- Serotonergic effects — serotonin is a major satiety neurotransmitter, and serotonergic dysfunction is associated with carbohydrate craving (the so-called "carbohydrate-craving serotonin hypothesis" originally proposed by Wurtman and Wurtman in the 1970s). Insulin signaling in the brain enhances tryptophan uptake into serotonergic neurons (insulin promotes amino acid uptake into other tissues, which competitively reduces large neutral amino acids in plasma except for tryptophan, which has its own transport mechanism — the net effect is increased tryptophan availability for serotonin synthesis). On this hypothesis, restored insulin signaling from chromium supplementation would enhance brain serotonin synthesis and serotonergic tone.
- Noradrenergic effects — norepinephrine in the hypothalamic paraventricular nucleus is appetite-suppressing (this is the mechanism of older anorectic drugs like phentermine, which is a norepinephrine-releasing agent). Chromium has been shown in animal studies to affect noradrenergic neurotransmission in the hypothalamus, though the mechanism is less well-characterized than the serotonergic mechanism.
- Dopaminergic effects — the rewarding aspect of palatable food consumption is mediated through mesolimbic dopaminergic signaling. There is preliminary evidence that chromium may modestly modulate dopaminergic function, potentially reducing food reward salience, though this is more speculative.
The integrated picture its supporters propose: chromium picolinate, by improving insulin signaling in the central nervous system, modulates multiple appetite-regulating neurotransmitter systems in directions that favor satiety and reduce food craving. This is proposed as mechanistically distinct from the appetite suppressant drugs (phentermine, lorcaserin, glucagon-like peptide-1 (GLP-1) agonists) but operationally similar in producing reduced caloric intake. Lorcaserin left the U.S. market in 2020 after the FDA asked for its withdrawal, because cancer was diagnosed in 7.7% of those taking it and 7.1% of those on placebo in a safety trial.
What is not known: no human study on this page measured brain insulin signaling or brain serotonin after chromium. The only direct brain evidence read for this page comes from rats given chromium into the brain, in which food intake fell as the dose rose (Anton 2008).
The glucagon-like peptide-1 receptor agonists (semaglutide, liraglutide, tirzepatide) have substantially transformed the obesity pharmacology landscape since 2020 and produce far larger weight loss than chromium picolinate. Chromium's place is now narrower than it was before the glucagon-like peptide-1 era: supporters describe it as a low-cost add-on for people with mild-moderate weight challenges and carbohydrate craving who are not on glucagon-like peptide-1 therapy, or as a complementary option for people already taking these drugs.
Fat Mass vs Lean Mass Composition
An important sub-question for any weight-loss intervention is whether the weight lost is primarily fat or primarily lean tissue. Lean tissue loss is metabolically and functionally undesirable — it reduces resting metabolic rate, predisposes to weight regain, and (in older adults) accelerates sarcopenia.
The body-composition trials of chromium picolinate do not agree. The Kaats trials are reported as showing preferential fat-mass loss with lean mass preservation or modest increase, while Volpe 2001, Lukaski 1996 and Trent 1995 found no significant effect on body composition. The proposed mechanism is the insulin sensitization itself: improved insulin signaling enhances amino acid uptake into skeletal muscle (insulin is an anabolic hormone, and muscle protein synthesis is partly insulin-dependent), which preserves muscle during caloric restriction. The same insulin sensitization in adipose tissue restores normal lipolysis suppression in the fed state and may enhance lipolysis in the fasted state.
Supporters describe the net body-composition effect as favorable even when total weight change is modest: chromium-supplemented subjects losing proportionally more fat and less muscle than placebo-supplemented subjects. The Cochrane review found "no firm evidence" across doses on body fat percentage.
This has practical implications for older adults attempting weight loss. Loss of muscle mass during caloric restriction is a major concern in patients over 65, and any intervention that preserves muscle during weight loss is valuable for long-term function. Supporters describe chromium picolinate as an add-on in this setting, alongside adequate protein intake (1.0–1.2 g/kg/day is the figure given for older adults attempting weight loss) and resistance training.
Exercise Synergy and Resistance Training
Resistance training is the most reliable intervention for preserving and building lean mass, and aerobic training is the most reliable intervention for caloric expenditure and improved insulin sensitivity. Chromium picolinate has been studied as an adjunct to both modalities, with mixed results.
- Resistance training — Lukaski 1996 (covered in detail in the Insulin Sensitivity deep-dive) is the classic citation. In this trial of 36 men over 8 weeks, strength and muscle mass rose with training independently of chromium, and the authors concluded that routine chromium supplementation "has no beneficial effects on body-composition change or strength gain in men." Transferrin saturation, a measure of iron status, fell more with chromium picolinate (24%) than with chromium chloride or placebo (10-13%). Several subsequent trials have produced mixed results; supporters suggest chromium picolinate may enhance the body-composition benefits of resistance training in untrained or moderately trained individuals but adds little in already highly trained athletes (whose insulin signaling is presumably already well-optimized through training adaptation).
- Aerobic training — the evidence here is sparser. Aerobic training itself improves insulin sensitivity substantially, and chromium's additive benefit is small. The Volpe 2001 trial (weight training and walking) found no significant change in body composition from chromium during a combined exercise program.
- Athletes and trace element status — intense endurance training increases urinary chromium loss, raising the theoretical possibility that elite endurance athletes might develop chromium-marginal status with associated impaired glucose handling during prolonged exercise. The practical impact appears modest in well-nourished athletes. Lukaski and colleagues left open whether supplementing people with diminished chromium status helps, writing that this "remains to be determined."
Supporters describe chromium picolinate as a small add-on to a structured exercise and diet program for weight management. It does not substitute for exercise; the exercise effect is described as several-fold larger.
Supplement Quality and Reformulation Cautions
Chromium picolinate is sold in the United States as a dietary supplement under DSHEA (the Dietary Supplement Health and Education Act of 1994), which means it is not subject to the same pre-market regulatory review as prescription pharmaceuticals. Product quality and label accuracy vary considerably across manufacturers.
- Form authentication — authentic chromium picolinate is a specific 1:3 chromium-to-picolinate stoichiometry. Cheap or counterfeit products may contain chromium chloride or other inexpensive chromium forms with picolinate added separately, providing different bioavailability than legitimate chromium picolinate. Independent lab testing programs provide some assurance of label accuracy.
- Dose accuracy — products are sometimes overdosed or underdosed relative to label claims. Independent lab verification is intended to reduce this risk.
- Excipients and binders — chromium picolinate tablets often include binders, fillers, and disintegrants that vary in quality. Minimally formulated products exist for people with sensitivities.
- Hexavalent chromium contamination — trivalent chromium (Cr3+) is the supplement form and is nutritionally safe. Hexavalent chromium (Cr6+) is an industrial toxicant and known carcinogen. Supplement makers describe their chromium ingredient as pure trivalent; contamination with hexavalent chromium is a theoretical risk in poorly sourced products, and independent lab testing is one way it is checked.
- Storage — chromium picolinate is stable at room temperature in a sealed container. Heat and humidity accelerate degradation. Refrigeration is unnecessary.
- Combination products — many weight-loss supplements combine chromium picolinate with stimulants (caffeine, synephrine), thyroid extracts, or other actives. These combinations multiply both potential benefits and potential adverse effects. Each component of a combination product carries its own effects and cautions.
The 2006 case of acute renal failure associated with a chromium picolinate-containing supplement (reported by Wani and colleagues in Annals of Pharmacotherapy) involved a 24-year-old man with a single right kidney who had taken a multi-ingredient workout supplement for 2 weeks; its main ingredients were chromium picolinate, Sida cordifolia, synephrine and guarana. He needed hemodialysis and recovered, and the authors rated the link as probable. The abstract gives no dose. The case prompted some regulatory attention but did not result in any restriction on chromium picolinate sales in the U.S. Doses of 200–1,000 mcg/day from quality-controlled products are described as appearing safe long-term in monitored populations.
The trial record on side effects is thin. Onakpoya 2013 listed watery stools, vertigo, headaches and hives. The Cochrane review found that only three of its nine trials reported adverse events; it counted two serious adverse events at 1,000 micrograms and one at 400 micrograms, and one serious event among placebo participants.
Realistic Expectations and Clinical Place
Realistic expectations for chromium picolinate as part of a weight-management strategy:
- Magnitude of weight loss — modest. The Onakpoya 2013 meta-analysis pooled effect was approximately 0.5 kg over 8–24 weeks. The Cochrane figure was 1.1 kg at 12 to 16 weeks. Supporters describe individual responders seeing 2–5 kg of fat loss and non-responders no change; no trial on this page reports that figure. This is substantially smaller than effects achievable with glucagon-like peptide-1 agonists (10–15% of body weight), bariatric surgery (25–35% of body weight), or sustained caloric restriction with exercise (5–10% of body weight).
- Time course — the trials ran for 8–24 weeks of consistent supplementation, and no trial on this page reports weight loss within days. Supporters use 12 weeks as an evaluation period.
- Best-responder phenotype — supporters name insulin-resistant adults with carbohydrate craving and snacking patterns, and people with metabolic syndrome, polycystic ovary syndrome (PCOS), or established type 2 diabetes, as more likely to respond than otherwise-healthy adults seeking cosmetic weight loss. In type 2 diabetes specifically, a 2024 meta-analysis of 14 trials found no significant effect on body weight (−0.26 kg, 95% confidence interval −0.69 to 0.16), body mass index, waist or fat mass overall; a subgroup analysis showed lower fat mass at age 55 and over and with the picolinate form.
- Combination with other interventions — chromium picolinate is described as an adjunct to a structured diet and exercise program, not a substitute for them. The Volpe 2001 trial paired it with a supervised exercise program.
- Dose — 200–400 mcg/day chromium picolinate is the dose range used in most weight-management trials. Going higher (up to 1,000 mcg/day, the dose used in the Anderson Beijing diabetes trial) is described as possibly producing slightly larger effects with diminishing returns and small theoretical safety concerns at the upper end; the Cochrane review found no dose pattern.
- Cost — chromium picolinate is among the cheapest weight-management supplements, typically $5–15 per month for a quality-verified product.
- Stopping criteria — supporters consider that if no measurable benefit (weight change, body composition change, reduced carbohydrate craving) appears after 12–16 weeks of consistent dosing within a weight-management program, chromium picolinate is unlikely to help that individual.
For people with severe obesity (body mass index (BMI) > 35) or weight-related medical complications, the interventions with larger measured effects are supervised lifestyle programs, glucagon-like peptide-1 agonists and bariatric surgery. For people with mild-moderate weight challenges in the context of insulin resistance and carbohydrate cravings, supporters describe chromium picolinate as a low-cost, low-risk adjunct with modest expected benefit.
This content is provided for informational purposes only and does not constitute medical advice. Chromium may potentiate the effect of insulin and oral antidiabetic drugs, which can push blood sugar lower. A chromium picolinate-containing supplement has been linked to acute kidney failure in a case report, in a man with one kidney. The trials pooled by the Cochrane review excluded pregnant women, so they give no safety information for pregnancy.
Key Research Papers
- Kaats GR, Blum K, Fisher JA, Adelman JA (1996). Effects of chromium picolinate supplementation on body composition: a randomized, double-masked, placebo-controlled study. Current Therapeutic Research 57(10):747-756. — doi:10.1016/s0011-393x(96)80080-4
- Kaats GR, Blum K, Pullin D, Keith SC, Wood R (1998). A randomized, double-masked, placebo-controlled study of the effects of chromium picolinate supplementation on body composition: a replication and extension of a previous study. Current Therapeutic Research 59(6):379-388. — doi:10.1016/s0011-393x(98)85040-6
- Volpe SL, Huang HW, Larpadisorn K, Lesser II (2001). Effect of chromium supplementation and exercise on body composition, resting metabolic rate and selected biochemical parameters in moderately obese women following an exercise program. Journal of the American College of Nutrition 20(4):293-306. — PubMed PMID: 11506057
- Davidson JR, Abraham K, Connor KM, McLeod MN (2003). Effectiveness of chromium in atypical depression: a placebo-controlled trial. Biological Psychiatry 53(3):261-264. — PubMed PMID: 12559660
- Docherty JP, Sack DA, Roffman M, Finch M, Komorowski JR (2005). A double-blind, placebo-controlled, exploratory trial of chromium picolinate in atypical depression: effect on carbohydrate craving. Journal of Psychiatric Practice 11(5):302-314. — PubMed PMID: 16184071
- Onakpoya I, Posadzki P, Ernst E (2013). Chromium supplementation in overweight and obesity: a systematic review and meta-analysis of randomized clinical trials. Obesity Reviews 14(6):496-507. — PubMed PMID: 23495911
- Tian H, Guo X, Wang X, et al. (2013). Chromium picolinate supplementation for overweight or obese adults. Cochrane Database of Systematic Reviews (11):CD010063. — PubMed PMID: 24293292
- Anton SD, Morrison CD, Cefalu WT, et al. (2008). Effects of chromium picolinate on food intake and satiety. Diabetes Technology and Therapeutics 10(5):405-412. — PubMed PMID: 18715218
- Lukaski HC, Bolonchuk WW, Siders WA, Milne DB (1996). Chromium supplementation and resistance training: effects on body composition, strength, and trace element status of men. American Journal of Clinical Nutrition 63(6):954-965. — PubMed PMID: 8644693
- Wani S, Weskamp C, Marple J, Spry L (2006). Acute tubular necrosis associated with chromium picolinate-containing dietary supplement. Annals of Pharmacotherapy 40(3):563-566. — PubMed PMID: 16492795
- Wurtman RJ, Wurtman JJ (1995). Brain serotonin, carbohydrate-craving, obesity and depression. Obesity Research 3(Suppl 4):477S-480S. — PubMed PMID: 8697046
- Trent LK, Thieding-Cancel D (1995). Effects of chromium picolinate on body composition. Journal of Sports Medicine and Physical Fitness 35(4):273-280. — PubMed PMID: 8776075
- Vajdi M, Khajeh M, Safaei E, et al. (2024). Effects of chromium supplementation on body composition in patients with type 2 diabetes: a dose-response systematic review and meta-analysis of randomized controlled trials. Journal of Trace Elements in Medicine and Biology 81:127338. — PubMed PMID: 37952433
- Federal Trade Commission (1996). Analysis of proposed consent order to aid public comment: chromium picolinate dietary supplements. Federal Register 61(222), November 15, 1996. — govinfo.gov notice
- U.S. Food and Drug Administration (2020). FDA requests the withdrawal of the weight-loss drug lorcaserin from the market. Drug Safety Communication. — fda.gov communication
PubMed Topic Searches
Connections
- All Minerals
- Chromium Overview
- Chromium Benefits Hub
- Chromium for Blood Sugar
- Chromium for Insulin Sensitivity
- Chromium for Lipid Profile
- Obesity
- Metabolic Syndrome
- Insulin Resistance
- Polycystic Ovary Syndrome
- Depression
- Fasting
- Blood Sugar
- Berberine
- Cinnamon
- Magnesium
- Tryptophan
- Fasting Insulin
- Hemoglobin A1c
- Deficiency
- Toxicity
- History