Chromium for Blood Sugar Regulation
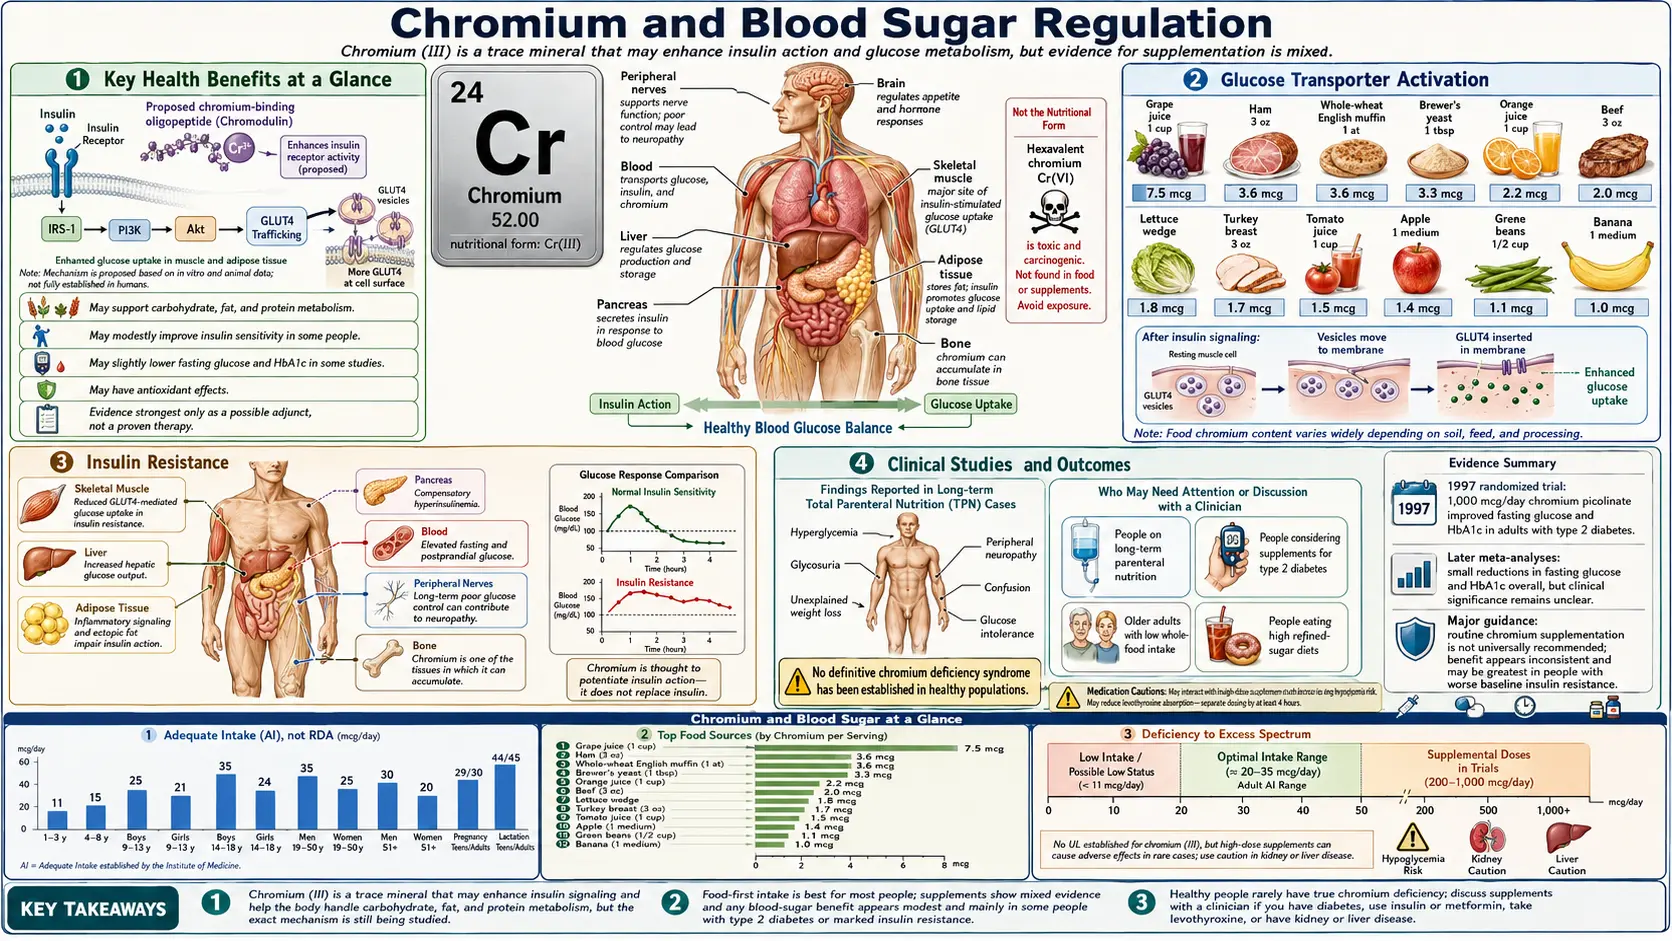
Chromium is a trace mineral long studied for a possible role in blood-sugar control; whether it is an essential nutrient is now disputed (Vincent, 2017, Journal of Nutrition). Its proposed mechanism of action involves the potentiation of insulin signaling at the cellular level through the oligopeptide chromodulin, which binds to activated insulin receptors and can amplify their tyrosine kinase activity by up to eight-fold in a test-tube study using membrane fragments from rat fat cells. Historic case reports of high blood sugar and glucose intolerance resolving with chromium repletion in patients on chromium-free total parenteral nutrition were long taken as evidence that chromium is an essential trace element for glucose homeostasis; that view is now disputed. The clinical evidence is heterogeneous: meta-analyses (Balk et al., 2007, Diabetes Care) report modest reductions in hemoglobin A1c (HbA1c) in patients with type 2 diabetes but no consistent effect in healthy or prediabetic populations. This deep-dive details molecular mechanisms at the insulin receptor, the chromodulin activation cycle, GLUT4 translocation enhancement, and the clinical evidence spanning type 2 diabetes, insulin resistance, metabolic syndrome, polycystic ovary syndrome (PCOS), and gestational diabetes.
Table of Contents
- Key Health Benefits at a Glance
- Insulin Receptor Potentiation
- Glucose Transporter Activation
- The Chromodulin Mechanism
- Type 2 Diabetes Evidence
- Insulin Resistance
- Metabolic Syndrome
- Clinical Studies and Outcomes
- Chromium’s Status as an Essential Nutrient Is Disputed
- Key Research Papers
- Connections
- Featured Videos
Key Health Benefits at a Glance
Before diving into the mechanism-level detail, the following is a high-level summary of the evidence-backed metabolic benefits of adequate chromium status. Each is explored in more depth below, and supporting studies are linked in the Research Papers section.
- Amplifies insulin receptor activity — Through chromodulin, chromium increased insulin receptor tyrosine kinase activity up to eight-fold in a test-tube study using membrane fragments from rat fat cells, lowering the insulin threshold required for downstream signaling.
- Enhances GLUT4 translocation — By strengthening PI3K/Akt signaling, chromium increases the number of GLUT4 glucose transporters that reach the plasma membrane of muscle and adipose cells in response to insulin.
- Modest hemoglobin A1c reduction in type 2 diabetes — The Balk 2007 Diabetes Care systematic review reported a mean hemoglobin A1c reduction of ~0.6 percentage points with chromium supplementation in patients with established type 2 diabetes, with no benefit in non-diabetic subjects.
- Dose-response evidence — Anderson's landmark 1997 trial in China (180 people with type 2 diabetes) found hemoglobin A1c lower than placebo after 4 months at both 200 mcg/day and 1,000 mcg/day of chromium picolinate (7.5% and 6.6%, against 8.5% on placebo); fasting glucose was lower only at 1,000 mcg/day, and fasting and 2-hour insulin fell significantly in both chromium groups.
- Parenteral nutrition case reports — Historic TPN case reports linked chromium deficiency to glucose intolerance that resolved upon repletion; the best-known 1977 report describes one patient whose glucose tolerance became normal after chromium was added to her infusion.
- FDA review — In a 2006 evidence-based review of chromium picolinate and the risk of type 2 diabetes, the US Food and Drug Administration allowed one qualified health claim, about the risk of insulin resistance, and concluded that “the relationship between chromium picolinate intake and insulin resistance is highly uncertain.”
- Reduced postprandial glucose excursions — Consistent with enhanced insulin-stimulated glucose uptake in peripheral tissues.
- Benefits in polycystic ovary syndrome and gestational diabetes — Small trials have reported improved insulin sensitivity in polycystic ovary syndrome and GDM populations, though larger confirmatory studies are needed.
- Generally safe at nutritional doses — Long-term trials at up to 1,000 mcg/day chromium picolinate have not identified adverse effects in monitored populations.
Insulin Receptor Potentiation
Chromium does not act as a hormone or direct glucose-lowering agent. Instead, it functions as a cofactor that enhances the ability of insulin to activate its receptor and initiate downstream signaling events. The insulin receptor is a transmembrane tyrosine kinase composed of two extracellular alpha subunits and two transmembrane beta subunits. When insulin binds to the alpha subunits, the beta subunits undergo autophosphorylation on specific tyrosine residues, initiating a cascade of intracellular events.
- Enhanced autophosphorylation: Chromium, through its incorporation into the oligopeptide chromodulin, amplifies the autophosphorylation activity of the insulin receptor beta subunit. This means that in the presence of adequate chromium, the receptor phosphorylates more tyrosine residues per insulin-binding event, generating a stronger intracellular signal.
- Prolonged receptor activation: Chromodulin binding to the activated insulin receptor appears to sustain the duration of receptor kinase activity, delaying receptor internalization and degradation. This extended signaling window allows for more complete execution of insulin's metabolic effects, including glucose uptake and glycogen synthesis.
- Insulin receptor substrate (IRS) phosphorylation: The amplified receptor kinase activity leads to increased phosphorylation of insulin receptor substrate proteins (IRS-1 and IRS-2), which serve as docking platforms for downstream signaling molecules. Enhanced IRS phosphorylation propagates a stronger signal through the PI3K/Akt pathway, the principal mediator of insulin's metabolic actions.
Glucose Transporter Activation
The ultimate physiological outcome of insulin signaling in peripheral tissues is the translocation of glucose transporter proteins to the cell surface, enabling glucose to enter the cell. Chromium's enhancement of this process is central to its role in blood sugar regulation.
- GLUT4 vesicle trafficking: In skeletal muscle and adipose tissue, insulin stimulates the movement of GLUT4-containing vesicles from intracellular storage compartments to the plasma membrane. This process requires activation of the PI3K/Akt signaling cascade and subsequent phosphorylation of AS160 (Akt substrate of 160 kDa), a Rab-GTPase-activating protein that controls vesicle fusion. By amplifying Akt activation, chromium increases the number of GLUT4 transporters that reach the cell surface in response to a given insulin stimulus.
- Increased glucose uptake capacity: With more GLUT4 transporters present on the cell membrane, the maximal rate of glucose uptake per cell is increased. This is particularly important in skeletal muscle, which is responsible for approximately 70 to 80 percent of insulin-stimulated glucose disposal in the postprandial state.
- GLUT4 gene expression: Some research suggests that chronic chromium supplementation may upregulate the expression of the GLUT4 gene (SLC2A4) itself, increasing the total cellular pool of GLUT4 protein available for translocation. This represents a longer-term adaptive mechanism through which chromium may improve glucose homeostasis.
- GLUT2 in hepatocytes: In the liver, glucose transport is primarily mediated by GLUT2, which operates independently of insulin-stimulated translocation. However, chromium's enhancement of hepatic insulin signaling affects the metabolic fate of glucose once it enters the hepatocyte, promoting glycogen synthesis over gluconeogenesis in the fed state.
The Chromodulin Mechanism
Chromodulin, also known as low-molecular-weight chromium-binding substance (LMWCr), is the key molecular mediator of chromium's biological activity in insulin signaling. Understanding chromodulin's mechanism of action is essential to understanding how chromium influences blood sugar regulation.
- Structure and composition: Chromodulin is an oligopeptide with a molecular weight of approximately 1,500 daltons. It consists of only four types of amino acid residues: glycine, cysteine, glutamate, and aspartate. The peptide binds four chromic (Cr3+) ions in a tetranuclear assembly, and all four chromium ions must be present for full biological activity.
- Activation cycle: In the basal (non-insulin-stimulated) state, chromodulin exists in the cytoplasm in its apo-form (without bound chromium). When insulin binds its receptor and triggers signaling, chromium is mobilized from the bloodstream via transferrin receptor-mediated endocytosis and released into the cytoplasm. The apo-chromodulin then binds the incoming chromium ions to form the active holo-chromodulin complex. This cycle is a proposed model: a 2017 review by the chemist whose laboratory reported the eight-fold result states that the proposed molecular mechanisms “have not been definitively shown to occur in animals.”
- Receptor interaction: Holo-chromodulin binds directly to the intracellular kinase domain of the insulin receptor beta subunit. A 1997 test-tube study using membrane fragments from rat fat cells and isolated rat insulin receptor found that chromodulin increased insulin-stimulated receptor tyrosine kinase activity by up to eight-fold, a substantial amplification of the insulin signal in that laboratory system (Davis and Vincent, 1997).
- Signal termination and chromium excretion: When insulin levels decline and the insulin receptor is deactivated, chromodulin is released from the receptor. The chromium ions are subsequently excreted in the urine, meaning that each cycle of insulin signaling consumes chromium that must be replenished through dietary intake. This urinary loss is one reason why chronically elevated insulin levels, as seen in insulin resistance, may increase chromium requirements.
Type 2 Diabetes Evidence
Type 2 diabetes mellitus is characterized by progressive insulin resistance and eventual beta-cell failure, leading to chronic hyperglycemia. Chromium supplementation has been extensively studied as an adjunctive intervention in this condition.
- Fasting blood glucose reductions: Multiple randomized controlled trials have demonstrated that chromium supplementation, typically at doses of 200 to 1,000 micrograms per day as chromium picolinate, can reduce fasting blood glucose levels in patients with type 2 diabetes. The magnitude of reduction varies across studies but is generally in the range of 15 to 30 mg/dL in individuals with elevated baseline values.
- Hemoglobin A1c (HbA1c) improvements: hemoglobin A1c reflects average blood glucose levels over the preceding two to three months and is a critical clinical marker for diabetes management. Meta-analyses of chromium supplementation trials have reported mean reductions in hemoglobin A1c of approximately 0.6 percentage points (Balk 2007) and 0.55 percentage points (Suksomboon 2014). Not every review agrees: a 2015 meta-analysis of 14 randomized trials (Yin and Phung) found that chromium picolinate, chromium yeast and brewer’s yeast “did not show statistically significant effects on A1C.”
- Postprandial glucose: Chromium supplementation has been shown to reduce postprandial (after-meal) glucose excursions, consistent with its mechanism of enhancing insulin-stimulated glucose uptake in peripheral tissues. Lower postprandial glucose peaks are associated with reduced glycemic variability and lower risk of diabetes complications.
- Dose-response relationship: A landmark study conducted in China by Anderson and colleagues demonstrated a dose-dependent response to chromium picolinate supplementation in subjects with type 2 diabetes. In this trial of 180 men and women, hemoglobin A1c was lower in both chromium groups than with placebo after 4 months (8.5% on placebo, 7.5% at 200 micrograms per day and 6.6% at 1,000 micrograms per day). Fasting glucose was lower only in the 1,000-microgram group, and fasting and 2-hour insulin fell significantly in both chromium groups.
- Limitations and variability: Not all clinical trials have shown significant benefits, and the overall evidence base is heterogeneous. Factors that influence the response to chromium supplementation include baseline chromium status, severity of insulin resistance, duration of supplementation, form and dose of chromium used, and concurrent diabetes management. Individuals with the most severe insulin resistance and poorest glycemic control tend to derive the greatest benefit. The Balk 2007 review included 41 trials, “almost half of which were of poor quality,” and noted that “larger effects were more commonly observed in poor-quality studies.” In the Yin and Phung 2015 meta-analysis, which analysed each form of chromium separately, only brewer’s yeast lowered fasting glucose (by 19.23 mg/dL), and no form changed A1C.
- NIH Office of Dietary Supplements review: A 2016 review by scientists at the US National Institutes of Health Office of Dietary Supplements examined 20 randomized controlled trials of chromium in type 2 diabetes. Few trials reached treatment goals: fasting glucose in 5 of 20, HbA1c in 3 of 14, and both in 1 of 14. HbA1c fell by 0.5% or more in 5 of 14 trials. The authors concluded that chromium supplements “have limited effectiveness” for blood-sugar control in type 2 diabetes.
Insulin Resistance
Insulin resistance is a condition in which target tissues (primarily skeletal muscle, liver, and adipose tissue) exhibit diminished responsiveness to insulin, requiring higher concentrations of the hormone to achieve normal glucose disposal. Chromium addresses insulin resistance at the receptor level.
- Restoring insulin sensitivity: By enhancing insulin receptor kinase activity through chromodulin, chromium effectively lowers the threshold of insulin needed to activate downstream signaling pathways. This restores a degree of insulin sensitivity in resistant tissues without altering insulin secretion from the pancreatic beta cells.
- Reducing compensatory hyperinsulinemia: In insulin-resistant individuals, the pancreas compensates by secreting increasingly large amounts of insulin to maintain normoglycemia. By improving tissue sensitivity to insulin, chromium can reduce the demand on beta cells, lowering circulating insulin levels. This is protective because chronic hyperinsulinemia contributes to further metabolic deterioration, including dyslipidemia and hypertension.
- Adipose tissue insulin signaling: Insulin resistance in adipose tissue leads to uncontrolled lipolysis, releasing excessive free fatty acids into the circulation. These free fatty acids exacerbate insulin resistance in muscle and liver through lipotoxicity. Chromium's improvement of insulin signaling in adipose tissue helps suppress inappropriate lipolysis and reduce circulating free fatty acid levels.
- Skeletal muscle glucose disposal: Since skeletal muscle accounts for the majority of insulin-stimulated glucose uptake, chromium's effects on muscle insulin signaling have the greatest quantitative impact on whole-body glucose disposal. Enhanced GLUT4 translocation in muscle tissue is the primary mechanism through which chromium improves postprandial glucose clearance.
- Hepatic insulin resistance: In the liver, insulin resistance manifests as a failure to suppress gluconeogenesis and glycogenolysis in the fed state, resulting in excessive hepatic glucose output. Chromium's enhancement of hepatic insulin signaling helps restore appropriate suppression of endogenous glucose production after meals.
Metabolic Syndrome
Metabolic syndrome is a cluster of interrelated metabolic abnormalities that significantly increase the risk of cardiovascular disease and type 2 diabetes. The International Diabetes Federation defines metabolic syndrome as the presence of central obesity plus any two of the following: elevated triglycerides, reduced high-density lipoprotein (HDL) cholesterol, elevated blood pressure, or elevated fasting blood glucose. Chromium's multifaceted metabolic effects make it relevant to several components of this syndrome.
- Central obesity and visceral fat: Visceral adipose tissue is more metabolically active and more resistant to insulin's antilipolytic effects than subcutaneous fat. Some studies have reported modest reductions in body fat, particularly central adiposity, with chromium supplementation, potentially mediated through improved insulin-regulated lipid metabolism.
- Dyslipidemia: The dyslipidemia of metabolic syndrome, characterized by elevated triglycerides and low high-density lipoprotein cholesterol, is driven in part by hepatic insulin resistance and excessive free fatty acid flux. Chromium supplementation has been associated with improvements in triglyceride and high-density lipoprotein cholesterol levels in individuals with metabolic syndrome features.
- Blood pressure: While chromium's effects on blood pressure are less consistently documented than its effects on glucose and lipid metabolism, improvements in insulin sensitivity may contribute to modest blood pressure reductions through enhanced endothelial nitric oxide production and reduced sympathetic nervous system activation.
- Inflammatory markers: Metabolic syndrome is associated with a state of chronic low-grade inflammation, reflected in elevated levels of C-reactive protein, interleukin-6, and tumor necrosis factor-alpha. Chromium supplementation has been shown to reduce several of these inflammatory biomarkers, suggesting an anti-inflammatory effect that may be secondary to improved metabolic regulation or may involve direct modulation of inflammatory signaling pathways.
Clinical Studies and Outcomes
The clinical evidence for chromium's role in blood sugar regulation spans several decades and includes both observational studies and randomized controlled trials conducted across diverse populations.
- Parenteral nutrition studies: Some of the earliest clinical evidence came from case reports of patients receiving long-term total parenteral nutrition (TPN) without chromium supplementation. The best-known report (Jeejeebhoy, 1977) describes one woman on long-term TPN who developed glucose intolerance, a 15% weight loss and nerve damage (peripheral neuropathy). Daily insulin added to her infusion nearly kept her blood sugar normal, but her glucose tolerance did not improve. After insulin was stopped and 250 micrograms of chromium a day was added to her infusion for 2 weeks, her glucose tolerance became normal; insulin was not needed over the next 5 months, and her nerve function returned to normal. These cases were long taken as evidence of chromium's essential role in glucose metabolism; that view is now disputed.
- Gestational diabetes: Preliminary studies have examined chromium supplementation in women with gestational diabetes mellitus (GDM). Some trials have reported improvements in fasting and postprandial glucose levels and reduced insulin requirements, though the evidence base remains limited and larger randomized trials are needed.
- Polycystic ovary syndrome (PCOS): polycystic ovary syndrome is frequently associated with insulin resistance, and chromium supplementation has been investigated as an intervention in affected women. Several small trials have reported improvements in insulin sensitivity, fasting glucose, and hormonal parameters with chromium picolinate supplementation in polycystic ovary syndrome patients.
- Corticosteroid-induced hyperglycemia: Corticosteroids are a common cause of iatrogenic hyperglycemia and insulin resistance. A limited number of studies have explored whether chromium supplementation can mitigate steroid-induced glucose dysregulation, with some positive preliminary findings.
- Combination with other nutrients: Research has examined chromium in combination with other nutrients that influence glucose metabolism, including alpha-lipoic acid, biotin, and cinnamon extract. Some combination studies have reported synergistic effects on glycemic control, though it can be difficult to isolate the contribution of chromium when multiple active agents are used simultaneously.
- Long-term safety data: Clinical trials of chromium supplementation lasting up to several years have not identified significant adverse effects at doses up to 1,000 micrograms per day of chromium picolinate. Kidney and liver function parameters have remained stable in monitored populations. However, a 1998 case report describes a 33-year-old woman who took 1,200 to 2,400 micrograms per day of chromium picolinate for 4 to 5 months to lose weight. She developed kidney failure needing dialysis, liver injury (liver enzymes 15 to 20 times normal), breakdown of red blood cells (hemolysis), anemia and low platelets; her liver function returned to normal before discharge, and one year later all her laboratory values were normal.
This content is provided for informational purposes only and does not constitute medical advice. Chromium may potentiate the glucose-lowering effect of insulin and oral antidiabetic drugs, which can push blood sugar too low.
Chromium’s Status as an Essential Nutrient Is Disputed
Nearly 60 years ago, chromium (as the trivalent ion) was proposed to be an essential element, and many papers still describe it that way — the 1997 Anderson trial and the 2014 Suksomboon meta-analysis both open by calling chromium an essential nutrient. In a 2017 review, John Vincent, the chemist whose laboratory reported the eight-fold chromodulin result in 1997, wrote that the results of new studies indicate that chromium “currently can only be considered pharmacologically active and not an essential element.”
- Animal and human effects: The same review states that chromium has been effective in certain rodent models, but that “beneficial effects in humans have not been unequivocally established.”
- Mechanism: It also states that molecular mechanisms have been proposed for the beneficial effects “but have not been definitively shown to occur in animals” — this applies to the chromodulin cycle described above.
- Marketing claims: The review notes that claims marketing chromium to reduce body mass and build muscle are no longer allowed in the United States, because they are not supported by experiments.
Key Research Papers
- Anderson RA (1998). Chromium, glucose intolerance and diabetes. Journal of the American College of Nutrition. 17(6):548-555. — DOI: 10.1080/07315724.1998.10718802. — doi:10.1080/07315724.1998.10718802
- Anderson RA, Cheng N, Bryden NA, et al. (1997). Elevated intakes of supplemental chromium improve glucose and insulin variables in individuals with type 2 diabetes. Diabetes. 46(11):1786-1791. — DOI: 10.2337/diab.46.11.1786. — PubMed PMID: 9356027
- Balk EM, Tatsioni A, Lichtenstein AH, Lau J, Pittas AG (2007). Effect of chromium supplementation on glucose metabolism and lipids: a systematic review of randomized controlled trials. Diabetes Care. 30(8):2154-2163. — DOI: 10.2337/dc06-0996. — doi:10.2337/dc06-0996
- Vincent JB (2000). The biochemistry of chromium. Journal of Nutrition. 130(4):715-718. — PubMed PMID: 10736319
- Yin RV, Phung OJ (2015). Effect of chromium supplementation on glycated hemoglobin and fasting plasma glucose in patients with diabetes mellitus. Nutrition Journal. 14:14. — PubMed PMID: 25971249
- Jeejeebhoy KN, Chu RC, Marliss EB, et al. (1977). Chromium deficiency, glucose intolerance, and neuropathy reversed by chromium supplementation, in a patient receiving long-term total parenteral nutrition. American Journal of Clinical Nutrition. 30(4):531-538. — PubMed PMID: 192066
- Mertz W (1993). Chromium in human nutrition: a review. Journal of Nutrition. 123(4):626-633. — PubMed PMID: 8463863
- Cefalu WT, Hu FB (2004). Role of chromium in human health and in diabetes. Diabetes Care. 27(11):2741-2751. — PubMed PMID: 15505017
- Suksomboon N, Poolsup N, Yuwanakorn A (2014). Systematic review and meta-analysis of the efficacy and safety of chromium supplementation in diabetes. Journal of Clinical Pharmacy and Therapeutics. 39(3):292-306. — PubMed PMID: 24635480
- Ngala RA, Awe MA, Nsiah P (2018). The effects of plasma chromium on lipid profile, glucose metabolism and cardiovascular risk in type 2 diabetes mellitus. PLoS ONE. — PubMed PMID: 29975702
- Lukaski HC, Bolonchuk WW, Siders WA, Milne DB (1996). Chromium supplementation and resistance training: effects on body composition, strength, and trace element status of men. American Journal of Clinical Nutrition. — PubMed PMID: 8644693
- Lamson DW, Plaza SM (2002). The safety and efficacy of high-dose chromium. Alternative Medicine Review. — PubMed PMID: 12126463
- Vincent JB (2017). New Evidence against Chromium as an Essential Trace Element. Journal of Nutrition. 147(12):2212-2219. — PubMed PMID: 29021369
- Davis CM, Vincent JB (1997). Chromium oligopeptide activates insulin receptor tyrosine kinase activity. Biochemistry. 36(15):4382-4385. — PubMed PMID: 9109644
- Trumbo PR, Ellwood KC (2006). Chromium picolinate intake and risk of type 2 diabetes: an evidence-based review by the United States Food and Drug Administration. Nutrition Reviews. 64(8):357-363. — PubMed PMID: 16958312
- Costello RB, Dwyer JT, Bailey RL (2016). Chromium supplements for glycemic control in type 2 diabetes: limited evidence of effectiveness. Nutrition Reviews. 74(7):455-468. — PubMed PMID: 27261273
- Cerulli J, Grabe DW, Gauthier I, Malone M, McGoldrick MD (1998). Chromium picolinate toxicity. Annals of Pharmacotherapy. 32(4):428-431. — PubMed PMID: 9562138
PubMed Topic Searches
Connections
- All Minerals
- Chromium Overview
- Chromium Benefits Hub
- Chromium for Insulin Sensitivity
- Chromium for Lipid Profile
- Chromium for Weight Management
- Insulin Resistance
- Diabetes
- Metabolic Syndrome
- Polycystic Ovary Syndrome
- Blood Sugar
- Insulin Resistance (Blood Sugar Benefits) — diet and lifestyle reversal of insulin resistance.
- Fasting
- Magnesium
- Zinc
- Hemoglobin A1C
- Fasting Insulin
- Cinnamon
- Gestational Diabetes
- Obesity
- Deficiency
- Toxicity
- History