Boron Toxicity: What the Evidence Shows
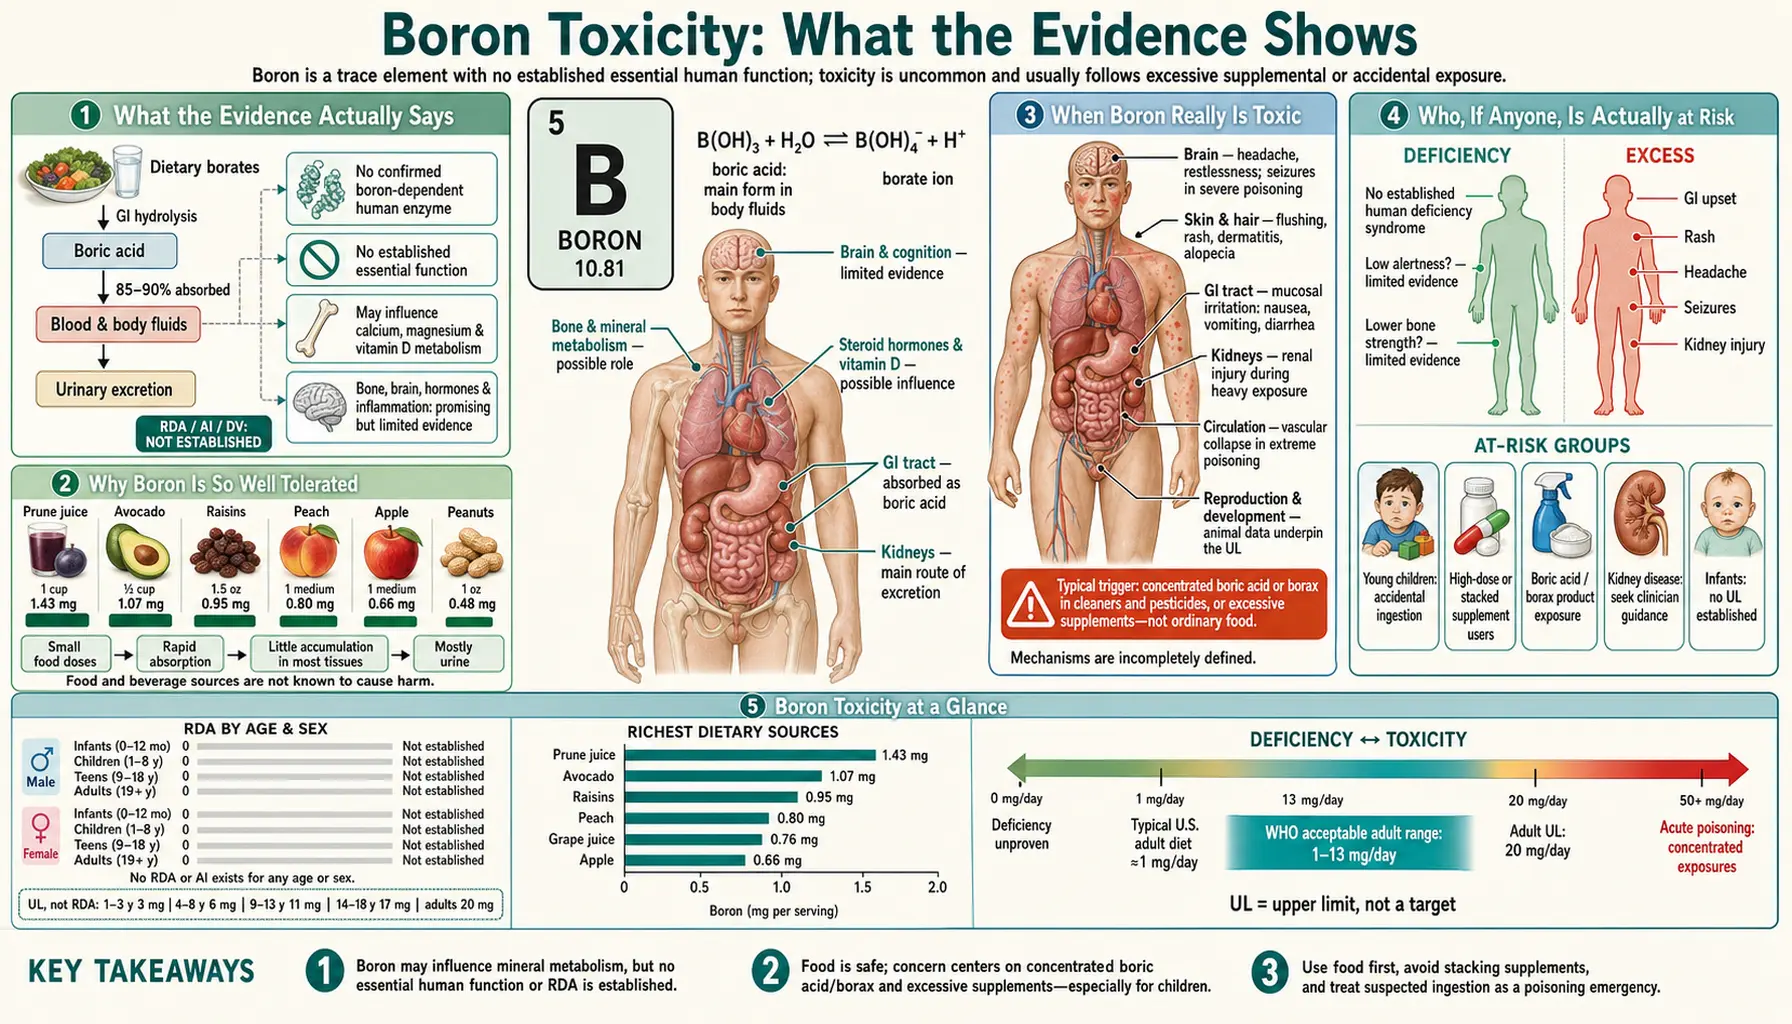
Here is the honest bottom line, stated up front: for ordinary people eating ordinary food, boron toxicity is not a real-world concern. Boron is a trace element you take in every day from fruit, vegetables, nuts, legumes, and drinking water — usually only 1 to 3 milligrams — and your kidneys clear it efficiently in the urine, so it does not pile up. There is no recognized "boron poisoning" from a normal diet, and no credible evidence that food-level boron harms healthy adults. Real toxicity exists, but it comes from a different world: large accidental or deliberate ingestions of boric acid or borax (most often a curious toddler swallowing a roach-killer powder, an old antiseptic, or a borax cleaning product), heavy industrial or occupational exposure, and very high-dose supplements taken well beyond the upper limits. Even then, the historical record is reassuring: the great majority of accidental boric-acid ingestions cause no symptoms or only mild, self-limited stomach upset, and serious harm is rare. This page is deliberately candid — it explains what the evidence actually shows, why boron is so well tolerated, who the genuinely at-risk people are, and the few simple safety points — rather than inventing a syndrome that does not exist. The real risks are concentrated boron products (boric acid, borax) within reach of children, and mega-doses of boron supplements — not food.
Table of Contents
What the Evidence Actually Says
It is worth being blunt, because the internet is not: there is no such thing as dietary boron toxicity in healthy people. Boron is a naturally occurring trace element present in plants and water, and a normal mixed diet supplies only about 1 to 3 milligrams of boron per day — mostly from fruit (apples, pears, grapes, raisins, prunes), leafy and other vegetables, nuts, legumes, coffee, and wine. At these everyday amounts boron is harmless, and decades of nutrition research have never identified a clinical poisoning caused by eating boron-rich food. If you are worried that eating a lot of fruit and nuts could give you "too much boron," you can set that worry down. It does not happen.
So what is true? Three things, and it helps to keep them separate from each other:
- Acute toxicity is possible only from large doses of concentrated boron compounds. The substances that cause real poisoning are not foods — they are boric acid and borax (sodium borate), the industrial and household chemicals used in some pesticides, roach and ant killers, older antiseptics and eyewashes, certain cleaning and laundry products, and slime-making kits. Toxicity requires swallowing a meaningful quantity of one of these, not eating boron-containing food.
- Even most accidental ingestions turn out fine. This is the genuinely reassuring part. The largest clinical series ever published — 784 boric acid ingestions reviewed at two regional poison centers — found that 88.3% of people had no symptoms at all, and that the most common symptoms were vomiting, abdominal pain, and diarrhea. None of the 784 developed severe toxicity.
- Fatal poisoning is rare and takes an extreme dose. Deaths from boric acid have occurred, but historically they involved very large ingestions (often grams to tens of grams), or repeated heavy exposure, or a vulnerable patient. The cases that reach the medical literature precisely because they are unusual — a fatal adult ingestion, a dramatic "boiled-lobster" red rash — are the exception, not the rule.
An old, misleading reputation hangs over boric acid because of poisonings that happened a century ago, when it was used freely as a food preservative and a wound antiseptic, sometimes applied to large raw surfaces or to infants. Modern regulation removed it from those uses, and acute boron poisoning became uncommon. The lesson historians of toxicology draw is not that boron is especially dangerous — it is that dose and route are everything, and that the dangerous scenarios are specific and avoidable.
Why Boron Is So Well Tolerated
Why does the body handle dietary boron so gracefully? The simplest answer is that boron does not accumulate. Unlike the heavy metals that build up in tissue over years — lead in bone, mercury in the brain, cadmium in the kidney — boron behaves more like a guest that never unpacks. Picture a sink with the drain wide open: pour water in at a reasonable rate and the level never rises, because it leaves as fast as it arrives. That is essentially how the body treats boron from food.
The biology behind that analogy is well described. Boron taken in by mouth is almost completely absorbed from the gut — typically more than 90% — which sounds alarming until you learn the other half of the story: it is then excreted rapidly and almost entirely by the kidneys in the urine, with a half-life in the body of only about a day. Because the kidneys keep clearing it, blood levels from a normal diet stay low and stable. The body does not have a large boron "store" the way it stores iron or copper; whatever you eat today is largely gone tomorrow. This efficient in-and-out handling is the central reason ordinary intake is harmless and why deliberately overloading the system is what it takes to cause harm.
That same property explains the shape of real toxicity. To overwhelm a system with an open drain, you have to pour in far more than it can carry — a single huge dose (a child swallowing a jar of roach powder), or a steady heavy load that keeps the input high day after day (occupational dust, or chronic mega-dosing). When that happens, the excess that the kidneys cannot keep up with begins to irritate the gut, the skin, and eventually other systems. But the threshold is genuinely high relative to dietary intake. Authoritative bodies have set a Tolerable Upper Intake Level (UL) for adults of about 20 mg of boron per day — and even that ceiling is built on animal reproductive studies with large safety margins, not on harm seen in people eating food. Twenty milligrams is something like ten times a typical daily dietary intake, which tells you how much headroom ordinary eating leaves.
One more honest qualifier: "well tolerated" is a statement about the general, healthy population. The one organ that makes the whole system work — the kidney — is also the weak point. If the kidneys are not clearing boron normally, the open drain starts to close, and the math changes. That is the thread running through the genuinely at-risk groups described below.
When Boron Really Is Toxic
To be candid rather than alarmist, it is worth describing exactly what real boron toxicity looks like — because the point of naming it is to recognize the few situations that matter, not to fear food. Genuine toxicity comes from concentrated boron compounds in non-food amounts, and it shows up in a handful of recognizable patterns.
- Acute ingestion of boric acid or borax. This is the classic poisoning. The early and most common effects are gastrointestinal — nausea, vomiting (sometimes blue-green), diarrhea, and abdominal pain. With larger doses, the picture can broaden to headache, restlessness, and, in serious cases, kidney injury (the very organ the body relies on to clear boron) and effects on the nervous system. As noted, most such ingestions — especially the small amounts a toddler typically manages to swallow — cause little or nothing, but the dose-dependent progression is why any significant ingestion deserves a call to Poison Control.
- The "boiled-lobster" rash. A striking and well-documented sign of significant acute boric acid toxicity is a diffuse, bright-red, sunburn-like flush of the skin that can later peel — described in the medical literature as a "boiled lobster" appearance. It is uncommon, but it is one of the few findings fairly specific to boron and a signal that the exposure was substantial.
- Hair loss (toxic alopecia) from chronic exposure. Repeated or sustained over-exposure to boron — historically from chronic ingestion of boric-acid-containing products — has caused reversible hair loss. This is a chronic-overdose phenomenon, not something dietary boron does, and it generally recovers once the source is removed.
- Massive or fatal overdose. Deaths are rare and require extreme doses, but they have occurred — for example, a documented fatal adult ingestion of boric acid. These tragic cases are the reason concentrated boron products carry warnings, and the reason storage away from children, and out of reach of anyone who might ingest them deliberately, matters.
A useful mental frame: the symptoms above are real, but they sit at the far end of a dose spectrum whose near end — everyday food — is completely benign. The danger belongs to boric acid and borax; it is not a reason to second-guess a handful of raisins.
Who, If Anyone, Is Actually at Risk
For the vast majority of people the honest answer is: no one in your household is realistically at risk of boron toxicity from diet. The exposures that cause harm are specific, and they cluster in a short list of edge cases worth knowing precisely so you can ignore the rest of the worry.
- Young children — by far the biggest real-world group. Almost all reported boric-acid poisonings are accidental ingestions by toddlers and small children who find a roach-killer bait, a box of borax, an old bottle of boric-acid eyewash, or a slime kit. This is an access problem, not a nutrition problem, and it is almost entirely preventable by storage. It is the single most important practical risk on this page.
- People with reduced kidney function. Because the kidneys are the body's only meaningful route for clearing boron, anyone whose kidneys are impaired clears it more slowly, so a given exposure goes further. People with significant chronic kidney disease (see Kidney Disease) are the group for whom even modest supplemental boron is a concern.
- Workers with heavy occupational exposure. People who mine, refine, or handle borate compounds — and breathe borate dust — can take in far more boron than the diet ever delivers. The most carefully studied question here has been male fertility, because high-dose animal studies showed effects on the testes. A 2010 study of 192 men, including heavily exposed boron workers, found no significant correlations between blood or urine boron and adverse semen parameters; the authors note that the workers' exposures did not reach those that caused adverse effects in animal studies. Occupational settings nonetheless use exposure limits and dust controls as a sensible precaution.
- Deliberate or repeated mega-dosing. A person who chooses to take very high-dose boron supplements far above the upper limits, day after day, is creating a chronic-overload scenario the body did not evolve to handle. This is self-imposed (see the next section).
Notice what is not on this list: people who eat a lot of fruit, nuts, beans, or coffee; people who drink boron-containing water at normal levels; people taking a modest boron supplement at typical doses. None of those are recognized causes of boron toxicity.
Supplements and the Upper Limits
Boron supplements (often sold as boron citrate, glycinate, or aspartate, and marketed for bone, joint, and hormone support — see the Boron Benefits hub for what the evidence does and does not support) are the one route by which an otherwise sensible adult could plausibly take in too much boron. The numbers make the safety margin clear and easy to respect:
- Typical dietary intake: about 1–3 mg/day from food and water.
- Common supplement doses: usually 3–10 mg/day — below the US upper limit, and reaching the European one at the top of that range.
- Tolerable Upper Intake Level (UL) for adults: 20 mg/day from all sources combined in the United States (Institute of Medicine, 2001, based on reproductive and developmental effects in animal studies), and 10 mg/day in Europe (European Food Safety Authority, 2004) — the levels each body regards as unlikely to cause harm over time.
So the practical guidance is simple: a typical boron supplement of a few milligrams a day sits below both upper limits, and the trouble cases involve taking many times more "because more must be better." It is not. There is no demonstrated benefit to pushing boron toward or past the upper limit, and doing so removes the generous safety margin for no reason. As a useful comparison, even research using relatively high supplemental doses (around 10 mg/day) of boron for cardiovascular risk factors has been studied as a deliberately elevated intake — at the European upper limit and below the US one — not as an everyday recommendation.
The upper limits count all sources, so a multi-mineral that also contains boron adds to a boron supplement. In pregnancy and breastfeeding the limits are the same as for other adults: 20 mg/day in the United States at ages 19–50 (17 mg/day at 14–18) and 10 mg/day in Europe. Kidney disease changes the picture, because the kidneys are the body's main route for clearing boron and impaired kidneys clear it more slowly. Boron from food needs no such accounting — you cannot reach the upper limit by eating.
Boron Safety in Everyday Life
Because dietary boron toxicity is not a real clinical problem, the practical points here are few, and mostly about a few concentrated products rather than diet:
- Storage of concentrated boron products. This is the one that genuinely matters. Boric acid roach/ant powders and baits, borax laundry booster and cleaning products, boric-acid eyewash, and slime kits are safest stored high, closed, and out of reach of children and pets. The entire real-world risk of acute boron toxicity is here, and storage almost entirely solves it.
- The Poison Control number. In the United States, the Poison Help line is 1-800-222-1222 (free, 24/7). It takes calls about a child swallowing a boron-containing product — most ingestions are minor, and the line can tell whether anything needs to be done.
- Supplement doses. Most boron supplements supply a few milligrams a day; the upper limits, counting all sources, are 20 mg/day in the United States and 10 mg/day in Europe.
- Boron-rich foods are not a toxicity risk. Apples, pears, prunes, raisins, grapes, nuts, legumes, leafy greens, coffee, and wine are good sources of boron and contribute to its modest health benefits.
- Kidney disease. Impaired clearance is the main thing that shifts the safety math for supplemental boron, because the kidneys are the body's main route for removing it.
That really is the whole program. The reassuring truth — worth repeating because it runs against the alarming tone found online — is that boron is one of the better-tolerated minerals, and that protecting against its rare toxicity is mostly a matter of keeping a couple of cleaning and pest-control products where small children cannot reach them.
When to Seek Care / Red Flags
Because everyday boron is harmless, the red flags here are tied to ingestion of a concentrated boron product (boric acid or borax) or to heavy exposure — not to diet. Poison Control (1-800-222-1222 in the U.S.) and hospitals treat the following as urgent after such an exposure:
- A child has swallowed a boric-acid bait/powder, borax product, boric-acid eyewash, or slime kit — Poison Control takes the call even when the child seems fine, so the amount and next steps can be assessed.
- Repeated vomiting or diarrhea after ingesting a boron product, especially if the vomit looks blue-green.
- A bright-red, sunburn-like rash (the "boiled-lobster" appearance), particularly if it later starts to peel — a sign of significant acute toxicity.
- Drowsiness, agitation, confusion, or a seizure following a large ingestion — signs hospitals treat as an emergency.
- Reduced urination, or known kidney disease combined with a boron ingestion or heavy exposure — impaired clearance raises the stakes.
- Unexplained hair loss in someone with ongoing heavy or chronic boron exposure — a sign linked to ongoing heavy exposure.
For everyone else — the people simply eating a boron-containing diet or taking a supplement within the upper limits — there is nothing to watch for, because there is no toxicity to catch. Questions about an exposure are what Poison Control answers, usually quickly. For the other side of this mineral — the question of whether getting enough boron matters — see the Boron Deficiency hub.
Key Research Papers
- Litovitz TL, Klein-Schwartz W, Oderda GM, Schmitz BF (1988). Clinical manifestations of toxicity in a series of 784 boric acid ingestions. The American Journal of Emergency Medicine;6(3):209-213. — DOI: 10.1016/0735-6757(88)90001-0. — doi:10.1016/0735-6757(88)90001-0
- Nielsen FH (2014). Update on human health effects of boron. Journal of Trace Elements in Medicine and Biology;28(4):383-387. — PubMed PMID: 25063690
- Nielsen FH (1997). Boron in human and animal nutrition. Plant and Soil;193(1-2):199-208. — DOI: 10.1023/a:1004276311956. — doi:10.1023/a:1004276311956
- Hunt CD (2007). Dietary Boron: Evidence for Essentiality and Homeostatic Control in Humans and Animals. In Advances in Plant and Animal Boron Nutrition;251-267. — DOI: 10.1007/978-1-4020-5382-5_25. — doi:10.1007/978-1-4020-5382-5_25
- EFSA Scientific Panel on Dietetic Products, Nutrition and Allergies (2004). Opinion related to the Tolerable Upper Intake Level of Boron (Sodium Borate and Boric Acid). EFSA Journal;2(8):80. — DOI: 10.2903/j.efsa.2004.80. — doi:10.2903/j.efsa.2004.80
- Restuccio A, Mortensen ME, Kelley MT (1992). Fatal ingestion of boric acid in an adult. The American Journal of Emergency Medicine;10(6):545-547. — DOI: 10.1016/0735-6757(92)90180-6. — doi:10.1016/0735-6757(92)90180-6
- Teshima D, Morishita K, Ueda Y, et al. (1992). Clinical Management of Boric Acid Ingestion: Pharmacokinetic Assessment of Efficacy of Hemodialysis. Journal of Pharmacobio-Dynamics;15(6):287-294. — DOI: 10.1248/bpb1978.15.287. — doi:10.1248/bpb1978.15.287
- Lung D, Clancy C (2009). "Boiled lobster" rash of acute boric acid toxicity. Clinical Toxicology;47(5):432. — DOI: 10.1080/15563650902948859. — doi:10.1080/15563650902948859
- Stein KM, Odom RB, Justice GR, Martin GC (1973). Toxic Alopecia From Ingestion of Boric Acid. Archives of Dermatology;108(1):95-97. — DOI: 10.1001/archderm.1973.01620220057014. — doi:10.1001/archderm.1973.01620220057014
- Robbins WA, Xun L, Jia J, Kennedy N, Elashoff DA, Ping L (2010). Chronic boron exposure and human semen parameters. Reproductive Toxicology;29(2):184-190. — DOI: 10.1016/j.reprotox.2009.11.003. — doi:10.1016/j.reprotox.2009.11.003
- Donoiu I, Militaru C, Obleagă O, et al. (2018). Effects of boron-containing compounds on cardiovascular disease risk factors — A review. Journal of Trace Elements in Medicine and Biology;50:47-56. — DOI: 10.1016/j.jtemb.2018.06.003. — doi:10.1016/j.jtemb.2018.06.003
- Newnham RE (1994). Essentiality of boron for healthy bones and joints. Environmental Health Perspectives;102(Suppl 7):83-85. — DOI: 10.2307/3431968. — doi:10.2307/3431968
PubMed Topic Searches
- PubMed: Boric acid ingestion: toxicity and clinical outcomes
- PubMed: Boron tolerable upper intake level and safety in humans
- PubMed: Boron pharmacokinetics, absorption, and urinary excretion
- PubMed: Boron occupational exposure and reproductive effects
- PubMed: Boron supplementation and human health effects (reviews)