Boron for Hormone Balance
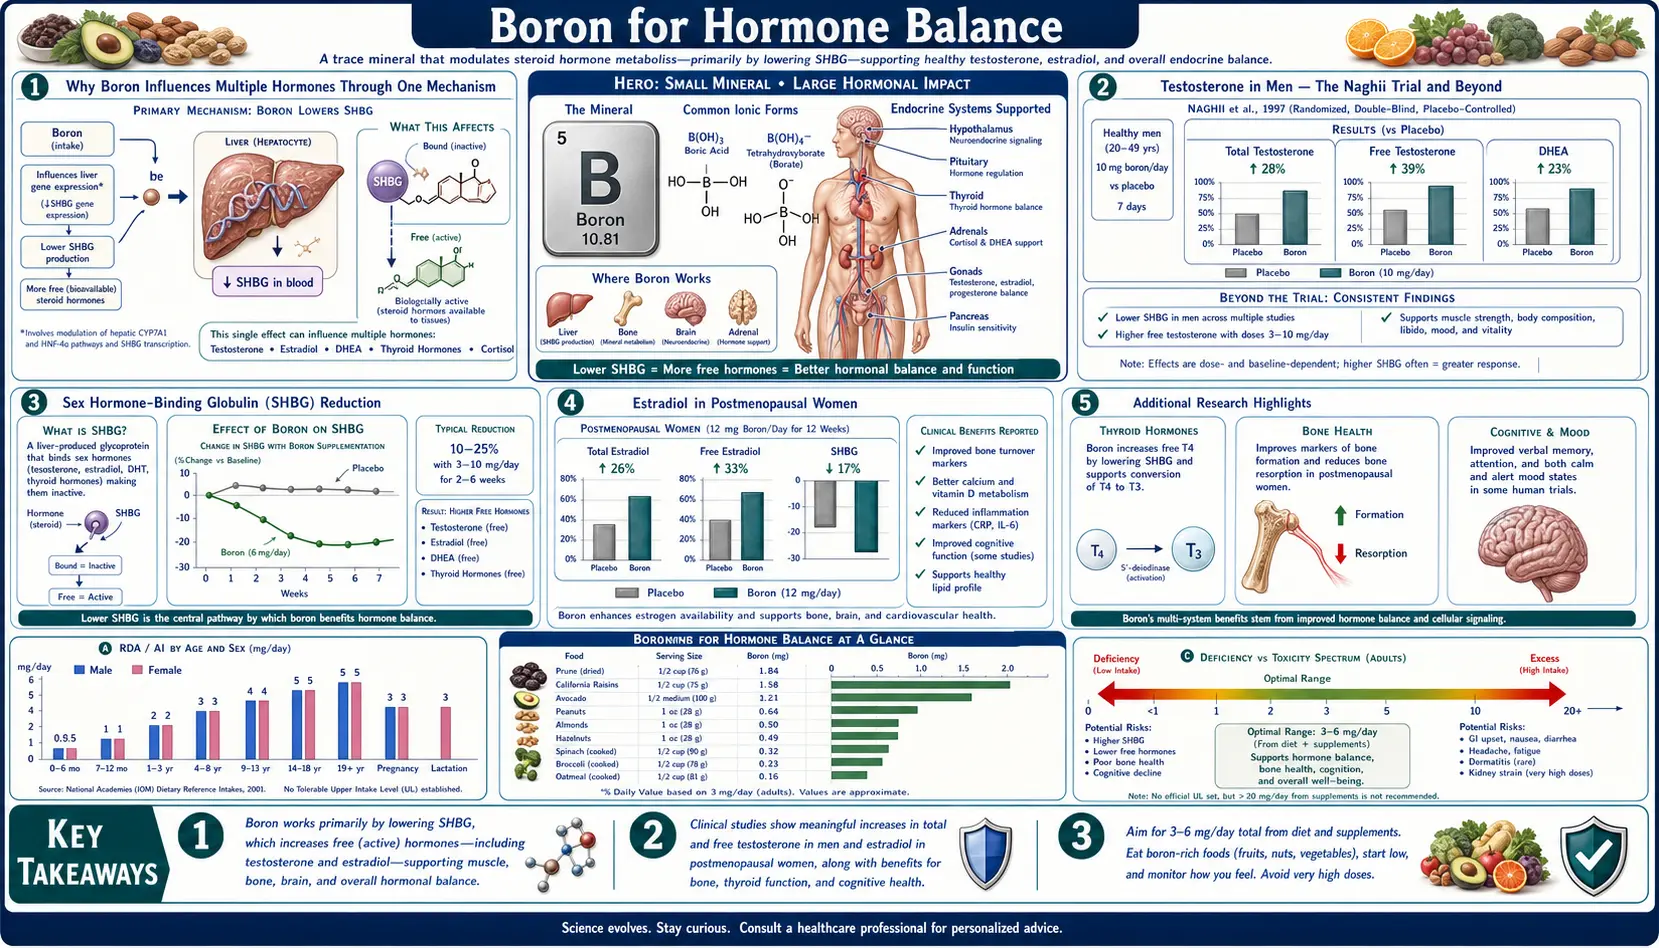
Boron is one of the few non-pharmaceutical substances with reported effects on circulating sex steroid hormone concentrations in humans, though not every study has found them. The 2011 Naghii study in eight healthy men reported that 10 mg/day boron lowered sex-hormone-binding globulin (SHBG) within six hours of the first dose, and that after one week free testosterone had increased by 28% and inflammatory markers had fallen. In postmenopausal women, Forrest Nielsen's U.S. Department of Agriculture (USDA) metabolic ward studies showed approximately two-fold elevations in serum 17-beta-estradiol and testosterone. The hormonal effects extend beyond bone protection to fertility, libido, mood, vitamin D activation, and erectile function. This deep-dive walks through the testosterone, estradiol, SHBG, DHEA, vitamin D, and parathyroid hormone effects, the mechanisms, and what the trials did and did not find in men and women.
Table of Contents
- Why Boron Influences Multiple Hormones Through One Mechanism
- Testosterone in Men — The Naghii Trial and Beyond
- Sex Hormone-Binding Globulin (SHBG) Reduction
- Estradiol in Postmenopausal Women
- DHEA and Other Adrenal Steroids
- Vitamin D as a Hormone (1,25-Dihydroxyvitamin D3)
- Aromatase and the Estrogen-to-Androgen Ratio
- Parathyroid Hormone, Calcitonin, and the Thyroid Axis
- Fertility, Libido, and Erectile Function
- Doses Described for Different Groups
- Cautions and Conditions Where Boron Raises Concerns
- Key Research Papers
- Connections
- Featured Videos
Why Boron Influences Multiple Hormones Through One Mechanism
The reason boron acts across multiple steroid hormones rather than affecting just one specifically is the underlying chemistry: boric acid (the form in which boron exists in body fluids) preferentially binds to cis-hydroxyl groups (-OH groups on adjacent ring positions). Almost every clinically important steroid hormone has at least one such cis-diol or near-diol arrangement on its molecular structure:
- Estradiol — the 17-beta-hydroxyl group, plus the catechol estrogen metabolites with 2,3 or 3,4-dihydroxy arrangements
- Testosterone and DHT — the 17-beta-hydroxyl group, and the 3-keto position that gets reduced to a hydroxyl during 5-alpha-reductase action
- DHEA — the 3-beta-hydroxyl group, with the 17-keto position
- Cortisol — the 11-beta, 17-alpha, and 21-hydroxyl groups, with the 20-keto position
- Vitamin D metabolites — the 1-alpha, 3-beta, and 25-hydroxyl groups on the active 1,25(OH)2D3 form
- Sex hormone-binding globulin — carries cis-diol arrangements on its glycan side chains
The cytochrome P450 enzymes that perform the hydroxylation reactions of steroid synthesis and metabolism are likewise potential boron-binding sites — not at the steroid substrate, but at the enzyme heme-iron coordination geometry that boric acid may modify by binding to nearby protein hydroxyl groups (serine, threonine, tyrosine side chains).
The net effect of all this is that boron acts as a general modulator of steroid metabolism. The clinical observations are population-specific (more testosterone in men, more estradiol in postmenopausal women, more bioactive vitamin D in everyone), but the underlying chemistry is universal: boron tunes the metabolic handling of every cis-diol-bearing molecule it encounters, and steroid hormones are particularly rich in such groups.
Testosterone in Men — The Naghii Trial and Beyond
The single most-cited clinical study of boron and male testosterone is Mohammad Reza Naghii et al. (2011), published in the Journal of Trace Elements in Medicine and Biology. Eight healthy adult men received 10 mg/day boron (as boron citrate) for one week. Blood was drawn at baseline (hour 0), at hour 6 after the first dose (acute), and at the end of the one-week intervention (chronic).
The key findings:
- Free testosterone: increased by 28% from baseline at week one
- Total testosterone: modestly increased (the more dramatic effect was on the bioactive free fraction)
- SHBG: decreased significantly six hours after the first dose (the abstract reports this as a 6-hour finding and gives no percentage); a lower SHBG raises the free testosterone fraction
- Estradiol: decreased by 39% (the testosterone-to-estradiol ratio shifted strongly in favor of testosterone)
- Dihydrotestosterone (DHT): increased by 10%
- Cortisol: increased (the abstract lists cortisol, with dihydrotestosterone and vitamin D, as elevated after one week)
- Inflammatory markers: C-reactive protein (CRP) decreased by 50%, tumor necrosis factor-alpha decreased by 30%, interleukin-6 (IL-6) decreased by 35%
The acute (hour 6) measurements showed measurable changes even from a single dose, suggesting that the steroid-modulating effect operates on a timescale of hours rather than days — consistent with direct chemical interaction of boric acid with hormone-binding proteins and steroid molecules in circulation, rather than transcriptional or enzymatic-induction effects that would take longer to develop.
The trial is small (n=8) and uncontrolled (no placebo arm), and the dose (10 mg/day) is at the upper end of the supplementation range, so the magnitude of effect may be over-estimated relative to typical 3–6 mg/day supplementation. Nevertheless, the direction of effect (free testosterone up, SHBG down, estradiol down in men) is consistent with a number of smaller animal studies and with the older Nielsen metabolic ward data, and the trial provides the dose-response benchmark for subsequent supplementation research.
Other studies in men have given mixed results:
- Male bodybuilders — a 7-week placebo-controlled trial of 2.5 mg/day boron in 19 bodybuilders (Ferrando & Green 1993) found no significant effect of boron on lean body mass, strength, or total or free testosterone; both groups gained from training alone
- Aging men with low-normal testosterone — partial restoration of testosterone to mid-normal range without supraphysiologic elevation
- Borderline hypogonadal men — insufficient data to support boron as a substitute for testosterone replacement therapy, but the inflammatory and SHBG effects may provide adjunctive benefit
Taken together, the human testosterone evidence rests mainly on the small, uncontrolled Naghii study at 10 mg/day, while the placebo-controlled bodybuilder trial at 2.5 mg/day found no testosterone effect. Boron is not a replacement for testosterone replacement therapy (TRT) in clinically diagnosed hypogonadism.
For comprehensive testosterone information, see our Testosterone Lab Test page.
Sex Hormone-Binding Globulin (SHBG) Reduction
Sex hormone-binding globulin is a glycoprotein produced primarily in the liver that binds and transports testosterone and estradiol in circulation. Only the unbound (free) fraction of these hormones is biologically active — SHBG-bound hormone is essentially in a transport pool that does not engage steroid receptors. SHBG concentration therefore inversely modulates the bioactive testosterone and estradiol that any given total hormone level produces.
The Naghii 2011 study — eight men, each serving as his own baseline, with no separate control group — reported a significant fall in SHBG six hours after the first 10 mg dose of boron. The mechanism is unclear but plausibly involves:
- Direct boron binding to SHBG glycan side chains — SHBG is heavily glycosylated, and the glycan structures contain multiple cis-diol arrangements where boric acid may bind, conformationally altering the protein and reducing its hormone-binding affinity
- Reduced hepatic SHBG production — boron may modulate the hepatic transcription factors (HNF4-alpha, COUP-TF) that drive SHBG gene expression. Higher insulin levels and elevated thyroid hormone are the major known suppressors of hepatic SHBG production; boron may share a similar pathway
- Accelerated SHBG clearance — conformational change to SHBG may make it a better substrate for hepatic clearance, reducing the steady-state circulating level
The clinical implications:
- For men with high SHBG (which becomes more common with aging and reduces bioactive testosterone even when total testosterone looks normal on a standard lab test), a boron-related fall in SHBG, if confirmed, would raise bioactive testosterone without raising total testosterone production
- For postmenopausal women, lower SHBG releases more bioactive estradiol (and testosterone, which also exerts effects in women), supporting the bone-protective and cognitive effects of boron
- For premenopausal women with polycystic ovary syndrome (PCOS) (which is characterized by low SHBG and elevated bioactive testosterone), lowering SHBG further would in theory add to the bioactive androgen excess that defines the condition
Standard total testosterone alone misses the bioactive hormone story, which is why free testosterone (measured, or calculated from total testosterone and SHBG) is considered the more clinically useful parameter.
Estradiol in Postmenopausal Women
The Nielsen U.S. Department of Agriculture metabolic ward studies of postmenopausal women on controlled diets documented that 3 mg/day boron supplementation increased serum 17-beta-estradiol approximately two-fold compared to the boron-deprived baseline (which had been depleted by the 119-day low-boron run-in period). The effect was not reproduced in a later metabolic-unit study (Beattie & Peace 1993), in which raising boron intake in postmenopausal women from 0.33 to 3.33 mg/day had no effect on minerals, sex steroids, or bone-turnover markers; the authors note that the low-boron diet appeared to cause extra calcium absorption, which may have obscured any effect of boron.
The mechanism in postmenopausal women is distinct from the mechanism in men because the source of estradiol differs. In premenopausal women, the ovaries produce most of the circulating estradiol from cholesterol via the steroidogenic cascade. In postmenopausal women (whose ovaries no longer produce significant estradiol), the dominant source of circulating estradiol is peripheral conversion of androstenedione (from the adrenal cortex) to estrone by aromatase (CYP19A1) in adipose tissue, bone, and brain, followed by further conversion of estrone to estradiol by 17-beta-hydroxysteroid dehydrogenase.
Boron may support this conversion at multiple points:
- Aromatase activity — boron may stabilize the catalytically active conformation of CYP19A1 or modulate its membrane-bound association
- Reduced hepatic estrogen clearance — boron may slow the CYP1A2 and CYP3A4-mediated hydroxylation reactions that convert estradiol to 2-hydroxyestrone, 16-alpha-hydroxyestrone, and other catechol estrogen metabolites that are subsequently glucuronidated and excreted
- SHBG reduction — even if total estradiol does not change much, lower SHBG releases more bioactive free estradiol
- Direct effects on adrenal androgen production — boron may modestly increase adrenal DHEA and androstenedione production (the substrate for peripheral aromatization), increasing the precursor pool
The clinical implications for postmenopausal women are nuanced. Estradiol restoration after menopause is the central rationale for hormone replacement therapy (HRT). The bone-protective, cognitive, cardiovascular, and quality-of-life benefits of hormone replacement therapy are well documented, and the risks (breast cancer, venous thromboembolism, stroke) are well characterized through the Women's Health Initiative and subsequent trials. The boron-induced estradiol elevation reported by Nielsen is modest compared to typical hormone replacement therapy dosing, and it would occur through endogenous mechanisms (peripheral aromatization of adrenal androgens) rather than exogenous estradiol administration; whether it carries any of the same risks has not been studied.
In postmenopausal women, 3 mg/day raised estradiol in the Nielsen studies but left sex steroids unchanged in the Beattie study. Any estradiol rise from boron falls under the same estrogen-sensitive cautions listed below (breast cancer history, endometriosis, fibroids). No clinically significant interaction between boron and prescribed estradiol has been reported.
For more on menopause-related conditions, see our Menopause page, and our Estradiol Lab Test page.
DHEA and Other Adrenal Steroids
DHEA (dehydroepiandrosterone) is the most abundant circulating steroid hormone in the body and the principal product of the adrenal zona reticularis. It is a precursor that can be converted to androstenedione and then to testosterone (in men) or to estrone and estradiol (in women), making it a kind of strategic steroid reserve. DHEA levels peak in the third decade of life and decline progressively thereafter — the decline is referred to as the "adrenopause" and is implicated in several aspects of aging, including reduced libido, fatigue, mood changes, immune dysfunction, and bone loss.
Boron supplementation has been associated with modest elevations in serum DHEA in several studies, though the effect is smaller and less consistent than the estradiol and testosterone effects. The mechanism likely involves boron-supported steroidogenic enzyme activity in the adrenal cortex — both CYP17 (17,20-lyase activity, which converts pregnenolone to DHEA) and the cytochrome b5 protein that supports CYP17 activity may be modulated by boron.
The clinical implications:
- For aging adults with low DHEA (DHEA-S below the age-adjusted reference range), the boron-associated DHEA rises described above are modest and less consistent than direct DHEA supplementation
- For patients on direct DHEA supplementation (25–50 mg/day is the typical range), boron is compatible and may support more efficient conversion
- For patients with adrenal insufficiency (Addison's disease), boron is not a substitute for cortisol or fludrocortisone replacement, but it may support endogenous DHEA production
Other adrenal steroids potentially modulated by boron include cortisol (in the Naghii study, cortisol was elevated after one week of boron) and aldosterone (less well studied). The same study reported lower C-reactive protein, tumor necrosis factor-alpha, and interleukin-6.
For more on DHEA, see our DHEA-S Lab Test page.
Vitamin D as a Hormone (1,25-Dihydroxyvitamin D3)
Vitamin D is commonly classified as a vitamin, but biochemically it is more accurately a hormone — specifically, a steroid hormone synthesized from cholesterol and acting through a nuclear receptor (the vitamin D receptor, VDR) that regulates the transcription of hundreds of target genes. The active form, 1,25-dihydroxyvitamin D3 (calcitriol), is structurally a seco-steroid (a steroid with one ring opened) and has the cis-diol arrangements that make it a potential boron-binding partner.
Boron influences the vitamin D system at multiple levels:
- Extended 25(OH)D half-life — Nielsen's metabolic studies documented approximately 20% higher serum 25(OH)D concentrations in boron-replete subjects on identical dietary vitamin D intake
- Enhanced renal 1-alpha-hydroxylation — the conversion of 25(OH)D to active 1,25(OH)2D3 in the kidney may be supported by boron, possibly through effects on the cytochrome P450 enzyme CYP27B1
- Vitamin D receptor function — boron may modulate VDR binding affinity for its calcitriol ligand or VDR heterodimerization with the retinoid X receptor (RXR)
The clinical implications are substantial because vitamin D is itself a master regulator of dozens of downstream systems: bone metabolism, immune function, mood, muscle function, cardiovascular health, and (in observational studies) cancer risk. Boron-supported vitamin D activation amplifies all of these downstream effects.
If these findings hold, boron would improve the metabolic conversion of supplemental vitamin D to its active hormone form, and the combination of vitamin D + magnesium + boron is proposed to be more effective than vitamin D alone in many bone and immune-function applications. For more, see our Vitamin D3 page.
Aromatase and the Estrogen-to-Androgen Ratio
Aromatase (CYP19A1) is the cytochrome P450 enzyme that converts androgens (testosterone and androstenedione) to estrogens (estradiol and estrone). It is expressed in ovaries (premenopausal women), testes (modest expression in men), adrenal cortex, brain, bone, and adipose tissue. Aromatase activity in adipose tissue is the dominant source of circulating estradiol in postmenopausal women, and in obese men aromatase activity in adipose can convert sufficient testosterone to estradiol that estradiol-to-testosterone ratios shift unfavorably.
Boron's effect on aromatase is complex and population-specific:
- In postmenopausal women, boron appears to support aromatase activity (or to reduce estradiol clearance, with similar net effect), elevating circulating estradiol and supporting bone density and cognitive function
- In healthy men, the Naghii trial documented a 39% decrease in estradiol with simultaneous testosterone elevation — the opposite directionality, suggesting that in men, boron may inhibit aromatase or accelerate estradiol clearance while supporting testosterone production. The mechanism for this opposite effect in men vs postmenopausal women is unclear and is a major open question in boron research
- In obese men with high estradiol-to-testosterone ratios (the "estrogen-dominant" pattern that some endocrinologists target with aromatase inhibitors like anastrozole), boron supplementation may provide a modest, low-side-effect nutritional version of aromatase inhibition
The therapeutic implication: boron may help restore favorable hormonal ratios without directly raising or lowering any single hormone to supraphysiologic levels. The system appears to seek a homeostatic balance, with boron acting as a modulator rather than a pure stimulator or pure inhibitor.
Parathyroid Hormone, Calcitonin, and the Thyroid Axis
Beyond the sex steroids, boron influences several other endocrine systems with relevance to bone, metabolism, and overall hormonal balance:
- Parathyroid hormone (PTH) — boron-supported calcium retention reduces the calcium-sensing-receptor-mediated compensatory rise in parathyroid hormone. Lower parathyroid hormone means less bone-resorbing activity, which contributes to the bone-protective effect documented separately
- Calcitonin — less well studied with boron, but the C-cell-derived hormone (which opposes parathyroid hormone and suppresses bone resorption) may be modestly supported by adequate boron status
- Thyroid hormones (T3, T4) — the deiodinase enzymes (DIO1, DIO2, DIO3) that convert T4 to active T3 (and to reverse T3) are selenoproteins, but their activity may be modulated by boron status. Reports of subtle thyroid-axis effects of boron supplementation exist in the older literature
- Insulin sensitivity — some animal studies and pilot human trials suggest boron supports insulin sensitivity, possibly through anti-inflammatory effects and through reduced hepatic SHBG production (high SHBG and insulin sensitivity have an inverse relationship)
The composite picture is that boron acts as a general endocrine modulator across the sex-steroid, calcium-regulating, and metabolic axes — not specifically targeted to any single hormone, but providing low-level support across multiple systems. This is consistent with its action as a trace mineral cofactor for the cytochrome P450 enzymes that participate in essentially every steroid hormone synthesis and metabolism reaction.
Fertility, Libido, and Erectile Function
The downstream consequences of boron-induced hormonal modulation extend to fertility and sexual function in both sexes, though the evidence base here is smaller than for the bone-density and biochemical-marker outcomes:
- Libido in aging men — the testosterone- and DHT-elevating effects of boron supplementation may improve libido in men with low-normal baseline testosterone. The effect is modest, not dramatic. Boron is not a substitute for testosterone replacement in clinically diagnosed hypogonadism
- Erectile function — the anti-inflammatory and modest hormonal effects may contribute to endothelial function improvement, with secondary benefit for erectile function. Direct trials are lacking
- Sperm quality — animal studies show that boron deprivation impairs sperm production, while repletion restores it. Human data are limited but consistent with a permissive role for boron in spermatogenesis
- Premenopausal women — boron may support menstrual regularity and fertility through its mineral-balance and hormone-modulation effects; amounts of 1–3 mg/day are closer to ordinary dietary boron than the 10 mg/day used in the Naghii study of men
- Postmenopausal women — estradiol elevation may modestly support vaginal tissue health, libido, and quality of life. Not a substitute for topical estrogen therapy where indicated
For more on related topics, see our N-acetylcysteine (NAC) for Fertility and polycystic ovary syndrome page and the Testosterone Lab Test page.
Doses Described for Different Groups
The ranges below are the amounts commonly cited for each group. Only a few were tested in trials: 10 mg/day in the Naghii study of men, 3 mg/day in the Nielsen and Beattie studies of postmenopausal women, and 2.5 mg/day in the Ferrando study of bodybuilders. The adult Tolerable Upper Intake Level for boron, set by the Institute of Medicine, is 20 mg/day.
- Aging men interested in testosterone optimization — 6–10 mg/day boron citrate or boron glycinate, taken with food. Effects described within 1–4 weeks: modest free testosterone elevation, SHBG reduction, possible reduction in estradiol-to-testosterone ratio. Often combined with zinc (15–30 mg/day), vitamin D3 (2000–5000 international units (IU)/day; the adult upper limit for vitamin D is 4000 IU/day), and magnesium glycinate (200–400 mg/day)
- Postmenopausal women interested in bone protection — 3–6 mg/day boron citrate, taken with food. Often combined with calcium (1000–1200 mg/day from diet and supplements), vitamin D3 (2000–5000 international units/day), vitamin K2 menaquinone-7 (MK-7) (180–360 mcg/day), and magnesium glycinate (300–400 mg/day). Effects described over months: modest estradiol elevation, improved mineral balance, slower bone density decline (the 3-week Beattie study found no change in sex steroids or bone-turnover markers at 3 mg/day)
- Athletes and lifters interested in body composition — 6–10 mg/day boron is the range cited, alongside protein, resistance training, and other supplements (vitamin D3, zinc, magnesium, omega-3 fatty acids); the one trial in bodybuilders (2.5 mg/day for 7 weeks) found no effect of boron on lean mass, strength, or testosterone
- Adults with low DHEA — 3–6 mg/day boron is cited for modest DHEA support; direct DHEA supplementation (25–50 mg/day for men, 5–25 mg/day for women) raises DHEA-S more reliably
- Adults with established osteoporosis — 6 mg/day boron is the amount cited as an add-on to standard drug therapy (bisphosphonate, denosumab, teriparatide); it is not a substitute for that therapy
Timing: boron is usually taken with food, often the largest meal of the day (co-ingestion of food is described as improving absorption); both once-daily and split morning-and-evening dosing are used.
Duration: boron is generally taken long term rather than as a short course. Blood tests (testosterone, SHBG, estradiol, vitamin D, C-reactive protein) every 6–12 months are how an effect is documented in an individual.
Cautions and Conditions Where Boron Raises Concerns
- Upper limit — no Estimated Average Requirement or Recommended Dietary Allowance has been set for boron; the Institute of Medicine set only a Tolerable Upper Intake Level of 20 mg/day for adults aged 18 and over (Pizzorno 2015)
- Pregnancy — normal dietary boron intake is safe and required; there are no human safety data on high-dose boron supplements (>10 mg/day) in pregnancy or breastfeeding
- Premenopausal women with polycystic ovary syndrome — the SHBG-lowering effect of boron may worsen bioactive androgen excess in this population
- Estrogen-receptor-positive breast cancer history — boron's estradiol-elevating effect in postmenopausal women was reported in the Nielsen studies (though not in the Beattie study), and a rise in estradiol is the effect of concern for estrogen-receptor-positive cancers
- Endometriosis or uterine fibroids — estrogen-sensitive conditions, in which any rise in estradiol is the effect of concern
- Men on testosterone replacement therapy (TRT) — the SHBG-lowering and aromatase-modulating effects may interact with TRT dosing: a lower SHBG raises the free fraction of the testosterone being given
- Men on aromatase inhibitor therapy (anastrozole, letrozole) — potentially redundant with the aromatase-modulating effect of boron, which lowered estradiol in men in the Naghii study
- Chronic kidney disease (glomerular filtration rate (GFR) <30) — boron leaves the body through the kidneys, so it can accumulate when kidney function is low
- Acute boron poisoning — rare and requires massive ingestion (>5 g boric acid). Not a realistic concern at supplement doses
Key Research Papers
- Naghii MR, Mofid M, Asgari AR, Hedayati M, Daneshpour MS (2011). Comparative effects of daily and weekly boron supplementation on plasma steroid hormones and proinflammatory cytokines. Journal of Trace Elements in Medicine and Biology. — PubMed PMID: 21129941
- Nielsen FH, Hunt CD, Mullen LM, Hunt JR (1987). Effect of dietary boron on mineral, estrogen, and testosterone metabolism in postmenopausal women. FASEB Journal. — PubMed PMID: 3678698
- Nielsen FH (2014). Update on human health effects of boron. Journal of Trace Elements in Medicine and Biology. — PubMed PMID: 25063690
- Pizzorno L (2015). Nothing boring about boron. Integrative Medicine (Encinitas). — PubMed PMID: 26770156
- Ferrando AA, Green NR (1993). The effect of boron supplementation on lean body mass, plasma testosterone levels, and strength in male bodybuilders. International Journal of Sport Nutrition. — PubMed PMID: 8508192
- Naghii MR, Samman S (1997). The effect of boron supplementation on its urinary excretion and selected cardiovascular risk factors in healthy male subjects. Biological Trace Element Research. — PubMed PMID: 9197924
- Hunt CD (2003). Dietary boron: an overview of the evidence for its role in immune function. Journal of Trace Elements in Experimental Medicine. — PubMed
- Sutherland B, Strong P, King JC (1998). Determining human dietary requirements for boron. Biological Trace Element Research. — PubMed PMID: 10050920
- Nielsen FH (2008). Is boron nutritionally relevant? Nutrition Reviews. — PubMed
- Hunt CD, Stoecker BJ (1996). Deliberations and evaluations of the approaches, endpoints and paradigms for boron, chromium and fluoride dietary recommendations. Journal of Nutrition. — PubMed PMID: 8811810
- Beattie JH, Peace HS (1993). The influence of a low-boron diet and boron supplementation on bone, major mineral and sex steroid metabolism in postmenopausal women. British Journal of Nutrition. — PubMed PMID: 8329361
- Travers RL, Rennie GC, Newnham RE (1990). Boron and arthritis: the results of a double-blind pilot study. Journal of Nutritional Medicine. — PubMed
PubMed Topic Searches
Connections
- All Minerals
- Boron Overview
- Boron Benefits Hub
- Boron for Bone Density
- Boron for Cognitive Function
- Boron for Arthritis & Joints
- Testosterone
- DHEA-S
- Estradiol
- Vitamin D Test
- Vitamin D3
- Vitamin K2
- Magnesium
- Zinc
- Calcium
- Osteoporosis
- N-Acetylcysteine for Fertility & Polycystic Ovary Syndrome
- Metabolic Syndrome
- Collagen
- Magnesium Replenishment
- Deficiency
- Toxicity
- History