Calcium for Bone Health
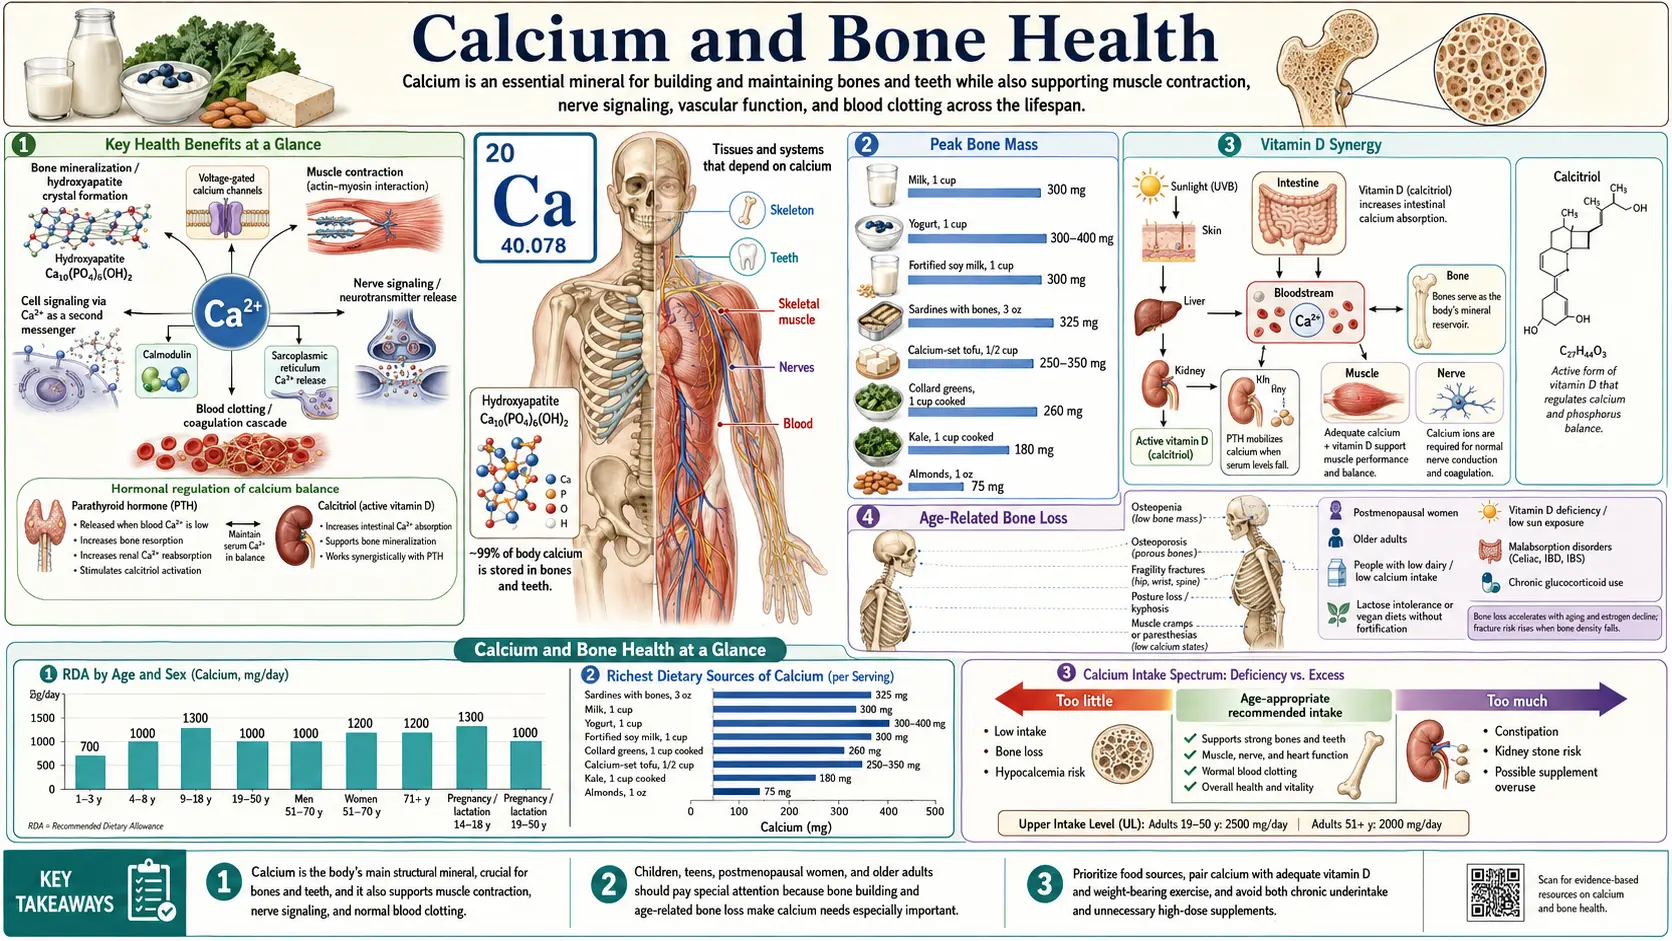
The skeleton is not a static structure but a dynamic, living tissue that undergoes continuous renewal throughout life. Bone serves as the body's primary calcium reservoir, containing about 99% of the body's calcium (Bonjour 2011), largely as hydroxyapatite crystals deposited within a collagen matrix. The relationship between calcium and bone health is fundamental: adequate calcium intake and absorption are prerequisites for building strong bones during growth, maintaining bone density during adulthood, and slowing bone loss during aging. However, later evidence complicates the older narrative that more calcium is always better: a meta-analysis of 59 trials found that more calcium from food or supplements raised bone mineral density by about 0.6–1.8%, with no further gain after the first year (Tai 2015), and a companion review judged the evidence that calcium supplements prevent fractures weak and inconsistent (Bolland 2015).
This page covers the remodeling cycle, the cellular biology of osteoblasts and osteoclasts, the accrual of peak bone mass, osteoporosis prevention, the inseparable partnership between calcium and vitamin D, the loading response to weight-bearing exercise, factors that enhance or inhibit absorption, and the biology of age-related bone loss.
Table of Contents
Key Health Benefits at a Glance
Before diving into the mechanism-level detail, the following summarizes what the research reports about calcium and bone. Each is explored in more depth below, and supporting studies are linked in the Research Papers section.
- Peak bone mass – The National Osteoporosis Foundation's 2016 position statement found its best evidence (grade A) for positive effects of calcium intake and physical activity on bone accrual, especially in late childhood and the peripubertal years (Weaver 2016, peak bone mass statement).
- Reference intakes set from bone health – The U.S. RDA for adults is 1,000 mg/day from 19 to 50; 1,000 mg/day for men and 1,200 mg/day for women aged 51 to 70; and 1,200 mg/day over 70 (Food and Nutrition Board, via the NIH Office of Dietary Supplements). The Institute of Medicine based these values on bone health (Ross 2011).
- Small, non-progressive bone-density gains – In the Tai 2015 meta-analysis of people over 50, gains were similar whether the extra calcium came from food or supplements, with or without vitamin D, at doses of 1,000 mg/day or more versus less, and whether baseline dietary intake was below or above 800 mg/day; the authors judged the gains unlikely to produce a clinically significant reduction in fractures.
- Fracture findings with vitamin D are mixed – A 2016 meta-analysis from the National Osteoporosis Foundation (Weaver et al., Osteoporos Int; eight trials, 30,970 participants) reported 15% fewer total fractures and 30% fewer hip fractures with calcium plus vitamin D. The 2014 Cochrane review found a small reduction in hip fracture (RR 0.84; Avenell 2014), while in the Women's Health Initiative (WHI) trial the hip-fracture hazard ratio was 0.88, not statistically significant (Jackson 2006). The U.S. Preventive Services Task Force (USPSTF) found in 2018 that daily supplementation with 400 IU or less of vitamin D and 1,000 mg or less of calcium has no benefit for the primary prevention of fractures in community-dwelling postmenopausal women (Grossman 2018).
- Calcium supplements alone: weak fracture evidence – Across 26 trials, calcium supplements were associated with fewer total fractures (RR 0.89), but in the four trials at lowest risk of bias there was no effect at any site; the authors concluded that the evidence that supplements prevent fractures is weak and inconsistent (Bolland 2015, BMJ).
- Depends on vitamin D – Active vitamin D (calcitriol) is the main hormonal driver of active intestinal calcium absorption.
- Responds to mechanical loading – Weight-bearing exercise stimulates osteocyte-driven Wnt/beta-catenin signaling that promotes bone formation.
- Supplements and the heart – A 2011 reanalysis of the WHI trial combined with other trials associated calcium supplements with a modest rise in myocardial infarction risk (Bolland 2011); later analyses point in both directions, and the debate is covered in the Cardiovascular Health deep-dive.
The Bone Remodeling Cycle
Bone remodeling is the lifelong process by which old or damaged bone is removed and replaced with new bone tissue. This process occurs at discrete sites called basic multicellular units (BMUs) and follows a tightly regulated sequence of phases.
- Activation – Mechanical stress, microdamage, or hormonal signals trigger the recruitment of osteoclast precursors to a specific site on the bone surface. Osteocytes, embedded within the mineralized matrix and making up 90% to 95% of all bone cells in adult bone (Bonewald 2011), act as mechanosensors and orchestrate this initiation by releasing signaling molecules including RANKL and sclerostin.
- Resorption – Mature osteoclasts attach to the bone surface, forming a sealed compartment called the resorption lacuna (Howship's lacuna). They secrete hydrochloric acid to dissolve the mineral phase and cathepsin K to degrade the collagen matrix. This process releases calcium, phosphate, and collagen fragments into the extracellular fluid. Resorption at a single site takes weeks.
- Reversal – After osteoclasts complete resorption and undergo apoptosis, reversal cells (likely of mononuclear/macrophage lineage) prepare the resorbed surface for new bone formation by depositing a thin layer of cement substance.
- Formation – Osteoblasts, derived from mesenchymal stem cells, migrate to the resorbed site and begin synthesizing new osteoid, the unmineralized organic matrix composed primarily of type I collagen. Over the following weeks, hydroxyapatite crystals are deposited within this matrix in a process called mineralization. Formation at a site takes considerably longer, on the order of months.
- Quiescence – Once formation is complete, some osteoblasts become embedded in the new bone as osteocytes, some flatten into bone-lining cells, and others undergo apoptosis. The remodeled site enters a resting phase until the next cycle is initiated.
Throughout adult life, these teams of osteoclasts and osteoblasts periodically replace old bone with new (Manolagas 2000). The balance between resorption and formation determines whether bone mass is maintained, gained, or lost.
Osteoblasts vs. Osteoclasts
The two principal effector cells of bone remodeling have opposing functions, and the balance between their activities determines net bone mass.
Osteoblasts: The Bone Builders
- Origin – Osteoblasts differentiate from mesenchymal stem cells in the bone marrow under the influence of transcription factors including Runx2 and osterix, as well as signaling pathways such as Wnt/beta-catenin.
- Function – They synthesize and secrete the organic components of bone matrix, predominantly type I collagen, along with non-collagenous proteins such as osteocalcin, osteopontin, and bone sialoprotein. They also produce alkaline phosphatase, which facilitates mineralization by increasing local phosphate concentrations.
- Regulation of osteoclasts – Osteoblasts express RANKL (receptor activator of nuclear factor kappa-B ligand) on their surface, which binds to RANK on osteoclast precursors and promotes osteoclast differentiation and activation. They also produce osteoprotegerin (OPG), a decoy receptor that binds RANKL and inhibits osteoclastogenesis. The RANKL/OPG ratio is a critical determinant of bone resorption.
Osteoclasts: The Bone Resorbers
- Origin – Osteoclasts are large, multinucleated cells derived from the monocyte/macrophage lineage of hematopoietic stem cells. Their differentiation requires macrophage colony-stimulating factor (M-CSF) and RANKL.
- Function – They are the only cells capable of resorbing mineralized bone. Using a specialized ruffled border membrane, they create an acidic microenvironment that dissolves hydroxyapatite, and they secrete proteolytic enzymes to degrade the organic matrix.
- Calcium mobilization – Through their resorptive activity, osteoclasts release calcium from the skeleton into the blood. This process is stimulated by PTH (acting indirectly through osteoblasts) and is the primary mechanism by which the body accesses its skeletal calcium reserves during periods of dietary insufficiency.
Peak Bone Mass
Peak bone mass refers to the maximum amount of bone tissue accumulated during growth and development, typically achieved by the late twenties to early thirties. It is one of the most important determinants of fracture risk later in life.
- Genetic factors – Heredity accounts for most of the variation in peak bone mass; the National Osteoporosis Foundation's 2016 position statement states that lifestyle choices influence 20–40% of adult peak bone mass (Weaver 2016, peak bone mass statement). Variants in genes encoding the vitamin D receptor, collagen type I, estrogen receptors, LRP5 (a Wnt signaling co-receptor), and RANKL have been studied as contributors to individual differences.
- Calcium intake during growth – The same position statement graded the evidence for calcium intake A, its strongest grade, with late childhood and the peripubertal years described as a critical period for bone accretion. The U.S. RDA for ages 9 to 18 is 1,300 mg/day (NIH Office of Dietary Supplements).
- Physical activity – Weight-bearing and high-impact activities during youth stimulate bone formation and increase peak bone mass. The mechanical loading effect is site-specific; for example, the dominant arm of tennis players shows measurably greater bone density than the non-dominant arm.
- Hormonal status – Estrogen and testosterone are essential for achieving peak bone mass. Delayed puberty, amenorrhea, or hypogonadism during adolescence can result in suboptimal bone accrual.
- Nutritional factors beyond calcium – The position statement found good evidence for a role of vitamin D and dairy consumption, and called for more rigorous trial data on many other lifestyle factors. Protein, phosphorus, magnesium, zinc, vitamin K, and vitamin C are also studied as contributors to bone development. Severe caloric restriction during growth years compromises peak bone mass.
Osteoporosis Prevention
Osteoporosis is a systemic skeletal disease characterized by low bone mass and microarchitectural deterioration of bone tissue, leading to increased fragility and susceptibility to fractures. The World Health Organization criteria define it by bone mineral density: a value 2.5 or more standard deviations below the young-adult mean (a T-score of −2.5 or lower), with values between 1 and 2.5 standard deviations below that mean classed as low bone mass, or osteopenia (Kanis 1994). Research on prevention spans the whole lifespan, from peak bone mass in youth to the rate of bone loss in later life.
- Calcium reference intakes – The recommended dietary allowance (RDA) for calcium is 1,000 mg/day for most adults and 1,200 mg/day for women over 50 and men over 70; the Tolerable Upper Intake Level (UL) is 2,500 mg/day for ages 19 to 50 and 2,000 mg/day over 50 (NIH Office of Dietary Supplements). The figure below sets these out by sex and age.
- Dietary sources – The NIH Office of Dietary Supplements describes milk, yogurt, and cheese as rich natural sources; nondairy sources include canned fish eaten with the bones, such as sardines and salmon, and certain vegetables such as kale, bok choy, and broccoli. In its food table, 3 ounces of sardines canned in oil with bones provide 325 mg and 1 cup of whole milk 276 mg.
- Factors linked to bone loss – High sodium intake increases urinary calcium excretion. High caffeine consumption may modestly reduce calcium absorption. Heavy alcohol intake impairs osteoblast function. Smoking is associated with faster bone loss and higher fracture risk. Chronic use of glucocorticoids is one of the most common causes of secondary osteoporosis.
- Falls – Many osteoporotic fractures follow a fall; approaches studied for reducing falls include balance training, vision correction, review of medicines that cause dizziness, and home modifications such as removing tripping hazards and installing grab bars.
- Screening – Dual-energy X-ray absorptiometry (DXA) is the standard method for measuring bone mineral density. The USPSTF (2025) recommends screening for osteoporosis in women 65 years or older and in postmenopausal women younger than 65 at increased risk, and concluded that the evidence is insufficient to assess screening in men (Nicholson 2025).
RDA and UL values from the NIH Office of Dietary Supplements calcium fact sheet (Food and Nutrition Board); the Institute of Medicine set the calcium RDAs from bone health (Ross 2011).
Vitamin D Synergy
Vitamin D and calcium are metabolically inseparable when it comes to bone health. Without adequate vitamin D, the body cannot efficiently absorb dietary calcium, regardless of how much calcium is consumed.
- Intestinal calcium absorption – Active vitamin D (1,25-dihydroxyvitamin D, or calcitriol) increases active intestinal calcium absorption by upregulating the expression of the epithelial calcium channel TRPV6, the intracellular calcium-binding protein calbindin-D9k, and the basolateral calcium pump PMCA1b in enterocytes.
- Consequences of deficiency – Vitamin D deficiency leads to impaired calcium absorption, secondary hyperparathyroidism (elevated PTH due to low calcium), increased bone resorption, and ultimately osteomalacia in adults (characterized by inadequately mineralized osteoid) or rickets in children (characterized by defective growth plate mineralization).
- Reference intakes – The Institute of Medicine set vitamin D RDAs of 600 IU/day for ages 1 to 70 and 800 IU/day for ages 71 and older, based on bone health and assuming minimal sun exposure (Ross 2011).
- Combined supplementation – In the 2014 Cochrane review, vitamin D alone was unlikely to prevent hip fracture (11 trials, 27,693 participants; RR 1.12) or any new fracture, while vitamin D plus calcium produced a small reduction in hip fracture (9 trials, 49,853 participants; RR 0.84). The review estimated this as one fewer hip fracture per 1,000 older adults per year among community residents and nine fewer per 1,000 per year in institutions (Avenell 2014). A 2007 meta-analysis reached a similar conclusion, with a pooled hip-fracture RR of 1.10 for vitamin D alone and 0.82 for vitamin D with calcium (Boonen 2007). The best-known positive trial gave 3,270 healthy ambulatory women in France, mean age 84, 1.2 g of calcium and 800 IU of vitamin D3 daily for 18 months, and reported 43% fewer hip fractures than placebo (Chapuy 1992). Reid and Bolland (2020) concluded that calcium, vitamin D, or both do not prevent fractures in community-dwelling adults, while a large study in vitamin D-deficient nursing home residents did show fracture prevention.
- Serum 25(OH)D levels – The Institute of Medicine's RDAs correspond to a serum 25-hydroxyvitamin D level of at least 20 ng/mL (50 nmol/L), which it judged to meet the needs of at least 97.5% of the population; it found that higher values were not consistently associated with greater benefit (Ross 2011). Some other groups and practitioners use higher thresholds; the Vitamin D3 page sets out the different positions.
- Vitamin K and osteocalcin – Vitamin K is the cofactor that carboxylates osteocalcin, a calcium-binding protein made by bone-forming cells. The idea that taking calcium and vitamin D without enough vitamin K sends calcium to arteries rather than bone is a hypothesis, not a trial finding — covered in the Cardiovascular Health deep-dive. A 2019 meta-analysis found no evidence that vitamin K affects bone mineral density or vertebral fractures in postmenopausal or osteoporotic patients, and judged the evidence insufficient to confirm a possible reduction in clinical fractures (Mott 2019).
Weight-Bearing Exercise
Mechanical loading is one of the most potent stimuli for bone formation. Wolff's Law states that bone adapts its structure to the forces placed upon it, becoming stronger in response to loading and weaker when loads are removed.
- Mechanotransduction – Osteocytes detect mechanical strain through their extensive dendritic network within the lacunar-canalicular system. When loaded, fluid flow through these tiny channels creates shear stress on osteocyte membranes, triggering signaling cascades that suppress sclerostin production (an inhibitor of bone formation) and promote Wnt signaling, which stimulates osteoblast activity.
- High-impact activities – Running, jumping, stair climbing, and sports involving quick directional changes (such as tennis and basketball) generate ground reaction forces that stimulate bone formation, particularly in the hip and spine.
- Resistance training – Weightlifting and other resistance exercises apply force to bones through muscle and tendon attachments, stimulating bone formation at these sites.
- Non-weight-bearing activity – Swimming and cycling provide little skeletal loading. Cosmonauts on Mir flights lasting 4 to 14.4 months lost bone mineral despite an in-flight exercise program (LeBlanc 2000), illustrating the importance of gravitational loading.
Calcium Absorption Factors
Only a fraction of dietary calcium is actually absorbed into the bloodstream. Several factors raise or lower the fraction absorbed.
- Vitamin D status – As described above, calcitriol drives active intestinal absorption, and vitamin D deficiency impairs it.
- Amount at one time – The NIH Office of Dietary Supplements states that absorption from food is about 45% at intakes of 200 mg/day but only 15% at intakes above 2,000 mg/day, and that absorption from supplements is highest at doses of 500 mg or less; for example, about 36% of a 300 mg dose and 28% of a 1,000 mg dose is absorbed.
- Gastric acid – According to the NIH Office of Dietary Supplements, calcium carbonate dissolves less well in people with low stomach acid unless it is taken with a meal, while calcium citrate depends less on stomach acid and can be absorbed without food. Proton pump inhibitors, H2 receptor antagonists, and achlorhydria all lower stomach acid.
- Oxalates – Oxalic acid, found in high concentrations in spinach, rhubarb, beet greens, and Swiss chard, binds calcium and forms insoluble calcium oxalate, significantly reducing calcium bioavailability from these foods. In a crossover study in 13 healthy adults, mean calcium absorption was 5.1% from spinach and 27.6% from milk (Heaney 1988).
- Phytates – Phytic acid, present in whole grains, legumes, nuts, and seeds, can bind calcium and reduce its absorption, though the effect is generally less pronounced than that of oxalates. Soaking, sprouting, or fermenting these foods reduces their phytate content.
- Fiber – Very high fiber intakes from concentrated sources may modestly reduce calcium absorption, though the effect of dietary fiber from mixed food sources appears to be clinically insignificant.
- Enhancers of absorption – Lactose may enhance calcium absorption in infants. Certain non-digestible oligosaccharides (prebiotics such as inulin and fructooligosaccharides) can improve calcium absorption in the large intestine by promoting fermentation and lowering colonic pH.
- Age – The NIH Office of Dietary Supplements states that net absorption is as high as 60% in infants and young children and about 25% in adults, declining further with age, partly due to reduced vitamin D production and activation, decreased expression of intestinal calcium transport proteins, and reduced responsiveness to calcitriol.
Age-Related Bone Loss
After peak bone mass is achieved, bone density remains relatively stable through the thirties and early forties. Thereafter, a gradual decline begins, accelerating significantly in women after menopause.
- Involutional bone loss – From midlife, both men and women lose bone gradually. This age-related loss is driven by a gradual shift in the remodeling balance, with resorption slightly exceeding formation at each remodeling site.
- Menopausal bone loss – In the Study of Women's Health Across the Nation (1,902 women), bone density changed little in the pre- and early perimenopause, declined substantially in the late perimenopause, and continued to fall at a similar pace in the first postmenopausal years; loss was about 35–55% slower in women in the top third of body weight than in the bottom third (Finkelstein 2008). Estrogen deficiency increases RANKL expression and decreases OPG production by osteoblasts, leading to enhanced osteoclast formation and activity. Estrogen withdrawal also shortens osteoblast lifespan and reduces their bone-forming capacity.
- Trabecular vs. cortical bone – Trabecular (cancellous) bone, with its high surface-area-to-volume ratio, is remodeled more rapidly and is therefore lost more quickly than cortical (compact) bone. This is one explanation offered for vertebral compression fractures (vertebral bodies are rich in trabecular bone) tending to appear earlier in life than hip fractures.
- Sarcopenia and bone loss – Age-related muscle loss (sarcopenia) reduces the mechanical loading on the skeleton, contributing to further bone loss. The combination of osteoporosis and sarcopenia (sometimes termed "osteosarcopenia") is associated with higher fracture and fall risk in older adults.
- Reference intakes in older adults – The calcium RDA rises to 1,200 mg/day for women at age 51 and for men at age 71; for men aged 51 to 70 it stays at 1,000 mg/day (NIH Office of Dietary Supplements). The vitamin D RDA rises from 600 to 800 IU/day at 71 and older (Ross 2011).
- Secondary causes of bone loss – In addition to aging and menopause, many medical conditions and medications accelerate bone loss, including hyperthyroidism, hyperparathyroidism, celiac disease, inflammatory bowel disease, chronic kidney disease, rheumatoid arthritis, prolonged glucocorticoid therapy, aromatase inhibitors, anticonvulsants, and GnRH agonists.
This content is provided for informational purposes only and does not constitute medical advice. The research raises particular questions about supplemental calcium for people with kidney disease, kidney stones, cardiovascular disease, or hypercalcemia; decisions about supplements belong with a clinician.
Key Research Papers
- Tai V, Leung W, Grey A, Reid IR, Bolland MJ (2015). Calcium intake and bone mineral density: systematic review and meta-analysis. BMJ. — DOI: 10.1136/bmj.h4183. — doi:10.1136/bmj.h4183
- Weaver CM, Alexander DD, Boushey CJ, et al. (2016). Calcium plus vitamin D supplementation and risk of fractures: an updated meta-analysis from the National Osteoporosis Foundation. Osteoporosis International. — DOI: 10.1007/s00198-015-3386-5. — doi:10.1007/s00198-015-3386-5
- Bolland MJ, Grey A, Avenell A, Gamble GD, Reid IR (2011). Calcium supplements with or without vitamin D and risk of cardiovascular events: reanalysis of the Women's Health Initiative Limited Access Dataset and meta-analysis. BMJ. — DOI: 10.1136/bmj.d2040. — doi:10.1136/bmj.d2040
- Jackson RD, LaCroix AZ, Gass M, et al. (2006). Calcium plus vitamin D supplementation and the risk of fractures (WHI). NEJM. — DOI: 10.1056/NEJMoa055218. — doi:10.1056/NEJMoa055218
- Bonjour JP (2011). Calcium and phosphate: a duet of ions playing for bone health. Journal of the American College of Nutrition. 30(5 Suppl 1):438S–448S. — PubMed PMID: 22081690
- Heaney RP (1990). Calcium intake and bone health throughout life. Journal of the American Medical Women's Association. 45(3):80–86. — PubMed PMID: 2186080
- Boonen S, Lips P, Bouillon R, Bischoff-Ferrari HA, Vanderschueren D, Haentjens P (2007). Need for additional calcium to reduce the risk of hip fracture with vitamin D supplementation: evidence from a comparative meta-analysis of randomized controlled trials. JCEM. 92(4):1415–1423. — PubMed PMID: 17264183
- Chapuy MC, Arlot ME, Duboeuf F, et al. (1992). Vitamin D3 and calcium to prevent hip fractures in elderly women. NEJM. — DOI: 10.1056/NEJM199212033272305. — doi:10.1056/NEJM199212033272305
- Boyle WJ, Simonet WS, Lacey DL (2003). Osteoclast differentiation and activation. Nature. — DOI: 10.1038/nature01658. — doi:10.1038/nature01658
- Bonewald LF (2011). The amazing osteocyte. Journal of Bone and Mineral Research. — DOI: 10.1002/jbmr.320. — doi:10.1002/jbmr.320
- Manolagas SC (2000). Birth and death of bone cells: basic regulatory mechanisms and implications for the pathogenesis and treatment of osteoporosis. Endocrine Reviews. 21(2):115–137. — PubMed PMID: 10782361
- Reid IR, Bolland MJ (2020). Calcium and/or vitamin D supplementation for the prevention of fragility fractures: who needs it? Nutrients. — DOI: 10.3390/nu12041011. — doi:10.3390/nu12041011
- Bolland MJ, Leung W, Tai V, Bastin S, Gamble GD, Grey A, Reid IR (2015). Calcium intake and risk of fracture: systematic review. BMJ. 351:h4580. — PubMed PMID: 26420387
- Avenell A, Mak JC, O'Connell D (2014). Vitamin D and vitamin D analogues for preventing fractures in post-menopausal women and older men. Cochrane Database of Systematic Reviews. (4):CD000227. — PubMed PMID: 24729336
- US Preventive Services Task Force; Grossman DC, Curry SJ, Owens DK, et al. (2018). Vitamin D, calcium, or combined supplementation for the primary prevention of fractures in community-dwelling adults: US Preventive Services Task Force recommendation statement. JAMA. 319(15):1592–1599. — PubMed PMID: 29677309
- US Preventive Services Task Force; Nicholson WK, Silverstein M, Wong JB, et al. (2025). Screening for osteoporosis to prevent fractures: US Preventive Services Task Force recommendation statement. JAMA. 333(6):498–508. — PubMed PMID: 39808425
- Kanis JA, Melton LJ 3rd, Christiansen C, Johnston CC, Khaltaev N (1994). The diagnosis of osteoporosis. Journal of Bone and Mineral Research. 9(8):1137–1141. — PubMed PMID: 7976495
- Weaver CM, Gordon CM, Janz KF, et al. (2016). The National Osteoporosis Foundation's position statement on peak bone mass development and lifestyle factors: a systematic review and implementation recommendations. Osteoporosis International. 27(4):1281–1386. — PubMed PMID: 26856587
- Ross AC, Manson JE, Abrams SA, et al. (2011). The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. Journal of Clinical Endocrinology and Metabolism. 96(1):53–58. — PubMed PMID: 21118827
- Heaney RP, Weaver CM, Recker RR (1988). Calcium absorbability from spinach. American Journal of Clinical Nutrition. 47(4):707–709. — PubMed PMID: 3354496
- Mott A, Bradley T, Wright K, Cockayne ES, Shearer MJ, Adamson J, Lanham-New SA, Torgerson DJ (2019). Effect of vitamin K on bone mineral density and fractures in adults: an updated systematic review and meta-analysis of randomised controlled trials. Osteoporosis International. 30(8):1543–1559. — PubMed PMID: 31076817
- LeBlanc A, Schneider V, Shackelford L, et al. (2000). Bone mineral and lean tissue loss after long duration space flight. Journal of Musculoskeletal and Neuronal Interactions. 1(2):157–160. — PubMed PMID: 15758512
- Finkelstein JS, Brockwell SE, Mehta V, et al. (2008). Bone mineral density changes during the menopause transition in a multiethnic cohort of women. Journal of Clinical Endocrinology and Metabolism. 93(3):861–868. — PubMed PMID: 18160467
PubMed Topic Searches
- PubMed: Calcium and BMD RCTs
- PubMed: Calcium, vitamin D, fracture meta-analyses
- PubMed: Peak bone mass and calcium
- PubMed: RANKL / OPG bone remodeling
- PubMed: Hydroxyapatite mineralization
- PubMed: Postmenopausal bone loss
External Authoritative Resources
Connections
- All Minerals
- Calcium (Main Page)
- Calcium Benefits Hub
- Calcium for Cardiovascular Health
- Calcium for Muscle Function
- Calcium for Nerve Transmission
- Osteoporosis
- Vitamin D3
- Vitamin K2
- Magnesium
- Phosphorus
- Boron
- Boron and Bone Density
- Manganese
- Manganese and Bone Formation
- Silicon
- Collagen
- Milk
- Arthritis
- Deficiency
- Toxicity
- History
- Sources