Bhringraj for the Liver and Other Ayurvedic Uses
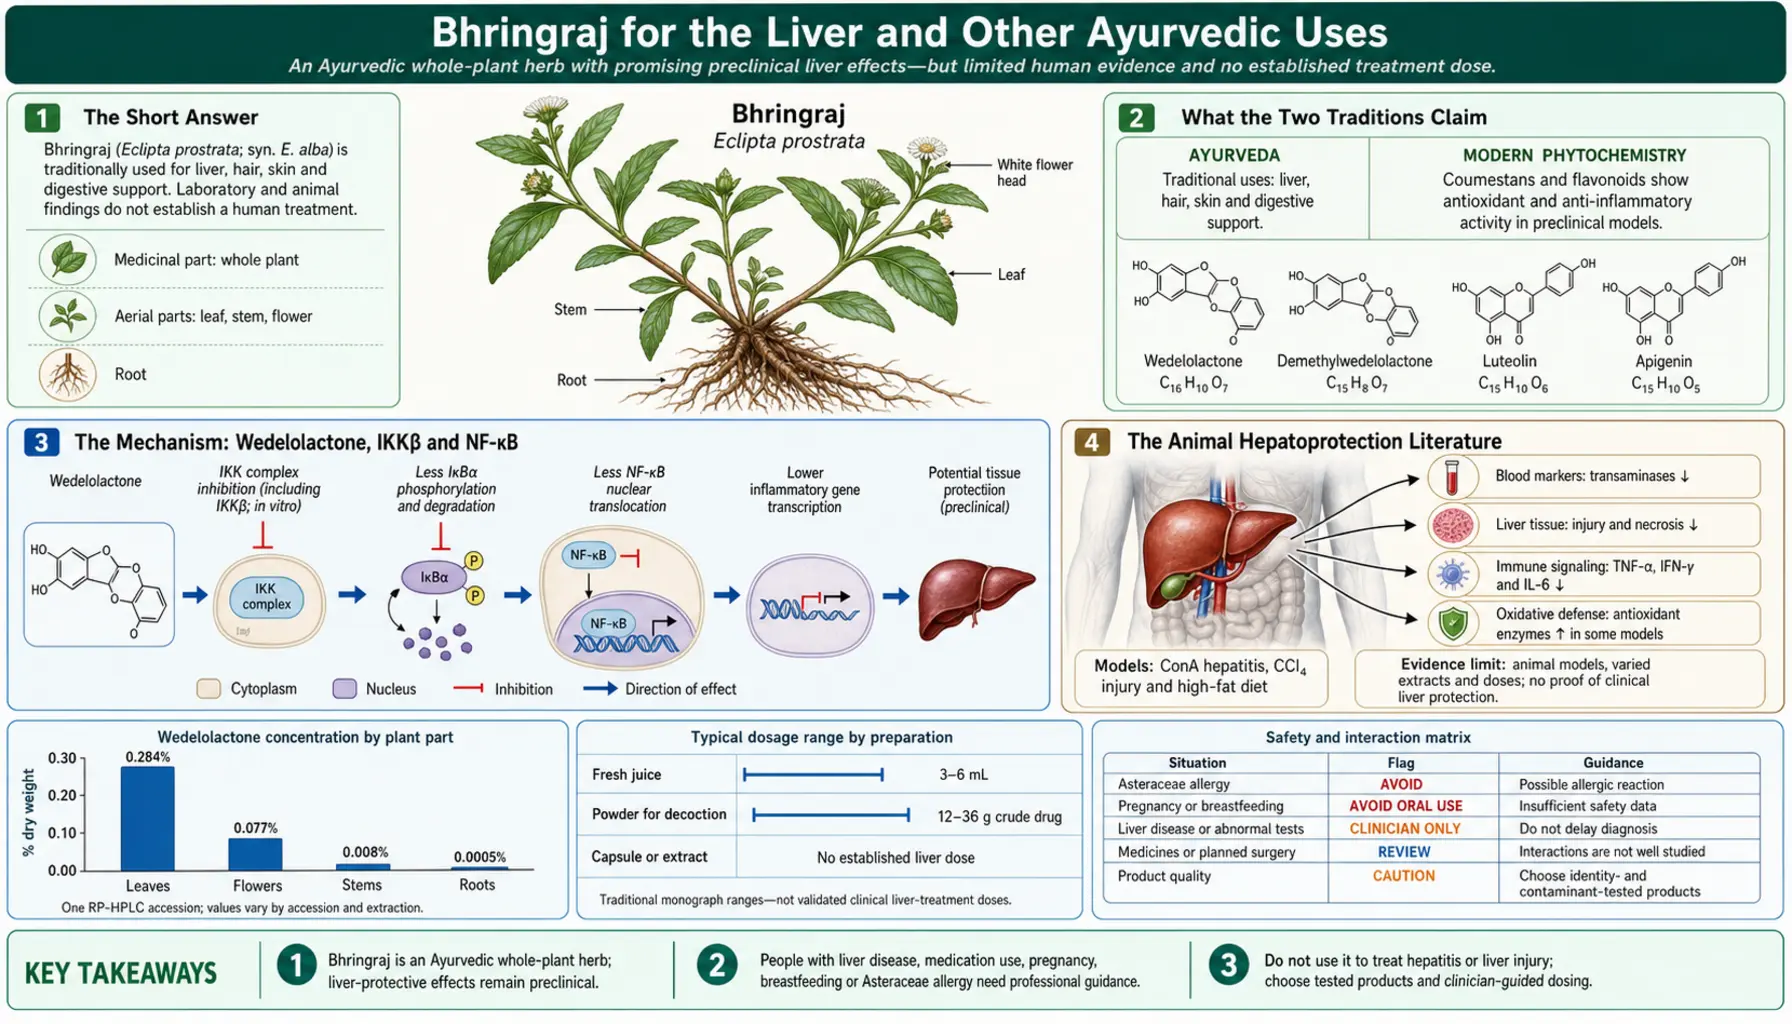
Hair is why people buy bhringraj. The liver is what most of its research is about. After the hair studies, the second and largest preclinical strand for Eclipta prostrata is hepatoprotection — rodent experiments in which extracts blunted chemically induced liver injury — and it comes with a mechanism that is unusually specific for a herbal claim: wedelolactone inhibits IKKβ, the kinase that switches on NF-κB, which is the central amplifier of inflammatory liver injury.
That is a coherent story with a molecular target, replicated across independent laboratories, and it is still entirely animal and in vitro. There is no controlled human trial of this plant for any liver condition. This page separates what the animal work shows from what it cannot, flags the trap where a multi-herb Ayurvedic liver product's trial results get quietly credited to bhringraj, names the endpoints a real human study would use, and then ranks the plant's other traditional indications by how much is actually known about each.
Table of Contents
- The Short Answer
- What the Two Traditions Claim
- The Mechanism: Wedelolactone, IKKβ and NF-κB
- The Animal Hepatoprotection Literature
- The Design Flaw Nobody Mentions
- The Polyherbal Trap — and What a Famous Liver Formula's Trials Show
- The Human Column, and What Would Fill It
- Why Jaundice Is the Worst Symptom to Self-Treat
- Other Traditional Uses, Ranked by Evidence
- Evidence Ledger
- Key Research Papers
- Connections
- Featured Videos
The Short Answer
- Rodent hepatoprotection is real and reasonably consistent. Extracts given before or alongside carbon tetrachloride, paracetamol or ethanol reduce the rise in serum transaminases, limit histological necrosis and preserve liver glutathione, across multiple independent groups. Cross-laboratory consistency is a genuine quality signal in preclinical work.
- The mechanism is specific, not hand-waving. An IKKβ inhibitor is an anti-inflammatory in the most literal molecular sense, and NF-κB activation in liver macrophages is central to how a chemical insult becomes cell death.
- Almost all of it is prophylaxis, not treatment. The standard design pre-treats the animal, which models prevention of an acute poisoning, not therapy of established liver disease. This is the most important limitation and it is rarely stated.
- There is no human trial. Absent, not negative. Nobody has run and failed this experiment.
- The famous Ayurvedic liver trial is not about this plant. A long-marketed multi-herb Ayurvedic liver formula — the polyherbal whose randomised trials people reach for — does not contain Eclipta. Its 2003 trial in alcoholic liver disease was negative; a 2025 meta-analysis of 10 trials found improvement in a few measures but not in most liver tests. Those are verdicts on that formula, not on bhringraj, and conflating the two misrepresents both.
- Self-treating jaundice is the one genuinely dangerous thing on this page. Not because the herb is toxic, but because the causes of jaundice include several that are time-critical.
What the Two Traditions Claim
Ayurveda. Bhringaraja is a liver and jaundice herb as well as a hair herb — used for kamala (jaundice) and disorders of yakrit (the liver), classically as the fresh expressed juice (svarasa) taken with honey, or as dried powder, and frequently as one component of a compound liver preparation rather than alone. It is classed as a rasayana, a rejuvenative, and appears in the Ayurvedic Pharmacopoeia of India.
Chinese medicine. The same aerial parts, as mo han lian (墨旱蓮), are used on a completely different theory: a herb that nourishes liver and kidney yin and cools the blood to stop bleeding. "Liver" in that sentence is a functional category in Chinese medicine and is not the organ of Western hepatology — a point worth stating, because the apparent agreement between the two traditions is partly an artefact of translation. Its best-known appearance is Er Zhi Wan (二至丸, "Two Solstices Pill"), pairing mo han lian with the fruit of Ligustrum lucidum.
Two large traditions adopting the same weed independently is a genuinely interesting fact, and it is worth being clear about what kind of fact it is. Convergence tells you the plant was available and salient in wet-ground agricultural landscapes across Asia, and that both systems found it worth a monograph. It does not corroborate efficacy: two traditions can reach the same wrong conclusion about a conspicuous plant as easily as the same right one. Traditional use establishes what people did, at what dose, for how long, and with what observed harm — which is real information, and is exactly the information a safety assessment uses.
The Mechanism: Wedelolactone, IKKβ and NF-κB
The chemistry here is better characterised than most herbal mechanisms, and it is worth setting out properly because it is the strongest part of the bhringraj file.
Wedelolactone — a coumestan, accompanied by demethylwedelolactone — has three reported activities in cell-free and cell-culture systems that all point the same way:
- IKKβ inhibition. The IKK complex phosphorylates IκB, which releases NF-κB to enter the nucleus and switch on inflammatory gene transcription. Wedelolactone was reported to suppress lipopolysaccharide-induced caspase-11 expression by directly inhibiting the IKK complex, in Cell Death and Differentiation; find it on PubMed. This is the best-replicated molecular claim about the plant.
- 5-lipoxygenase inhibition. Wagner and Fessler reported in vitro 5-LOX inhibition by Eclipta alba extracts and by wedelolactone itself in Planta Medica in 1986 — blocking leukotriene synthesis, a second and independent anti-inflammatory route.
- Secretory phospholipase A2 inhibition — the property behind the snake-venom work, and upstream of both the eicosanoid pathways.
Why that is a rational hepatoprotective target. In liver injury, damaged hepatocytes release signals that activate Kupffer cells, the liver's resident macrophages. Kupffer-cell NF-κB activation drives tumour necrosis factor and interleukin production, which recruits neutrophils and amplifies injury well beyond the original insult. Interrupting that loop upstream is a strategy the pharmaceutical industry has pursued in its own right, and several IKKβ programmes exist. So this is not a folk mechanism retrofitted to a folk claim; it is a target other people are trying to drug.
There is also reported work on wedelolactone and hepatic stellate cells, the cells whose activation lays down fibrosis — the current state of it can be seen by searching wedelolactone and hepatic stellate cells. In a human stellate-cell line grown in the laboratory (LX-2), wedelolactone lowered collagen I and alpha-smooth-muscle actin, two markers of stellate-cell activation, and blocked nuclear factor-κB (NF-κB) activity (Xia and colleagues, 2013). A 2024 laboratory study reported that it eased liver fibrosis and stellate-cell activation by suppressing the Hippo/YAP/TAZ pathway (Zhang and colleagues, 2024). That is laboratory work about fibrosis, several steps from an outcome in a person.
The gap the mechanism cannot cross. Every one of those results is about an isolated compound at a concentration chosen by the experimenter, in a dish. To connect it to a person swallowing a herb you need to know how much wedelolactone is in the preparation, how much is absorbed, what the liver does to it on first pass, what free concentration it reaches, and for how long. None of that has been measured in humans. A potent inhibitor that never reaches its target is a pharmacology fact and not a medicine, and the plant's saponins are known to be poorly absorbed as a class, which is a reason to expect the gap rather than assume it away.
The Animal Hepatoprotection Literature
The rodent work goes back decades and follows a recognisable template. Saxena, Singh and Anand reported hepatoprotective effects of Eclipta alba on subcellular levels in rats in the Journal of Ethnopharmacology in 1993, and the broader body can be surveyed with a search for Eclipta hepatoprotective studies.
What the studies typically do. A hepatotoxin — carbon tetrachloride most often, sometimes paracetamol, ethanol, thioacetamide or galactosamine — is given to rats or mice, with or without an Eclipta extract, and usually with silymarin from milk thistle as the positive control. The outcomes measured are serum alanine and aspartate aminotransferase, alkaline phosphatase and bilirubin; tissue glutathione, superoxide dismutase, catalase and lipid-peroxidation markers; and liver histology scored for necrosis and inflammation.
What they find. Reasonably consistently: lower transaminase rises, preserved glutathione, reduced lipid peroxidation, less necrosis on histology. Different extracts (aqueous, ethanolic, methanolic), different doses and different toxins, pointing the same direction across independent groups. That consistency is worth something. Preclinical literatures that fall apart on replication usually do so early, and this one has not.
What they cannot tell you.
- Carbon tetrachloride poisoning is not liver disease. It is a free-radical-mediated acute chemical injury, chosen because it is reproducible in a week. Human liver disease is fatty liver from insulin resistance, alcohol over decades, chronic viral hepatitis, autoimmune disease. A compound that blunts an acute solvent injury has not been shown to touch any of those.
- Transaminases are a marker, not an outcome. Alanine aminotransferase (ALT) falling is not the same as fibrosis regressing or a patient living longer. Drug development has repeatedly learned this the hard way.
- Dose translation is unresolved. Rodent milligram-per-kilogram doses do not convert to a human dose without allometric scaling and pharmacokinetic data, and the pharmacokinetics do not exist. This page will not print a human-equivalent dose, because any figure would be arithmetic on a missing input.
The Design Flaw Nobody Mentions
Read the methods sections and a pattern appears: the extract is usually given before, or at the same time as, the toxin. Sometimes for days beforehand. Occasionally afterwards, but pre-treatment is the norm.
That design measures prophylaxis against a poisoning that has not happened yet. It is a legitimate experiment and it is not the clinical question. Nobody arrives at a clinic having taken bhringraj in advance of their hepatitis. The question a patient has — "I have raised liver enzymes or fatty liver; will this help?" — is a treatment of established disease question, and the pre-treatment design cannot answer it.
The distinction matters more than it sounds, because the two situations engage different biology. Blocking the initiation of an oxidative injury is easier than reversing established inflammation and fibrosis; the history of hepatology is full of agents that did the first and not the second. When a supplement's marketing describes "liver support" and its evidence is a pre-treatment rodent study, the mismatch is not a technicality — it is the whole claim.
The Polyherbal Trap — and What a Famous Liver Formula's Trials Show
Bhringraj is rarely used alone for the liver. It appears as one component of compound Ayurvedic preparations, and this creates the most common way liver claims for it get inflated: a trial of a seven-herb product is quoted as evidence for one of its herbs.
Two separate errors need untangling.
Error one: crediting a formula's result to a component
Where a study used a multi-herb liver formula containing Eclipta among six or ten others, its result is evidence about that product. It cannot be apportioned to a component, and this is doubly true in Ayurveda, where compound formulation is often intended to produce an effect the ingredients do not have separately — synergy is the design goal, not an accident. If a formula works because of its combination, single-component attribution is unsound by the formula's own logic.
Error two: assuming the famous trial is even about this plant
The most-cited human evidence in Ayurvedic hepatology belongs to a long-marketed multi-herb Ayurvedic liver formula that has actually been through randomised trials. And here is the point that most articles never check: the classic formula does not contain Eclipta. It is built on caper root (Capparis spinosa) and chicory (Cichorium intybus) with a handful of further herbs including Solanum nigrum, Cassia occidentalis, Terminalia arjuna, Achillea millefolium and Tamarix gallica. Marketed formulations do change over time and between countries, so the label is the authority — but the trials people wave at bhringraj were run on a product that does not contain it.
And the alcoholic liver disease result was negative, which is a separate finding worth reporting straight. A double-blind, randomised, placebo-controlled trial of that formula in 80 people with alcoholic liver disease, reported by de Silva and colleagues in the Journal of Ethnopharmacology in 2003, found no significant difference in clinical outcome or liver chemistry at any point over 6 months; a further randomised double-blind trial in alcoholic cirrhosis, discussed in the hepatology literature, likewise reported no survival benefit, and secondary observations from it have been debated since — see the same formula in alcoholic cirrhosis. This page does not restate figures from the second trial, because its primary metadata could not be verified here.
A 2025 meta-analysis gives a more mixed picture across liver diseases. Pooling 10 randomised trials with 758 patients, it found benefits for the same formula in loss of appetite, in bringing one liver enzyme reading (serum glutamic-pyruvic transaminase, SGPT) back toward normal (mean difference −16.37) and in markers of fat metabolism in people with liver cirrhosis. It found no significant effect on serum glutamic-oxaloacetic transaminase, alanine aminotransferase (ALT), aspartate aminotransferase (AST), alkaline phosphatase, bilirubin or blood measures. The authors rated the quality of the evidence from very low to moderate — mostly low or very low, because the trials were small and at high risk of bias (Priya and colleagues, 2025).
Why report someone else's negative trial on a bhringraj page? Because it fixes two things at once:
- It shows that Ayurvedic liver products can be trialled and have been, which removes the "traditional medicine cannot be tested" defence entirely.
- It marks the difference between tested and absent. That formula has verdicts on real endpoints — negative in the 2003 alcoholic liver disease trial, and mixed in the 2025 meta-analysis, with one enzyme reading and fat-metabolism markers improved and most liver tests unchanged. Bhringraj has no verdict at all. Those are different epistemic positions, and it is not honest to let bhringraj borrow the positive glow of "Ayurvedic liver herb" while its better-tested neighbour has actually been put to the test.
The same reasoning applies to Er Zhi Wan on the Chinese side: any result from that pill is a result for Eclipta plus Ligustrum, not for Eclipta. And on this site, the Triphala dosing and safety page works through the identical problem for haritaki inside a three-fruit formula.
The Human Column, and What Would Fill It
There is no randomised controlled trial of Eclipta prostrata for hepatitis, fatty liver disease, alcohol-related liver disease, drug-induced liver injury, cirrhosis or raised transaminases of unknown cause. The search that ought to return one — Eclipta clinical trial, liver — does not.
Naming the instruments that would be used is the strongest honest move available here, because every one of them is standard equipment in hepatology trials, used routinely on drugs and on other botanicals. Their absence from the Eclipta file is a choice nobody made deliberately, not an impossibility.
- Serum alanine aminotransferase and aspartate aminotransferase (AST) normalisation rates over 12–24 weeks — the cheapest endpoint, and the one a supplement trial has no excuse for omitting.
- Liver fat by MRI-PDFF (proton density fat fraction), the current quantitative standard for steatosis, or controlled attenuation parameter on FibroScan as the cheaper alternative.
- Liver stiffness by transient elastography in kilopascals, or MR elastography, for fibrosis.
- Non-invasive fibrosis scores — FIB-4, the non-alcoholic fatty liver disease (NAFLD) fibrosis score, enhanced liver fibrosis panel — validated and free to compute.
- Paired liver biopsy with a scored histological outcome (steatohepatitis resolution, fibrosis-stage improvement) where the question justifies it.
- Hard clinical endpoints for advanced disease: decompensation, transplant, death — the endpoints the cirrhosis trial of that multi-herb formula went after and did not meet.
- Product characterisation — the extract assayed for wedelolactone, so a positive result could be reproduced.
A live search for randomised liver trials using MRI-PDFF and elastography shows how routine this machinery is. Point it at bhringraj and the question would be settled in a year.
Why Jaundice Is the Worst Symptom to Self-Treat
This is the one place on the bhringraj file where real harm is plausible, and the harm is not from the herb.
Bhringraj's classical indication is kamala — jaundice. Jaundice is a sign, not a diagnosis, and its causes include several in which delay changes the outcome:
- Biliary obstruction — a gallstone in the common bile duct, a stricture, or a tumour of the pancreas or bile duct. Obstruction with infection (ascending cholangitis) is a surgical emergency.
- Acute viral hepatitis, which needs identifying because some forms are treatable and all are transmissible.
- Drug-induced liver injury, where the treatment is stopping the offending agent — which cannot happen if nobody looks for it.
- Haemolysis, which is a blood problem presenting as a liver sign.
- Decompensating chronic liver disease, where jaundice marks a change in trajectory.
Liver disease is also silent until it is advanced. Fatty liver and early fibrosis produce no symptoms, which is exactly why they are missed and exactly why a herb that makes someone feel they are addressing the problem is risky in a way its own toxicology cannot capture. Liver problems are found with a liver function panel, a blood test; a supplement does not detect them.
One thing this page will not do is manufacture a hazard. Eclipta prostrata has no notable hepatotoxicity signal — the research direction is the opposite — and it is not on the herb list that fills liver-injury registries. That said, herbal and dietary supplements are a documented and growing share of drug-induced liver injury cases: the US Drug-Induced Liver Injury Network reported on liver injury from herbals and supplements in Hepatology in 2014. Among 839 people with liver injury enrolled from 2004 to 2013, the share caused by herbals and supplements rose from 7% to 20%, and injury from supplements other than bodybuilding products led to death or liver transplant more often than injury from medications (13% versus 3%). The category has a problem; this plant is not one of its named offenders. Both halves of that sentence are true and both belong on the page.
Other Traditional Uses, Ranked by Evidence
Ordered by how much is actually known, strongest first — which is close to the reverse of how they are marketed.
- Hair and scalp. The tradition's flagship use (kesharaja, "king of hair") and the only claim with topical rodent studies using a hair endpoint and a drug comparator. Still no human trial. Examined in full on the hair-growth page. Tier: animal.
- Liver protection. This page. Tier: animal, prophylactic designs.
- Anti-inflammatory activity. The best-characterised molecular story — IKKβ, 5-LOX, sPLA2 — supported by rodent oedema and analgesia models. Bioavailability is the unanswered question. Tier: in vitro plus animal.
- Snakebite. Genuinely interesting pharmacology: wedelolactone neutralises myotoxic phospholipase A2 in pit-viper venom, in rodents, usually with compound and venom mixed or given immediately. It is not a basis for human use under any circumstances. Snakebite is a time-critical emergency, antivenom is the only treatment, neurotoxic venom components are untouched by this mechanism, and any delay is tissue destroyed or a diaphragm failing. The main page states this at length and it is repeated here because it is the one thing on the whole file that could kill someone. Tier: animal, and clinically contraindicated as a substitute for care.
- Bleeding and "cooling the blood" (mo han lian). A traditional haemostatic indication sitting alongside an in vitro literature on platelets and coagulation that disagrees with itself — results point both ways depending on extract and assay. Coumestans are related to coumarins, but anticoagulant activity requires the 4-hydroxycoumarin dimer structure of warfarin and dicoumarol, which wedelolactone does not have; so the chemistry neither contradicts nor explains the traditional use. The direction of the effect is unresolved, which matters most for people facing surgery or taking blood thinners — see the safety page. Tier: contradictory in vitro.
- Blood sugar. Rodent studies report hypoglycaemic activity for Eclipta extracts — see Eclipta hypoglycaemic studies in rats. This is listed here as an interaction caution rather than a benefit: an unquantified glucose-lowering effect matters to someone on insulin or a sulfonylurea, and it is not a reason to use the plant for diabetes. Tier: animal.
- Antimicrobial and antiviral screening. Extracts inhibit various organisms in culture, as do most plant extracts; a live search shows the field at Eclipta antiviral and antimicrobial in vitro. In one laboratory study, an Eclipta alba extract strongly inhibited the hepatitis C virus copying enzyme (the NS5B replicase) in the test tube and reduced virus replication in cultured cells; the active compounds were identified as wedelolactone, luteolin and apigenin (Manvar and colleagues, 2012). That is test-tube and cell-culture work, not a human trial. Worth contrasting with Phyllanthus amarus, the Indian plant that actually accumulated human hepatitis B trials from the late 1980s onward, with early positive results that later replications did not sustain — the Phyllanthus hepatitis B literature. That is what a real attempt at an antiviral herbal programme looks like, and bhringraj has nothing comparable. Tier: in vitro.
- Memory, vision, tinnitus, premature greying, lower-back weakness. These belong to the Chinese yin-deficiency pattern rather than to Western diagnostic categories, and the pattern is treated with formulas, not single herbs. For memory specifically, the tradition's designated medhya herb is Bacopa monnieri, not bhringraj, and bacopa is the one with human trials. Tier: traditional use only.
- Immunomodulation, anticancer, antivenom-adjacent, wound healing, and the rest of the review-article list. Cell-culture screening results. Every well-studied plant has a list like this, and it is not a list of uses. Tier: preliminary.
Evidence Ledger
Distinguishing absent (never tested) from negative (tested and failed), because the two verdicts are routinely collapsed and the collapse always favours the untested claim.
- Wedelolactone inhibits IKKβ and 5-LOX. Tier: in vitro, replicated. Verdict: established as chemistry.
- Eclipta extracts reduce chemically induced liver injury in rodents. Tier: animal, multiple independent groups. Verdict: supported in animals, predominantly as prophylaxis.
- Wedelolactone affects hepatic stellate cell activation. Tier: cell culture. Verdict: preliminary.
- Bhringraj improves any human liver measure — alanine aminotransferase, liver fat, stiffness, histology. Tier: none. Verdict: absent.
- Bhringraj treats hepatitis, fatty liver or cirrhosis. Tier: none. Verdict: absent.
- Polyherbal Ayurvedic liver products improve outcomes in alcoholic liver disease. Tier: human, randomised. Verdict: negative for the product tested — and that product does not contain Eclipta.
- Reaches an effective free concentration in a human liver after an oral dose. Tier: none; no human pharmacokinetics exist. Verdict: unknown, and it is the hinge the whole claim turns on.
- Safe to substitute for medical assessment of jaundice or abnormal liver tests. Verdict: no — and this is the page's only real hazard.
- Notably hepatotoxic itself. Tier: no signal in the literature reviewed. Verdict: checked and clear — not a documented cause of liver injury.
Key Research Papers
Where a paper's PubMed record was checked, its PMID is the link; topic searches are kept for the wider literature. Metadata below is plain text so it can be checked; where it could not be verified, the finding is described and a topic search is given instead.
- Wagner H, Geyer B, Kiso Y, Hikino H, Rao GS. Coumestans as the main active principles of the liver drugs Eclipta alba and Wedelia calendulacea. Planta Medica, 1986;(5):370–4. PubMed PMID: 3797500 — The paper that tied the liver reputation to the coumestans — and covered two genera at once.
- Wagner H, Fessler B. [In vitro 5-lipoxygenase inhibition by Eclipta alba extracts and the coumestan derivative wedelolactone]. Planta Medica, 1986;(5):374–7. Article in German. PubMed PMID: 3797501 — In vitro.
- Saxena AK, Singh B, Anand KK. Hepatoprotective effects of Eclipta alba on subcellular levels in rats. Journal of Ethnopharmacology, 1993;40(3):155–61. PubMed PMID: 8145570 — Animal. Representative of the template the whole literature follows.
- Kobori M, Yang Z, Gong D, et al. Wedelolactone suppresses LPS-induced caspase-11 expression by directly inhibiting the IKK complex. Cell Death and Differentiation, 2004;11(1):123–30. PubMed PMID: 14526390 — In vitro, isolated compound.
- de Silva HA, Saparamadu PA, Thabrew MI, Pathmeswaran A, Fonseka MM, de Silva HJ. Liv.52 in alcoholic liver disease: a prospective, controlled trial. Journal of Ethnopharmacology, 2003;84(1):47–50. PubMed PMID: 12499076 — Human, randomised — negative. A polyherbal that does not contain Eclipta, and the reason "Ayurvedic liver formula" is not a recommendation.
- Priya A, Kumari M, Kumar A, Kumari K, Kumar A, Ranjan J, Majhee L. Effect of LIV-52 for the Treatment of Hepatic Disorders: A Systematic Review and Meta-Analysis. Journal of Integrative and Complementary Medicine, 2025;31(12):1021–1030. PubMed PMID: 40601500 — Meta-analysis of 10 randomised trials, 758 patients — mixed; evidence mostly low or very low quality. The same multi-herb formula, which does not contain Eclipta.
- The same multi-herb formula in alcoholic liver cirrhosis, randomised double-blind trial — find on PubMed. Human, randomised — no survival benefit reported. Primary metadata unverified here; described, not quoted.
- Navarro VJ, Barnhart H, Bonkovsky HL, et al. Liver injury from herbals and dietary supplements in the U.S. Drug-Induced Liver Injury Network. Hepatology, 2014;60(4):1399–408. PubMed PMID: 25043597 — Context for the supplement category — in which Eclipta is not a named offender.
- Manvar D, Mishra M, Kumar S, Pandey VN. Identification and evaluation of anti hepatitis C virus phytochemicals from Eclipta alba. Journal of Ethnopharmacology, 2012;144(3):545–54. PubMed PMID: 23026306 — In vitro and cell culture.
- Xia Y, Chen J, Cao Y, Xu C, Li R, Pan Y, Chen X. Wedelolactone exhibits anti-fibrotic effects on human hepatic stellate cell line LX-2. European Journal of Pharmacology, 2013;714(1–3):105–11. PubMed PMID: 23791612 — Cell culture.
- Zhang W, Gao K, Bai Y, Xu D, Zhao M, Tao X, Wang J. Wedelolactone Attenuates Liver Fibrosis and Hepatic Stellate Cell Activation by Suppressing the Hippo Pathway. Rejuvenation Research, 2024;27(6):207–219. PubMed PMID: 39276092 — Laboratory study.
- Live literature search: the full Eclipta hepatoprotection literature — note how uniformly the designs are pre-treatment.
- Live literature search: wedelolactone and hepatic stellate cells.
- Live literature search: Eclipta clinical trials in liver disease — the search that should return something and does not.
- Live literature search: how liver trials are actually measured — MRI-PDFF, elastography, paired biopsy.
- Live literature search: Phyllanthus amarus and hepatitis B — the comparator that shows a traditional plant can accumulate real human data, and what happens when replication is attempted.
PubMed Topic Searches
- Eclipta, both binomials
- Wedelolactone, NF-κB and IKK
- Eclipta and blood glucose in rodents
- Er Zhi Wan (Ligustrum + Eclipta)
- Limits of the carbon-tetrachloride model
- Silymarin trials — the positive control in the rodent studies, and the liver herb with human data.
- Evaluating jaundice — why it needs a clinician.
- Eclipta antiviral and antimicrobial screening
Connections
- All Herbs
- Bhringraj (Eclipta prostrata) — the main topic page, including the snakebite section in full.
- Bhringraj for Hair Growth — the claim most readers arrive for.
- Which Bhringraj? — why the shared coumestan chemistry cannot confirm identity.
- Oils, Formulations and Safety — interactions, including the glucose and bleeding cautions raised above.
- Milk Thistle: Liver Protection — silymarin is the positive control in the rodent studies and the liver herb with the most human data.
- Milk Thistle in Hepatitis — what a serious attempt at a herbal liver trial programme looks like.
- Curry Leaf: Cholesterol and Liver — the same rodent-only pattern in a neighbouring herb.
- Triphala Dosing and Safety — the polyherbal attribution problem worked through in detail.
- Turmeric — another NF-κB-modulating Ayurvedic plant with the same bioavailability problem.
- Non-Alcoholic Fatty Liver Disease — the condition most often self-treated with liver herbs.
- Cirrhosis — why silent liver disease is a bad thing to self-manage.
- Hepatitis C — a liver disease that is now curable with real drugs.
- Liver Function Tests — how liver injury is actually measured.
This page is educational and is not medical advice. Bhringraj is not a proven treatment for any liver condition; the evidence is traditional use plus rodent studies, mostly of prevention rather than treatment, and no controlled human trial exists. Jaundice, dark urine, abnormal liver tests or right-upper-abdominal pain are signs that hospitals treat as needing prompt assessment — several causes are time-critical. This plant is not a snakebite treatment: snakebite is an emergency and antivenom is the only treatment.