⚠ Evidence warning: Clinical trials or other evidence do not support the claims that saw palmetto relieves overactive bladder, urinary symptoms after prostate surgery and recurrent urinary tract infection. This page keeps it as a report of what people, websites or other media say.
Saw Palmetto for Urinary Function
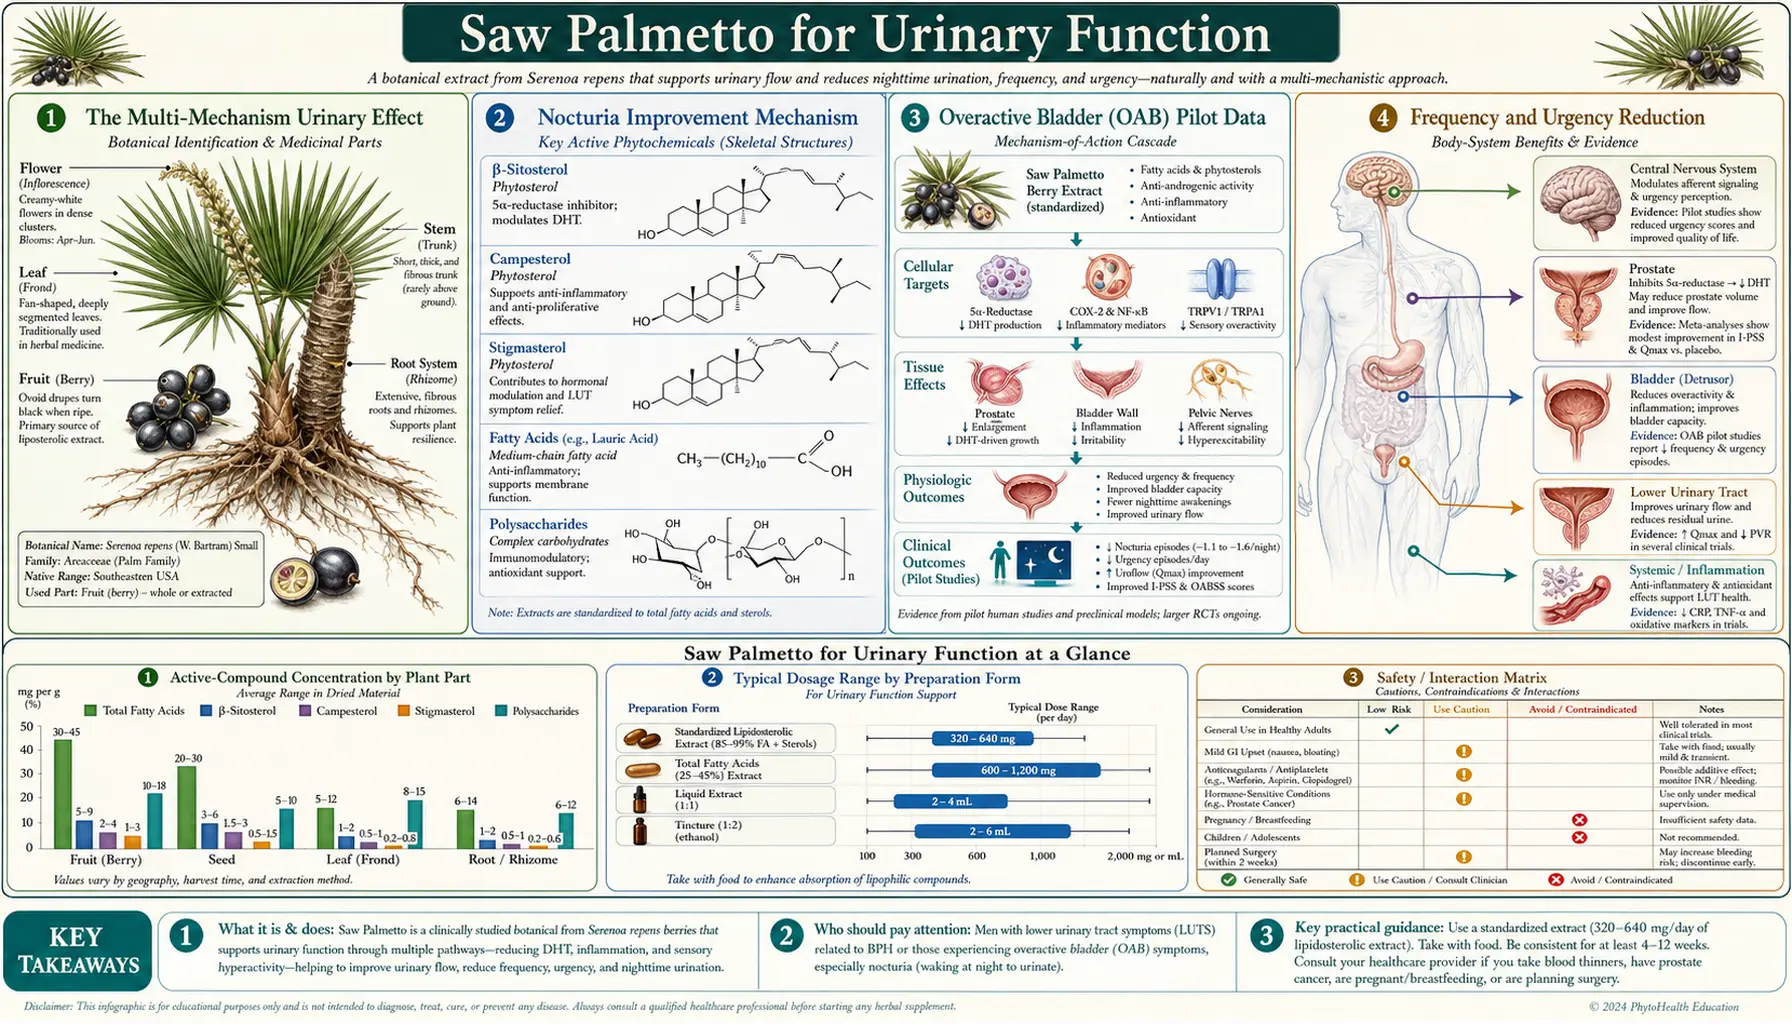
Saw palmetto's urinary effects extend beyond the canonical benign prostatic hyperplasia (BPH) indication into several adjacent areas where the herb has accumulated meaningful clinical experience and small-trial data: overactive bladder syndrome (OAB), post-prostatectomy urinary symptoms, nocturia from mixed mechanisms, lower urinary tract symptoms (LUTS) in women with bladder dysfunction, and chronic prostatitis / chronic pelvic pain syndrome (CP/CPPS). The mechanistic basis is the same triple action that drives the benign prostatic hyperplasia effect — partial alpha-1 adrenergic blockade reduces bladder neck smooth muscle tone, anti-inflammatory action reduces detrusor irritation, and the slower 5-alpha-reductase mechanism contributes through the prostatic urethra and detrusor androgen-receptor pathways. This page covers each of these adjacent urinary applications honestly, with the same emphasis on realistic effect size and patient selection that the benign prostatic hyperplasia page applies, recognizing that several of these indications have far thinner published evidence than the benign prostatic hyperplasia core indication.
Table of Contents
- The Multi-Mechanism Urinary Effect
- Nocturia Improvement Mechanism
- Overactive Bladder (OAB) Pilot Data
- Frequency and Urgency Reduction
- Post-Prostatectomy Use
- Chronic Prostatitis / CPPS
- Female Lower Urinary Tract Symptoms
- Combination with Anticholinergics and Beta-3 Agonists
- Why Workup Matters Before Empiric Therapy
- How the Evidence Applies by Symptom Pattern
- Key Research Papers
- Connections
- Featured Videos
The Multi-Mechanism Urinary Effect
The lower urinary tract is composed of the bladder (smooth-muscle detrusor body, internal urethral sphincter), the prostate (in men, surrounding the prostatic urethra), the bladder neck (densely innervated by alpha-1 receptors), and the external striated sphincter (under voluntary control). Symptomatic urinary dysfunction in older men typically reflects a mix of contributions: prostate volume causing mechanical obstruction, alpha-1 mediated smooth muscle tone causing functional obstruction, detrusor overactivity causing urgency and frequency, detrusor underactivity causing incomplete emptying, and the central nervous system contribution from impaired bladder filling sensation in aging.
Saw palmetto's actions touch several of these components:
- Bladder neck and prostatic urethra alpha-1 antagonism — partial blockade of alpha-1 adrenergic receptors reduces smooth-muscle tone in the dynamic outflow component. The effect is weaker than tamsulosin or alfuzosin but acts at the same anatomic target.
- Prostatic anti-inflammatory effects — COX/LOX inhibition in inflamed prostatic tissue reduces irritative symptoms that arise from chronic prostatic inflammation (a contributor to LUTS independent of prostate volume).
- Detrusor effects (indirect) — chronic outflow obstruction produces secondary detrusor hypertrophy and instability. Reducing the outflow obstruction with saw palmetto's combined alpha-1 and anti-androgen effects may produce secondary improvement in detrusor function over months.
- Anti-edematous effects on bladder/prostate tissues — the empirical observation of rapid subjective "decompression" within days of starting saw palmetto suggests an immediate anti-edematous mechanism that improves outflow before any anti-androgen volume change could occur.
The net urinary effect in responders is improvement in both obstructive symptoms (weak stream, hesitancy, incomplete emptying) and irritative symptoms (frequency, urgency, nocturia). The relative balance of these two improvements varies by patient phenotype.
Nocturia Improvement Mechanism
Nocturia — awakening at night to urinate — is the symptom most consistently improved by saw palmetto across the published trial literature. A 1998 systematic review in JAMA (Wilt and colleagues, 18 randomised trials, 2,939 men, studies lasting 9 weeks on average) found an average reduction of 0.76 nocturia episodes per night across 10 pooled trials, a clinically meaningful change for patients whose sleep quality was the dominant motivation for seeking treatment.
Later and larger trials did not confirm a clear benefit. The 2023 Cochrane review pooled 27 randomised trials with 4,656 men. In the trials at low risk of bias, saw palmetto alone made little to no difference to urinary symptom scores compared with placebo at 3–6 months (an average of 0.90 points lower on the 35-point International Prostate Symptom Score) or at 12–17 months, and little to no difference to quality of life; side effects were about as common as on placebo. The reviewers concluded that saw palmetto alone gives little to no benefit for urinary symptoms from an enlarged prostate.
Nocturia has multiple causes that contribute independently and additively:
- Reduced functional bladder capacity — either from detrusor overactivity (urgency at low fill volumes) or from poor emptying with elevated post-void residual. Saw palmetto's outflow effects modestly improve emptying, which over months reduces the residual urine that effectively shrinks functional capacity.
- Increased nocturnal urine production (nocturnal polyuria) — age-related loss of the circadian arginine vasopressin rhythm, which normally concentrates urine at night. Saw palmetto does not address this directly, so patients whose nocturia is primarily from nocturnal polyuria respond less well.
- Increased global urine production (24-hour polyuria) — from diabetes mellitus, diabetes insipidus, hypercalcemia, lithium, or excessive fluid intake. These require diagnostic workup and addressing the underlying cause.
- Sleep disorders — obstructive sleep apnea is a major cause of nocturia in older men. The mechanism is fragmented sleep producing increased awareness of bladder filling and apnea-driven atrial natriuretic peptide release driving nocturnal urine production. Treating the sleep apnea often resolves the nocturia.
The implication: when saw palmetto reduces nocturia, the reduction is mediated primarily by improvement in functional bladder capacity through the outflow mechanisms. Patients whose nocturia is dominated by nocturnal polyuria or sleep apnea respond less well, which is why sorting out the cause of nocturia matters before assuming a prostatic mechanism. A simple 24-hour voiding diary (recording time and volume of every void) reliably distinguishes the dominant mechanism and is the standard first step in sorting out the cause of nocturia.
Overactive Bladder (OAB) Pilot Data
Overactive bladder syndrome is characterized by urgency, with or without urge incontinence, usually accompanied by frequency and nocturia, in the absence of urinary tract infection or other obvious pathology. OAB affects approximately 16% of adults over age 40, with prevalence rising with age. The standard pharmacotherapy is anticholinergics (oxybutynin, tolterodine, solifenacin, darifenacin) or the beta-3 adrenergic agonist mirabegron, both of which suppress detrusor overactivity.
Saw palmetto for OAB is an investigational use with limited published evidence. The mechanistic logic is twofold: first, the alpha-1 antagonism may reduce bladder neck reflex stimulation of the detrusor; second, the anti-inflammatory mechanism may reduce neurogenic detrusor irritation arising from prostatic inflammation in men with both benign prostatic hyperplasia and OAB symptoms.
Published reports on this question are few:
- Combination saw palmetto + anticholinergic therapy has been reported in observational case series as producing additive symptom relief without prohibitive side effects.
The honest summary: saw palmetto for isolated OAB (without coexisting benign prostatic hyperplasia) is poorly studied, and no controlled trial has tested it as a first treatment. For men with combined benign prostatic hyperplasia and OAB symptoms — a very common combination — practitioners describe saw palmetto as an addition to anticholinergic or mirabegron therapy when the benign prostatic hyperplasia component contributes meaningfully to the irritative symptoms.
Frequency and Urgency Reduction
Frequency (more than 8 voids per 24 hours) and urgency (a strong sudden need to void with inability to defer) are the irritative LUTS most consistently improved across saw palmetto trials. Mechanism: the combination of anti-inflammatory action in the prostatic tissue (reducing the neurogenic detrusor irritation that arises from inflamed prostatic afferents) and partial alpha-1 antagonism in the bladder neck.
A 2019 Russian report (Vinarov and colleagues) followed 30 men at risk of benign prostatic hyperplasia progression who took 320 mg of saw palmetto extract daily for 15 years, in an open study with no comparison group; it reported no progression in symptom scores, prostate volume, urine flow or residual urine, and no drug-related side effects. An 8-week open pilot trial with no comparison group (Suter 2013, 82 men, 320 mg daily, led by the product maker's medical department) reported the International Prostate Symptom Score falling from 14.4 to 6.9 points, with improved sexual function; it did not report urgency or frequency counts separately.
The largest placebo-controlled test is the US CAMUS trial (Complementary and Alternative Medicine for Urological Symptoms; JAMA 2011): 369 men aged 45 and over took saw palmetto or placebo for 72 weeks, with the saw palmetto dose raised from 320 mg to 640 mg and then 960 mg a day. Symptom scores fell 2.20 points on saw palmetto and 2.99 points on placebo; saw palmetto was no better than placebo on any secondary outcome, including nocturia, and no clearly attributable side effects were found.
Practitioners describe this time course in men who respond:
- Frequency improvement over the first 4-8 weeks — voids per day declining from approximately 10-12 toward 7-9
- Urgency episodes declining gradually over 8-12 weeks — the strong "need to go right now" sensation becomes less intense and more deferrable
- Concurrent reduction in nocturia (often the first improvement noticed because of its sleep-disruption impact)
- Less reliable improvement in urge incontinence, which usually requires anticholinergic or behavioral therapy
Post-Prostatectomy Use
Patients who have undergone radical prostatectomy for prostate cancer often have persistent or new lower urinary tract symptoms even after the prostate has been completely removed. The mechanisms are different from benign prostatic hyperplasia but partially overlap:
- Anastomotic stricture or bladder neck contracture — mechanical obstruction at the surgical anastomosis
- Detrusor overactivity — from radiation or surgical bladder denervation
- Sphincter weakness causing stress incontinence — from surgical disruption of the external sphincter
- Pelvic floor dysfunction — from neuromuscular reorganization after surgery
- Persistent post-prostatectomy nocturia — one of the most common complaints, often multifactorial
Saw palmetto's post-prostatectomy use is poorly studied but has accumulated practitioner experience. The mechanistic logic that remains relevant after prostate removal: alpha-1 antagonism at the bladder neck (which remains innervated), anti-inflammatory effects on the urinary tract, and the anti-edematous mechanism that may help in the post-surgical inflammatory recovery period.
The 5-alpha-reductase mechanism becomes essentially irrelevant after radical prostatectomy because the target tissue (prostate) has been removed. For hair-loss use, the scalp 5-alpha-reductase target remains after prostatectomy.
For nocturia and irritative symptoms after prostatectomy, practitioners use saw palmetto as an add-on to standard post-prostatectomy management (pelvic floor physical therapy, behavioral retraining, anticholinergics for detrusor overactivity, possibly alpha-blockers for bladder neck contracture). New or worsening post-surgical symptoms can come from treatable mechanical causes such as a stricture or bladder neck contracture, which an herb does not open.
Chronic Prostatitis / CPPS
Chronic prostatitis / chronic pelvic pain syndrome (CP/CPPS, NIH category III) is a heterogeneous condition characterized by pelvic pain and urinary symptoms in the absence of demonstrable bacterial infection. It accounts for approximately 90% of all chronic prostatitis presentations and is one of the most difficult urologic syndromes to treat reliably. The U.S. National Institutes of Health-Chronic Prostatitis Symptom Index (NIH-CPSI) is the standard severity instrument.
Saw palmetto's anti-inflammatory mechanism makes it theoretically appealing for CP/CPPS. A few small studies have explored this:
- Kaplan 2004 randomized 64 men aged 24–58 with CP/CPPS, in an open-label trial, to saw palmetto (325 mg daily) or finasteride for 1 year. The NIH-CPSI score fell from 23.9 to 18.1 on finasteride (p<0.003) but barely moved on saw palmetto, from 24.7 to 24.6 (p=0.41).
- Several combination products pairing saw palmetto with other anti-inflammatory phytotherapies (quercetin, pollen extract, palmitoylethanolamide) have shown modest benefit in CP/CPPS pilot trials.
The honest summary: saw palmetto monotherapy for CP/CPPS has not shown clear benefit in the limited published trials. It may have a role as part of a multi-modal regimen that also addresses pelvic floor dysfunction (physical therapy), inflammation (nonsteroidal anti-inflammatory drugs (NSAIDs), pollen extract), neurogenic pain (tricyclic antidepressants, gabapentinoids), and psychological factors (cognitive behavioral therapy). CP/CPPS is a syndrome where single-agent herbal therapy has not produced dramatic results, and urology practices that specialise in it use several treatments together.
Female Lower Urinary Tract Symptoms
Saw palmetto in women is most familiar in the contexts of androgenetic hair loss, polycystic ovary syndrome (PCOS), and hirsutism (see the Hormonal Effects & Cautions page). Its use for female LUTS is less common but has been explored for several specific indications:
- Overactive bladder in postmenopausal women — the alpha-1 antagonism and anti-inflammatory effects could theoretically reduce detrusor irritation. Small open-label observational data suggest modest benefit; controlled trials are lacking.
- Recurrent urinary tract infection prevention — some practitioners use saw palmetto adjunctively in women with recurrent urinary tract infection (UTI), on the rationale that urinary stasis from poor emptying may contribute. The evidence is anecdotal.
- Interstitial cystitis / bladder pain syndrome — the anti-inflammatory mechanism is theoretically relevant but there are no published trials. Several combination phytotherapy products marketed for interstitial cystitis contain saw palmetto.
For women, the relevant cautions are the theoretical anti-androgen mechanism (which is the basis for saw palmetto's use in polycystic ovary syndrome and hirsutism but could theoretically affect other androgen-dependent processes) and the absence of safety data in pregnancy and lactation. For premenopausal women, the same theoretical anti-androgen action is why an interaction with hormonal contraception is raised; no study has tested the combination.
Combination with Anticholinergics and Beta-3 Agonists
Patients with combined benign prostatic hyperplasia and overactive bladder — a common combination, sometimes called "mixed LUTS" — are often treated with more than one agent. Combinations with saw palmetto that practitioners describe:
- Anticholinergics (oxybutynin, tolterodine, solifenacin, darifenacin, fesoterodine, trospium) — these suppress detrusor overactivity through muscarinic receptor blockade. Combining with saw palmetto addresses both the bladder (urgency, frequency) and the prostate/outflow (weak stream, hesitancy) sides of mixed LUTS. The combination is generally well tolerated. The known additive effects are dry mouth, constipation, and (in older patients) cognitive effects from the anticholinergic component. Anticholinergic burden is now a recognized risk factor for dementia in older adults.
- Mirabegron or vibegron (beta-3 adrenergic agonists) — these suppress detrusor overactivity through a non-anticholinergic mechanism, avoiding the cognitive concerns. Combining with saw palmetto provides bladder + outflow coverage with a cleaner side effect profile, particularly for older patients. Cost is higher than anticholinergics.
- Tamsulosin or other alpha-blockers — combining saw palmetto with a prescription alpha-blocker is mechanistically redundant on the alpha-1 axis but adds the 5-alpha-reductase and anti-inflammatory components. The combination is generally well tolerated but can produce additive orthostatic hypotension (a drop in blood pressure on standing up, with dizziness).
Urology practice applies the same patient selection logic to combinations as to single agents: confirming the diagnosis, identifying the dominant symptom mechanism, choosing agents that target that mechanism, and using the lowest effective doses to limit the combined side effect burden.
Why Workup Matters Before Empiric Therapy
The most consequential mistake patients make with saw palmetto for urinary symptoms is empiric self-treatment without ruling out treatable underlying causes. The differential diagnosis of LUTS in older men includes several conditions that demand specific therapy:
- Prostate cancer — can present with LUTS identical to benign prostatic hyperplasia. A baseline prostate-specific antigen (PSA) test and digital rectal exam are part of the standard evaluation before benign prostatic hyperplasia treatment. Saw palmetto produces minimal prostate-specific antigen effect (unlike finasteride which halves prostate-specific antigen), so prostate-specific antigen screening remains interpretable on saw palmetto.
- Urinary tract infection — can produce acute LUTS that resolve with appropriate antibiotic therapy. A urinalysis and urine culture are the standard tests when symptoms are new or worsening, particularly with painful urination (dysuria) or blood in the urine (hematuria).
- Bladder cancer — can produce irritative LUTS, particularly with microhematuria. Blood in the urine is standardly investigated with imaging (computed tomography (CT) urogram) and cystoscopy regardless of urinary symptoms.
- Urethral stricture — from prior infection, trauma, or instrumentation. Produces obstructive symptoms not responsive to medical therapy.
- Neurogenic bladder — from spinal cord pathology, diabetes, or multiple sclerosis. Requires urodynamic evaluation for proper management.
- Bladder stones — can produce intermittent obstruction and irritative symptoms. Diagnosed by imaging.
- Acute urinary retention — sudden inability to pass urine, a urologic emergency that hospitals treat by draining the bladder with a catheter; herbal therapy does not act on that time scale.
The standard urologic evaluation of a man over 50 with new or worsening urinary symptoms includes a directed history, a symptom score (the International Prostate Symptom Score (IPSS) or the American Urological Association Symptom Index (AUASI)), digital rectal exam, urinalysis, prostate-specific antigen, and a measurement of post-void residual urine (bladder scan or in-office ultrasound) before medical therapy. This brief workup distinguishes benign prostatic hyperplasia from competing diagnoses in the great majority of cases and provides the baseline values needed to track response to therapy.
How the Evidence Applies by Symptom Pattern
How the urinary-function evidence and practitioner experience line up with each symptom pattern:
- Nocturia as dominant symptom — a 24-hour voiding diary distinguishes nocturnal polyuria from reduced functional capacity. With reduced capacity (most nocturia volume in daytime range, urgency-driven nighttime voiding), practitioners try saw palmetto. With nocturnal polyuria (large nighttime urine volume), saw palmetto is unlikely to help; the usual causes are sleep apnea, leg edema, peripheral venous insufficiency, late-day diuretic dosing, or heart problems.
- Urgency and frequency as dominant symptoms — practitioners use saw palmetto alone or with mirabegron or an anticholinergic, judging the result after 8–12 weeks. The CAMUS trial found no benefit over placebo after 72 weeks.
- Obstructive symptoms (weak stream, hesitancy) as dominant — saw palmetto is used for mild cases; tamsulosin or alfuzosin for moderate-to-severe cases; an alpha-blocker plus finasteride or dutasteride for advanced cases or a large prostate.
- Mixed LUTS with both obstructive and irritative components — often treated with a combination from the start; saw palmetto plus an anticholinergic or mirabegron is one low-risk combination practitioners use.
- Post-prostatectomy symptoms — treatable mechanical causes (stricture, contracture) are ruled out by urologic evaluation; saw palmetto is used as an add-on to pelvic floor physical therapy and standard post-surgical care.
- Chronic prostatitis / CPPS — treated with several approaches together. Saw palmetto can be one component; on its own it showed no benefit in the one year-long trial.
Key Research Papers
- Wilt TJ, Ishani A, Stark G, et al. (1998). Saw palmetto extracts for treatment of benign prostatic hyperplasia: a systematic review. JAMA 280(18):1604-9. — PubMed PMID: 9820264
- Vinarov AZ, Spivak LG, Platonova DV, Rapoport LM, Korolev DO (2019). 15 years' survey of safety and efficacy of Serenoa repens extract in benign prostatic hyperplasia patients with risk of progression. Urologia 86(1):17-22. — PubMed PMID: 29741118
- Suter A, Saller R, Riedi E, Heinrich M (2013). Improving BPH symptoms and sexual dysfunctions with a saw palmetto preparation? Results from a pilot trial. Phytotherapy Research 27(2):218-26. — PubMed PMID: 22522969
- Kaplan SA, Volpe MA, Te AE (2004). A prospective, 1-year trial using saw palmetto versus finasteride in the treatment of category III prostatitis/chronic pelvic pain syndrome. Journal of Urology 171(1):284-8. — PubMed PMID: 14665895
- Debruyne F, Koch G, Boyle P, et al. (2002). Comparison of a phytotherapeutic agent (Permixon) with an alpha-blocker (Tamsulosin) in the treatment of benign prostatic hyperplasia: a 1-year randomized international study. European Urology 41(5):497-506. — PubMed PMID: 12074791
- Bayne CW, Donnelly F, Ross M, Habib FK (1999). Serenoa repens (Permixon): a 5alpha-reductase types I and II inhibitor — new evidence in a coculture model of BPH (laboratory study). Prostate 40(4):232-41. — PubMed PMID: 10420151
- Goepel M, Hecker U, Krege S, Rübben H, Michel MC (1999). Saw palmetto extracts potently and noncompetitively inhibit human alpha1-adrenoceptors in vitro. Prostate 38(3):208-15. — PubMed PMID: 10068345
- Paubert-Braquet M, Mencia Huerta JM, Cousse H, Braquet P (1997). Effect of the lipidic lipidosterolic extract of Serenoa repens (Permixon) on the ionophore A23187-stimulated production of leukotriene B4 (LTB4) from human polymorphonuclear neutrophils (laboratory study). Prostaglandins Leukotrienes and Essential Fatty Acids 57(3):299-304. — PubMed PMID: 9384520
- Glemain P, Coulange C, Billebaud T, et al. (2002). Tamsulosin with or without Serenoa repens in benign prostatic hyperplasia: the OCOS trial. Progrès en Urologie 12(3):395-403. — PubMed PMID: 12189745
- Carraro JC, Raynaud JP, Koch G, et al. (1996). Comparison of phytotherapy (Permixon) with finasteride in the treatment of benign prostate hyperplasia: a randomized international study of 1,098 patients. Prostate 29(4):231-40. — PubMed PMID: 8876706
- Franco JV, Trivisonno L, Sgarbossa NJ, et al. (2023). Serenoa repens for the treatment of lower urinary tract symptoms due to benign prostatic enlargement. Cochrane Database of Systematic Reviews 6:CD001423. — PubMed PMID: 37345871
- Barry MJ, Meleth S, Lee JY, et al.; CAMUS Study Group (2011). Effect of increasing doses of saw palmetto extract on lower urinary tract symptoms: a randomized trial. JAMA 306(12):1344-51. — PubMed PMID: 21954478
PubMed Topic Searches
Connections
- All Herbs
- Saw Palmetto Overview
- Saw Palmetto Benefits Hub
- Saw Palmetto for Prostate & Benign Prostatic Hyperplasia
- Saw Palmetto for Hair Loss
- Hormonal Effects & Cautions
- Benign Prostatic Hyperplasia (BPH)
- Prostate Conditions
- Urinary Tract Infections
- Erectile Dysfunction
- Low Testosterone & TRT
- Prostate-Specific Antigen Test
- Testosterone Test
- Hormone Panel
- Zinc
- History