⚠ Evidence warning: Clinical trials or other evidence do not support the claim that saw palmetto works well for men whose benign prostatic hyperplasia matches its mechanism profile, or that it gives the immediate symptomatic relief many users report within the first week. This page keeps it as a report of what people, websites or other media say.
Saw Palmetto for Prostate Health and Benign Prostatic Hyperplasia (BPH)
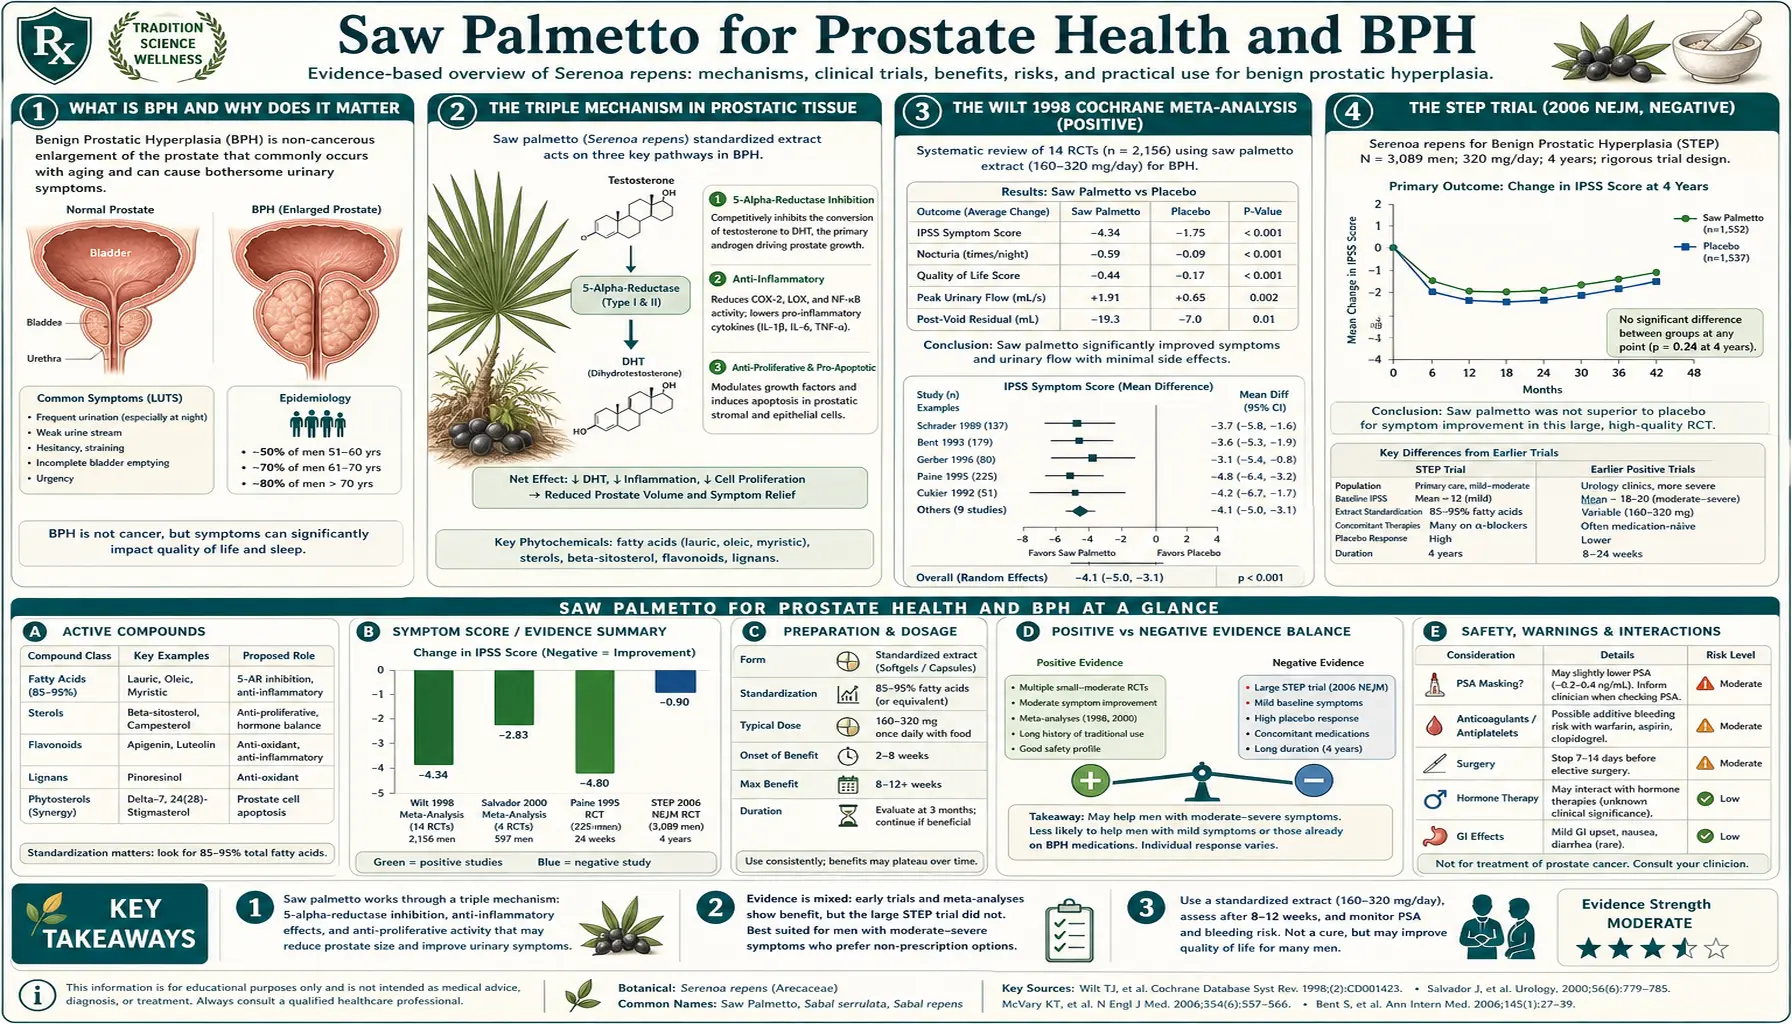
Saw palmetto is the most-studied and most-debated herbal therapy for benign prostatic hyperplasia (BPH) in the modern medical literature. The trajectory is unusual: an extensive wave of positive 1990s and early-2000s European trials of the standardized liposterolic extract reported symptom improvements roughly comparable to finasteride, leading the Wilt 1998 systematic review in JAMA (18 trials, 2,939 men) to conclude the herb was probably effective. Then two carefully designed and adequately powered American confirmatory trials — STEP (Bent 2006, NEJM) and CAMUS (Barry 2011, JAMA) — found no difference from placebo, even when CAMUS escalated dose to triple the standard. The honest take is that this is not a clear-cut "it works" or "it doesn't work" question. The most likely reconciliation involves three factors: extract quality (a hexane extract of saw palmetto, the European liposterolic preparation tested in the positive trials, differs chemically from many generic U.S. products), patient phenotype (early-disease patients with inflammation-predominant symptoms may respond; advanced-disease patients with large-volume hyperplasia probably do not), and the placebo effect being unusually large in benign prostatic hyperplasia symptom trials. This article walks through the evidence on both sides honestly.
Table of Contents
- What is Benign Prostatic Hyperplasia and Why Does It Matter
- The Triple Mechanism in Prostatic Tissue
- The Wilt 1998 JAMA Meta-Analysis (Positive)
- The STEP Trial (2006 NEJM, Negative)
- The CAMUS Trial (2011 JAMA, Negative at Triple Dose)
- Hexane Extract vs Other Extracts — The Quality Issue
- Comparison to Finasteride and Dutasteride
- Comparison to Tamsulosin (Alpha-Blocker)
- Combination Therapy and Adjunctive Use
- Symptom Severity and the Trial Evidence
- Key Research Papers
- Connections
- Featured Videos
What is Benign Prostatic Hyperplasia and Why Does It Matter
Benign prostatic hyperplasia (BPH) is the most common urological condition of aging men. By age 60, approximately 50% of men have histologic benign prostatic hyperplasia; by age 80, that figure exceeds 80%. Roughly a quarter of those affected develop clinically significant lower urinary tract symptoms (LUTS) sufficient to warrant treatment. The clinical syndrome arises from two physically separable but clinically intertwined processes:
- Static component (mass effect) — the gland enlarges through epithelial and stromal hyperplasia driven by dihydrotestosterone (DHT), the more potent androgen produced from testosterone by 5-alpha-reductase. The enlarged transition zone physically compresses the prostatic urethra, creating mechanical obstruction.
- Dynamic component (smooth muscle tone) — the prostatic stroma and bladder neck are densely innervated by alpha-1 adrenergic receptors. Sympathetic tone increases with aging and stress, producing functional obstruction independent of gland size.
The symptoms patients actually notice fall into two categories: obstructive symptoms (weak stream, hesitancy, intermittent flow, post-void dribbling, sensation of incomplete emptying) and irritative symptoms (urinary frequency, urgency, nocturia, dysuria). Severe untreated benign prostatic hyperplasia leads to acute urinary retention, recurrent urinary tract infection, bladder stones, hydronephrosis, and eventually renal insufficiency. The International Prostate Symptom Score (IPSS) is the standard severity instrument; scores of 0-7 are mild, 8-19 moderate, 20-35 severe. The American Urological Association Symptom Index (AUASI) is essentially the same instrument under a different name and is what STEP and CAMUS used as the primary endpoint.
Treatment options include watchful waiting (for IPSS <8), saw palmetto and other phytotherapies, alpha-1 blockers (tamsulosin, alfuzosin, doxazosin), 5-alpha-reductase inhibitors (finasteride, dutasteride), combination drug therapy (dutasteride-tamsulosin), minimally invasive procedures (water vapour thermal therapy, prostatic urethral lift), and surgical resection (TURP, HoLEP, simple prostatectomy). Saw palmetto sits at the gentle end of this spectrum, with the appeal that it has been used safely for decades and avoids the sexual side effects that drive many men to discontinue finasteride.
The Triple Mechanism in Prostatic Tissue
The pharmacology of saw palmetto liposterolic extract has been characterized in both cell culture and tissue-biopsy studies. The combined effect is fundamentally a multi-mechanism modulation, not a single dominant pathway.
- 5-alpha-reductase inhibition (anti-androgen, static component) — the fatty acid fraction of the extract non-competitively inhibits both type I and type II isoforms of 5-alpha-reductase. The Marks 2001 tissue-biopsy study in Urology took prostate needle biopsies before and after a 6-month randomized trial of a saw palmetto herbal blend (saw palmetto combined with other ingredients, not saw palmetto alone) versus placebo in 40 men with symptomatic benign prostatic hyperplasia: tissue DHT fell by 32%, from 6.49 to 4.40 ng/g, in the blend group (P <0.005), with no significant change in the placebo group. The study's abstract does not report serum DHT. In the companion 2000 Journal of Urology trial of the same blend (44 men), the clinical measures were only slightly better than placebo (not statistically significant).
- Alpha-1 adrenergic blockade (dynamic component) — both binding studies and isolated tissue strip experiments have shown the fatty acid fraction antagonizes alpha-1 adrenergic receptors in bladder neck and prostatic urethral smooth muscle. The effect is weaker than tamsulosin or alfuzosin but is mechanistically the same and contributes to the immediate symptomatic relief many users report within the first week, well before any anti-androgen volume effect could occur.
- Anti-inflammatory and anti-edematous effects — saw palmetto fatty acids inhibit both cyclooxygenase (COX) and 5-lipoxygenase (5-LOX) in prostatic tissue, reducing prostaglandin and leukotriene synthesis. Chronic prostatic inflammation is now recognized as an independent contributor to benign prostatic hyperplasia symptom severity (the REDUCE trial sub-analyses established this clearly), and reducing inflammatory burden plausibly reduces irritative symptoms (urgency, frequency, dysuria) independent of any change in gland size.
A theoretical fourth mechanism — pro-apoptotic effects on prostatic epithelium — has been shown in cell culture but remains poorly characterized in vivo. The clinical-pharmacology summary is that saw palmetto produces partial (not full) inhibition across three distinct pathways simultaneously. When the patient's benign prostatic hyperplasia phenotype matches that profile — modest gland enlargement, significant inflammatory and smooth-muscle-tone contributions to symptoms — the herb works well. When the phenotype is dominated by large-volume hyperplasia, the partial DHT effect is described as insufficient, and this is the group treated with full-strength finasteride or dutasteride.
The Wilt 1998 JAMA Meta-Analysis (Positive)
Timothy Wilt and colleagues published the first comprehensive systematic review of saw palmetto for benign prostatic hyperplasia in JAMA in 1998, with subsequent Cochrane updates. The original analysis pooled 18 randomized controlled trials enrolling 2,939 men with symptomatic benign prostatic hyperplasia, comparing standardized liposterolic saw palmetto extract (typically 320 mg/day) against placebo or active comparator. The pooled results were strongly positive:
- Nocturia reduced by an average of 0.76 times per night (95% confidence interval (CI) -1.22 to -0.32; 10 studies)
- Peak urinary flow rate improved by 1.93 mL/sec (95% confidence interval 0.72-3.14)
- Self-rated symptom improvement more likely than on placebo: risk ratio for improvement 1.72 (95% CI 1.21-2.44; 6 studies)
- Side-effect profile roughly comparable to placebo and dramatically better than finasteride for sexual side effects
- Head-to-head comparison with finasteride in two trials showed similar improvement in symptom scores and peak urine flow; erectile dysfunction was more frequent with finasteride (4.9%) than with saw palmetto (1.1%)
The Wilt review was influential. It coincided with the late-1990s wave of European urology guidelines incorporating phytotherapy as a legitimate first-line option for mild-to-moderate benign prostatic hyperplasia, and it drove the sustained popularity of saw palmetto in the U.S. supplement market. The review's methodological caveats — many of the included trials were short (often 8-12 weeks), used heterogeneous extracts and dosing regimens, and were conducted primarily in Europe with a hexane extract of saw palmetto — were noted but did not prevent broad clinical adoption.
A 2012 Cochrane update by Tacklind et al. revisited the question with additional newer trials, including STEP and CAMUS, and downgraded the conclusion. The pooled effect on AUASI/IPSS shrank substantially when the larger high-quality trials were included, and the same team's 2012 summary of the update in BJU International concluded that Serenoa repens does not improve LUTS or peak urinary flow compared with placebo, even at double and triple the usual dose.
The newest Cochrane review, published in 2023 by Franco and colleagues, narrowed the question to comparisons with placebo and included 27 studies with 4,656 men (19 studies of saw palmetto alone and 8 of saw palmetto combined with other herbal agents). Using only the studies at low risk of bias, saw palmetto alone made little to no difference to urinary symptoms at 3 to 6 months (a difference of -0.90 points on the 0-35 IPSS scale; 9 studies, 1,681 men) and at 12 to 17 months (a difference of 0.07 points; 3 studies, 898 men), and the review graded this evidence as high-certainty. It probably made little to no difference to side effects (risk ratio 1.01). For products combining saw palmetto with other herbal agents, the review reported more uncertainty (low-certainty evidence). The review's conclusion: saw palmetto alone provides little to no benefit for men with lower urinary tract symptoms due to benign prostatic enlargement.
The STEP Trial (2006 NEJM, Negative)
Stephen Bent and colleagues published the STEP trial (Saw Palmetto Treatment for Enlarged Prostates) in the New England Journal of Medicine in 2006. STEP was the first methodologically rigorous American attempt to confirm the European positive trials, and the results landed like a bombshell in the integrative medicine community.
The design: 225 men aged 49 and older with moderate-to-severe symptoms of BPH (AUASI >= 8) were randomized to 160 mg of standardized saw palmetto extract twice daily (320 mg/day total, the standard European dose) or matched placebo for 12 months. The primary outcomes were change in AUASI and change in peak urinary flow at 12 months. The trial was adequately powered, used a single well-characterized extract, was double-blinded, and reported a very low loss-to-follow-up rate.
The result: no significant difference between saw palmetto and placebo on any primary or secondary outcome. AUASI improved by 0.68 points in the saw palmetto group and 0.72 points in the placebo group (essentially identical). Peak urinary flow improved similarly in both groups. There was no difference in prostate volume, prostate-specific antigen (PSA), residual urine volume, quality-of-life scores, or any of the secondary endpoints. The adverse event profile was comparable between groups.
STEP's methodological strengths were considerable, and the trial was widely interpreted as showing that the earlier European positive trials had been driven by publication bias, methodological weaknesses, or both. Critics pointed out that STEP used a standardized saw palmetto extract from a commercial producer, supplied by the National Center for Complementary and Alternative Medicine (NCCAM), which was chemically characterized but differed in unspecified ways from the European hexane-extract preparation. The extract-quality debate began in earnest here.
The CAMUS Trial (2011 JAMA, Negative at Triple Dose)
The Complementary and Alternative Medicines for Urological Symptoms (CAMUS) trial, published by Michael Barry and colleagues in JAMA in 2011, was designed specifically to address the criticism that STEP had used too low a dose. CAMUS enrolled 369 men with moderate-to-severe LUTS and randomized them to escalating doses of saw palmetto extract: 320 mg/day for 24 weeks, then 640 mg/day for the next 24 weeks, then 960 mg/day (triple the standard) for the final 24 weeks. The trial did not use STEP's extract: it used an ethanol extract of ripe, dried saw palmetto berries made by a German manufacturer (the CAMUS report contrasts this with the carbon dioxide extraction used for the STEP product), compared against matched placebo.
The result: no significant benefit of saw palmetto over placebo at any of the three doses across 72 weeks of treatment. The mean change in AUASI from baseline to 72 weeks was -2.20 in the saw palmetto group and -2.99 in the placebo group (the placebo group actually did slightly better, though not significantly). Peak flow, residual urine, prostate volume, prostate-specific antigen, and quality-of-life scores all showed no statistically significant difference. The dose-response curve was flat. The share of men whose AUASI score fell by at least 3 points at 72 weeks was 42.6% in the saw palmetto group and 44.2% in the placebo group.
CAMUS was widely interpreted as the definitive nail in the coffin of the benign prostatic hyperplasia-and-saw-palmetto hypothesis, at least as it applied to the extracts tested in American patients. The trial design directly addressed the "wrong dose" objection to STEP and still found nothing. Mainstream urology guidelines updated to reflect this, and the American Urological Association benign prostatic hyperplasia guideline currently does not recommend saw palmetto.
However, two important caveats remain. First, CAMUS used an ethanol extract and STEP a carbon dioxide extract; neither tested the hexane extract used in many of the positive European trials, leaving the extract-quality question unresolved. Second, both STEP and CAMUS enrolled men with moderate-to-severe baseline symptoms (mean AUASI ~14), which is the patient population in which finasteride or dutasteride are most often used. Whether saw palmetto helps men with mild symptoms (AUASI 8-13) who do not yet qualify for prescription therapy has not been adequately tested in a high-quality American trial.
Hexane Extract vs Other Extracts — The Quality Issue
The "extract quality" debate is more substantive than it sounds. The extract tested in most of the positive European trials (sold across Europe as a prescription phytomedicine) is produced by hexane extraction of dried Serenoa repens berries and contains a defined fatty acid and sterol profile. Most U.S. retail saw palmetto products are produced by ethanol or supercritical CO2 extraction, with significantly different chemical profiles.
A 2004 chemical comparison of 14 brands of saw palmetto extract by Habib and Wyllie, using liquid and gas chromatography, found that many brands showed a significantly different proportional content of free fatty acids, methyl and ethyl esters, long-chain esters and glycerides. Other points made in the extract-quality debate:
- The hexane extract contains roughly 85-95% free fatty acids by weight
- Some generic U.S. extracts contain as little as 40-60% free fatty acids, with the balance made up of triglycerides, waxes, and other non-bioactive lipid material
- The phytosterol content (beta-sitosterol, campesterol, stigmasterol) varies by an order of magnitude across commercial products
- STEP used a carbon dioxide extract and CAMUS an ethanol extract; neither was the hexane extract used in most of the positive European trials
- Berry-powder products (whole berry powder in a capsule) contain almost no extracted fatty acid concentrate and are not the same preparation as the standardized liposterolic extract tested in the trials
A 2018 meta-analysis limited to the hexane extract (Vela-Navarrete and colleagues) pooled 27 studies — 15 randomized controlled trials and 12 observational studies, analysed together and separately — with 5,800 men in total. Compared with placebo, men taking the extract had 0.64 fewer night-time trips to urinate and an extra 2.75 mL/s of peak urine flow. Compared with alpha-blockers, the improvement in symptom score (IPSS) was similar (weighted mean difference 0.57 points, P = 0.18). Stomach and gut upset was the most frequent side effect (mean incidence 3.8%). An earlier 2004 meta-analysis of the same extract (Boyle and colleagues; 14 randomized and 3 open-label trials, 4,280 men) found peak urine flow rose by a further 1.02 mL/s over placebo and night-time voids fell by a further 0.38.
A 2019 Russian report by Vinarov and colleagues followed 30 men at risk of benign prostatic hyperplasia progression who took a saw palmetto extract, 320 mg once a day, for 15 years, in an open study with no comparison group. It reported no progression in symptom and quality-of-life scores, prostate volume, urine flow or residual urine, and no adverse events related to the extract.
The products tested in the trials described on this page were standardized liposterolic extracts at 320 mg/day: the hexane extract in most of the positive European trials, a carbon dioxide extract in STEP and an ethanol extract in CAMUS. Some saw palmetto product labels state a free fatty acid content (for example "85% or greater"); whole-berry powder products contain the ground berry rather than an extract. Independent testing programmes check whether a supplement's contents match its label.
Comparison to Finasteride and Dutasteride
Finasteride (5 mg tablets for benign prostatic hyperplasia; 1 mg tablets for hair loss) is the prototypical 5-alpha-reductase inhibitor. It selectively inhibits type II 5-alpha-reductase and reduces serum DHT by approximately 70% and intra-prostatic DHT by 80-90%. Over 12-24 months it reduces prostate volume by approximately 20% and IPSS scores by 3-4 points, with the largest benefit in men with starting prostate volume above 40 mL.
Dutasteride is the second-generation drug that inhibits both type I and type II 5-alpha-reductase isoforms, achieving approximately 95% serum DHT suppression. Symptomatic benefit is roughly comparable to finasteride. Dutasteride is preferred in patients with very large prostates or those who have inadequate response to finasteride.
How does saw palmetto compare? On the strongest interpretation of the positive European trials, saw palmetto produces symptom improvements roughly equivalent to finasteride in mild-to-moderate benign prostatic hyperplasia, with a fraction of the sexual side effects. On the interpretation of STEP/CAMUS, saw palmetto produces no benefit at all and finasteride is dramatically superior.
The sexual side effect comparison is consistent across all studies and matters a great deal in clinical practice. In the 4-year placebo-controlled study on the finasteride (5 mg) label, during the first year impotence was reported by 8.1% of men on finasteride versus 3.7% on placebo, decreased libido by 6.4% versus 3.4%, and decreased volume of ejaculate by 3.7% versus 0.8%; in years 2 to 4, impotence (5.1% versus 5.1%) and decreased libido (2.6% versus 2.6%) were no more common than on placebo. A small but real subset of users develop persistent post-finasteride syndrome with sexual dysfunction lasting months to years after discontinuation. Saw palmetto's sexual side effect rate in controlled trials is statistically indistinguishable from placebo, and there is no recognized post-saw-palmetto persistent syndrome. This difference matters most to men for whom sexual function is a primary concern.
Comparison to Tamsulosin (Alpha-Blocker)
Tamsulosin is a selective alpha-1A adrenergic receptor antagonist that relaxes bladder neck and prostatic urethral smooth muscle. It provides rapid symptomatic relief (within 1-2 weeks) without affecting prostate volume. IPSS improvement is typically 4-6 points. Side effects include orthostatic hypotension (less than non-selective alpha-blockers but still present), retrograde ejaculation in 10-20% of users, intraoperative floppy iris syndrome (a concern for cataract surgery), and nasal congestion.
Head-to-head trials of saw palmetto versus tamsulosin have generally shown comparable symptomatic improvement in mild-to-moderate benign prostatic hyperplasia, with saw palmetto producing fewer adverse events but a slightly slower onset of benefit. The Debruyne 2002 PERMAL trial recruited 811 men with symptomatic benign prostatic hyperplasia in 11 European countries and randomized 704 of them to tamsulosin 0.4 mg/day or a hexane extract of saw palmetto 320 mg/day for 12 months. At 12 months the symptom score (I-PSS) had fallen by 4.4 points in each group, peak urine flow had risen by 1.8 mL/s with the extract and 1.9 mL/s with tamsulosin, and ejaculation disorders occurred more often in the tamsulosin group.
The mechanistic logic is consistent: saw palmetto's alpha-1 blockade is partial but contributes to the rapid symptom relief many users report, while the slower 5-alpha-reductase and anti-inflammatory effects accrue over months. Tamsulosin produces a stronger alpha-1 effect but does nothing for the underlying gland enlargement, which is why tamsulosin is often combined with a 5-alpha-reductase inhibitor in moderate-to-severe benign prostatic hyperplasia (dutasteride-tamsulosin is one such combination).
Combination Therapy and Adjunctive Use
Several combination products exist that pair saw palmetto with other phytotherapies or nutrients with prostate-relevant mechanisms:
- Saw palmetto + pygeum (Prunus africana) — pygeum bark extract has independent anti-inflammatory and anti-androgen activity in prostatic tissue. The Wilt 2002 Cochrane review of pygeum reported modest symptom benefits roughly comparable to saw palmetto.
- Saw palmetto + stinging nettle root (Urtica dioica) — nettle root contains lignans that may modulate sex hormone binding globulin (SHBG) and reduce free DHT availability. Several European combination products pair saw palmetto with nettle root.
- Saw palmetto + beta-sitosterol — isolated beta-sitosterol (a phytosterol present in saw palmetto extract) has independent evidence of benefit in benign prostatic hyperplasia (Berges 1995 Lancet, Klippel 1997). The combination provides higher phytosterol delivery than saw palmetto extract alone.
- Saw palmetto + pumpkin seed oil — pumpkin seed oil is rich in delta-7-sterols and zinc, both relevant to prostatic tissue homeostasis. The combination is popular in European phytotherapy products.
- Saw palmetto + zinc + selenium — the trace mineral additions address well-documented deficiencies in many benign prostatic hyperplasia patients. Zinc in particular is concentrated in the prostate at 10x serum levels in healthy tissue, with measurable reductions in benign prostatic hyperplasia tissue.
Saw palmetto can also be used as an adjunct to prescription benign prostatic hyperplasia therapy. Some patients on finasteride alone get partial relief and add saw palmetto for the alpha-1 and anti-inflammatory mechanisms that finasteride does not address. There are no formal interaction studies in this combination but no recognized adverse interactions either. An additive (mild) lowering of blood pressure has been raised as a possibility in men on tamsulosin who add saw palmetto; tamsulosin itself can cause orthostatic hypotension (a drop in blood pressure on standing).
Symptom Severity and the Trial Evidence
The trials on this page enrolled men in particular symptom ranges. Using the standard IPSS bands from the background section (0-7 mild, 8-19 moderate, 20-35 severe), the evidence lines up as follows:
- Milder symptoms — IPSS 8-13, small to moderate prostate (<40 mL on ultrasound). Whether saw palmetto helps this group has not been tested separately in a high-quality American trial (STEP and CAMUS enrolled men with a mean AUASI of about 14). The trials used 320 mg/day of a standardized liposterolic extract; CAMUS first raised the dose after 24 weeks. Saw palmetto's sexual side-effect rate in controlled trials did not differ from placebo, while finasteride's largest benefit is in men whose prostate is above 40 mL.
- Moderate symptoms — IPSS 14-19 with a mixed obstructive/irritative pattern. STEP and CAMUS enrolled men in this range and found no difference from placebo; most studies in the 2023 Cochrane review enrolled men with IPSS 8 to 19.
- Severe or complicated disease — IPSS >= 20, large prostate (>60 mL), elevated prostate-specific antigen requiring workup, recurrent acute urinary retention, post-void residual >200 mL, bladder stones, hydronephrosis. CAMUS enrolled men with AUASI scores of 8 to 24; the complications listed here are those the background section names as consequences of severe untreated disease, and in standard urology care they are treated with prescription combination therapy or procedures. Sudden inability to pass urine (acute urinary retention) is a sign hospitals treat as urgent.
- Conditions with look-alike symptoms — chronic prostatitis, neurogenic bladder, urethral stricture and bladder cancer can cause the same urinary symptoms as benign prostatic hyperplasia. Saw palmetto has not been shown to treat any of them, and time spent on it can delay finding the real cause.
On the size of the effect: in CAMUS, 42.6% of men on saw palmetto and 44.2% on placebo improved by at least 3 points on the symptom score, and the 2023 Cochrane review found high-certainty evidence that saw palmetto alone makes little to no difference to urinary symptoms compared with placebo.
Key Research Papers
- Wilt TJ et al. (1998). Saw palmetto extracts for treatment of benign prostatic hyperplasia: a systematic review. JAMA. — PubMed PMID: 9820264
- Bent S et al. (2006). Saw palmetto for benign prostatic hyperplasia (STEP trial). NEJM. — PubMed PMID: 16467543
- Barry MJ et al. (2011). Effect of increasing doses of saw palmetto extract on lower urinary tract symptoms (CAMUS trial). JAMA. — PubMed PMID: 21954478
- Tacklind J et al. (2012). Serenoa repens for benign prostatic hyperplasia. Cochrane Database of Systematic Reviews 12:CD001423. — PubMed PMID: 23235581
- MacDonald R et al. (2012). Serenoa repens monotherapy for benign prostatic hyperplasia (BPH): an updated Cochrane systematic review. BJU International 109(12):1756-61. — PubMed PMID: 22551330
- Franco JV et al. (2023). Serenoa repens for the treatment of lower urinary tract symptoms due to benign prostatic enlargement. Cochrane Database of Systematic Reviews 6:CD001423. — PubMed PMID: 37345871
- Marks LS et al. (2001). Tissue effects of saw palmetto and finasteride: use of biopsy cores for in situ quantification of prostatic androgens. Urology 57(5):999-1005. — PubMed PMID: 11337315
- Marks LS et al. (2000). Effects of a saw palmetto herbal blend in men with symptomatic benign prostatic hyperplasia. Journal of Urology 163(5):1451-6. — PubMed PMID: 10751856
- Debruyne F et al. (2002). Comparison of a phytotherapeutic agent (Permixon) with an alpha-blocker (Tamsulosin) in the treatment of benign prostatic hyperplasia: a 1-year randomized international study (PERMAL trial). European Urology 41(5):497-506. — PubMed PMID: 12074791
- Vinarov AZ et al. (2019). 15 years' survey of safety and efficacy of Serenoa repens extract in benign prostatic hyperplasia patients with risk of progression. Urologia 86(1):17-22. — PubMed PMID: 29741118
- Habib FK et al. (2005). Serenoa repens (Permixon) inhibits the 5alpha-reductase activity of human prostate cancer cell lines without interfering with PSA expression. International Journal of Cancer 114(2):190-4. — PubMed PMID: 15543614
- Habib FK, Wyllie MG (2004). Not all brands are created equal: a comparison of selected components of different brands of Serenoa repens extract. Prostate Cancer and Prostatic Diseases 7(3):195-200. — PubMed PMID: 15289814
- Boyle P et al. (2004). Updated meta-analysis of clinical trials of Serenoa repens extract in the treatment of symptomatic benign prostatic hyperplasia. BJU International. — PubMed PMID: 15049985
- Suter A et al. (2013). Improving BPH symptoms and sexual dysfunctions with a saw palmetto preparation? Results from a pilot trial. Phytotherapy Research 27(2):218-26. — PubMed PMID: 22522969
- Vela-Navarrete R et al. (2018). Efficacy and safety of Serenoa repens (Permixon) for the treatment of lower urinary tract symptoms suggestive of BPH: systematic review. BJU International. — PubMed PMID: 29694707
- Plosker GL, Brogden RN (1996). Serenoa repens (Permixon). A review of its pharmacology and therapeutic efficacy in benign prostatic hyperplasia. Drugs & Aging. — PubMed PMID: 8922564
PubMed Topic Searches
Connections
- All Herbs
- Saw Palmetto Overview
- Saw Palmetto Benefits Hub
- Saw Palmetto for Hair Loss
- Saw Palmetto for Urinary Function
- Hormonal Effects & Cautions
- Benign Prostatic Hyperplasia (BPH)
- Prostate Conditions
- Erectile Dysfunction
- Urinary Tract Infections
- Low Testosterone & TRT
- Prostate-Specific Antigen Test
- Testosterone Test
- Hormone Panel
- Zinc
- History