Saw Palmetto for Hair Loss
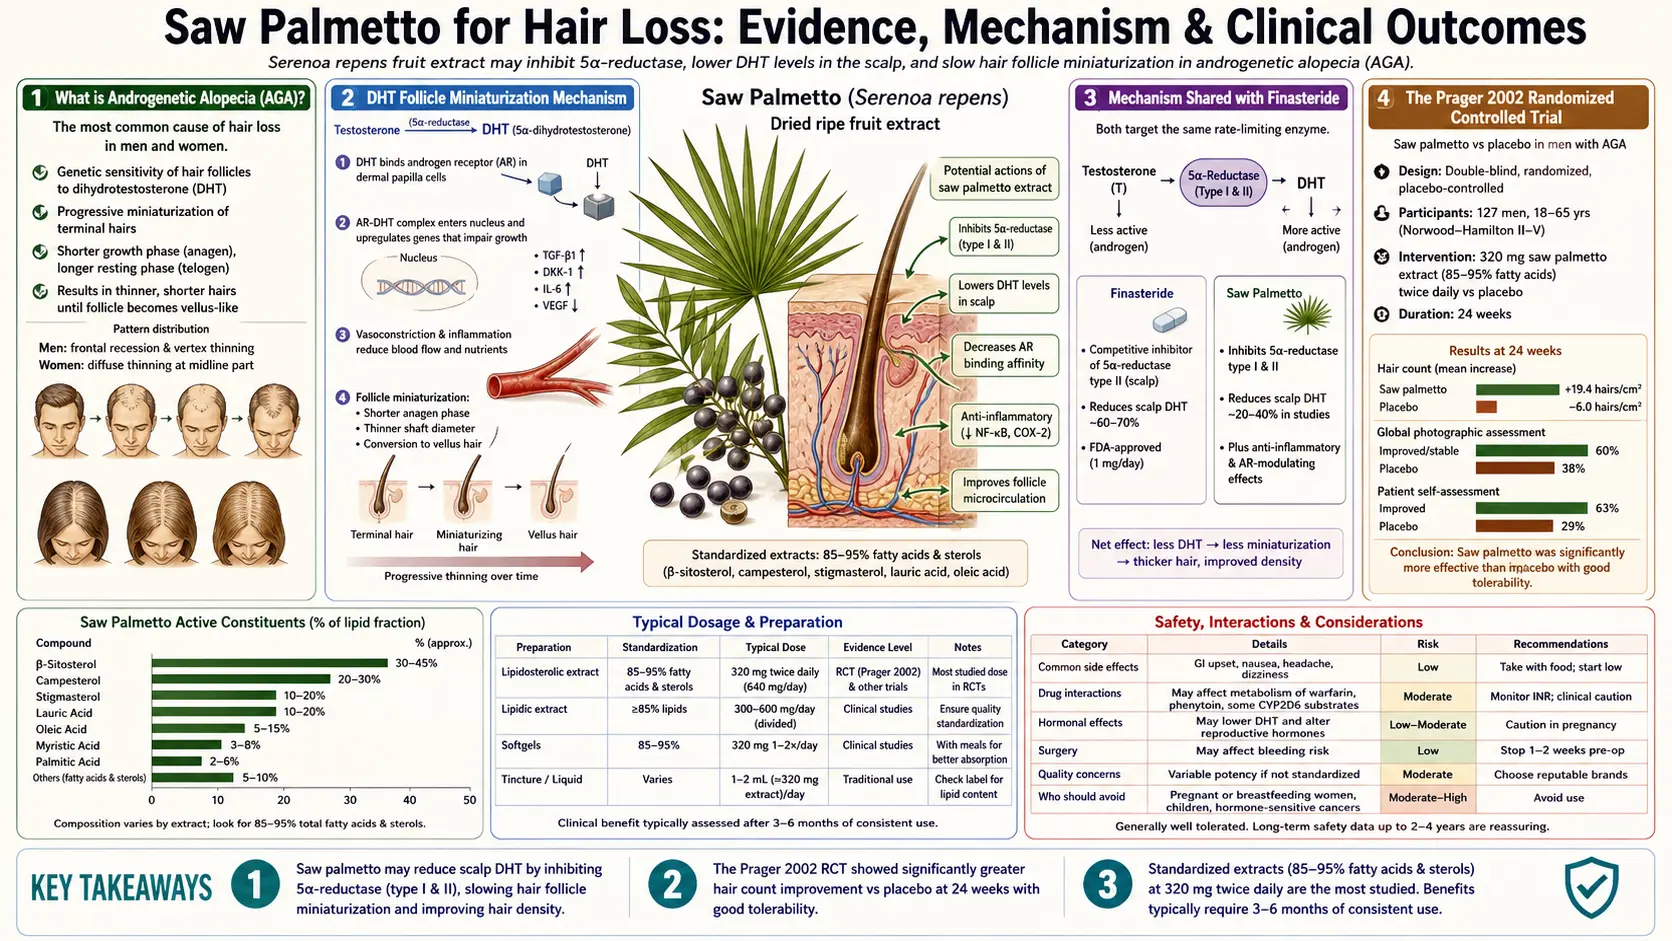
Androgenetic alopecia — male-pattern and female-pattern hair loss — is driven by the same dihydrotestosterone (DHT) mechanism that drives benign prostatic hyperplasia, just expressed in a different tissue. Genetically susceptible hair follicles in the temples, vertex, and crown produce 5-alpha-reductase locally and convert testosterone into DHT, which progressively miniaturizes those follicles over years to decades. The DHT-blocking logic that underlies the prescription standard finasteride is precisely the same logic that drives saw palmetto's use for hair loss. The randomized controlled evidence base is thinner than for benign prostatic hyperplasia (BPH) but more consistently positive — the small Prager 2002 pilot trial reported that 6 of 10 men on a saw palmetto and beta-sitosterol formula were rated improved, and later open-label studies have reported smaller but positive findings. The honest framing: in the one two-year head-to-head study, 38% of men on saw palmetto had increased hair growth against 68% on oral finasteride, and saw palmetto has a much better tolerability profile and no recognized post-discontinuation persistent syndrome, taking 6-12 months to show benefit and requiring lifelong continuation.
Interactive Visualization Hair Growth & Loss — shrink a follicle with DHT, or shed on a three-month delay Cycle a scalp of follicles through anagen, catagen and telogen, then miniaturize them with DHT year by year — or dump them all into shedding three months after a stressor. Launch →
Table of Contents
- What is Androgenetic Alopecia
- The DHT Follicle Miniaturization Mechanism
- Mechanism Shared with Finasteride
- The Prager 2002 Randomized Controlled Trial
- Subsequent Observational and Open-Label Data
- Topical Saw Palmetto vs Oral
- Comparison to Finasteride
- Combination with Minoxidil
- Realistic Timeline and Expectations
- Female-Pattern Hair Loss
- Key Research Papers
- Connections
- Featured Videos
What is Androgenetic Alopecia
Androgenetic alopecia (AGA) is the most common cause of hair loss in both men and women. By age 50, approximately 50% of men show clinically evident male-pattern baldness; lifetime prevalence in men approaches 80%. In women, the corresponding female-pattern hair loss (FPHL) affects roughly 30% by age 70, typically with diffuse thinning of the central scalp rather than the receding hairline and crown balding seen in men.
The clinical pattern in men follows the Hamilton-Norwood scale: stage I (no recession) progressing through frontal-temporal recession, vertex thinning, and eventual confluent baldness sparing only the occipital horseshoe of permanent terminal hairs. The classification has prognostic and therapeutic value — early-stage AGA (Norwood I-III) is the population most likely to respond to medical therapy, while late-stage AGA (Norwood VI-VII) has too few viable miniaturized follicles remaining for medical therapy to restore meaningful hair.
The underlying biology is a genetically programmed sensitivity of follicles in the androgen-sensitive scalp regions (frontal, vertex) to dihydrotestosterone. The occipital follicles are genetically resistant to DHT — which is why hair transplants from the occipital donor area to the bald frontal region thrive permanently, and why DHT-blocking medications spare the occipital region from any effect, beneficial or otherwise.
The DHT Follicle Miniaturization Mechanism
Androgen-sensitive follicles in the scalp express 5-alpha-reductase (both type I and type II isoforms, with type I more abundant in scalp than in prostate) and androgen receptors. Circulating testosterone freely diffuses into the follicle, is locally converted to DHT, and binds to the androgen receptor. The DHT-AR complex then translocates to the nucleus and modifies the transcription of dozens of follicle-relevant genes.
The net effect on a susceptible follicle is progressive miniaturization across consecutive hair cycles. Each anagen (growth) phase becomes shorter, the resulting hair shaft becomes thinner and shorter, and the follicle eventually produces only a fine vellus hair instead of a terminal hair. Over years to decades, the affected scalp region transitions from full terminal-hair coverage to fine vellus hairs that are clinically invisible at conversational distance. The follicle is never actually destroyed (which is why medical therapy can produce some regrowth even years into AGA) — it is merely deactivated to vellus production.
Several therapeutic approaches address this mechanism at different steps:
- Reduce local DHT — the 5-alpha-reductase inhibitor approach. Finasteride (oral 1 mg, type II selective) and dutasteride (oral 0.5 mg, dual type I and II) reduce serum and follicular DHT. Saw palmetto produces partial inhibition of both isoforms.
- Block androgen receptor — spironolactone (oral, often used in women) and topical antiandrogens compete with DHT for binding to the receptor.
- Stimulate follicle metabolism directly — minoxidil (topical 2-5%) and oral low-dose minoxidil (0.25-2.5 mg) open potassium channels in follicle vasculature and prolong anagen. This works through a non-androgen mechanism and is complementary to DHT-blocking agents.
- Reduce inflammation — ketoconazole shampoo, low-level laser therapy, and others may contribute by addressing the perifollicular inflammation present in some AGA patients.
Mechanism Shared with Finasteride
Saw palmetto and finasteride share the 5-alpha-reductase inhibition mechanism but differ substantially in potency and selectivity:
- Finasteride — selective type II inhibitor (the dominant isoform in prostate; secondary in scalp). Oral 1 mg daily suppresses serum DHT by about 65% within 24 hours, according to the drug label, and scalp DHT by approximately 60%. Effect persists for the lifetime of treatment; DHT rebounds within weeks of discontinuation.
- Dutasteride — dual type I and II inhibitor. Oral 0.5 mg daily reduces serum DHT by approximately 95%. Off-label for AGA in the U.S.; approved in some countries including South Korea and Japan.
- Saw palmetto — non-competitive inhibitor of both type I and type II, with modest potency. In the Marks 2001 biopsy study, a saw palmetto herbal blend taken for 6 months by 40 men with benign prostatic hyperplasia lowered prostate-tissue DHT by 32% (6.49 to 4.40 ng/g); serum DHT changes are usually reported as small, though a 2023 trial of an oral saw palmetto oil found lower serum DHT than placebo. Scalp-level effects have not been directly measured in biopsy studies but are inferred from clinical hair-density outcomes.
The relevant therapeutic insight: finasteride's 65% DHT reduction is far more than necessary to halt AGA progression in most patients. The dose-response curve flattens above approximately 40% DHT reduction. Saw palmetto's partial inhibition may be sufficient for many patients while remaining below the threshold at which systemic anti-androgen side effects (libido reduction, erectile dysfunction, ejaculatory disorders, gynecomastia) become clinically apparent.
This is the mechanistic basis for the consistent observation that saw palmetto produces hair-density improvement in a substantial fraction of users with essentially no recognized sexual side effects — in contrast to finasteride, for which the drug label reports an increase in hair, rated by an independent panel from photographs, in 48% of men at 12 months and 66% at 2 years (7% on placebo), drug-related sexual side effects in 3.8% of men in the first year (2.1% on placebo), and persistent sexual symptoms after stopping in a small but real subset.
The Prager 2002 Randomized Controlled Trial
The Prager 2002 trial published in the Journal of Alternative and Complementary Medicine is the foundational randomized controlled evidence for saw palmetto in androgenetic alopecia. The abstract calls it a pilot study; an erratum to the paper was published in 2006. The design:
- Men aged 23-64 in good health with mild-to-moderate AGA; 10 received the active formula
- Randomized, double-blind, to a botanical 5-alpha-reductase inhibitor combination of saw palmetto liposterolic extract and beta-sitosterol, or placebo
- Outcome assessed by blinded investigator photograph review using a 7-point change scale (very much worse to very much better) and by self-report
The results were striking for such a small trial: 6 of 10 men (60%) given the active formula were rated as improved at the final visit by blinded investigative staff. No adverse events of consequence were reported in either group. Sexual function was not formally measured but no spontaneous reports of dysfunction emerged.
The trial has obvious limitations — small sample size, relatively short follow-up, combination product rather than saw palmetto alone, primary outcome based on photograph review rather than hair counts. But the magnitude of the effect and the alignment with the established DHT-blocking mechanism made it a watershed paper for the integrative dermatology community. In the larger two-year Rossi study, the response to saw palmetto was lower: 38% of men improved.
Subsequent Observational and Open-Label Data
Later studies and reviews:
- Rossi 2012 — open-label study of 100 men with mild-to-moderate AGA taking oral saw palmetto 320 mg/day or finasteride 1 mg/day for 2 years. Judged on global photographs, 38% of men on saw palmetto had increased hair growth, against 68% on finasteride; finasteride acted at both the front and the crown (vertex), saw palmetto mainly at the crown. The authors conclude saw palmetto could improve AGA while finasteride confirmed its efficacy.
- Wessagowit 2016 — Thai pilot study, open and without placebo: 50 men aged 20-50 used topical saw palmetto products for 24 weeks; average hair count and terminal hair count rose at weeks 12 and 24, with limited side effects.
- Murugusundram 2009 — a two-page commentary, not a study: it notes saw palmetto is widely advertised for hair loss, that self-medication risks missing early prostate cancer, and that there is little evidence of efficacy, calling for larger trials.
- Evron 2020 — systematic review of saw palmetto in alopecia: 5 randomized trials and 2 prospective cohort studies of topical and oral products (100-320 mg) reported a 60% improvement in overall hair quality, a 27% improvement in total hair count, increased hair density in 83.3% of patients and stabilised disease in 52%. Saw palmetto was well tolerated, but the authors note that robust high-quality data are lacking.
- Sudeep 2023 — double-blind, placebo-controlled trial in 80 men and women aged 18-50 with mild-to-moderate AGA: a standardized saw palmetto oil as a 400 mg capsule, or a 20% topical formulation, daily for 16 weeks cut hair fall from baseline by up to 29% (oral) and 22% (topical) and raised hair density by 5.17% and 7.61%; the oral form lowered serum DHT against placebo, and no serious side effects were seen. Most of the authors work for the extract's manufacturer.
- Gupta 2026 — network meta-analysis of 23 studies of off-label treatments for male AGA (6-month change in hair density): topical minoxidil 5% ranked most effective, and topical saw palmetto was among the other treatments showing benefit; the authors call for better comparative trials.
The cumulative evidence picture: saw palmetto produces measurable improvement in androgenetic alopecia in a substantial fraction of users (38% in the two-year Rossi study; 6 of 10 men in the small Prager pilot), with effect sizes smaller than oral finasteride but achieved with a far more favorable tolerability profile. The evidence base is admittedly thin compared to the dense randomized-trial evidence for finasteride, but it is internally consistent across multiple study designs and aligns with the established DHT-blocking mechanism.
Topical Saw Palmetto vs Oral
Saw palmetto is available in both oral capsule and topical (lotion, shampoo, scalp serum) formulations. The relative merits:
- Oral 320 mg/day — the dose used in the two-year Rossi study; the trials in the Evron review used 100-320 mg. A saw palmetto herbal blend lowered prostate-tissue DHT by 32% in a biopsy study (Marks 2001), and comparable scalp DHT reduction is inferred. Six to twelve months to clinically visible effect on hair. Side effect profile essentially comparable to placebo in controlled trials. Cost roughly $0.30-$0.80 per day for verified high-quality 85%+ free fatty acid product.
- Topical (typically 1-5% saw palmetto extract in lotion or scalp serum) — the theoretical advantage is targeted delivery to scalp follicles without systemic absorption. The practical reality is that the published evidence base is much thinner than for oral, several topical products have proprietary formulations that are not chemically characterized, and the question of whether the active fatty acids actually penetrate the scalp barrier to reach the follicle target depth has not been rigorously answered.
- Saw palmetto shampoo (typically 0.5-2%) — the contact time of shampoo with scalp is far too brief (1-3 minutes) for meaningful absorption of fatty acid actives. Shampoos may have some adjunctive value through ketoconazole-like anti-inflammatory effects on the scalp, but there is no evidence for them as primary therapy.
What the published evidence covers: most of the trials used an oral standardized liposterolic extract (320 mg/day in the two-year Rossi study); topical minoxidil adds a separate, non-androgen mechanism; and topical saw palmetto has a thinner but growing evidence base, with a 2023 placebo-controlled trial and a 2026 network meta-analysis both reporting benefit.
Comparison to Finasteride
Finasteride 1 mg/day (the U.S. Food and Drug Administration-approved dose for AGA) remains the most extensively evidenced oral medical therapy for AGA. In the dose-ranging studies, 1 mg and 5 mg worked about equally and better than 0.2 mg, while 0.01 mg was no better than placebo (Roberts 1999). The trade-offs between finasteride and saw palmetto:
- Efficacy — finasteride: in the drug label's trials, an independent panel rating photographs found an increase in hair in 48% of men at 12 months and 66% at 2 years (7% on placebo); at 5 years 48% had more hair and 42% no further visible loss. Saw palmetto: 38% had increased hair growth after 2 years in the Rossi study, with somewhat smaller magnitude per responder. In that head-to-head study, 68% of men on finasteride improved against 38% on saw palmetto.
- Sexual side effects — finasteride: in the label's first-year trial data (945 men against 934 on placebo), decreased libido 1.8% vs 1.3%, erectile dysfunction 1.3% vs 0.7% and ejaculation disorder 1.2% vs 0.7%; 3.8% had one or more, against 2.1% on placebo. Persistent symptoms after stopping are reported in a minority — in one retrospective study of over 400 men on 1 mg, 0.8% had persistent erectile dysfunction (Nestor 2021 review). Saw palmetto: rates in controlled trials are statistically indistinguishable from placebo. No recognized persistent syndrome.
- Gynecomastia risk — finasteride: in the hair-loss trials, breast tenderness and enlargement were no more common than on placebo, according to the label, which lists them among post-marketing reports. Saw palmetto: no reported cases in the controlled literature.
- Prostate cancer interaction — finasteride lowers prostate-specific antigen (PSA) by approximately 50%, requiring physicians to double the measured prostate-specific antigen when interpreting cancer screening tests. Finasteride may shift detected cancers toward higher Gleason grades (the PCPT debate). Saw palmetto produces minimal prostate-specific antigen effect and does not complicate prostate cancer screening.
- Cost — finasteride: generic 1 mg costs approximately $0.30-$1.00/day depending on source. Saw palmetto: approximately $0.30-$0.80/day for verified high-quality product. Both are affordable.
- Discontinuation pattern — both medications require continuous lifetime use to maintain benefit; both produce hair loss reversion to baseline within 12 months of discontinuation. Persistent post-finasteride syndrome is a minority outcome but is the most serious dealbreaker for some patients.
In summary: finasteride produces more reliable and stronger benefit, with a sexual side-effect risk of a few percent that leads many men to decline or stop it. Saw palmetto produces less reliable benefit with no recognised sexual side-effect signal in its trials, and it is the option men turn to when they decline finasteride or stopped it because of side effects.
Combination with Minoxidil
Minoxidil (topical 2% or 5%) and oral low-dose minoxidil (0.25-2.5 mg) work through a non-androgen mechanism — potassium channel opening, follicle vascular bed dilation, and prolongation of the anagen growth phase. The mechanism is entirely complementary to DHT-blocking agents, and the combination of minoxidil with finasteride or saw palmetto is generally superior to either monotherapy.
The standard practice in AGA management is to use minoxidil and a DHT-blocker together from the start, on the rationale that the two address different aspects of the underlying pathology. For people choosing saw palmetto over finasteride, the combination practitioners describe is saw palmetto 320 mg/day oral + minoxidil 5% topical once or twice daily (or oral minoxidil 0.25-1.25 mg/day for those who cannot tolerate topical).
The realistic timeline with combination therapy: minoxidil produces visible effects faster (3-6 months) than saw palmetto (6-12 months), so the early benefit is largely from minoxidil and the late stabilization and longer-term maintenance is largely from saw palmetto. Some patients see a transient increase in shedding (telogen effluvium) during the first 4-8 weeks of minoxidil — this is the cycle synchronization effect of pushed-into-anagen follicles, not a sign that the treatment is failing, and resolves spontaneously.
Realistic Timeline and Expectations
Saw palmetto for AGA is a long-term commitment, not a quick fix. The typical course:
- Months 0-3 — no visible change. The therapeutic effect is mediated by changes in follicle cycle behavior over multiple cycles, and visible hair shaft changes lag the underlying biology by months. Month 2 is too early to judge whether it is working.
- Months 3-6 — possible reduction in shedding, possible early sense of slightly thicker hair. Reduced shedding is often the first noticeable change. Reduced shedding without visible regrowth is a real treatment response — it means the follicle cycle is normalizing.
- Months 6-12 — visible hair density improvement in responders. This is when photographs or the mirror show stabilization at minimum and modest regrowth in many users. Trials judge this from standardized photographs (well-lit, same camera angle and distance, dry hair) taken at the start and compared at months 6 and 12.
- Months 12-24 — continued slow improvement plateauing toward stable maintenance. The maximum benefit is usually achieved by 18-24 months and is maintained as long as treatment continues.
- Discontinuation — benefit reverses over 6-18 months back to the trajectory the patient would have been on without treatment. Saw palmetto is not curative; it is maintenance therapy that requires lifetime continuation.
The realistic expectation is "modest improvement and stabilization," not "thick full head of hair." AGA medical therapy at its best stops or modestly reverses miniaturization. It does not bring back hair that has been gone for years; for that, hair transplantation is the only effective option.
Female-Pattern Hair Loss
Female-pattern hair loss (FPHL) shares the DHT-driven follicle miniaturization mechanism with male AGA but typically presents as diffuse central scalp thinning rather than the temporal recession and vertex balding of men. The Ludwig classification (stages I-III) is the standard severity instrument. Postmenopausal women are particularly affected, as the loss of ovarian estrogen production unmasks the underlying androgen sensitivity.
Saw palmetto's use in FPHL is less well-studied than in male AGA but follows the same logic. The herb is appealing for women because oral finasteride is generally avoided in women of reproductive potential (teratogenicity concern; not approved by U.S. Food and Drug Administration (FDA) for women) and finasteride's efficacy in postmenopausal women is mixed. Spironolactone (oral, off-label) is the most-used pharmaceutical alternative for FPHL but has its own side effect profile.
Saw palmetto 320 mg/day combined with topical minoxidil 2-5% is one combination used by women with FPHL who decline or cannot use spironolactone. The 2023 Sudeep placebo-controlled trial enrolled both men and women with pattern hair loss (results above). Larger controlled trials in women are lacking.
Critically, in premenopausal women hair loss more often has an underlying cause that can be tested for — polycystic ovary syndrome (PCOS), thyroid disease, iron deficiency — and the anti-androgen effects of saw palmetto have theoretical though not documented implications for hormonal contraception. See the Hormonal Effects & Cautions page for the full safety discussion in women, including polycystic ovary syndrome and hirsutism applications.
Key Research Papers
- Prager N et al. (2002). A randomized, double-blind, placebo-controlled trial to determine the effectiveness of botanically derived inhibitors of 5-alpha-reductase in the treatment of androgenetic alopecia. Journal of Alternative and Complementary Medicine. — PubMed PMID: 12006122
- Rossi A et al. (2012). Comparative effectiveness of finasteride vs Serenoa repens in male androgenetic alopecia: a two-year study. International Journal of Immunopathology and Pharmacology. — PubMed PMID: 23298508
- Wessagowit V et al. (2016). Treatment of male androgenetic alopecia with topical products containing Serenoa repens extract. Australasian Journal of Dermatology, 57(3):e76-82. — PubMed PMID: 26010505
- Murugusundram S (2009). Serenoa repens: does it have any role in the management of androgenetic alopecia? Journal of Cutaneous and Aesthetic Surgery, 2(1):31-2. — PubMed PMID: 20300369
- Evron E et al. (2020). Natural hair supplement: friend or foe? Saw palmetto, a systematic review in alopecia. Skin Appendage Disorders. — PubMed PMID: 33313047
- Dhariwala MY, Ravikumar P (2019). An overview of herbal alternatives in androgenetic alopecia. Journal of Cosmetic Dermatology. — PubMed PMID: 30980598
- Trüeb RM (2006). Pharmacologic interventions in aging hair. Clinical Interventions in Aging, 1(2):121-9. — PubMed PMID: 18044109
- Hugo Perez BS (2004). Ketoconazole as an adjunct to finasteride in the treatment of androgenetic alopecia in men. Medical Hypotheses. A hypothesis paper on ketoconazole 2% shampoo with finasteride in men; background to the ketoconazole line above. — PubMed PMID: 14729013
- Olsen EA, Weiner MS, Delong ER, Pinnell SR (1985). Topical minoxidil in early male pattern baldness. Journal of the American Academy of Dermatology, 13(2 Pt 1):185-92. — PubMed PMID: 3900155
- Kaufman KD et al. (1998). Finasteride in the treatment of men with androgenetic alopecia. Journal of the American Academy of Dermatology. — PubMed PMID: 9777765
- Roberts JL, Fiedler V, Imperato-McGinley J, et al. (1999). Clinical dose ranging studies with finasteride, a type 2 5alpha-reductase inhibitor, in men with male pattern hair loss. Journal of the American Academy of Dermatology, 41(4):555-63. — PubMed PMID: 10495375
- Marks LS, Hess DL, Dorey FJ, Luz Macairan M, Cruz Santos PB, Tyler VE (2001). Tissue effects of saw palmetto and finasteride: use of biopsy cores for in situ quantification of prostatic androgens. Urology, 57(5):999-1005. — PubMed PMID: 11337315
- Sudeep HV, Rashmi S, Jestin TV, Richards A, Gouthamchandra K, Shyamprasad K (2023). Oral and topical administration of a standardized saw palmetto oil reduces hair fall and improves the hair growth in androgenetic alopecia subjects — a 16-week randomized, placebo-controlled study. Clinical, Cosmetic and Investigational Dermatology, 16:3251-3266. — PubMed PMID: 38021422
- Gupta AK, Compton SAH, Liddy A, Talukder M, Wang T, Bamimore MA (2026). Beyond minoxidil: off-label therapies for male androgenetic alopecia — a systematic review with network meta-analyses. Medicina (Kaunas), 62(7):1282. — PubMed PMID: 42512824
- Nestor MS, Ablon G, Gade A, Han H, Fischer DL (2021). Treatment options for androgenetic alopecia: efficacy, side effects, compliance, financial considerations, and ethics. Journal of Cosmetic Dermatology, 20(12):3759-3781. — PubMed PMID: 34741573
- Finasteride 1 mg tablets, U.S. prescribing information (adverse reactions table, clinical studies, pharmacodynamics). DailyMed, U.S. National Library of Medicine. — DailyMed label
PubMed Topic Searches
Connections
- All Herbs
- Hair Growth, Thinning & Why Hair Falls Out — interactive animation
- Saw Palmetto Overview
- Saw Palmetto Benefits Hub
- Saw Palmetto for Prostate & Benign Prostatic Hyperplasia
- Saw Palmetto for Urinary Function
- Hormonal Effects & Cautions
- Alopecia
- Hair Loss
- Polycystic Ovary Syndrome (PCOS)
- Testosterone Test
- Hormone Panel
- Zinc
- History