Boswellia for Joint Pain & Osteoarthritis
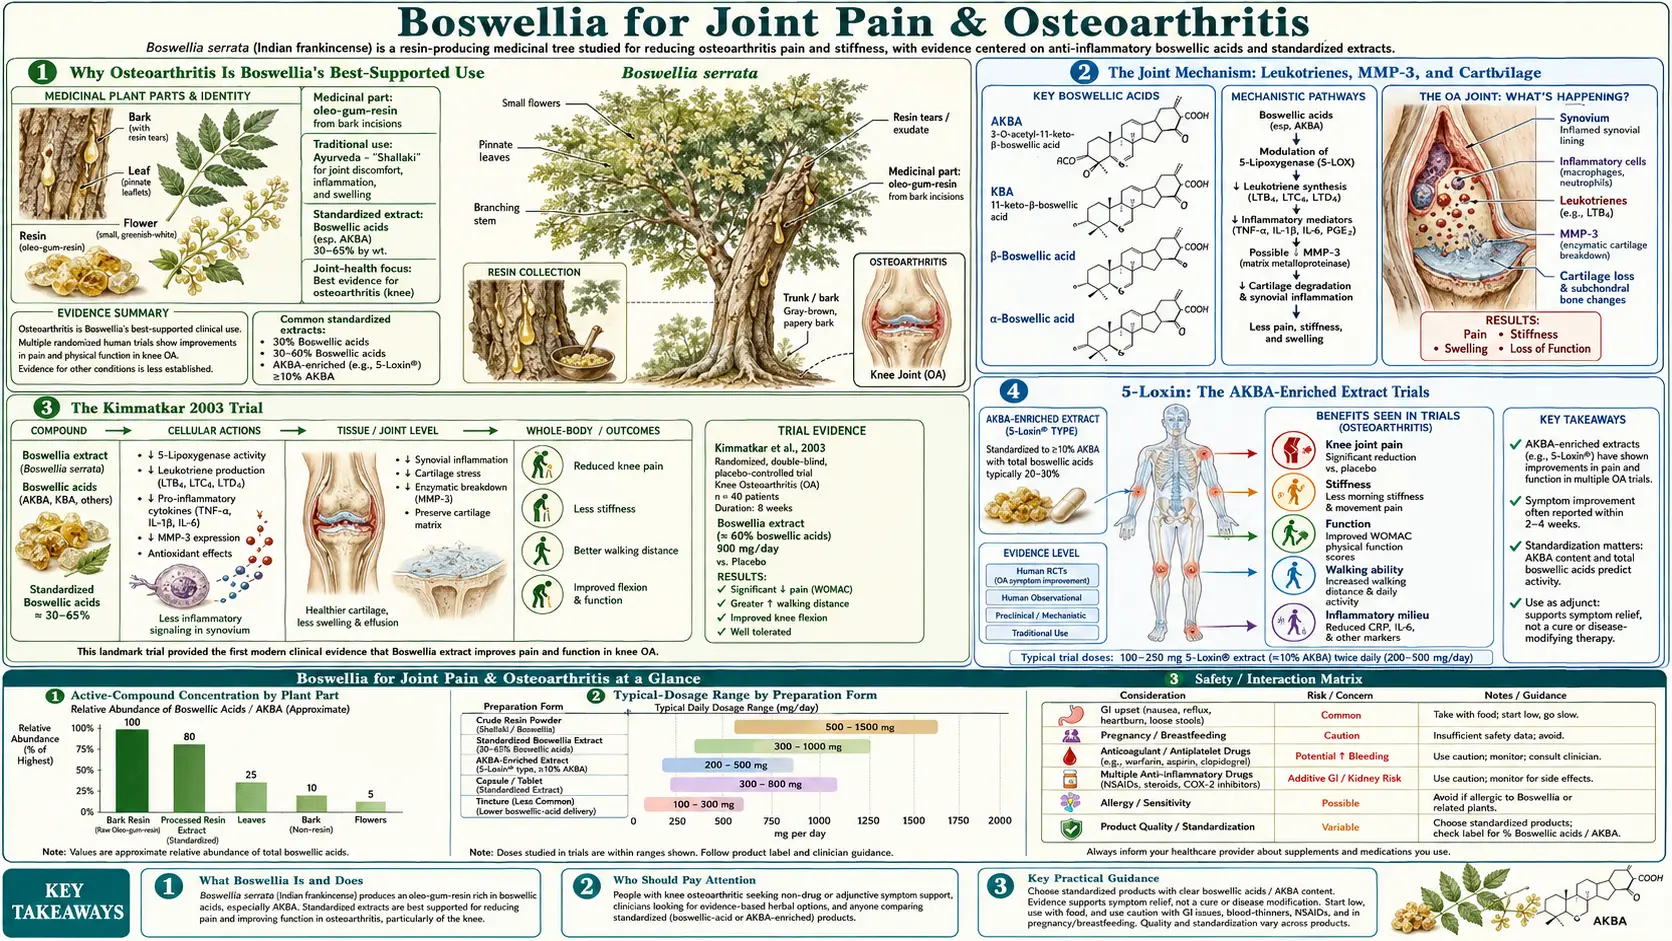
Knee osteoarthritis is the use of Boswellia with the most human research behind it. Several randomized, placebo-controlled trials — using standardized extracts such as one enriched to 30% acetyl-11-keto-β-boswellic acid (AKBA) and a faster-acting one that adds Boswellia's non-volatile oil — have reported meaningful reductions in pain and stiffness and improvements in physical function, sometimes within a week. A 2020 systematic review and meta-analysis pooling seven trials in 545 patients concluded that Boswellia may relieve pain and stiffness and improve joint function; a 2024 meta-analysis of 13 studies found no clear overall effect because the studies differed so much, though Boswellia did better than placebo. This page walks through what each trial actually measured, how large the effect is, how it compares to nonsteroidal anti-inflammatory drugs (NSAIDs) and other joint supplements, and the honest limitations — small sample sizes, heterogeneous extracts, and frequent manufacturer sponsorship.
Table of Contents
- Why Osteoarthritis Is Boswellia's Best-Supported Use
- The Joint Mechanism: Leukotrienes, MMP-3, and Cartilage
- The Kimmatkar 2003 Trial
- The AKBA-Enriched Extract Trials
- The AKBA Extract With Boswellia Oil: Faster Onset
- The 2019 Pilot Trial and the 2020 and 2024 Meta-Analyses
- How Boswellia Compares to Nonsteroidal Anti-Inflammatory Drugs and Other Supplements
- Dosing, Onset, and What to Realistically Expect
- Cautions and Limitations of the Evidence
- Key Research Papers
- External Resources
- Connections
- Featured Videos
Why Osteoarthritis Is Boswellia's Best-Supported Use
Osteoarthritis is often described as a simple wear-and-tear disease, but that picture is incomplete. Modern rheumatology recognizes a substantial inflammatory component: the synovium (the membrane lining the joint) becomes inflamed, inflammatory cells release enzymes that degrade cartilage, and pro-inflammatory signaling molecules amplify pain. This inflammatory dimension is exactly where a 5-lipoxygenase inhibitor like Boswellia has a plausible role, and it is why Boswellia has been tested more heavily in osteoarthritis than in almost any other condition.
The result is that osteoarthritis has accumulated the strongest clinical evidence base for Boswellia. Rather than one isolated study, there are multiple randomized, double-blind, placebo-controlled trials from different research groups, using several different standardized extracts, and a 2020 meta-analysis that pooled them. When several trials point the same direction, confidence rises — even if each individual trial is modest in size — though a 2024 meta-analysis of a wider set of studies found the overall picture less clear (see below).
This does not mean Boswellia is a cure or that it reverses the underlying joint damage. What the evidence supports is symptomatic relief: less pain, less stiffness, better function. For a chronic condition where the mainstay drugs carry real long-term risks to the stomach, kidneys, and heart, the authors of that 2024 meta-analysis write that people exposed to the side effects of nonsteroidal anti-inflammatory drugs could benefit from Boswellia extracts.
The Joint Mechanism: Leukotrienes, MMP-3, and Cartilage
The proposed mechanism in the joint follows directly from Boswellia's core pharmacology, covered in depth on the mechanism page. Acetyl-11-keto-β-boswellic acid (AKBA) inhibits 5-lipoxygenase, reducing the synthesis of leukotrienes such as leukotriene B4. Leukotriene B4 is a potent recruiter of neutrophils and a driver of inflammatory signaling within the inflamed synovium.
A particularly interesting finding comes from the 2008 osteoarthritis trial of the 30% AKBA extract, which reported a reduction in matrix metalloproteinase-3 (MMP-3) in the synovial fluid of treated patients. MMP-3 is one of the cartilage-degrading enzymes implicated in the structural progression of osteoarthritis. If Boswellia genuinely lowers MMP-3 activity in the joint, that raises the possibility of an effect beyond pure symptom relief — a potential influence on the degradative process itself. This remains a hypothesis rather than a proven disease-modifying effect; it has not been confirmed by long-term structural imaging trials, so it is promising rather than established.
What the mechanism does clearly explain is why the side-effect profile differs from nonsteroidal anti-inflammatory drugs. Because Boswellia works mainly on the leukotriene arm rather than by blocking the COX enzymes that protect the stomach lining and kidney blood flow, it does not carry the same signature risk of gastric ulceration seen with chronic nonsteroidal anti-inflammatory drug (NSAID) use.
The Kimmatkar 2003 Trial
One of the earliest rigorous trials was published by Kimmatkar and colleagues in Phytomedicine in 2003. It was a randomized, double-blind, placebo-controlled crossover study of a standardized Boswellia serrata extract in 30 patients with osteoarthritis of the knee, 15 starting on each treatment. Each group took its treatment for eight weeks, had a washout break, then switched to the other treatment for eight weeks. The crossover design is a useful feature: each patient received both Boswellia and placebo in sequence, so each person effectively served as their own control.
Patients taking the Boswellia extract reported a decrease in knee pain, an increase in knee flexion (range of motion), and an increase in walking distance, along with a reduced frequency of joint swelling. X-rays showed no change. When patients were switched to placebo, the benefits regressed. The extract was well tolerated, with only minor gastrointestinal complaints.
The trial is small, and it was published in a specialty phytomedicine journal rather than a major rheumatology journal, which limits the weight it carries. But as the first well-designed placebo-controlled crossover study, it set the direction that later, better-standardized trials would confirm.
The AKBA-Enriched Extract Trials
A significant advance came with a Boswellia extract deliberately enriched to contain 30% AKBA — concentrating the single most potent boswellic acid. Sengupta and colleagues published a double-blind, randomized, placebo-controlled trial of this extract in Arthritis Research & Therapy in 2008, enrolling 75 patients with knee osteoarthritis over 90 days at two dose levels (100 mg and 250 mg once daily).
Both doses produced statistically significant improvements in pain and physical-function scores compared with placebo. Notably, the 250 mg group showed measurable improvement as early as seven days — unusually fast for a botanical. The trial also reported the reduction in synovial-fluid MMP-3 discussed above. The extract was well tolerated across the study period.
Publication in Arthritis Research & Therapy, a peer-reviewed rheumatology journal, gave this trial more visibility and credibility than most earlier Boswellia studies. It is fair to note that the study was connected to the manufacturer of the standardized extract, which is common in supplement research and is why independent replication matters — but the double-blind, placebo-controlled design and the objective synovial-fluid biomarker are meaningful strengths.
The AKBA Extract With Boswellia Oil: Faster Onset
A next-generation preparation combines AKBA (at least 20%, per its trial report) with the non-volatile oil of Boswellia to improve absorption — a response to the well-known bioavailability problem of boswellic acids. Two trials examined it:
- Sengupta 2010 (International Journal of Medical Sciences) directly compared 100 mg of the 30% AKBA extract, 100 mg of the oil-combined extract, and placebo in 60 knee-osteoarthritis patients (20 per group; 57 finished) over 90 days. Both active extracts significantly improved pain and function versus placebo, and the oil-combined extract tended to work somewhat faster (significant improvement as early as seven days) and to a somewhat greater degree at the same dose — consistent with its absorption-enhancing design. The cartilage-enzyme (MMP-3) result reported for it came from laboratory cell studies (in vitro), not from patients.
- Vishal 2011 (International Journal of Medical Sciences) tested 100 mg of the oil-combined extract against placebo in 60 patients over 30 days, and reported significant improvements in pain scores and functional ability as early as five days into treatment. The trial carried a clinical-trial registration number, a marker of methodological rigor.
The recurring theme — rapid onset within days — is one of the more distinctive features of the Boswellia osteoarthritis literature and separates it from supplements like glucosamine that typically require many weeks. As with the 2008 study, these two trials were funded by the extract manufacturer, so independent confirmation strengthens the case.
The 2019 Pilot Trial and the 2020 and 2024 Meta-Analyses
More recent work has continued to support the joint indication. A 2019 pilot randomized, double-blind, placebo-controlled trial by Majeed and colleagues in Phytotherapy Research tested a standardized Boswellia serrata extract in 48 knee-osteoarthritis patients over 120 days. The treatment group showed improvements in physical function with reduced pain and stiffness compared with placebo, and the authors reported an improved knee joint gap and reduced bone spurs (osteophytes) on X-ray, lower high-sensitivity C-reactive protein (a blood marker of inflammation), and no serious adverse events. All the authors are affiliated with the companies that hold the patents and trademarks on the extract. As a small pilot, its imaging findings are exploratory rather than definitive, and the 2003 crossover trial above saw no X-ray change.
The most useful single reference for a lay reader is the 2020 systematic review and meta-analysis by Yu and colleagues in BMC Complementary Medicine and Therapies, which pooled seven randomized controlled trials involving 545 patients, comparing Boswellia with placebo or Western medicine. Its conclusion was measured and honest: Boswellia and its extracts may relieve pain and stiffness and improve joint function, with a suggested treatment duration of at least four weeks at doses of 100–250 mg. The authors also flagged the limitations of the underlying evidence — relatively small trials, varied extracts, generally medium-to-low trial quality, and no reporting of results between weeks one and four or of doses outside 100–250 mg — which is why they framed the benefit as probable rather than certain.
A 2024 systematic review and meta-analysis by Dalmonte and colleagues in Phytotherapy Research pooled 13 studies, with 850 patients scored on the Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC, a questionnaire on pain, stiffness and function) and 1,185 scored on a visual analog scale (VAS, a pain rating). Taken all together, it did not detect a significant effect (p = 0.0865 for WOMAC, p = 0.3966 for VAS), which the authors put down to how much the studies differed. When only the comparisons against placebo were examined, Boswellia groups had significantly lower WOMAC scores. The authors state that further high-quality studies are needed.
How Boswellia Compares to Nonsteroidal Anti-Inflammatory Drugs and Other Supplements
A common practical question is how Boswellia stacks up against the alternatives. Here honesty requires acknowledging what the trials do and do not show:
- Versus nonsteroidal anti-inflammatory drugs — most Boswellia trials compared it to placebo, not to a full dose of a nonsteroidal anti-inflammatory drug, so there is limited direct head-to-head data proving equivalent pain relief. What can be said is that the symptomatic improvements are clinically meaningful and that Boswellia lacks the characteristic cyclooxygenase-1-related gastric and renal risks of long-term nonsteroidal anti-inflammatory drug use. The research describes a possible gentler option for people who cannot tolerate nonsteroidal anti-inflammatory drugs, not a proven equal in analgesic power.
- Versus glucosamine and chondroitin — Boswellia's trials tend to show faster onset (days to weeks) than glucosamine, whose evidence is contested and whose benefit, if any, appears slowly.
- Combined with curcumin — several products pair Boswellia with curcumin, and some small trials of the combination report benefit. The two act on overlapping but distinct inflammatory pathways, which is a reasonable rationale, though combination trials cannot separate which ingredient does the work. A 2026 network meta-analysis by Inprasit and colleagues pooled 20 randomized trials with 1,633 people with knee osteoarthritis: modified Boswellia formulations improved WOMAC pain, stiffness and knee function compared with the other groups, while only modified turmeric formulations lowered VAS pain scores compared with placebo. Side effects did not differ significantly, and the authors write that combined preparations warrant further investigation.
- Alongside other botanicals — ginger and turmeric have their own osteoarthritis evidence and are frequently stacked with Boswellia in joint formulas.
Dosing, Onset, and What to Realistically Expect
Doses reported for these extracts:
- AKBA-enriched extracts — roughly 100–250 mg once daily, the range used in the positive trials.
- Broadly standardized Boswellia serrata extract — roughly 300–400 mg two to three times daily, standardized to a stated boswellic-acid percentage.
- Food — boswellic acids are fat-soluble, and a 2004 crossover study in healthy men found that taking an extract with a high-fat meal raised blood levels of several boswellic acids several-fold compared with fasting.
- Time frame — while some patients in trials improved within a week, the 2020 meta-analysis suggests at least four weeks to judge the effect. A rule of thumb, not a trial finding: no benefit after six to eight weeks makes later benefit unlikely.
The trials describe Boswellia as a symptom-reliever for osteoarthritis, not a regenerative therapy. What they mainly measured is a noticeable reduction in day-to-day pain and stiffness and improved ability to walk and move — not a reversal of joint damage on X-ray.
Cautions and Limitations of the Evidence
- Trial size and sponsorship — the osteoarthritis trials are individually small (typically 30–75 patients) and several were connected to extract manufacturers. This does not invalidate them, but it widens the uncertainty and makes independent replication valuable.
- Extract heterogeneity — different studies used different extracts with different AKBA content, so results are not perfectly interchangeable across products. The trial results come from extracts with a stated AKBA percentage.
- Gastrointestinal side effects — usually mild (nausea, reflux, occasional diarrhea), but not absent.
- Medication interactions — a 2022 review of herb-drug interactions rates Boswellia's interaction potential as generally low, but lists laboratory findings that it inhibits cytochrome P450 drug-processing enzymes and alters drug transport proteins, two case reports of a raised international normalized ratio (INR, the blood-clotting test) in people taking the anticoagulant warfarin, and a possible interaction with the immunosuppressants cyclosporine and tacrolimus. Among arthritis drugs, those two are the ones it names as possibly affected.
- What the trials did not test — persistent or worsening joint pain can have other causes, and these trials enrolled people with diagnosed osteoarthritis of the knee. They tested Boswellia as a supplement, and other parts of osteoarthritis care include exercise, weight management, physical therapy, and medication.
Key Research Papers
- Kimmatkar N, Thawani V, Hingorani L, Khiyani R (2003). Efficacy and tolerability of Boswellia serrata extract in treatment of osteoarthritis of knee — a randomized double blind placebo controlled trial. Phytomedicine — PubMed PMID: 12622457
- Sengupta K, Alluri KV, Satish AR, et al. (2008). A double blind, randomized, placebo controlled study of the efficacy and safety of 5-Loxin for treatment of osteoarthritis of the knee. Arthritis Research & Therapy — PubMed PMID: 18667054
- Sengupta K, Krishnaraju AV, Vishal AA, et al. (2010). Comparative efficacy and tolerability of 5-Loxin and Aflapin against osteoarthritis of the knee. International Journal of Medical Sciences — PubMed PMID: 21060724
- Vishal AA, Mishra A, Raychaudhuri SP (2011). A double blind, randomized, placebo controlled clinical study evaluates the early efficacy of Aflapin in subjects with osteoarthritis of knee. International Journal of Medical Sciences — PubMed PMID: 22022214
- Majeed M, Majeed S, Narayanan NK, Nagabhushanam K (2019). A pilot, randomized, double-blind, placebo-controlled trial to assess the safety and efficacy of a novel Boswellia serrata extract in the management of osteoarthritis of the knee. Phytotherapy Research — PubMed PMID: 30838706
- Yu G, Xiang W, Zhang T, et al. (2020). Effectiveness of Boswellia and Boswellia extract for osteoarthritis patients: a systematic review and meta-analysis. BMC Complementary Medicine and Therapies — PubMed PMID: 32680575
- Dalmonte T, Andreani G, Rudelli C, Isani G (2024). Efficacy of extracts of oleogum resin of Boswellia in the treatment of knee osteoarthritis: a systematic review and meta-analysis. Phytotherapy Research — PubMed PMID: 39314013
- Inprasit C, Bunyamahote S, Boonpattharatthiti K, et al. (2026). Evaluating the efficacy and safety of Curcuma longa, Boswellia serrata, and their mixed formulation in treating knee osteoarthritis: a systematic review and network meta-analysis. Complementary Therapies in Medicine — PubMed PMID: 41082950
- Sterk V, Büchele B, Simmet T (2004). Effect of food intake on the bioavailability of boswellic acids from a herbal preparation in healthy volunteers. Planta Medica — PubMed PMID: 15643550
- Lippert A, Renner B (2022). Herb-drug interaction in inflammatory diseases: review of phytomedicine and herbal supplements. Journal of Clinical Medicine — PubMed PMID: 35329893
- Safayhi H, Mack T, Sabieraj J, et al. (1992). Boswellic acids: novel, specific, nonredox inhibitors of 5-lipoxygenase. Journal of Pharmacology and Experimental Therapeutics — PubMed PMID: 1602379
- Ammon HP (2006). Boswellic acids in chronic inflammatory diseases. Planta Medica — PubMed PMID: 17024588
- Abdel-Tawab M, Werz O, Schubert-Zsilavecz M (2011). Boswellia serrata: an overall assessment of in vitro, preclinical, pharmacokinetic and clinical data. Clinical Pharmacokinetics — PubMed PMID: 21553931