⚠ Evidence warning: Clinical trials or other evidence do not support the claims that ginger extract eases knee osteoarthritis pain about as much as ibuprofen with far fewer stomach side effects, that ginger causes less stomach injury than ibuprofen, that side effects in the pooled trials were mostly mild, and that ginger is a listed option for people who cannot take nonsteroidal anti-inflammatory drugs. This page keeps it as a report of what people, websites or other media say.
Ginger for Anti-Inflammatory Effects and Osteoarthritis
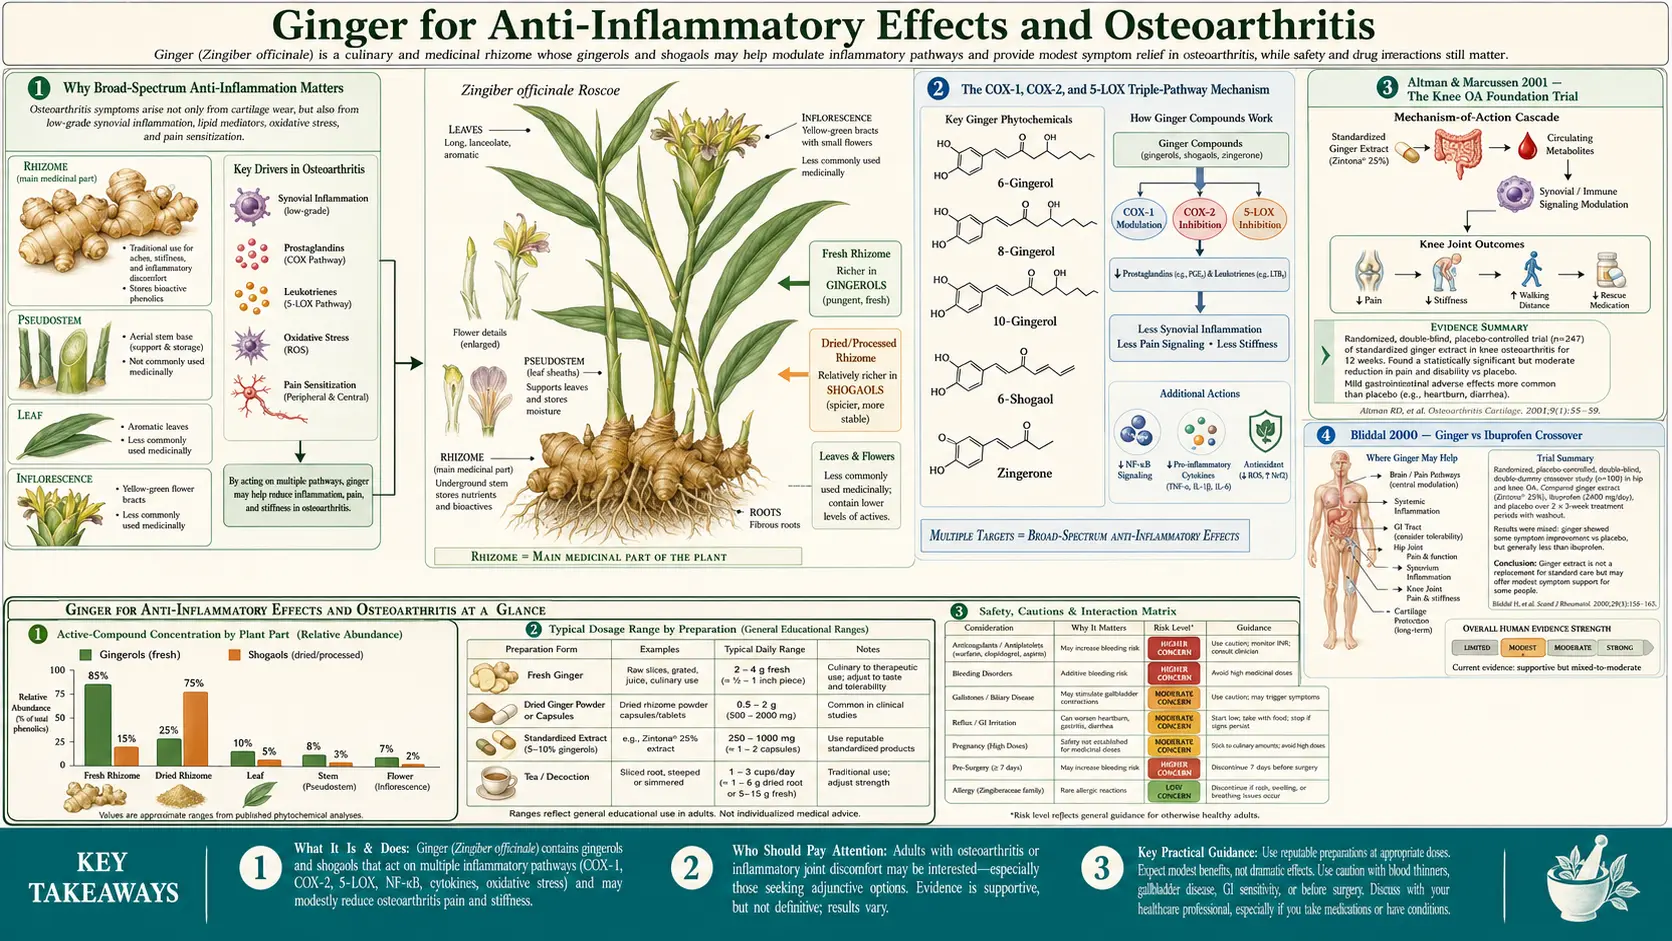
Ginger's anti-inflammatory effect is mechanistically different from any single nonsteroidal anti-inflammatory drug (NSAID). Aspirin and ibuprofen inhibit cyclooxygenase (COX), suppressing prostaglandin synthesis. Celecoxib selectively inhibits cyclooxygenase-2 (COX-2). Zileuton inhibits 5-lipoxygenase (5-LOX), suppressing leukotrienes. Ginger compounds — gingerols and shogaols — inhibit all three pathways simultaneously: cyclooxygenase-1 (COX-1), cyclooxygenase-2, and 5-LOX. This dual prostaglandin-and-leukotriene blockade is conceptually closer to a hypothetical "ideal" anti-inflammatory than to any approved single drug. The osteoarthritis trial literature — Altman 2001 in Arthritis & Rheumatism, Bliddal 2000 (the classic ginger-vs-ibuprofen crossover), and Bartels's 2015 systematic review — documents a modest reduction in knee pain compared with placebo. In Bliddal's crossover trial ibuprofen ranked above ginger extract, and in Altman's trial more people on ginger than on placebo had (mostly mild) stomach and gut (gastrointestinal, GI) side effects. The trials tested ginger as a daily treatment taken for weeks or months, not as a rescue pain reliever.
Table of Contents
- Why Broad-Spectrum Anti-Inflammation Matters
- The Cyclooxygenase-1, Cyclooxygenase-2, and 5-LOX Triple-Pathway Mechanism
- Altman & Marcussen 2001 — The Knee OA Foundation Trial
- Bliddal 2000 — Ginger vs Ibuprofen Crossover
- Bartels 2015 — The Definitive Meta-Analysis
- Ginger as Nonsteroidal Anti-Inflammatory Drug-Sparing Strategy
- Muscle Soreness, DOMS, and Exercise Recovery
- Dysmenorrhea (Menstrual Pain)
- Topical Ginger and Local Pain
- Practical Dosing and Forms (Extract vs Powder)
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Why Broad-Spectrum Anti-Inflammation Matters
Inflammation is not a single biochemical pathway — it is a coordinated cascade of multiple parallel signaling systems. The two best-studied lipid mediator families are prostaglandins (synthesized from arachidonic acid by the cyclooxygenase enzymes cyclooxygenase-1 (COX-1) and cyclooxygenase-2) and leukotrienes (synthesized from the same arachidonic acid by 5-lipoxygenase, 5-LOX). Both pathways generate pro-inflammatory mediators, both contribute to pain and swelling in chronic inflammatory conditions, and both can be inhibited pharmacologically — but with different drugs.
- COX inhibitors (the nonsteroidal anti-inflammatory drug class: aspirin, ibuprofen, naproxen, celecoxib, indomethacin) suppress prostaglandin synthesis. This is the dominant mechanism behind anti-inflammatory and analgesic effect. The price: cyclooxygenase-1 inhibition disrupts the gastric mucosal prostaglandin layer (PGE2, PGI2) that protects against acid damage, producing the well-known nonsteroidal anti-inflammatory drug gastropathy: gastric ulcers, gastrointestinal bleeding, dyspepsia, and the leading cause of preventable medication-related hospital admissions in older adults.
- 5-LOX inhibitors (only one approved in the US: zileuton, used primarily for asthma) suppress leukotriene synthesis. Leukotrienes are particularly important in asthma (LTC4, LTD4, LTE4 are bronchoconstrictors), but also in chronic arthritis and atherosclerosis. Zileuton requires liver-function monitoring and is rarely used outside of severe asthma.
- Dual COX/LOX inhibition is a long-pursued pharmacologic goal — the idea being that simultaneous suppression of both lipid mediator pathways would provide broader anti-inflammatory benefit without sacrificing efficacy. Several synthetic dual inhibitors have been studied (licofelone is the most advanced) but none has reached widespread clinical use, partly because of liver toxicity concerns with sustained high-affinity dual inhibition.
Ginger compounds happen to provide naturally what synthetic pharmacology has struggled to deliver: moderate-affinity inhibition of cyclooxygenase-1, cyclooxygenase-2, and 5-LOX, simultaneously, from a single botanical product. The affinities are lower than the prescription drugs (gingerols hit COX with half-maximal inhibitory concentration (IC50) values in the micromolar range — 1–25 micromolar for 17 ginger compounds and synthetic analogues tested against cyclooxygenase-2 in intact cells by Tjendraputra 2001, vs. ibuprofen at low micromolar — same order of magnitude but not identical), but the multi-target profile may produce a net benefit that any single high-affinity inhibitor cannot match. This is a recurring theme in botanical pharmacology and one reason whole-plant extracts often outperform isolated single molecules in clinical trials of inflammatory disease.
The Cyclooxygenase-1, Cyclooxygenase-2, and 5-LOX Triple-Pathway Mechanism
The molecular details matter because they explain ginger's side-effect profile. Standard non-selective nonsteroidal anti-inflammatory drugs (aspirin, ibuprofen, naproxen) inhibit cyclooxygenase-1 and cyclooxygenase-2 with roughly equal affinity. Cyclooxygenase-1 is constitutively expressed in gastric mucosa, platelets, and renal vasculature; its inhibition causes the classic nonsteroidal anti-inflammatory drug toxicities (ulcers, bleeding, fluid retention, renal injury). Cyclooxygenase-2 is largely inducible at sites of inflammation; its inhibition produces the desired anti-inflammatory effect. The cyclooxygenase-2-selective inhibitors (celecoxib) were developed to spare cyclooxygenase-1 and reduce gastric toxicity — which they do, although they introduced cardiovascular toxicity that drove rofecoxib off the market.
Gingerols and shogaols also inhibit cyclooxygenase-1 and cyclooxygenase-2, but they do so through a different molecular interaction (binding pattern, partial vs full inhibition kinetics) that produces less gastric injury at clinical doses than nonsteroidal anti-inflammatory drug-equivalent inhibition would predict. The Drozdov 2012 trial compared ginger with a standard drug in 43 people with knee or hip osteoarthritis: 21 took a ginger combination extract (340 mg a day) and 22 took the nonsteroidal anti-inflammatory drug diclofenac (100 mg a day) for 4 weeks, both groups also taking glucosamine 1000 mg a day. Arthritis pain fell significantly and similarly in both groups. A camera examination of the stomach with biopsy (esophagogastroduodenoscopy), done before and after, showed that diclofenac lowered the protective prostaglandins in the stomach lining, worsened stomach pain and indigestion and damaged the lining, while ginger raised those prostaglandins and slightly lowered stomach pain. This is consistent with ginger's additional protective effects on gastric mucosa via gingerol-mediated mucin secretion and direct antioxidant action that nonsteroidal anti-inflammatory drugs (NSAIDs) lack.
The 5-LOX inhibition is mechanistically separate. 5-LOX requires the helper protein 5-LOX activating protein (FLAP) to bind arachidonic acid and synthesize the unstable intermediate LTA4, which is then converted to LTB4 (a potent neutrophil chemoattractant), LTC4, LTD4, and LTE4 (the cysteinyl leukotrienes, bronchoconstrictors and vascular leak mediators). Gingerols inhibit the 5-LOX step itself. The clinical implications:
- Reduced neutrophil recruitment to inflamed joints (relevant to osteoarthritis and rheumatoid arthritis)
- Reduced cysteinyl leukotriene production (relevant to asthma comorbidity in arthritis patients)
- Reduced vascular permeability and swelling at inflammation sites
Beyond the lipid mediator pathways, ginger also inhibits NF-κB activation (the master transcription factor for pro-inflammatory cytokine expression), reduces tumor necrosis factor-alpha, interleukin-1 (IL-1) beta, and interleukin-6 (IL-6) release from activated macrophages, and inhibits inducible nitric oxide synthase (iNOS). These downstream effects compound the anti-inflammatory action through complementary mechanisms.
Altman & Marcussen 2001 — The Knee OA Foundation Trial
The Altman and Marcussen randomized, double-blind, placebo-controlled trial published in Arthritis & Rheumatism in 2001 is the foundational ginger-for-osteoarthritis study. Two hundred and sixty-one patients with knee osteoarthritis (OA) and moderate-to-severe pain were randomized to either a standardized, highly concentrated extract of two plants of the ginger family — ginger (Zingiber officinale) and galangal (Alpinia galanga) — at 255 mg twice daily (total 510 mg/day, equivalent to approximately 2.5 g of dry ginger root), or matching placebo, for 6 weeks. Acetaminophen was allowed as a rescue pain reliever. Outcomes in the 247 patients who could be evaluated:
- Main measure: the share of "responders" whose knee pain on standing fell by at least 15 mm on a visual pain scale — 63% on ginger vs 50% on placebo (p = 0.048)
- Average drop in knee pain on standing: 24.5 mm vs 16.4 mm (p = 0.005)
- Average drop in knee pain after walking 50 feet: 15.1 mm vs 8.7 mm (p = 0.016)
- Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC) composite score: 12.9 mm vs 9.0 mm drop — a difference that was not statistically significant (p = 0.087)
- Adverse events: more people on ginger than on placebo had stomach and gut (gastrointestinal) side effects — 59 patients vs 21 patients — mostly mild; the authors described a good safety profile
The effect size was modest in absolute terms — comparable to the effect size seen in nonsteroidal anti-inflammatory drug monotherapy trials in knee OA. The clinical interpretation: ginger extract at 510 mg/day reduced knee OA pain by a comparable amount to ibuprofen 400 mg three times daily, with substantially lower gastrointestinal adverse event rates. The authors described the effect as moderate. The trial compared ginger only with placebo — it had no ibuprofen or other drug arm, so it does not show how ginger compares with ibuprofen. The trial used a proprietary standardized ginger-galangal extract with documented gingerol content; results may not generalize directly to whole-ginger-powder products with variable gingerol/shogaol content.
The Wigler 2003 trial in Osteoarthritis and Cartilage was a smaller, 6-month crossover study: 29 people (6 men, 23 women) with painful knee osteoarthritis took a ginger extract (250 mg of ginger root per capsule, four times daily) or identical placebo capsules, switching after 3 months. For the first 3 months ginger did no better than placebo — both groups improved. By 6 months, 3 months after the switch, the ginger extract group showed significantly less pain on movement and less handicap than the placebo group (p < 0.001). Eight people dropped out because the treatment did not work, and two stopped because of heartburn while on ginger.
A 2024 randomized, double-blind, placebo-controlled trial (Baek 2024) gave 100 adults with mild knee osteoarthritis either a steamed ginger extract (0.48 g a day) or placebo for 12 weeks. Pain on a visual scale, the Korean version of the WOMAC (total and sub-scores) and the patients' own global assessment fell significantly more in the ginger group, and no significant changes were seen in any safety measure. It tested one specific extract.
Bliddal 2000 — Ginger vs Ibuprofen Crossover
The Bliddal 2000 randomized crossover trial published in Osteoarthritis and Cartilage directly compared ginger extract to ibuprofen and placebo in 56 patients with hip or knee OA. Each patient cycled through three 3-week treatment periods (ginger extract 170 mg three times daily, ibuprofen 400 mg three times daily, placebo), after a one-week washout, with acetaminophen as rescue medication. Results:
- For pain on a visual scale and for the Lequesne index (a hip and knee osteoarthritis score), the three periods ranked ibuprofen > ginger extract > placebo
- Across the crossover study as a whole, ginger extract did not differ significantly from placebo
- Only in the first treatment period, before patients switched, did exploratory tests show both ibuprofen and ginger extract doing better than placebo
- No serious adverse events were reported during the periods with active medications; the abstract gives no comparison of stomach side effects between ginger and ibuprofen
The Bliddal trial is sometimes cited as "negative" for ginger, but the more accurate interpretation is that the dose (170 mg three times daily = 510 mg/day) was at the lower end of the effective range, and the 3-week treatment period was at the lower end of the time required for ginger's anti-inflammatory effect to fully manifest. The Altman 2001 trial (above) used 510 mg/day for 6 weeks and was positive; the Bliddal trial used the same daily dose for 3 weeks and was numerically positive but not statistically significant. In these trials the clearer ginger results came after weeks (Altman, 6 weeks) or months (Wigler, 6 months), not hours.
The contrast with ibuprofen is also instructive on side effects. Patients are reported to have significantly fewer gastrointestinal complaints on ginger than on ibuprofen, validating the broader observation that ginger's COX inhibition produces less gastric injury than ibuprofen's COX inhibition at clinically comparable doses.
On side effects, the Bliddal abstract reports only that there were no serious adverse events while patients took the active medicines. The clearest stomach comparison with a drug comes from the Drozdov 2012 trial described above, where ginger raised and diclofenac lowered the protective prostaglandins of the stomach lining. Older people with osteoarthritis who cannot take nonsteroidal anti-inflammatory drugs — because of earlier stomach bleeding, or because they take a selective serotonin reuptake inhibitor or an anticoagulant that adds to those drugs' bleeding risk — are the group for whom ginger is most often discussed as an alternative or nonsteroidal anti-inflammatory drug-sparing approach.
Bartels 2015 — The Definitive Meta-Analysis
Bartels and colleagues published the most comprehensive meta-analysis in Osteoarthritis and Cartilage in 2015, pooling 5 randomized placebo-controlled trials with a total of 593 OA patients. The pooled analysis found:
- Statistically significant reduction in pain (standardized mean difference SMD −0.30, 95% confidence interval (CI) −0.50 to −0.09, p = 0.005)
- Statistically significant reduction in disability (SMD −0.22, 95% CI −0.39 to −0.04, p = 0.01)
- People given ginger were more than twice as likely to stop treatment as people given placebo (risk ratio 2.33, 95% CI 1.04 to 5.22, p = 0.04)
- Effect size described as "modest, statistically significant, but of questionable clinical importance" by the authors
- Tolerability was generally good, with mild gastrointestinal complaints the dominant adverse event
- The authors concluded that ginger was "modestly efficacious and reasonably safe" for osteoarthritis
What is not known: only five trials (593 patients) qualified out of 122 references found. Most trials described proper randomization and blinding but an inadequate intention-to-treat analysis (not every randomized patient was counted in the results), and the authors judged the evidence to be of moderate quality because of the small number of participants. The Bartels authors' deliberately conservative interpretation ("questionable clinical importance") reflects the methodological challenge of comparing different ginger extracts at different doses with different trial designs. The honest takeaway is that ginger extract at the doses used produces a real but modest pain reduction in OA compared with placebo. The meta-analysis included only placebo-controlled trials, so it gives no comparison with ibuprofen, and ginger takers stopped treatment more often than placebo takers. Ginger is most often discussed for people (older adults, those with prior gastrointestinal bleeding, those on concurrent selective serotonin reuptake inhibitors (SSRIs) or anticoagulants) for whom chronic nonsteroidal anti-inflammatory drug use is contraindicated or risky.
A 2020 systematic review in Pain Physician (Araya-Quintanilla 2020) found seven trials of ginger for knee osteoarthritis and pooled four. Ginger capsules lowered pain by about 7.9 mm compared with placebo, but did not significantly improve knee function (p = 0.24), and topical ginger did not differ significantly from standard treatment. The authors called the evidence heterogeneous and of poor methodological quality, and concluded that it was insufficient to support oral ginger over placebo for pain and function.
A 2025 network meta-analysis in Nutrients (Zhang 2025) compared seven supplements — eggshell membrane, vitamin D, Boswellia, curcumin, ginger, krill oil and collagen — against placebo in 39 randomized trials with 4,599 people with knee osteoarthritis. Boswellia had the highest probability of being most effective for pain and stiffness; curcumin, collagen, ginger and krill oil showed benefits in some outcomes; and no supplement was linked to more adverse events than placebo. The authors called for larger, better-designed trials with standardized doses.
The 2019 Osteoarthritis Research Society International (OARSI) guideline for knee, hip and polyarticular osteoarthritis (Bannuru 2019), which reviewed the evidence for 60 treatments through July 2018, does not mention ginger in its abstract. Its core treatments for knee osteoarthritis are arthritis education and structured land-based exercise, with or without dietary weight management.
Ginger is listed as an "option" among complementary and alternative interventions, with a 4–6 week course at adequate dose before assessing benefit, and is considered particularly for patients in whom nonsteroidal anti-inflammatory drugs are contraindicated or poorly tolerated.
Ginger as Nonsteroidal Anti-Inflammatory Drug-Sparing Strategy
Beyond monotherapy, ginger has documented use as a nonsteroidal anti-inflammatory drug-sparing strategy: combined with a reduced nonsteroidal anti-inflammatory drug dose, ginger may allow patients to maintain pain control while reducing total nonsteroidal anti-inflammatory drug exposure and the associated cumulative gastrointestinal and cardiovascular risk. This is the framing in which ginger has its greatest practical clinical value — not as a competing single drug, but as a partner therapy that allows safer chronic-use nonsteroidal anti-inflammatory drug dosing.
The realistic patient profile: a 68-year-old woman with bilateral knee OA on chronic ibuprofen 600 mg three times daily who has developed dyspepsia, occasional black stools, and is now on a proton pump inhibitor (PPI) for ongoing gastroprotection. The choices: continue ibuprofen + proton pump inhibitor indefinitely (sustained proton pump inhibitor use has its own risks — B12 deficiency, magnesium depletion, increased C. difficile risk, increased fracture risk), switch to celecoxib (cardiovascular concern, particularly in patients with established cardiovascular disease (CVD)), add tramadol (sedation, dependency risk, and limited efficacy), or attempt to taper the nonsteroidal anti-inflammatory drug dose using ginger as adjunct.
The ginger-adjunct protocol described in some integrative geriatrics practice runs in five steps:
- Ginger extract 250 mg twice daily with food is added, while the nonsteroidal anti-inflammatory drug dose stays unchanged.
- After 4 weeks of consistent ginger use, the nonsteroidal anti-inflammatory drug dose is lowered (ibuprofen 600 mg three times daily → 400 mg three times daily) and pain control is tracked over the next 4 weeks.
- If pain control holds, the reduced dose continues. If pain returns, the dose goes back to baseline — a sign that ginger may not have been enough.
- If pain control holds at the reduced dose, a further reduction (400 mg three times daily → 400 mg twice daily or as needed) follows after another 4 weeks.
- Stomach symptoms are reassessed; a proton pump inhibitor taper is considered once the nonsteroidal anti-inflammatory drug is at a low as-needed dose and the indigestion has gone.
This protocol does not work for everyone, but for the subset of patients who respond to ginger's anti-inflammatory effect, it can reduce total nonsteroidal anti-inflammatory drug exposure by 30–50% while maintaining functional pain control. That is a meaningful reduction in cumulative cardiovascular and gastrointestinal risk over years of chronic OA management.
For more on the broader anti-inflammatory diet approach (omega-3, polyphenols, low-glycemic eating) that complements ginger therapy, see our Anti-Inflammatory Diet page. For the sister-rhizome anti-inflammatory option, see Turmeric / curcumin, which works through different mechanisms (NF-κB inhibition, direct cytokine modulation) and is often combined with ginger in practical anti-inflammatory regimens.
Muscle Soreness, DOMS, and Exercise Recovery
Delayed-onset muscle soreness (DOMS) — the soreness that peaks 24–72 hours after unfamiliar or eccentric exercise — is driven by inflammatory cytokines (interleukin-6, tumor necrosis factor-alpha) and prostaglandin/leukotriene mediators released by mechanically damaged muscle fibers. The Black 2010 trial in Journal of Pain tested whether daily ginger supplementation could reduce DOMS:
- Two separate, identical double-blind placebo-controlled randomized experiments: study 1 gave 34 volunteers 2 g daily of raw ginger or placebo, and study 2 gave 40 volunteers 2 g daily of heat-treated ginger or placebo, for 11 days
- On day 8, subjects performed 18 eccentric (lowering) actions of the elbow flexors to induce DOMS
- Pain, perceived effort, blood prostaglandin E2, arm volume (swelling), range of motion and strength were measured before and for 3 days after the exercise
- 24 hours after exercise, raw ginger reduced muscle pain by 25% (p = 0.041) and heat-treated ginger by 23% (p = 0.049) compared with placebo; effects on the other measures were smaller
- Raw ginger (richer in gingerols) and heat-treated ginger (richer in shogaols) gave similar pain reductions — heat treatment did not enhance the effect
The practical implication for athletes and active patients: a daily ginger habit (typically taken with breakfast) reduces post-exercise soreness without the gastrointestinal and renal concerns of nonsteroidal anti-inflammatory drug use for exercise recovery. The dose used was 2 g/day, which is at the higher end of the typical supplementation range; 1–1.5 g/day in the form of capsules with morning meal is the more sustainable long-term regimen.
For the broader question of nonsteroidal anti-inflammatory drugs for exercise recovery: there is now reasonable evidence that high-dose nonsteroidal anti-inflammatory drug use immediately post-exercise may actually impair muscle protein synthesis and adaptation to training, suggesting that ginger (with its non-COX anti-inflammatory components) may be mechanistically superior for the athlete who wants pain relief without blocking the inflammatory signals required for training adaptation. This remains an area of active investigation.
Dysmenorrhea (Menstrual Pain)
Primary dysmenorrhea (painful menstruation in the absence of identifiable pelvic pathology) is driven primarily by elevated PGF2-alpha and PGE2 production by the menstruating endometrium. The pain mechanism is so reliably prostaglandin-mediated that nonsteroidal anti-inflammatory drugs are the gold-standard first-line therapy (with effect sizes comparable to or larger than for OA).
Multiple randomized trials have tested ginger as an alternative to nonsteroidal anti-inflammatory drugs for dysmenorrhea. The results have been consistently positive:
- Ozgoli 2009 (Journal of Alternative and Complementary Medicine): 150 students with primary dysmenorrhea divided into three equal groups taking ginger 250 mg four times daily, mefenamic acid 250 mg four times daily, or ibuprofen 400 mg four times daily, taken from menstrual onset for 3 days. All three groups had comparable pain reduction. No statistically significant difference between ginger and either nonsteroidal anti-inflammatory drug.
- Rahnama 2012 (BMC Complementary and Alternative Medicine): 120 students with moderate or severe primary dysmenorrhea were assigned to ginger root powder 500 mg three times daily or placebo (analysed: 56 ginger, 46 placebo) in two schedules — starting 2 days before the period and continuing through its first 3 days, or the first 3 days only. Ginger reduced pain severity more than placebo in both schedules (p = 0.015 and p = 0.029) and shortened pain in the first schedule (p = 0.017). This trial had no mefenamic acid arm.
- Daily 2015 systematic review (Pain Medicine): of 7 qualifying trials, 4 compared ginger with placebo during the first 3–4 days of the cycle and were pooled; ginger lowered pain scores (effect −1.85, 95% CI −2.87 to −0.84, p = 0.0003). The authors called this "suggestive evidence" for 750–2000 mg ginger powder during the first 3–4 days of the cycle. The abstract makes no comparison with nonsteroidal anti-inflammatory drugs.
- Moshfeghinia 2024 systematic review and meta-analysis (Journal of Integrative and Complementary Medicine): 24 studies reviewed, 12 pooled. Ginger reduced pain intensity (SMD −1.13, 95% CI −1.59 to −0.68) and pain duration (SMD −0.29) more than placebo, and did not differ from nonsteroidal anti-inflammatory drugs (SMD 0.01, 95% CI −0.24 to 0.25) or exercise for pain intensity. Safety data were rarely reported, and the authors note risk of bias in the included studies.
The trials used 250 mg ginger powder four times daily (Ozgoli) or 500 mg three times daily (Rahnama), starting at the onset of the period or 2 days before it and continuing for 3–5 days. Women with nonsteroidal anti-inflammatory drug intolerance, gastritis or anticoagulant use, or who prefer an herbal approach, are the group for whom ginger is discussed as an alternative.
The mechanism is the same COX/LOX inhibition discussed above, applied to the prostaglandin-driven uterine cramping rather than to joint inflammation. The dosing is higher than the OA dose (because dysmenorrhea is acute and requires rapid effect) and the duration is shorter (3 days per cycle, not chronic).
Topical Ginger and Local Pain
Topical ginger preparations — creams, oils, compresses — have a small but growing evidence base for localized musculoskeletal pain. The mechanism is partly local COX/LOX inhibition by gingerols absorbed through skin, partly counterirritant warming sensation from activation of transient receptor potential vanilloid 1 (TRPV1, the capsaicin receptor) by 6-shogaol, and partly placebo/massage effects from application.
A typical topical regimen for OA pain: ginger essential oil 2–3 drops in a carrier oil (coconut, olive, or jojoba), applied to the affected joint twice daily and massaged in. Some patients prefer commercially prepared ginger creams (often combined with cayenne for stronger TRPV1 effect, or with arnica for additional anti-inflammatory action). The Therapeutic Goods Administration (Australia) and the European Medicines Agency both list topical ginger as a traditional use for muscle and joint pain.
The traditional Chinese medicine preparation of a fresh ginger compress — warm ginger root grated onto a cloth and applied to a painful area — has been used for centuries for arthritis, menstrual cramps, and lower back pain. The mechanism is the same TRPV1 warming sensation plus modest transdermal gingerol absorption. There is little formal trial evidence for this preparation but considerable clinical tradition.
Compared with topical nonsteroidal anti-inflammatory drugs (diclofenac gel, ibuprofen gel), topical ginger has a less robust evidence base but comparable safety. Some people who want no systemic nonsteroidal anti-inflammatory drug exposure at all combine topical ginger with topical diclofenac, applied at different times of day, for localized joint pain.
Practical Dosing and Forms (Extract vs Powder)
For anti-inflammatory indications, the dosing is different from the nausea dosing covered in the Nausea Relief page. Key differences:
- Standardized extract vs whole powder — for nausea, simple ginger powder works well. For sustained anti-inflammatory effect (osteoarthritis, chronic pain), standardized ginger and ginger-galangal extracts standardized to 5% gingerols and 6% shogaols have stronger trial evidence than unstandardized powder. The lower daily dose of extract (250–500 mg) corresponds to roughly 1–2 g of whole ginger root by gingerol content.
- Sustained vs acute dosing — nausea benefit is rapid (within hours of dosing). Anti-inflammatory benefit builds over weeks. The osteoarthritis trials measured their results after 4 weeks (Drozdov), 6 weeks (Altman), 12 weeks (Baek) or 6 months (Wigler).
- Combination with turmeric — the combination of standardized ginger and standardized turmeric (curcumin with piperine for absorption) is common in commercial "joint health" products and has some evidence for additive benefit through complementary mechanisms (ginger's COX/LOX inhibition + curcumin's NF-κB suppression). A typical combination supplies ginger 250 mg + curcumin 500 mg, taken twice daily with food.
- Timing relative to nonsteroidal anti-inflammatory drugs — people who combine ginger with a nonsteroidal anti-inflammatory drug often take them at different times of day (e.g. ginger in the morning, ibuprofen as needed) to lessen the combined load on the stomach, even though ginger's gastrointestinal profile is gentler than nonsteroidal anti-inflammatory drugs.
Amounts used in trials and in practice, by condition:
- Knee/hip osteoarthritis: ginger extract 250 mg twice daily with meals; or whole ginger powder 1 g twice daily
- Chronic generalized inflammation, exercise recovery: 1–2 g whole ginger powder/day in divided doses with meals
- Acute dysmenorrhea: 250 mg four times daily for 3 days from menstrual onset (the Ozgoli trial schedule)
- Acute muscle/joint pain: 500 mg every 4 hours, up to 2 g/day
- Topical pain: 2–3 drops ginger essential oil in 1 tsp carrier oil, massaged in twice daily
Cautions and Drug Interactions
- Bleeding risk — ginger inhibits thromboxane synthesis and reduces platelet aggregation. The clinical relevance at culinary doses is minimal but at therapeutic doses (especially 2+ g daily) becomes more significant. Because of this antiplatelet effect, practitioners commonly describe stopping therapeutic-dose ginger 1–2 weeks before a procedure with significant bleeding risk.
- Warfarin interaction — case reports describe international normalized ratio (INR) elevation when ginger is started in patients on warfarin. In those reports the rise came after ginger was started, which is why more frequent international normalized ratio checks during the first 2–4 weeks are a common clinical practice. For direct oral anticoagulants (apixaban, rivaroxaban, dabigatran, edoxaban), data are sparser; the additive antiplatelet effect plausibly increases bleeding risk modestly.
- Aspirin combination — the antiplatelet effects of low-dose aspirin (81 mg/day) and therapeutic ginger likely add. For people on aspirin for heart protection, the two antiplatelet effects add together; none of the trials on this page measured the bleeding risk of that combination.
- Selective serotonin reuptake inhibitors and nonsteroidal anti-inflammatory drugs combination — selective serotonin reuptake inhibitors (sertraline, fluoxetine, escitalopram) increase gastrointestinal bleeding risk by inhibiting platelet serotonin uptake. The combination of selective serotonin reuptake inhibitor (SSRI) + nonsteroidal anti-inflammatory drug + ginger compounds this. For patients on this combination, the rationale for adding ginger as a nonsteroidal anti-inflammatory drug-sparing strategy (allowing nonsteroidal anti-inflammatory drug dose reduction) is actually strengthened.
- Gastritis or peptic ulcer disease — ginger is generally well-tolerated and may even help (see the Drozdov 2012 nonsteroidal anti-inflammatory drug-gastropathy trial above), but for people with active ulceration practitioners describe starting at lower doses (125 mg) and increasing slowly.
- Pregnancy and anti-inflammatory use — while ginger is well-established safe in pregnancy for nausea, the anti-inflammatory doses (1–2 g/day for OA) have less direct pregnancy safety data: the pregnancy safety record comes from nausea doses, not from 1–2 g a day taken for weeks or months.
- Calcium-channel blockers — theoretical interaction (ginger has mild calcium-channel blocking activity that may add to amlodipine, nifedipine, etc.), though clinical relevance appears minimal.
Key Research Papers
- Altman RD, Marcussen KC (2001). Effects of a ginger extract on knee pain in patients with osteoarthritis. Arthritis & Rheumatism 44(11):2531–2538. — PubMed PMID: 11710709
- Bliddal H, Rosetzsky A, Schlichting P et al. (2000). A randomized, placebo-controlled, cross-over study of ginger extracts and ibuprofen in osteoarthritis. Osteoarthritis and Cartilage 8(1):9–12. — PubMed PMID: 10607493
- Bartels EM, Folmer VN, Bliddal H et al. (2015). Efficacy and safety of ginger in osteoarthritis patients: a meta-analysis of randomized placebo-controlled trials. Osteoarthritis and Cartilage 23(1):13–21. — PubMed PMID: 25300574
- Wigler I, Grotto I, Caspi D, Yaron M (2003). The effects of Zintona EC (a ginger extract) on symptomatic gonarthritis. Osteoarthritis and Cartilage 11(11):783–789. — PubMed PMID: 14609531
- Baek HI, Shen L, Ha KC et al. (2024). Effectiveness and safety of steamed ginger extract on mild osteoarthritis: a randomized, double-blind, placebo-controlled clinical trial. Food & Function 15(18):9512–9523. — PubMed PMID: 39212491
- Araya-Quintanilla F, Gutierrez-Espinoza H, Munoz-Yanez MJ et al. (2020). Effectiveness of ginger on pain and function in knee osteoarthritis: a PRISMA systematic review and meta-analysis. Pain Physician 23(2):E151–E161. — PubMed PMID: 32214292
- Zhang Y, Gui Y, Adams R et al. (2025). Comparative effectiveness of nutritional supplements in the treatment of knee osteoarthritis: a network meta-analysis. Nutrients 17(15):2547. — PubMed PMID: 40806131
- Bannuru RR, Osani MC, Vaysbrot EE et al. (2019). OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and Cartilage 27(11):1578–1589. — PubMed PMID: 31278997
- Black CD, Herring MP, Hurley DJ, O'Connor PJ (2010). Ginger (Zingiber officinale) reduces muscle pain caused by eccentric exercise. Journal of Pain 11(9):894–903. — PubMed PMID: 20418184
- Drozdov VN, Kim VA, Tkachenko EV, Varvanina GG (2012). Influence of a specific ginger combination on gastropathy conditions in patients with osteoarthritis of the knee or hip. Journal of Alternative and Complementary Medicine 18(6):583–588. — PubMed PMID: 22784345
- Ozgoli G, Goli M, Moattar F (2009). Comparison of effects of ginger, mefenamic acid, and ibuprofen on pain in women with primary dysmenorrhea. Journal of Alternative and Complementary Medicine 15(2):129–132. — PubMed PMID: 19216660
- Rahnama P, Montazeri A, Huseini HF et al. (2012). Effect of Zingiber officinale R. rhizomes (ginger) on pain relief in primary dysmenorrhea: a placebo randomized trial. BMC Complementary and Alternative Medicine 12:92. — PubMed PMID: 22781186
- Daily JW, Zhang X, Kim DS, Park S (2015). Efficacy of ginger for alleviating the symptoms of primary dysmenorrhea: a systematic review and meta-analysis of randomized clinical trials. Pain Medicine 16(12):2243–2255. — PubMed PMID: 26177393
- Moshfeghinia R, Salmanpour N, Ghoshouni H et al. (2024). Ginger for pain management in primary dysmenorrhea: a systematic review and meta-analysis. Journal of Integrative and Complementary Medicine 30(11):1016–1030. — PubMed PMID: 38770631
- Tjendraputra E, Tran VH, Liu-Brennan D, Roufogalis BD, Duke CC (2001). Effect of ginger constituents and synthetic analogues on cyclooxygenase-2 enzyme in intact cells. Bioorganic Chemistry 29(3):156–163. — PubMed PMID: 11437391
- Grzanna R, Lindmark L, Frondoza CG (2005). Ginger—an herbal medicinal product with broad anti-inflammatory actions. Journal of Medicinal Food 8(2):125–132. The classic anti-inflammatory mechanism review. — PubMed PMID: 16117603
- Aryaeian N, Shahram F, Mahmoudi M et al. (2019). The effect of ginger supplementation on some immunity and inflammation intermediate genes expression in patients with active rheumatoid arthritis. Gene 698:179–185. — PubMed PMID: 30844477
- Funk JL, Frye JB, Oyarzo JN et al. (2016). Anti-inflammatory effects of the essential oils of ginger (Zingiber officinale Roscoe) in experimental rheumatoid arthritis. PharmaNutrition 4(3):123–131. — PubMed PMID: 27872812
- Lakhan SE, Ford CT, Tepper D (2015). Zingiberaceae extracts for pain: a systematic review and meta-analysis. Nutrition Journal 14:50. — PubMed PMID: 25972154
PubMed Topic Searches
Connections
- All Herbs
- Ginger Overview
- Ginger Benefits Hub
- Ginger for Nausea Relief
- Ginger Digestive & Gastroparesis
- Ginger for Migraine & Pain
- Turmeric / Curcumin (Sister Anti-Inflammatory)
- Black Seed (Nigella sativa)
- Arthritis
- Chronic Pain
- Dysmenorrhea
- Anti-Inflammatory Diet
- Aspirin (Nonsteroidal Anti-Inflammatory Drug Class Reference)
- Omega-3 Fatty Acids (Complementary Anti-Inflammatory)
- Inflammatory Markers (C-Reactive Protein, Erythrocyte Sedimentation Rate)
- Osteoarthritis — the joint disease the Altman, Bliddal and Bartels ginger trials were designed to treat.
- History