⚠ Evidence warning: Clinical trials or other evidence do not support the claims that topical glycyrrhetinic acid compares with topical acyclovir for cold sores, that glycyrrhizin is additive with interferon-alpha through a separate molecular action, and that case series support its broad-spectrum antiviral activity. This page keeps it as a report of what people, websites or other media say.
Licorice Antiviral Activity (Glycyrrhizin)
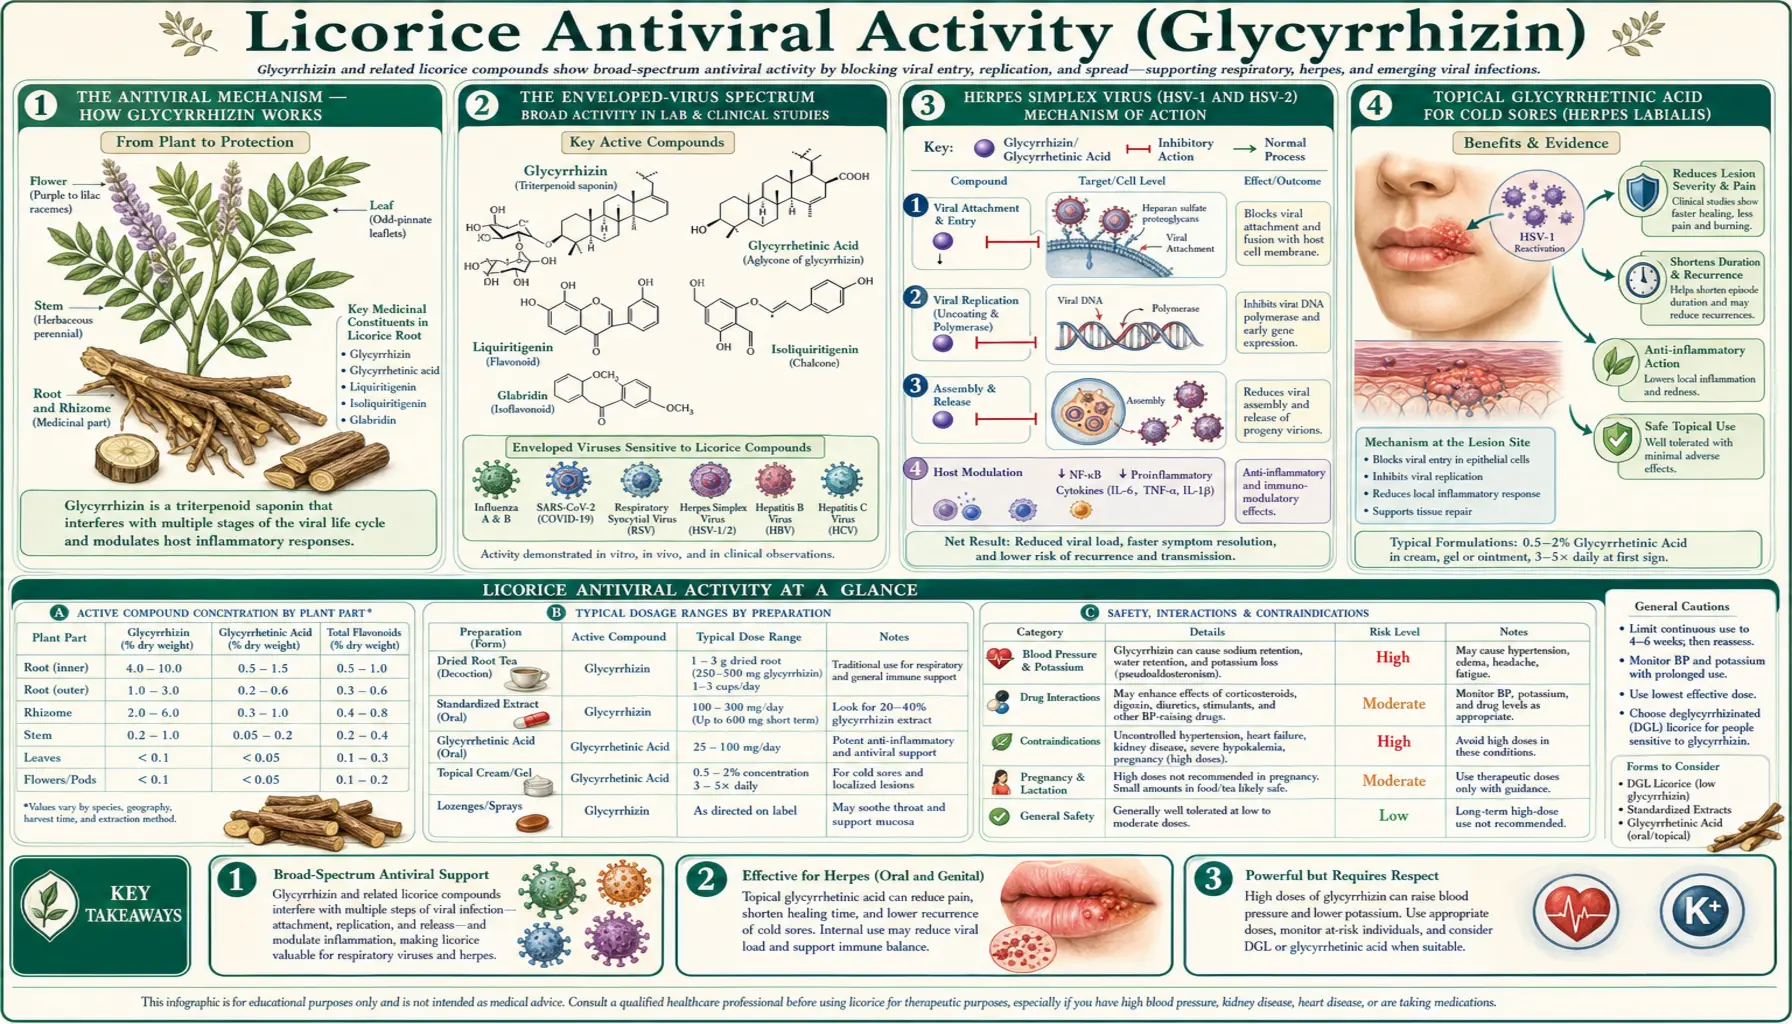
Glycyrrhizin (and its active metabolite glycyrrhetinic acid) has documented in vitro and in vivo antiviral activity against a wide range of enveloped DNA and RNA viruses — herpes simplex virus (HSV-1, HSV-2), Epstein-Barr virus (EBV), cytomegalovirus (CMV), hepatitis B virus (HBV), hepatitis C virus (HCV), and, historically notable, the original SARS coronavirus in the 2003 outbreak. In Japan, an intravenous glycyrrhizin preparation (SNMC) has been used in chronic viral hepatitis for decades, with documented reductions in liver enzyme elevation and long-term reductions in hepatocellular carcinoma incidence in chronic hepatitis C virus patients. Topical glycyrrhetinic acid is in widespread cosmetic and over-the-counter use for recurrent labial herpes (cold sores). Oral whole licorice does not reach the systemic glycyrrhizin levels of intravenous preparations and its clinical antiviral effect at oral doses is more modest; integrative practitioners describe using it as an adjunct for chronic viral infections, particularly chronic Epstein-Barr virus reactivation syndromes and chronic hepatitis maintenance. This page covers the mechanism, the major virus families, the key laboratory papers (Crance 2003 on flaviviruses, Cinatl 2003 on SARS), and the doses used in studies and integrative practice.
Table of Contents
- The Antiviral Mechanism — How Glycyrrhizin Works
- The Enveloped-Virus Spectrum
- Herpes Simplex Virus (HSV-1 and HSV-2)
- Topical Glycyrrhetinic Acid for Cold Sores
- Epstein-Barr Virus and Chronic Reactivation
- Cytomegalovirus (CMV)
- Hepatitis B and C — Japanese Clinical Experience
- Intravenous Glycyrrhizin (SNMC) — Japan's Long-Running Hepatitis Treatment
- The Cinatl 2003 Lancet SARS Paper — Historical Context
- Human Immunodeficiency Virus Pilot Data and Adjunct Use
- Oral vs Intravenous Glycyrrhizin — Why Bioavailability Matters
- Doses Used in Studies and Practice
- Key Research Papers
- Connections
- Featured Videos
The Antiviral Mechanism — How Glycyrrhizin Works
Glycyrrhizin appears to disrupt viral replication through multiple parallel mechanisms, which collectively explain its activity against an unusually broad range of enveloped viruses. The mechanisms identified to date:
- Inhibition of viral entry and membrane fusion — glycyrrhizin disrupts the lipid bilayer of enveloped virions and interferes with the conformational changes in viral fusion proteins that are required for the virus to enter the host cell. This step appears to be one of the most reliable mechanisms and is implicated in activity against HSV, HCV, hepatitis B virus, and SARS coronavirus.
- Inhibition of viral protein synthesis — in established infections, glycyrrhizin reduces the production of viral structural and non-structural proteins, slowing the production of new virions and shifting the host-virus equilibrium in favor of the host immune response.
- Modulation of host signaling — glycyrrhizin upregulates host interferon production (particularly interferon-gamma, IFN-gamma) and modulates the NF-kappa-B pathway in ways that enhance antiviral innate immunity. This is a host-directed rather than direct-acting antiviral mechanism.
- Inhibition of viral replication enzymes — for some viruses (hepatitis C virus in particular), glycyrrhizin shows weak inhibitory activity against viral polymerases and proteases at high concentrations.
- Reduction of latency reactivation — in chronic herpesvirus infections (HSV, EBV, cytomegalovirus), glycyrrhizin appears to reduce the rate of reactivation from latency, possibly by interfering with the viral transcription factors that initiate the reactivation cascade.
The combined effect explains the unusual breadth of antiviral activity. Glycyrrhizin is not as potent as direct-acting antivirals (acyclovir, oseltamivir, sofosbuvir, the COVID protease inhibitors) against any single virus, but it produces detectable activity against many viruses and acts at multiple steps in the viral lifecycle, which makes resistance development unlikely. The pharmacological profile is that of a broad-spectrum, modest-potency, host-supportive antiviral — used as an adjunct, not as primary therapy for acute serious viral disease.
The Enveloped-Virus Spectrum
Glycyrrhizin's activity is concentrated on enveloped viruses — viruses that acquire a lipid bilayer envelope from the host cell membrane during budding. The list includes most herpesviruses, hepatitis B, hepatitis C, human immunodeficiency virus (HIV), influenza, respiratory syncytial virus (RSV), coronaviruses, and many others. Non-enveloped viruses (poliovirus, rotavirus, norovirus, adenovirus, papillomaviruses) are generally less affected, because the mechanisms that target the lipid envelope are not available.
Within the enveloped-virus category, the activity is most reliably documented for:
- Herpesviruses — HSV-1 (oral herpes), HSV-2 (genital herpes), varicella-zoster virus (VZV: chickenpox, shingles), Epstein-Barr virus (mononucleosis, lymphoma), cytomegalovirus (congenital infection, transplant reactivation), human herpesvirus 6 (HHV-6: roseola, possible chronic fatigue association), human herpesvirus 8 (HHV-8: Kaposi sarcoma)
- Hepatitis viruses — hepatitis B virus (chronic hepatitis B), hepatitis C virus (chronic hepatitis C)
- Retroviruses — human immunodeficiency virus (mixed evidence, small effect)
- Coronaviruses — SARS-CoV (the original 2003 SARS, documented in Cinatl 2003 Lancet)
- Respiratory viruses — influenza A in animal models, respiratory syncytial virus in cell culture
This page covers herpesviruses, hepatitis viruses, and SARS in detail. The other applications are less well-documented and not central to current integrative use of licorice.
Herpes Simplex Virus (HSV-1 and HSV-2)
Herpes simplex viruses establish lifelong latent infection in sensory ganglia after primary infection, with periodic reactivation producing the recognizable mucocutaneous lesions — cold sores (HSV-1 most commonly) or genital herpes (HSV-2 most commonly, with HSV-1 increasingly causing genital disease as well). Standard pharmacologic management uses nucleoside analog antivirals (acyclovir, valacyclovir, famciclovir) for acute outbreaks and chronic suppression.
Glycyrrhizin has documented in vitro activity against both HSV-1 and HSV-2, with half-maximal effective concentration (EC50, the dose that blocks half the viral activity) values in the low-micromolar range. The mechanism appears to involve interference with the viral fusion step and possibly inhibition of viral immediate-early gene expression that drives reactivation from latency. In animal models of recurrent ocular HSV-1 keratitis, topical glycyrrhizin reduced reactivation frequency and lesion severity.
The clinical translation has been most successful for topical applications (see next section). For systemic management of recurrent labial or genital herpes, oral whole licorice has been used as an adjunct in integrative protocols at doses of 75-150 mg of glycyrrhizin per day, but the evidence for clinical benefit at these doses is anecdotal rather than trial-based. In standard care, people with frequent outbreaks (>6 per year for labial, >4-6 per year for genital) are offered daily (suppressive) acyclovir or valacyclovir, and practitioners describe licorice as an adjunct only.
Topical Glycyrrhetinic Acid for Cold Sores
Topical glycyrrhetinic acid is one of the most widely used over-the-counter botanical antivirals globally, found in dozens of branded cold-sore products in Europe and Asia. The typical preparation is a 1-2% glycyrrhetinic acid cream or gel, applied at the first sign of tingling or prodromal symptoms and continued 4-5 times daily until the lesion fully heals.
Users and practitioners describe the following with topical glycyrrhetinic acid for recurrent labial herpes:
- Shorter-lasting lesions
- Reduced lesion size at peak
- Faster pain resolution
- Reduced rate of vesicle formation if applied very early (prodrome stage)
- Excellent local tolerability (no irritation, no systemic absorption at clinically meaningful levels)
The effect size is modest but real, comparable to topical acyclovir cream (5%) and somewhat less than oral valacyclovir taken at prodrome.
People with infrequent cold sores who prefer not to use prescription antivirals often reach for topical glycyrrhetinic acid first. For frequent or severe outbreaks, oral valacyclovir is the standard prescription treatment.
An interesting practical note: dabbing whole licorice extract or even deglycyrrhizinated licorice (DGL) paste (DGL powder mixed with a few drops of water) directly on an early cold sore is a folk remedy with the same theoretical rationale and many anecdotal reports of efficacy. The DGL paste lacks the standardized glycyrrhetinic acid concentration of commercial topical products and is unlikely to be as consistently effective, but in a pinch it represents the same active class.
Epstein-Barr Virus and Chronic Reactivation
Epstein-Barr virus (EBV) infects roughly 95% of adults worldwide. Primary infection in adolescence or young adulthood causes infectious mononucleosis; primary infection in childhood is typically asymptomatic. After primary infection, Epstein-Barr virus establishes lifelong latency in memory B cells. Chronic active EBV (CAEBV) and chronic Epstein-Barr virus reactivation syndromes are increasingly recognized as contributors to chronic fatigue, autoimmune disease (multiple sclerosis, lupus, rheumatoid arthritis), and several lymphoproliferative malignancies.
Glycyrrhizin has documented anti-EBV activity in cell culture, with reduction of viral DNA replication and reduction of viral antigen expression. The mechanism is similar to its anti-HSV activity, with the additional consideration that Epstein-Barr virus-driven B cell proliferation is also reduced by glycyrrhizin's anti-inflammatory and immune-modulating effects.
The clinical evidence for licorice in chronic active Epstein-Barr virus is suggestive but limited. Integrative-medicine practitioners working with chronic fatigue and post-viral fatigue patients often include licorice (typically whole-root extract at 100-300 mg standardized to glycyrrhizin) as part of multi-herb antiviral protocols that also include monolaurin, lysine, lemon balm, and olive leaf extract. The evidence for the combined protocol is anecdotal-to-case-series in quality. For patients with documented chronic Epstein-Barr virus reactivation (positive Epstein-Barr virus early antigen antibody, elevated viral loads), practitioners describe this approach as an adjunct alongside standard medical evaluation.
For more on the chronic fatigue and post-viral fatigue context, see our Chronic Fatigue page.
Cytomegalovirus (CMV)
Cytomegalovirus is another ubiquitous herpesvirus (50-90% seroprevalence depending on geography and socioeconomics) that establishes lifelong latency and can reactivate in immunocompromised hosts — particularly transplant recipients, late-stage human immunodeficiency virus patients, and chemotherapy patients. Primary cytomegalovirus in pregnancy is a leading cause of congenital infection. Glycyrrhizin has documented activity against cytomegalovirus in cell culture, with EC50 values comparable to those for HSV.
The clinical use of glycyrrhizin in cytomegalovirus is limited but interesting. In Japan, Numazaki and colleagues (1994) gave intravenous glycyrrhizin (SNMC, see below), 50 mL a day for more than one week, to three infants with cytomegalovirus infection and abnormal liver function; liver function had become normal by the end of the course. The clinical evidence is limited to this very small case series. The evidence is case-series quality but supports the broad-spectrum antiviral activity of the molecule.
For most clinical scenarios where cytomegalovirus is the issue (transplant prophylaxis, acquired immunodeficiency syndrome-associated cytomegalovirus retinitis), ganciclovir, valganciclovir, foscarnet, and letermovir are the standard drugs and licorice has no established role. Licorice may have a small adjunct role in immunocompetent cytomegalovirus-mononucleosis syndromes, where the clinical picture is closer to Epstein-Barr virus mononucleosis and supportive antiviral effects are useful but specific antiviral therapy is not indicated.
Hepatitis B and C — Japanese Clinical Experience
Chronic viral hepatitis (hepatitis B virus and hepatitis C virus) is the most-studied indication for therapeutic glycyrrhizin, with decades of Japanese clinical experience and a respectable in-vitro literature. A related laboratory paper, Crance JM et al. 2003 in Antiviral Research, did not test hepatitis viruses: it tested interferon-alpha, ribavirin, 6-azauridine, and glycyrrhizin against 11 disease-causing flaviviruses (the dengue, Japanese encephalitis, tick-borne and yellow fever groups) in Vero cells, and found that glycyrrhizin inhibited their replication at high concentrations that did not harm the cells.
Combination of glycyrrhizin with interferon-alpha produced additive (not synergistic) effects. Activity was not dependent on the cortisol-related 11-beta-HSD2 mechanism — this is a separate molecular action of glycyrrhizin.
The long-running Japanese clinical experience with intravenous glycyrrhizin in chronic hepatitis C virus has documented reductions in liver enzyme elevation, possible reductions in long-term liver fibrosis, and most importantly a reduction in hepatocellular carcinoma incidence in long-term chronic hepatitis C virus patients on chronic glycyrrhizin therapy. With the arrival of direct-acting antivirals (sofosbuvir-based regimens) for hepatitis C virus in the 2010s, the role of glycyrrhizin in hepatitis C virus management has shrunk dramatically — hepatitis C virus is now curable in >95% of patients with 8-12 weeks of well-tolerated oral antivirals, and glycyrrhizin is not used as primary therapy. Glycyrrhizin retains a small role for the rare patient who has failed direct-acting antiviral therapy or who has contraindications to it.
For hepatitis B virus, glycyrrhizin shows similar in-vitro activity but the clinical evidence base is smaller. The mainstays of hepatitis B virus therapy remain tenofovir, entecavir, and pegylated interferon; glycyrrhizin has only an adjunct role at most.
Intravenous Glycyrrhizin (SNMC) — Japan's Long-Running Hepatitis Treatment
SNMC is an intravenous preparation containing 0.2% glycyrrhizin, 0.1% cysteine, and 2.0% glycine, used in Japan for liver disease for decades. The cysteine and glycine are added to the formulation primarily to mitigate the mineralocorticoid effects of the glycyrrhizin (the rationale is partly empirical, partly based on amino-acid metabolism in the liver), though the mineralocorticoid effects (salt retention, high blood pressure, low potassium) are not fully eliminated, and blood pressure and potassium are still monitored in people receiving SNMC.
The SNMC regimen described for chronic hepatitis is 40-100 mL daily by slow intravenous (IV) infusion, 5 days per week, for an extended period (months to years in some patients). Documented effects:
- Sustained reductions in serum alanine aminotransferase (ALT) and aspartate aminotransferase (AST) elevations (the conventional surrogate for liver inflammation)
- Modest reductions in viral load in chronic hepatitis B virus and hepatitis C virus (smaller than direct-acting antivirals)
- In a long-term Japanese cohort (Arase 1997, a retrospective study), reduced incidence of liver cancer (hepatocellular carcinoma) in 84 chronic hepatitis C virus patients given SNMC (100 mL daily for 8 weeks, then 2-7 times a week) compared with a concurrent group of 109 patients given other herbal medicine such as vitamin K: 15-year liver cancer rates were 12% vs 25%
- Reduced incidence of liver fibrosis progression on serial biopsy
- Generally well-tolerated when monitored, with the principal adverse effect being the predicted mineralocorticoid syndrome (hypokalemia, hypertension, edema) in some patients requiring dose adjustment
SNMC remains in active use in Japan and several Asian countries, primarily for patients with chronic hepatitis B virus (for which direct-acting cures do not yet exist), for hepatitis C virus patients who failed or could not tolerate direct-acting antivirals, and for non-viral chronic liver disease (alcoholic liver disease, nonalcoholic steatohepatitis, autoimmune hepatitis). Outside Japan it is rarely used; the closest Western equivalent is oral glycyrrhizin extract preparations at high dose, which do not approach the systemic glycyrrhizin exposure of SNMC but provide a partial substitute.
The SNMC experience is the strongest single piece of evidence for glycyrrhizin's genuine antiviral activity in human disease. The decades-long clinical record, with serial biopsies and long-term outcome data, is much more substantial than any equivalent natural-product clinical experience in Western pharmacology.
The Cinatl 2003 Lancet SARS Paper — Historical Context
In June 2003, in the immediate aftermath of the original SARS coronavirus outbreak (SARS-CoV, distinct from the much later SARS-CoV-2 of 2019-2023), Jindrich Cinatl and colleagues published a Lancet letter titled "Glycyrrhizin, an active component of liquorice roots, and replication of SARS-associated coronavirus." The work was rapid and limited — an in-vitro screen comparing the antiviral activity of glycyrrhizin, ribavirin, 6-azauridine, pyrazofurin, and mycophenolic acid against two clinical isolates of the SARS coronavirus in Vero cell culture.
The finding was striking: of all the compounds, glycyrrhizin was the most active in inhibiting replication of the virus. It had the highest selectivity index (67, the ratio of the dose that harms cells to the dose that blocks the virus), although its EC50 of about 300 mg/L was higher than those of pyrazofurin (4.2 mg/L) and 6-azauridine (16.8 mg/L). The mechanism appeared to involve inhibition of viral replication and viral adsorption to host cells. The authors explicitly suggested that further clinical investigation of glycyrrhizin in SARS patients would be warranted.
The 2003 SARS outbreak was contained primarily by public-health measures (case isolation, quarantine, contact tracing) before any antiviral therapy was tested in randomized trials. SARS-CoV essentially disappeared by mid-2004. Glycyrrhizin was never formally trialed in SARS patients. The Cinatl paper remained a curious historical footnote — an early example of natural-product screening in a novel respiratory virus outbreak — until the 2019-2023 SARS-CoV-2 pandemic produced renewed interest in the question of whether glycyrrhizin had analogous activity against the new coronavirus.
This page does not discuss SARS-CoV-2 or COVID-19. The historical SARS-CoV (2003) discussion is included because it is part of the long-standing scientific record of glycyrrhizin's antiviral activity and predates the much more politicized later coronavirus context. The 2003 in-vitro signal informs the general antiviral mechanism discussion but does not by itself support any specific clinical recommendation.
Human Immunodeficiency Virus Pilot Data and Adjunct Use
Glycyrrhizin and human immunodeficiency virus is a small but interesting literature. The earliest work in the 1980s and 1990s showed in-vitro inhibition of HIV-1 replication in cultured T cells at concentrations achievable with intravenous SNMC, and several small clinical case series from Japan reported sustained CD4 count stability or improvement in chronic human immunodeficiency virus patients on long-term intravenous glycyrrhizin. The mechanism appeared to involve interference with reverse transcriptase activity at high glycyrrhizin concentrations and possibly with viral entry through gp120-CD4 interactions.
The arrival of effective combination antiretroviral therapy (the protease-inhibitor breakthrough of 1996 and subsequent integrase-inhibitor era) made glycyrrhizin clinically irrelevant as primary human immunodeficiency virus therapy — the small reductions in viral activity from glycyrrhizin are dwarfed by the multi-log reductions achievable with modern combination antiretroviral therapy (ART). Glycyrrhizin retains a possible adjunct role in two scenarios: chronic-hepatitis-coinfected human immunodeficiency virus patients (where the liver-protective effects are theoretically useful) and patients on long-term ART who have stable virologic suppression but ongoing immune activation (a population in whom anti-inflammatory adjuncts are an area of clinical research).
The positive 1989 Japanese report (Mori and colleagues: nine hemophilia patients with HIV given 200-800 mg a day of intravenous glycyrrhizin for more than 8 weeks; OKT4 (CD4) helper cells rose in 8 of the 9) has not been independently replicated in modern trials and does not by itself support glycyrrhizin in human immunodeficiency virus care today. In the combination antiretroviral therapy era, those drugs are the primary therapy.
Oral vs Intravenous Glycyrrhizin — Why Bioavailability Matters
The single most important practical limitation on oral whole licorice as an antiviral is bioavailability. Glycyrrhizin is poorly absorbed from the intestine in its native form (5-10% oral bioavailability) and undergoes substantial first-pass metabolism in the liver to glycyrrhetinic acid, which is more bioavailable but has different pharmacological activity. Peak plasma concentrations of glycyrrhizin after oral administration are typically in the low micromolar range — below the concentrations at which significant in-vitro antiviral activity is observed for most viruses.
Intravenous glycyrrhizin (SNMC) bypasses this bioavailability limitation entirely and reliably achieves the high-micromolar plasma concentrations needed for measurable antiviral activity. This is why the strongest clinical evidence for glycyrrhizin antiviral effect comes from the Japanese SNMC experience — the route of administration is doing critical pharmacological work that oral preparations cannot match.
For the patient using oral whole licorice as an integrative antiviral, this means realistic expectations: modest, supportive, host-directed effects are plausible; direct potent antiviral effects comparable to oseltamivir or valacyclovir are not. The oral antiviral activity is more about supporting the host's own antiviral response (innate immunity modulation, mucosal immunoglobulin A (IgA) support, anti-inflammatory action) than about reaching virion-killing concentrations in tissue. This framing helps explain why oral licorice shows benefit in some chronic indolent viral conditions (chronic Epstein-Barr virus reactivation, chronic hepatitis maintenance) but is rarely the right answer for acute severe viral illness.
Doses Used in Studies and Practice
- Recurrent labial herpes (cold sores) — users describe topical 1-2% glycyrrhetinic acid cream applied 4-5× daily from the first tingling (prodrome) until the lesion heals, sometimes combined with oral lysine (1 g 3× daily) and topical lemon balm (Melissa officinalis). For frequent outbreaks, daily oral valacyclovir (suppression) is the standard prescription approach.
- Chronic Epstein-Barr virus reactivation — practitioners use standardized whole-root licorice extract 100-300 mg twice daily (delivering ~75-150 mg glycyrrhizin per day), combined with monolaurin, lysine, and lemon balm, usually for 8-12 weeks followed by a break or a switch to DGL. Because glycyrrhizin raises blood pressure and lowers blood potassium, both are monitored during these courses, as described on the safety page.
- Chronic hepatitis B or C maintenance (post-eradication or eradication-ineligible) — given under liver-specialist (hepatology) supervision: oral high-dose glycyrrhizin preparations or, where available, intravenous SNMC. Direct-acting antivirals remain the standard treatment where they apply.
- Genital herpes outbreaks — oral valacyclovir or acyclovir is the standard of care; practitioners describe licorice as an adjunct at most, alongside antiviral treatment.
- Generic adjunct antiviral support during cold/flu season — practitioners describe DGL chewables daily (for the gut-mucosal immunoglobulin A support) plus episodic short-course whole licorice extract during active illness; combined with elderberry, zinc, and vitamin D.
For all chronic uses of whole licorice, the safety constraints outlined on the Cortisol and Hypertension Warning page apply — whole licorice taken regularly can raise blood pressure and lower potassium (pseudoaldosteronism, a hormone-like effect of glycyrrhizin), whatever the reason it is taken.
Key Research Papers
- Cinatl J et al. (2003). Glycyrrhizin, an active component of liquorice roots, and replication of SARS-associated coronavirus. The Lancet 361(9374):2045-46. — PubMed PMID: 12814717
- Crance JM et al. (2003). Interferon, ribavirin, 6-azauridine and glycyrrhizin: antiviral compounds active against pathogenic flaviviruses. Antiviral Research 58(1):73-79. — PubMed PMID: 12719009
- Pompei R et al. (1979). Glycyrrhizic acid inhibits virus growth and inactivates virus particles. Nature 281(5733):689-690. — PubMed PMID: 233133
- Arase Y et al. (1997). The long-term efficacy of glycyrrhizin in chronic hepatitis C patients. Cancer 79(8):1494-1500. — PubMed PMID: 9118029
- van Rossum TG et al. (1998). Glycyrrhizin as a potential treatment for chronic hepatitis C. Alimentary Pharmacology & Therapeutics. — PubMed PMID: 9570253
- Sato H et al. (1996). Therapeutic basis of glycyrrhizin on chronic hepatitis B. Antiviral Research. — PubMed PMID: 8783808
- Lin JC (2003). Mechanism of action of glycyrrhizic acid in inhibition of Epstein-Barr virus replication in vitro. Antiviral Research. — PubMed PMID: 12834859
- Hoever G et al. (2005). Antiviral activity of glycyrrhizic acid derivatives against SARS-coronavirus. Journal of Medicinal Chemistry 48(4):1256-1259. — PubMed PMID: 15715493
- Numazaki K et al. (1994). Effect of glycyrrhizin in children with liver dysfunction associated with cytomegalovirus infection. Tohoku Journal of Experimental Medicine. — PubMed PMID: 8073426
- Mori K et al. (1989). Effects of glycyrrhizin (SNMC: Stronger Neo-Minophagen C) in hemophilia patients with HIV-1 infection. Tohoku Journal of Experimental Medicine. — PubMed PMID: 2781539
- Curreli F et al. (2005). Glycyrrhizic acid alters Kaposi sarcoma-associated herpesvirus latency, triggering p53-mediated apoptosis in transformed B lymphocytes. Journal of Clinical Investigation. — PubMed PMID: 15765147
- Fiore C et al. (2008). Antiviral effects of Glycyrrhiza species. Phytotherapy Research 22(2):141-148. — PubMed PMID: 17886224
PubMed Topic Searches
Connections
- All Herbs
- Licorice Overview
- Licorice Benefits Hub
- Adrenal Support and Cortisol
- Gastrointestinal Health and Ulcers
- Cortisol and Hypertension Warning
- Lemon Balm
- Elderberry
- Olive Leaf
- Echinacea
- Hepatitis
- Herpes Simplex Virus
- Epstein-Barr Virus
- Chronic Fatigue
- Vitamin D3
- Vitamin C
- Zinc
- Lysine
- Immune Boosting
- History