⚠ Evidence warning: Clinical trials or other evidence do not support the claims that a licorice rinse shortens canker sores to 4-6 days and is a safe, reasonable first-line option for recurrent canker sores. This page keeps it as a report of what people, websites or other media say.
Licorice for Gastrointestinal (GI) Health and Peptic Ulcers (DGL)
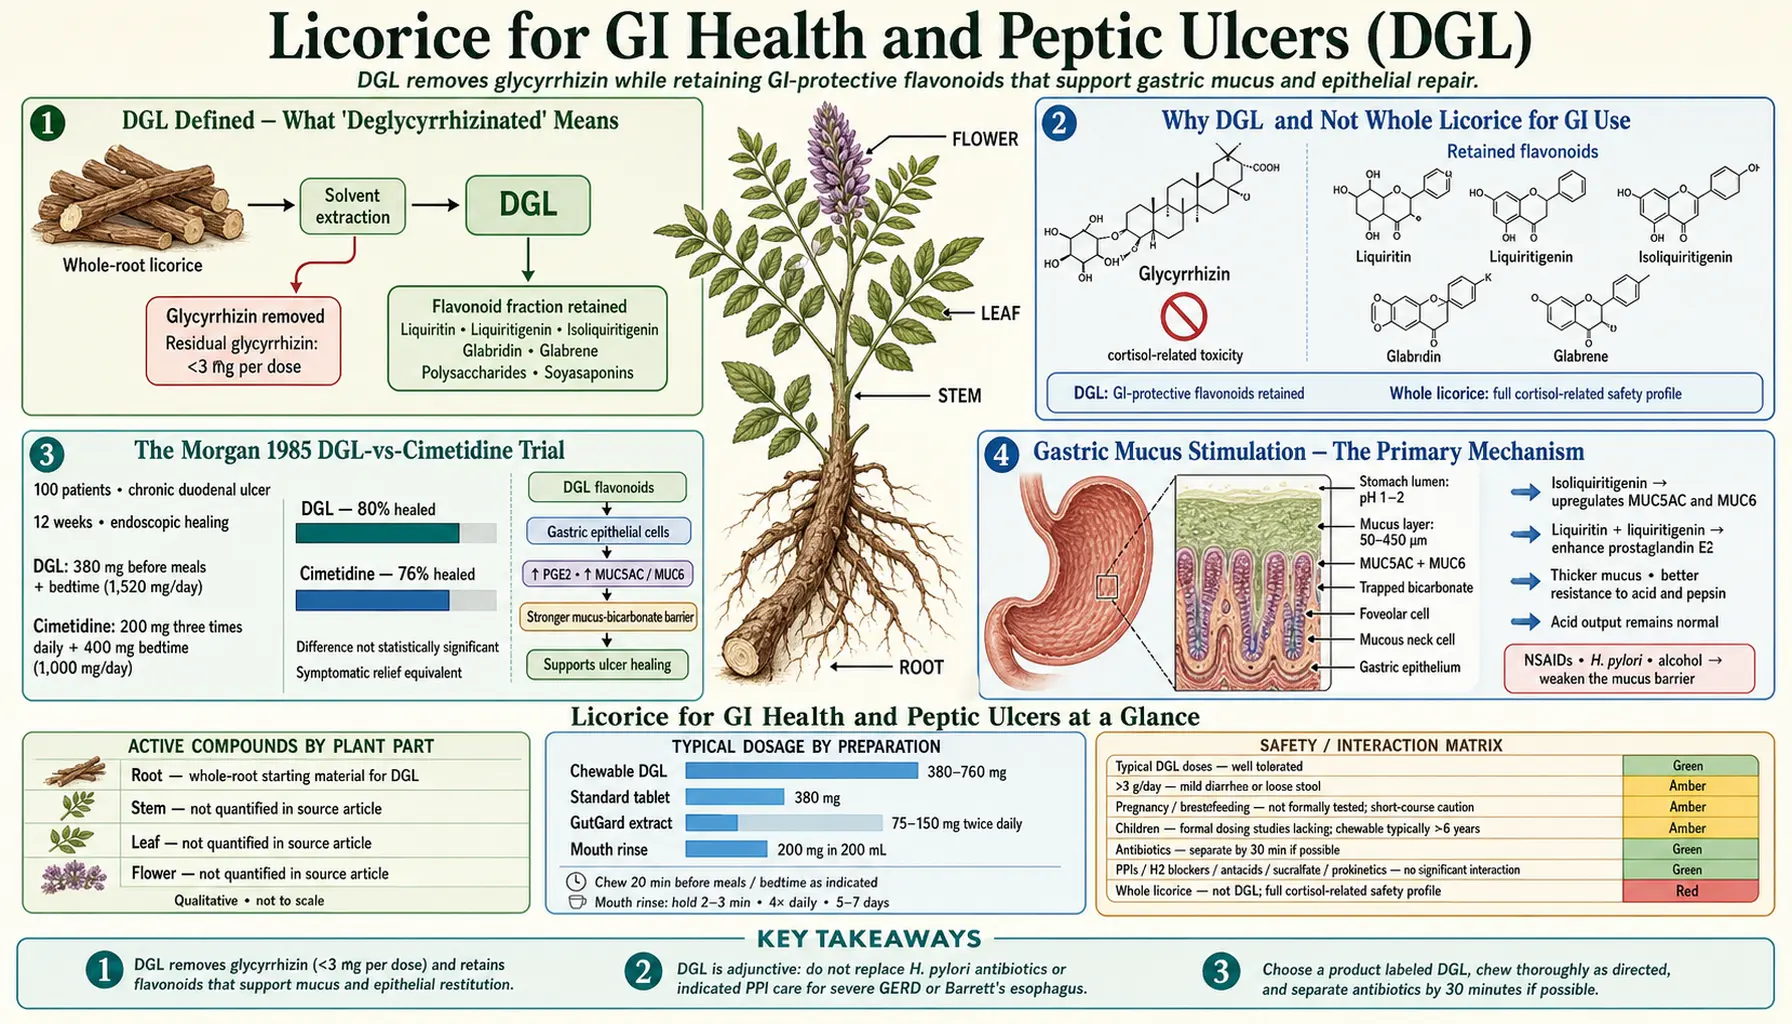
Deglycyrrhizinated licorice (DGL) is the most-studied botanical intervention for peptic ulcer disease, gastritis, and reflux esophagitis. By removing glycyrrhizin from whole licorice, DGL eliminates the cortisol-prolonging side effect profile while preserving the flavonoid fraction that stimulates gastric mucus secretion, accelerates epithelial restitution after injury, and exhibits direct activity against Helicobacter pylori. In a 100-patient trial published in Gut in 1982, Morgan and colleagues found that a DGL-antacid tablet healed gastric ulcers about as often as cimetidine (an H2-receptor blocker): roughly 63% at six weeks and 91% at 12 weeks, with no significant difference between the two. In the 1960s and 1970s, the synthetic glycyrrhetinic acid derivative carbenoxolone was used routinely in British hospitals for peptic ulcer and is the structural template that led to modern peptic-ulcer drug design. Today DGL retains a respected place in the natural pharmacopeia for ulcer prevention, dyspepsia management, nonsteroidal anti-inflammatory drug (NSAID) gastroprotection, oral aphthous ulcer (canker sore) treatment, and as a supportive adjunct to standard H. pylori eradication. This page covers each application, the mechanism, the chewable-vs-capsule formulation question, dosing convention, and the (small) safety considerations that distinguish DGL from whole licorice.
Table of Contents
- DGL Defined — What "Deglycyrrhizinated" Means
- Why DGL and Not Whole Licorice for Gastrointestinal Use
- The Morgan DGL-Antacid vs Cimetidine Trials (1982 and 1985)
- Gastric Mucus Stimulation — The Primary Mechanism
- Epithelial Restitution — The Second Mechanism
- DGL and Helicobacter pylori — Adjunct Role
- Functional Dyspepsia (Licorice Flavonoid Extract Trial)
- Reflux and Gastroesophageal Reflux Disease (GERD)
- Nonsteroidal Anti-Inflammatory Drug Gastroprotection
- Oral Aphthous Ulcer (Canker Sore) Treatment
- The Carbenoxolone Story — The Synthetic Cousin
- Chewable vs Capsule Formulation
- Dosing and Practical Use
- Safety Profile of DGL
- Key Research Papers
- Connections
- Featured Videos
DGL Defined — What "Deglycyrrhizinated" Means
Deglycyrrhizinated licorice (DGL) is whole-root licorice from which the glycyrrhizin (glycyrrhizic acid) has been removed by solvent extraction. The standard preparation reduces glycyrrhizin content to less than 3 mg per dose, well below the threshold at which 11-beta-HSD2 inhibition produces detectable cortisol prolongation or mineralocorticoid effects. The European Pharmacopoeia and the United States Pharmacopeia both specify the deglycyrrhization process and the residual glycyrrhizin upper limit.
What remains after deglycyrrhization is the flavonoid fraction: liquiritin, liquiritigenin, isoliquiritigenin, glabridin, glabrene, and dozens of minor flavonoids, plus polysaccharides, soyasaponins (other than glycyrrhizin), and a small amount of essential-oil-soluble fraction. These constituents are responsible for the gastric-mucosal effects that make DGL clinically useful, and they are not the constituents responsible for the cortisol-prolongation problem.
From a labeling perspective: products marked "DGL" or "deglycyrrhizinated licorice" reliably meet this specification. Products marked simply "licorice extract" or "licorice root" do not — they are whole-licorice preparations and carry the full cortisol-related safety profile. The distinction matters for people taking blood-pressure medicine: the cortisol-related effect that raises blood pressure comes from glycyrrhizin, which DGL has had removed, while daily whole licorice carries it in full.
Why DGL and Not Whole Licorice for Gastrointestinal Use
The flavonoid fraction is the gastrointestinal-protective fraction. Glycyrrhizin contributes nothing useful to ulcer healing or gastric mucus stimulation. Removing glycyrrhizin eliminates the cortisol-related toxicity without sacrificing any of the gastrointestinal-protective benefit. From a benefit-risk perspective, there is essentially no clinical scenario in which whole licorice is preferable to DGL for peptic ulcer, gastritis, reflux, or dyspepsia — the same effect is available at lower risk.
This is unusual in herbal pharmacology. Most herbs cannot be cleanly fractionated into a "useful part" and a "toxic part"; the full constituent profile is needed to reproduce the traditional clinical effect. Licorice is the exception. The 1950s discovery that DGL retained ulcer activity without the mineralocorticoid effect was a small revolution in botanical pharmacology and led to the development of the synthetic carbenoxolone derivative (discussed below).
The historical exception was the use of whole licorice in classical Chinese formulas as a harmonizer (gan cao). In that context, licorice was rarely the dominant ingredient and was typically used at low doses (3-9 g of raw root in a daily decoction shared with 8-15 other herbs), and the formulas were prescribed for short courses. Even so, modern TCM practitioners increasingly substitute DGL for whole licorice in patients with hypertension or cardiovascular risk, with no apparent loss of efficacy for gastrointestinal (GI) indications.
The Morgan DGL-Antacid vs Cimetidine Trials (1982 and 1985)
The best-known modern trial of DGL in peptic ulcer disease was run by Morgan AG and colleagues and published in Gut in 1982. 100 patients with benign gastric ulcer were treated in a single-blind trial checked by endoscopy, comparing two regimens:
- DGL-antacid arm — a DGL-antacid tablet, six tablets daily
- Cimetidine arm — cimetidine 1 g daily
Ulcer healing was checked after six weeks and, if incomplete, after a further six weeks:
- Healed at six weeks: about 63%
- Healed at 12 weeks: about 91%
- Difference between the two regimens: not statistically significant
Relief of daytime pain did not differ between the two regimens, but cimetidine relieved night pain better over the first two weeks. After healing, doses were lowered for maintenance (cimetidine 400 mg at night; the DGL-antacid tablet two tablets twice daily). Morgan's follow-up paper in Gut in 1985 reported two years of this maintenance in 82 patients with a healed gastric ulcer: ulcers came back in 12% (4 of 34) of the DGL-antacid group and 10% (4 of 41) of the cimetidine group in the first year, and in 29% (9 of 31) and 25% (8 of 32) by the end of the second year. Ulcers returned quickly once maintenance stopped. The tablet in both trials combined DGL with antacids, so these trials do not separate the effect of the DGL from that of the antacid.
Not every DGL ulcer trial was positive. In a 1978 trial in Gut, 96 patients with gastric ulcer were randomly given DGL or a placebo; after four weeks there was no difference between the groups in complete healing, in the reduction of ulcer area, or in clinical improvement.
The Morgan trials found the DGL-antacid tablet comparable to cimetidine, the standard ulcer drug of its day. Cimetidine was the first H2-receptor blocker; other H2 blockers followed (ranitidine, famotidine — on 1 April 2020 the US Food and Drug Administration asked manufacturers to withdraw all ranitidine products from the US market because of a contaminant, N-nitrosodimethylamine), and then proton-pump inhibitors (omeprazole, esomeprazole, pantoprazole). DGL is still used as a botanical option by people who prefer not to use proton pump inhibitors (PPIs) long-term, who have rebound symptoms on proton pump inhibitor (PPI) withdrawal, or who use proton pump inhibitors intermittently and want a daily maintenance option.
One limitation of the Morgan-era data is that it predates the recognition of Helicobacter pylori as the underlying cause of most duodenal ulcers (Marshall and Warren's 1983 paper). Modern duodenal ulcer management now starts with H. pylori eradication (triple or quadruple antibiotic therapy plus a proton pump inhibitor) rather than acid suppression alone. DGL in the modern era is used either as adjunct during H. pylori eradication, as maintenance therapy in the post-eradication phase, or as primary therapy for the subset of duodenal ulcers that are not H. pylori-positive (often nonsteroidal anti-inflammatory drug-associated).
Gastric Mucus Stimulation — The Primary Mechanism
The gastric epithelium is protected from autodigestion by a layer of mucus 50-450 micrometers thick, composed of gel-forming mucins (principally MUC5AC and MUC6) secreted by foveolar and mucous neck cells. This mucus layer traps a thin layer of bicarbonate at its base, creating a neutralizing buffer at the cell surface even when luminal pH is 1-2. Disruption of this mucus barrier — by nonsteroidal anti-inflammatory drugs (NSAIDs) that inhibit prostaglandin-mediated mucus secretion, by H. pylori that secretes urease and proteases that thin the mucus, or by alcohol that solubilizes the gel structure — exposes the underlying epithelium to acid attack and is the proximate mechanism of most peptic ulcers.
The DGL flavonoid fraction stimulates gastric mucus secretion through several pathways. Isoliquiritigenin appears to upregulate MUC5AC and MUC6 expression at the transcriptional level. Liquiritin and liquiritigenin enhance prostaglandin E2 production in gastric epithelial cells (the same prostaglandin pathway that nonsteroidal anti-inflammatory drugs inhibit). The result is a thicker, more robust mucus layer that better resists acid penetration and pepsin digestion.
This mechanism explains why DGL works as both a treatment (helping existing ulcers heal by restoring mucosal defense) and a prevention (protecting against nonsteroidal anti-inflammatory drug-induced injury when taken prophylactically). It also explains why DGL works without altering gastric acid output — unlike H2 blockers and proton pump inhibitors, which reduce acid production, DGL leaves acid output normal and strengthens the mucosal defense that handles the acid. This is mechanistically appealing because chronic acid suppression has its own downstream consequences (small intestinal bacterial overgrowth, calcium and magnesium malabsorption, B12 malabsorption, increased infection risk).
Epithelial Restitution — The Second Mechanism
The gastric and duodenal mucosa is one of the body's most rapidly regenerating tissues — the entire epithelial surface is turned over every 3-7 days under normal conditions. When superficial injury occurs (a small erosion from nonsteroidal anti-inflammatory drugs, a stress-related lesion, the early-stage breakdown that precedes a frank ulcer), epithelial restitution is the rapid migration of viable cells from the wound margins to cover the denuded area, followed by full epithelial regeneration from the gastric pit stem cells. This process can resurface a small erosion within 30-60 minutes when the local environment is supportive.
DGL flavonoids appear to accelerate the restitution process by several mechanisms: increased local prostaglandin E2 production (cytoprotective), increased expression of cell-migration-related cytoskeletal proteins, antioxidant action that protects migrating cells from reactive oxygen species at the wound margin, and reduced local inflammation that would otherwise impede restitution. In cell-culture and animal models, DGL or its flavonoid components measurably accelerate epithelial wound closure compared to vehicle control.
Practitioners take this to mean that DGL suits daily preventive use better than acute rescue. It is traditionally taken before meals (when the gastric acid stimulus peaks) and at bedtime (when the next-morning acid peak follows hours of low intake), with the aim of supporting the local environment that allows the natural restitution process to keep pace with the constant minor injury that any acid-secreting stomach inflicts on itself.
DGL and Helicobacter pylori — Adjunct Role
Helicobacter pylori is the gram-negative, microaerophilic, urease-producing bacterium implicated in roughly 70% of gastric ulcers and 90% of duodenal ulcers globally. Discovery of the organism by Marshall and Warren (Nobel Prize 2005) transformed peptic ulcer disease from a chronic relapsing condition managed by acid suppression into a curable infectious disease managed by short-course antibiotic therapy. The current standard for H. pylori eradication is one of several multi-drug regimens (clarithromycin triple therapy, bismuth quadruple therapy, levofloxacin-based salvage therapy) plus a proton-pump inhibitor, typically given for 10-14 days.
DGL has documented direct inhibitory activity against H. pylori in vitro. The mechanism is not fully characterized but appears to involve flavonoid-mediated disruption of bacterial cell membranes and inhibition of urease activity. The in vivo activity is much weaker than the in vitro activity, however — DGL alone has not been shown to eradicate H. pylori, and the standard antibiotic regimens above are the treatments shown to cure the infection.
Two trials in people tested licorice against H. pylori, neither using DGL itself. In a 2016 randomized trial of 120 people in Iran, adding licorice to a standard clarithromycin-based triple regimen for two weeks raised the eradication rate, checked six weeks after treatment, to 83.3% versus 62.5% with the triple regimen alone. In a 2013 placebo-controlled trial of 107 people, a flavonoid-rich licorice extract used alone (150 mg once daily for 60 days, no antibiotics) gave a negative stool antigen test at day 60 in 56% of the extract group versus 4% on placebo, and a negative breath test in 48% of the extract group.
The adjunct role for DGL in H. pylori management is twofold: (a) taken during antibiotic eradication, DGL appears to reduce the gastric mucosal irritation that the antibiotics themselves cause and may improve patient tolerance of the multi-drug protocol; (b) taken in the post-eradication phase, DGL supports mucosal recovery in the gastric epithelium that was damaged by the chronic H. pylori infection. There is also some evidence that DGL may reduce the rate of reinfection or recolonization, though this is less well-established.
For patients in whom standard antibiotic eradication has failed (resistant H. pylori is increasingly common), DGL is sometimes used as part of an extended natural protocol that includes mastic gum (also active against H. pylori), broccoli sprouts (sulforaphane), Manuka honey, and probiotic strains shown to inhibit H. pylori. These approaches are not among the standard first-line regimens, which are the treatments with trial evidence for curing the infection.
Functional Dyspepsia (Licorice Flavonoid Extract Trial)
Functional dyspepsia is the technical term for chronic upper-abdominal discomfort (postprandial fullness, early satiety, epigastric pain, epigastric burning) in the absence of an identifiable organic cause — ulcers, erosions, and tumors have been ruled out by endoscopy. It is one of the most common gastrointestinal complaints in primary care and is notoriously difficult to treat conventionally; proton pump inhibitors, prokinetics, and tricyclic antidepressants all have modest effect sizes and significant side-effect burdens.
A standardized, flavonoid-rich licorice extract has been tested in functional dyspepsia in one randomized, double-blind, placebo-controlled trial (Raveendra 2012): patients received the extract 75 mg twice daily or placebo for 30 days. Compared with placebo, the extract group had a significantly greater fall in total symptom scores and in the Nepean Dyspepsia Index (a quality-of-life score) at day 15 and at day 30, and the extract was generally well tolerated. The 2023 Cochrane review of non-Chinese herbal medicines for functional dyspepsia found only this one licorice trial, with 50 participants, and rated its evidence as moderate certainty.
This extract is essentially DGL with the flavonoid fraction further concentrated and standardized, so the proposed mechanism is the same as DGL more broadly (mucus stimulation, anti-inflammatory action, accelerated epithelial restitution). Practitioners describe it as an option for people who have already tried proton pump inhibitors, who have rebound symptoms when they try to stop them, or who prefer a botanical option. The trial used 75 mg twice daily. Dosing is straightforward: 75-150 mg twice daily, taken 30 minutes before meals.
Reflux and Gastroesophageal Reflux Disease (GERD)
Gastroesophageal reflux disease (GERD) involves the regurgitation of gastric contents into the esophagus, causing the characteristic heartburn and acid taste. Chronic untreated gastroesophageal reflux disease predisposes to Barrett's esophagus (intestinal metaplasia of the lower esophageal epithelium) and, rarely, to esophageal adenocarcinoma. Modern management is dominated by proton-pump inhibitors, which reduce gastric acid output by 90% or more and reliably relieve symptoms.
DGL is not a substitute for proton pump inhibitor therapy in moderate-to-severe gastroesophageal reflux disease or in any patient with Barrett's esophagus, where the dominant goal is acid suppression and where the trial evidence overwhelmingly favors proton pump inhibitor. Practitioners describe DGL use in two specific scenarios:
- Mild intermittent reflux — the patient who has heartburn 1-2 times per week, typically diet- or stress-triggered, and prefers not to be on daily proton pump inhibitor. DGL chewed before the high-risk meal (large dinner, alcohol-containing meal, late-evening meal) provides demulcent coating and mucus stimulation that reduces symptom intensity. Often combined with marshmallow root, slippery elm, and dietary modification.
- Proton pump inhibitor taper — the patient who has been on proton pump inhibitor long-term and wants to discontinue. Proton pump inhibitor rebound (rebound acid hypersecretion after discontinuation) is a well-documented phenomenon that makes many patients feel worse for 2-6 weeks after stopping their proton pump inhibitor and concludes that they "still need it." Practitioners report that DGL during the taper period helps with the rebound symptoms enough that many patients can discontinue proton pump inhibitor, particularly when combined with H2 blocker bridging and dietary modification.
In severe gastroesophageal reflux disease or Barrett's esophagus, DGL has been described only as a supportive adjunct, because acid suppression is the treatment with trial evidence there. For the more common mild reflux, practitioners describe DGL as a first botanical option.
Nonsteroidal Anti-Inflammatory Drug Gastroprotection
Nonsteroidal anti-inflammatory drugs — aspirin, ibuprofen, naproxen, diclofenac, and dozens of others — cause gastric and small-intestinal injury through two mechanisms: (a) direct topical toxicity to the gastric epithelium, and (b) systemic inhibition of cyclooxygenase-1 (COX-1), reducing the prostaglandin signaling that normally stimulates gastric mucus and bicarbonate secretion. Nonsteroidal anti-inflammatory drug gastropathy is the leading cause of medication-related gastrointestinal bleeding and is responsible for thousands of hospitalizations and deaths per year in the United States alone.
Standard gastroprotection for high-risk nonsteroidal anti-inflammatory drug users (older patients, history of ulcer, concurrent anticoagulation, concurrent corticosteroid) is a proton-pump inhibitor or misoprostol (a synthetic prostaglandin E1 analog). DGL has been studied as an alternative or adjunct gastroprotective agent in animal models and small clinical trials, with positive but limited evidence. The mechanism is mechanistically appealing: DGL restores the gastric mucus-bicarbonate barrier that the nonsteroidal anti-inflammatory drug has compromised, working with the body's defense system rather than suppressing acid production.
For low-dose aspirin users (cardioprotective daily aspirin 81 mg) at moderate risk, practitioners describe DGL 380-760 mg taken with the daily aspirin as a botanical gastroprotective approach. For higher-dose nonsteroidal anti-inflammatory drug users (full-strength ibuprofen for chronic pain, regular naproxen for arthritis), the gastroprotection named in gastroenterology guidelines is misoprostol or a proton pump inhibitor, and DGL is described only as additional support.
Oral Aphthous Ulcer (Canker Sore) Treatment
Recurrent aphthous stomatitis (canker sores) afflicts approximately 20% of adults at some point. The lesions are painful round-to-oval ulcers in the non-keratinized oral mucosa, with a yellow-white fibrinous base and a red inflammatory halo. Most heal spontaneously in 7-14 days, but the recurrent nature of the problem motivates a search for symptom-shortening interventions.
The evidence for licorice on canker sores comes from two small studies. In a 1989 report from India, 20 people with aphthous ulcers used a DGL mouthwash, with no comparison group: 15 of them described 50-75% improvement within one day, followed by complete healing of the ulcers by the third day. In a 2008 randomized, double-blind trial in the United States, a dissolving adhesive patch containing licorice (glycyrrhiza) root extract was compared with a placebo patch (23 people in each group) and with no treatment (23 people): by the fourth day, 81% of the licorice-patch group reported no pain before stimulation, against 63% with the placebo patch and 40% with no treatment, and by the eighth day their ulcers were significantly smaller. The rinse practitioners describe uses DGL dissolved in water (200 mg DGL in 200 mL warm water) held in the mouth for 2-3 minutes, four times daily for several days; that amount comes from practice, not from these study abstracts. Reported benefits of DGL on canker sores include shorter overall ulcer duration (typically 4-6 days instead of 7-14).
The mechanism is presumed to be the same flavonoid-mediated epithelial restitution and anti-inflammatory action that operates in the stomach, applied topically to the oral mucosa. A DGL rinse is cheap, and practitioners describe it as well tolerated. The intervention is cheap, safe, and well-tolerated, and is a reasonable first-line option for a non-immunocompromised patient with recurrent canker sores.
For recurrent aphthous stomatitis that does not respond to topical interventions, the differential diagnosis includes nutritional deficiency (iron, B12, folate, zinc), gluten sensitivity, Behçet's disease, human immunodeficiency virus (HIV), and inflammatory bowel disease. Canker sores that keep returning are a known sign of these conditions, which topical treatment does not address.
The Carbenoxolone Story — The Synthetic Cousin
Carbenoxolone is a synthetic derivative of glycyrrhetinic acid (the active metabolite of glycyrrhizin), developed in the 1960s as an oral ulcer-healing drug. It was widely used in British hospitals through the 1970s with respectable healing rates for gastric and duodenal ulcers, until two developments changed prescribing patterns: (a) H2 blockers (cimetidine, ranitidine) arrived in the late 1970s with better efficacy and fewer side effects, and (b) the mineralocorticoid effects of carbenoxolone (the same 11-beta-HSD2 inhibition mechanism as glycyrrhizin) were better characterized and discouraged routine use, particularly in older patients.
Carbenoxolone remains historically important for two reasons. First, it is an example of a clinically used drug whose entire structural and pharmacological design derived from a botanical lead (licorice). The discovery pipeline ran: ancient herbal observation → identification of glycyrrhizin as the active → identification of glycyrrhetinic acid as the active metabolite → semisynthetic modification (carbenoxolone) to improve ulcer-healing potency at the cost of greater mineralocorticoid effect → clinical use → obsolescence by safer alternatives. This is one of the more transparent botanical-to-pharmaceutical pathways in 20th-century drug development.
Second, the carbenoxolone experience reinforced the case for DGL. If a more potent glycyrrhetinic acid derivative produced enough mineralocorticoid effect to limit its clinical use, then deglycyrrhizination of the natural plant material was clearly the smarter direction — preserve the flavonoid-mediated ulcer-healing fraction (the part that produces the gastric mucus and restitution effects), remove the glycyrrhizin entirely (eliminating the cortisol problem). The DGL approach has aged better than the carbenoxolone approach.
Chewable vs Capsule Formulation
DGL is commercially available in two main formulations: chewable tablets (the original format) and swallowed capsules. Practitioners describe the chewable form as more effective for upper gastrointestinal applications, for a specific physiological reason.
Chewing mechanically stimulates salivary secretion and triggers the cephalic phase of digestion, which includes a vagally mediated increase in gastric mucus secretion. When DGL is dissolved in saliva during chewing, it contacts the oral mucosa, esophageal mucosa, and gastric mucosa directly as it is swallowed. The flavonoids exert local effects on each surface they touch. For aphthous ulcer or for esophageal reflux symptoms, this local contact is essential and a swallowed capsule simply will not deliver the same effect.
For pure gastric or duodenal applications — preventing nonsteroidal anti-inflammatory drug injury, supporting H. pylori eradication, managing functional dyspepsia — the capsule form may be acceptable but is generally still considered inferior to the chewable. Most experienced practitioners default to chewable DGL for all upper gastrointestinal indications and reserve capsules for patients who genuinely cannot tolerate the slightly bitter chewable taste.
The usual dose unit is 380 mg per chewable tablet. The usual direction is to chew thoroughly (30-60 seconds), so that the dissolved tablet coats the mouth and the upper esophagus before swallowing. Practitioners note that a small amount of water afterward does not matter, while rinsing the mouth out immediately after chewing washes away much of that coating.
Dosing and Practical Use
Doses used in the trials described on this page:
- Gastric ulcer (Morgan 1982) — a DGL-antacid tablet, six tablets daily for 6-12 weeks; maintenance (Morgan 1985) two tablets twice daily for up to two years
- Functional dyspepsia (Raveendra 2012) — a flavonoid-rich licorice extract, 75 mg twice daily for 30 days
- H. pylori (Puram 2013) — the same type of extract, 150 mg once daily for 60 days, without antibiotics
- Canker sores (Das 1989) — a DGL mouthwash; the study abstract gives no amount
Amounts practitioners describe, which were not tested in the trials above:
- Peptic ulcer (active treatment) — 380-760 mg chewed 20 minutes before each meal and at bedtime (3-4 times daily), for 8-12 weeks alongside H. pylori eradication when the infection is present
- Functional dyspepsia / chronic gastritis — 380 mg chewed 20 minutes before meals
- Gastroesophageal reflux disease / reflux symptom management — 380-760 mg chewed before the high-risk meal (typically the largest evening meal), used as needed
- Proton pump inhibitor taper support — 380 mg chewed twice daily during the taper window and for 6-8 weeks after discontinuation
- Nonsteroidal anti-inflammatory drug gastroprotection (low-dose aspirin) — 380 mg chewed with the daily aspirin
- Oral aphthous ulcer (canker sore) — 200 mg DGL dissolved in 200 mL warm water as a mouth rinse, held for 2-3 minutes, 4 times daily for 5-7 days
- Standardized flavonoid extract — 75-150 mg twice daily before meals; convenient for the patient who dislikes chewable taste
DGL can be taken concurrently with proton pump inhibitors, H2 blockers, antacids, sucralfate, and prokinetics without significant interaction. The one practical caution is that chewing DGL immediately before an antibiotic dose may slightly delay antibiotic absorption due to the mucus-coating effect, and practitioners describe leaving about 30 minutes between the two.
Safety Profile of DGL
DGL has one of the cleanest safety profiles in the herbal medicine canon. Long-term use is well-tolerated, no significant drug interactions are clinically meaningful at typical doses, no contraindications apply to specific populations beyond standard pregnancy caution (precautionary; the studied DGL doses have not shown harm but no fetal-outcome trials exist), and no monitoring is required. The contrast with whole licorice could not be sharper.
The only commonly reported adverse effect is mild diarrhea or loose stool at high doses (>3 g/day), which resolves with dose reduction. Occasional patients report mild nausea or oral irritation from the chewable form; these are not class effects but appear to relate to specific commercial preparations.
For pregnant or breastfeeding patients, DGL is not formally tested but is widely used in midwifery and integrative-OB practice for pregnancy-related reflux and indigestion. The deglycyrrhization process removes the constituent (glycyrrhizin) that drives the pregnancy concerns about whole licorice (preterm birth, altered fetal cortisol regulation), so the theoretical safety profile is favorable. Practitioners who use it in pregnancy describe short-course symptomatic use rather than chronic high-dose therapy; no pregnancy safety trial exists.
For pediatric use, DGL has been used in children with reflux and gastritis without reported safety concerns, though formal pediatric dosing studies are lacking. The chewable format is well-tolerated by children old enough to chew safely (typically >6 years).
Key Research Papers
- Morgan AG, McAdam WA, Pacsoo C, Darnborough A (1982). Comparison between cimetidine and Caved-S in the treatment of gastric ulceration, and subsequent maintenance therapy. Gut 23(6):545-551. — PubMed PMID: 7042486
- Morgan AG, Pacsoo C, McAdam WA (1985). Maintenance therapy: a two year comparison between Caved-S and cimetidine treatment in the prevention of symptomatic gastric ulcer recurrence. Gut 26(6):599-602. — PubMed PMID: 4007604
- Bardhan KD, Cumberland DC, Dixon RA, Holdsworth CD (1978). Clinical trial of deglycyrrhizinised liquorice in gastric ulcer. Gut 19(9):779-782. — PubMed PMID: 361512
- Tewari SN & Wilson AK (1973). Deglycyrrhizinated liquorice in duodenal ulcer. The Practitioner. — PubMed PMID: 4581313
- Raveendra KR et al. (2012). An extract of Glycyrrhiza glabra (GutGard) alleviates symptoms of functional dyspepsia: a randomized, double-blind, placebo-controlled study. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 21747893
- Wittschier N et al. (2009). Aqueous extracts and polysaccharides from liquorice roots inhibit adhesion of Helicobacter pylori to gastric mucosa. Journal of Ethnopharmacology. — PubMed PMID: 19607905
- Das SK et al. (1989). Deglycyrrhizinated liquorice in aphthous ulcers. Journal of the Association of Physicians of India. — PubMed PMID: 2632514
- Martin MD et al. (2008). A controlled trial of a dissolving oral patch for the treatment of aphthous ulcers. General Dentistry. — PubMed PMID: 18348383
- Hajiaghamohammadi AA, Zargar A, Oveisi S, Samimi R, Reisian S (2016). To evaluate of the effect of adding licorice to the standard treatment regimen of Helicobacter pylori. Brazilian Journal of Infectious Diseases 20(6):534-538. — PubMed PMID: 27614124
- Báez G, Vargas C, Arancibia M, Papuzinski C, Franco JV (2023). Non-Chinese herbal medicines for functional dyspepsia. Cochrane Database of Systematic Reviews 6:CD013323. — PubMed PMID: 37323050
- Puram S et al. (2013). Effect of GutGard in the management of Helicobacter pylori: a randomized double blind placebo controlled study. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 23606875
- Dehpour AR, Zolfaghari ME, Samadian T, Kobarfard F, Faizi M, Assari M (1995). Antiulcer activities of liquorice and its derivatives in experimental gastric lesion induced by ibuprofen in rats. International Journal of Pharmaceutics 119(2):133-138. — doi:10.1016/0378-5173(94)00377-H
- Wang Z & Nixon DW (2001). Licorice and cancer. Nutrition and Cancer. — PubMed PMID: 11588889
- Larkworthy W & Holgate PF (1975). Deglycyrrhizinized liquorice in the treatment of chronic duodenal ulcer. A retrospective endoscopic survey of 32 patients. The Practitioner. — PubMed PMID: 772652
- Marshall BJ & Warren JR (1984). Unidentified curved bacilli in the stomach of patients with gastritis and peptic ulceration. The Lancet. — PubMed
- Bell AE et al. (1985). Properties of gastric and duodenal mucus: effect of proteolysis, disulfide reduction, bile, acid, ethanol, and hypertonicity on mucus gel structure. Gastroenterology. — PubMed PMID: 3917263
PubMed Topic Searches
Connections
- All Herbs
- Licorice Overview
- Licorice Benefits Hub
- Adrenal Support and Cortisol
- Antiviral Activity
- Cortisol and Hypertension Warning
- Marshmallow Root
- Slippery Elm
- Aloe Vera
- Ginger
- Peptic Ulcer Disease
- Gastritis
- Gastroesophageal Reflux Disease
- Reflux and Heartburn
- Functional Dyspepsia
- Helicobacter pylori
- Gut Healing
- Aspirin Side Effects
- Canker Sores
- History