⚠ Evidence warning: Clinical trials or other evidence do not support the claim that topical Echinacea speeds the healing of chronic and infected wounds, venous and diabetic ulcers and reduces scarring, or that an Echinacea mouth rinse reaches antifungal levels against thrush. This page keeps it as a report of what people, websites or other media say.
Echinacea Antimicrobial Activity and Wound Healing
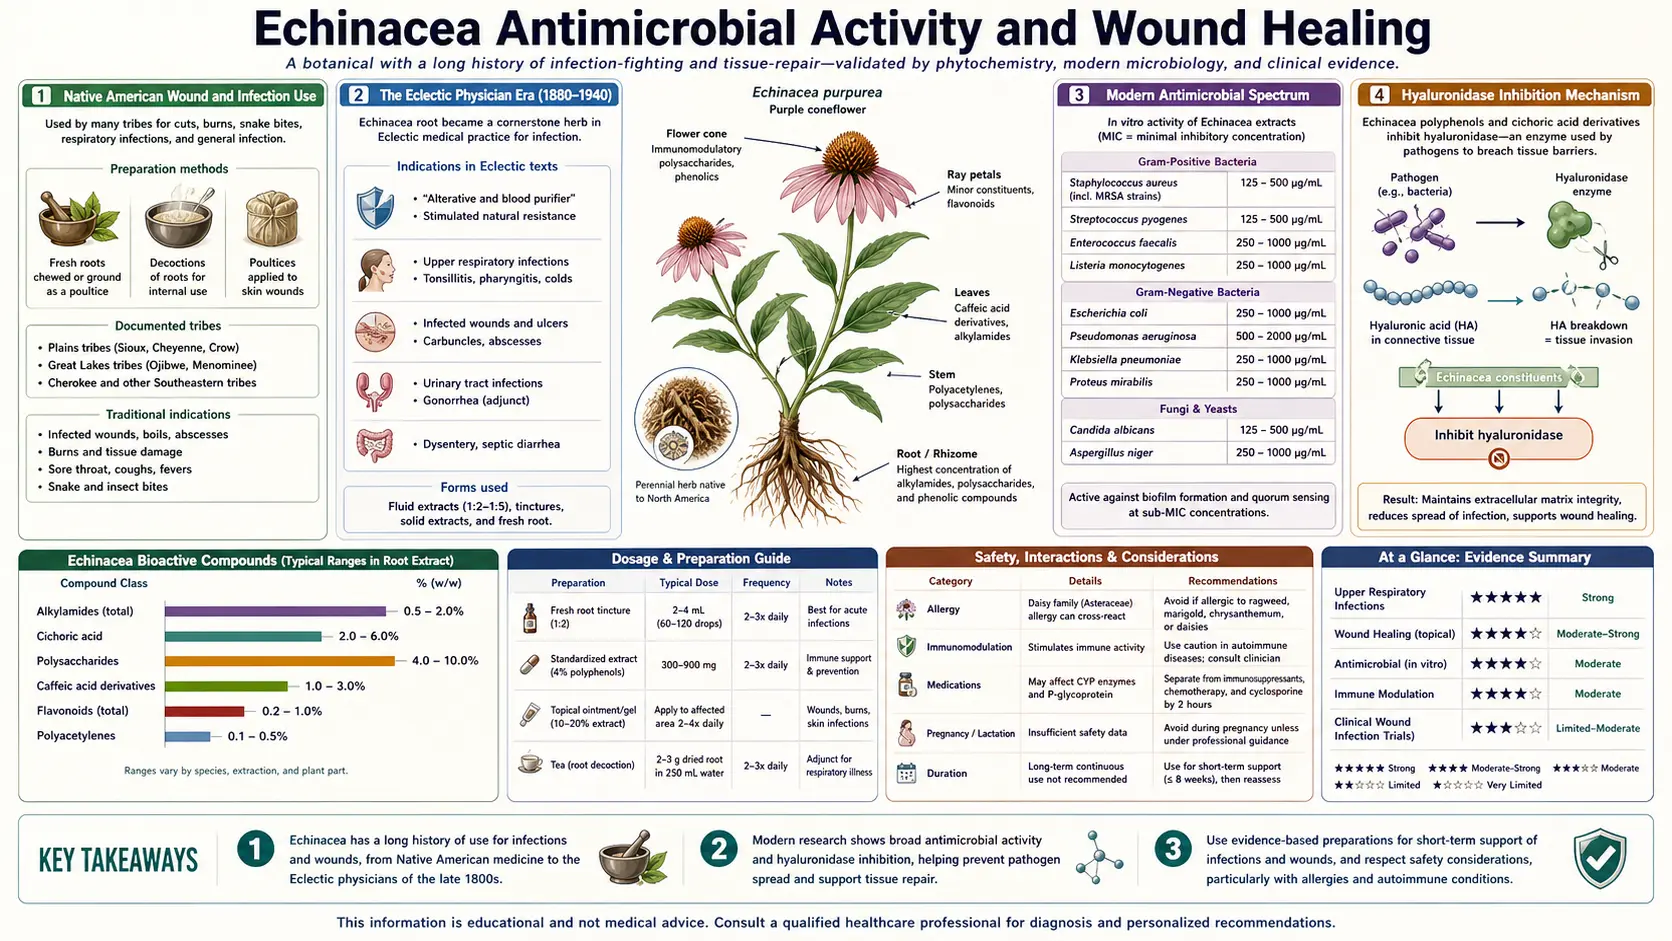
Long before "Echinacea for colds" became the modern marketing pitch, the plant was the most important external-medicine herb of the Plains tribes of North America. The Lakota, Cheyenne, Comanche, and Pawnee used the root of Echinacea angustifolia as a poultice on snakebites, infected wounds, abscesses, burns, insect stings, and gangrenous extremities. The Eclectic physicians of the 1880s adopted the same indication, and "Echafolta" and "Specific Echinacea" were standard pharmacy items for septic conditions before the antibiotic era arrived in the 1940s. Laboratory studies have found that a standardized E. purpurea extract readily kills Streptococcus pyogenes and Haemophilus influenzae; Staphylococcus aureus was less sensitive and Candida albicans relatively resistant. The mechanism is not classical antibiotic-style bacterial-cell-wall disruption but rather a combination of hyaluronidase inhibition (which slows tissue spread of invading bacteria), direct membrane disruption by the lipophilic alkylamides, and host wound-healing acceleration through fibroblast stimulation. The German Commission E formally approved external Echinacea preparations for poorly-healing wounds and chronic ulcerations, and the herb remains a staple of European wound-care herbal practice.
Table of Contents
- Native American Wound and Infection Use
- The Eclectic Physician Era (1880-1940)
- Modern Antimicrobial Spectrum
- Hyaluronidase Inhibition Mechanism
- Alkylamide Membrane Disruption
- Antifungal Activity (Candida)
- Wound-Healing Mechanism
- Topical Preparations (Cream, Ointment, Poultice)
- Wound and Mouth-Sore Studies
- German Commission E and European Medicines Agency Approval
- How Topical Echinacea Is Used
- Key Research Papers
- Connections
- Featured Videos
Native American Wound and Infection Use
The principal medicinal use of Echinacea in pre-Columbian North America was as an external-application wound and antivenom herb. Ethnobotanical documentation from the 19th and early 20th centuries records consistent use of E. angustifolia root by at least 14 distinct Plains and Great Basin tribal nations:
- Snakebite — the most widely reported use. The root was chewed and applied directly to the bite site, with the patient also consuming a decoction of the root internally. Used for rattlesnake bite specifically across multiple Plains nations.
- Insect stings and bites — spider bite, scorpion sting, wasp sting, mosquito bite were all treated with topical root paste.
- Wounds and abscesses — the root was chewed and packed into wounds, or a decoction was used to wash wounds and infected abscess cavities. The Lakota name Iccap'eta-hu translates roughly as "burning plant" referring to the tingling sensation of fresh root contact with mucous membranes.
- Burns — topical application of root paste to burn injury.
- Toothache and gum infection — the root was held between the cheek and gum or chewed to bathe the affected tooth. The tongue-tingling alkylamide sensation also produced a numbing effect.
- Sore throat — root chewed slowly to release saliva-mediated extraction onto the throat tissue.
- Septic and gangrenous conditions — advanced infected wounds and necrotic tissue were dressed with Echinacea root preparations as one of the few options available in pre-antibiotic indigenous practice.
The ethnobotanical record was the bridge that brought Echinacea to settler-Western medicine. Dr. H.C.F. Meyer, a German immigrant practicing in Pawnee City, Nebraska, in the 1870s, observed Native American use of the plant for snakebite and adopted it into his own practice as "Meyer's Blood Purifier." Meyer's commercial preparations were widely advertised in the 1880s and 1890s, and his correspondence with John King and John Uri Lloyd (the leading Eclectic medical figures of the era) brought Echinacea into the formal Eclectic pharmacopoeia.
The Eclectic Physician Era (1880-1940)
The Eclectic medical movement (1830s-1940s) was a uniquely American school of botanical medicine that integrated indigenous herbal knowledge with formal Western medical practice. The Eclectic Medical Institute in Cincinnati and the Lloyd Brothers Pharmaceutical Company were the institutional centers. From approximately 1885 to 1940, Echinacea was one of the most-prescribed botanical medicines in the United States, with hundreds of clinical case reports published in the Eclectic Medical Journal.
Standard Eclectic indications for Echinacea included:
- Septicemia and blood poisoning — the era's leading cause of post-traumatic and post-surgical mortality. Echinacea was used both topically on the wound and internally as a tincture in cases of advancing bacterial infection.
- Boils, carbuncles, and abscesses — with consistent reporting of accelerated drainage and resolution.
- Acute pharyngitis and tonsillitis — including diphtheritic pharyngitis (before diphtheria antitoxin was available).
- Peritonitis and acute appendicitis — used as adjunct to drainage, with some recorded cases of resolution without surgery (which would now be considered remarkable but plausible given that antibiotic-treated appendicitis is increasingly accepted in modern practice).
- Erysipelas, cellulitis, and lymphangitis — the streptococcal skin and soft-tissue infections, against which the antimicrobial activity of Echinacea is most clearly demonstrated in modern lab studies.
- Septic ulcerations, gangrene, and post-traumatic infection — the same wound-care indications as Plains-tribes use, formalized into clinical practice.
The Eclectic clinical experience was largely lost with the school's decline after the 1910 Flexner Report and the antibiotic revolution of the 1940s. The German Commission E monographs and, later, the European Medicines Agency monograph effectively re-established formal regulatory recognition of the external-wound indication, though without the breadth of the original Eclectic use spectrum. The modern European herbal-practice approval for poorly-healing wounds and chronic ulcerations is a narrow modern echo of what was once a much broader clinical application.
Modern Antimicrobial Spectrum
In-vitro antimicrobial testing has documented direct activity of Echinacea extracts against multiple clinically important bacterial and fungal pathogens. The activity is generally moderate — less potent than classical antibiotics — but is reproducible and clinically relevant for topical use where high local concentrations can be achieved:
- Streptococcus pyogenes (Group A strep, the cause of strep throat, scarlet fever, erysipelas, necrotizing fasciitis) — consistent susceptibility across multiple studies, with minimum inhibitory concentrations (MICs) in the low milligram-per-milliliter range
- Haemophilus influenzae (otitis media, bacterial sinusitis, lower respiratory infection) — documented activity, particularly relevant given the upper-respiratory clinical-use pattern
- Legionella pneumophila — in-vitro activity demonstrated, clinical relevance unclear
- Staphylococcus aureus, both methicillin-resistant Staphylococcus aureus (MRSA) and methicillin-sensitive strains — less sensitive to the bactericidal effect than the bacteria above in the 2010 study
- Mycobacterium smegmatis — also less sensitive in the same study; clinical evidence is absent
- Candida albicans — relatively resistant in the same study; see the fungal section below
The bactericidal study behind this list (Sharma and colleagues, 2010) used a standardized commercial E. purpurea extract. It readily killed Streptococcus pyogenes, Haemophilus influenzae and Legionella pneumophila, and it also reversed the inflammation those bacteria triggered in cultured airway (bronchial) cells. Staphylococcus aureus (both methicillin-resistant and sensitive strains) and Mycobacterium smegmatis were less sensitive to being killed, though the inflammation they triggered was still reversed, and Candida albicans was relatively resistant. These are laboratory (cell-culture) results, not results in people.
The clinical translation is that Echinacea is not a substitute for conventional antibiotic therapy in established serious bacterial infection. Herbal practice uses it as an add-on in mild surface infections, in wound care where pathogen load is part of the slow-healing picture, and in upper-respiratory infections where the antimicrobial activity combines with the immune-modulation and direct antiviral activity against the predominant viral pathogens.
Hyaluronidase Inhibition Mechanism
One of the most well-characterized antimicrobial-adjacent mechanisms of Echinacea is inhibition of bacterial hyaluronidase. Hyaluronic acid is a high-molecular-weight glycosaminoglycan that forms a key component of the extracellular matrix of human connective tissue, particularly in skin, joints, and fascial planes. It functions as a tissue-binding "glue" that resists invasion by foreign matter.
Many bacterial pathogens have evolved hyaluronidase enzymes that depolymerize host hyaluronic acid, dissolving the connective tissue barrier and permitting rapid bacterial spread along tissue planes. Streptococcus pyogenes, Staphylococcus aureus, Clostridium perfringens, and Streptococcus pneumoniae all express hyaluronidase. The dramatic tissue-spreading infections (necrotizing fasciitis, gas gangrene, severe cellulitis) depend on hyaluronidase activity for their characteristic rapid spread.
Echinacea caffeic acid derivatives are competitive hyaluronidase inhibitors. In E. angustifolia root, a 1993 laboratory study found chicoric acid (also spelled cichoric acid) and caftaric acid to be the strongest, with half-maximal inhibitory concentrations (IC50) of 0.42 and 0.61 millimolar (mM), against 1.85 mM for cynarine and 2.25 mM for chlorogenic acid; the most active crude extract fractions had IC50 values of 0.44 to 0.62 mg per mL. These are millimolar, not micromolar, amounts. Echinacoside is found mainly in E. pallida, with only traces in E. angustifolia. No study has shown that these concentrations are reached in a human wound. The mechanism explains:
- The traditional Plains-tribes use for snakebite (most snake venoms contain hyaluronidase as a spreading factor)
- The traditional use for tissue-spreading infections like erysipelas and cellulitis
- The Eclectic-era observations of rapid localization and walling-off of advancing soft-tissue infections after Echinacea poultice application
- The modern topical use for slow-healing wounds where pathogen-driven tissue breakdown contributes to the failure to heal
An animal study supports the link. In a 2002 rat study, the total root extract of E. pallida and its constituent echinacoside, applied to the skin, showed good anti-inflammatory and wound-healing effects compared with E. purpurea and untreated controls; the authors put this down to echinacoside’s hyaluronidase blocking. It was a rat study, not a human trial.
The hyaluronidase-inhibition mechanism is distinct from direct bacterial killing. Echinacea does not necessarily reduce bacterial counts in the infected wound; instead it slows the spread of the infection while host immune mechanisms (which Echinacea also supports through the immunomodulation mechanism) catch up and clear the pathogens. This is a fundamentally different therapeutic strategy from classical antibiotics and explains why Echinacea continues to have a useful role in wound care alongside (not instead of) conventional antimicrobials when needed.
Alkylamide Membrane Disruption
The lipophilic alkylamides have direct antimicrobial activity through a second mechanism — insertion into and disruption of bacterial and fungal cell membranes. The dodeca-2,4,8,10-tetraenoic acid isobutylamide is the prototypical example. Its long unsaturated hydrocarbon chain is structurally similar to membrane-active fatty acids and can integrate into bacterial cell membranes, altering membrane fluidity, disrupting proton gradients, and ultimately producing cell-membrane permeabilization at sufficient local concentration.
This mechanism is most relevant for topical applications where direct contact between high concentrations of alkylamide and the pathogen is achievable. For oral systemic dosing, plasma alkylamide concentrations are well below the membrane-disrupting threshold, so the systemic antimicrobial effect (if any) is mediated through the immune-modulation mechanisms rather than direct pathogen killing.
The tongue-tingling sensation experienced after a swig of fresh Echinacea root tincture is direct evidence of the alkylamide's membrane-active properties — the same lipophilic interaction with bacterial membranes also stimulates oral free-nerve-ending sensory neurons. This sensory effect can be used as a quality-control indicator for tincture potency: a tincture that does not produce strong tongue tingling has likely lost its alkylamide content through age, heat exposure, or poor manufacturing.
Antifungal Activity (Candida)
Several Echinacea-fungal interaction studies have documented activity against pathogenic Candida species:
- Candida albicans (the most common oral and vaginal candidiasis pathogen) — relatively resistant to a standardized E. purpurea extract in the 2010 bactericidal study (Sharma and colleagues)
- Candida glabrata, C. krusei, C. tropicalis — the non-albicans Candida species that are increasingly common and often azole-resistant; documented in-vitro susceptibility
- Aspergillus species — some activity demonstrated, clinical relevance limited
- Trichophyton rubrum and other dermatophytes — documented inhibition relevant for topical use in tinea infections
The antifungal mechanism involves both the membrane-disrupting alkylamide effect and the immune-modulation effect on macrophage-mediated fungal killing. For oral candidiasis (thrush), traditional use is an Echinacea tincture swished and held in the mouth for 30-60 seconds; practitioners hold that this reaches mucosal concentrations high enough for a direct antifungal effect. This has not been tested in trials.
For vaginal candidiasis, oral Echinacea has been used as part of comprehensive integrative protocols, often combined with topical antifungals, probiotics, and dietary modifications. The Echinacea contribution is primarily immune-modulation rather than direct antifungal effect since systemic plasma concentrations after oral dosing are well below the in-vitro antifungal threshold.
Wound-Healing Mechanism
Beyond the antimicrobial activity, Echinacea actively promotes wound healing through several mechanisms on the host wound-bed:
- Fibroblast stimulation — topical Echinacea increases fibroblast proliferation in wound-bed biopsies and accelerates collagen deposition during the proliferative phase of wound healing (day 3 through week 3 of a typical healing wound)
- Angiogenesis support — new blood vessel formation in the wound bed is enhanced, improving oxygen and nutrient delivery for active healing
- Reduced inflammation phase duration — the early inflammatory phase of wound healing (days 1-3) tends to resolve faster with topical Echinacea, allowing the proliferative phase to begin sooner
- Epithelial migration — keratinocyte migration across the wound surface (the closure of the epithelial defect) is modestly accelerated
- Reduced scar formation — some animal-model evidence suggests reduced hypertrophic scarring with topical Echinacea-treated wounds compared with controls, possibly through modulation of the transforming growth factor beta (TGF-beta) signaling that drives excessive collagen deposition
- Hyaluronidase inhibition extends to host tissue — the same mechanism that slows bacterial spread also protects newly-deposited extracellular matrix from inflammation-associated degradation
Laboratory work on this exists. A 2023 study made E. purpurea extracts in glycerol. They blocked hyaluronidase (IC50 values below 30 microlitres of extract per mL) and helped human skin cells (HaCaT keratinocytes) close a scratch “wound” in a dish at concentrations as low as 2.5 microlitres of extract per mL. This is cell work, not a human wound trial.
The combined antimicrobial-plus-wound-healing activity is the rationale for the modern European topical-wound indication. Slow-healing wounds (diabetic foot ulcers, venous stasis ulcers, pressure ulcers, post-surgical dehiscence) often involve both bacterial colonization and impaired host healing response. Echinacea preparations address both, complementing rather than replacing conventional wound-care interventions (debridement, compression for venous ulcers, offloading for diabetic foot ulcers, systemic antibiotics if needed for established infection).
Topical Preparations (Cream, Ointment, Poultice)
Several topical Echinacea preparations are commercially available, each with different characteristics:
- Standardized E. purpurea hand cream and wound gel — commercial products with a standardized E. purpurea extract in a moisturizing or hydrogel base. The hand creams are sold for daily skin maintenance and minor surface healing; the wound gels for cuts, abrasions, and slow-healing surface wounds.
- Echinacea ointment (various manufacturers) — oil-based ointment preparations suitable for chapped, cracked, or weeping skin lesions. The oil base extends the local contact time of the active constituents.
- Echinacea-containing wound-care formulations — the European herbal-medicine market includes a range of combined products incorporating Echinacea with calendula (Calendula officinalis), arnica (Arnica montana), comfrey (Symphytum officinale), and St. John's wort (Hypericum perforatum) for wound and bruise applications.
- DIY tincture-soaked dressings — a traditional approach soaks gauze in an alcoholic Echinacea tincture (typically diluted 1:5 in saline or water), laid on the wound bed under a non-adherent secondary dressing; herbal sources describe changing it every 12-24 hours.
- Powdered root poultice — the historical preparation used by Plains tribes and Eclectic physicians. Dried Echinacea root powder mixed with hot water to form a paste, applied directly to the wound, covered with a cloth dressing. Rarely used in modern Western practice but remains the highest-concentration topical application for severe infected wounds in some traditional-herbal protocols.
For minor everyday cuts, scrapes, and surface wounds in immunocompetent patients, ordinary wound care (cleansing with mild soap and water, topical antiseptic or petroleum jelly, non-adherent dressing) is generally adequate. Echinacea topical preparations offer no clear advantage in these uncomplicated cases. The niche described in herbal practice is slow-healing wounds, chronic ulcerations, infected wounds where systemic antibiotics are contraindicated or insufficient, and in patients with impaired wound healing (diabetes, peripheral arterial disease, elderly, immunocompromised).
Wound and Mouth-Sore Studies
The evidence for Echinacea on wounds is much thinner than the cold-and-flu literature. What exists is an animal study, case series, and two small trials of Echinacea tablets for mouth sores:
- Speroni 2002 (animal study) — in rats, the total root extract of E. pallida and its constituent echinacoside, applied to the skin, showed good anti-inflammatory and wound-healing effects compared with E. purpurea and untreated controls; the authors credit echinacoside’s hyaluronidase-blocking activity
- Multiple case series in the European herbal-medicine literature report successful use of topical Echinacea for slow-healing diabetic foot ulcers, post-radiation skin breakdown, and pressure ulcers, though without the methodological rigor of large randomized trials
- Saberi 2022 (mouth sores, tablets) — in a randomized, double-blind, placebo-controlled trial of 70 people with erosive oral lichen planus, Echinacea tablets taken three times a day for 35 days, alongside betamethasone lotion or nystatin mouthwash, lowered pain scores more than placebo at every visit (P < 0.001)
- Khozeimeh 2018 (mouth sores, tablets) — in 50 people with recurrent minor mouth ulcers (aphthous ulcers), 25 took three Echinacea tablets a day for five weeks and 25 took no tablets; over six months the tablet group had fewer ulcers, less pain, more complete healing and fewer recurrences. There was no placebo.
The two human trials used tablets taken by mouth, not a cream, and treated mouth sores, not skin wounds. For creams and ointments on wounds, the support is laboratory and animal work plus the long traditional-use history. The German Commission E and European Medicines Agency monographs accept the wound-healing indication as a "traditional use" supported by extensive ethnopharmacological history rather than as a "well-established medical use" requiring large modern randomized controlled trials (RCTs).
German Commission E and European Medicines Agency Approval
The German Commission E (the regulatory body for herbal medicines in Germany from 1978-1994) issued formal monographs for Echinacea angustifolia, E. pallida, and E. purpurea, with approved indications including:
- E. purpurea aerial-parts pressed juice — internal: prevention and supportive treatment of colds and chronic infections of the respiratory and lower urinary tract; external: poorly-healing wounds and chronic ulcerations
- E. pallida root — supportive treatment of flu-like infections
- E. angustifolia root — no formal monograph approval despite extensive traditional use, primarily due to the absence of standardized clinical trials at the time of Commission E review
The European Medicines Agency (EMA) Committee on Herbal Medicinal Products (HMPC) has subsequently issued European Union-wide monographs for several Echinacea preparations, including a monograph for Echinaceae purpureae herba (the pressed juice of the fresh flowering aerial parts; EMA/HMPC/48704/2014 Corr., first published 2015). Its two indications are classed differently:
- Internal use (by mouth): short-term prevention and treatment of common colds — classed as “well-established use”, meaning published scientific evidence of effectiveness and safety covering at least 10 years in the EU
- External use (on the skin): treatment of small superficial wounds — classed as “traditional use”, meaning the clinical-trial evidence is insufficient, but the use is plausible and has been used safely for at least 30 years, including at least 15 years in the EU
The EMA’s summary limits these medicines to adults and adolescents over 12, and states that wound symptoms lasting more than one week are a reason to consult a doctor or qualified healthcare practitioner. A call for new scientific data for a periodic review of the monograph (Revision 2) ran from February to May 2024.
The regulatory acceptance is meaningful because it establishes Echinacea as a recognized medicinal product in European Union herbal regulation, with standards for manufacturing quality, labeling, and pharmacovigilance comparable to (though distinct from) conventional pharmaceutical regulation.
How Topical Echinacea Is Used
How herbal sources describe topical Echinacea use, set beside the standard care for each problem:
- Minor cuts and abrasions — used alongside ordinary cleansing. Herbal sources describe a thin layer of Echinacea cream or ointment 2-3 times daily after gentle cleansing, under a non-adherent dressing where needed.
- Slow-healing surface wounds — herbal sources describe Echinacea ointment or cream 2-3 times daily alongside standard wound care, continued for the duration of healing.
- Chronic venous leg ulcers — compression therapy is the primary treatment in standard care; herbal practice uses topical Echinacea alongside compression, not in place of it.
- Diabetic foot ulcers — standard care is taking pressure off the foot (offloading), blood-sugar control, and checks for poor leg circulation (peripheral arterial disease) and bone infection (osteomyelitis); herbal practice uses topical Echinacea only alongside that care, not as a replacement for it.
- Suspected bacterial wound infection — topical Echinacea is not a substitute for systemic antibiotics. Spreading redness (erythema), warmth, drainage, red streaks running up from the wound (lymphangitis), and fever or feeling generally unwell (systemic symptoms) are signs of spreading infection that hospitals treat as urgent.
- Insect bites and stings — a fresh Echinacea poultice or topical ointment is used traditionally, and people report some relief and faster settling. Severe allergic reactions (anaphylaxis) are treated with epinephrine, not Echinacea.
- Snakebite — the traditional indication, but modern treatment of envenomation is antivenom, supportive care, and emergency medical management. Echinacea has historical interest only in this setting.
- Mucosal use (mouth, throat) — traditionally, an alcoholic tincture diluted 1:3 to 1:5 in water is used as a gargle or mouthwash for sore throat or oral inflammation, held in the mouth for 30-60 seconds before spitting or swallowing.
For more on related botanical wound-care herbs, see our pages on Goldenseal (traditionally combined with Echinacea for both internal and topical use in infection) and on Bone Broth (a collagen-rich traditional food). For severe infections requiring antimicrobial therapy, see the Infectious Disease section.
Key Research Papers
- Sharma SM, Anderson M, Schoop SR, Hudson JB (2010). Bactericidal and anti-inflammatory properties of a standardized Echinacea extract (Echinaforce): dual actions against respiratory bacteria. Phytomedicine 17(8-9):563-568. — PubMed PMID: 20036523
- Hudson J, Vimalanathan S (2011). Echinacea—A source of potent antivirals for respiratory virus infections. Pharmaceuticals (Basel) 4(7):1019-1031. — doi:10.3390/ph4071019
- Speroni E, Govoni P, Guizzardi S, Renzulli C, Guerra MC (2002). Anti-inflammatory and cicatrizing activity of Echinacea pallida Nutt. root extract. Journal of Ethnopharmacology 79(2):265-272. — PubMed PMID: 11801391
- Wagner H, Jurcic K (2002). Immunological studies of Revitonil, a phytopharmaceutical containing Echinacea purpurea and Glycyrrhiza glabra root extract. Phytomedicine 9(5):390-397. — PubMed PMID: 12222657
- Bisset NG (1994). Herbal Drugs and Phytopharmaceuticals (Wichtl M, ed.) CRC Press. Echinacea purpurea monograph. (Book; not indexed in PubMed.)
- Stimpel M, Proksch A, Wagner H, Lohmann-Matthes ML (1984). Macrophage activation and induction of macrophage cytotoxicity by purified polysaccharide fractions from the plant Echinacea purpurea. Infection and Immunity 46(3):845-849. — PubMed PMID: 6389368
- Binns SE, Hudson J, Merali S, Arnason JT (2002). Antiviral activity of characterized extracts from Echinacea spp. (Heliantheae: Asteraceae) against herpes simplex virus (HSV-I). Planta Medica 68(9):780-783. — PubMed PMID: 12357386
- Mishima S, Saito K, Maruyama H, Inoue M, Yamashita T, Ishida T, Gu Y (2004). Antioxidant and immuno-enhancing effects of Echinacea purpurea. Biological and Pharmaceutical Bulletin 27(7):1004-1009. — PubMed PMID: 15256730
- Kim LS, Waters RF, Burkholder PM (2002). Immunological activity of larch arabinogalactan and Echinacea: a preliminary, randomized, double-blind, placebo-controlled trial. Alternative Medicine Review 7(2):138-149. — PubMed PMID: 11991793
- Hudson JB (2012). Applications of the phytomedicine Echinacea purpurea (Purple Coneflower) in infectious diseases. Journal of Biomedicine and Biotechnology 2012:769896. — PubMed PMID: 22131823
- Facino RM, Carini M, Aldini G, Marinello C, Arlandini E, Franzoi L, Colombo M, Pietta P, Mauri P (1993). Direct characterization of caffeoyl esters with antihyaluronidase activity in crude extracts from Echinacea angustifolia roots by fast atom bombardment tandem mass spectrometry. Farmaco 48(10):1447-1461. — PubMed PMID: 8117383
- Ciganović P, Jakupović L, Momchev P, Nižić Nodilo L, Hafner A, Zovko Končić M (2023). Extraction optimization, antioxidant, cosmeceutical and wound healing potential of Echinacea purpurea glycerolic extracts. Molecules 28(3):1177. — PubMed PMID: 36770844
- Saberi Z, Etemadi M, Faghihian E (2022). Evaluation of the efficacy of Echinacea on clinical indices of erosive oral lichen planus: a randomized double-blind clinical trial. Dental Research Journal (Isfahan) 19:98. — PubMed PMID: 36605140
- Khozeimeh F, Saberi Z, Tavangar A, Badi FF (2018). Effect of herbal Echinacea on recurrent minor oral aphthous ulcer. Open Dentistry Journal 12:567-571. — PubMed PMID: 30258501
- European Medicines Agency, Committee on Herbal Medicinal Products. European Union herbal monograph on Echinacea purpurea (L.) Moench., herba recens. EMA/HMPC/48704/2014 Corr. (2015). — EMA: Echinaceae purpureae herba