Echinacea for Cold and Flu Prevention
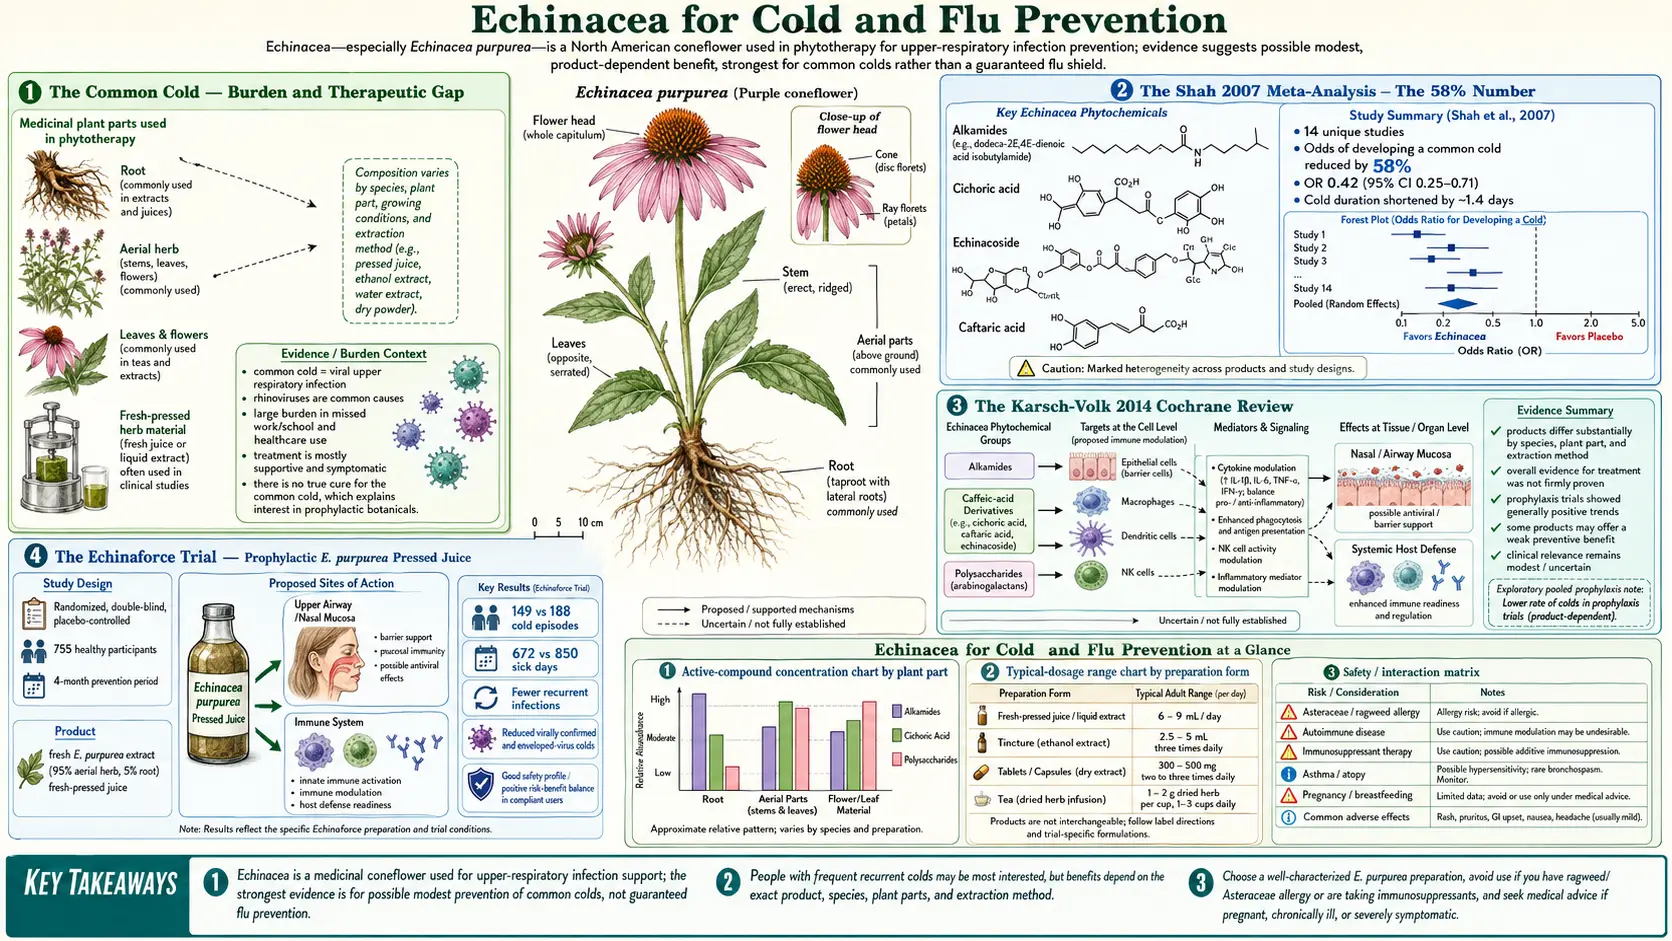
Echinacea is the most-studied herb in the world for the common cold, with more than two dozen randomized controlled trials and several large meta-analyses. The headline finding from the Shah 2007 Lancet Infectious Diseases meta-analysis is that Echinacea reduced the odds of developing a cold by 58% and shortened cold duration by approximately 1.4 days compared with placebo, but those numbers conceal a large amount of preparation-by-preparation variability. The 2014 Karsch-Volk Cochrane review of 24 trials found that none of the individual prevention comparisons reached statistical significance, but a post hoc pooling suggested a relative risk reduction of 10% to 20%, and the authors judged a weak benefit from some Echinacea products possible. This deep-dive walks through the major trials, the preparation-method variable that determines whether a given study shows benefit or null, the prophylaxis-versus-at-onset distinction, the species and plant-part differences that explain the inconsistency, the trials in children, and the preparations and doses the trials used.
Table of Contents
- The Common Cold — Burden and Therapeutic Gap
- The Shah 2007 Meta-Analysis — The 58% Number
- The Karsch-Volk 2014 Cochrane Review
- The 2012 Jawad Trial — Prophylactic Fresh-Plant E. purpurea Extract
- Three Species, Different Chemistry, Different Trial Results
- Root vs Aerial Parts — Why It Matters
- Prophylaxis vs At-Onset Treatment
- The Negative Trials (Turner 2005, Barrett 2010)
- Influenza — What the Evidence Does and Doesn't Show
- Preparations and Doses Used in the Trials
- Echinacea Trials in Children
- Key Research Papers
- Connections
- Featured Videos
The Common Cold — Burden and Therapeutic Gap
The common cold (acute viral rhinopharyngitis) is the most common acute illness in the developed world. The average adult experiences two to three episodes per year, the average school-age child six to ten. The economic burden in the United States alone is estimated at $40 billion annually in direct medical costs plus lost productivity. There is no curative therapy — the more than 200 rhinoviruses and dozens of coronavirus, parainfluenza, respiratory syncytial virus (RSV), and adenovirus serotypes that cause colds make vaccine development effectively impossible.
The conventional pharmacy aisle for cold treatment is mostly symptomatic: decongestants (pseudoephedrine, oxymetazoline), antihistamines, expectorants (guaifenesin), antitussives (dextromethorphan), and analgesic-antipyretics (acetaminophen, ibuprofen). None of these shorten the underlying viral illness; they only blunt the symptoms while the immune system clears the infection over five to ten days. Antibiotics are inappropriate and harmful for viral colds — they don't help the virus, they kill the patient's commensal microbiome, and they drive antibiotic resistance.
The therapeutic gap is exactly the niche Echinacea occupies in the popular pharmacopoeia. Roughly 10 million U.S. adults take Echinacea annually, the great majority for cold or flu. It is the second-most-used botanical in the country after ginseng. The clinical question is whether the popular use is supported by evidence. The answer, properly stratified by preparation, is a qualified yes — for some products taken in some patterns, there is a real but modest benefit.
The Shah 2007 Meta-Analysis — The 58% Number
The most-cited single statistic on Echinacea comes from Shah and colleagues at the University of Connecticut, published in The Lancet Infectious Diseases in July 2007. The authors pooled 14 placebo-controlled randomized trials and reported two headline numbers:
- Incidence reduction: 58% — the odds ratio for developing a cold while taking Echinacea (any preparation, any species) compared with placebo was 0.42 (95% confidence interval 0.25-0.71)
- Duration reduction: 1.4 days — weighted mean difference in cold duration between Echinacea and placebo arms across the trials
Those numbers received enormous press coverage, including front-page treatment in The New York Times, and remain the most widely-quoted figures on Echinacea efficacy. They were also immediately controversial. Critics pointed out that the meta-analysis pooled wildly heterogeneous preparations (root vs aerial; tincture vs pressed juice vs encapsulated dry herb; E. purpurea vs E. angustifolia vs E. pallida vs combinations) and used statistical methods that the critics argued exaggerated the apparent benefit. The Shah authors defended their methods as appropriate given the underlying biology of the herb — the assumption being that the active mechanisms are common to all species and preparations even if the constituent ratios differ.
The 2014 Karsch-Volk Cochrane review (next section) revisited the same evidence base with more rigorous methods and reached a more measured conclusion: none of the individual prevention comparisons was statistically significant, and a post hoc pooling suggested a relative risk reduction of 10% to 20% — far smaller than the 58% Shah number.
The Karsch-Volk 2014 Cochrane Review
The definitive evidence synthesis is the Cochrane systematic review by Karsch-Volk and colleagues, published in February 2014 as Cochrane Database of Systematic Reviews Issue 2: CD000530, an update of the earlier 2006 version. The review included 24 double-blind randomized controlled trials with a combined enrollment of 4,631 participants. Key findings:
- Prevention trials — because the studies differed so strongly, the authors did not pool them for the main analysis. None of the 12 prevention comparisons reporting the number of people with at least one cold found a statistically significant difference; a post hoc pooling of their results suggested a relative risk reduction of 10% to 20%. Evidence from seven of the trials was available for preparations based on the aerial parts of E. purpurea.
- Treatment trials — trials starting Echinacea at symptom onset rather than prophylactically showed less consistent benefit. Of the seven treatment trials reporting data on the duration of colds, only one showed a significant effect of Echinacea over placebo.
- Adverse events — the number of people dropping out or reporting adverse effects did not differ significantly between Echinacea and placebo groups in prevention and treatment trials. In prevention trials, however, there was a trend towards more people dropping out because of adverse events in the Echinacea groups.
The Cochrane authors emphasized a methodological point that is essential to understanding the Echinacea literature: products sold as Echinacea differ appreciably in their composition, mainly because of the plant material used, the extraction method and added components, and the trials used a variety of preparations based on different species and plant parts. Because of this strong clinical heterogeneity, the authors refrained from pooling the studies for their main analysis.
The bottom-line Cochrane conclusion: "Echinacea products have not here been shown to provide benefits for treating colds, although, it is possible there is a weak benefit from some Echinacea products: the results of individual prophylaxis trials consistently show positive (if non-significant) trends, although potential effects are of questionable clinical relevance." This is a notably less enthusiastic conclusion than the Shah 58% meta-analysis. The two reviews point the same way for prevention, but the Cochrane authors judged the size of any effect to be of questionable clinical relevance.
A later 2019 systematic review and meta-analysis of randomized double-blind placebo-controlled trials (David and Cunningham, Complementary Therapies in Medicine) found a risk ratio of 0.78 (95% confidence interval 0.68-0.88) for getting an upper respiratory tract infection while taking echinacea. It found no evidence of an effect on how long the infections lasted (mean difference -0.45 days), and its safety analysis found a risk ratio of 1.09 (95% confidence interval 0.95-1.25), so no risk was apparent in the short term. The authors wrote that echinacea might have a preventive effect but that whether this effect is clinically meaningful is debatable, and that the strength of their conclusions is limited by the risk of selective reporting and by the many different preparations tested.
The 2012 Jawad Trial — Prophylactic Fresh-Plant E. purpurea Extract
The trial its authors describe as the largest clinical trial to date of Echinacea's safety and efficacy is the 2012 randomized double-blind placebo-controlled trial by Jawad and colleagues published in Evidence-Based Complementary and Alternative Medicine. The trial enrolled 755 healthy adults randomized to either a standardised fresh-plant Echinacea purpurea extract (an alcohol extract of freshly harvested E. purpurea, 95% aerial parts and 5% root) or matching placebo, taken three times daily for four months during the cold season. Participants recorded cold symptoms and adverse events in a diary, and nasal secretions were sampled during colds and screened for viruses.
Results were notable:
- Cold episodes over four months: 149 episodes (672 cold days in total) in the Echinacea arm vs 188 episodes (850 cold days) with placebo. Both differences were 26%; the difference in cold days reached statistical significance (P < 0.05)
- Adverse events: 293 with Echinacea and 306 with placebo; 9% and 10% of participants had adverse events at least possibly related to the study drug, so the safety of Echinacea was noninferior to placebo
- Recurrent infections: 65 recurring infections in 28 participants with Echinacea vs 100 in 43 participants with placebo, a 59% difference (P < 0.05)
- Cold episodes also treated with pain medication: 52% more in the placebo group (P < 0.05)
- Virus-confirmed colds: Echinacea inhibited virally confirmed colds and especially prevented infections with enveloped viruses (P < 0.05); the preventive effect increased with how closely participants kept to the dosing schedule
The Jawad trial is the largest single trial behind Echinacea cold prevention. The preparation specifics matter — it is an alcoholic extract of freshly harvested E. purpurea (95% aerial parts, 5% root) at a specific extraction ratio, not a generic Echinacea capsule. Generic "Echinacea" capsules in the supplement aisle vary enormously in species, plant part, and preparation method, and many are not equivalent to the trial preparation.
Three Species, Different Chemistry, Different Trial Results
The genus Echinacea contains nine species native to North America, but only three are in significant commercial cultivation:
- E. purpurea — the most widely cultivated species, recognizable by its purple petals with a prominent orange-spiked central cone. Highest in cichoric acid (a caffeic acid derivative), present in alkylamides at moderate concentration, contains substantial high-molecular-weight polysaccharides in aerial parts. Used in pressed-juice and tincture preparations, both aerial parts and root.
- E. angustifolia — the species used most extensively by the Plains tribes of North America, the species adopted by the Eclectic physicians of the late 1800s, and the species used in the original European clinical research. Highest in alkylamides (the tongue-tingling lipophilic compounds that bind cannabinoid receptor type 2 (CB2)) and in echinacoside. Lower in cichoric acid. Typically used as a root tincture.
- E. pallida — the pale purple coneflower. High in echinacoside but lower in alkylamides than E. angustifolia. Historically used as a substitute for E. angustifolia when the latter was scarce, and frequently adulterates E. angustifolia products in the marketplace.
The three species are not interchangeable in trials. A meta-analysis that pools, for example, a E. purpurea aerial-parts pressed juice with an E. angustifolia root alcoholic tincture is essentially averaging two different drugs. The Karsch-Volk Cochrane review noted that the trials used a variety of preparations based on different species and plant parts, that evidence from seven trials was available for preparations based on the aerial parts of E. purpurea, and refrained from pooling the studies for its main analysis because of their strong clinical heterogeneity. Trials of E. angustifolia alcoholic root tinctures have shown more variable results, partly because the alcoholic extraction loses the polysaccharide fraction and partly because the bioavailability of the lipophilic alkylamides is preparation-sensitive.
Root vs Aerial Parts — Why It Matters
Different plant parts within the same Echinacea species contain different constituent ratios:
- Root — higher in alkylamides (especially for E. angustifolia), higher in echinacoside, lower in cichoric acid, lower in high-molecular-weight polysaccharides
- Aerial parts (leaves, stems, flowers) — higher in cichoric acid (especially for E. purpurea), higher in high-molecular-weight polysaccharides, lower in alkylamides
The traditional Eclectic-physician use was E. angustifolia root tincture, on the principle that the root contained the most concentrated medicinal activity. Modern German and European herbal medicine has largely shifted to E. purpurea aerial-parts pressed juice, driven by the trial evidence for E. purpurea aerial-part preparations and by cultivation practicality (the aerial parts can be harvested annually without destroying the plant; the root harvest kills the plant and requires 3-4 years of growth).
The label is the only way to tell these preparations apart. A product labeled simply "Echinacea" without species or plant-part specification is essentially uncharacterized. The best-studied preparations are: (1) standardised fresh-plant E. purpurea extracts (the 2012 Jawad trial used one made from 95% aerial parts and 5% root, the strongest single piece of evidence), and (2) E. angustifolia root alcoholic tincture, which rests on traditional Eclectic use. Products falling outside those two categories may still be effective but lack direct trial validation.
Prophylaxis vs At-Onset Treatment
Echinacea trials fall into two categories that differ substantially in design and outcome:
- Prophylaxis trials — participants take Echinacea continuously through cold season (typically 2-4 months) and the primary outcome is the incidence or total days of cold symptoms. The Jawad 2012 trial is the prototypical example. These trials generally show modest reductions in cold incidence and total cold-symptom days.
- At-onset treatment trials — participants start Echinacea at first cold symptoms (sneezing, sore throat) and continue for 7-10 days, with the primary outcome being symptom severity score or duration of illness. Results have been more mixed — some trials show modest reductions in severity and duration, others show no significant difference from placebo.
The mechanistic explanation for the prophylaxis-vs-onset difference is that the alkylamide-mediated cannabinoid receptor type 2 (CB2) modulation, the caffeic-acid-mediated antioxidant and antiviral effects, and the polysaccharide-mediated immune priming all need time to reach steady state in tissues. Starting Echinacea at symptom onset of a cold — when viral replication is already underway — gives less time for the modulatory effects to develop than continuous prophylactic dosing.
In the trials on this page, the more consistent results come from continuous prophylaxis through cold season, as in the 2012 Jawad trial, rather than from starting at first sniffle; the Cochrane authors found that individual prophylaxis trials consistently showed positive (if non-significant) trends. The at-onset approach is not without evidence but the effect size is more modest and less consistent across trials.
The Negative Trials (Turner 2005, Barrett 2010)
Two widely-publicized trials reported negative results and deserve direct discussion because they are frequently cited as evidence that Echinacea "doesn't work":
- Turner 2005 (New England Journal of Medicine) — Ronald Turner and colleagues at the University of Virginia randomly assigned 437 volunteers to one of three E. angustifolia root extracts (made with supercritical carbon dioxide, 60 percent ethanol or 20 percent ethanol) or placebo, given either as prophylaxis beginning seven days before the virus challenge or as treatment beginning at the time of the challenge. The results for 399 volunteers who were challenged with rhinovirus type 39 were analysed. None of the three Echinacea extracts had a statistically significant effect on rates of infection or severity of symptoms. The trial used three different E. angustifolia root extracts at relatively low daily doses (1.5 g/day of dried herb equivalent). Critics noted that the dose was low and the preparation was root-only rather than an E. purpurea aerial-part preparation like the one with the strongest trial evidence, and that experimental rhinovirus inoculation in a lab is a different clinical scenario from natural cold acquisition in community settings.
- Barrett 2010 (Annals of Internal Medicine) — Bruce Barrett and colleagues at the University of Wisconsin enrolled 719 patients aged 12 to 80 with a new-onset common cold and assigned them to four groups: no pills, placebo pills (blinded), echinacea pills (blinded) or echinacea pills (open-label). The echinacea tablets contained the equivalent of 675 mg E. purpurea root and 600 mg E. angustifolia root; the echinacea groups received the equivalent of 10.2 g of dried echinacea root during the first 24 hours and 5.1 g during each of the next 4 days. Mean global severity was 236 in the blinded echinacea group vs 264 in the blinded placebo group, a 28-point trend toward benefit that was not statistically significant (P = 0.089). Mean illness duration was 6.34 days vs 6.87 days, a nonsignificant 0.53-day benefit (P = 0.075). The authors noted that higher-than-expected variability limited the trial's power to detect small benefits. The trial is sometimes labeled "negative," but the point estimates favor Echinacea; the trial simply did not reach the high bar of statistical significance.
Neither trial fundamentally contradicts the positive evidence from trials of fresh-plant E. purpurea extracts. The Turner trial used a preparation (low-dose E. angustifolia root) that differs from the trial-validated preparations. The Barrett trial used an at-onset treatment design where, as discussed above, the effect is smaller and less consistent than in prophylactic designs. The overall body of evidence, properly stratified by preparation and design, supports a modest benefit for trial-validated preparations used prophylactically — a conclusion consistent with the Karsch-Volk Cochrane review's measured language.
Influenza — What the Evidence Does and Doesn't Show
The clinical evidence for Echinacea specifically for influenza (as distinct from the more general "common cold") is sparser but generally favorable. The trials and observational data suggest:
- In-vitro antiviral activity against multiple influenza A strains, including H1N1 and H5N1, has been demonstrated in cell culture for a standardised E. purpurea extract. The mechanism appears to be inhibition of viral binding to host cells (hemagglutination assays showed the extract blocked the virus's receptor binding), plus antioxidant effects that reduce host-tissue damage from the inflammatory response.
- The Pleschka 2009 study in Virology Journal found in cell culture that the standardised E. purpurea extract inactivated human H1N1, highly pathogenic avian H5 and H7 influenza viruses and swine-origin H1N1. When H5N1 virus was passaged repeatedly under treatment, no extract-resistant variants emerged, in contrast to oseltamivir, which produced resistant viruses; the oseltamivir-resistant virus was just as susceptible to the extract as the original virus. These are laboratory (cell-culture) results.
- A 2015 trial by Raus and colleagues in Current Therapeutic Research compared a hot drink based on a standardised E. purpurea extract, taken for 10 days, with oseltamivir taken for 5 days (followed by 5 days of placebo) in 473 patients with early influenza symptoms (48 hours or less). Recovery was comparable: 50.2% vs 48.8% after 5 days and 90.1% vs 84.8% after 10 days, and noninferiority was demonstrated. Complications occurred in 2.46% vs 6.45% (P = 0.076), and fewer adverse events (particularly nausea and vomiting) were observed with the echinacea drink. The trial tested the echinacea drink as an alternative to oseltamivir, not as an add-on.
The caveat is that none of these data are nearly as strong as the conventional antiviral evidence for neuraminidase inhibitors (oseltamivir, zanamivir) and baloxavir in early influenza. The Raus trial excluded pregnant or breastfeeding women, people taking steroid or immune-suppressive medication, and people with chronic heart disease, asthma or other respiratory disorders, diabetes, or liver or kidney disorders, so it did not test Echinacea as a replacement for those drugs in these higher-risk groups. See our Influenza page for more on conventional and integrative approaches.
Preparations and Doses Used in the Trials
The preparations, doses and schedules below are those used in the adult trials on this page, with traditional practice labelled as such:
- Preparation tested — the 2012 Jawad prevention trial used a standardised fresh-plant Echinacea purpurea extract (an alcohol extract of 95% aerial parts and 5% root). E. angustifolia root alcoholic tinctures and combination E. purpurea aerial + root tinctures are also sold by herbal suppliers; the root tincture rests on traditional Eclectic use.
- Prevention dose in the trial — Jawad trial participants swallowed 3 × 0.9 mL per day (corresponding to 2,400 mg of extract per day) continuously for four months; each dose was diluted in water and held in the mouth for 10 seconds. For a 1:5 alcoholic root tincture, the traditional Eclectic dose is approximately 2-4 mL three times daily. Most prevention trials ran continuously for 2-4 months during peak cold season.
- Dose during a cold in the trial — during acute colds, Jawad trial participants raised the dose to 5 × 0.9 mL per day (4,000 mg of extract per day). In treatment trials started at the first cold symptoms, the 2010 Barrett trial gave the equivalent of 10.2 g of dried root in the first 24 hours and 5.1 g on each of the next 4 days, and the 2003 Taylor trial in children continued for up to 10 days; treatment trials have less consistent results than prevention trials.
- Dried-herb capsules — the alkylamides degrade in dried herb stored at room temperature, and the polysaccharide fraction is poorly bioavailable in dry capsules without the alcoholic-extract matrix. Liquid tinctures and pressed juices have outperformed dried encapsulated products in trials.
- Cycling — some traditional herbalists cycle Echinacea (3 weeks on, 1 week off) with the aim of preventing receptor desensitization, though there is no specific trial evidence for this practice. Continuous 4-month use in the Jawad trial produced 293 adverse events with Echinacea vs 306 with placebo.
- Other measures used alongside — Vitamin D3 repletion (most U.S. adults are deficient in winter), zinc lozenges at symptom onset, and adequate sleep are all separately evidence-supported and synergistic.
The average benefit reported in the reviews above is modest: the Cochrane post hoc pooling suggested a 10% to 20% relative risk reduction in getting a cold and the 2019 meta-analysis a risk ratio of 0.78, while for duration the Shah 2007 meta-analysis reported a cold 1.4 days shorter but only one of seven treatment trials in the Cochrane review, and none of the evidence in the 2019 meta-analysis, showed an effect. In the adult trials and reviews above, adverse events did not differ significantly from placebo, although the Cochrane review noted a trend towards more people dropping out because of adverse events in prevention trials. The cost (under $30 for a season's supply of a standardised extract or a comparable tincture) is low.
Echinacea Trials in Children
- Taylor 2003 (JAMA) — a randomized, double-blind, placebo-controlled trial treated upper respiratory infections in healthy children aged 2 to 11 with Echinacea purpurea or placebo, started at the onset of symptoms and continued for up to 10 days. Data were analyzed on 707 infections in 407 children. There was no difference in duration (median 9 days overall; P = .89) or in overall severity (median 33 in both groups; P = .69). Rash occurred during 7.1% of the infections treated with echinacea and 2.7% of those treated with placebo (P = .008).
- Ogal 2021 (European Journal of Medical Research) — a randomized, blinded trial gave children aged 4 to 12 tablets of a standardised fresh-plant E. purpurea extract (400 mg) or vitamin C (50 mg) three times daily for prevention, in two 2-month periods separated by a 1-week break. There were 429 cold days among 103 children with Echinacea and 602 among 98 children with vitamin C (p < 0.001). Six children (5.8%) with Echinacea and 15 children (15.3%) with vitamin C needed antibiotics, and complications such as otitis media, sinusitis or pneumonia numbered 11 vs 30 (p = 0.0030). Adverse events numbered 76 with Echinacea and 105 with vitamin C. The comparison group took vitamin C, not a placebo.
- Pham 2025 (Clinical Nutrition ESPEN) — a systematic review and meta-analysis of 9 randomized controlled trials in children found that E. purpurea lowered the incidence of upper respiratory tract infections (risk ratio 0.81) and antibiotic use (risk ratio 0.18) and shortened treatment duration (standardized mean difference -0.19). Adverse events were moderately increased (risk ratio 1.38), though generally mild, and the authors wrote that the safety profile remains unclear and that further research is needed.
Key Research Papers
- Karsch-Volk M, Barrett B, Kiefer D, Bauer R, Ardjomand-Woelkart K, Linde K (2014). Echinacea for preventing and treating the common cold. Cochrane Database of Systematic Reviews, Issue 2: CD000530. — PubMed PMID: 24554461
- Shah SA, Sander S, White CM, Rinaldi M, Coleman CI (2007). Evaluation of echinacea for the prevention and treatment of the common cold: a meta-analysis. The Lancet Infectious Diseases 7(7):473-480. — PubMed PMID: 17597571
- Jawad M, Schoop R, Suter A, Klein P, Eccles R (2012). Safety and efficacy profile of Echinacea purpurea to prevent common cold episodes: a randomized, double-blind, placebo-controlled trial. Evidence-Based Complementary and Alternative Medicine 2012:841315. — PubMed PMID: 23024696
- Turner RB, Bauer R, Woelkart K, Hulsey TC, Gangemi JD (2005). An evaluation of Echinacea angustifolia in experimental rhinovirus infections. New England Journal of Medicine 353(4):341-348. — PubMed PMID: 16049208
- Barrett B, Brown R, Rakel D, Mundt M, Bone K, Barlow S, Ewers T (2010). Echinacea for treating the common cold: a randomized trial. Annals of Internal Medicine 153(12):769-777. — PubMed PMID: 21173411
- Pleschka S, Stein M, Schoop R, Hudson JB (2009). Anti-viral properties and mode of action of standardized Echinacea purpurea extract against highly pathogenic avian influenza virus (H5N1, H7N7) and swine-origin H1N1 (S-OIV). Virology Journal 6:197. — PubMed PMID: 19912623
- Raus K, Pleschka S, Klein P, Schoop R, Fisher P (2015). Effect of an Echinacea-based hot drink versus oseltamivir in influenza treatment: a randomized, double-blind, double-dummy, multicenter, noninferiority clinical trial. Current Therapeutic Research 77:66-72. — PubMed PMID: 26265958
- Schoop R, Klein P, Suter A, Johnston SL (2006). Echinacea in the prevention of induced rhinovirus colds: a meta-analysis. Clinical Therapeutics 28(2):174-183. — PubMed PMID: 16678640
- Goel V, Lovlin R, Barton R, Lyon MR, Bauer R, Lee TD, Basu TK (2004). Efficacy of a standardized echinacea preparation (Echinilin) for the treatment of the common cold: a randomized, double-blind, placebo-controlled trial. Journal of Clinical Pharmacy and Therapeutics 29(1):75-83. — PubMed PMID: 14748902
- Lindenmuth GF, Lindenmuth EB (2000). The efficacy of echinacea compound herbal tea preparation on the severity and duration of upper respiratory and flu symptoms: a randomized, double-blind placebo-controlled study. Journal of Alternative and Complementary Medicine 6(4):327-334. — PubMed PMID: 10976979
- Sperber SJ, Shah LP, Gilbert RD, Ritchey TW, Monto AS (2004). Echinacea purpurea for prevention of experimental rhinovirus colds. Clinical Infectious Diseases 38(10):1367-1371. — PubMed PMID: 15156472
- Ross SM (2016). Echinacea purpurea: a proprietary extract of Echinacea purpurea is shown to be safe and effective in the prevention of the common cold. Holistic Nursing Practice 30(1):54-57. — PubMed PMID: 26633727
- David S, Cunningham R (2019). Echinacea for the prevention and treatment of upper respiratory tract infections: A systematic review and meta-analysis. Complementary Therapies in Medicine 44:18-26. — PubMed PMID: 31126553
- Taylor JA, Weber W, Standish L, Quinn H, Goesling J, McGann M, Calabrese C (2003). Efficacy and safety of echinacea in treating upper respiratory tract infections in children: a randomized controlled trial. JAMA 290(21):2824-2830. — PubMed PMID: 14657066
- Ogal M, Johnston SL, Klein P, Schoop R (2021). Echinacea reduces antibiotic usage in children through respiratory tract infection prevention: a randomized, blinded, controlled clinical trial. European Journal of Medical Research 26(1):33. — PubMed PMID: 33832544
- Pham TP, Vu TM, Doan PM, Nguyen TT, Bui TT, Ha TH, Hoang TK, Taufani IP, Ha HA (2025). Efficacy and safety of Echinacea purpurea in treating upper respiratory infections and complications of otitis media in children: Systematic review and meta-analysis. Clinical Nutrition ESPEN 67:702-713. — PubMed PMID: 40311928