⚠ Evidence warning: Clinical trials or other evidence do not support the claim that a dandelion "bitter before meals" routine reliably improves functional dyspepsia, bloating and low stomach acid within 3–14 days and is "one of the most effective single interventions" for these complaints. This page keeps it as a report of what people, websites or other media say.
Dandelion as a Digestive Aid
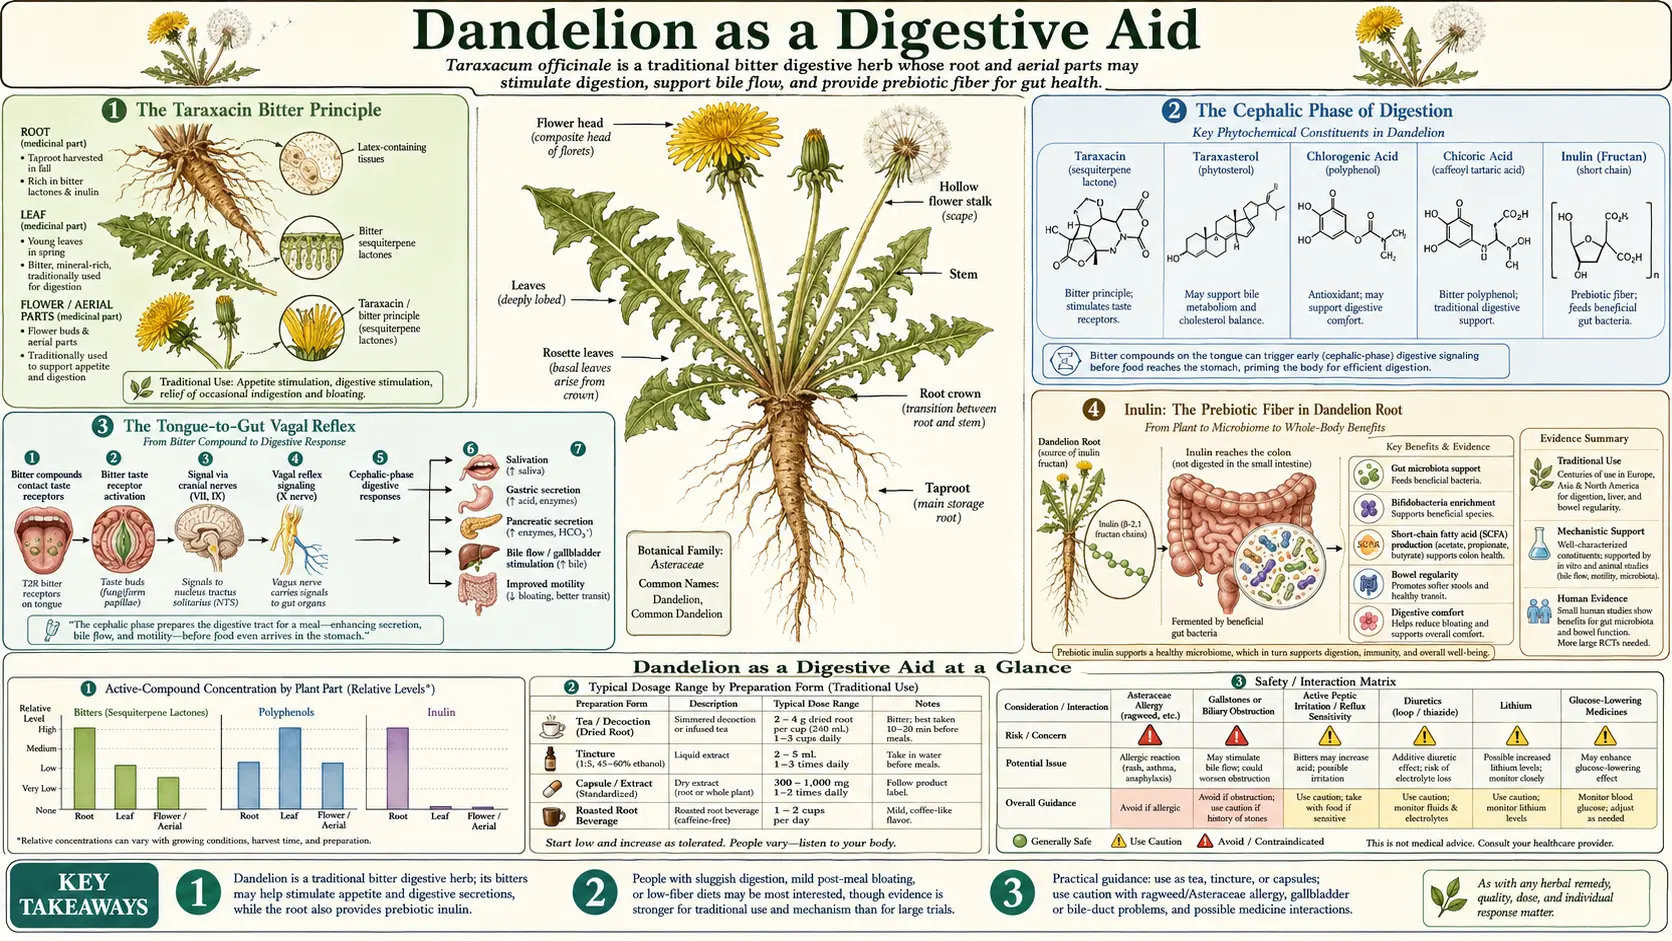
Dandelion is one of the classical "digestive bitters" of European traditional medicine, a category of herbs that work primarily through gustatory stimulation: the bitter principle (taraxacin, a sesquiterpene lactone) binds to bitter taste receptors on the tongue and triggers a vagal reflex that pre-stimulates the entire upstream digestive cascade — saliva, gastric acid, pancreatic enzymes, and bile — before food even reaches the gut. This is the "cephalic phase" of digestion, which the modern American diet has progressively stripped through plant breeding for sweetness and bitterness-suppressing food technology. The root of the plant also contains substantial inulin, a prebiotic fructan that selectively feeds bifidobacteria and produces short-chain fatty acids, supporting downstream gut barrier and microbiome health. This deep-dive walks through the bitter mechanism, the inulin prebiotic effect, the traditional aperitif use, the roasted-root dandelion coffee tradition, the adjunctive role in irritable bowel syndrome (IBS) and functional dyspepsia, and the practical "bitter before meals" protocol that produces noticeable improvement in digestion within days.
Table of Contents
- The Taraxacin Bitter Principle
- The Cephalic Phase of Digestion
- The Tongue-to-Gut Vagal Reflex
- Inulin: The Prebiotic Fiber in Dandelion Root
- Short-Chain Fatty Acids and Gut Barrier
- The Traditional European Bitter Aperitif
- Roasted Dandelion-Root Coffee
- Dandelion Wine and Flower Fermentation
- Functional Dyspepsia and Bloating
- Irritable Bowel Syndrome Adjunct
- Hypochlorhydria and Low Stomach Acid
- Dosage and "Bitter Before Meals" Protocol
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Taraxacin Bitter Principle
The primary bitter principle of dandelion is taraxacin (also called taraxinic acid 1'-O-beta-D-glucopyranoside), a sesquiterpene lactone concentrated in the latex (milky sap) of the plant. Sesquiterpene lactones are a chemical class of plant defense compounds known for intense bitterness, found in many of the medicinally bitter Asteraceae (daisy family) herbs — including chamomile, feverfew, artichoke, chicory, wormwood, and yarrow.
Other related bitter compounds in dandelion include taraxacerin, lactucin, lactucopicrin, and 11β,13-dihydrolactucin. The bitterness intensity varies with the plant part: the latex of the broken stem is the most intensely bitter, the leaf is moderately bitter (more so before the plant flowers), and the root is the least bitter but still distinctly so when prepared as a tincture or strong tea. Roasting the root caramelizes some sugars and softens the bitterness considerably — this is why roasted dandelion-root tea has a much more palatable, coffee-like flavor than fresh-root preparations.
The bitterness of taraxacin is "clean" — it activates bitter taste receptors strongly without producing the harsh, lingering, or astringent quality of some other bitters (like quassia or gentian, which can be overwhelmingly bitter). This makes dandelion one of the more clinically usable bitters: bitter enough to produce a real cephalic-phase response, but not so unpleasant that patients refuse to take it.
The Cephalic Phase of Digestion
Digestion is conventionally divided into three phases:
- Cephalic phase — before food enters the gut, triggered by the sight, smell, taste, or even the anticipation of food. Mediated by the vagus nerve, originating in the brain (the "cephalic" part referring to the head).
- Gastric phase — once food is in the stomach, triggered by stomach distention and by the chemical contents of the meal. Mediated by both local nervous reflexes within the stomach wall and by hormones like gastrin.
- Intestinal phase — once chyme enters the small intestine, triggered by chemical and mechanical stimuli in the duodenum. Mediated by hormones including cholecystokinin (CCK), secretin, and gastric inhibitory polypeptide (GIP).
The cephalic phase has historically been underappreciated in medical training. Pavlov's classical experiments with dogs (the salivation in response to a bell predicting food) established the cephalic phase, but the clinical implications were rarely emphasized until the modern interest in mindful eating, vagal tone, and functional digestive disorders revived interest.
Quantitatively, the cephalic phase accounts for approximately 30% of total digestive secretion in a healthy meal eaten under normal conditions (relaxed, attentive to the food, not rushed or stressed). When the cephalic phase is intact, the rest of digestion proceeds smoothly. When the cephalic phase is suppressed (eating while distracted, while stressed, while rushing, or while consuming food with no bitter component to stimulate the reflex), the gastric and intestinal phases must compensate without the upstream preparation, often resulting in the postprandial bloating, sluggish digestion, and "I just ate but I'm still not satisfied" sensation that characterize modern functional digestive complaints.
The clinical relevance of bitter herbs like dandelion: they restore the cephalic phase that the modern diet and eating pattern have weakened. A few drops of dandelion tincture in a small glass of water, taken 15-20 minutes before a meal, produces a noticeable bitter sensation on the tongue, triggers the cephalic reflex, and primes the digestive cascade. The downstream effects — better digestion, less bloating, more sense of satisfaction after meals, improved bowel regularity — are often apparent within 3-7 days of starting the practice.
The Tongue-to-Gut Vagal Reflex
The molecular and neural anatomy of the bitter reflex is now well-mapped. The pathway:
- Bitter compound binds tongue receptors — taraxacin (and other dandelion sesquiterpene lactones) binds to multiple members of the TAS2R bitter taste receptor family expressed on type II taste cells in taste buds across the tongue, with particular concentration in the posterior tongue and back wall of the pharynx. Humans have approximately 25 different TAS2R genes; different bitter compounds bind different combinations of receptors.
- Signal transduction in the taste cell — TAS2R receptors are G-protein-coupled receptors (GPCRs) signaling through the alpha-gustducin / phospholipase C beta 2 / IP3 / calcium release pathway. The calcium signal opens the TRPM5 ion channel, depolarizing the taste cell.
- Neurotransmitter release — the depolarized type II taste cell releases adenosine triphosphate (ATP) onto type III taste cells and onto the afferent terminals of the chorda tympani nerve (anterior tongue), the glossopharyngeal nerve (posterior tongue), and the vagus nerve (pharynx and laryngeal region).
- Signal to brainstem — the gustatory afferent signal travels via these three cranial nerves to the nucleus of the solitary tract (NTS) in the medulla oblongata. The NTS is the central integration site for taste, visceral, and cardiovascular afferents.
- Efferent vagal output — the NTS triggers parasympathetic efferent output via the dorsal motor nucleus of the vagus nerve, which sends efferent signals back down to the salivary glands, stomach, pancreas, liver, gallbladder, and proximal small intestine.
- Downstream digestive secretion — the parasympathetic signal triggers:
- Salivation from parotid, submandibular, and sublingual glands — rich in alpha-amylase, lingual lipase, lysozyme, and bicarbonate
- Gastric acid secretion from parietal cells via acetylcholine release at the M3 muscarinic receptor
- Pancreatic exocrine secretion via acetylcholine and indirect CCK release — amylase, lipase, and proenzyme proteases
- Gallbladder contraction with bile release via CCK
- Increased gastric motility and stomach emptying
- Activation of intestinal motility and Migrating Motor Complex
Interestingly, TAS2R bitter receptors are not only expressed on the tongue. They are also expressed on enteroendocrine cells lining the gut, on smooth muscle cells in the airways, on sinus epithelium, and on immune cells. Some of the downstream effects of bitter herbs may be mediated through these "ectopic" bitter receptors, particularly in the gut where direct contact of swallowed bitter compounds with TAS2R-expressing enteroendocrine cells can stimulate local hormone release including glucagon-like peptide-1 (GLP-1), PYY, and CCK independent of the tongue-mediated reflex.
Whether bitter herbs act when swallowed in capsules that bypass the tongue is less clear. In the human studies summarised by McMullen and colleagues (2015), encapsulated caffeine produced cardiovascular responses, which shows that bitter receptors in the gut are functionally active in humans; however, neither encapsulated gentian nor encapsulated wormwood produced cardiovascular responses during the gastric phase.
What those studies measured when the bitter was tasted is also different from the vagal model above. In adults, gentian and wormwood increased the tension (tonus) of the small resistance blood vessels; this was a sympathetic reflex, evident after 5 minutes and dose dependent. After a meal, the authors explain, this works alongside increased heart activity to support the extra blood flow to the gut (postprandial hyperaemia) and to maintain blood pressure. They concluded that gentian and wormwood "facilitate rather than stimulate digestive activity when postprandial hyperaemia is inadequate". Dandelion itself was not tested.
Inulin: The Prebiotic Fiber in Dandelion Root
The second major digestive mechanism of dandelion is the inulin content of the root. Inulin is a fructan polysaccharide — a chain of fructose units linked together with a terminal glucose, ranging from 2 to 60 units long. Humans do not produce any enzyme capable of digesting fructans; they pass undigested through the stomach and small intestine to reach the colon, where colonic bacteria selectively ferment them.
Dandelion root is one of the richest natural sources of inulin in the plant kingdom. The inulin content varies with season and the age of the plant:
- First-year root, autumn-harvested: 20-40% inulin by dry weight, the peak storage period
- First-year root, spring-harvested: 10-20% inulin, after the plant has used winter stores
- Second-year root, autumn: 15-25% inulin
- Second-year root, spring: 5-15% inulin
For comparison, chicory root (the most concentrated commercial source of inulin) is approximately 40-60% inulin by dry weight; Jerusalem artichoke tubers are approximately 15-20% inulin; garlic is approximately 11% inulin; onions are approximately 2-6% inulin; bananas are approximately 0.5% inulin. Dandelion root is in the same league as the dedicated inulin-source plants and is far richer than the inulin content of common dietary vegetables.
Inulin is one of the best-characterized "prebiotic" substrates — meaning it selectively feeds beneficial gut bacteria without feeding the less desirable ones. The dominant beneficiaries are members of the genus Bifidobacterium, which express the fructofuranosidase enzymes needed to hydrolyze inulin and use the released fructose for growth. Bifidobacterium species are widely considered beneficial members of the gut microbiome, associated with reduced inflammation, improved bowel regularity, reduced risk of colon cancer, and improved metabolic markers.
The bifidogenic effect of dandelion root has been shown in a laboratory (test-tube) study: an infusion of dandelion root stimulated the growth of 14 strains of bifidobacteria in vitro, and dandelion oligofructans were an important source of carbon and energy for the bifidobacteria tested (Trojanová 2004). The bifidogenic effect is one of the mechanistically best-supported benefits of long-term daily dandelion-root tea consumption, although no human feeding trial of dandelion root is among this page's sources.
A 2022 review of dandelion and gastrointestinal diseases (Li and colleagues) describes the evidence as in vivo and in vitro studies (animal and laboratory work). It concludes that research on digestive-protective dandelion products "remains limited", and that more clinical studies are required on the metabolism, bioavailability and safety of dandelion's compounds.
Short-Chain Fatty Acids and Gut Barrier
When bifidobacteria and other colonic microbes ferment inulin, the primary metabolic products are short-chain fatty acids (SCFAs) — principally acetate, propionate, and butyrate. Short-chain fatty acids are not waste products; they are biologically active signaling molecules and energy sources with substantial physiological effects on the host:
- Butyrate — the preferred energy source for colonocytes (the epithelial cells lining the colon). A colon adequately supplied with butyrate maintains barrier integrity, low-level local immune activation, and normal cell turnover. Butyrate also has systemic effects on inflammation, insulin sensitivity, and even on the central nervous system through gut-brain axis signaling.
- Propionate — partly metabolized by colonocytes, partly absorbed into the portal circulation. Propionate reaches the liver and modulates hepatic lipid and glucose metabolism, generally favorably. It also has appetite-modulating effects through gut-derived satiety signaling.
- Acetate — the most abundant short-chain fatty acid (SCFA) produced. Largely absorbed into the systemic circulation where it serves as an energy substrate for peripheral tissues and as a signaling molecule for adipose tissue, muscle, and brain.
The short-chain fatty acid-driven benefits of inulin fermentation include:
- Improved colonic barrier integrity (reduced "leaky gut" / intestinal permeability)
- Reduced colonic inflammation
- Improved bowel regularity (short-chain fatty acids stimulate normal peristalsis)
- Reduced systemic inflammatory markers (C-reactive protein (CRP), tumor necrosis factor-alpha)
- Modest improvement in glucose tolerance and insulin sensitivity
- Modest reduction in total and low-density lipoprotein (LDL) cholesterol
- Reduced risk of colorectal cancer (epidemiologic association)
The connection from dandelion root tea to these systemic effects is: dandelion root tea provides inulin, inulin is fermented by bifidobacteria, the fermentation produces short-chain fatty acids, and short-chain fatty acids provide the metabolic and inflammatory benefits. The chain is mechanistically clean; the magnitude of effect from any individual dietary source of inulin depends on the dose and on the individual's baseline microbiome composition.
The Traditional European Bitter Aperitif
The European cultural tradition of taking a small bitter alcoholic beverage before meals — the "aperitif" tradition — is one of the few surviving practical applications of bitter-herb digestive support in everyday Western culture. The tradition crosses national boundaries: Italy, France, Germany and Hungary all have their commercial aperitif and digestif bitters, from the Italian bitter amari (some of them artichoke-based) and the French vermouths to the German and Hungarian herbal liqueurs.
The aperitif tradition originated as a digestive practice. A small (1-2 oz / 30-60 mL) glass of a bitter herbal liqueur, sipped slowly over 10-20 minutes before a meal, would coat the tongue with bitter compounds, trigger the cephalic-phase reflex discussed above, and prepare the digestive system for the meal to come. The dilution in a small amount of carbonated water (a common way of serving commercial aperitif and digestif bitters) preserved the bitter exposure while making the drink palatable.
Dandelion-leaf tincture, taken 15-20 minutes before meals in a small glass of water or sparkling water, replicates the same physiologic effect of the traditional aperitif without the alcohol. Some integrative formulations combine dandelion with other digestive bitters (gentian, artichoke leaf, chicory root, orange peel, angelica root) to produce a more complex bitter profile similar to the classical aperitif herbs. Swedish bitters, a traditional formulation (which contains dandelion, gentian, angelica, rhubarb, aloe, myrrh, and several other bitter herbs), is one such combined bitter tincture in the integrative-medicine tradition.
The practical adoption of the aperitif practice has been one of the most effective single interventions for patients with functional dyspepsia, post-meal bloating, and reduced appetite. The effect typically becomes apparent within 3-7 days of starting daily pre-meal bitters, with continued improvement over several weeks of consistent use.
Roasted Dandelion-Root Coffee
One of the most pleasant whole-food forms of dandelion for daily long-term use is roasted dandelion-root coffee. The preparation has a long tradition in Europe and North America, particularly during periods of coffee scarcity (the Napoleonic Wars, the World Wars, the American Civil War's southern blockade) when roasted root substitutes filled the gap left by unavailable coffee beans.
The preparation: clean autumn-harvested dandelion roots are chopped into small pieces, dried, then roasted in a slow oven (around 200°F / 95°C) until they turn dark brown and develop a rich coffee-like aroma. The roasted root is ground (in a coffee grinder is fine) and brewed in the same way as ground coffee — either by drip, French press, percolator, or simmered briefly in water and then strained.
The flavor: similar to coffee but milder, with a distinct earthy, slightly sweet, slightly bitter quality. Drinkers describe it as a cross between coffee and chicory-and-coffee (the New Orleans-style coffee blend uses roasted chicory root, which is botanically close to dandelion). The roasting process caramelizes the inulin and develops Maillard-reaction products (the same browning reaction that gives roasted coffee its flavor profile), so the final brewed beverage has substantially less raw bitterness than fresh dandelion root preparations.
Benefits relative to coffee:
- No caffeine, suitable for evening drinking or for people who don't tolerate caffeine well
- Retains the prebiotic inulin (though roasting partly depolymerizes it)
- Retains hepatobiliary and bitter-reflex effects, though somewhat reduced by roasting
- No tannin-related interactions with iron absorption (an issue with regular black coffee at meals)
- Generally gentler on the stomach for people with gastritis or reflux
Drawbacks relative to coffee: no caffeine for those who want the stimulant effect; less intense flavor; less widely available commercially than instant coffee or whole-bean coffee.
Commercial roasted-dandelion drinks are sold in natural food stores, both as blends (with other roasted plant materials such as carob, chicory, beet, barley and rye, some of them instant) and as single-ingredient roasted dandelion root products. Home roasting from foraged or commercial dried dandelion roots is also straightforward.
Herbal writers describe one cup of roasted dandelion-root coffee a day as a low-effort, pleasant way to bring dandelion's hepatobiliary and prebiotic effects into a long-term daily routine.
Dandelion Wine and Flower Fermentation
Dandelion wine is one of the oldest fermented preparations of the plant, with a tradition stretching back centuries in European folk practice and Native American adoption (Ojibwe, Iroquois, and other Eastern Woodlands cultures used dandelion flowers in fermented and unfermented preparations). The wine is made from the bright yellow flower heads, ideally collected at midday on a sunny day when the flowers are fully open.
The basic process: 4-6 quarts of fresh dandelion flowers are stripped from the green calyx (the green base of the flower; if left in, the wine becomes excessively bitter). The yellow petals are steeped in boiling water for 24 hours, then strained. Sugar, lemon, orange, and wine yeast are added to the strained "tea." The mixture ferments for several weeks, is racked off the sediment, and ages for several months to a year. The finished wine is golden, lightly floral, mildly sweet, low to moderate alcohol (8-12%).
The literary fame of dandelion wine comes from Ray Bradbury's 1957 novel Dandelion Wine, which used the family ritual of making dandelion wine each summer as a metaphor for capturing the essence of childhood summers in jars to be opened in winter. The actual home-fermentation tradition is older and far more widespread than the novel's framing suggests — nearly every rural European-descended family in temperate North America had at least one elder who made dandelion wine each spring or summer.
From a strictly medicinal perspective, dandelion wine is the weakest preparation. The fermentation degrades many of the bitter sesquiterpene lactones; the dilution and the sugar content reduce the therapeutic intensity; and the alcohol content limits dosing. The wine's appeal is cultural and culinary rather than primarily medicinal. The most therapeutically active dandelion preparations remain the dried-leaf tea, the dried-root tea, the tinctures of leaf and root separately, and the fresh young leaves in salad.
The aperitif use of dandelion wine — a small glass before dinner — is the closest the wine comes to its medicinal antecedents, providing some of the same cephalic-phase bitter stimulation that the more concentrated bitter tinctures provide.
Functional Dyspepsia and Bloating
Functional dyspepsia — persistent or recurrent upper abdominal discomfort, early satiety, postprandial fullness, or epigastric pain in the absence of an identifiable structural cause — affects approximately 10-15% of adults in developed countries. The Rome IV diagnostic criteria divide it into postprandial distress syndrome (PDS, dominated by fullness and early satiety) and epigastric pain syndrome (EPS, dominated by burning or pain). Both subtypes are commonly comorbid with irritable bowel syndrome and with reflux disease.
Pharmaceutical management options are limited and only modestly effective. Acid-suppression with proton pump inhibitors (omeprazole, esomeprazole) helps the EPS subtype somewhat. Prokinetic agents (metoclopramide, domperidone outside the US) help the PDS subtype somewhat but have side-effect profiles that limit long-term use. The newer cyclic 5-HT4 agonists (prucalopride) have shown modest benefit in some studies.
Herbal practitioners use dandelion as an adjunctive support for functional dyspepsia, particularly the postprandial distress subtype, where in their view the bitter-mediated cephalic phase enhancement directly addresses the underlying functional deficit. The regimen they describe is 2-5 mL of dandelion root tincture (or combined dandelion + gentian + artichoke leaf tincture) in a small glass of water, 15-20 minutes before each main meal, and they report the effect typically becoming noticeable within 7-14 days, with continued improvement over 8-12 weeks.
The German Commission E monograph specifically lists "dyspeptic complaints" as an approved indication for dandelion. The EU herbal monograph on dandelion (EMA/HMPC/212895/2008) from the European Medicines Agency's herbal committee lists dandelion root with herb as a "traditional herbal medicinal product for the relief of symptoms related to mild digestive disorders (such as feeling of abdominal fullness, flatulence, and slow digestion) and temporary loss of appetite". This is a traditional-use indication, not a well-established-use one: the monograph states that the product is for use in specified indications "exclusively based upon long-standing use".
A 2025 review of medicinal plants in food supplements for digestive disorders (Teterovska and colleagues) identified 218 such supplements on the Latvian market; dandelion was among the most frequently used plants. Label claims most often referred to supporting digestion, relieving bloating and maintaining normal gut function, but the review found that "the majority of claims lacked robust clinical substantiation, and were based primarily on traditional use".
Irritable Bowel Syndrome Adjunct
Irritable bowel syndrome (IBS) is a related functional gastrointestinal disorder, characterized by recurrent abdominal pain associated with defecation or with change in bowel habit, in the absence of identifiable structural disease. In the Rome Foundation Global Study of 73,076 adults in 33 countries, 4.1% of internet-survey respondents and 1.5% of household-interview respondents met the current Rome IV criteria for irritable bowel syndrome, compared with 10.1% and 3.5% under the older Rome III criteria. Management is largely empirical: low-FODMAP diet, soluble fiber, antispasmodics, probiotics, neuromodulators (low-dose tricyclic antidepressants for diarrhea-predominant irritable bowel syndrome (IBS-D), selective serotonin reuptake inhibitors (SSRIs) for constipation-predominant irritable bowel syndrome (IBS-C)), and patient education about the functional nature of the condition.
Dandelion's role in irritable bowel syndrome management is adjunctive and somewhat nuanced. For constipation-predominant irritable bowel syndrome, dandelion root inulin can contribute to improved bowel regularity through the prebiotic and short-chain fatty acid mechanisms, and dandelion's bile-flow stimulation can help with the sluggish digestion that often accompanies constipation-predominant irritable bowel syndrome. For diarrhea-predominant irritable bowel syndrome, however, dandelion inulin can sometimes worsen symptoms — some irritable bowel syndrome patients have a small-intestinal bacterial overgrowth (SIBO) component, and rapid fermentation of inulin in the small intestine can produce gas, bloating, and worsening of the irritable bowel syndrome symptoms.
The approach practitioners describe for people with irritable bowel syndrome who try dandelion:
- A small starting dose (2-3 g of dried root in a single daily cup of tea, or 1-2 mL of tincture twice daily)
- 7-14 days of watching for symptom improvement vs worsening
- If symptoms worsen (particularly bloating, abdominal pain, distension), small intestinal bacterial overgrowth is suspected and the inulin-containing root preparations are reduced or stopped; the leaf preparations (low inulin) may still be tolerated
- If symptoms improve, the dose is continued and raised gradually
- If symptoms are mixed (some better, some worse), small intestinal bacterial overgrowth is tested for with a lactulose or glucose breath test, and any overgrowth is addressed before inulin-rich prebiotics are tried again
For more on the small intestinal bacterial overgrowth consideration, see our small intestinal bacterial overgrowth page, which discusses prebiotic tolerance issues at length. For more on the FODMAP framework, dandelion-root inulin would be classified as a high-FODMAP food (specifically an oligosaccharide / fructan) and would be excluded during the elimination phase of a low-FODMAP trial. The dandelion leaf is FODMAP-neutral and would be allowed.
Hypochlorhydria and Low Stomach Acid
Hypochlorhydria (low stomach acid) is more common than is generally recognized, particularly in older adults, in patients on chronic proton pump inhibitor therapy, and in patients with autoimmune atrophic gastritis. Symptoms include postprandial bloating, early satiety, undigested food in stool, low B12 absorption (with associated fatigue, neurologic symptoms, or anemia), and increased susceptibility to enteric infections (low stomach acid is the first defense against swallowed pathogens).
Pharmaceutical "acid replacement" therapy with betaine HCl supplements is one option, but is somewhat awkward in practice and not appropriate for all patients. Herbal practitioners describe bitter herbs, which in their model stimulate the body's own gastric acid secretion through the cephalic-phase vagal reflex, as a more physiologic alternative for people with mild hypochlorhydria not severe enough to require betaine HCl replacement.
In this practitioner model, dandelion fits this niche: the bitter taraxacin triggers vagal stimulation of parietal cell acetylcholine release, which directly stimulates gastric H+/K+ ATPase activity and increases gastric acid output. Practitioners describe the effect as not as powerful as betaine HCl but more physiologic, simultaneously stimulating other digestive secretions, and use it as first-line support in mild hypochlorhydria before moving to betaine HCl replacement.
The protocol they describe: 2-5 mL of dandelion tincture (root or leaf; root is somewhat more bitter) in a small glass of water, 15-20 minutes before each main meal, for 4-8 weeks with symptom monitoring, continued as a long-term daily practice if symptoms improve, and followed by betaine HCl if symptoms do not improve or worsen. Inappropriate use of betaine HCl in people with normal stomach acid (normochlorhydria) can cause symptomatic gastritis.
Dosage and "Bitter Before Meals" Protocol
For digestive aid applications, herbal practice uses dandelion as either root or leaf, with somewhat different emphases. The amounts below are those described in herbal practice:
For bitter-mediated digestive stimulation (cephalic phase enhancement):
- Dandelion root tincture (1:5 in 40% alcohol) — 2-5 mL in 1-2 oz of water, 15-20 minutes before each main meal. The most concentrated bitter preparation. The form most likely to produce strong cephalic-phase effects.
- Dandelion leaf tincture (1:3 in 30% alcohol) — 2-5 mL in 1-2 oz of water, 15-20 minutes before each main meal. Somewhat less bitter than the root tincture but more diuretic.
- Fresh dandelion leaves in pre-meal salad — the most traditional whole-food form. A handful of young pre-flowering leaves as part of a salad eaten as the first course of a meal. The bitterness from chewing engages the cephalic-phase reflex.
- Combined bitter tinctures (Swedish bitters or similar) — 2-5 mL in water before meals. The combined herbs produce a more complex bitter profile and may be more effective than single-herb dandelion tincture.
For inulin prebiotic effects:
- Roasted dandelion-root tea — 1-2 cups daily, brewed from 1-2 teaspoons (2-4 g) of dried roasted root per cup
- Dandelion-root capsules (non-roasted) — 500-1500 mg, twice daily with meals; provides higher per-dose inulin than roasted root tea
- Raw or lightly roasted dandelion root powder in smoothies — 1-2 teaspoons daily; mixes well into smoothies, oatmeal, or kefir
The "bitter before meals" routine as herbal practitioners describe it for functional digestive complaints:
- 3 mL of dandelion root tincture (or Swedish bitters) mixed into 2 oz of warm water
- Sipped slowly over 1-2 minutes, each sip swished in the mouth for tongue contact
- A 15-20 minute wait for the cephalic-phase reflex to peak
- The meal eaten in a relaxed, attentive manner (no phones, no screens, no rushing)
- Thorough chewing — the mechanical and sensory experience of chewing engages and prolongs the cephalic-phase response
- Repeated daily before each main meal for at least 14 days before the effect is judged
Practitioners report that the effect on functional dyspepsia and post-meal bloating is often noticeable within 7 days and reliably evident within 14 days when the routine is followed consistently, and describe it as a practice that can be continued long term.
For comparison, the EU herbal monograph on dandelion (EMA/HMPC/212895/2008) gives these traditional-use amounts for mild digestive disorders in adolescents, adults and the elderly: comminuted dried root with herb, 3-4 g as a decoction or 4-10 g as an infusion up to 3 times daily; or liquid extract, 35 drops (about 1 ml) or 90 drops (3.15 ml) 3 times daily, by mouth.
Cautions
- Gallstone disease — the EU herbal monograph lists gallstones as a contraindication, together with obstructions of the bile ducts, cholangitis (bile-duct inflammation), liver diseases and any other biliary diseases; active cholecystitis (gallbladder inflammation) is one of these biliary diseases. The cholagogue effect can precipitate biliary colic in patients with known gallstones.
- Active gastric ulcer — bitter herbs that stimulate gastric acid secretion can worsen active gastric or duodenal ulcer. The EU herbal monograph lists active peptic ulcer as a contraindication.
- Small intestinal bacterial overgrowth (SIBO) — inulin-rich root preparations can worsen small intestinal bacterial overgrowth symptoms. The leaf preparation is FODMAP-neutral and may be better tolerated.
- FODMAP-sensitive irritable bowel syndrome — dandelion root inulin is a high-FODMAP fructan and is excluded during the elimination phase of a low-FODMAP trial. Leaf preparations are FODMAP-neutral.
- Asteraceae allergy — cross-reactive with ragweed, chamomile, and other daisy-family plants. The EU herbal monograph lists hypersensitivity to dandelion or to other plants of the Asteraceae (Compositae) family as a contraindication.
- Pregnancy and lactation — the EU herbal monograph states that safety during pregnancy and lactation has not been established and that, in the absence of sufficient data, use during pregnancy and lactation is not recommended. Herbal writers also report that the bitter principles cross into breast milk and can produce bitter milk that infants may reject; they caution against concentrated bitter tinctures while breastfeeding and regard modest food use of dandelion as acceptable.
- Drug interactions — modest CYP1A2 and CYP3A4 modulation in vitro; clinical significance is uncertain but generally small. No specific high-magnitude drug interactions consistently reported.
The EU herbal monograph adds further safety facts relevant to digestion. Epigastric pain and hyperacidity (stomach pain and too much stomach acid) may occur, and so may allergic reactions; the frequency of both is not known. It states that use in people with kidney failure, diabetes or heart failure "should be avoided because of possible risks due to hyperkalemia" (high blood potassium). Use in children under 12 years of age has not been established, due to lack of adequate data. Under interactions with other medicines, it lists "None reported."
Key Research Papers
- Trojanova I, Rada V, Kokoska L, Vlkova E (2004). The bifidogenic effect of Taraxacum officinale root. Fitoterapia. — PubMed PMID: 15567259
- Wirngo FE, Lambert MN, Jeppesen PB (2016). The physiological effects of dandelion (Taraxacum officinale) in type 2 diabetes. Review of Diabetic Studies. — PubMed PMID: 28012278
- McMullen MK, Whitehouse JM, Towell A (2015). Bitters: time for a new paradigm. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 26074998
- Chambers ES, Preston T, Frost G, Morrison DJ (2018). Role of gut microbiota-generated short-chain fatty acids in metabolic and cardiovascular health. Current Nutrition Reports. — PubMed PMID: 30264354
- Roberfroid M (2007). Prebiotics: the concept revisited. Journal of Nutrition. — PubMed PMID: 17311983
- Gibson GR, Roberfroid MB (1995). Dietary modulation of the human colonic microbiota: introducing the concept of prebiotics. Journal of Nutrition. — PubMed PMID: 7782892
- Behrens M, Meyerhof W (2011). Gustatory and extragustatory functions of mammalian taste receptors. Physiology and Behavior. — PubMed PMID: 21324331
- Schutz K, Carle R, Schieber A (2006). Taraxacum — a review on its phytochemical and pharmacological profile. Journal of Ethnopharmacology. — PubMed PMID: 16950583
- Janda K, Gutowska I, Geszke-Moritz M, Jakubczyk K (2021). The common cichory (Cichorium intybus L.) as a source of extracts with health-promoting properties. Molecules. — PubMed PMID: 33807029
- Talley NJ, Ford AC (2015). Functional dyspepsia. New England Journal of Medicine. — PubMed PMID: 26535514
- Sperber AD, Bangdiwala SI, Drossman DA, Ghoshal UC, Simren M, Tack J, et al. (2021). Worldwide prevalence and burden of functional gastrointestinal disorders, results of Rome Foundation Global Study. Gastroenterology 160(1):99-114.e3. — PubMed PMID: 32294476
- Li Y, Chen Y, Sun-Waterhouse D (2022). The potential of dandelion in the fight against gastrointestinal diseases: a review. Journal of Ethnopharmacology 293:115272. — PubMed PMID: 35405251
- Teterovska R, Skotele RE, Maurina B, Sile I (2025). Medicinal plants in food supplements for gastrointestinal disorders: critical assessment of health claims on gastric acid regulation. Nutrients 17(23):3674. — PubMed PMID: 41373965