Star Anise for Respiratory Health and Cough
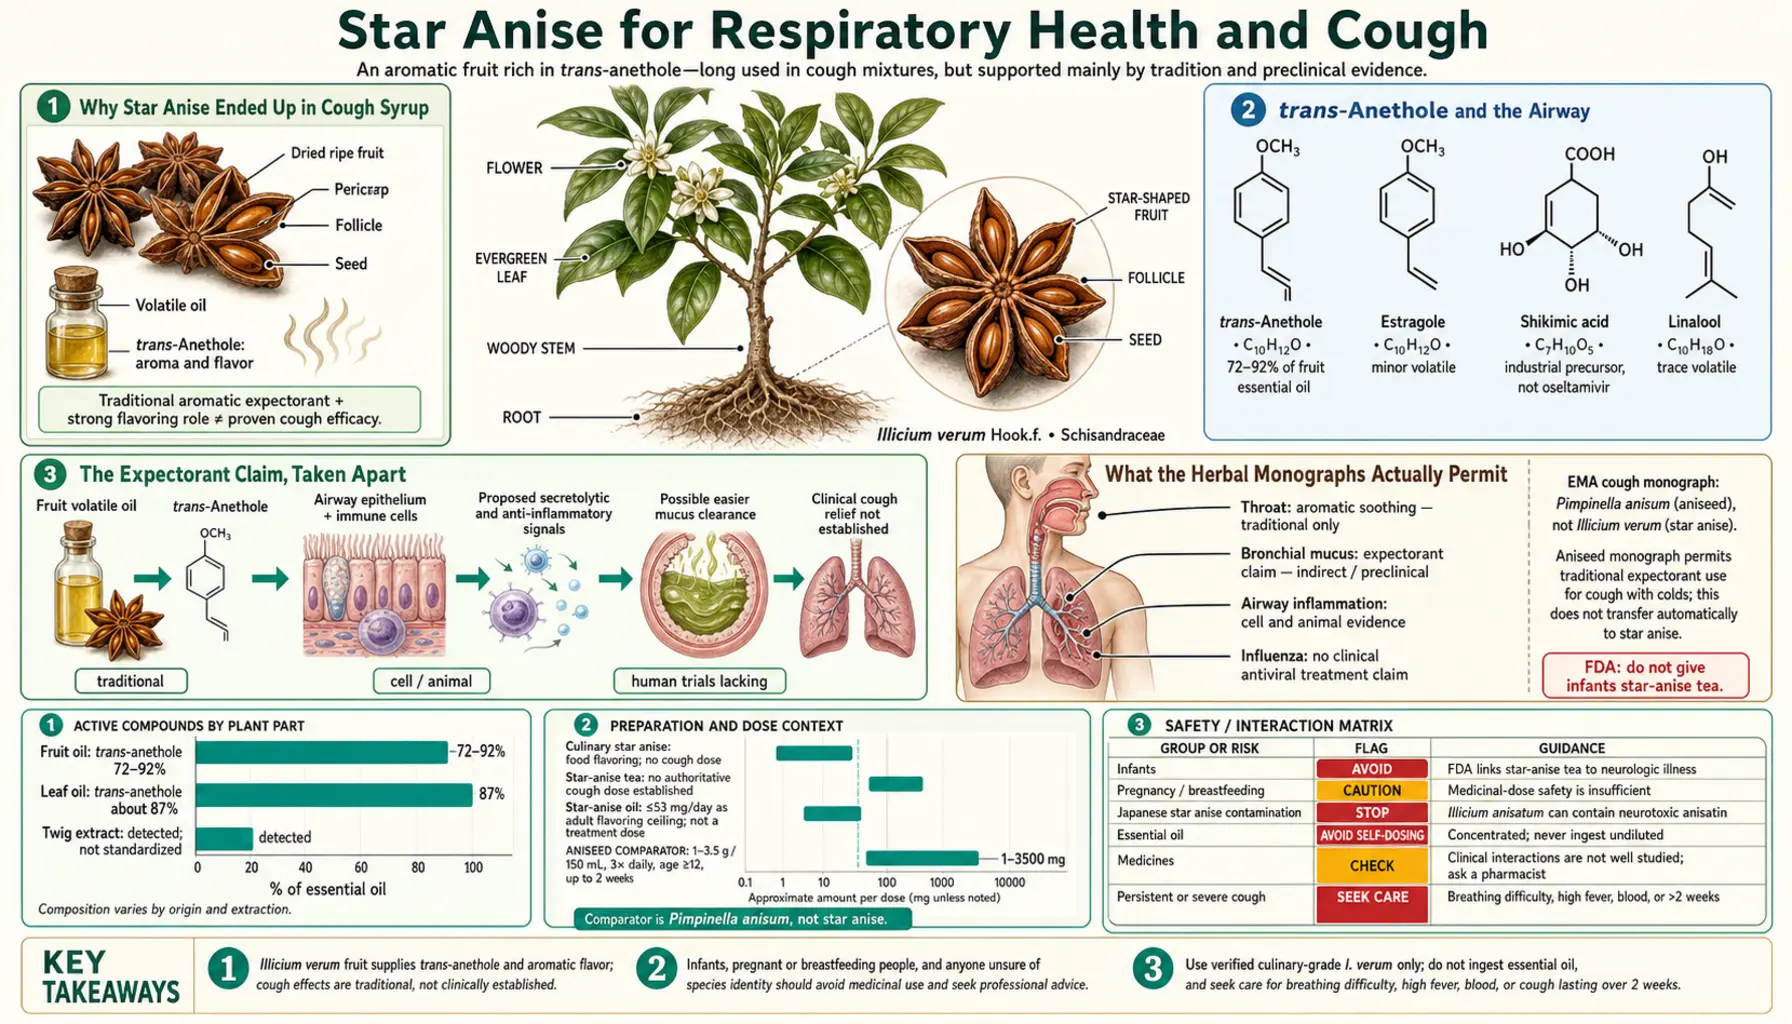
If you have ever tasted a cough syrup, a throat lozenge or a children's chest rub and thought “licorice,” you were almost certainly tasting anethole — and there is a reasonable chance it came from star anise or its close flavour relative aniseed. That flavour is not decoration. Anise-family volatiles have been in European cough preparations for four hundred years, and star anise carries a formal place in the German Commission E monographs for catarrh of the respiratory tract, while its close flavour relative aniseed has a European Union traditional-use monograph for coughs associated with colds.
This page sets out what that actually means. It means star anise has a long, documented, regulator-acknowledged tradition of use for coughs. It does not mean anyone has run a randomised controlled trial of star anise for cough and found it works. The distinction matters, and monograph language is often quoted in a way that erases it.
There is also a firm age line in the record. Star anise's respiratory tradition is an adult tradition. The preparations that have harmed people are strong infusions and teas, and most reported cases are infants — usually given tea for colic rather than cough, but the exposure route is identical — though adult outbreaks are recorded too (see Children, Cough and Star Anise). Nothing on this page applies to babies.
Table of Contents
- Why Star Anise Ended Up in Cough Syrup
- trans-Anethole and the Airway
- The Expectorant Claim, Taken Apart
- What the Herbal Monographs Actually Permit
- Grading the Respiratory Evidence, Claim by Claim
- Laboratory Antimicrobial Work on Respiratory Organisms
- Anti-Inflammatory and Antioxidant Findings
- Children, Cough and Star Anise
- How Star Anise Is Actually Used for Cough
- Cough Remedies With Better Evidence Than Star Anise
- When a Cough Needs a Clinician, Not a Spice
- Key Research Papers
- Connections
- Featured Videos
Why Star Anise Ended Up in Cough Syrup
Three separate forces put anise volatiles into respiratory medicine, and untangling them explains why the tradition is so much stronger than the evidence.
First, taste. Anethole is roughly thirteen times sweeter than table sugar on the tongue and reads as warm and soothing rather than bitter. Any medicine intended for a person with a raw throat benefits enormously from that, and pharmacists worked this out long before anyone could measure a receptor. A large share of anise flavouring in cough products is doing exactly this job and nothing more.
Second, the sensory illusion of relief. Volatile aromatics stimulate cold and irritant receptors in the mouth, throat and nasal passages — the same trick menthol plays. That produces a genuine, immediate, subjectively powerful sensation of clearer breathing and a calmer throat without necessarily changing airflow, mucus or inflammation at all. It is a real effect on how you feel and a small or absent effect on the disease. Both facts deserve to be stated together.
Third, an actual pharmacological rationale. Anethole and related essential-oil components relax smooth muscle in isolated tissue preparations, including airway tissue, and volatile oils have measurable effects on airway secretions. This is the part with laboratory substance behind it, and it is covered in the next two sections.
Historically, star anise reached Europe in the sixteenth century and slotted straight into an existing pharmacy category alongside aniseed, fennel, licorice, hyssop and thyme — the warm sweet aromatics used for “catarrh,” a term that covered everything from a head cold to chronic bronchitis. In Chinese and Vietnamese practice star anise sat differently: primarily a warming interior herb for cold-type abdominal pain, with respiratory use secondary. The cough association is more European than East Asian, which is worth knowing when you see it presented as ancient Chinese medicine.
trans-Anethole and the Airway
Star anise fruit yields roughly 5 to 10 percent essential oil, and trans-anethole makes up 80 to 90 percent of that oil. When people discuss star anise pharmacology they are, to a first approximation, discussing one molecule.
The isolated-tissue evidence. The classic work here is Reiter and Brandt's 1985 study in Arzneimittel-Forschung, which screened the volatile oils of 22 plants, and some of their constituents, against tracheal and ileal smooth muscle strips from guinea pigs. Every oil relaxed the tracheal muscle, but anise oil (like fennel oil) increased the contractions of the ileal strip instead of relaxing it. Boskabady and Ramazani-Assari's 2001 paper in the Journal of Ethnopharmacology went further on the airway specifically, showing that Pimpinella anisum extract relaxes isolated guinea pig tracheal chains and probing the mechanism. Anise is not star anise, but it is anethole-dominant in the same way, and this is the closest direct evidence the airway claim has.
What that does and does not establish. A tracheal chain in an organ bath is a strip of tissue bathed directly in a known concentration of compound, with no liver, no gut wall and no bloodstream in the way. It tells you a molecule can relax airway smooth muscle. It does not tell you that drinking a cup of tea delivers enough of that molecule to the bronchi of a living person to matter. That gap — from organ bath to human airway — is where most herbal respiratory claims quietly fail, and for star anise it has never been bridged by a trial.
Evidence tier: preliminary (isolated tissue and animal). Mechanistically coherent, clinically unproven.
Bronchodilation is not the same as cough suppression anyway. Relaxing airway smooth muscle helps in bronchoconstriction — the wheeze of asthma. Most everyday coughs are not bronchoconstriction; they are cough-reflex hypersensitivity plus mucus plus inflamed upper airway. A compound that relaxes bronchi could be genuinely useful in one and irrelevant in the other. “Relaxes tracheal smooth muscle” does not mean “stops a cough,” and star anise has never been tested as an asthma treatment in humans. No study supports it as an asthma treatment or as a replacement for an inhaler.
The Expectorant Claim, Taken Apart
“Expectorant” is used loosely in marketing and precisely in pharmacology, and the imprecision hides a lot. There are two distinct mechanisms:
- Secretolytic — changing the mucus itself, making it thinner and less viscous so it can move.
- Secretomotor — increasing the rate at which the ciliated airway lining sweeps mucus upward, without necessarily changing the mucus.
Volatile oils are traditionally claimed to do both, on the reasoning that a fraction of inhaled or ingested aromatic compounds is excreted across the airway epithelium, drawing water with it and stimulating the cilia. There is a real experimental literature on essential oils and mucociliary transport, mostly in animal models and isolated preparations, and the effects reported are typically modest.
For star anise specifically, human data is absent. There is no trial measuring sputum viscosity, mucociliary clearance or cough frequency in people given star anise. The claim rests on class-level reasoning about volatile oils plus the traditional monograph, and that is a much weaker foundation than a product label implies.
Evidence tier: traditional use, with class-level animal plausibility.
One honest observation about steam. A great deal of the relief people get from an aromatic inhalation is the steam — warm humidified air genuinely loosens secretions and soothes an irritated upper airway — and a star anise steam bowl works partly because it is a steam bowl. That is not a criticism. Warm humid air is cheap, safe for adults and works. It just means the credit is distributed differently than the label suggests.
What the Herbal Monographs Actually Permit
Two regulatory documents get quoted constantly, usually without their qualifiers.
The German Commission E monograph for star anise fruit lists uses covering catarrh of the respiratory tract and dyspeptic complaints. Commission E monographs were compiled in the 1980s and 1990s by an expert commission weighing traditional use, plausibility and whatever literature existed. They are a considered regulatory judgement about acceptable traditional use. They are not systematic reviews of clinical trials, and for star anise there were essentially no trials to review.
The European Medicines Agency, through its Committee on Herbal Medicinal Products, has no monograph for star anise: its list of herbal substances has no star anise entry. The monograph usually quoted is for aniseed (Anisi fructus, Pimpinella anisum), the anethole-rich flavour relative, as a traditional herbal medicinal product — a specific legal category. The label matters enormously:
- A well-established use designation means there is recognised scientific evidence of efficacy, usually including clinical trials.
- A traditional use designation means the indication rests on plausibility plus at least thirty years of documented use, with no requirement for trial evidence, and products carry a statement that their use is based exclusively on long-standing use.
Aniseed is in the second category. Its monograph indications cover use as an expectorant for coughs associated with colds and mild indigestion complaints including bloating and flatulence; use is limited to adults and adolescents over 12 years and to no longer than two weeks. Star anise itself has no such European Union monograph, and its infant poisoning reports are described on the safety page.
So when a package or a blog says “approved in Europe for coughs,” the accurate translation for aniseed is: permitted to be sold with a cough indication on the basis of tradition, for adults and adolescents over 12, for up to two weeks, with an explicit statement that its use is based on long-standing use. For star anise there is no European Union monograph to translate.
Grading the Respiratory Evidence, Claim by Claim
Nothing here is dropped for being thinly supported — each claim is listed with the tier it honestly occupies.
- “Soothes a sore, tickly throat.” Plausible and largely non-controversial. Warm liquid, sweetness and aromatic sensory effects all contribute. Much of this is not specific to star anise.
- “Loosens phlegm / acts as an expectorant.” Traditional use, with class-level animal plausibility. No human data for star anise.
- “Relieves a dry cough.” Traditional use. Recognised in monographs on that basis alone.
- “Relaxes the airways.” Preliminary, isolated tissue. Demonstrated in organ baths with anethole-rich extracts; never demonstrated in a human lung.
- “Fights respiratory infections.” Preliminary, in vitro only, and not transferable. See the next section.
- “Reduces airway inflammation.” Preliminary, cell culture and rodent.
- “Prevents or treats flu.” No evidence, and the proposed mechanism does not hold together. This is the shikimic acid myth — see the antiviral page.
- “Safe for a baby's cough.” False and specifically dangerous.
Laboratory Antimicrobial Work on Respiratory Organisms
Star anise essential oil inhibits a wide range of bacteria and fungi in culture, and the literature includes work against organisms relevant to the respiratory tract as well as food-spoilage species. The mechanism is unglamorous and well understood: anethole and other lipophilic volatiles insert into and destabilise microbial membranes, leaking ions and small molecules until the cell fails. It is a physical mode of action, which is also why resistance to it develops less readily than resistance to a targeted antibiotic — a genuinely interesting property for food preservation research.
Why it does not transfer to your chest. Three reasons, each sufficient on its own:
- Concentration. Inhibitory concentrations in these assays are typically in the range of hundreds to thousands of micrograms per millilitre applied directly to organisms on a plate. Drinking star anise tea does not produce anything remotely comparable at a site of infection.
- Distribution. Anethole is absorbed, metabolised in the liver and excreted. It does not accumulate in bronchial secretions at antimicrobial concentrations.
- Target. Most acute coughs, bronchitis included, are viral. A membrane-disrupting antibacterial would be the wrong tool even if it reached the tissue.
Evidence tier: preliminary, in vitro. Legitimate research with a legitimate application in food science. Star anise is not an antibiotic, and no human trial shows it treating any infection.
Anti-Inflammatory and Antioxidant Findings
Star anise extracts reduce inflammatory signalling in cell models and in rodents, lowering markers such as tumor necrosis factor-α and interleukin-6, and the flavonoid fraction — chiefly quercetin and kaempferol glycosides — scavenges free radicals in chemical assays. Anethole itself has been studied for anti-inflammatory and analgesic effects in rodent models, and the 2016 review by Aprotosoaie, Costache and Miron in Advances in Experimental Medicine and Biology gathers this literature across organ systems.
Airway inflammation is the core problem in asthma and in chronic bronchitis, so anti-inflammatory activity is the right kind of finding to be interested in. But the distance from “lowers interleukin-6 (IL-6) in stimulated macrophages” to “improves symptoms in a person with airway disease” is enormous, and has not been crossed for star anise. Reported effects are also generally modest by pharmaceutical standards.
Evidence tier: preliminary (cell culture and rodent). “Star anise is anti-inflammatory” is a true statement about an assay and an unproven statement about a person.
Children, Cough and Star Anise
This section exists because cough is the commonest reason a worried parent reaches for a herbal remedy, and because star anise is the wrong one to reach for.
Infants: documented harm. In a 2004 Pediatrics case series, Ize-Ludlow and colleagues reported 7 infants with neurological reactions after star anise tea given at home, found evidence that Chinese star anise had been contaminated with Japanese star anise, and concluded that star anise tea “should no longer be administered to infants.” Two independent reasons converge. First, commercial star anise has repeatedly been found adulterated with Japanese star anise (Illicium anisatum), whose anisatin content is a potent gamma-aminobutyric acid-A antagonist and has caused documented seizures in infants. Second, even genuine Illicium verum contains small quantities of veranisatins, neurotoxic sesquiterpene lactones described by Nakamura, Okuyama and Yamazaki in Chemical & Pharmaceutical Bulletin in 1996. In that mouse study the veranisatins caused convulsions and death at an oral dose of 3 mg/kg, and veranisatin A reduced stimulated movement at 0.1 mg/kg against 0.03 mg/kg for anisatin — compounds present in the edible species and delivered to a very small body in a strong infusion. No cough benefit has been shown that would offset this.
Adults are poisoned too. In the Netherlands in 2001, 63 people fell ill with malaise, nausea and vomiting 2 to 4 hours after drinking one herbal tea that was found to contain the Japanese star anise toxin anisatin; 22 needed hospital care, 16 of them for generalised tonic-clonic seizures, and all recovered with supportive treatment (Johanns and colleagues, 2002). A 2024 case series from Bhutan describes two more emergency-department cases of star anise toxicity with gut and nervous-system symptoms (Wangdi and colleagues).
Young children: culinary and medicinal exposure differ. Star anise simmered in a family pot of broth and then removed is a completely different exposure from a medicinal infusion, and it is not the concern. Brewed star anise tea as a remedy is. The European Union aniseed monograph's age limit (adults and adolescents over 12) draws a similar line for the related spice.
What actually helps a child's cough. Honestly and unglamorously: fluids, warm drinks, humidified air, rest, and — for children over one year — honey, which has the best evidence of any home remedy for nocturnal cough in children and is the subject of a Cochrane review. Honey is not given under twelve months because of the risk of infant botulism. Over-the-counter cough and cold medicines are not recommended for young children by most paediatric bodies, and this is one of the rare cases where the herbal alternative with real trial data is also the cheapest thing in the cupboard.
How Star Anise Is Actually Used for Cough
Described because readers will do it anyway, and doing it well is safer than doing it badly. All of the following is for adults.
- Whole, ground or bagged. Ground star anise and pre-bagged “star anise tea” cannot be checked by eye at all, and fruits sold broken or ground are one reason contamination is common. Whole stars cannot be reliably checked by eye either: Chinese and Japanese star anise look almost the same, a 2011 Swiss infant poisoning involved an infusion of 4 to 5 whole fruits whose sample held 7,800 µg/kg anisatin (the Swiss limit is 1,000 µg/kg), and only laboratory tests — thin-layer chromatography and liquid chromatography with mass spectrometry — reliably tell the species apart (Perret 2011; Lederer 2006).
- Weak, not strong. The traditional adult preparation is one star, or one lightly crushed star, in a large mug of hot water, steeped a few minutes. The infant poisonings involved much stronger infusions (in the Swiss case, 4 to 5 fruits per 200 mL bottle, three bottles in a few hours).
- Short-term. Traditional use is a few days for an acute cough. Star anise contains estragole, which causes liver tumours in rodents at high doses, and there is no safety data for concentrated infusions drunk daily for months.
- Better in company. The traditional cough combinations put anise volatiles alongside thyme, licorice, marshmallow root or mullein, and most of those partners carry more of the actual soothing effect.
- Steam inhalation. A star or two in a bowl of hot water, towel over the head, eyes closed, face far enough away not to scald. Most of the benefit is the steam. Scalds from inhalation bowls of boiling water are a recognised injury in children.
- The essential oil is not a drink. Star anise essential oil is highly concentrated in anethole and contains estragole. It is used for flavouring and perfumery under strict limits, not taken internally.
Cough Remedies With Better Evidence Than Star Anise
Several cough remedies have more trial evidence than star anise:
- Honey — the strongest evidence base of any home cough remedy, particularly for night-time cough in children over one year, and the subject of a Cochrane review. The 2018 update (6 trials, 899 children aged 12 months to 18 years) found honey probably reduces cough frequency more than placebo (mean difference −1.62 on a 7-point scale) or no treatment (−1.05), and may work about as well as dextromethorphan; most children were treated for one night only. Evidence tier: randomised trials and systematic review.
- Ivy leaf (Hedera helix) extract — standardised preparations have been studied in paediatric and adult cough with reasonable results, and are widely licensed in Europe. Evidence tier: randomised trials, mostly open-label or industry-sponsored.
- Pelargonium sidoides extract — a body of randomised trial evidence in acute bronchitis. The newest trial, PHYTOBRONCH (Switzerland, 2026; open-label, 332 adults), found no significant difference from usual care in the time to halve symptoms (p = 0.578) or in antibiotic use (17.4% vs 25.2%, p = 0.309), and side effects, all mild, were more frequent (32.3% vs 21.5%). Evidence tier: randomised trials, with mixed results.
- Thyme, usually combined with primrose root — trial evidence for the fixed combination in acute bronchitis. Evidence tier: randomised trials of the combination.
- Warm fluids and humidified air — modest, safe, immediate.
- Marshmallow root and other demulcents — mucilage coats an irritated throat. Thin trial evidence, very good safety, and a genuinely different mechanism from anything star anise offers.
Star anise's honest position in this list is as a pleasant, traditional, adult-only adjunct with no trial evidence of its own — not a first-line choice.
When a Cough Needs a Clinician, Not a Spice
Most acute coughs settle in one to three weeks without treatment. These signs are ones that doctors treat as needing prompt assessment:
- Breathlessness at rest, chest pain, or a fast breathing rate
- Coughing blood
- A cough lasting more than three weeks, or eight weeks in an adult who smokes
- Fever with rigors, confusion, or feeling seriously unwell — possible pneumonia
- Unexplained weight loss, night sweats, or a hoarse voice lasting more than three weeks
- Wheeze that is new, or worsening breathlessness in someone with known asthma or bronchitis
- Any cough in a baby under three months, or a child who is struggling to breathe, feed or stay awake
A persistent cough is a symptom that deserves a diagnosis. See Chronic Cough for the differential.
Key Research Papers
Entries for a single paper end with its PubMed PMID link; entries marked “Find on PubMed” are topic searches.
- Wang GW, Hu WT, Huang BK, Qin LP. “Illicium verum: a review on its botany, traditional use, chemistry and pharmacology.” Journal of Ethnopharmacology, 2011. The standard reference for star anise chemistry and pharmacology, including the respiratory tradition. PubMed PMID: 21549817
- Boskabady MH, Ramazani-Assari M. “Relaxant effect of Pimpinella anisum on isolated guinea pig tracheal chains and its possible mechanism(s).” Journal of Ethnopharmacology, 2001. The most directly airway-relevant work on an anethole-dominant plant. PubMed PMID: 11137352
- Reiter M, Brandt W. “Relaxant effects on tracheal and ileal smooth muscles of the guinea pig.” Arzneimittel-Forschung, 1985. The classic comparative screen of 22 plant volatile oils and some constituents on airway and gut smooth muscle. PubMed PMID: 4039178
- Aprotosoaie AC, Costache II, Miron A. “Anethole and its role in chronic diseases.” Advances in Experimental Medicine and Biology, 2016. A review of anethole pharmacology, including anti-inflammatory and smooth-muscle effects. PubMed PMID: 27771928
- Patra JK, Das G, Bose S, et al. “Star anise (Illicium verum): chemical compounds, antiviral properties, and clinical relevance.” Phytotherapy Research, 2020. Useful for the breadth of laboratory work on the species; read with attention to evidence tier. PubMed PMID: 31997473
- Nakamura T, Okuyama E, Yamazaki M. “Neurotropic components from star anise (Illicium verum Hook. fil.)” Chemical & Pharmaceutical Bulletin, 1996. The veranisatins — neuroactive compounds in the edible species, and part of the case against strong infusions for children. PubMed PMID: 8904818
- Ize-Ludlow D, Ragone S, Bruck IS, Bernstein JN, Duchowny M, Peña BM. “Neurotoxicities in infants seen with the consumption of star anise tea.” Pediatrics, 2004. The paediatric case series behind every age restriction on this page. PubMed PMID: 15492355
- Oduwole O, Udoh EE, Oyo-Ita A, Meremikwu MM. “Honey for acute cough in children.” Cochrane Database of Systematic Reviews, 2018;4:CD007094. The benchmark review for home cough remedies in children. PubMed PMID: 29633783
- Randomised trials of standardised ivy-leaf (Hedera helix) extract in cough and acute bronchitis. Find on PubMed
- Bourqui A, Corpataux O, Bonofiglio F, Dubois J, Abolhassani N, Baggio S, Csajka C, Rodondi PY, Podmore C. “Pelargonium sidoides extract (EPs 7630) versus usual care for acute bronchitis in Swiss primary care (PHYTOBRONCH): a pragmatic, open-label, randomised controlled trial.” NPJ Primary Care Respiratory Medicine, 2026;36:41. PubMed PMID: 42014704
- Johanns ES, van der Kolk LE, van Gemert HM, Sijben AE, Peters PW, de Vries I. “An epidemic of epileptic seizures after consumption of herbal tea.” Nederlands Tijdschrift voor Geneeskunde, 2002;146:813-6 (in Dutch). PubMed PMID: 12014242
- Wangdi S, Wangdi J, Wangchuk N. “Case series: star anise toxicity presenting to the emergency department in Eastern Regional Referral Hospital in Bhutan.” International Journal of Emergency Medicine, 2024;17:122. PubMed PMID: 39266976
- Perret C, Tabin R, Marcoz JP, Llor J, Cheseaux JJ. “Apparent life-threatening event in infants: think about star anise intoxication!” Archives de Pédiatrie, 2011;18:750-3 (in French). PubMed PMID: 21652187
- Lederer I, Schulzki G, Gross J, Steffen JP. “Combination of TLC and HPLC-MS/MS methods. Approach to a rational quality control of Chinese star anise.” Journal of Agricultural and Food Chemistry, 2006;54:1970-4. PubMed PMID: 16536563
- Experimental work on essential oils, airway secretion and mucociliary clearance — the class-level basis for the expectorant claim. Find on PubMed
- Antibacterial and antifungal activity of Illicium verum essential oil against respiratory and food-borne organisms. Find on PubMed
Connections
- All Herbs
- Star Anise (Illicium verum) — the main reference page: botany, chemistry, culinary use and cautions.
- Star Anise, Shikimic Acid and Antiviral Research — why the flu claim fails, in chemical detail.
- Star Anise Safety — the adulteration problem behind the age restrictions above.
- Thyme and Thyme Benefits — the anise partner in cough preparations, with actual trial data for the thyme–primrose combination.
- Mullein and Mullein Benefits — the classic demulcent expectorant of Western herbal practice.
- Marshmallow Root — mucilage for a raw throat, a genuinely different mechanism.
- Elecampane and Horehound — the other traditional European cough herbs star anise was blended with.
- Licorice and Licorice Benefits — the other “licorice” cough herb, chemically unrelated, with a real blood-pressure caution.
- Fennel and Fennel Benefits — the anethole relative, used the same way and better studied.
- Elderberry Benefits — the other herb people reach for at the first sign of a cold, with its own evidence limits.
- Bronchitis — the condition most often behind a productive cough.
- Chronic Cough — when a cough stops being self-limiting and needs a diagnosis.
- Asthma — why “relaxes airway smooth muscle” does not make it a substitute for an inhaler.
- Pulmonology — the full respiratory disease index.
Disclaimer. This page is educational and is not medical advice. Star anise has no clinical trial evidence for any respiratory condition; its cough indication in the German Commission E monograph rests on long-standing traditional use, and the European Union monograph for its relative aniseed is limited to adults and adolescents over 12 and to no more than two weeks. Star anise tea has caused seizures and other neurological reactions in infants, and the 2004 Pediatrics case series concluded it should no longer be given to infants. No study shows star anise treating asthma, pneumonia, influenza or any infection, or replacing prescribed inhalers, antibiotics or antivirals. Safety of concentrated infusions and the essential oil in pregnancy and breastfeeding has not been established, and the anise toxins behind the poisoning cases cause seizures, which raises a particular concern for people with epilepsy or a seizure history. Breathlessness, chest pain, coughing blood, or a cough in a baby under three months are signs that hospitals treat as urgent.