Saffron for Mood and Depression
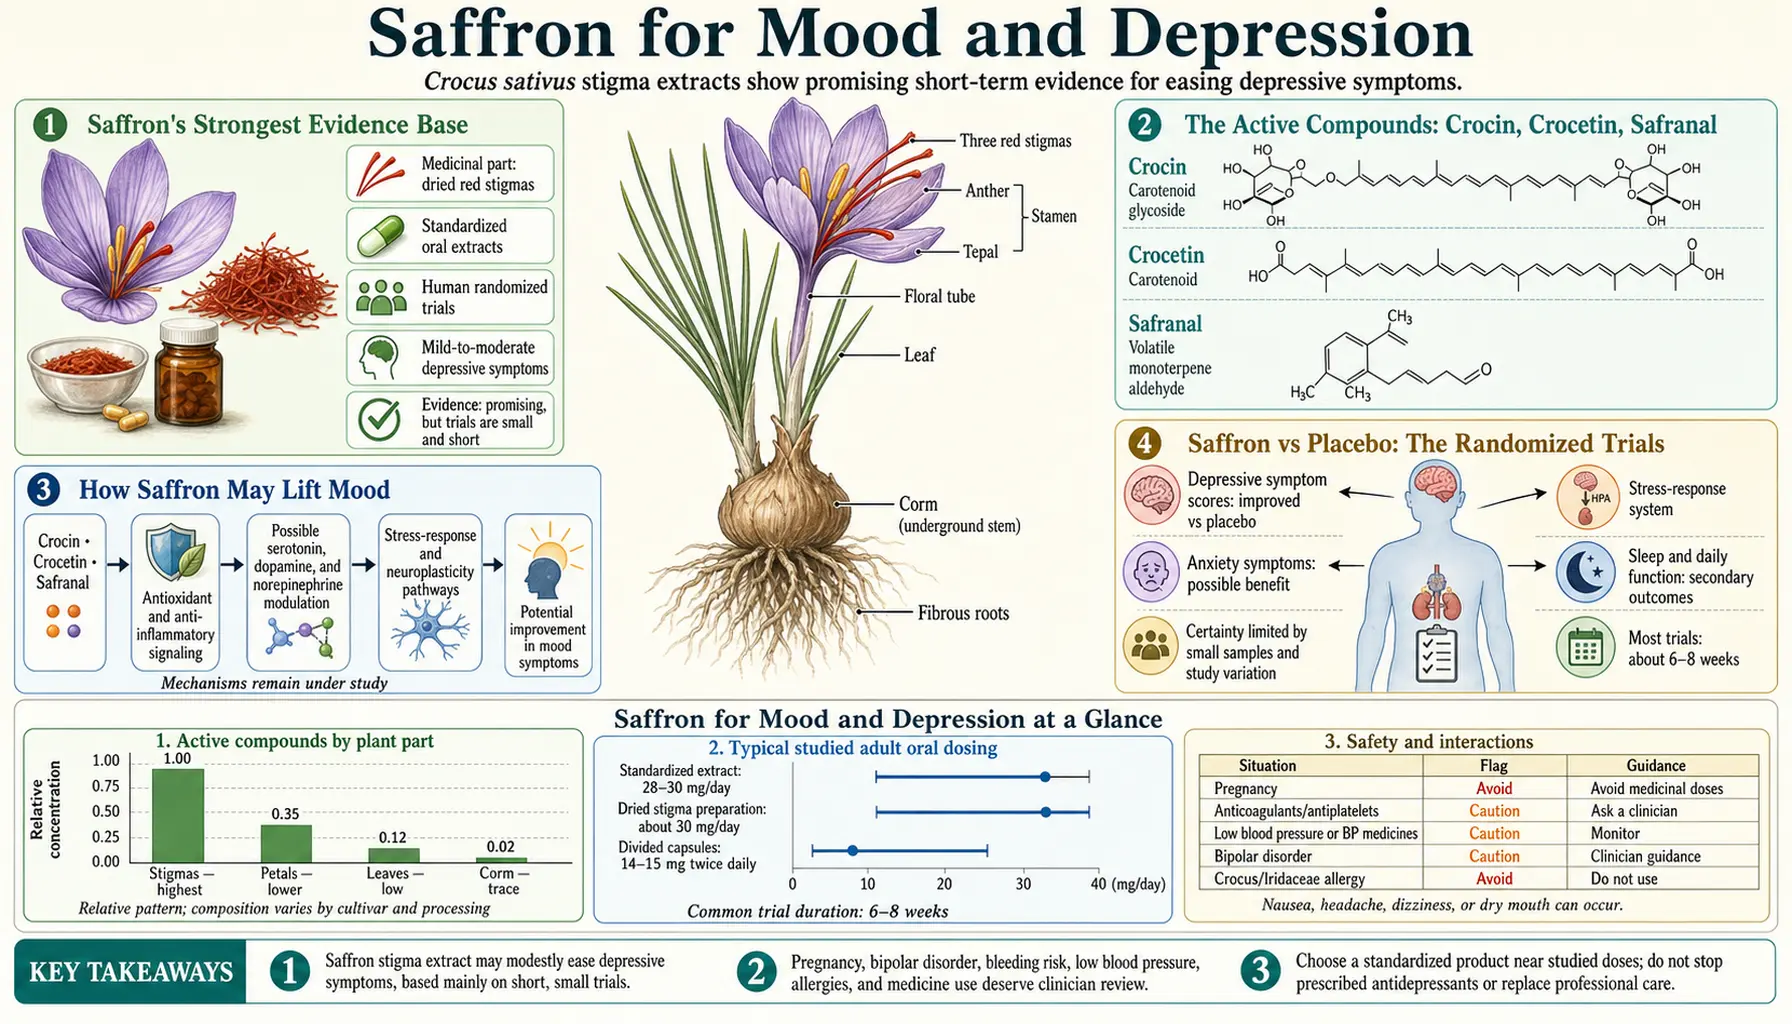
Depression is the use of saffron with the most human trial data behind it. Since 2004, randomized, double-blind trials have tested saffron — usually 30 mg per day — in adults with mild-to-moderate depression, against placebo and against the antidepressants imipramine, fluoxetine, citalopram, and sertraline. Most of the early trials came from one research group in Tehran. In those trials saffron did better than placebo and showed no statistically significant difference from the comparison drug over six to eight weeks, and several meta-analyses have pooled the results. The same reviews also report small samples, short follow-up, trials concentrated in one country, high heterogeneity in the newest pooled analysis, and evidence of publication bias. This page sets out both sides. Trial results are not evidence about stopping a prescribed antidepressant: decisions about medicines belong with the prescriber.
Table of Contents
- Saffron's Strongest Evidence Base
- The Active Compounds: Crocin, Crocetin, Safranal
- How Saffron May Affect Mood
- Saffron vs Placebo: The Randomized Trials
- Head-to-Head With Antidepressants
- What the Meta-Analyses Show
- Add-On Use and SSRI Side Effects
- Standardized Extracts and Newer Trials
- Doses and Durations Used in the Trials
- Limitations of the Evidence
- Safety Findings
- Key Research Papers
- External Authoritative Resources
- Connections
- Featured Videos
Saffron's Strongest Evidence Base
Most herbal remedies rest on tradition, laboratory data, and a few small studies. For depression, saffron has been tested in randomized, double-blind trials (neither patient nor researcher knew who got saffron), with a placebo or an antidepressant as the comparison, using validated rating scales such as the Hamilton Depression Rating Scale (HAM-D) and the Beck Depression Inventory (BDI).
Iran produces about 90 percent of the world's saffron and, as the 2013 meta-analysis by Hausenblas and colleagues notes, generates most of the research into its medical uses. The first trials came from the psychiatric research center at Roozbeh Hospital, Tehran University of Medical Sciences, led by Shahin Akhondzadeh, starting in 2004. Akhondzadeh is an author on every one of the five trials pooled in that meta-analysis, which describes them as single-center trials run in the same clinical setting in Iran; its authors called for larger trials by research teams outside Iran. Later trials came from other Iranian centers (Mashhad, Hamadan), from Australia, and elsewhere.
The pooled result is that, in adults with mild-to-moderate depression, saffron at about 30 mg per day reduced depression scores more than placebo, and the trials comparing it with an antidepressant found no statistically significant difference. Those trials did not include people with severe or treatment-resistant depression, and none tested replacing an antidepressant in people already stable on one.
The Active Compounds: Crocin, Crocetin, Safranal
Saffron threads are the dried stigmas of the flower Crocus sativus. Their color, bitterness, and aroma come from a few families of compounds, which laboratory studies have examined for effects related to mood:
- Crocin — the water-soluble carotenoid pigment responsible for saffron's deep red-gold color. Chemically it is crocetin bound to sugar molecules, which makes it far more water-soluble than typical carotenoids like beta-carotene.
- Crocetin — the smaller carotenoid "core" released when crocin is broken down.
- Safranal — the volatile molecule that gives saffron its distinctive hay-and-honey aroma. It forms from a bitter precursor called picrocrocin as saffron dries. In laboratory studies it is the constituent credited with inhibiting serotonin reuptake.
Supplements used in trials are usually standardized to a stated content of these markers (for example, a minimum percentage of crocins, or a fixed amount of safranal), so that each dose delivers a consistent amount. Standardization and quality are covered on the sources, dosing, and safety page.
How Saffron May Affect Mood
The mechanism is not established. Reviews by Lopresti and Drummond (2014) and Matraszek-Gawron and colleagues (2022) summarize several proposed pathways, drawn almost entirely from cell and animal studies:
- Monoamine reuptake. In laboratory studies crocin inhibits the reuptake of dopamine and noradrenaline, and safranal inhibits the reuptake of serotonin — the same broad targets as many conventional antidepressants.
- Other receptor effects. The 2022 review also lists NMDA-receptor antagonism and action at GABA receptors as proposed mechanisms.
- Anti-inflammatory and antioxidant action. In rodent models of depression, crocin lowered inflammatory markers such as TNF-alpha and interleukin-6; the reviews link the antidepressant and neuroprotective effects to anti-inflammatory and antioxidant activity.
- Neurotrophic effects. Animal studies report increased brain-derived neurotrophic factor (BDNF), a protein tied to mood disorders, in the hippocampus after saffron or crocin.
What the human trials measured is a change in depression scores. The pathways above are proposed explanations for that change, not demonstrated causes of it in people.
Saffron vs Placebo: The Randomized Trials
Two early placebo-controlled trials set the template. Both were run by the Tehran group:
Akhondzadeh and colleagues (2005), Phytotherapy Research. Forty adult outpatients with major depression (baseline HAM-D score of at least 18) were randomized to saffron stigma 30 mg per day, taken in two doses, or placebo for six weeks at a single center. The saffron group did significantly better on the Hamilton scale (p < 0.001), and side effects did not differ significantly between the groups. The authors wrote that a large-scale trial was justified.
Moshiri and colleagues (2006), Phytomedicine. This trial tested the petals of the saffron flower (a cheaper part of the plant than the stigma) at 30 mg per day against placebo for six weeks in forty adults with mild-to-moderate depression. The petal extract also did better than placebo on the Hamilton scale (p < 0.001).
Later placebo-controlled trials tested saffron in other groups and other countries, with mixed results on different scales; the meta-analyses below summarize them.
Head-to-Head With Antidepressants
Saffron has also been compared directly with prescription antidepressants. In each of these trials the abstract reports no statistically significant difference between the two arms:
- Versus imipramine (a tricyclic antidepressant) — Akhondzadeh and colleagues (2004): 30 adult outpatients, saffron 30 mg per day versus imipramine 100 mg per day for six weeks (P = 0.09 for the difference). Anticholinergic effects such as dry mouth, and sedation, were seen more often with imipramine. The authors called it a pilot trial and wrote that a large-scale trial with a placebo control was warranted.
- Versus fluoxetine (an SSRI) — Noorbala and colleagues (2005): 40 adult outpatients, saffron 30 mg per day versus fluoxetine 20 mg per day for six weeks (P = 0.71), with no significant difference in side effects. A second pilot trial from the same group, Akhondzadeh Basti and colleagues (2007), compared saffron petal 15 mg twice daily with fluoxetine 10 mg twice daily for eight weeks in 40 outpatients (P = 0.84; remission rate 25% in both groups). Shahmansouri and colleagues (2014) compared saffron 30 mg per day with fluoxetine 40 mg per day for six weeks in 40 patients with depression after a percutaneous coronary intervention (a heart procedure); the reduction in Hamilton scores did not differ significantly (P = 0.62), and the authors named the small sample and short observation period as the main limitations.
- Versus citalopram (an SSRI) — Ghajar and colleagues (2017): 66 patients with major depressive disorder with anxious distress were randomized to saffron 30 mg per day or citalopram 40 mg per day for six weeks; 60 finished. Both groups improved, and the difference between arms was not significant (P = 0.984). A published letter by Fountoulakis (2018) questioned whether the trial showed saffron to be as effective as citalopram.
- Versus sertraline (an SSRI) — Ahmadpanah and colleagues (2019): 50 older outpatients with major depressive disorder received saffron 60 mg per day or sertraline 100 mg per day for six weeks; depression scores fell over time with no advantage for either arm.
Figures as reported in each trial's PubMed abstract.
These results are often summarized as "non-inferiority", and the 2019 meta-analysis by Tóth and colleagues used that word for the pooled comparison. The limits matter. The abstracts do not report a pre-specified non-inferiority margin, so what they report is the absence of a statistically significant difference, which is not the same as showing the two treatments are equal. With 30 to 66 patients per trial, a real difference could go undetected. None of the comparisons included a placebo arm, so they cannot show that either treatment beat placebo in that sample. The drug doses ranged from a starting dose (fluoxetine 20 mg per day) to higher doses (fluoxetine 40 mg, citalopram 40 mg, sertraline 100 mg). Every trial lasted six to eight weeks, was run in Iran, and shared one senior author, and none enrolled people with severe depression.
What the Meta-Analyses Show
Meta-analyses pool the trials to estimate an overall effect. They differ in which trials they include, and they report the evidence's weaknesses as well as the effect:
- Hausenblas and colleagues (2013) pooled five trials (two against placebo, three against an antidepressant). The effect size against placebo was large (1.62, P < 0.001); against antidepressants it was close to zero (−0.15). Heterogeneity was zero for both comparisons (I² = 0%), and the mean Jadad quality score was 5. All five trials were single-center trials in the same clinical setting in Iran, lasted six to eight weeks, used 30 mg per day, enrolled 30 to 42 patients each, and had no follow-up; the authors wrote that more data were needed to understand publication bias. Two of the authors declared that they served as scientific advisors and consultants to a supplement company that markets a product containing saffron.
- Lopresti and Drummond (2014) identified six high-quality randomized, double-blind studies; saffron had large effects against placebo and similar efficacy to antidepressants. They described the research as "initial support" for saffron in mild-to-moderate depression.
- Yang and colleagues (2018) included seven trials and rated their overall quality as moderate. Against placebo the standardized mean difference was −1.22 (95% CI −1.94 to −0.49); against antidepressants it was 0.16 (95% CI −0.25 to 0.57). They reported moderate heterogeneity.
- Tóth and colleagues (2019), in Planta Medica, included eleven trials in mild-to-moderate depression and pooled nine. Saffron did better than placebo (g = 0.891, 95% CI 0.369 to 1.412, p = 0.001) and was described as non-inferior to the antidepressants tested (g = −0.246, 95% CI −0.495 to 0.004, p = 0.053). The authors assessed risk of bias with the Cochrane tool and tested heterogeneity with Cochran's Q and I²; the abstract does not give those results.
- Marx and colleagues (2019), in Nutrition Reviews, included 23 studies. Saffron had a large effect against placebo for depressive symptoms (g = 0.99) and anxiety symptoms (g = 0.95), and as an add-on to antidepressants (g = 1.23). Egger's regression test found evidence of publication bias, and the authors cited that and the lack of regional diversity as reasons further trials are required.
- Khaksarian and colleagues (2019) included eight studies. Against placebo the standardized mean difference was −0.86, with a 95% confidence interval of −1.73 to 0.00 that reaches zero; against fluoxetine it was 0.11 (95% CI −0.20 to 0.43).
- Dai and colleagues (2020) included twelve studies and found saffron better than placebo and as effective as antidepressants, with no difference in adverse effects; they wrote that multicenter trials with larger samples, longer treatment, and different ethnic groups are required.
- Musazadeh and colleagues (2022) pooled seven earlier meta-analyses in an umbrella review. Saffron reduced BDI scores, but did not significantly change HAM-D scores; the authors concluded it "cannot be considered as a single therapeutic approach to treat depression."
- Shafiee and colleagues (2025) compared saffron with SSRIs across eight studies and found no significant difference for depression (SMD 0.10, 95% CI −0.09 to 0.29) or, in four studies, anxiety. Participants taking saffron had fewer adverse events than those taking an SSRI.
- Mahmoudi and colleagues (2026) reviewed 34 placebo-controlled trials with 1,769 participants and rated the certainty of evidence with GRADE. Saffron reduced self-rated BDI scores (14 trials; WMD −4.39, 95% CI −6.64 to −2.15) and BAI anxiety scores, but with very high heterogeneity (I² = 92.3% and 94.8%). They found no significant effect on the clinician-rated HAM-D or HAM-A, or on the POMS mood scale. Certainty was rated moderate, and the authors wrote that the lack of clinician-rated effects "underscores need for high-quality trials."
The early analyses, built on a handful of trials from one group, found large effects with no heterogeneity. The larger and more recent analyses still find an effect on self-rated scales, but report publication bias (Marx 2019), very high heterogeneity, and no significant effect on clinician-rated scales (Mahmoudi 2026; Musazadeh 2022). None of the trials cited on this page carries a retraction or an expression of concern in PubMed or Crossref (checked October 2026).
Add-On Use and SSRI Side Effects
Some trials looked at saffron alongside conventional treatment rather than instead of it:
As an add-on. Talaei and colleagues (2015), a pilot trial in Mashhad, gave 40 patients with major depressive disorder an SSRI (fluoxetine, sertraline, or citalopram) plus either crocin 30 mg per day or placebo for four weeks. The crocin group improved significantly more on the self-rated Beck depression and anxiety inventories. The authors listed poor compliance, the short trial period, the small sample, and self-report measures as the main limitations. In Australia, Lopresti and colleagues (2019) enrolled 160 adults with persistent depression despite an antidepressant and gave them a standardized saffron extract (14 mg twice daily) or placebo for eight weeks: the clinician-rated MADRS score fell 41% with saffron and 21% with placebo, but the self-rated MADRS fell 27% and 26%, and the authors called the results conflicting. That trial was funded by the extract's manufacturer.
For SSRI-related sexual side effects. Sexual dysfunction is a common side effect of SSRIs. Modabbernia and colleagues (2012) randomized 36 married men whose depression was stabilized on fluoxetine to saffron 15 mg twice daily or placebo for four weeks; 30 finished. Saffron improved erectile function, intercourse satisfaction, and total scores more than placebo, but not orgasmic function, overall satisfaction, or desire. A companion trial by Kashani and colleagues (2013) in 38 women taking fluoxetine 40 mg per day found improvement in the total sexual-function score, including arousal, lubrication, and pain, but not in desire, satisfaction, or orgasm. Both trials came from the Tehran group.
Standardized Extracts and Newer Trials
Much of the newer research outside Iran uses one standardized saffron extract with a fixed content of active compounds per dose. Saffron sold as threads varies in strength with grade and storage, and is often adulterated, as the safety page details.
- Kell and colleagues (2017) randomized 128 adults who reported low mood but had no depression diagnosis to the extract at 28 mg per day, 22 mg per day, or placebo for four weeks. The 28 mg dose reduced negative mood and stress- and anxiety-related symptoms on self-report scales; the 22 mg dose had no effect. The authors named the self-reported screening and testing as the main weakness. The trial was funded by the extract's manufacturer.
- Lopresti and colleagues (2018) gave 80 young people aged 12 to 16 with mild-to-moderate anxiety or depressive symptoms the extract (14 mg twice daily) or placebo for eight weeks; 68 finished. The teenagers' own reports improved more with saffron, but parents' reports were inconsistent. This trial was also funded by the manufacturer.
- Lopresti and colleagues (2025) gave 202 adults with subclinical depressive symptoms 28 mg per day or placebo for twelve weeks, described by its authors as the largest saffron trial to date. Saffron improved the primary self-rated depression score more than placebo (Cohen's d = 0.39), with no between-group differences on the other secondary outcomes and a large placebo response. Two authors were employees of the extract's manufacturer, which sponsored the study.
These trials extend the research beyond diagnosed major depression to people with low mood, stress, and mild anxiety, measured mostly by self-report. Their manufacturer funding is a recognized source of bias, which is why reviews weigh them alongside the academic trials.
Doses and Durations Used in the Trials
The doses used across the depression trials are consistent:
- Dose: most trials used 30 mg of saffron per day, usually split into two doses; the sertraline comparison in older adults used 60 mg per day, and the standardized-extract trials used 28 mg per day (14 mg twice daily).
- Duration: the trials cited here ran four to eight weeks, with one twelve-week trial. Saffron was taken daily throughout.
- Form: trials used capsules or tablets of stigma, petal, or a standardized extract, not culinary threads. Amounts used in cooking are far below the trial doses.
- Who was studied: adults (and, in one trial, adolescents) with mild-to-moderate symptoms. Severe, psychotic, and bipolar depression were not studied, so there is no trial evidence for saffron in those conditions.
Saffron can interact with other medicines (see Safety Findings below). Decisions about supplements, especially alongside a prescribed antidepressant, belong with a doctor or pharmacist.
Limitations of the Evidence
The reviews above name the same weaknesses repeatedly:
- Small samples. The Iranian trials cited here enrolled 30 to 66 people each; the five pooled in 2013 enrolled 30 to 42 each.
- Short duration. Most trials lasted four to eight weeks; the five pooled in 2013 had no follow-up assessments. Short trials say nothing about relapse or long-term use.
- One country, one group. Most of the trials were run in Iran, and the early and head-to-head trials share one senior author. Hausenblas (2013) called for trials by teams outside Iran, and Marx (2019) cited the lack of regional diversity.
- Publication bias and heterogeneity. Marx and colleagues (2019) found evidence of publication bias; Mahmoudi and colleagues (2026) found I² above 90% and no significant effect on clinician-rated scales.
- Funding. The standardized-extract trials were funded by the extract's manufacturer, and the authors of the 2013 meta-analysis declared consulting ties to a supplement company.
- Mild-to-moderate only. The trials did not cover severe depression, and none tested replacing a working antidepressant with saffron.
The positive signal on self-rated depression scores is repeated across many trials, but these limitations are why the newest review asks for high-quality trials.
Safety Findings
- Stopping antidepressants. Suddenly stopping an SSRI or other antidepressant can cause withdrawal symptoms and a relapse of depression. None of the saffron trials tested replacing an antidepressant; changes to prescribed treatment are made with the prescriber.
- Serotonergic overlap. Because saffron constituents inhibit serotonin reuptake in laboratory studies, combining saffron with SSRIs, SNRIs, MAO inhibitors, tramadol, triptans, or other serotonergic drugs is a theoretical concern. The add-on trials above combined saffron or crocin with an SSRI under trial supervision.
- Severe symptoms. Saffron has not been tested as sole treatment for severe depression, bipolar disorder, psychosis, or suicidal thoughts. Anyone in crisis can reach emergency services or a local crisis line.
- Pregnancy. Saffron has traditional use as an emmenagogue and, at high doses, to induce labor or end a pregnancy. A 2026 integrative review on saffron and pregnancy (Alshdefat and colleagues) found that higher doses or occupational exposure (women working in saffron fields) were linked to uterine stimulation and increased miscarriage risk. The 2017 toxicology review by Bostan and colleagues reports malformations in animal studies at high doses but not at pharmacological doses, and notes that clinical trials on safety in pregnancy are insufficient. See the safety page.
- High doses. The trials used about 30 mg per day. A 2017 toxicology review found no significant toxicity at therapeutic doses in clinical and experimental studies. At much higher doses, the 2026 pregnancy review summarizes earlier pharmacology reviews: more than 5 grams can be toxic and 20 grams may be fatal.
Key Research Papers
- Akhondzadeh S, Tahmacebi-Pour N, Noorbala AA, et al. (2005). Crocus sativus L. in the treatment of mild to moderate depression: a double-blind, randomized and placebo-controlled trial. Phytotherapy Research — PubMed PMID: 15852492
- Akhondzadeh S, Fallah-Pour H, Afkham K, et al. (2004). Comparison of Crocus sativus L. and imipramine in the treatment of mild to moderate depression: a pilot double-blind randomized trial. BMC Complementary and Alternative Medicine — PubMed PMID: 15341662
- Noorbala AA, Akhondzadeh S, Tahmacebi-Pour N, et al. (2005). Hydro-alcoholic extract of Crocus sativus L. versus fluoxetine in the treatment of mild to moderate depression. Journal of Ethnopharmacology — PubMed PMID: 15707766
- Moshiri E, Basti AA, Noorbala AA, et al. (2006). Crocus sativus L. (petal) in the treatment of mild-to-moderate depression: a double-blind, randomized and placebo-controlled trial. Phytomedicine — PubMed PMID: 16979327
- Shahmansouri N, Farokhnia M, Abbasi SH, et al. (2014). A randomized, double-blind, clinical trial comparing the efficacy and safety of Crocus sativus L. with fluoxetine for improving mild to moderate depression in post percutaneous coronary intervention patients. Journal of Affective Disorders — PubMed PMID: 24289892
- Ghajar A, Neishabouri SM, Velayati N, et al. (2017). Crocus sativus L. versus citalopram in the treatment of major depressive disorder with anxious distress: a double-blind, controlled clinical trial. Pharmacopsychiatry — PubMed PMID: 27701683
- Ahmadpanah M, Ramezanshams F, Ghaleiha A, et al. (2019). Crocus sativus L. (saffron) versus sertraline on symptoms of depression among older people with major depressive disorders. Psychiatry Research — PubMed PMID: 31669837
- Talaei A, Hassanpour Moghadam M, Sajadi Tabassi SA, et al. (2015). Crocin, the main active saffron constituent, as an adjunctive treatment in major depressive disorder: a randomized, double-blind, placebo-controlled pilot clinical trial. Journal of Affective Disorders — PubMed PMID: 25484177
- Modabbernia A, Sohrabi H, Nasehi AA, et al. (2012). Effect of saffron on fluoxetine-induced sexual impairment in men: randomized double-blind placebo-controlled trial. Psychopharmacology — PubMed PMID: 22552758
- Lopresti AL, Drummond PD, Inarejos-García AM, Prodanov M (2018). affron, a standardised extract from saffron for the treatment of youth anxiety and depressive symptoms: a randomised, double-blind, placebo-controlled study. Journal of Affective Disorders — PubMed PMID: 29510352
- Kell G, Rao A, Beccaria G, et al. (2017). affron a novel saffron extract improves mood in healthy adults over 4 weeks in a double-blind, parallel, randomized, placebo-controlled clinical trial. Complementary Therapies in Medicine — PubMed PMID: 28735826
- Hausenblas HA, Saha D, Dubyak PJ, Anton SD (2013). Saffron (Crocus sativus L.) and major depressive disorder: a meta-analysis of randomized clinical trials. Journal of Integrative Medicine — PubMed PMID: 24299602
- Tóth B, Hegyi P, Lantos T, et al. (2019). The efficacy of saffron in the treatment of mild to moderate depression: a meta-analysis. Planta Medica — PubMed PMID: 30036891
- Lopresti AL, Drummond PD (2014). Saffron (Crocus sativus) for depression: a systematic review of clinical studies and examination of underlying antidepressant mechanisms of action. Human Psychopharmacology — PubMed PMID: 25384672
- Akhondzadeh Basti A, Moshiri E, Noorbala AA, et al. (2007). Comparison of petal of Crocus sativus L. and fluoxetine in the treatment of depressed outpatients: a pilot double-blind randomized trial. Progress in Neuro-Psychopharmacology and Biological Psychiatry — PubMed PMID: 17174460
- Marx W, Lane M, Rocks T, et al. (2019). Effect of saffron supplementation on symptoms of depression and anxiety: a systematic review and meta-analysis. Nutrition Reviews — PubMed PMID: 31135916
- Yang X, Chen X, Fu Y, et al. (2018). Comparative efficacy and safety of Crocus sativus L. for treating mild to moderate major depressive disorder in adults: a meta-analysis of randomized controlled trials. Neuropsychiatric Disease and Treatment — PubMed PMID: 29849461
- Khaksarian M, Behzadifar M, Behzadifar M, et al. (2019). The efficacy of Crocus sativus (Saffron) versus placebo and Fluoxetine in treating depression: a systematic review and meta-analysis. Psychology Research and Behavior Management — PubMed PMID: 31118846
- Dai L, Chen L, Wang W (2020). Safety and efficacy of saffron (Crocus sativus L.) for treating mild to moderate depression: a systematic review and meta-analysis. Journal of Nervous and Mental Disease — PubMed PMID: 32221179
- Musazadeh V, Zarezadeh M, Faghfouri AH, et al. (2022). Saffron, as an adjunct therapy, contributes to relieve depression symptoms: an umbrella meta-analysis. Pharmacological Research — PubMed PMID: 34757208
- Shafiee A, Jafarabady K, Seighali N, et al. (2025). Effect of saffron versus selective serotonin reuptake inhibitors (SSRIs) in treatment of depression and anxiety: a meta-analysis of randomized controlled trials. Nutrition Reviews — PubMed PMID: 38913392
- Mahmoudi R, Mohammadi-Sartang M, Servatyari K, Rafieipour N (2026). Effect of saffron on depression, anxiety and mood disorder: a GRADE assessed systematic review and meta-analysis of 34 randomized controlled trials. Nutritional Neuroscience — PubMed PMID: 41693488
- Matraszek-Gawron R, Chwil M, Terlecki K, Skoczylas MM (2022). Current knowledge of the antidepressant activity of chemical compounds from Crocus sativus L. Pharmaceuticals — PubMed PMID: 36678554
- Kashani L, Raisi F, Saroukhani S, et al. (2013). Saffron for treatment of fluoxetine-induced sexual dysfunction in women: randomized double-blind placebo-controlled study. Human Psychopharmacology — PubMed PMID: 23280545
- Lopresti AL, Smith SJ, Hood SD, Drummond PD (2019). Efficacy of a standardised saffron extract (affron®) as an add-on to antidepressant medication for the treatment of persistent depressive symptoms in adults: a randomised, double-blind, placebo-controlled study. Journal of Psychopharmacology — PubMed PMID: 31475623
- Lopresti AL, Smith SJ, Marx W, et al. (2025). An examination into the effects of a saffron extract (Affron) on mood and general wellbeing in adults experiencing low mood: a randomized, double-blind, placebo-controlled trial. Journal of Nutrition — PubMed PMID: 40414301
- Fountoulakis KN (2018). Is really Crocus sativus as effective as citalopram in the treatment of depression? [letter]. Pharmacopsychiatry — PubMed PMID: 28351080
- Bostan HB, Mehri S, Hosseinzadeh H (2017). Toxicology effects of saffron and its constituents: a review. Iranian Journal of Basic Medical Sciences — PubMed PMID: 28293386
- Alshdefat A, Ayed A, Aqtam I, et al. (2026). Saffron and pregnancy: cultural practices, beliefs, and safety evidence: an integrative review. Journal of Evidence-Based Integrative Medicine — PubMed PMID: 42186868