Rosemary for Hair Loss (Androgenetic Alopecia)
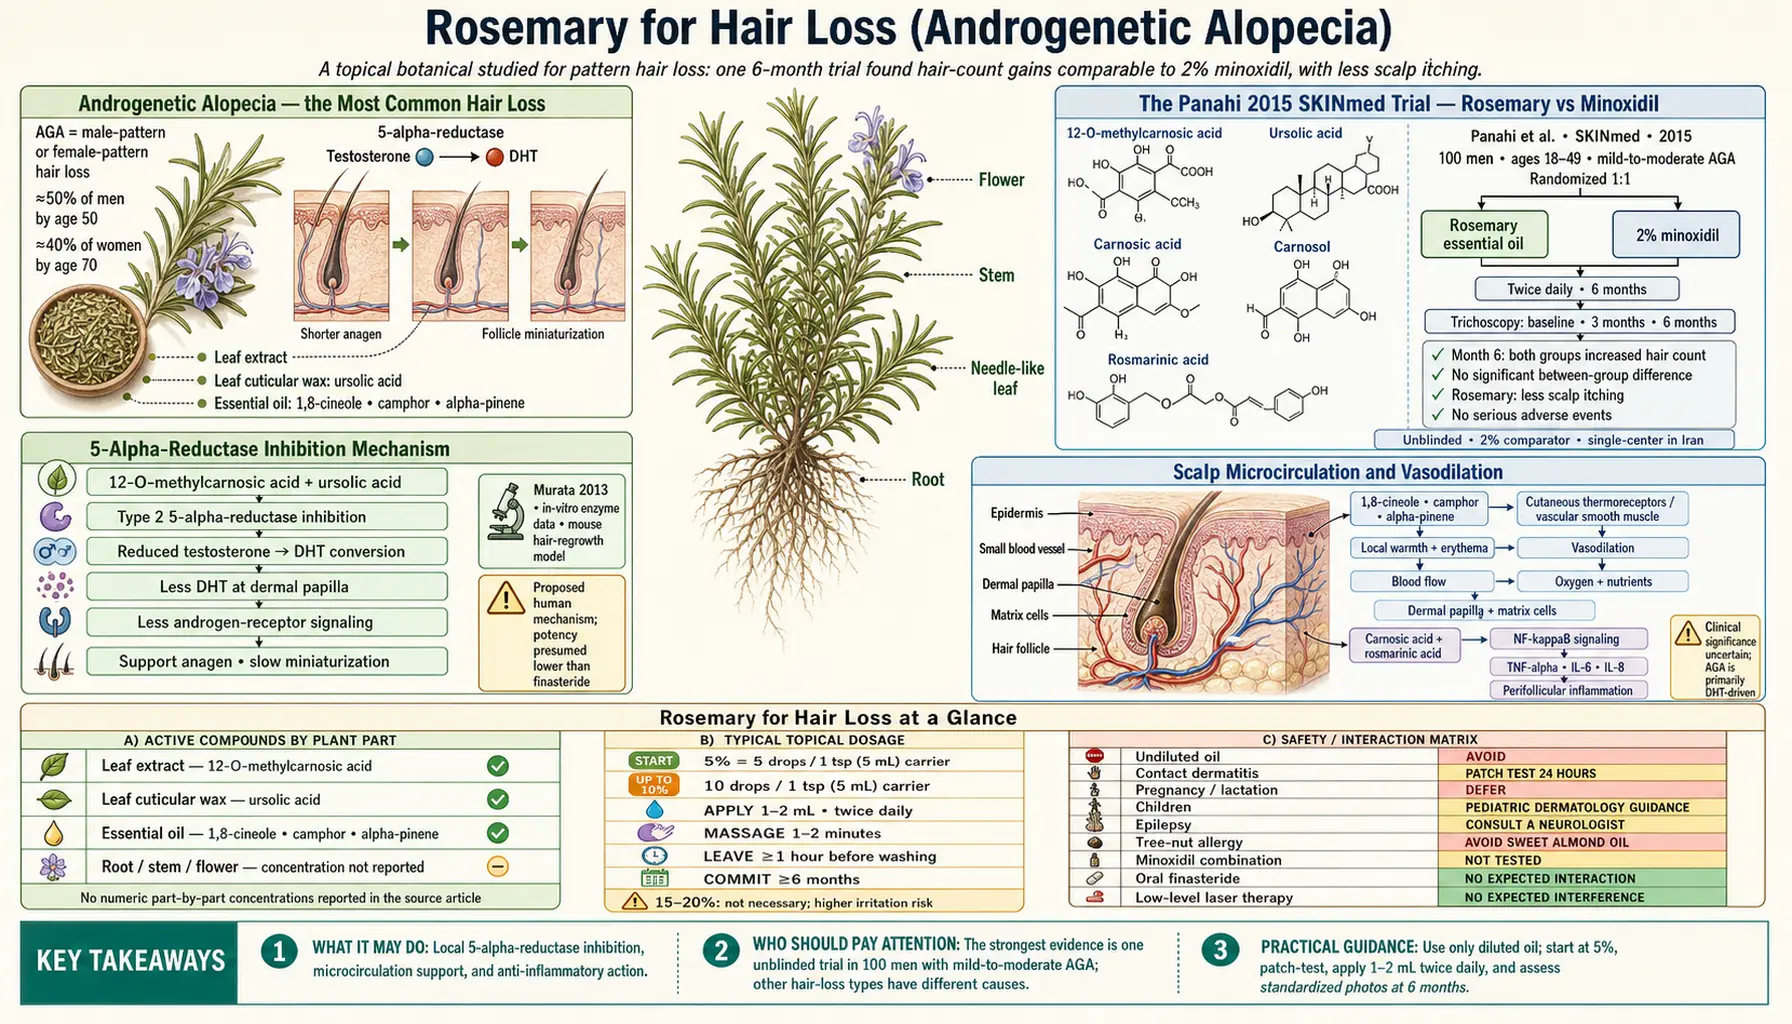
The most-cited clinical trial of any herbal remedy for androgenetic alopecia (pattern hair loss) is the 2015 Panahi study published in SKINmed. One hundred men with mild-to-moderate androgenetic alopecia were randomized to twice-daily topical application of rosemary essential oil (diluted in a carrier oil) or 2% minoxidil (the active ingredient in Rogaine) for six months. Both groups showed comparable, statistically significant increases in hair count from baseline at month 6, with no significant difference between the two treatments. The rosemary group reported less scalp itching as a side effect than the minoxidil group. The proposed mechanism is multifactorial — 5-alpha-reductase inhibition (reducing the conversion of testosterone to the follicle-miniaturizing DHT), improved scalp microcirculation, and anti-inflammatory effects on the perifollicular inflammation that characterizes AGA. This deep-dive walks through the trial in detail, the proposed mechanisms, how the trial's topical protocol is used in practice, and the important limitations.
Interactive Visualization Hair Growth & Loss — shrink a follicle with DHT, or shed on a three-month delay Cycle a scalp of follicles through anagen, catagen and telogen, then miniaturize them with DHT year by year — or dump them all into shedding three months after a stressor. Launch →
Table of Contents
- Androgenetic Alopecia — the Most Common Hair Loss
- The Panahi 2015 SKINmed Trial — Rosemary vs Minoxidil
- 5-Alpha-Reductase Inhibition Mechanism
- Scalp Microcirculation and Vasodilation
- Anti-Inflammatory Effects on the Perifollicular Niche
- Topical Use in Practice
- Carrier Oils and Dilution
- Expectations and Realistic Timeline
- Combination Strategies (Minoxidil, Finasteride, Microneedling)
- Other Hair Loss Types (Alopecia Areata, Telogen Effluvium)
- Cautions and Side Effects
- Key Research Papers
- Connections
- Featured Videos
Androgenetic Alopecia — the Most Common Hair Loss
Androgenetic alopecia (AGA, also called male-pattern or female-pattern hair loss) is the most common form of hair loss in both sexes, affecting roughly 50% of men by age 50 and approximately 40% of women by age 70. It is a polygenic, androgen-driven condition in which scalp hair follicles progressively miniaturize over years to decades, producing the characteristic patterns of temporal and vertex thinning in men and diffuse central thinning with preserved hairline in women.
The pathophysiology is well-mapped:
- Genetically susceptible scalp hair follicles express high levels of 5-alpha-reductase, the enzyme that converts circulating testosterone into dihydrotestosterone (DHT), a more potent androgen
- DHT binds androgen receptors on the dermal papilla cells at the base of each hair follicle, triggering progressive shortening of the anagen (growth) phase and lengthening of the telogen (rest) phase
- With each successive hair cycle, the new hair produced is finer, shorter, and grows for a shorter time — the process called miniaturization
- Eventually the follicle produces only vellus-grade fine hairs or stops producing visible hair entirely
- A low-grade perifollicular inflammation (sometimes called "microinflammation") contributes to the progression and may be the explanation for the modest scalp tenderness many AGA patients report
The current evidence-based pharmacological treatments are:
- Topical minoxidil (2% or 5%) — mechanism not fully understood, but increases scalp microcirculation, prolongs the anagen phase, and may directly stimulate dermal papilla cells. Available over the counter as Rogaine. Effect is partial and requires indefinite use to maintain.
- Oral finasteride (1 mg/day) or oral dutasteride — pharmaceutical 5-alpha-reductase inhibitors; finasteride is U.S. Food and Drug Administration-approved for male AGA, while the dutasteride label lists only benign prostatic hyperplasia. Reduce DHT production and slow progression. Sexual side effects (decreased libido, erectile dysfunction) occur in a small minority of users.
- Topical finasteride — increasingly available off-label, with potentially fewer systemic side effects than oral.
- Low-level laser therapy (LLLT) — U.S. Food and Drug Administration-cleared red-light caps and combs; modest but real efficacy.
- Hair transplantation — surgical relocation of follicles from the genetically resistant occipital scalp to bald areas.
The question rosemary research addresses is whether a botanical preparation can occupy a useful niche alongside or in place of these pharmaceutical and surgical options — particularly for patients who experience or fear side effects of minoxidil or finasteride.
The Panahi 2015 SKINmed Trial — Rosemary vs Minoxidil
The pivotal clinical trial supporting rosemary's use in AGA is Panahi Y, Taghizadeh M, Marzony ET, Sahebkar A. "Rosemary oil vs minoxidil 2% for the treatment of androgenetic alopecia: a randomized comparative trial." SKINmed 2015;13(1):15-21.
Trial design:
- 100 men aged 18-49 years with mild-to-moderate androgenetic alopecia (Norwood-Hamilton II-III/IIIv)
- Randomized 1:1 to twice-daily topical application of rosemary essential oil (diluted, exact formulation specified in the paper) or 2% minoxidil solution
- Treatment duration: 6 months
- Primary outcome: hair count from a standardized professional microphotographic assessment at baseline, 3 months, and 6 months
- Secondary outcomes: patient-reported satisfaction, scalp itching frequency
Results at 6 months:
- Hair count increased significantly from baseline in both groups — with no statistically significant difference between rosemary and minoxidil
- The rosemary group reported significantly less scalp itching than the minoxidil group (one of the common side effects of minoxidil)
- No serious adverse events in either group
- Patient satisfaction was high and comparable between groups
Important methodological caveats:
- The trial was unblinded (the appearance and smell of rosemary oil are distinctive and cannot be plausibly blinded against minoxidil)
- The comparator was 2% minoxidil, which has lower efficacy than the now-standard 5% minoxidil for men. The non-inferiority claim against 5% minoxidil is not directly tested.
- Single-center, single-country (Iran) trial. Replication in other populations would strengthen the evidence base.
- The exact essential oil source, chemotype, and dilution were specified but the protocol has not been widely replicated in subsequent trials with the same precise formulation.
- The "hair count" outcome captures both terminal hair and the conversion of vellus hairs to terminal hairs, but does not directly capture subjective perception of hair density
Despite these caveats, the Panahi trial is the strongest single piece of clinical evidence available for any plant-based topical treatment for AGA, and it has been widely cited in the dermatology and cosmetic literature.
5-Alpha-Reductase Inhibition Mechanism
The most pharmacologically interesting proposed mechanism for rosemary's AGA effect is 5-alpha-reductase inhibition — the same enzyme target as the U.S. Food and Drug Administration-approved oral medications finasteride and dutasteride. Multiple in vitro studies have demonstrated that rosemary extracts and several individual constituents inhibit the enzyme.
The Murata 2013 Phytotherapy Research paper systematically tested rosemary leaf extract and isolated compounds against the type 2 5-alpha-reductase enzyme (the dominant isoform in scalp follicles). Results:
- Rosemary leaf extract inhibited 5-alpha-reductase by 82.4% at 200 µg/mL and 94.6% at 500 µg/mL in a laboratory enzyme assay
- The most potent identified individual constituent was 12-O-methylcarnosic acid, with potency in the range of well-known plant 5-alpha-reductase inhibitors
- Ursolic acid, present in the cuticular wax of rosemary leaves, also showed significant inhibition
- In a parallel mouse model of testosterone-induced hair loss, topical rosemary extract improved hair regrowth comparable to topical finasteride
The translational significance: topical application of a 5-alpha-reductase inhibitor to the scalp produces local DHT suppression at the dermal papilla, without the systemic DHT suppression and associated sexual side effects of oral finasteride. This is the rationale for the recent dermatology interest in compounded topical finasteride preparations. Rosemary essential oil and rosemary leaf extract may achieve a similar local-only DHT-suppressing effect through their natural constituents, although the potency is presumably lower than pharmaceutical finasteride.
Other natural 5-alpha-reductase inhibitors that share this mechanism include saw palmetto (Serenoa repens), pumpkin seed oil, and green tea epigallocatechin gallate (EGCG). There is conceptual interest in combination topical formulations that stack multiple natural 5-alpha-reductase inhibitors for additive effect, although well-controlled trials of such combinations are sparse.
Scalp Microcirculation and Vasodilation
A second proposed mechanism for rosemary's AGA effect parallels the proposed mechanism of minoxidil itself — improvement of scalp microcirculation, increasing blood flow and oxygen and nutrient delivery to the dermal papilla and matrix cells at the base of each hair follicle.
Rosemary essential oil applied topically produces local warmth and erythema (rubefacient effect) similar to the effects of menthol, capsaicin, or methyl salicylate. The vasodilatory effect is mediated by the volatile monoterpenes (1,8-cineole, camphor, alpha-pinene) acting on cutaneous thermoreceptors and possibly directly on vascular smooth muscle.
The clinical significance of improved scalp blood flow for AGA is uncertain. The simple version — "more blood flow means more nutrients to the follicle, therefore better hair growth" — is intuitive but probably too simple. AGA hair follicles are miniaturized despite normal scalp blood flow; the primary problem is DHT-driven follicular signaling, not nutrient delivery. Nonetheless, sustained improvement of scalp circulation may modestly support the metabolically active anagen phase, and may have synergy with the 5-alpha-reductase inhibition above.
An ancillary benefit of the rubefacient effect: it provides a sensible feedback signal that the topical is doing something. Patients can feel the warmth and tingling, which improves adherence to a twice-daily topical regimen that requires sustained compliance to produce results.
Anti-Inflammatory Effects on the Perifollicular Niche
A third mechanism is the broader anti-inflammatory activity of rosemary's phenolic compounds (carnosic acid, carnosol, rosmarinic acid). AGA is associated with a low-grade perifollicular lymphohistiocytic inflammation, sometimes called "microinflammation," that may contribute to the progressive miniaturization process and to the modest scalp tenderness or itching that many AGA patients report.
Topical application of rosemary delivers carnosic acid and rosmarinic acid to the scalp surface, with some penetration into the upper dermis. These compounds suppress NF-kappaB signaling and reduce the local production of pro-inflammatory cytokines (tumor necrosis factor-alpha, interleukin-6, IL-8). In principle, dampening the perifollicular inflammation would reduce one of the drivers of progression and may improve the local environment for hair regrowth.
The anti-inflammatory effect may also explain the less itching observation from the Panahi trial — rosemary actively suppresses scalp inflammation while minoxidil, particularly the propylene-glycol-vehicle formulations, can provoke contact dermatitis and scalp irritation in a significant minority of users.
Topical Use in Practice
How the Panahi protocol is commonly translated into at-home use:
- The oil — at-home use starts from 100% pure Rosmarinus officinalis essential oil; a supplier's Certificate of Analysis shows the chemotype and 1,8-cineole content. Cost is typically $10-25 for a 15 mL bottle.
- Dilution in a carrier oil — the essential oil is mixed at 5-10% concentration in a carrier oil (jojoba, coconut, argan, or pure castor oil). 5% is about 5 drops of rosemary essential oil per 1 teaspoon (5 mL) of carrier oil; 10% is about 10 drops per teaspoon. A 2-4 week supply is usually pre-mixed in a small dropper bottle and kept at room temperature away from light.
- Twice-daily application — as in the trial, typically 1-2 mL massaged into the affected scalp areas morning and evening, worked in with the fingertips for 1-2 minutes. The brief massage itself may have a small mechanical effect on circulation.
- Contact time — the active compounds need time to penetrate, so the oil is usually left on for at least 1 hour before any same-day hair wash. Many protocols leave the oil on overnight after evening application.
- Duration of at least 6 months — the Panahi trial showed effects at 6 months, with minimal effect visible before 3 months. Hair growth is intrinsically slow (about 0.5 inch/month in active follicles) and even effective treatments require months to produce visible changes.
- Standardized photo monitoring — the trial assessed hair from standardized photographs at baseline, 3 months, and 6 months; consistent photos under matched lighting and hair-styling conditions serve the same purpose at home. Subjective day-to-day assessment in the bathroom mirror is unreliable for tracking subtle hair density changes.
Commercial rosemary-based hair oils are an alternative that handles the dilution and packaging; several skincare makers sell pre-diluted rosemary scalp oils. How much rosemary oil a product contains shows in its ingredient list — listed prominently, or at the end after numerous filler ingredients.
Carrier Oils and Dilution
The choice of carrier oil is not pharmacologically irrelevant — different carrier oils have different penetration characteristics, contribute their own scalp effects, and combine with rosemary essential oil to produce different overall properties.
- Jojoba oil — technically a liquid wax with a structure similar to human sebum. Penetrates well, does not clog pores, neutral effects on the hair shaft. Good general-purpose carrier for scalp applications.
- Fractionated coconut oil — medium-chain triglycerides, light, non-greasy, penetrates well. Solid (whole) coconut oil is too heavy and difficult to wash out; fractionated is the more practical form.
- Argan oil — rich in oleic acid, linoleic acid, and vitamin E. Adds its own scalp-conditioning effect. Popular choice in commercial hair-oil formulations.
- Pure castor oil — very heavy and viscous; some traditional protocols use it for scalp applications under the theory that the slow penetration provides prolonged exposure. Difficult to wash out; more often used as a small fraction (10-20%) of a mixed carrier than as a sole carrier.
- Sweet almond oil — light, well-tolerated, good general-purpose carrier. It comes from a tree nut, which raises a concern for people with tree-nut allergy.
- Avocado oil — rich in monounsaturated fats and vitamin E; penetrates well. Slightly heavy texture.
What is known about dilution:
- Undiluted rosemary essential oil on the scalp is too concentrated — it produces irritation and possible sensitization over time
- 5% concentration in carrier (5 drops per teaspoon) is the commonly described starting concentration; many users tolerate 10% without irritation
- Higher concentrations (15-20%) are not pharmacologically necessary and increase the risk of contact dermatitis and sensitization
- When scalp irritation develops, the usual responses are a lower concentration, a different carrier oil, or a 1-2 week break
Expectations and Realistic Timeline
Setting realistic expectations is important — AGA is a chronic progressive condition, and even the most effective treatments produce modest cosmetic improvement rather than dramatic restoration. Honest framing:
- Months 0-2 — no visible change. Some users notice reduced scalp itching (if it was present at baseline) and reduced rate of hairs lost to brushing/showering. This is normal and reflects stabilization rather than regrowth.
- Months 2-3 — some users notice "baby hairs" appearing at hairline or thinning areas. These are vellus-grade fine hairs that may or may not progress to terminal hairs.
- Months 3-4 — some shedding of telogen hairs as the treatment shifts follicles into a new growth cycle. This is the "shedding phase" and is a generally favorable sign rather than a treatment failure (the lost hairs are being pushed out by new hairs growing in beneath).
- Months 4-6 — visible change in hair density may become detectable in photographs at standardized lighting conditions. The Panahi trial demonstrated statistically significant hair count increases by month 6.
- Months 6-12 — continued slow improvement plateau in most users. The benefit, like the benefit of minoxidil and finasteride, is dependent on continued use — stopping treatment reverts hair density to the pre-treatment baseline over 6-12 months.
Important: even the most effective AGA treatments cannot regrow hair from completely scarred or absent follicles. The treatment goal is preservation and modest improvement of follicles that are miniaturized but still alive. For very advanced AGA (Norwood-Hamilton V-VII in men, severe central scalp baldness in women), where cosmetic restoration of bald areas is the goal, hair transplantation is the option a dermatologist would discuss.
Combination Strategies (Minoxidil, Finasteride, Microneedling)
Most dermatology AGA experts consider combination therapy more effective than any single modality. Rosemary fits naturally into several combination protocols:
- Rosemary oil + topical minoxidil — combination users typically apply the rosemary oil in the morning and the minoxidil in the evening, at opposite ends of the day, so each absorbs without interference. The Panahi trial did not test the combination, but mechanistically they are complementary rather than competing.
- Rosemary oil + oral finasteride — no pharmacological interaction is expected when men taking finasteride add rosemary oil as topical support. The topical 5-alpha-reductase inhibition by rosemary acts locally on scalp follicles; the oral finasteride produces systemic DHT reduction.
- Rosemary oil + microneedling (dermarolling) — periodic gentle microneedling of the scalp (typically 0.5-1.5 mm needles, weekly to biweekly) can improve absorption of topical products and may have its own modest hair-stimulatory effect by triggering local wound-healing growth factors. Some protocols apply rosemary oil immediately after a microneedling session for enhanced penetration.
- Rosemary oil + low-level laser therapy — LLLT caps (U.S. Food and Drug Administration-cleared red-light therapy devices) can be used in parallel with topical rosemary. The mechanisms are distinct and there is no expected interference.
- Rosemary oil + nutritional support — iron, vitamin D, zinc, and biotin status are often checked alongside, particularly in women with AGA where iron deficiency is a common contributor. See the hair loss page for the nutritional workup.
An example of how these options are combined: rosemary oil at 5% in jojoba carrier twice daily, 5% minoxidil once daily, weekly 0.5 mm microneedling, and a comprehensive iron and vitamin D panel to look for any nutritional contributor, with oral finasteride as a later step discussed with a dermatologist if the response after 6-12 months is inadequate.
Other Hair Loss Types (Alopecia Areata, Telogen Effluvium)
Most of the rosemary clinical evidence is specific to androgenetic alopecia. Other forms of hair loss have different pathophysiology and the same treatment may not apply.
- Alopecia areata — an autoimmune attack on hair follicles producing patchy or total hair loss, unrelated to androgens. The 1998 Hay/Jamieson Archives of Dermatology aromatherapy trial (rosemary, thyme, lavender, cedarwood essential oils in a mixed carrier) showed efficacy versus placebo carrier oil for alopecia areata at 7 months. This is a separate evidence base from AGA. The new JAK inhibitors (baricitinib, ritlecitinib, deuruxolitinib) are the current U.S. Food and Drug Administration-approved treatments. See the Alopecia page for the broader treatment landscape.
- Telogen effluvium — sudden diffuse hair shedding triggered by stress, illness, postpartum hormone shifts, thyroid dysfunction, severe iron deficiency, or major nutritional inadequacy. Resolves with treatment of the trigger; rosemary oil is not a primary intervention. Once the root cause is addressed (typically identified through thyroid, iron, ferritin, and stress workup), hair regrows spontaneously over 3-6 months.
- Frontal fibrosing alopecia — a scarring alopecia primarily in postmenopausal women, with progressive hairline recession and loss of eyebrows. Inflammatory rather than androgenic; treated with topical steroids, oral hydroxychloroquine, or low-dose oral minoxidil. Topical rosemary is not specifically evidence-based here.
- Scarring (cicatricial) alopecias — permanent destruction of follicles from inflammatory or infectious causes. Topical treatments cannot regrow hair from destroyed follicles.
Cautions and Side Effects
- Contact dermatitis — the most common side effect. A patch test — a small dilution on the forearm 24 hours before the first scalp application — is the usual check. Rash, itching, or burning are the signs; a lower concentration or a different carrier oil are the usual responses.
- Sensitization with prolonged use — like many essential oils, rosemary can produce delayed-onset sensitization over months to years of consistent use. When a previously-tolerated regimen suddenly produces irritation, a 2-4 week break or a switch to a different botanical regimen are the usual responses.
- Photosensitivity — rosemary essential oil is not strongly photosensitizing, and the scalp is rarely exposed to direct sun; night-time application or hair coverage limits what exposure there is.
- Pregnancy and lactation — there is no good safety data on medicinal-strength topical essential oil applications in pregnancy or lactation. Mild scalp use is unlikely to produce harm, but no formal safety studies exist.
- Eye irritation — rosemary oil in the eyes produces stinging and tearing; oil left on the hands after scalp application is the usual route.
- Children — the safety of topical essential oil use in children is not established, which makes it a question for a pediatric dermatologist.
- Epilepsy — concentrated essential oil exposure can lower seizure threshold in susceptible individuals. The concern applies to people with a personal or family history of seizure disorder, for whom concentrated topical rosemary essential oil is a question for a neurologist.
- Hair color and texture — rosemary oil does not chemically alter hair color, but the natural pigments in the oil can leave a slight warm tint on very pale blond or white hair with repeated heavy application.
Key Research Papers
- Panahi Y, Taghizadeh M, Marzony ET, Sahebkar A (2015). Rosemary oil vs minoxidil 2% for the treatment of androgenetic alopecia: a randomized comparative trial. SKINmed. — PubMed PMID: 25842469
- Murata K, Noguchi K, Kondo M, Onishi M, Watanabe N et al. (2013). Promotion of hair growth by Rosmarinus officinalis leaf extract. Phytotherapy Research. — PubMed PMID: 22517595
- Hay IC, Jamieson M, Ormerod AD (1998). Randomized trial of aromatherapy. Successful treatment for alopecia areata. Archives of Dermatology. — PubMed
- Begum A, Sandhya S, Shaffath Ali S, Vinod KR, Reddy S, Banji D (2013). An in-depth review on the medicinal flora Rosmarinus officinalis (Lamiaceae). Acta Scientiarum Polonorum Technologia Alimentaria 12(1):61-73. — PubMed PMID: 24584866
- Rastegar H, Ahmadi Ashtiani H, Aghaei M, Ehsani A, Barikbin B (2013). Combination of herbal extracts and platelet-rich plasma induced dermal papilla cell proliferation: involvement of ERK and Akt pathways. Journal of Cosmetic Dermatology 12(2):116-22. — PubMed PMID: 23725305
- Ezekwe N, King M, Hollinger JC (2020). The use of natural ingredients in the treatment of alopecias. Journal of Clinical and Aesthetic Dermatology. — PubMed PMID: 33178378
- Lourith N, Kanlayavattanakul M (2013). Hair loss and herbs for treatment. Journal of Cosmetic Dermatology. — PubMed PMID: 23992163
- Trüeb RM (2006). Pharmacologic interventions in aging hair. Clinical Interventions in Aging 1(2):121-9. — PubMed PMID: 18044109
- Pekmezci E, Turkoglu M (2017). Minoxidil acts as an antiandrogen: a study of 5-alpha-reductase type 2 gene expression in a human keratinocyte cell line. Acta Dermatovenerologica Croatica. — PubMed PMID: 30064598
PubMed Topic Searches
Connections
- All Herbs
- Hair Growth, Thinning & Why Hair Falls Out — interactive animation
- Rosemary Overview
- Rosemary Benefits Hub
- Rosemary for Cognitive Function
- Rosemary for Antioxidant & Anti-Aging
- Rosemary for Digestive & Liver
- Hair Loss (Symptom Overview)
- Alopecia
- Saw Palmetto (DHT Inhibitor)
- Lavender (Hair Trial Companion)
- Thyme
- Biotin
- Vitamin D3
- Iron (Ferritin)
- Zinc
- History