⚠ Evidence warning: Clinical trials or other evidence do not support the claim that rosemary tea relieves gas, bloating and after-meal fullness and stimulates bile flow in people. This page keeps it as a report of what people, websites or other media say.
Rosemary for Digestive and Liver Function
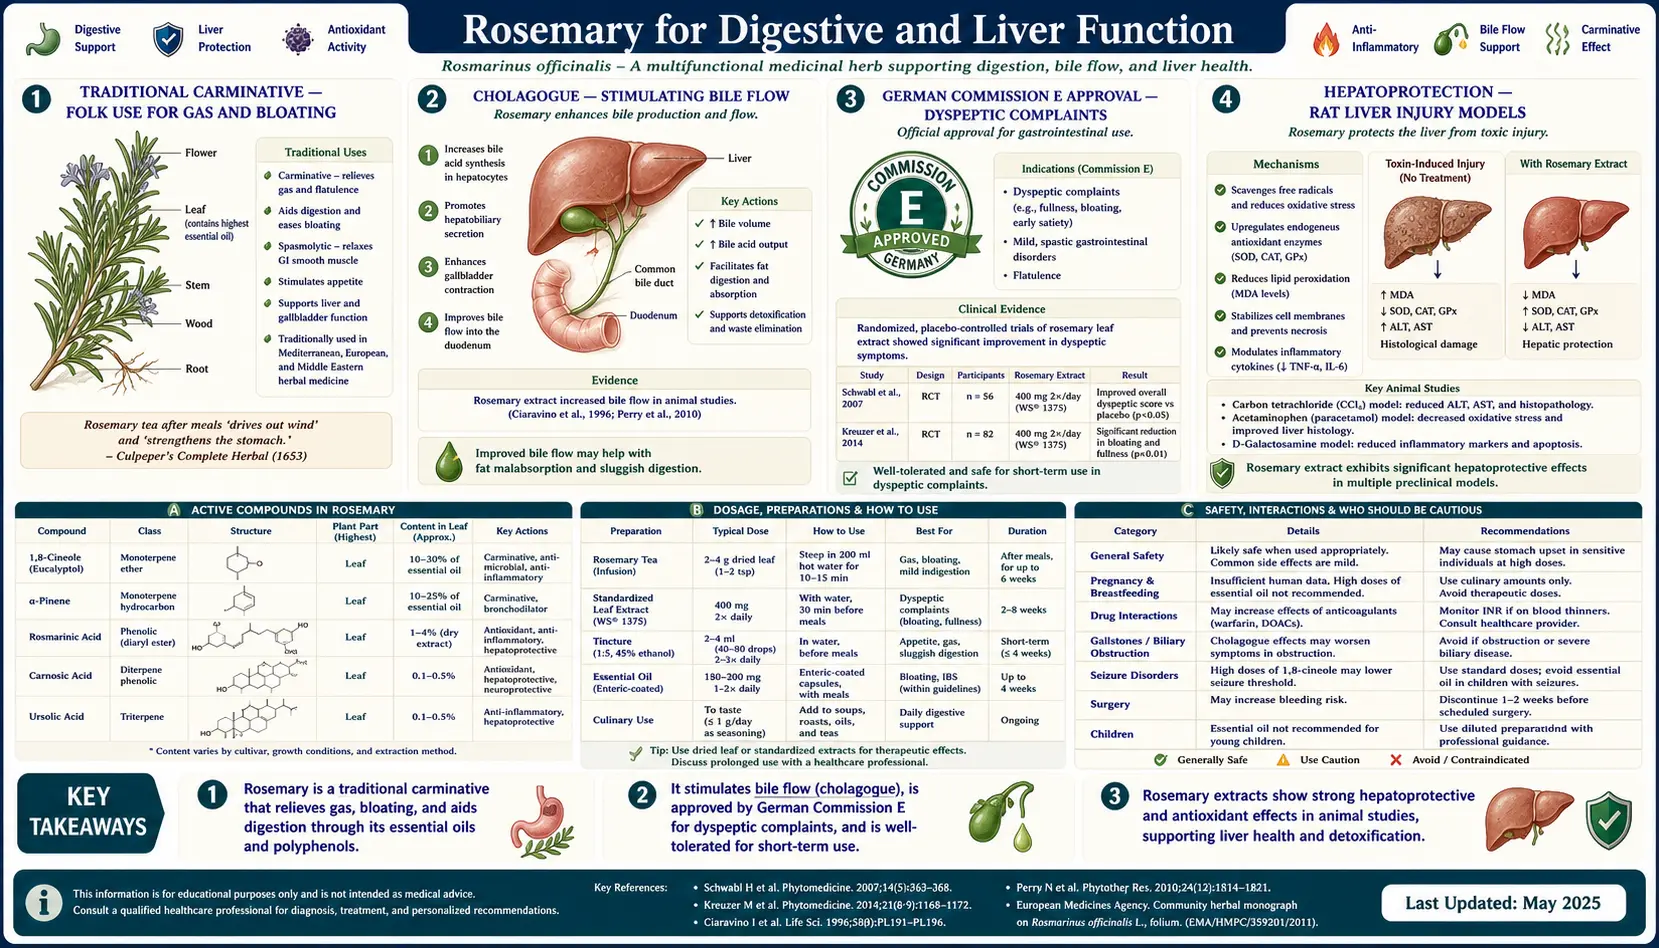
Rosemary's traditional use as a digestive remedy is older than the Renaissance herbals and is one of the few herb-and-spice applications formally codified by the German Commission E, the historical regulatory authority on European phytomedicine. Commission E approved rosemary leaf for "dyspeptic complaints" — gas, bloating, mild gastrointestinal cramping, and the sluggish digestion that follows a heavy meal. The traditional mechanism categories are carminative (relieving gas, mediated by the volatile monoterpenes 1,8-cineole and alpha-pinene relaxing intestinal smooth muscle) and cholagogue (stimulating bile flow from the gallbladder, mediated by the bitter principles and phenolic diterpenes acting on the duodenal mucosa). A separate and increasingly well-documented effect is hepatoprotection — rat models of liver injury induced by carbon tetrachloride, acetaminophen overdose, and chronic ethanol have shown reduced hepatocellular damage when carnosic acid, carnosol, or whole rosemary extract is administered before or during the toxin exposure. The mechanism is the same Nrf2 / antioxidant chemistry covered on the antioxidant page, applied to the specific oxidative-stress vulnerability of the liver. This deep-dive walks through the traditional uses, the Commission E approval, the hepatoprotective animal evidence, the COX-inhibition contribution to anti-inflammatory action in the gut, and the important cautions around essential oil dosing.
Table of Contents
- Traditional Carminative — the Folk Use for Gas and Bloating
- Cholagogue — Stimulating Bile Flow
- German Commission E Approval — Dyspeptic Complaints
- Hepatoprotection — the Rat Liver Injury Models
- Carbon Tetrachloride (CCl4) Hepatotoxicity
- Acetaminophen (Paracetamol) Hepatotoxicity
- Chronic Ethanol Liver Injury
- Cyclooxygenase-1 and Cyclooxygenase-2 Inhibition — Anti-Inflammatory Mechanism
- Effects on the Gut Microbiome
- Non-Alcoholic Fatty Liver Disease — Mechanistic Relevance
- How Rosemary Is Prepared for Digestion
- Essential Oil Cautions — the Oral Hazard
- Key Research Papers
- Connections
- Featured Videos
Traditional Carminative — the Folk Use for Gas and Bloating
A carminative in traditional Western herbalism is an herb that relieves intestinal gas, bloating, and the mild crampy abdominal discomfort that often accompanies heavy or rich meals. The classical carminatives include fennel, anise, caraway, dill, peppermint, ginger, and rosemary — all of them rich in volatile aromatic compounds that have direct relaxing effects on intestinal smooth muscle.
The traditional use of rosemary as a post-meal digestive aid is documented across the Mediterranean culinary tradition. Roasted meat with rosemary (still a defining preparation of Italian and Provencal cooking) is not merely a flavor pairing — the herb actively helps the digestion of the fat-rich meal it garnishes. Sprigs of fresh rosemary floated in olive oil or in red wine vinegar produce digestive tonics that have been part of European folk medicine for centuries.
The pharmacological basis of the carminative effect is well-characterized:
- 1,8-cineole and alpha-pinene in the volatile fraction relax intestinal smooth muscle through a mechanism that includes calcium-channel inhibition and direct effects on muscarinic acetylcholine receptors
- Borneol and camphor have similar antispasmodic activity
- The relaxation of smooth muscle helps expel trapped intestinal gas and reduces the crampy "spasm" that contributes to functional dyspepsia
- The aromatic volatiles also stimulate salivary and gastric secretion, supporting the upstream stages of digestion
In people's descriptions, a cup of rosemary tea taken after a rich meal often produces noticeable belching and gas release within 10-20 minutes, accompanied by relief of post-prandial fullness. The same effect is what makes a digestif of grappa or amaro (often containing carminative herbs including rosemary) traditional in Italian cuisine.
Cholagogue — Stimulating Bile Flow
A cholagogue is an herb that stimulates the contraction of the gallbladder and the release of stored bile into the duodenum, accelerating the digestion of dietary fats. Bile contains bile salts (which emulsify dietary lipids and form mixed micelles with cholesterol and fat-soluble vitamins), phospholipids, cholesterol, and bilirubin. Inadequate bile flow contributes to fat maldigestion (steatorrhea, oily stools), fat-soluble vitamin malabsorption, and the bloating and discomfort associated with heavy fatty meals.
Cholagogue action by rosemary is mediated primarily by the bitter principles — the phenolic diterpenes (carnosic acid, carnosol) and the small amount of bitter components in the leaf. When these compounds contact the bitter taste receptors on the tongue and the small intestinal mucosa, they trigger a vagal reflex that stimulates gallbladder contraction and bile release. This is the same mechanism behind the European tradition of taking a bitter digestif before or after a meal — the bitter taste itself, even before absorption, activates the digestive cascade.
Cholagogue effects reported for rosemary, in rat studies and in herbal tradition:
- Increased bile flow (choleretic activity) in rats given ethanol extracts of rosemary — dose-related, and stronger for extracts of young sprouts than of the whole plant (Hoefler and colleagues, 1987)
- Faster gallbladder contraction with bitter herb mixtures containing rosemary — described in herbal tradition and practice
- Less upper-abdominal fullness after fatty meals in people with functional dyspepsia taking rosemary leaf preparations — described in herbal tradition and practice
The clinical relevance is concentrated in patients with mild functional dyspepsia, post-cholecystectomy syndrome (after gallbladder removal, when bile delivery becomes continuous-low-flow rather than meal-stimulated bolus), and the slowed digestion of aging or chronic illness. For people with documented bile flow obstruction (gallstones, biliary stricture), herbal practice generally withholds cholagogue herbs, because increasing bile flow against a partial obstruction can precipitate biliary colic. The European Medicines Agency's public summary for rosemary leaf likewise lists obstruction of the bile duct, inflammation of the gallbladder, gallstones and any liver disease as conditions in which rosemary leaf medicines are not used.
German Commission E Approval — Dyspeptic Complaints
The German Commission E was a multidisciplinary regulatory body established by the German Federal Institute for Drugs and Medical Devices in 1978 to evaluate the safety and efficacy of botanical medicines used in Germany. From 1978 to 1994 Commission E reviewed approximately 380 herbs and published monographs categorizing each as Approved (safety and efficacy documented), Unapproved (insufficient evidence or known safety concerns), or Neutral. The Commission E monographs remain influential in the European Medicines Agency's current herbal monograph system and in international phytomedicine practice.
Commission E approved rosemary leaf for the following internal uses:
- Dyspeptic complaints — gas, bloating, mild epigastric discomfort, sluggish digestion
- Average daily dose: 4-6 g of dried leaf, equivalent to a strong infusion two to three times daily
- Contraindications: pregnancy (medicinal doses)
And approved rosemary oil for the following uses (external only):
- Supportive therapy for rheumatic complaints — topical application as part of liniments and topical preparations
- Circulatory problems — external use to improve peripheral circulation
The European Medicines Agency (EMA) herbal committee assessed Rosmarini folium (rosemary leaf) together with Rosmarini aetheroleum (rosemary essential oil). Its first Community herbal monograph on rosemary leaf was adopted in 2010 and has since been superseded: a revised EU herbal monograph (Revision 1) went to public consultation from December 2022 to March 2023, and the committee's final opinion on it was published on 26 September 2024. The EMA lists rosemary leaf, sold as a herbal tea to drink and as a bath additive, for traditional use in the symptomatic relief of dyspepsia and mild spasmodic disorders of the gastrointestinal tract (indigestion and mild gut cramps), and, as a bath additive, for minor muscle and joint pain and minor peripheral circulation complaints. “Traditional use” in EMA terms means the use rests on long-standing medicinal use, not on results from clinical studies. The EMA monographs are the current regulatory standard in the EU for rosemary preparations (EMA: Rosmarini folium).
Importantly, neither Commission E nor the European Medicines Agency approves oral consumption of rosemary essential oil. The essential oil is approved only for external use (topical or aromatherapy). The dried leaf and tea preparations are the approved internal forms. See the Essential Oil Cautions section below for the safety rationale.
Hepatoprotection — the Rat Liver Injury Models
A separate and increasingly well-documented effect of rosemary is hepatoprotection — protection of the liver against drug- and toxin-induced injury. The evidence base is primarily in rat models because the experimental induction of severe liver injury is unethical in humans, but the mechanistic story translates plausibly through shared mammalian biochemistry.
The standard rat liver injury models in which rosemary has been tested:
- Carbon tetrachloride (CCl4) — the classic experimental hepatotoxin, metabolized by cytochrome P450 2E1 (CYP2E1) to trichloromethyl radicals that drive massive lipid peroxidation and centrilobular hepatocyte necrosis
- Acetaminophen (paracetamol) — overdose model relevant to one of the most common causes of acute liver failure in humans; toxicity mediated by the reactive metabolite NAPQI
- Chronic ethanol — model of alcoholic fatty liver disease and progression to steatohepatitis
- Thioacetamide — alternative hepatotoxin producing centrilobular necrosis
- Galactosamine — model resembling viral hepatitis in its periportal necrosis pattern
- Cadmium and other heavy metals — cumulative hepatotoxin models
In these models, rosemary extract, carnosic acid, carnosol, or rosmarinic acid given before or alongside the toxin has been reported to reduce some of the following — though not in every study or with every preparation (see the limits below the list):
- Serum aspartate aminotransferase (AST) and alanine aminotransferase (ALT) (transaminases) elevations — the standard clinical markers of hepatocellular injury
- Hepatocellular necrosis on histology
- Hepatic lipid peroxidation markers (malondialdehyde, 4-hydroxynonenal)
- Hepatic glutathione depletion (the toxin-driven exhaustion of the liver's primary antioxidant defense)
- Inflammatory cytokine elevations (tumor necrosis factor-alpha, interleukin-6, IL-1beta)
The underlying mechanism in every case is the Nrf2-driven upregulation of glutathione synthesis, superoxide dismutase, catalase, and heme oxygenase-1, which collectively raise the liver's antioxidant capacity above what the toxin can overwhelm.
What these rat studies do not show. The protection depends on which part of the plant is used and on timing. In the 1987 rat study by Hoefler and colleagues, water extracts of young rosemary sprouts lowered the liver enzyme GPT (also called ALT) in the blood only when given before carbon tetrachloride poisoning; the extract of the whole plant did nothing, and neither extract helped when given after the poison. All of this work is in animals, at doses given as concentrated extracts.
Carbon Tetrachloride (CCl4) Hepatotoxicity
Carbon tetrachloride is the historical workhorse of experimental hepatotoxicology. It is metabolized in hepatocytes by cytochrome P450 2E1 (CYP2E1) to the highly reactive trichloromethyl free radical, which initiates massive lipid peroxidation of hepatocyte membranes, particularly the endoplasmic reticulum and mitochondrial membranes. The result is acute centrilobular hepatocyte necrosis (because cytochrome P450 2E1 is concentrated in zone 3 hepatocytes near the central vein), elevated transaminases, and at higher doses fulminant hepatic necrosis.
Rosemary CCl4 studies in rats report:
- In a 2002 rat study (Sotelo-Félix and colleagues), rosemary extract at 200 mg/kg a day, started 1 hour after carbon tetrachloride, completely normalized the rise in blood alanine aminotransferase (ALT) and bilirubin, fully prevented liver lipid peroxidation at 24 hours, and partially prevented inflammation, necrosis and vacuolation on histology. In the earlier 1987 rat study (Hoefler and colleagues), protection was seen only with young-sprout extract given before the toxin.
- Pre-treatment reduces histologic necrosis score and preserves more zone 3 hepatocytes
- The protective effect is dose-dependent and saturates at moderate doses
- Co-administration of just carnosic acid or carnosol (the isolated phenolic diterpenes) produces effects comparable to whole extract, confirming these as the principal active compounds
- The protection is mechanistically attributable to Nrf2 activation, glutathione preservation, and direct interception of the trichloromethyl free radical by the lipid-phase antioxidant activity of the diterpenes
The CCl4 model is most relevant clinically as a proof-of-mechanism for general lipid-peroxidation-driven hepatocellular injury. The same mechanism is relevant to many other forms of hepatotoxicity including acetaminophen overdose, severe ischemic injury (e.g., post-liver-transplant reperfusion injury), and toxic mushroom poisoning.
Acetaminophen (Paracetamol) Hepatotoxicity
Acetaminophen overdose is the leading cause of acute liver failure requiring transplantation in the United States and the United Kingdom. The toxicity mechanism is well-understood:
- At therapeutic doses, most acetaminophen is glucuronidated or sulfated to inactive metabolites and renally excreted
- A small fraction is oxidized by cytochrome P450 2E1 to the reactive intermediate N-acetyl-p-benzoquinone imine (NAPQI)
- NAPQI is normally rapidly conjugated and detoxified by hepatocellular glutathione
- At overdose, the glutathione pool is depleted, NAPQI accumulates and covalently binds hepatocyte proteins, producing oxidative stress and centrilobular necrosis
- The clinical antidote, N-acetylcysteine (NAC), provides cysteine for glutathione resynthesis and directly conjugates remaining NAPQI
In a 2023 rat study (Guimarães and colleagues), a rosemary glycolic extract injected into the abdominal cavity (intraperitoneally) for four days prevented liver lipid peroxidation after an acetaminophen overdose and kept blood ALT and AST at the levels of untreated rats. The proposed mechanism overlaps with the N-acetylcysteine mechanism — rosemary's Nrf2 activation upregulates the glutathione synthesis enzymes, increasing the rate at which depleted glutathione pools can be restored. This is a different mechanism than N-acetylcysteine's direct cysteine supplementation, but achieves a complementary endpoint of maintaining or restoring hepatocellular glutathione capacity.
The translational caveat: in clinical acetaminophen overdose, intravenous N-acetylcysteine remains the standard of care, started as soon as possible within the 8-hour optimal window. Rosemary extract is not a substitute for N-acetylcysteine. The conceptual interest is in dietary patterns that maintain robust baseline hepatic antioxidant defenses, potentially providing some protective margin against accidental supratherapeutic acetaminophen exposure and against the cumulative low-grade hepatotoxic stress of polypharmacy.
Chronic Ethanol Liver Injury
Chronic ethanol consumption produces a progression from alcoholic fatty liver (hepatic steatosis) through steatohepatitis to fibrosis and cirrhosis. The pathogenesis involves direct hepatotoxic effects of ethanol and its metabolite acetaldehyde, induction of cytochrome P450 2E1 (which generates reactive oxygen species during ethanol oxidation), depletion of hepatocellular glutathione, mitochondrial dysfunction, and chronic inflammatory activation of Kupffer cells.
Rat models of chronic ethanol-induced liver injury treated with rosemary extract or its carnosic acid have shown:
- Reduced hepatic triglyceride accumulation (less fatty liver)
- Reduced transaminase elevation
- Preserved hepatic glutathione pools
- Reduced inflammatory infiltrate on histology
- Reduced fibrosis progression in longer-duration studies
In one such study (Gao and colleagues, 2016), carnosic acid given to rats fed an ethanol liquid diet lowered blood aminotransferases, triglycerides and total cholesterol, and reduced oxidative stress, inflammation and liver-cell death.
The translational implications are limited. The protective effects in rat models do not constitute permission to consume excessive alcohol — the magnitude of human alcohol consumption that produces clinical alcoholic liver disease is far above what any dietary or supplemental antioxidant could realistically counterbalance. For patients with diagnosed alcoholic liver disease, the primary intervention is reduction or cessation of alcohol consumption; rosemary and other dietary antioxidants are at most an adjunct to it, not a replacement.
For patients with non-alcoholic fatty liver disease (NAFLD), the rosemary mechanism is more directly relevant — see the non-alcoholic fatty liver disease section below.
Cyclooxygenase-1 and Cyclooxygenase-2 Inhibition — Anti-Inflammatory Mechanism
A complementary anti-inflammatory mechanism contributing to rosemary's digestive and broader effects is inhibition of the cyclooxygenase enzymes cyclooxygenase-1 (COX-1) and cyclooxygenase-2 (COX-2), which convert arachidonic acid to prostaglandins and thromboxanes. Cyclooxygenase-1 is constitutively expressed and produces the "housekeeping" prostaglandins that maintain gastric mucosal integrity, platelet aggregation, and renal blood flow. Cyclooxygenase-2 is induced at sites of tissue injury and inflammation, producing the prostaglandins that drive pain, fever, and inflammation.
The non-steroidal anti-inflammatory drug class works primarily by inhibiting COX enzymes. Older nonsteroidal anti-inflammatory drugs (aspirin, ibuprofen, naproxen) inhibit both cyclooxygenase-1 and cyclooxygenase-2; the gastric ulceration side effect is attributable to the cyclooxygenase-1 inhibition that compromises gastric mucosal prostaglandin production. The selective cyclooxygenase-2 inhibitors (celecoxib) were developed to maintain anti-inflammatory efficacy while sparing gastric mucosal prostaglandins.
Rosemary extracts and isolated carnosol and rosmarinic acid have been shown to inhibit both cyclooxygenase-1 and cyclooxygenase-2 in vitro, with somewhat greater selectivity for cyclooxygenase-2 in some preparations. The clinical significance:
- Contributes to the anti-inflammatory and modest analgesic effects of rosemary preparations
- Likely contributes to the digestive benefit by reducing the inflammatory component of functional dyspepsia and irritable bowel syndrome (IBS)
- Theoretical platelet aggregation effect (cyclooxygenase-1 inhibition reduces thromboxane A2 production) — relevant to the cautions for patients on antiplatelet drugs
- Contributes to the rationale for topical rosemary preparations in rheumatic complaints (the Commission E external-use indication)
The potency of rosemary as a COX inhibitor is far lower than pharmaceutical nonsteroidal anti-inflammatory drugs (NSAIDs) — routine culinary use is unlikely to produce clinically significant effects equivalent to ibuprofen. High-dose extract use approaches a magnitude that could theoretically produce additive effects with low-dose aspirin or other antiplatelet drugs.
Effects on the Gut Microbiome
Rosemary essential oil, rosemary extracts, and isolated carnosic acid have direct antimicrobial activity against a range of bacterial and fungal species, including several human gut pathogens. This is one of the historical reasons rosemary was burned as a fumigant in medieval European sickrooms and used as a preservative for stored meat in pre-refrigeration cuisine.
Documented in vitro antimicrobial activity:
- Gram-positive bacteria — Staphylococcus aureus (including methicillin-resistant Staphylococcus aureus (MRSA) strains), Bacillus subtilis, Listeria monocytogenes
- Gram-negative bacteria — Escherichia coli, Salmonella, Helicobacter pylori
- Fungi — Candida albicans, Aspergillus species
- Biofilm disruption — rosemary essential oil and carvacrol-rich essential oils disrupt established bacterial biofilms in vitro
The translational significance for human gut health is moderate. The doses of rosemary consumed in cooking or in moderate tea use are unlikely to produce significant antimicrobial effects in the intact gut lumen. However, several clinical implications follow from the in vitro evidence:
- Rosemary's historical role as a food preservative was partly antimicrobial — reducing the bacterial spoilage of stored meat
- Anti-Helicobacter pylori activity has been studied as an adjunct in eradication regimens, although triple-therapy antibiotics remain the standard of care
- For patients with small intestinal bacterial overgrowth (SIBO), the combination of rosemary with other antimicrobial herbs (oregano, thyme, berberine) may contribute to herbal antimicrobial protocols, although evidence for the specific herbal contribution versus pharmaceutical antibiotics is limited
- Routine culinary use of rosemary is unlikely to produce gut microbiome dysbiosis — the antimicrobial effects at dietary doses appear to be modest and largely confined to opportunistic pathogen suppression rather than commensal disruption
Non-Alcoholic Fatty Liver Disease — Mechanistic Relevance
Non-alcoholic fatty liver disease (NAFLD) is now the most common chronic liver disease in the developed world, affecting an estimated 25-40% of adults. The pathogenesis involves hepatic insulin resistance, accumulation of triglycerides in hepatocytes, secondary oxidative stress and inflammation that can progress to non-alcoholic steatohepatitis (NASH), and eventually fibrosis and cirrhosis in a subset.
The mechanistic connections between rosemary's biology and non-alcoholic fatty liver disease pathophysiology:
- PPAR-gamma activation by carnosic acid — improves hepatic insulin sensitivity, reducing the primary driver of triglyceride accumulation
- AMP-activated protein kinase (AMPK) activation by carnosic acid and rosmarinic acid — promotes fatty acid oxidation and inhibits fatty acid synthesis, reducing hepatic triglyceride accumulation
- Nrf2 activation — counters the secondary oxidative stress that drives the progression from simple steatosis to steatohepatitis
- NF-kappaB inhibition — suppresses the inflammatory activation of Kupffer cells that drives steatohepatitis
- Effects on the gut microbiome and gut-liver axis — reduced bacterial translocation and lipopolysaccharide (LPS) delivery to the portal venous system, reducing inflammatory drive on the liver
A 2022 randomized, double-blind trial tested rosemary in people. 110 people with non-alcoholic fatty liver disease took 4 g of rosemary leaf powder or a starch placebo powder daily for 8 weeks, and everyone also received a weight-loss diet and physical-activity advice. Liver enzymes (ALT, AST, alkaline phosphatase and GGT), fasting blood sugar and insulin, insulin resistance, total and LDL cholesterol, triglycerides, weight, body mass index and waist size all fell in both groups, but the rosemary group did no better than the placebo group on any of them except one index of insulin-producing (beta-cell) function. The authors concluded that the changes in the rosemary group were not statistically different from those produced by the diet and activity programme alone. The strongest current evidence base for non-alcoholic fatty liver disease lifestyle intervention remains weight loss (5-10% body weight reduction reliably reverses steatosis in most patients) and the Mediterranean diet pattern (which includes regular rosemary use as one of many beneficial elements).
Rosemary and other Mediterranean herbs are a regular part of the Mediterranean diet pattern. As a supplement on top of weight loss, diet change and activity, rosemary leaf powder added nothing measurable over 8 weeks in the 2022 trial.
How Rosemary Is Prepared for Digestion
The preparations used in herbal tradition and practice for digestion:
- Rosemary tea — the standard preparation. The usual method is 1-2 teaspoons of dried rosemary leaf (or 1 tablespoon fresh chopped leaf) steeped in 8-10 oz of just-boiled water for 8-10 minutes, covered to retain the volatile fraction, with one cup drunk 15-30 minutes after a heavy meal; herbal practice describes 2-3 cups daily as well tolerated.
- Culinary use — rosemary is cooked routinely with fatty meals (roast meats, oily fish, hearty stews) and is traditionally credited with a modest digestive benefit. Cooks add it early for full flavor development; the volatile carminative fraction degrades with prolonged heat, which is why some also finish a dish with a small amount of fresh herb near the end of cooking.
- Bitter tincture — commercial digestive bitter formulas often contain rosemary along with gentian, dandelion, fennel, and other carminatives. Herbal practice uses 1-2 mL in a small amount of water 15 minutes before a meal, on the reasoning that the bitter taste triggers the upper-digestive cascade through the bitter taste receptor pathway.
- Standardized leaf extract capsules — 200-400 mg/day of standardized rosemary leaf extract is in the range used in clinical trials for general antioxidant and metabolic effects. Most users do not find capsules necessary if they routinely consume rosemary in cooking and tea.
- The essential oil is not an oral digestive — see the next section. Rosemary essential oil is not a safe replacement for rosemary leaf for oral digestive use.
Combination with other carminative herbs (peppermint, fennel, chamomile, ginger, lemon balm) is traditional and pharmacologically sensible — the carminative effects of different aromatic herbs often appear additive without dosage-dependent toxicity. A traditional after-dinner blend uses equal parts rosemary, peppermint, and fennel as a digestive infusion.
Essential Oil Cautions — the Oral Hazard
The single most important safety point about rosemary essential oil is that it is not safe for oral consumption at meaningful doses. The essential oil is far more concentrated than the dried leaf or any culinary preparation, and the volatile monoterpenes (camphor, 1,8-cineole) that produce the cognitive effects when inhaled can produce serious adverse effects when swallowed.
Documented toxicity from oral rosemary essential oil ingestion:
- Acute gastrointestinal toxicity — severe nausea, vomiting, gastrointestinal irritation, mucosal damage
- Hepatotoxicity — paradoxically, the same compounds that are hepatoprotective at low dietary doses can be hepatotoxic at concentrated essential oil doses
- Renal toxicity — nephrotoxic at supratherapeutic doses
- Central nervous system (CNS) toxicity — central nervous system depression, seizures (camphor is a well-known seizure-precipitating compound at high doses)
- Pregnancy harm — oral essential oil doses are abortifacient in animal models
The fundamental safety principle: the dose makes the poison. A teaspoon of dried rosemary leaf in tea is safe and beneficial. A teaspoon of pure rosemary essential oil is a medical emergency. The 100-200x concentration difference between dried herb and essential oil is the critical safety boundary.
Approved internal use of rosemary remains the dried leaf, the leaf tea, the standardized leaf extract (not essential oil), and modest culinary use. Approved external use of the essential oil includes aromatherapy (the inhalation cognitive use covered on the cognitive page) and topical use diluted in carrier oil (the hair-loss use covered on the hair loss page).
For accidental essential oil ingestion: contact Poison Control immediately (1-800-222-1222 in the US). Do not induce vomiting (caustic essential oils may produce additional esophageal damage on emesis). Provide supportive care including airway management, hydration, and treatment of specific toxicities.
Key Research Papers
- Hoefler C et al. (1987). Comparative choleretic and hepatoprotective properties of young sprouts and total plant extracts of Rosmarinus officinalis in rats. Journal of Ethnopharmacology 19(2):133-43. — PubMed PMID: 3613606
- Sotelo-Félix JI et al. (2002). Evaluation of the effectiveness of Rosmarinus officinalis (Lamiaceae) in the alleviation of carbon tetrachloride-induced acute hepatotoxicity in the rat. Journal of Ethnopharmacology 81(2):145-54. — PubMed PMID: 12065145
- Guimarães NSS et al. (2023). Rosemary (Rosmarinus officinalis L.) Glycolic Extract Protects Liver Mitochondria from Oxidative Damage and Prevents Acetaminophen-Induced Hepatotoxicity. Antioxidants (Basel) 12(3):628. — PubMed PMID: 36978874
- Romo Vaquero M et al. (2013). Bioavailability of the major bioactive diterpenoids in a rosemary extract: metabolic profile in the intestine, liver, plasma, and brain of Zucker rats. Molecular Nutrition & Food Research 57(10):1834-46. — PubMed PMID: 23625681
- Gao L et al. (2016). Carnosic acid alleviates chronic alcoholic liver injury by regulating the SIRT1/ChREBP and SIRT1/p66shc pathways in rats. Molecular Nutrition & Food Research 60(9):1902-11. — PubMed PMID: 27125489
- Bozin B et al. (2007). Antimicrobial and antioxidant properties of rosemary and sage essential oils. Journal of Agricultural and Food Chemistry. — PubMed PMID: 17708648
- Borges RS et al. (2019). Rosmarinus officinalis essential oil: a review of its phytochemistry, anti-inflammatory activity, and mechanisms of action. Journal of Ethnopharmacology. — PubMed PMID: 30287195
- Akbari S et al. (2022). Effect of rosemary leaf powder with weight loss diet on lipid profile, glycemic status, and liver enzymes in patients with nonalcoholic fatty liver disease: A randomized, double-blind clinical trial. Phytotherapy Research 36(5):2186-2196. — PubMed PMID: 35318738
- Andrade JM et al. (2018). Rosmarinus officinalis L.: an update review of its phytochemistry and biological activity. Future Science OA 4(4):FSO283. — PubMed PMID: 29682318
PubMed Topic Searches
Connections
- All Herbs
- Rosemary Overview
- Rosemary Benefits Hub
- Rosemary for Cognitive Function
- Rosemary for Antioxidant & Anti-Aging
- Rosemary for Hair Loss
- Peppermint (Carminative)
- Fennel (Carminative)
- Milk Thistle (Hepatoprotective)
- Dandelion (Cholagogue)
- Ginger (Digestive)
- N-Acetylcysteine (Acetaminophen Antidote)
- Glutathione
- Gastroenterology
- Hepatology
- History