⚠ Evidence warning: Clinical trials or other evidence do not support the claim that rosemary aroma works by crossing into the brain and inhibiting acetylcholinesterase; the prospective-memory and children's memory results come only from conference presentations and press releases, not peer-reviewed papers. This page keeps it as a report of what people, websites or other media say.
Rosemary for Cognitive Function and Memory
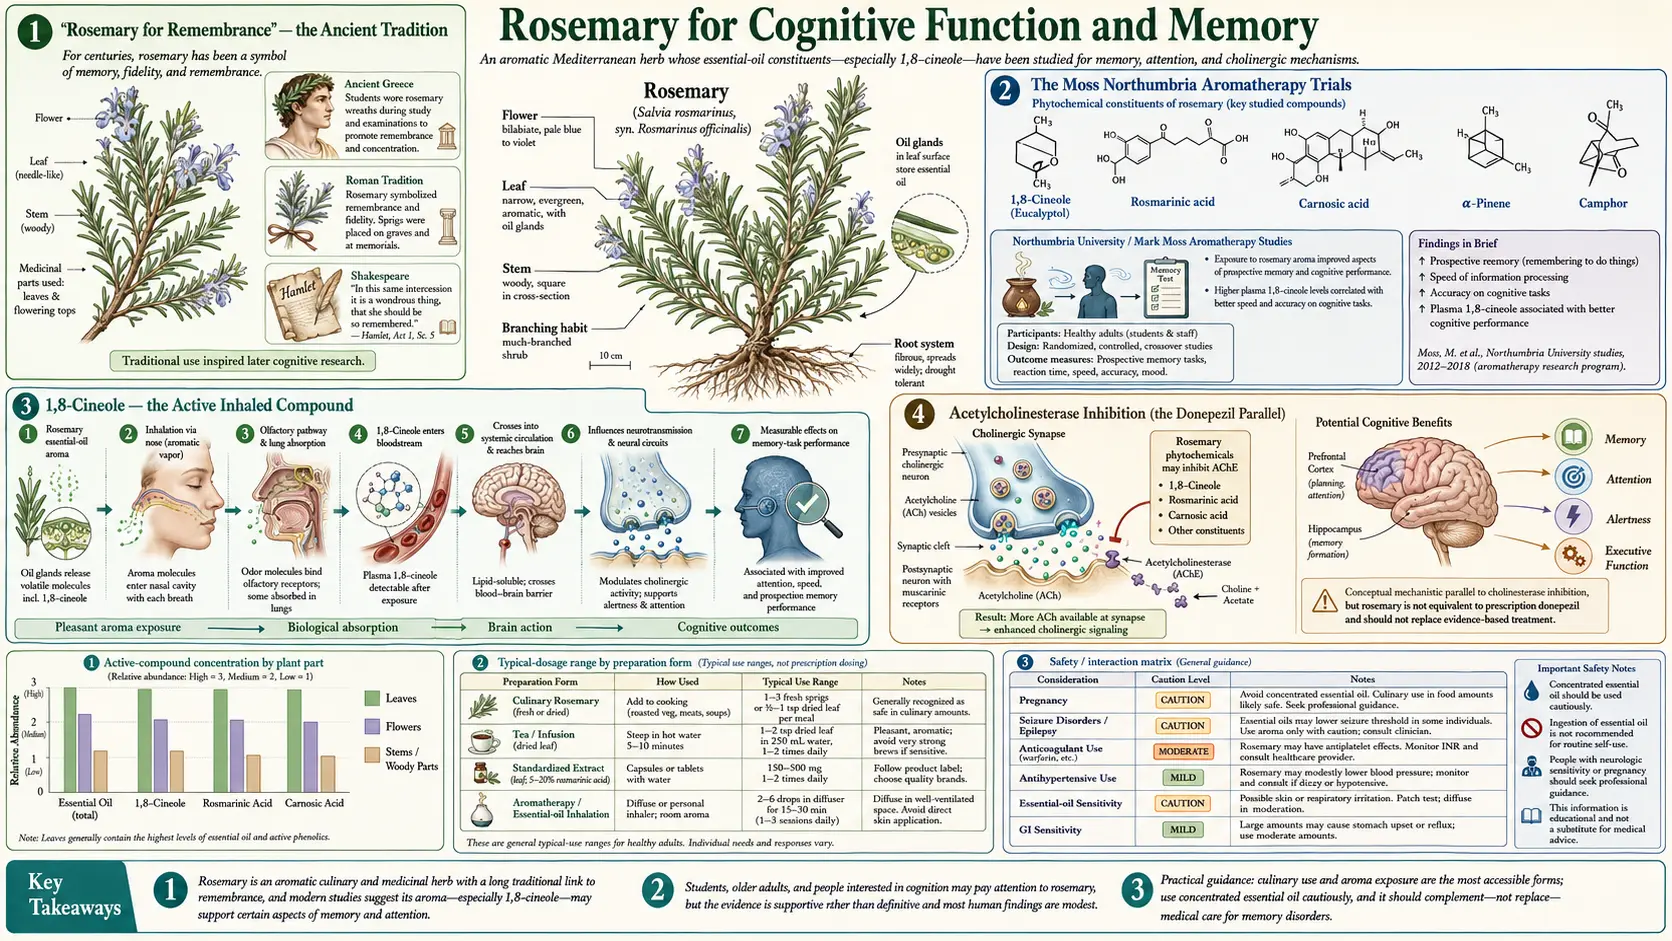
"There's rosemary, that's for remembrance; pray you, love, remember." Ophelia's line in Hamlet (Act IV, Scene V) is the best-known statement of a folk tradition that runs through ancient Greek and Roman writings — rosemary as the herb of memory, woven into students' hair during examinations and into mourners' wreaths to remember the dead. Four centuries after Shakespeare, the Mark Moss research group at Northumbria University ran a series of aromatherapy studies that put the folklore to a measurable test. In their 2003 trial of 144 healthy adults, people who worked in a cubicle scented with rosemary essential oil scored better on overall quality of memory than an unscented group, though their speed of memory was slower; in a 2013 conference presentation, 66 adults in a rosemary-scented room did better on prospective-memory tasks (remembering to do things later) than adults in an unscented room. The active inhaled compound is 1,8-cineole, a small lipophilic monoterpene that crosses the blood-brain barrier and acts as a reversible acetylcholinesterase inhibitor — the same enzyme class as the Alzheimer's drug donepezil. This deep-dive explores the Shakespearean tradition, the modern aromatherapy trials, the cholinergic mechanism, and the practical protocols for using rosemary aroma to support memory and concentration.
Table of Contents
- "Rosemary for Remembrance" — the Ancient Tradition
- The Moss Northumbria Aromatherapy Trials
- 1,8-Cineole — the Active Inhaled Compound
- Acetylcholinesterase Inhibition (the Donepezil Parallel)
- Prospective Memory — Why That Domain Specifically
- Crossing the Blood-Brain Barrier — Plasma 1,8-Cineole Correlations
- Alzheimer's Disease — Mechanistic Relevance and Trial Status
- Practical Aromatherapy Protocols
- Inhalation, Tea, Capsule, and Cooking Compared
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
"Rosemary for Remembrance" — the Ancient Tradition
The association of rosemary with memory runs back at least two thousand years. Ancient Greek students wore garlands of rosemary while studying for examinations, on the theory that the aroma sharpened recall. Dioscorides, writing in the first century, listed rosemary among the herbs that "warm the brain." Roman funerary rites used sprigs of rosemary at burials and on commemorative anniversaries — the herb of remembrance for the dead.
The Shakespearean reference is the most-cited statement of this tradition in English. In Hamlet, the bereaved and unraveling Ophelia distributes flowers to the court before her own death — "There's rosemary, that's for remembrance; pray you, love, remember." Shakespeare's audience would have recognized the herb's symbolic charge immediately; the line was not invention but allusion to existing English folk usage.
The same tradition persisted into the herbalism of the early modern period. John Gerard's 1597 Herball claimed rosemary "comforteth the cold, weake, and feeble braine in a most wonderful manner," and Nicholas Culpeper's 1652 The English Physitian recommended a rosemary chaplet "to comfort the head and the memory." Long-form folk traditions like these are sometimes dismissed as decorative superstition, but they also occasionally encode genuine pharmacological observations that modern science later confirms. The Moss Northumbria trials are the modern confirmation of this particular one.
The Moss Northumbria Aromatherapy Trials
The pivotal modern work on rosemary and cognition was done by Mark Moss and colleagues at Northumbria University in Newcastle, beginning with a 2003 paper in the International Journal of Neuroscience. The 2003 study randomized 144 healthy adults to one of three conditions in identical small cubicles: rosemary essential oil diffused into the air, lavender essential oil diffused, or unscented control. Participants completed a standardized cognitive battery including measures of memory, attention, and mood.
Results from the 2003 trial:
- The rosemary-exposed group showed significantly improved performance on overall quality of memory and secondary memory compared to control, but also an impairment of speed of memory
- The lavender-exposed group showed a significant decrement in working memory and slower reaction times on memory and attention tasks compared to control (consistent with lavender's sedative association)
- Mood differed by group — after the test battery, the control and lavender groups were significantly less alert than the rosemary group, and the control group was significantly less content than both the rosemary and lavender groups
- The effect was robust to expectancy controls — participants were not told what the experiment was investigating
Moss and Oliver followed up with a 2012 paper in Therapeutic Advances in Psychopharmacology that looked for the compound behind the effect. Twenty healthy volunteers did serial subtraction (counting backwards in steps) and visual information processing tasks in a cubicle scented with rosemary, and one blood sample was taken from each at the end of the session:
- Higher blood levels of absorbed 1,8-cineole went with better performance — for both speed and accuracy, so people were not simply trading accuracy for speed
- Higher 1,8-cineole levels also went with a fall in contentment (a mood rating)
- The study had no unscented comparison group, did not test prospective memory, and did not measure 1,8-cineole in the brain
Prospective memory — the cognitive function of remembering to perform an action at a future point (taking medication at a specific time, returning a phone call, etc.) — was the subject of a 2013 study by Jemma McCready and Mark Moss, presented at the British Psychological Society's annual conference and described in a Northumbria University press release; no peer-reviewed paper reporting it was found. Sixty-six people were randomly placed in a room scented with rosemary essential oil or an unscented room. The rosemary group did better both at remembering events and at remembering to complete timed tasks, and had significantly more 1,8-cineole in their blood plasma. The press release gives no percentage figures. Prospective memory is one of the first cognitive functions to decline in early Alzheimer's and is highly clinically relevant.
A 2017 study by Mark Moss and Victoria Earle, presented at the British Psychological Society's annual conference and described in the Society's press release (no peer-reviewed paper found), extended the work to school-age children. Forty children aged 10-11 performed memory tasks in a room either diffused with rosemary essential oil for ten minutes or unscented; the rosemary group scored significantly higher, with the largest difference on word recall. The effect of rosemary aroma on cognition appears to generalize across age groups and is not specific to elderly populations.
In older people, the dose of rosemary taken by mouth matters. In a 2012 crossover trial by Pengelly and colleagues, 28 adults with a mean age of 75 took a placebo and four different doses of dried rosemary leaf powder on separate visits. The lowest dose, 750 mg — the dose nearest normal cooking amounts, the authors note — sped up memory compared with placebo, while the highest dose, 6,000 mg, slowed it. Rosemary also had harmful effects on other measures of thinking, though these were less consistent.
1,8-Cineole — the Active Inhaled Compound
Rosemary essential oil contains roughly 30-40 distinct volatile compounds, but a single monoterpene — 1,8-cineole (also called eucalyptol) — appears to drive most of the cognitive effect. 1,8-cineole is also the principal volatile in eucalyptus oil, tea tree oil, and sage essential oil, and is present in modest amounts in basil and bay laurel.
The molecule has three properties that make it well-suited to a cognitive role after inhalation:
- Small molecular weight (154 Da) and lipophilic — it readily diffuses across the alveolar-capillary membrane after inhalation, entering systemic circulation within minutes
- Crosses the blood-brain barrier — the same lipophilicity that gets it into blood gets it across the BBB into the cerebrospinal fluid and brain parenchyma
- Reversible AChE inhibition — once in the brain, 1,8-cineole reversibly inhibits acetylcholinesterase, slowing the breakdown of synaptic acetylcholine and prolonging cholinergic neurotransmission
The Moss 2012 study measured 1,8-cineole in one blood sample taken at the end of each session and found that higher levels went with better speed and accuracy on the serial subtraction and visual information processing tasks. The authors concluded that compounds absorbed from rosemary aroma affect cognition and mood through different chemical pathways. Because the study measured blood, not brain, levels, the chain usually proposed remains a hypothesis: inhaled vapor → alveolar absorption → plasma 1,8-cineole → brain 1,8-cineole → AChE inhibition → prolonged cholinergic transmission → improved memory task performance.
Acetylcholinesterase Inhibition (the Donepezil Parallel)
Acetylcholinesterase (AChE) is the enzyme that breaks down acetylcholine in synaptic clefts. Inhibiting AChE prolongs the action of acetylcholine on its receptors, effectively amplifying cholinergic neurotransmission. This is one of the few drug mechanisms that has shown consistent (if modest) clinical benefit in mild-to-moderate Alzheimer's disease, and is the target of three Alzheimer's medications: donepezil, rivastigmine, and galantamine (originally from Galanthus snowdrop).
1,8-cineole is also an AChE inhibitor, but at much lower potency than the pharmaceutical drugs. Published IC50 values for 1,8-cineole against AChE are in the millimolar range, compared to nanomolar for donepezil. So the question becomes: how can a relatively weak inhibitor produce a measurable cognitive effect in healthy adults?
The likely answer is that the Moss aromatherapy effects are not pharmacological in the donepezil sense — they are pharmacognostic. The plasma concentrations achieved by inhalation are far below the levels needed to produce a clinically meaningful AChE inhibition in the way donepezil does, but they may be enough to produce a subtle, transient amplification of cholinergic tone that improves performance on demanding cognitive tasks in already-healthy brains. The effect is small enough that it would not be expected to alter the course of Alzheimer's disease, but large enough to be detected with adequate sample sizes in controlled studies of healthy participants.
An important caveat: galantamine, the AChE inhibitor derived from snowdrop bulbs, also has additional positive allosteric modulator activity at the nicotinic acetylcholine receptor that contributes to its clinical effect. It is possible that 1,8-cineole or other rosemary compounds have analogous additional cholinergic effects that have not yet been fully characterized. The full pharmacology of the rosemary cognitive effect is still being worked out.
Prospective Memory — Why That Domain Specifically
The Moss group's 2013 conference study chose prospective memory as its outcome. Prospective memory is the ability to remember to perform an intended action at a future time — remembering to take a medication at 9:00 PM, remembering to pass on a message to a colleague tomorrow morning, remembering to return a library book by the end of the week. It is functionally distinct from retrospective memory (remembering what was previously learned) and is one of the cognitive domains most sensitive to early decline in mild cognitive impairment and Alzheimer's disease.
Prospective memory has two components, both of which can be selectively measured:
- Event-based prospective memory — remembering to perform an action when a specific cue appears (e.g., "say ‘sky’ whenever the word ‘cloud’ appears in the test"). The 2013 Moss study used tasks of this kind, such as finding hidden objects at the end of the test.
- Time-based prospective memory — remembering to perform an action at a specific clock time (e.g., "press this button every two minutes"). Generally more difficult and more sensitive to age and cognitive impairment. The 2013 Moss study also asked participants to pass an object to the researcher at a set time.
In the 2013 conference study, the rosemary group did better than the unscented group both at remembering events and at remembering to complete timed tasks; the press release gives no percentage figures. The clinical relevance of this domain is concrete: this is the cognitive domain that determines whether a patient remembers to take a blood-pressure medication on time, whether an older adult remembers to turn off the stove after leaving the kitchen, and whether a busy professional remembers to make a scheduled phone call.
Crossing the Blood-Brain Barrier — Plasma 1,8-Cineole Correlations
The 2012 Moss study's most pharmacologically important finding was that 1,8-cineole from inhaled rosemary vapor reaches the bloodstream in measurable amounts, and that the level in one blood sample taken at the end of the session went with better cognitive performance. The study did not measure 1,8-cineole in the brain or spinal fluid, so it shows absorption into the blood, not passage across the blood-brain barrier.
Pharmacokinetic studies of inhaled 1,8-cineole in people report:
- Peak plasma concentration occurs approximately 18 minutes after inhalation begins (Jäger and colleagues, 1996)
- Plasma half-life is approximately 1.5-2 hours after exposure ends (an elimination half-life of 104.6 minutes in the 1996 study)
- Hepatic metabolism via cytochrome P450 3A4 (CYP3A4) to hydroxylated metabolites that are renally excreted
The practical implication is that the cognitive effect is time-limited. Blood 1,8-cineole peaks within about 18 minutes of starting inhalation; a diffuser running constantly will deplete its scent within a few hours, and blood 1,8-cineole steadily declines once exposure ends. Aromatherapy practitioners describe a brief 10-20 minute exposure to high-quality rosemary essential oil before a demanding task as more efficient than ambient long-duration exposure.
Alzheimer's Disease — Mechanistic Relevance and Trial Status
The shared AChE-inhibition mechanism between 1,8-cineole and the U.S. Food and Drug Administration-approved Alzheimer's drugs (donepezil, rivastigmine, galantamine) raises the obvious question: does rosemary or rosemary essential oil have a place in the treatment or prevention of Alzheimer's disease? The honest answer is that there is no high-quality clinical trial evidence in established Alzheimer's disease patients to support such a role. The Moss work was done in healthy adults, and a transient amplification of cholinergic tone in a healthy brain is not the same intervention as treatment of a brain with progressive cholinergic neuron loss.
Two small, short studies have tested rosemary aromatherapy in older people. In a 2009 Japanese study of 28 elderly people, 17 of whom had Alzheimer's disease, 28 days of aromatherapy with rosemary and lemon oils in the morning and lavender and orange oils in the evening was followed by significant improvement in personal orientation on two dementia rating scales, and the people with Alzheimer's improved on total scores of a touch-panel dementia test; routine laboratory tests showed no significant changes. In a 2024 randomised study of 63 adults aged 65 and over with diabetes, four weeks of inhaling lavender or rosemary oil was followed by better scores on an orientation-concentration test, lower anxiety and better sleep quality compared with each group's starting scores; the authors call for longer studies with more people.
However, several lines of evidence make rosemary plausibly relevant to Alzheimer's biology, even if direct treatment evidence is lacking:
- Carnosic acid as a neuroprotectant — the principal phenolic diterpene in rosemary (also discussed on the antioxidant page) is a potent Nrf2 activator that has shown neuroprotective activity in cellular and rodent models of Alzheimer's, Parkinson's, and ischemic stroke. Mechanism appears to be Nrf2-driven upregulation of glutathione and antioxidant defenses in neurons under oxidative stress.
- Rosmarinic acid and amyloid-beta aggregation — rosmarinic acid (also abundant in lemon balm) inhibits the aggregation of amyloid-beta peptide into the oligomers and fibrils that drive Alzheimer's pathology in cellular and transgenic mouse models.
- Anti-inflammatory effects on microglia — carnosol and carnosic acid suppress NF-kappaB activation in microglial cells, the brain's resident immune cells whose chronic activation drives much of the inflammatory damage in Alzheimer's.
For patients or family members of patients with established Alzheimer's disease, rosemary aromatherapy is a low-risk intervention that may produce subtle quality-of-life improvements (mood, alertness during demanding tasks, ease of caregiving environment), but the research does not show it treats the underlying disease. The medicines studied for that purpose are the pharmaceutical AChE inhibitors and the newer anti-amyloid monoclonal antibodies. A 2025 review reports that the FDA granted traditional approval to lecanemab in July 2023 and approved donanemab in July 2024; both clear amyloid from the brain and modestly slow decline in early-stage, biomarker-confirmed Alzheimer's disease, and both carry significant safety risks, including amyloid-related imaging abnormalities (ARIA). See the Alzheimer's Disease page for the full treatment landscape.
Practical Aromatherapy Protocols
How aromatherapy practitioners translate the Moss Northumbria study setup into home use:
- Essential oil quality — practitioners look for a 100% pure Rosmarinus officinalis essential oil sold with a Certificate of Analysis showing 1,8-cineole content of at least 25-30% (the ct. cineol chemotype). Lower-quality oils may have negligible 1,8-cineole content and not reproduce the cognitive effect.
- Diffuser approach — an ultrasonic or nebulizing diffuser is the simplest delivery. The usual home method is 3-5 drops of essential oil in the diffuser water reservoir, run for 15-20 minutes in a small to medium-sized room before a demanding cognitive task (study session, important meeting, exam preparation).
- Inhaler stick — for portable use during a workday, a personal aromatherapy inhaler (the small plastic tube with a cotton wick) holds about 15 drops of essential oil and provides a quick 30-second inhalation that can be repeated as needed.
- Direct sniff bottle — for occasional use, holding an opened bottle of essential oil 4-6 inches under the nose and taking 5-10 slow breaths is the lowest-cost protocol. A tightly capped bottle keeps the volatile fraction from evaporating between uses.
- Timing — in a 1996 study of inhaled 1,8-cineole, blood levels peaked about 18 minutes after inhalation began, and the plasma half-life was about 1.5-2 hours (104.6 minutes). In the Moss studies, people did the cognitive tasks while in the scented room.
Heat-based diffusion (candle warmers, electric tea-light burners) can degrade the more volatile fractions of the oil through excessive temperature. Ultrasonic diffusion at room temperature preserves the chemistry of the original oil.
Inhalation, Tea, Capsule, and Cooking Compared
An important practical clarification: most of the Moss cognitive studies used inhalation, but the cognitive effect is not limited to it — Moss's own 2018 rosemary-water trial (below) and the 2012 trial of dried rosemary leaf powder in older adults (above) found cognitive effects from rosemary taken by mouth. Other delivery modes for rosemary — eating it on roast lamb, drinking rosemary tea, or taking a rosemary leaf extract capsule — deliver rosemary's antioxidant and anti-inflammatory compounds (carnosic acid, carnosol, rosmarinic acid), but they deliver far less 1,8-cineole to the central nervous system than inhalation does.
The reason has to do with first-pass hepatic metabolism. Compounds absorbed from the gastrointestinal tract pass through the portal venous system to the liver before reaching systemic circulation, where they are metabolized by CYP enzymes and excreted as inactive metabolites. 1,8-cineole is a cytochrome P450 3A4 substrate, and a significant fraction of an oral dose is hepatically extracted on first pass. Inhaled 1,8-cineole, by contrast, is absorbed across the alveolar membrane directly into the pulmonary venous return, bypassing the liver entirely on its first circuit through the body. The result is a much higher plasma peak per unit dose from inhalation than from oral consumption.
Moss's group later tested drinking rather than smelling rosemary. In a 2018 trial, 80 healthy adults were randomly given 250 mL of a commercially available water containing a rosemary extract and hydrolat, or 250 mL of plain mineral water. The rosemary-water group showed a number of small but statistically significant gains on computerised cognitive tasks, which the authors describe as consistent with the earlier aroma findings. During the tasks, levels of deoxygenated haemoglobin in the brain, measured by near-infrared spectroscopy (light shone through the scalp), were significantly higher in the rosemary-water group, which the authors suggest may reflect better oxygen extraction when the brain is working hard.
The mode-specific clinical effects:
- Cognitive / memory effect — studied mostly by inhalation (aromatherapy, diffuser, inhaler stick, direct sniffing), but also found in trials of rosemary water and of a low dose (750 mg) of dried leaf powder by mouth.
- Antioxidant / hepatoprotective effect — requires oral consumption of significant doses. Cooking with the dried leaf, rosemary tea, leaf extract capsules.
- Hair-loss treatment — requires topical scalp application of diluted essential oil. See the hair loss page.
- Carminative / digestive effect — tea or culinary use; topical or inhalation will not achieve a digestive effect. See the digestive page.
This multi-mode profile is a real practical strength of rosemary as a household herb — the same plant is useful in three or four different ways, but each mode requires the right delivery to access the corresponding effect.
Cautions and Drug Interactions
- Pregnancy — medicinal doses of rosemary essential oil (oral or transdermal) are traditionally contraindicated in pregnancy due to historical use as an emmenagogue (menstruation-inducing agent). Culinary amounts in cooking are safe. Aromatherapy is generally considered safe for most pregnant women; the traditional concern applies to medicinal oral or transdermal doses.
- Epilepsy — rosemary essential oil, like many camphoraceous essential oils, can lower the seizure threshold in susceptible individuals. The concern applies most to people with a personal or family history of seizure disorder, and to concentrated rosemary essential oil exposure (aromatherapy, oral use, topical use of undiluted oil).
- Asthma and reactive airway disease — strong essential oil aromas can trigger bronchospasm in some asthmatic individuals; respiratory symptoms during exposure are the sign of this reaction.
- Blood pressure and heart rate — in a 2013 study of 20 healthy volunteers, inhaling rosemary oil significantly raised blood pressure, heart rate and breathing rate, and brain-wave recordings (EEG) shifted toward a more alert pattern (less alpha and more beta activity at the front of the brain); people felt more active and “fresher”. These stimulant effects matter most for people with high blood pressure or heart-rhythm problems.
- Cholinergic drug interactions — for patients taking pharmaceutical AChE inhibitors (donepezil, rivastigmine, galantamine) for Alzheimer's, concurrent use of rosemary essential oil aromatherapy is unlikely to produce a clinically meaningful additional inhibition, but theoretically additive cholinergic effects are possible. The combination is generally considered low-risk; the theoretical concern is a cholinergic effect added on top of the drug's own.
- Undiluted essential oil on skin — rosemary essential oil is sensitizing and irritating in its concentrated form. Topical use typically dilutes it to 2-5% in a carrier oil (see the hair loss page for full topical protocols).
- Essential oil by mouth — rosemary essential oil is highly concentrated; oral overdose can produce nausea, vomiting, gastrointestinal irritation, hepatotoxicity, and seizures. The dried leaf in cooking or tea is the safe oral form.
Key Research Papers
- Moss M, Cook J, Wesnes K, Duckett P (2003). Aromas of rosemary and lavender essential oils differentially affect cognition and mood in healthy adults. International Journal of Neuroscience. — PubMed PMID: 12690999
- Moss M, Oliver L (2012). Plasma 1,8-cineole correlates with cognitive performance following exposure to rosemary essential oil aroma. Therapeutic Advances in Psychopharmacology. — PubMed PMID: 23983963
- Moss M, Smith E, Milner M, McCready J (2018). Acute ingestion of rosemary water: Evidence of cognitive and cerebrovascular effects in healthy adults. Journal of Psychopharmacology. — PubMed PMID: 30318972
- Jäger W, Nasel B, Nasel C, Binder R, Stimpfl T, Vycudilik W, Buchbauer G (1996). Pharmacokinetic studies of the fragrance compound 1,8-cineol in humans during inhalation. Chemical Senses. — PubMed PMID: 8866111
- Moss L, Rouse M, Wesnes KA, Moss M (2010). Differential effects of the aromas of Salvia species on memory and mood. Human Psychopharmacology. — PubMed PMID: 20589925
- Sayorwan W et al. (2013). Effects of inhaled rosemary oil on subjective feelings and activities of the nervous system. Scientia Pharmaceutica. — PubMed PMID: 23833718
- Pengelly A et al. (2012). Short-term study on the effects of rosemary on cognitive function in an elderly population. Journal of Medicinal Food. — PubMed PMID: 21877951
- Perry NS, Houghton PJ, Theobald A, Jenner P, Perry EK (2000). In-vitro inhibition of human erythrocyte acetylcholinesterase by Salvia lavandulaefolia essential oil and constituent terpenes. Journal of Pharmacy and Pharmacology. — PubMed PMID: 10933142
- Satoh T et al. (2008). Carnosic acid, a catechol-type electrophilic compound, protects neurons via activation of the Keap1/Nrf2 pathway. Journal of Neurochemistry. — PubMed PMID: 17995931
- Habtemariam S (2016). The therapeutic potential of rosemary diterpenes for Alzheimer's disease. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 26941822
- Filiptsova OV et al. (2018). The effect of the essential oils of lavender and rosemary on the human short-term memory. Alexandria Journal of Medicine. — doi:10.1016/j.ajme.2017.05.004
- Diego MA et al. (1998). Aromatherapy positively affects mood, EEG patterns of alertness and math computations. International Journal of Neuroscience. — PubMed PMID: 10069621
- Jimbo D et al. (2009). Effect of aromatherapy on patients with Alzheimer's disease. Psychogeriatrics. — PubMed PMID: 20377818
- Can S, Yildirim Usta Y, Yildiz S, Tayfun K (2024). The effect of lavender and rosemary aromatherapy application on cognitive functions, anxiety, and sleep quality in the elderly with diabetes. Explore (New York). — PubMed PMID: 39047346
- Papaliagkas V (2025). Anti-Amyloid Therapies for Alzheimer's Disease: Progress, Pitfalls, and the Path Ahead. International Journal of Molecular Sciences. — PubMed PMID: 41096797
PubMed Topic Searches
Connections
- All Herbs
- Rosemary Overview
- Rosemary Benefits Hub
- Rosemary Antioxidant & Anti-Aging
- Rosemary for Hair Loss
- Rosemary for Digestive & Liver
- Alzheimer's Disease
- Parkinson's Disease
- Bacopa Monnieri
- Lemon Balm (Rosmarinic Acid)
- Sage (Salvia)
- Ginkgo Biloba
- Anxiety
- Aromatherapy — the inhaled essential-oil practice used in the Moss rosemary memory trials.
- Oxidative Stress
- Glutathione
- History