Garlic for Cardiovascular Health & Blood Pressure
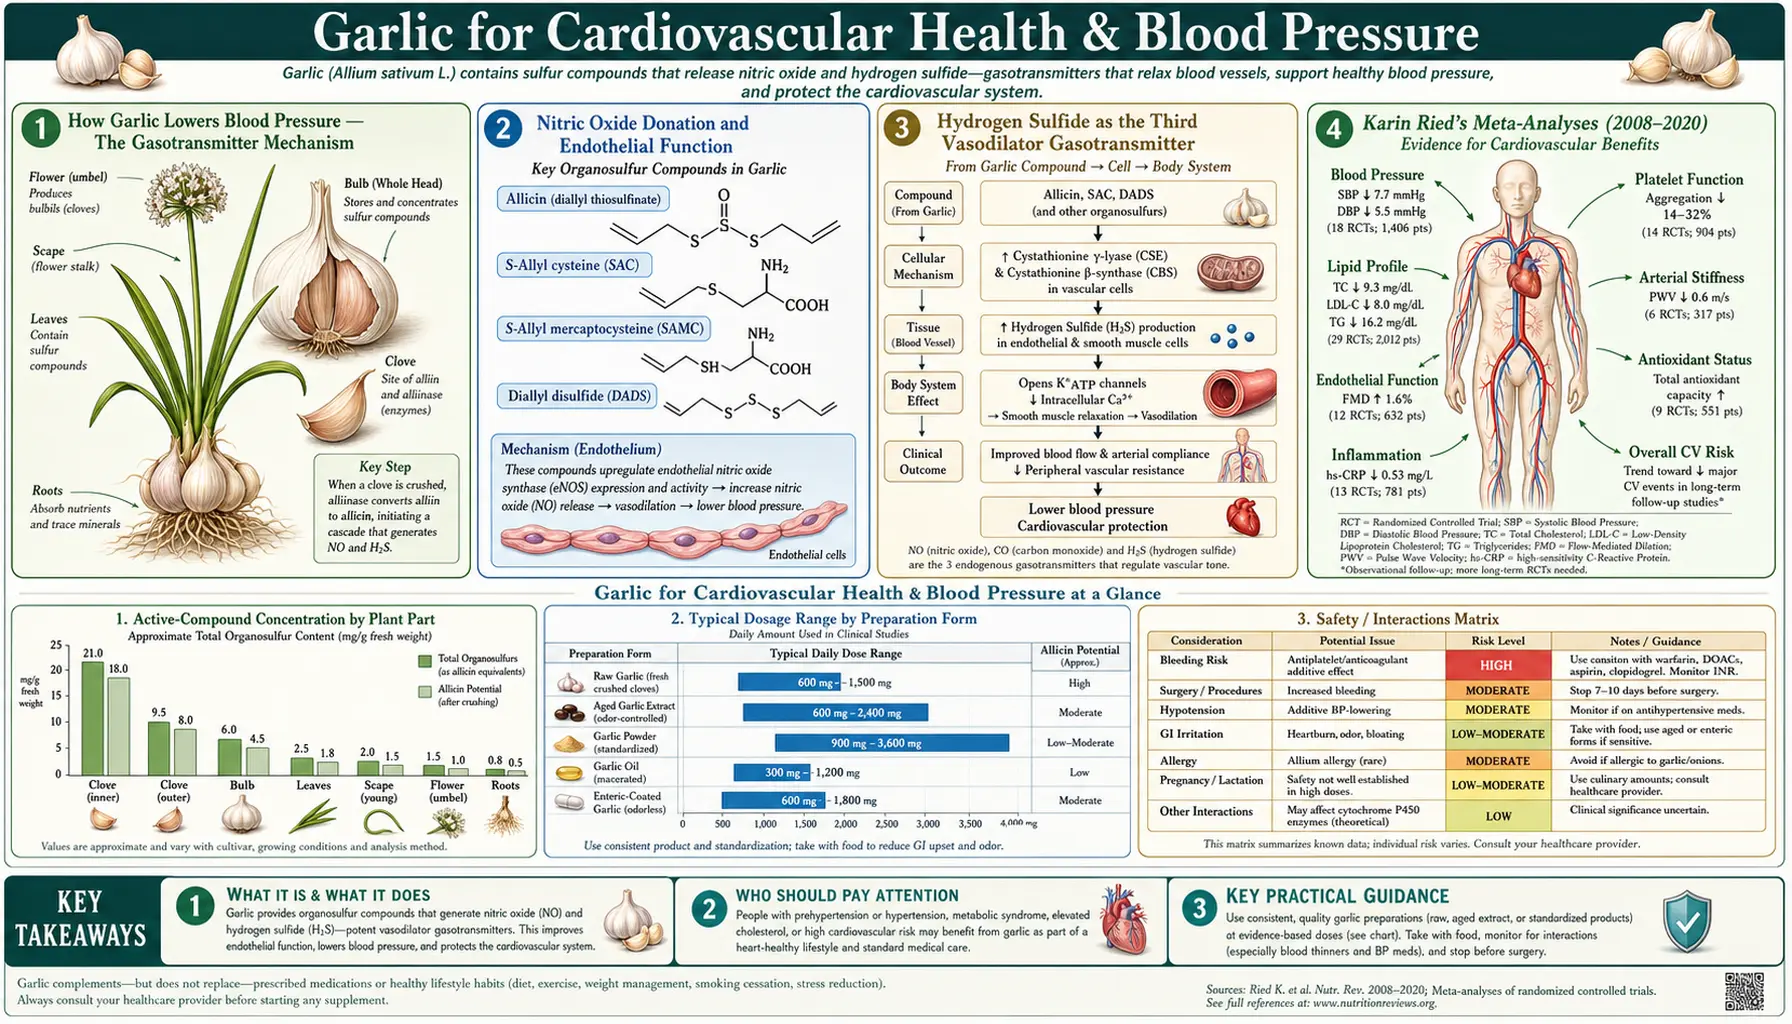
The most clinically actionable use of garlic in modern medicine is the treatment of mild-to-moderate hypertension with standardized aged garlic extract (AGE). The flagship body of evidence is a series of randomized trials and meta-analyses by Karin Ried and colleagues at the University of Adelaide, conducted from 2008 to 2020, with pooled analyses showing approximately −8 mmHg systolic and −5 mmHg diastolic blood-pressure reduction in hypertensive adults, and aged garlic extract trials using 480 mg to 1.2 g per day — an effect size that is genuinely comparable to a low-dose first-line antihypertensive drug. The mechanism is now well-mapped: allyl sulfur compounds in AGE donate hydrogen sulfide (H2S) and enhance nitric oxide (NO) bioavailability in the vascular endothelium, the two principal endogenous vasodilator gasotransmitters. This page walks through the trial evidence, the proper preparation and dosing, the realistic place of garlic in a hypertension treatment plan, and the meaningful cautions — especially the antiplatelet bleeding-risk interaction with prescription anticoagulants and with surgery.
Table of Contents
- How Garlic Lowers Blood Pressure — The Gasotransmitter Mechanism
- Nitric Oxide Donation and Endothelial Function
- Hydrogen Sulfide as the Third Vasodilator Gasotransmitter
- Karin Ried's Meta-Analyses (2008-2020)
- Effect Size vs First-Line Antihypertensives
- Aged Garlic Extract vs Fresh Garlic vs Powdered Tablets
- Doses Used in the Aged Garlic Extract Trials
- Beyond Blood Pressure: Arterial Stiffness, Endothelial Function, Gut Microbiome
- Combining Garlic with Prescription Antihypertensives
- Cautions — Bleeding Risk, Surgery, Anticoagulant Interactions
- Key Research Papers
- Connections
- Featured Videos
How Garlic Lowers Blood Pressure — The Gasotransmitter Mechanism
The mechanism by which garlic lowers blood pressure is now understood at the level of molecular pharmacology, and it is the same family of mechanisms that explains the clinical effects of organic nitrates (nitroglycerin, isosorbide mononitrate) and that explains the existence of nitric-oxide-mediated drug classes like sildenafil. Garlic-derived organosulfur compounds donate two distinct endothelium-derived vasodilator gases — nitric oxide (NO) and hydrogen sulfide (H2S) — in the vicinity of the vascular smooth muscle cell, triggering smooth-muscle relaxation, vasodilation, and a measurable drop in systemic arterial pressure.
The unique feature of garlic compared to the synthetic nitrate drugs is that it does not produce tachyphylaxis (tolerance) with sustained dosing the way nitroglycerin does, and that the effect is endothelium-dependent (it requires intact, functional endothelial cells), so it is a gentler, more physiologic stimulus to the same final pathway. The downside is that the effect is modest in magnitude (single-agent reductions in the range achievable by a single low-dose conventional antihypertensive), it requires sustained daily dosing for full effect (typically 8-12 weeks before maximum benefit), and the optimal preparation is aged garlic extract rather than the more familiar dietary forms.
The full cascade looks roughly like this: oral AGE delivers S-allyl cysteine (SAC) and small quantities of allyl polysulfides into systemic circulation. In the vascular endothelium, these compounds are metabolized in the presence of reduced glutathione to release hydrogen sulfide. H2S diffuses into adjacent vascular smooth-muscle cells, where it activates adenosine triphosphate-sensitive potassium channels (KATP), hyperpolarizes the cell, reduces calcium influx, and triggers smooth-muscle relaxation. In parallel, garlic compounds upregulate endothelial nitric oxide synthase (eNOS) activity and protect existing NO from oxidative inactivation, enhancing the NO arm of vasodilation. The net effect is reduced peripheral vascular resistance and a modest, sustained drop in arterial blood pressure.
Nitric Oxide Donation and Endothelial Function
Nitric oxide is the most thoroughly characterized of the three known gasotransmitters and is the dominant moment-to-moment regulator of vascular tone. It is produced in vascular endothelial cells by the enzyme endothelial nitric oxide synthase (eNOS) from the substrate L-arginine, in a reaction that requires the cofactor tetrahydrobiopterin (BH4). NO diffuses across the endothelial cell membrane to the adjacent vascular smooth muscle, where it activates soluble guanylate cyclase, raises intracellular cyclic GMP, and triggers smooth-muscle relaxation.
Endothelial dysfunction — the loss of normal NO-mediated vasodilator capacity — is one of the earliest measurable abnormalities in essentially all forms of cardiovascular disease, including hypertension, atherosclerosis, diabetes, and the metabolic syndrome. The Morihara 2002 (Life Sciences) and Williams 2005 (Phytotherapy Research) trials demonstrated that aged garlic extract enhances NO production both in cell culture (cultured human umbilical vein endothelial cells, HUVECs) and in vivo (men with established coronary artery disease, measured by brachial-artery flow-mediated dilation). In the Williams trial, 15 men with coronary artery disease, already treated with aspirin and a statin, took aged garlic extract and placebo for 2 weeks each in a crossover design; flow-mediated dilation rose 44% from baseline on aged garlic extract, mainly in men with the lowest starting values, while markers of oxidation and inflammation (oxidized LDL, C-reactive protein, interleukin-6) did not change significantly. The authors write that whether this improvement lowers the risk of future heart events "remains to be determined". The mechanism is twofold: AGE compounds upregulate eNOS mRNA and protein, increasing the enzymatic capacity to make NO; and they reduce oxidative inactivation of NO by superoxide (an effect attributable to the antioxidant capacity of S-allyl cysteine and related thiol-rich compounds).
This dual mechanism — more NO produced, less NO destroyed — is conceptually similar to the rationale for prescribing L-arginine or L-citrulline as cardiovascular supplements, though garlic has a stronger randomized-trial evidence base for the actual clinical endpoint of blood-pressure reduction. The Kim-Park / Ku 2000 study (Clinical and Experimental Pharmacology and Physiology) provided one of the early animal-model demonstrations that garlic-induced vasorelaxation is endothelium-dependent and is abolished by NOS inhibitors, establishing the centrality of the NO mechanism.
Hydrogen Sulfide as the Third Vasodilator Gasotransmitter
The recognition of hydrogen sulfide as a physiologic gasotransmitter is more recent — the modern era of H2S vascular biology began in the late 1990s and early 2000s, well after NO and carbon monoxide had been established. H2S is produced endogenously by three enzymes (cystathionine-β-synthase, cystathionine-γ-lyase, and 3-mercaptopyruvate sulfurtransferase) using L-cysteine as the principal substrate. In the vasculature, H2S produces vasodilation primarily by activating adenosine triphosphate-sensitive potassium channels (KATP) in vascular smooth muscle, leading to hyperpolarization and reduced calcium-dependent contraction. It also enhances NO bioavailability through complex cross-talk with the NO pathway.
The Benavides et al. 2007 paper in PNAS was the breakthrough demonstration that garlic's organosulfur compounds — specifically diallyl polysulfides — act as H2S donors in vascular tissue, releasing H2S in the presence of reduced glutathione at biologically meaningful concentrations. The vasoactivity of garlic in isolated rat aortic ring preparations correlated tightly with H2S production, and blockade of KATP channels abolished the response. This was the first molecular-level explanation for the long-observed but mechanistically obscure vasodilator effect of garlic.
The clinical relevance is that aged garlic extract, by delivering both S-allyl cysteine (which feeds into endogenous H2S biosynthesis via the cysteine pool) and small quantities of allyl polysulfides (which directly donate H2S), provides sustained, low-grade H2S signaling without the toxicity that would result from acute high-dose exposure (H2S at high concentration is a well-known mitochondrial poison). The body's natural H2S pathway provides the safety margin that synthetic H2S donor drugs (currently in early development) have to demonstrate the hard way.
Karin Ried's Meta-Analyses (2008-2020)
The single most important investigator in modern garlic-and-blood-pressure research is Karin Ried at the University of Adelaide and the Australian National Institute of Integrative Medicine. Ried has published a series of randomized controlled trials and meta-analyses, summarized below in roughly chronological order:
- Ried 2008 (BMC Cardiovascular Disorders) — a systematic review and meta-analysis of garlic-and-blood-pressure randomized controlled trials (RCTs), updating one from 1994: 11 of 25 studies in the review were suitable for pooling. Across all pooled trials, systolic blood pressure (BP) fell 4.6 mmHg compared with placebo. In the hypertensive subgroup, garlic preparations reduced systolic BP by 8.4 mmHg (4 trials) and diastolic by 7.3 mmHg (3 trials) compared with placebo, and the higher the starting blood pressure, the larger the drop; the effect in normotensives was much smaller and non-significant. This is the headline finding that established garlic as a credible blood pressure-lowering agent in the modern era.
- Ried 2013 dose-response trial (European Journal of Clinical Nutrition) — 79 general-practice patients whose systolic blood pressure stayed high despite their usual medication took one, two or four capsules a day of aged garlic extract (240, 480 or 960 mg, containing 0.6, 1.2 or 2.4 mg of S-allyl cysteine) or placebo for 12 weeks. Only the 480 mg group reached a significant systolic reduction: 11.8 mmHg over placebo (P=0.006). The 960 mg group reached a borderline reduction at 8 weeks (−7.4 mmHg, P=0.07); 240 mg and the diastolic changes were not different from placebo. Tolerability was high in all garlic groups.
- Ried 2016 updated meta-analysis (Journal of Nutrition) — 20 trials with 970 participants: systolic BP fell 5.1 mmHg and diastolic 2.5 mmHg compared with placebo. In the trials of people with high blood pressure (140/90 mmHg or more), systolic fell 8.7 mmHg (10 trials) and diastolic 6.1 mmHg (6 trials).
- Ried 2016 ("AGE at Heart" trial, Integrated Blood Pressure Control) — 88 people with uncontrolled high blood pressure took 1.2 g of aged garlic extract a day (1.2 mg S-allyl cysteine) or placebo for 12 weeks. Systolic BP fell 5.0 mmHg on average compared with placebo, and 11.5 mmHg systolic and 6.3 mmHg diastolic in responders. Central blood pressure and arterial-stiffness measures tended to improve more than on placebo.
- Ried 2018 ("GarGIC" trial, Frontiers in Nutrition) — a 12-week double-blind trial in 49 people with uncontrolled high blood pressure, using the same 1.2 g daily dose. Blood pressure fell 10 mmHg systolic and 5.4 mmHg diastolic compared with placebo; central blood pressure, pulse pressure and arterial stiffness were significantly lowered, and gut microbial richness and diversity rose, suggesting effects beyond direct vasodilation.
- Ried 2020 review (Experimental and Therapeutic Medicine) — the most recent comprehensive review, summarizing 12 years of trials and pooling 12 randomized controlled trials with 553 hypertensive participants. Garlic supplements lowered systolic blood pressure by an average of 8.3 mmHg and diastolic by 5.5 mmHg (8 trials, 374 people). The review also documents improvements in arterial stiffness, endothelial function, and the gut microbiome, and summarizes evidence that vitamin B12 status plays a role in whether blood pressure responds to garlic.
A 2025 meta-analysis by a different group (Bashiri 2025, Phytotherapy Research) pooled 19 trials of aged garlic in all kinds of participants, not only people with high blood pressure, and found a smaller average effect: systolic blood pressure fell 2.49 mmHg and LDL cholesterol 4.41 mg/dL, with no significant change in diastolic pressure or HDL cholesterol. The authors write that further high-quality trials are needed to confirm the findings.
The pattern across the Ried series is striking in its consistency: the effect is robust in hypertensives, much smaller in normotensives, described as dose-dependent above a threshold of approximately 300-400 mg/day of AGE (although in the 2013 dose trial only the 480 mg dose reached significance), and replicated with multiple preparations from multiple manufacturers. The 2012 Cochrane review by Stabler and colleagues was more cautious in its conclusions, emphasizing the methodological weaknesses of many of the included trials, but the more recent updates incorporating higher-quality randomized controlled trials have moved the consensus toward acceptance of a real, modest, clinically useful blood pressure-lowering effect.
Effect Size vs First-Line Antihypertensives
An 8-mmHg systolic blood-pressure reduction sounds small until it is put in context with what the first-line conventional antihypertensive drug classes achieve as single agents in similar populations. A representative comparison from the JNC-8 and subsequent hypertension trial literature:
- Thiazide diuretics (hydrochlorothiazide 25 mg/day, chlorthalidone 12.5-25 mg/day) — approximately 8-12 mmHg systolic reduction as monotherapy
- Angiotensin-converting enzyme inhibitors (ACE inhibitors) (lisinopril 10-40 mg/day, ramipril 5-10 mg/day) — approximately 8-12 mmHg systolic reduction as monotherapy
- Angiotensin receptor blockers (ARBs) (losartan 50-100 mg/day, valsartan 80-320 mg/day) — approximately 8-13 mmHg systolic reduction
- Calcium channel blockers (amlodipine 5-10 mg/day) — approximately 8-15 mmHg systolic reduction
- Aged garlic extract (480 mg to 1.2 g/day in the Ried trials) — 5.0 to 11.8 mmHg systolic reduction over placebo across the Ried aged-garlic trials
This is not to suggest that aged garlic extract is interchangeable with a thiazide or an angiotensin-converting enzyme inhibitor (ACE inhibitor) in a patient with stage-2 hypertension or with established cardiovascular disease — the prescription drugs have decades of randomized morbidity-and-mortality outcome data behind them (HOPE, ALLHAT, ONTARGET, etc.) and garlic does not. What the comparison does establish is that for a patient with mild (stage-1) hypertension who wants to try lifestyle and non-pharmaceutical interventions first — weight loss, DASH diet, sodium restriction, exercise — the addition of standardized aged garlic extract is a legitimate evidence-based component of that strategy and is one of the few herbal interventions with effect sizes that approach those of single-agent prescription drugs.
The patient population most likely to benefit, per the Ried trial inclusion criteria, is the adult with baseline systolic blood pressure in the 140-160 range, no compelling indication for a specific drug class (such as proteinuric diabetes or post-MI status), and a preference for non-pharmaceutical management. For more on the management of high blood pressure as a whole, see our Hypertension page.
Aged Garlic Extract vs Fresh Garlic vs Powdered Tablets
A common question is whether fresh garlic can stand in for the supplement for blood pressure. The Ried trials and the bulk of the modern cardiovascular literature have used standardized aged garlic extract for specific reasons:
- Standardization — AGE is standardized to a defined content of S-allyl cysteine (in the Ried trials, 0.6 mg per 240 mg capsule, and 1.2 mg in the 1.2 g daily dose). Fresh garlic varies dramatically in allicin-yielding potential by cultivar, growing region, time since harvest, and storage conditions.
- Stability — SAC and S-allyl mercaptocysteine in AGE are stable in storage for years. Allicin from fresh garlic decomposes within days at room temperature and within hours once dissolved in saliva or gastric fluid.
- Tolerability — AGE is essentially odorless. Fresh garlic at the dose required to deliver an equivalent amount of allyl sulfur compounds (estimated at roughly four to five cloves per day) produces severe halitosis, body odor, and gastrointestinal irritation in most users, making sustained compliance unrealistic.
- Trial evidence — the randomized cardiovascular evidence is almost exclusively from AGE, with smaller and more inconsistent evidence from powdered garlic tablets and very little from fresh garlic.
Powdered garlic tablets (plain garlic powder tablets, enteric-coated garlic tablets, and similar products) occupy an intermediate position. They contain dried, powdered garlic in a coated tablet that is designed to release allicin upon contact with intestinal fluid (the alliinase enzyme survives the drying process if it is not over-heated). The clinical evidence for powdered tablets is mixed, in part because the actual allicin yield varies dramatically from tablet to tablet and from product to product — the Sobenin 2008 trial of a time-released powdered garlic tablet did show meaningful lipid-lowering, but most negative garlic trials in the literature have used powdered preparations of uncertain real-world allicin yield.
Garlic oil (the steam-distilled lipid-soluble fraction) is concentrated in diallyl disulfide and diallyl trisulfide. The animal evidence for cardiovascular effects with garlic oil is strong, but the human cardiovascular trial data are limited and most garlic-oil capsules on the consumer market are sold for general "heart health" without specific blood pressure claims or standardization.
In the Ried blood-pressure trials, participants took standardized aged garlic extract at 480 mg to 1.2 g a day for 12 weeks. Fresh garlic remains a food with its culinary value and general phytochemical contribution to the diet; the randomized blood-pressure evidence comes mainly from aged garlic extract rather than from fresh garlic.
Doses Used in the Aged Garlic Extract Trials
The aged garlic extract blood-pressure trials used these doses and schedules:
- Doses tested: the 2013 dose trial gave one, two or four capsules a day (240, 480 or 960 mg of aged garlic extract, containing 0.6, 1.2 or 2.4 mg of S-allyl cysteine); the AGE at Heart and GarGIC trials gave 1.2 g a day (1.2 mg S-allyl cysteine).
- Dose with a significant effect in the dose trial: 480 mg a day (systolic −11.8 mmHg over placebo). The 960 mg dose reached a borderline reduction at 8 weeks (−7.4 mmHg, P=0.07), and 240 mg was not different from placebo.
- Time course: in the dose trial, blood pressure was measured at 4, 8 and 12 weeks; the dose, AGE at Heart and GarGIC trials each ran for 12 weeks.
- Responders and non-responders: in AGE at Heart the average systolic drop was 5.0 mmHg, and 11.5 mmHg systolic and 6.3 mmHg diastolic in responders; in GarGIC, vitamin B12 status played a role in whether blood pressure responded to garlic in 17% of patients.
In the 2013 dose trial, aged garlic extract was taken on top of the patients' existing blood-pressure medication. Garlic added on top of a prescription drug can produce additive blood pressure-lowering — a further drop where pressure is still high, and possible symptomatic hypotension or orthostasis (dizziness on standing) where it is not.
Beyond Blood Pressure: Arterial Stiffness, Endothelial Function, Gut Microbiome
The Ried 2016 AGE at Heart and 2018 GarGIC trials and the broader Ried 2020 review document several effects of sustained AGE supplementation that go beyond the simple blood-pressure number:
- Arterial stiffness — pulse-wave velocity (PWV), an independent cardiovascular risk marker, tended to improve over 12 weeks of AGE in AGE at Heart, and central blood pressure, pulse pressure and arterial stiffness were significantly lowered over 12 weeks in GarGIC. This implies a structural or vasomotor benefit to the large conduit arteries, not just a smooth-muscle tone effect.
- Endothelial function — flow-mediated dilation of the brachial artery, an established surrogate for endothelial health, improves with AGE in patients with coronary artery disease (Williams 2005). This is the functional readout of the NO and H2S mechanisms described above.
- Gut microbiome — AGE in the GarGIC trial produced a shift toward greater microbial richness and diversity and a marked increase in Lactobacillus and Clostridia species after 3 months; these groups include short-chain fatty acid producers. Whether this is a primary mechanism of the blood pressure effect or an epiphenomenon is unresolved; the AGE-microbiome-vascular-tone axis is an active research area.
- Vitamin B12 status — in GarGIC, vitamin B12 status played a role in whether blood pressure responded to garlic in 17% of patients, and the Ried 2020 review summarizes this as new evidence on who responds.
- Coronary artery calcium (CAC) progression — documented in the related Budoff 2009 trial, in which AGE plus B-vitamins / folate / L-arginine slowed coronary artery calcium accumulation over one year (covered in detail in the Cholesterol & Atherosclerosis page).
- Glycemic control — some evidence for modest improvement in fasting glucose and hemoglobin A1c (HbA1c) in metabolic-syndrome patients, of unclear clinical magnitude but consistent direction.
Combining Garlic with Prescription Antihypertensives
Aged garlic extract is generally well tolerated in combination with the major classes of conventional antihypertensive drugs. The principal interaction to anticipate is additive blood pressure-lowering, which is usually the desired effect but occasionally requires dose adjustment of the prescription drug:
- Angiotensin-converting enzyme inhibitors and angiotensin receptor blockers — additive blood pressure-lowering, no specific pharmacokinetic interaction documented. The combined effect can produce symptomatic hypotension and orthostatic symptoms (dizziness on standing).
- Calcium channel blockers — additive blood pressure-lowering, no documented pharmacokinetic interaction.
- Thiazide diuretics — additive blood pressure-lowering. AGE does not appear to potentiate the diuretic effect or alter electrolytes.
- Beta-blockers — additive blood pressure-lowering; no documented heart-rate interaction.
- Aldosterone antagonists (spironolactone, eplerenone) — additive blood pressure-lowering; no known potassium interaction.
- Vasodilators (hydralazine, minoxidil) — additive blood pressure-lowering, more likely to produce symptomatic hypotension when combined.
The clearest interaction is with antiplatelet and anticoagulant drugs — see the Cautions section below.
Cautions — Bleeding Risk, Surgery, Anticoagulant Interactions
- Antiplatelet / anticoagulant interaction — this is the headline safety concern with garlic at therapeutic doses. Allicin and especially ajoene inhibit platelet aggregation in vitro and in vivo. The concern applies to people taking warfarin, clopidogrel, prasugrel, ticagrelor, dabigatran, apixaban, rivaroxaban, or chronic high-dose aspirin, drugs that also reduce clotting. The interaction is not absolute — many patients on aspirin or warfarin take garlic supplements safely, and in the 12-week AGE at Heart trial (88 people with uncontrolled high blood pressure, 1.2 g aged garlic extract a day), aged garlic extract did not increase the risk of bleeding in patients on blood-thinning medication — but the bleeding risk varies from person to person; for warfarin it shows in the international normalized ratio (INR) blood test, and otherwise in bleeding and bruising trends.
- Surgery — pre-operative guidance commonly lists stopping all garlic supplements at least 7 days before any planned surgical or dental procedure with bleeding risk. This is the same time frame used for fish oil and ginkgo. The American Society of Anesthesiologists includes garlic on its standard list of supplements to discontinue pre-operatively.
- Childbirth — the same discontinuation principle applies; many obstetric protocols recommend stopping garlic supplements by 36 weeks gestation in anticipation of possible delivery-related bleeding.
- Gastrointestinal irritation — fresh garlic at high doses can produce heartburn, esophagitis, and nausea. AGE is much better tolerated; gastrointestinal complaints with AGE are uncommon at standard doses.
- Hypotension at the lower end of normal blood pressure — in people with baseline blood pressure under approximately 110/70, the additive effect of AGE is small but real, and a few patients have reported symptomatic orthostasis after starting garlic supplements.
- Human immunodeficiency virus (HIV) protease inhibitor interaction (saquinavir specifically) — in a study of 10 healthy volunteers (Piscitelli 2002), garlic caplets taken twice daily (41 doses) cut saquinavir blood levels: the area under the curve fell 51%, trough levels 49% and peak levels 54%. Ten days after the garlic was stopped, levels had returned only to 60–70% of their baseline values.
- Pregnancy — dietary garlic is safe and traditional in cuisines worldwide. High-dose garlic supplements have not been specifically studied in pregnancy; the bleeding-risk concern applies most in the third trimester.
- Children — garlic as food is appropriate at any age. High-dose garlic supplements for blood-pressure indications are not standard in pediatric practice.
Key Research Papers
- Ried K, Frank OR, Stocks NP, Fakler P, Sullivan T (2008). Effect of garlic on blood pressure: a systematic review and meta-analysis. BMC Cardiovascular Disorders 8:13. — PubMed PMID: 18554422
- Ried K, Frank OR, Stocks NP (2013). Aged garlic extract reduces blood pressure in hypertensives: a dose-response trial. European Journal of Clinical Nutrition 67:64-70. — PubMed PMID: 23169470
- Ried K (2016). Garlic lowers blood pressure in hypertensive individuals, regulates serum cholesterol, and stimulates immunity: an updated meta-analysis and review. Journal of Nutrition 146(2):389S-396S. — PubMed PMID: 26764326
- Ried K, Travica N, Sali A (2016). The effect of aged garlic extract on blood pressure and other cardiovascular risk factors in uncontrolled hypertensives: the AGE at Heart trial. Integrated Blood Pressure Control 9:9-21. — PubMed PMID: 26869811
- Ried K, Travica N, Sali A (2018). The Effect of Kyolic Aged Garlic Extract on Gut Microbiota, Inflammation, and Cardiovascular Markers in Hypertensives: The GarGIC Trial. Frontiers in Nutrition 5:122. — PubMed PMID: 30619868
- Ried K (2020). Garlic lowers blood pressure in hypertensive subjects, improves arterial stiffness and gut microbiota: A review and meta-analysis. Experimental and Therapeutic Medicine 19(2):1472-1478. — PubMed PMID: 32010325
- Bashiri S, TaghipourSheshdeh F, Foshati S, Askarpour M, Ahmadi A, Babajafari S (2025). The Effect of Aged Garlic Supplementation on Blood Pressure and Lipid Profile: A Dose-Response Grade-Assessed Systematic Review and Meta-Analysis of Randomized Controlled Trials. Phytotherapy Research 39(12):5669-5694. — PubMed PMID: 40628369
- Stabler SN, Tejani AM, Huynh F, Fowkes C (2012). Garlic for the prevention of cardiovascular morbidity and mortality in hypertensive patients. Cochrane Database of Systematic Reviews. — PubMed PMID: 22895963
- Benavides GA, Squadrito GL, Mills RW et al. (2007). Hydrogen sulfide mediates the vasoactivity of garlic. PNAS 104:17977-17982. — PubMed PMID: 17951430
- Morihara N, Sumioka I, Moriguchi T, Uda N, Kyo E (2002). Aged garlic extract enhances production of nitric oxide. Life Sciences 71:509-517. — PubMed PMID: 12052435
- Williams MJA, Sutherland WHF, McCormick MP, Yeoman DJ, de Jong SA (2005). Aged garlic extract improves endothelial function in men with coronary artery disease. Phytotherapy Research 19:314-319. — PubMed PMID: 16041725
- Wang HP, Yang J, Qin LQ, Yang XJ (2015). Effect of garlic on blood pressure: a meta-analysis. Journal of Clinical Hypertension 17(3):223-231. — PubMed PMID: 25557383
- Kim-Park S, Ku DD (2000). Garlic elicits a nitric oxide-dependent relaxation and inhibits hypoxic pulmonary vasoconstriction in rats. Clinical and Experimental Pharmacology and Physiology 27(10):780-786. — PubMed PMID: 11022969
- Ginter E, Simko V (2010). Garlic (Allium sativum L.) and cardiovascular diseases. Bratislava Medical Journal 111(8):452-456. — PubMed PMID: 21033626
- Ashraf R, Khan RA, Ashraf I (2011). Garlic (Allium sativum) supplementation with standard antidiabetic agent provides better diabetic control in type 2 diabetes patients. Pakistan Journal of Pharmaceutical Sciences 24(4):565-570. — PubMed PMID: 21959822
- Piscitelli SC, Burstein AH, Welden N, Gallicano KD, Falloon J (2002). The effect of garlic supplements on the pharmacokinetics of saquinavir. Clinical Infectious Diseases 34(2):234-238. — PubMed PMID: 11740713
PubMed Topic Searches
Connections
- All Herbs
- Garlic Overview
- Garlic Benefits Hub
- Garlic for Cholesterol & Atherosclerosis
- Garlic for Immune Function & Cold
- Garlic Antimicrobial Spectrum
- Hypertension
- Cardiovascular Disease
- Atherosclerosis
- Stroke
- Homocysteine
- Magnesium (Blood Pressure)
- Potassium (Blood Pressure)
- Hawthorn
- DASH Diet
- History