⚠ Evidence warning: Clinical trials or other evidence do not support the claims that garlic is a reasonable low-risk seasonal intervention for adults who wish to try it and a credible component of a winter-season immune-support strategy for healthy adults. This page keeps it as a report of what people, websites or other media say.
Garlic for Immune Function & the Common Cold
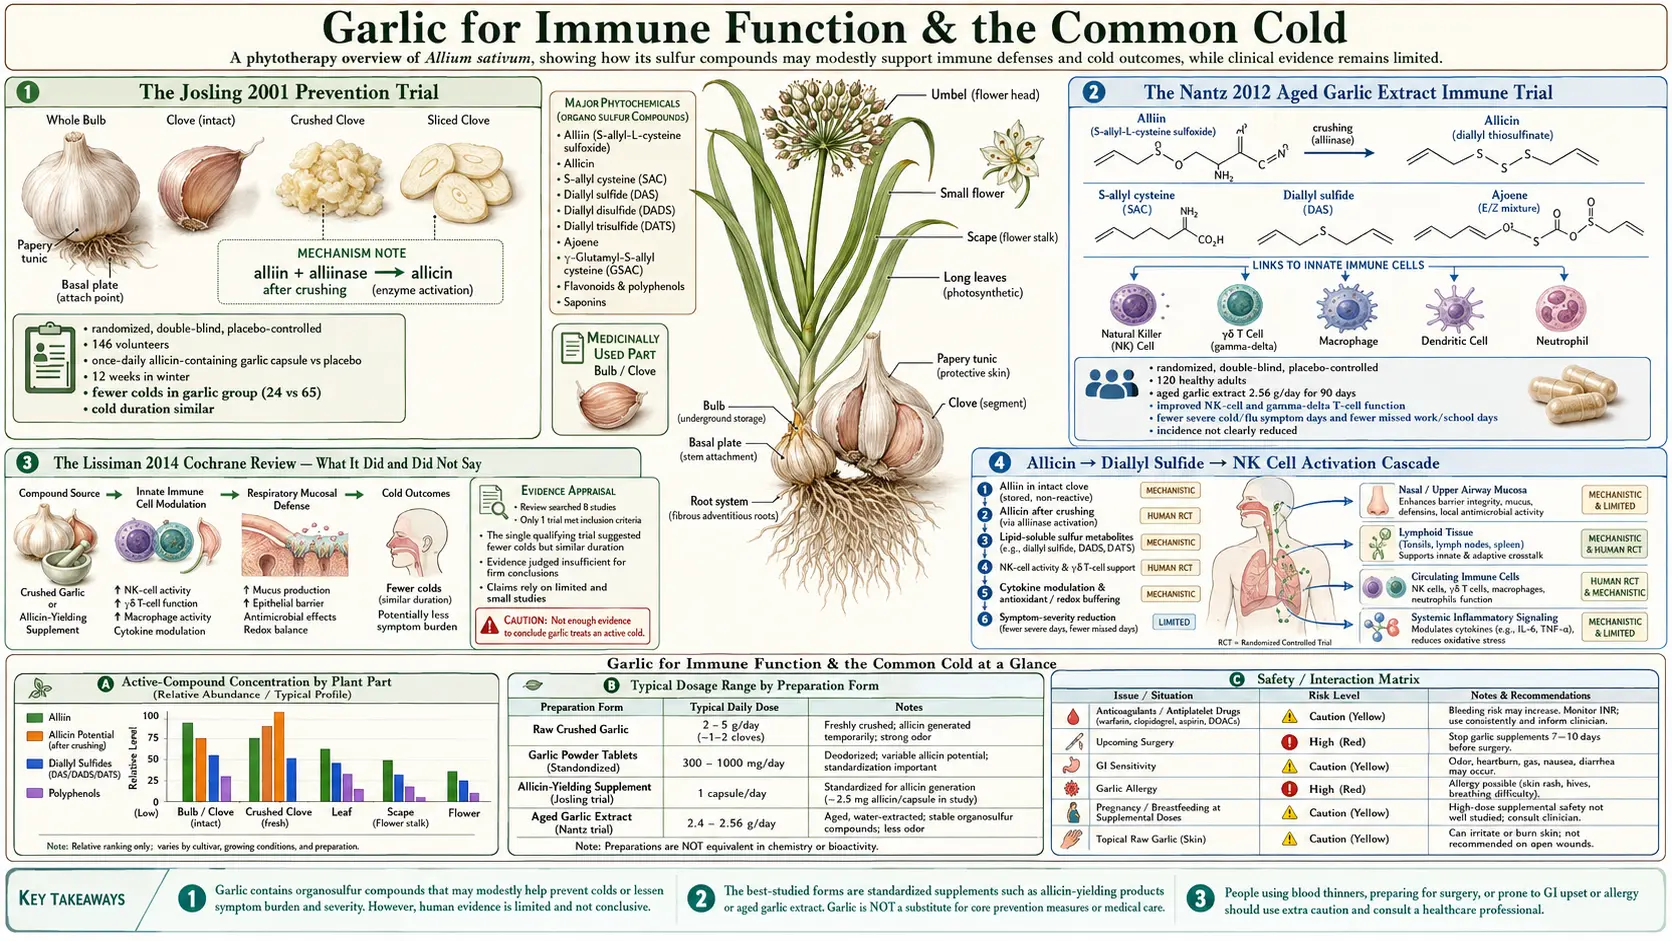
The signature garlic-and-immune trial is Peter Josling's 2001 study in Advances in Therapy — a 12-week, double-blind, placebo-controlled trial in 146 volunteers during winter cold season in which 65 colds occurred in the placebo group versus 24 in the group taking one allicin-containing garlic capsule a day, with symptoms lasting 1.52 days on average in the garlic group versus 5.01 days on placebo. The 2012 Nantz trial extended the picture to aged garlic extract and to mechanism, showing that AGE at 2.56 g/day enhanced γδ-T-cell and natural killer (NK) cell function, and the garlic group reported 21% fewer cold and flu symptoms. The 2014 Cochrane review by Lissiman, Bhasale, and Cohen has often been cited as "the evidence is thin," and on the strict Cochrane criteria for trial-quality scoring it is — only the Josling trial met all inclusion standards — but the totality of evidence including more recent trials supports a modest, real immune-protective effect from sustained garlic supplementation during respiratory virus season. The mechanism: allicin and its diallyl-sulfide metabolites activate macrophage and natural killer function, enhance γδ-T-cell proliferation, and reduce pro-inflammatory cytokine surges that contribute to cold-symptom severity. There is also an honest discussion to be had about the COVID-era garlic hype, which was not supported by any clinical trial and represented a reach beyond the evidence base.
Table of Contents
- The Josling 2001 Prevention Trial
- The Nantz 2012 Aged Garlic Extract Immune Trial
- The Lissiman 2014 Cochrane Review — What It Did and Did Not Say
- Allicin → Diallyl Sulfide → Natural Killer Cell Activation Cascade
- γδ-T Cells and Mucosal Surveillance
- Macrophage Activation and Inflammatory Cytokine Modulation
- Doses Used in Trials and in Practice for Cold & Flu Season
- Aged Garlic Extract vs Allicin Powder for Immune Use
- COVID-Era Caution — What the Evidence Supports and What It Does Not
- Cautions and Context
- Key Research Papers
- Connections
- Featured Videos
The Josling 2001 Prevention Trial
Peter Josling's 2001 study published in Advances in Therapy remains the single most-cited trial of garlic for the common cold and the only trial that meets the strict methodologic standards of the 2014 Cochrane review. The design: 146 healthy adult volunteers randomized in double-blind fashion to either an allicin-containing garlic supplement (one capsule a day; the Cochrane review describes it as containing 180 mg of allicin) or matched placebo, taken daily for 12 weeks across the November-to-February cold season in the United Kingdom. Subjects kept daily symptom diaries.
The primary outcome was number of common-cold episodes per group. Results:
- Number of colds: 65 colds in the placebo group versus 24 colds in the allicin group (P < .001); volunteers taking placebo were much more likely to have more than one cold during the 12 weeks
- Cold duration: when colds did occur in the allicin group, they were shorter (1.52 days vs 5.01 days mean duration in placebo)
- Symptom-day burden: the placebo group accumulated 366 cold symptom-days; the allicin group accumulated 111 cold symptom-days
- Side effects: the 2014 Cochrane review lists rash and odour among the adverse effects reported
The effect size in the Josling trial is large — substantially larger than is typical for nutritional interventions in respiratory virus prevention. The trial has been criticized on methodologic grounds (single-site, self-reported outcomes, modest sample size, unusually high cold rate in the placebo arm) but the design was rigorous double-blind, the placebo control was identical-appearing, and the symptom-diary outcome assessment is standard for upper respiratory tract infection trials. Independent replication of the Josling magnitude has been limited, which is part of why the Cochrane reviewers concluded that the clinical trial evidence is insufficient.
The practical takeaway from Josling is that an allicin-containing garlic preparation, taken daily across the cold season, may meaningfully reduce both the frequency and the duration of common-cold episodes in healthy adults — with the caveat that the magnitude in any individual user will depend on baseline cold-frequency, allicin yield of the actual preparation used, and adherence to daily dosing across a several-month period.
The Nantz 2012 Aged Garlic Extract Immune Trial
The 2012 Nantz study, published in Clinical Nutrition, extended the garlic-and-immune picture to standardized aged garlic extract and added a mechanism component. The design: 120 healthy adults (60 per group) randomized in double-blind fashion to either encapsulated AGE 2.56 g/day or placebo, for 90 days across cold/flu season, with blood draws for immune function studies at 45 and 90 days and prospectively collected symptom diaries.
Results:
- γδ-T-cell proliferation — after 45 days, γδ-T cells from the AGE group proliferated better than those from the placebo group (p = 0.039, 56 people tested). γδ-T cells are an unconventional T-cell subset important in early mucosal immunity to viral infection.
- Natural killer (NK) cell proliferation — also better in the AGE group after 45 days (p = 0.043, 56 people tested).
- Cold/flu incidence — after 90 days, the number of colds and flu episodes (a secondary outcome) was not statistically different between the groups
- Cold/flu symptom severity — the AGE group reported 21% fewer symptoms
- Days below par — the AGE group reported 61% fewer days, and 58% fewer occasions, on which they functioned below their usual level
- Work and school absenteeism — the AGE group missed 58% fewer work or school days because of illness (p = 0.035)
The pattern in Nantz is different from Josling: AGE did not appear to prevent infection (similar incidence in both arms) but did appear to ameliorate symptoms and reduce severity in those who did become infected, with parallel evidence of enhanced cellular immunity. This is consistent with AGE acting more on the immune-system-side of the host-pathogen interaction (improving the response to infection) rather than directly on the pathogen.
The Percival 2016 review in Journal of Nutrition summarizes the Nantz immune data and the broader pool of AGE-immune evidence. The Kyo 2001 study and the Ishikawa 2006 advanced-cancer natural killer-cell trial provide additional support for the immune-modulating effects of AGE specifically (as distinct from allicin-yielding raw garlic).
The Lissiman 2014 Cochrane Review — What It Did and Did Not Say
The Cochrane Database of Systematic Reviews published Lissiman, Bhasale, and Cohen's "Garlic for the common cold" in 2014, as an update of the review's 2012 version. The Cochrane methodology is rigorously focused on the strongest study designs (double-blind randomized controlled trials (RCTs) of acceptable quality) and applies strict inclusion criteria.
The 2014 Cochrane review identified eight trials as potentially relevant, of which only 1 (the Josling 2001 trial) met the inclusion criteria. The review's conclusion is often summarized in the popular press as "there is no evidence that garlic prevents the common cold," but the actual Cochrane wording is more nuanced: "There is insufficient clinical trial evidence regarding the effects of garlic in preventing or treating the common cold. A single trial suggested that garlic may prevent occurrences of the common cold but more studies are needed to validate this finding."
Cochrane's own reading of that one trial: 24 colds in the garlic group versus 65 on placebo, and 111 versus 366 days of illness, but once a cold had started, the number of days to recovery was similar in both groups (4.63 versus 5.63). The trial relied on colds the volunteers reported themselves, though the reviewers judged its randomisation and allocation concealment to be of reasonable quality. Reported adverse effects were rash and odour. The review adds that claims of effectiveness appear to rely largely on poor-quality evidence.
Several points are worth clarifying:
- "Insufficient evidence" is not "evidence of no effect" — the Cochrane reviewers explicitly did not conclude that garlic is ineffective. They concluded that there has not been enough rigorous trial activity to make a strong evidence-based recommendation. The Josling effect was acknowledged as positive but unreplicated.
- The Nantz 2012 trial was not yet included in the 2014 review's primary inclusion set because of differences in design and outcome assessment, but it adds supportive evidence to the bigger picture.
- The pattern of "single positive trial, methodologic concerns, unreplicated effect size" is common in natural-products research in general, because such trials are rarely commercially funded at the scale of drug trials. The Cochrane standard demands replication that the natural-products evidence base often does not contain, but the absence of expensive replication is not equivalent to refutation.
In summary: garlic for cold prevention rests on one trial that met Cochrane's standards and one supportive AGE trial, which falls short of the certainty Cochrane requires, but represents a reasonable low-risk seasonal intervention for adults who wish to try it. The evidence is at least as strong as that for many supplements that are widely used for the same indication.
Allicin → Diallyl Sulfide → Natural Killer Cell Activation Cascade
The molecular mechanism by which garlic enhances anti-viral immunity is partially mapped. The key downstream effector cells are natural killer (NK) cells and γδ-T cells, both of which are part of innate cell-mediated immunity against viral and intracellular bacterial infection.
The cascade:
- Crushing or chewing intact garlic releases allicin, which is rapidly metabolized in the gut and tissue to diallyl sulfide (DAS), diallyl disulfide (DADS), and diallyl trisulfide (DATS), all lipid-soluble organosulfur compounds.
- These polysulfides enter macrophages and dendritic cells in the gut-associated lymphoid tissue (GALT) and in systemic circulation, where they activate signaling pathways including the redox-sensitive Nrf2 antioxidant response and (paradoxically) the immune-activating NF-κB pathway in cell-context-specific ways.
- Activated macrophages secrete IL-12 and other Th1-polarizing cytokines, which enhance natural killer cell activity and prime the γδ-T-cell compartment.
- Natural killer cells circulating through tissue gain enhanced cytotoxic capacity against virally infected target cells, helping clear early-stage respiratory viral infection before it propagates.
- γδ-T cells, which are enriched at mucosal surfaces (including the respiratory and intestinal epithelium), respond to early viral infection with secretion of IFN-γ and direct cytotoxic activity.
The Charron 2015 study (Journal of Nutrition) gave 17 volunteers a meal containing 5 g of raw crushed garlic or a garlic-free meal (crossover design) and measured gene expression in whole blood 3 hours later. Seven genes were turned up after the garlic meal, including genes related to immunity, cell death (apoptosis) and the handling of foreign chemicals; five of the seven were also turned up when a garlic extract was added to cultured immune cells. This is a human in vivo signal consistent with the proposed cellular mechanism.
The Ishikawa 2006 trial in advanced-cancer patients (an immunocompromised population) randomized 50 people with inoperable digestive-system cancer (42 liver, 7 pancreatic, 1 colon) to AGE or placebo for 6 months in double-blind fashion. Both the number of natural killer cells and their activity rose significantly in the AGE group, and no adverse effects were seen in either group; quality of life, the trial's main outcome, did not improve.
γδ-T Cells and Mucosal Surveillance
γδ-T cells are a small but functionally important T-cell subset (typically less than 5% of circulating T cells) that recognize phosphoantigens and stress-induced ligands rather than the classical peptide-MHC complex recognized by αβ-T cells. They are enriched at mucosal surfaces, particularly the gut epithelium and the respiratory tract, where they serve as a rapid-response sentinel population.
The Nantz 2012 demonstration that AGE enhances γδ-T-cell proliferation is mechanistically aligned with the symptom-amelioration finding: a more responsive γδ-T-cell compartment at the respiratory mucosa would be expected to contain early viral infection more effectively and reduce symptom severity even if it does not prevent the initial mucosal exposure that triggers a cold.
The mechanism by which garlic compounds enhance γδ-T-cell function is incompletely understood. Hypothesized pathways include direct stimulation of phosphoantigen-recognizing γδ-T cells by sulfur-containing intermediates, indirect enhancement via macrophage activation and IL-12 secretion, and stress-response signaling via Nrf2 that increases γδ-T-cell ligand presentation on epithelial cells.
Macrophage Activation and Inflammatory Cytokine Modulation
A complicating element of garlic's immune effect is that it is bidirectional — it appears to enhance anti-viral innate immunity (activation of macrophages, natural killer cells, γδ-T cells) while simultaneously suppressing excessive inflammatory cytokine surges (tumor necrosis factor-α, interleukin-6, interleukin-1 beta (IL-1β)). This combination is actually desirable in the context of viral respiratory infection: a strong early innate response that clears the pathogen quickly, followed by appropriate resolution of inflammation that prevents the pro-inflammatory tissue damage and symptom burden of late-stage infection.
The Arreola 2015 review in Journal of Immunology Research summarizes the anti-inflammatory effects of garlic compounds. Laboratory work on macrophages is reported to show that aged garlic extract suppresses lipopolysaccharide-induced tumor necrosis factor-α and interleukin-6 (IL-6) release while preserving IFN-γ signaling.
This pattern is conceptually similar to the rationale for using zinc lozenges, vitamin C, and elderberry during cold and flu illness — modest enhancement of antiviral innate response combined with attenuation of inflammatory symptom-producing cytokines. None of these interventions, including garlic, is a cure for established viral respiratory illness, but they may meaningfully reduce symptom duration and severity when started at first symptoms.
Doses Used in Trials and in Practice for Cold & Flu Season
The amounts below are what the trials gave and what is described in everyday practice:
- In the trials: the Josling trial gave one allicin-containing garlic capsule a day (180 mg of allicin content, per the Cochrane review) for 12 weeks from November to February; the Nantz trial gave 2.56 g/day of aged garlic extract for 90 days; a Russian trial in children gave a 300 mg/day long-acting garlic tablet for 5 months.
- Seasonal use described in practice: aged garlic extract 1,000-2,000 mg/day taken daily through respiratory virus season (October through March in the temperate Northern Hemisphere).
- At first cold symptoms (practitioner use): some practitioners describe increasing to 2-3 g/day of AGE or 3-4 cloves of raw crushed garlic per day, and the "crush and wait" method (see Garlic main page) to maximize allicin yield at the start of acute symptoms.
- Combination with other respiratory-virus supports: garlic is often used alongside vitamin C (1-2 g/day), zinc lozenges (acute use), elderberry syrup (acute use), and N-acetylcysteine (NAC, 600-1,200 mg/day for mucolytic effect). See our pages on Elderberry, Vitamin C, and N-acetylcysteine.
- Time to effect: the prevention trials used daily doses across many weeks (the Josling trial was 12 weeks). For acute symptoms, people describe effects within 24-48 hours.
- Duration: use is usually seasonal, through winter; some adults with heavy exposure (healthcare workers, teachers, parents of young children) take it year-round.
For broader context on respiratory virus prevention and immune support, see our Immune Boosting page.
Aged Garlic Extract vs Allicin Powder for Immune Use
For the immune indication specifically, there is a reasonable argument for either preparation:
- Allicin powder (Josling-style) — the original positive prevention trial used this preparation. Higher in transient allicin, which may be the more pathogen-active molecule. Less rigorous mechanism data than AGE has accumulated. Some users find the odor uncomfortable even with enteric-coated tablets.
- Aged garlic extract (Nantz-style) — the more rigorously mechanism-studied preparation. Dominant in S-allyl cysteine and the diallyl-polysulfide metabolites that activate natural killer/γδ-T cell responses. Odorless and well tolerated. Better tolerated for long-term daily use across full cold seasons.
In short: aged garlic extract is the preparation with the more concentrated immune-mechanism data and is described as easier to tolerate over a full winter, while allicin-yielding powdered garlic is the preparation used in the Josling prevention trial.
COVID-Era Caution — What the Evidence Supports and What It Does Not
During the 2020-2022 COVID pandemic, garlic was promoted in some health-and-wellness circles as a preventive or therapeutic intervention against SARS-CoV-2 infection. COVID-19 itself is not covered here, and it is important to be clear that the existing garlic immune-function trial data — Josling 2001, Nantz 2012, and the related literature — do not extend to any specific virus, and they certainly do not extend to a novel pandemic respiratory virus that emerged after those trials were conducted. There is no published high-quality randomized trial evidence that garlic prevents or treats any specific viral respiratory pandemic.
The pandemic-era promotion of garlic was an instance of reach beyond the evidence base. The underlying garlic-and-immune mechanism is real and modestly effective for the heterogeneous mix of viruses that cause the common cold (rhinoviruses, coronaviruses, respiratory syncytial virus, parainfluenza, adenoviruses, etc.), but specific claims about any particular novel virus require trial-level evidence that has not been generated.
The honest position: garlic is a credible component of a general winter-season immune-support strategy for healthy adults. In summary: the garlic trials studied the common cold in healthy people. Garlic is not a substitute for vaccination against influenza or other vaccine-preventable respiratory infections, not a substitute for appropriate medical care of serious respiratory illness, and not a proven intervention for any specific novel virus.
Cautions and Context
- Antiplatelet / anticoagulant interaction — the same bleeding-risk consideration as for the cardiovascular and cholesterol pages applies. A 2000 review of herb–warfarin interactions lists garlic among the herbs that may increase the risk of bleeding or strengthen the effect of warfarin, noting that nearly all of this information comes from laboratory and animal studies or single case reports. The same concern applies to people taking other blood thinners such as clopidogrel, aspirin, or direct oral anticoagulants.
- Surgery / dental procedures — because of the bleeding concern, garlic supplements are commonly stopped at least 7 days before a procedure with bleeding risk.
- Not a substitute for vaccination — garlic does not replace annual influenza vaccination or other indicated vaccines. Immune-support supplements are an adjunct, not a primary preventive intervention.
- Not a substitute for medical care of serious illness — a severe or prolonged respiratory illness, or one with high fever, trouble breathing (dyspnea), chest pain, or confusion (altered mental status), shows signs that hospitals treat as urgent; home supplements do not treat these.
- Pregnancy — dietary garlic is an ordinary food; high-dose supplements carry the bleeding concern described above, which matters most in the third trimester, close to delivery.
- Pediatric use — dietary garlic at culinary doses is an ordinary part of children's food. One small Russian trial has tested a garlic supplement in children: 83 children aged 10-12 took a long-acting garlic tablet (300 mg a day) or placebo for 5 months, and acute respiratory infections were 1.7 times less common in the garlic group; an earlier open study in 172 children aged 7-16 (600 mg a day) reported no stomach or bowel side effects (Andrianova 2003).
- Immunocompromised patients — for patients on systemic immunosuppression (organ transplant, biologic agents for autoimmune disease, active cancer chemotherapy), the bidirectional effect on innate immunity may interact with the targeted immunosuppression in unpredictable ways.
- Realistic expectations — even in the best trial (Josling), the absolute risk reduction in colds was meaningful but not heroic. The trials reported fewer and milder colds, not their abolition.
Key Research Papers
- Josling P (2001). Preventing the common cold with a garlic supplement: a double-blind, placebo-controlled survey. Advances in Therapy 18:189-193. — PubMed PMID: 11697022
- Lissiman E, Bhasale AL, Cohen M (2014). Garlic for the common cold. Cochrane Database of Systematic Reviews CD006206. — PubMed PMID: 25386977
- Nantz MP, Rowe CA, Muller CE, Creasy RA, Stanilka JM, Percival SS (2012). Supplementation with aged garlic extract improves both NK and γδ-T cell function and reduces the severity of cold and flu symptoms: a randomized, double-blind, placebo-controlled nutrition intervention. Clinical Nutrition 31(3):337-344. — PubMed PMID: 22280901
- Percival SS (2016). Aged garlic extract modifies human immunity. Journal of Nutrition 146:433S-436S. — PubMed PMID: 26764332
- Kyo E, Uda N, Kasuga S, Itakura Y (2001). Immunomodulatory effects of aged garlic extract. Journal of Nutrition 131:1075S-1079S. — PubMed
- Ishikawa H, Saeki T, Otani T et al. (2006). Aged garlic extract prevents a decline of NK cell number and activity in patients with advanced cancer. Journal of Nutrition 136:816S-820S. — PubMed PMID: 16484572
- Charron CS, Dawson HD, Albaugh GP, Solverson PM, Vinyard BT, Solano-Aguilar GI, Molokin A, Novotny JA (2015). A single meal containing raw, crushed garlic influences expression of immunity- and cancer-related genes in whole blood of humans. Journal of Nutrition 145(11):2448-2455. — PubMed PMID: 26423732
- Arreola R, Quintero-Fabian S, Lopez-Roa RI et al. (2015). Immunomodulation and anti-inflammatory effects of garlic compounds. Journal of Immunology Research 2015:401630. — PubMed PMID: 25961060
- Andrianova IV, Sobenin IA, Sereda EV, Borodina LI, Studenikin MI (2003). Effect of long-acting garlic tablets "allicor" on the incidence of acute respiratory viral infections in children. Terapevticheskii Arkhiv 75(3):53-56. — PubMed PMID: 12718222
- Salman H, Bergman M, Bessler H, Punsky I, Djaldetti M (1999). Effect of a garlic derivative (alliin) on peripheral blood cell immune responses. International Journal of Immunopharmacology 21:589-597. — PubMed PMID: 10501628
- Lau BH (2001). Suppression of LDL oxidation by garlic. Journal of Nutrition 131(3s):985S-988S. — PubMed PMID: 11238802
- Bayan L, Koulivand PH, Gorji A (2014). Garlic: a review of potential therapeutic effects. Avicenna Journal of Phytomedicine 4:1-14. — PubMed
- Heck AM, DeWitt BA, Lukes AL (2000). Potential interactions between alternative therapies and warfarin. American Journal of Health-System Pharmacy 57(13):1221-1227. — PubMed PMID: 10902065