⚠ Evidence warning: Clinical trials or other evidence do not support the claims that garlic is a reasonable adjunct in borderline patients and alongside a statin, that aged garlic extract can be safely added to a statin with additive plaque-stabilizing benefit, that it is a reasonable single-agent strategy at borderline risk and part of a regimen in statin intolerance, that 480-1,200 mg/day is the dose range for lipid and plaque effects, and that fresh garlic is not an effective monotherapy. This page keeps it as a report of what people, websites or other media say.
Garlic for Cholesterol & Atherosclerosis
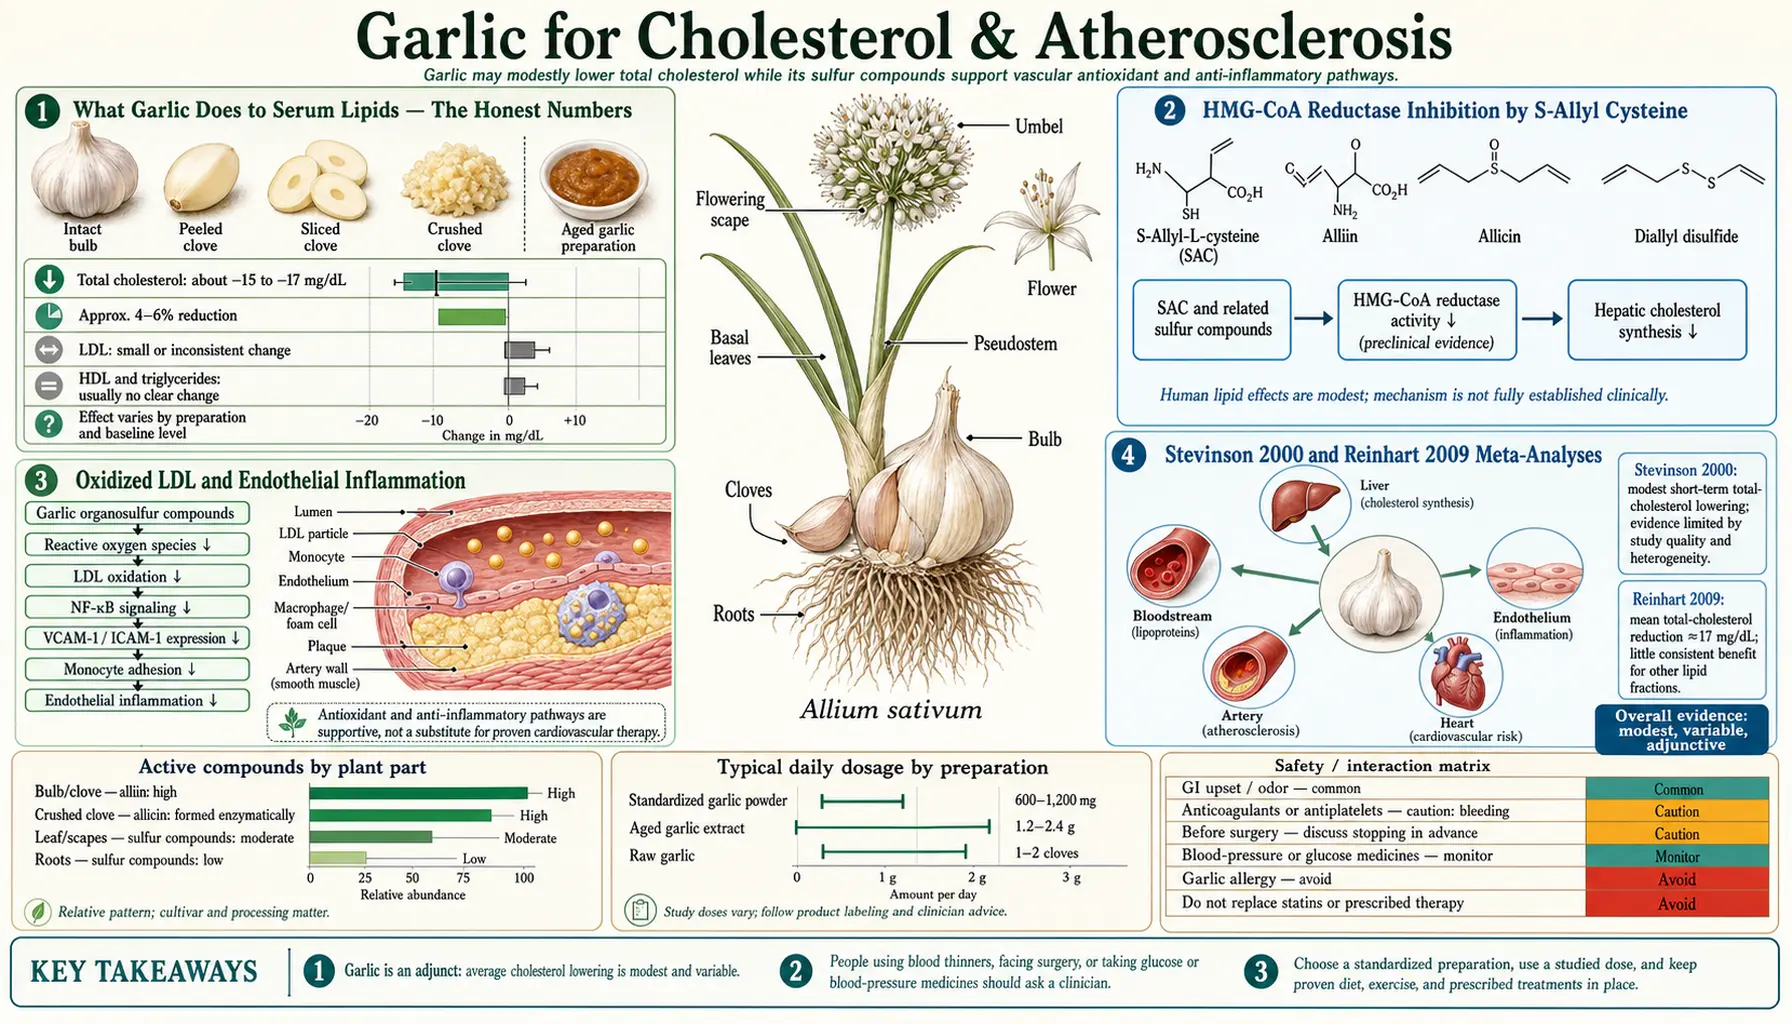
Garlic's effect on serum cholesterol is real but modest — the most rigorous meta-analyses (Stevinson 2000 in Annals of Internal Medicine, Reinhart 2009 in Nutrition Research Reviews) put the average total-cholesterol reduction at roughly 5-10% in hypercholesterolemic adults treated for 12+ weeks. Where garlic gets more interesting is in the harder cardiovascular endpoint of plaque progression as measured by coronary artery calcium (CAC) scoring. The Budoff 2009 randomized trial of an aged-garlic-extract-plus-cofactor formulation showed measurably slower coronary artery calcium accumulation over one year in adults with intermediate cardiovascular risk — an imaging measure closer to heart-disease events than the cholesterol number alone, although events themselves were not measured. This page maps the lipid mechanism (partial HMG-CoA reductase inhibition by S-allyl cysteine), the plaque-progression data, the realistic place of garlic next to statin therapy, and the cautions about garlic in patients already on lipid-lowering drugs.
Table of Contents
- What Garlic Does to Serum Lipids — The Honest Numbers
- HMG-CoA Reductase Inhibition by S-Allyl Cysteine
- Oxidized Low-Density Lipoprotein and Endothelial Inflammation
- Stevinson 2000 and Reinhart 2009 Meta-Analyses
- The Budoff 2009 Coronary Artery Calcium Trial
- Matsumoto 2016: Soft-Plaque Reduction in Metabolic Syndrome
- Garlic vs Statins, and Garlic + Statins
- Preparation Matters — AGE vs Powdered vs Oil
- Where Garlic Fits in the Whole Atherosclerosis-Prevention Picture
- Cautions — Statin Combination, Bleeding, Surgery
- Key Research Papers
- Connections
- Featured Videos
What Garlic Does to Serum Lipids — The Honest Numbers
Modern meta-analyses of randomized garlic-vs-placebo trials in adults with elevated cholesterol consistently report modest reductions in total cholesterol and low-density lipoprotein-cholesterol, smaller and less consistent changes in high-density lipoprotein (HDL) and triglycerides. Representative numbers from the better-quality trial pools:
- Total cholesterol — reduction of 15.7 mg/dL (0.41 mmol/L) in Stevinson 2000, 0.19 mmol/L in Reinhart 2009, and 17 mg/dL in Ried 2013 among people with total cholesterol above 200 mg/dL who took garlic for more than 2 months.
- Low-density lipoprotein-cholesterol — the pooled analyses disagree. Reinhart 2009 (29 trials) and Zeng 2012 (26 trials) found no significant effect on low-density lipoprotein; Ried 2013 (39 trials) found it about 9 mg/dL lower in people with total cholesterol above 200 mg/dL who took garlic for more than 2 months; a 2024 meta-analysis (Piragine 2024) found garlic-family extracts lowered it by about 12 mg/dL, with low certainty of evidence.
- High-density lipoprotein-cholesterol — either no change or small (1-3 mg/dL) increase. Not a major garlic effect.
- Triglycerides — small reduction (~10 mg/dL) in some trials, no change in others. Not a reliable garlic effect.
- Time course — minimum 8 weeks before measurable effect; maximum effect at 12-24 weeks of consistent daily use.
For context, a low-dose statin (rosuvastatin 5 mg or atorvastatin 10 mg) typically produces 30-40% low-density lipoprotein (LDL) reduction. Garlic at standard doses produces about one-fifth to one-quarter of that effect. No garlic trial has shown the mortality reduction that statin trials have demonstrated in people with established cardiovascular disease, a calculated 10-year atherosclerotic cardiovascular disease (ASCVD) risk above 10%, or low-density lipoprotein above 190 mg/dL. The garlic lipid trials enrolled mainly people with raised cholesterol (the trials in Stevinson 2000 required a mean total cholesterol of at least 200 mg/dL). Garlic is a reasonable adjunct for the borderline patient with mild dyslipidemia who is pursuing lifestyle and dietary approaches, and may be a useful add-on for the patient already on a tolerated statin dose whose low-density lipoprotein is close to but not quite at the target.
The more interesting question is whether garlic produces clinical event reduction independent of its modest lipid effect. The plaque-progression trials (Budoff 2009, Matsumoto 2016) suggest the answer is "probably yes" but the evidence base is not at the same level as for statins.
HMG-CoA Reductase Inhibition by S-Allyl Cysteine
The principal molecular mechanism of garlic's lipid effect is partial inhibition of HMG-CoA reductase — the same enzyme inhibited by statin drugs. HMG-CoA reductase catalyzes the rate-limiting step of cholesterol biosynthesis (the conversion of HMG-CoA to mevalonate), and its inhibition produces a compensatory upregulation of hepatic low-density lipoprotein receptors, increased uptake of circulating low-density lipoprotein, and a measurable drop in serum low-density lipoprotein.
The Gebhardt and Beck 1996 paper in Lipids was an early demonstration that garlic-derived organosulfur compounds inhibit cholesterol biosynthesis in primary rat hepatocyte cultures: allicin was the most potent (half-maximal effect at 17 micromolar), followed by diallyl disulfide (64 micromolar) and allyl mercaptan (450 micromolar), with HMG-CoA reductase as the apparent target. The Liu and Yeh 2002 study in the Journal of Nutrition found that the water-soluble garlic compounds S-allyl cysteine (a main compound of aged garlic extract), S-ethyl cysteine and S-propyl cysteine lowered HMG-CoA reductase activity by 30-40% in cultured rat liver cells, by switching the enzyme off (phosphorylation) rather than reducing the amount of enzyme made. The inhibition is partial — in contrast to the near-complete (>90%) inhibition achieved by therapeutic statin concentrations.
The partial inhibition is the mechanistic explanation for the modest clinical effect. Cholesterol biosynthesis is a tightly regulated homeostatic system, and partial inhibition of HMG-CoA reductase produces only partial compensation. A statin pushes the system to near-complete inhibition; garlic does not, and the lipid number reflects the difference. The advantage of partial inhibition is the absence of statin-class adverse effects — no myopathy, no rhabdomyolysis, no significant transaminase elevations, no demonstrated effect on coenzyme Q10 (CoQ10) status — though the corresponding absence of statin-class benefit (mortality reduction in secondary prevention) also has to be acknowledged.
Oxidized Low-Density Lipoprotein and Endothelial Inflammation
A second mechanism by which garlic may slow atherosclerosis — independent of its effect on total low-density lipoprotein concentration — is reduction in low-density lipoprotein oxidation. Oxidized low-density lipoprotein is the species actually taken up by macrophages in the vessel wall to form foam cells, the cellular initiator of atherosclerotic plaque. The total low-density lipoprotein number on a routine lipid panel includes both native (non-oxidized) and oxidized low-density lipoprotein, but only the oxidized fraction is atherogenic in the foam-cell sense.
Garlic compounds, especially the thiol-rich S-allyl cysteine, exhibit substantial antioxidant capacity in cell-based assays and in vivo measures of low-density lipoprotein oxidation susceptibility. The Lau 2001 paper (Journal of Nutrition) presented laboratory evidence that several garlic compounds suppress low-density lipoprotein oxidation in vitro, and noted that short-term garlic supplementation in human subjects increased the resistance of low-density lipoprotein to oxidation. The proposed clinical correlate is reduced expression of vascular cell adhesion molecules (VCAM-1, ICAM-1) on the endothelium, reduced monocyte adhesion, and a less inflammatory vessel wall.
This is part of why a small effect on total low-density lipoprotein can translate to a larger effect on the harder endpoint of plaque progression — the garlic-treated patient may have a similar low-density lipoprotein number to the placebo-treated patient but a lower fraction of that low-density lipoprotein is oxidized and atherogenic. Similar reasoning underlies the strong epidemiologic association between high-polyphenol Mediterranean diets and reduced atherosclerosis despite often unimpressive effects on routine lipid panels.
Stevinson 2000 and Reinhart 2009 Meta-Analyses
Two meta-analyses define the modern understanding of garlic's effect on serum lipids:
Stevinson, Pittler, and Ernst 2000 (Annals of Internal Medicine) pooled 13 randomized, double-blind, placebo-controlled trials of garlic preparations in 796 hypercholesterolemic adults. The pooled mean reduction in total cholesterol was 15.7 mg/dL (0.41 mmol/L) favoring garlic. The authors' conclusion, often quoted in the skeptical-of-garlic literature, was that the effect was "modest" and that "the use of garlic for hypercholesterolemia is of questionable value." The caution rested on a sensitivity analysis: when only the six diet-controlled trials with the highest methodological-quality scores were pooled, the difference shrank to 4.3 mg/dL and was not statistically significant, and the authors judged the robustness of the effect debatable.
Reinhart and colleagues 2009 (Nutrition Research Reviews) pooled 29 randomized placebo-controlled trials (searched through November 2007). Garlic lowered total cholesterol by 0.19 mmol/L and triglycerides by 0.11 mmol/L but had no significant effect on low-density or high-density lipoprotein; the authors concluded that the modest total-cholesterol drop was driven mostly by the triglyceride reduction, without appreciable low-density lipoprotein lowering. They noted that higher baseline total cholesterol and the use of dietary modification may alter the effect. The pattern is consistent with a real but modest pharmacologic effect that requires sustained dosing and is most measurable in the patients with the most room to improve.
The Zeng 2012 meta-analysis (Journal of the Science of Food and Agriculture, 26 trials) found that garlic lowered total cholesterol and triglycerides but did not change low-density lipoprotein, high-density lipoprotein or apolipoprotein B; the effects were larger with long-term use and higher baseline cholesterol, garlic powder and aged garlic extract lowered total cholesterol more, and garlic oil lowered triglycerides more. The Ried 2013 meta-analysis (Nutrition Reviews), the largest of the group with 39 trials of garlic preparations, found total cholesterol 17 mg/dL and low-density lipoprotein 9 mg/dL lower in people with total cholesterol above 200 mg/dL who took garlic for more than 2 months; high-density lipoprotein improved only slightly and triglycerides did not change significantly.
A 2024 meta-analysis (Piragine 2024, Phytotherapy Research) of 22 controlled studies in people with dyslipidemia found that garlic-family (Alliaceae) extracts lowered total cholesterol by about 15 mg/dL and low-density lipoprotein by about 12 mg/dL, and rated the certainty of the evidence as low.
Across these analyses the total-cholesterol effect is consistent, while the low-density lipoprotein effect differs from one analysis to the next; the open question is the clinical importance of the effect, not its existence.
The Budoff 2009 Coronary Artery Calcium Trial
The most clinically interesting garlic trial of the modern era is the Budoff 2009 randomized coronary artery calcium (CAC) progression study, published in Preventive Medicine. Coronary artery calcium scoring by cardiac computed tomography (CT) is the single best-validated imaging biomarker for total atherosclerotic burden and is a strong independent predictor of coronary events. Slowing coronary artery calcium progression in a randomized trial is meaningfully closer to "preventing heart attacks" than reducing a lipid number is.
The trial randomized 65 intermediate-risk adults to a formulation containing aged garlic extract (AGE, 250 mg) plus B6, B12, folate, and L-arginine, vs identical placebo, taken daily for one year. Coronary artery calcium progression was measured by cardiac computed tomography at baseline and 12 months. Results:
- Coronary artery calcium progression (defined as a rise of more than 15% a year) was significantly lower in the AGE-plus-cofactor group than on placebo after adjustment for cardiovascular risk factors.
- Vascular reactivity, measured as fingertip temperature rebound by digital thermal monitoring, improved significantly. Total cholesterol, low-density lipoprotein cholesterol, homocysteine and antibodies to oxidized low-density lipoprotein fell, while high-density lipoprotein, oxidized phospholipids on apolipoprotein B and lipoprotein(a) rose, compared with placebo.
- The intervention was well tolerated with no significant adverse events.
The principal limitation is that the trial used a multi-component formulation (AGE plus B-vitamins plus L-arginine plus folate), so the relative contribution of each component cannot be cleanly separated. The B-vitamin / folate component has its own homocysteine-lowering rationale, and L-arginine is an established nitric oxide (NO) precursor. Later work by the same group tested aged garlic extract alone (Matsumoto 2016, below): it found less low-attenuation plaque but no difference in total plaque, non-calcified plaque or dense calcium, so it does not show identical effects.
The brachial artery flow-mediated dilation evidence comes from a separate, smaller study. Williams and colleagues (2005) gave 15 men with coronary artery disease, already treated with aspirin and a statin, aged garlic extract or placebo for 2 weeks each in crossover order: flow-mediated dilation rose 44% from baseline on aged garlic extract, mainly in men with lower starting values, while markers of oxidant stress did not change significantly. The authors noted that whether this improvement lowers the risk of future heart events remains to be determined.
The clinical implication is important: a one-year intervention with a well-tolerated, low-cost, over-the-counter supplement slowed the progression of measurable atherosclerotic plaque compared with placebo. If this effect is durable over a decade of treatment, it could translate to meaningful reduction in coronary events. The follow-up event data are limited (this was a surrogate-endpoint trial, not a morbidity-and-mortality trial), but the direction is encouraging.
Matsumoto 2016: Soft-Plaque Reduction in Metabolic Syndrome
The Matsumoto 2016 study (Journal of Nutrition) extended the plaque-imaging evidence with a different imaging modality — computed tomography coronary angiography (CCTA) measurement of low-attenuation plaque, which is the soft, lipid-rich, vulnerable plaque most likely to rupture and trigger acute coronary syndromes. The trial assigned 55 metabolic-syndrome patients to aged garlic extract (2,400 mg/day, 27 patients) or placebo (28 patients), with scans about a year apart (354 days on average).
Results showed a statistically significant reduction in low-attenuation plaque in the AGE group: it changed by −1.5% on aged garlic extract versus +0.2% on placebo (P = 0.0049). Total plaque volume, non-calcified plaque and dense calcium (calcified, stable plaque) did not differ between the groups. This is mechanistically interesting because it suggests the AGE effect is concentrated on the inflammatory, lipid-rich, vulnerable component of plaque — precisely the fraction most relevant to acute event risk — rather than on the calcified, stable component.
The Wlosinska 2020 randomized trial (BMC Complementary Medicine and Therapies) provided additional confirmation: 104 patients with a Framingham risk score of 10 or more took aged garlic extract (2,400 mg/day) or placebo for one year (93 analysed). Coronary artery calcium progression changed significantly in favour of aged garlic extract (odds ratio 2.95), as did blood glucose and the inflammatory marker interleukin-6, and systolic blood pressure in the aged garlic group fell from 148 to 140 mmHg; no side effects were reported in either group.
The accumulating CAC and CCTA imaging evidence points in one direction: aged garlic extract, at 250 mg/day (with cofactors) to 2,400 mg/day for about one year, slowed measured coronary plaque progression in adults at intermediate or raised cardiovascular risk, with the clearest effect on the low-attenuation (soft) plaque fraction in Matsumoto 2016.
Garlic vs Statins, and Garlic + Statins
The honest comparison: statins are the most effective pharmacologic intervention for atherosclerotic cardiovascular disease in the history of cardiovascular medicine, with mortality reduction demonstrated in dozens of randomized trials encompassing hundreds of thousands of patients. No trial has tested aged garlic extract as a substitute for a statin. Aged garlic extract is a useful adjunct, not a substitute, in any patient who meets indications for statin therapy under current guidelines. The groups in which current guidelines call for statin therapy:
- Established ASCVD (prior myocardial infarction (MI), ischemic stroke, peripheral artery disease, coronary revascularization) — high-intensity statin is standard of care; garlic has not been tested as a substitute
- Low-density lipoprotein cholesterol (LDL-C) ≥ 190 mg/dL (suspect familial hypercholesterolemia) — high-intensity statin is standard of care; garlic has not been tested as a substitute
- Diabetes age 40-75 with low-density lipoprotein 70-189 — moderate-intensity statin is standard of care
- Primary prevention, 10-year ASCVD risk ≥ 7.5% — statin therapy is recommended in the guidelines
- Borderline risk (5-7.5%) — the guidelines treat statin therapy as optional, guided by risk-enhancing factors; AGE is a reasonable single-agent strategy with home blood pressure (BP) monitoring
- Low risk (<5%) — the guidelines put lifestyle first
For the patient already on a statin, AGE can be safely added (no documented adverse pharmacokinetic interaction with the common statins) and may provide additive plaque-stabilization benefit beyond the statin's lipid effect. Aged garlic extract has no documented adverse pharmacokinetic interaction with the common statins, and in the Williams 2005 study the men were already taking aspirin and a statin when their flow-mediated dilation improved. For people who cannot tolerate statins (muscle pain, liver-enzyme rise, true allergy), the non-statin cholesterol drugs are bempedoic acid, ezetimibe and proprotein convertase subtilisin/kexin type 9 (PCSK9) inhibitors. For the patient who is statin-intolerant, AGE plus these non-statin options becomes part of a reasonable individualized regimen.
For more on the management of atherosclerotic disease as a whole, see our Atherosclerosis page and the Cardiovascular Disease overview.
Preparation Matters — AGE vs Powdered vs Oil
As with the blood-pressure indication, the lipid and atherosclerosis trial evidence is dominated by standardized aged garlic extract. Powdered garlic tablets have produced positive results in some trials (Sobenin 2008, Koscielny 1999) but with substantially more variability, attributable to differences in actual allicin yield from the tablet. Garlic oil has produced inconsistent lipid results in the human trial literature, despite strong animal-model evidence.
Doses and forms used in the trials cited on this page:
- Aged garlic extract: the plaque trials used 250 mg/day with B vitamins, folic acid and L-arginine (Budoff 2009) and 2,400 mg/day (Matsumoto 2016, Wlosinska 2020), each for about one year; in Ried 2013 the cholesterol effect appeared when garlic was taken for more than 2 months. Outside those trials, 480-1,200 mg/day in divided doses is the range described for aged garlic extract, for at least 12 weeks before judging lipid effect and at least 12 months for plaque-progression endpoints.
- Powdered tablets: 600-1,200 mg/day is the range described for powder tablets; allicin yield differs between products, one reason given for their variable results.
- Garlic oil: inconsistent lipid results in human trials; in Zeng 2012 garlic oil lowered triglycerides more than total cholesterol.
- Fresh garlic: a traditional food; the lipid and plaque trials cited here tested supplements, not fresh garlic; it is not an effective monotherapy for lipid or atherosclerosis indications.
Where Garlic Fits in the Whole Atherosclerosis-Prevention Picture
Garlic supplementation is one input among many in a comprehensive cardiovascular-risk-reduction strategy. The largest effect sizes in atherosclerosis prevention come from interventions outside the supplement category — statin therapy in the right candidates, blood-pressure control to target, smoking cessation, weight loss, exercise, and dietary pattern (Mediterranean or DASH). Garlic adds incremental benefit on top of those interventions and is most worthwhile in patients who are already doing the higher-leverage things.
A rough hierarchy of cardiovascular interventions by demonstrated effect size:
- Smoking cessation — the single most consequential cardiovascular intervention; reduces 10-year event risk by 30-50% in smokers within a few years of quitting
- Statin therapy in indicated patients — 25-30% relative risk reduction for major cardiovascular events
- Blood pressure control to target — 20-25% relative risk reduction for stroke and 15-20% for coronary events
- Mediterranean / DASH dietary pattern — 20-30% relative risk reduction in PREDIMED-type trial outcomes
- Regular aerobic exercise (150 min/week) — 20-30% relative risk reduction
- Aged garlic extract — smaller incremental contribution on top of above; meaningful for patients who are already doing the high-leverage things and want additional intervention
- Omega-3 supplementation — small effect (REDUCE-IT showed icosapent ethyl reduced events; over-the-counter (OTC) fish oil has not shown the same)
The patient most likely to derive measurable additional benefit from garlic supplementation is the patient who has already addressed the higher-leverage items and is in the intermediate-risk band with borderline lipid and blood pressure numbers. For the patient who is still smoking, sedentary, and 50 pounds overweight, the marginal benefit of garlic is small compared to what addressing the upstream factors would deliver.
Cautions — Statin Combination, Bleeding, Surgery
- Statin combination — aged garlic extract has no documented adverse interaction with the common statins (atorvastatin, rosuvastatin, simvastatin, pravastatin, lovastatin, pitavastatin). Liver function tests are part of routine statin care regardless of garlic use.
- Antiplatelet / anticoagulant interaction — the dominant safety concern, repeated here from the Cardiovascular & Blood Pressure page. Garlic compounds inhibit platelet aggregation, and combination with warfarin, clopidogrel, prasugrel, ticagrelor, dabigatran, apixaban, rivaroxaban, or chronic high-dose aspirin can increase bleeding risk. The interaction is not an absolute contraindication; with warfarin, the international normalized ratio (INR) blood test measures the blood-thinning effect.
- Surgery / dental procedures — because of the antiplatelet effect, garlic supplements are commonly stopped at least 7 days before a procedure with bleeding risk.
- Fish oil / omega-3 combination — both have mild antiplatelet effects; combining is usually fine in healthy patients but adds to bleeding risk in patients already on other antiplatelet/anticoagulant therapy.
- Saquinavir interaction — garlic reduces saquinavir plasma concentrations, a drop that can weaken this human immunodeficiency virus (HIV) drug.
- Renal function — no documented effect on renal function or hemodynamics; no specific dose adjustment needed in chronic kidney disease.
- Pregnancy — dietary garlic is safe; high-dose supplements are not specifically studied in pregnancy, and the concern raised for the third trimester is bleeding risk.
- Hepatic disease — no documented hepatotoxicity from AGE at standard doses; no specific monitoring required.
- What the trials measured — lipid panels before and after treatment; coronary artery calcium at baseline and 1 year (Budoff 2009); blood pressure; tolerability (gastrointestinal symptoms, odor, taste).
Key Research Papers
- Stevinson C, Pittler MH, Ernst E (2000). Garlic for treating hypercholesterolemia. A meta-analysis of randomized clinical trials. Annals of Internal Medicine 133(6):420-429. — PubMed PMID: 10975959
- Reinhart KM, Talati R, White CM, Coleman CI (2009). The impact of garlic on lipid parameters: a systematic review and meta-analysis. Nutrition Research Reviews 22:39-48. — PubMed PMID: 19555517
- Budoff MJ, Ahmadi N, Gul KM et al. (2009). Aged garlic extract supplemented with B vitamins, folic acid and L-arginine retards the progression of subclinical atherosclerosis: a randomized clinical trial. Preventive Medicine 49:101-107. — PubMed PMID: 19573556
- Williams MJ, Sutherland WH, McCormick MP, Yeoman DJ, de Jong SA (2005). Aged garlic extract improves endothelial function in men with coronary artery disease. Phytotherapy Research 19(4):314-319. — PubMed PMID: 16041725
- Gebhardt R, Beck H (1996). Differential inhibitory effects of garlic-derived organosulfur compounds on cholesterol biosynthesis in primary rat hepatocyte cultures. Lipids 31:1269-1276. — PubMed PMID: 8972460
- Liu L, Yeh YY (2002). S-alk(en)yl cysteines of garlic inhibit cholesterol synthesis by deactivating HMG-CoA reductase in cultured rat hepatocytes. Journal of Nutrition 132(6):1129-1134. — PubMed PMID: 12042421
- Lau BH (2001). Suppression of LDL oxidation by garlic. Journal of Nutrition 131(3s):985S-988S. — PubMed PMID: 11238802
- Sobenin IA, Andrianova IV, Demidova ON, Gorchakova T, Orekhov AN (2008). Lipid-lowering effects of time-released garlic powder tablets in double-blinded placebo-controlled randomized study. Journal of Atherosclerosis and Thrombosis 15:334-338. — PubMed PMID: 19060427
- Koscielny J, Klussendorf D, Latza R et al. (1999). The antiatherosclerotic effect of Allium sativum. Atherosclerosis 144:237-249. — PubMed PMID: 10381297
- Zeng T, Guo FF, Zhang CL, Song FY, Zhao XL, Xie KQ (2012). A meta-analysis of randomized, double-blind, placebo-controlled trials for the effects of garlic on serum lipid profiles. Journal of the Science of Food and Agriculture. — PubMed PMID: 22234974
- Matsumoto S, Nakanishi R, Li D et al. (2016). Aged garlic extract reduces low attenuation plaque in coronary arteries of patients with metabolic syndrome. Journal of Nutrition 146:427S-432S. — PubMed PMID: 26764322
- Wlosinska M, Nilsson AC, Hlebowicz J et al. (2020). The effect of aged garlic extract on the atherosclerotic process — a randomized double-blind placebo-controlled trial. BMC Complementary Medicine and Therapies 20:132. — PubMed PMID: 32349742
- Ried K, Toben C, Fakler P (2013). Effect of garlic on serum lipids: an updated meta-analysis. Nutrition Reviews 71(5):282-299. — PubMed PMID: 23590705
- Piragine E, Malanima MA, Ceccanti C, Guidi L, Martelli A, Lucenteforte E, Calderone V (2024). Alliaceae versus Brassicaceae for dyslipidemia: state of the art and future perspectives. Systematic review and meta-analysis of clinical studies. Phytotherapy Research 38(12):5765-5781. — PubMed PMID: 39343737