⚠ Evidence warning: Clinical trials or other evidence do not support the claims that fenugreek alone can be a first-line trial before metformin and that it adds to drug therapy by a stated 0.3-0.7 points of hemoglobin A1c. This page keeps it as a report of what people, websites or other media say.
Fenugreek for Blood Sugar & Type 2 Diabetes
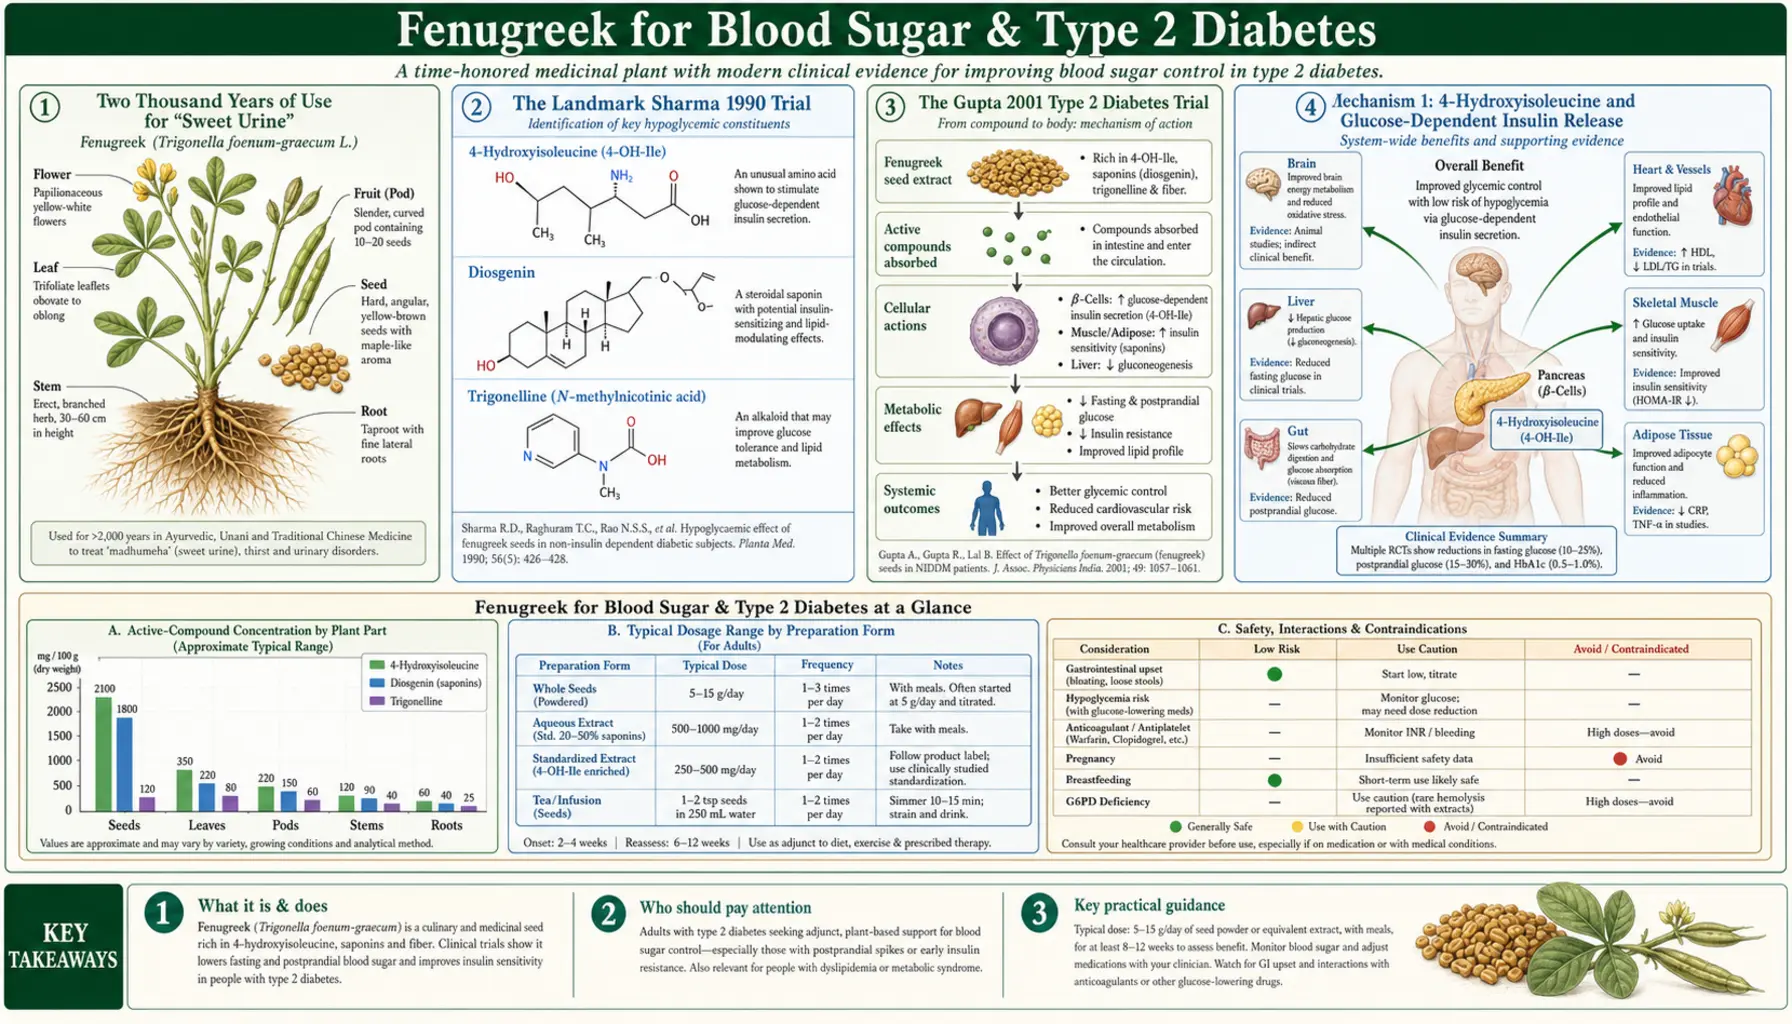
Fenugreek seed has been used continuously in traditional Indian, Egyptian, and Middle Eastern medicine for "sweet urine" (the ancient description of diabetes) for at least two thousand years, and modern trials and pooled analyses report a glucose-lowering effect in people with diabetes, although the authors of a 2014 meta-analysis rated most of those trials as low in methodological quality. A much-cited early study is Sharma et al. 1990, a 10-day crossover study in insulin-dependent (type 1) diabetes that used 100 g of defatted fenugreek seed powder daily and reported 54% less glucose in the urine over 24 hours. The Gupta 2001 trial in 25 people with newly diagnosed type 2 diabetes used 1 g/day of a hydroalcoholic seed extract in a randomized double-blind setting: fasting and 2-hour glucose did not differ from placebo, while the area under the curve for glucose and insulin was significantly lower. The proposed mechanism is a dual action: 4-hydroxyisoleucine, a non-protein amino acid unique to fenugreek, directly stimulates pancreatic beta-cell insulin release in a glucose-dependent manner, while the seed's viscous galactomannan fiber slows gastric emptying and carbohydrate absorption. This page walks through every clinical trial of note, contrasts fenugreek with metformin and sulfonylureas, and reports the doses trials have used, including the 5-25 g/day range, along with the situations where the evidence is strongest and weakest.
Table of Contents
- Two Thousand Years of Use for "Sweet Urine"
- The Sharma 1990 Trial in Type 1 Diabetes
- The Gupta 2001 Type 2 Diabetes Trial
- Mechanism 1: 4-Hydroxyisoleucine and Glucose-Dependent Insulin Release
- Mechanism 2: Galactomannan Fiber and Carbohydrate Absorption
- The 5-25 g/day Dose-Response Curve
- Meta-Analyses: What the Pooled Evidence Says
- Fenugreek and Metformin: An Indirect Comparison and Adjunct Use
- Prediabetes: The Gaddam 2015 Prevention Trial
- Practical Use: Form, Timing, and Monitoring
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Two Thousand Years of Use for "Sweet Urine"
Fenugreek (Trigonella foenum-graecum) is one of the oldest cultivated plants in continuous medicinal use. Charred seeds have been recovered from Tutankhamun's tomb (circa 1320 BCE), and the Ebers Papyrus (circa 1550 BCE) describes a fenugreek preparation for what would today be recognized as a wasting/polyuric condition consistent with diabetes mellitus. In Indian Ayurveda, methi seeds appear in formulations for "madhumeha" (literally "sweet urine") in the Charaka Samhita and Sushruta Samhita, both compiled in the early centuries CE. In Greco-Arab Unani medicine, fenugreek (hulba) was a primary agent for "ziyabetis" — the same Greek root that gave us "diabetes."
Modern interest began in the 1930s and accelerated dramatically after the Sharma group at the National Institute of Nutrition in Hyderabad, India, published their first metabolic ward studies in the late 1980s. Today fenugreek is one of only a handful of botanical agents (alongside berberine, bitter melon, and gymnema) with multiple randomized controlled trials supporting a clinically meaningful glycemic effect.
The Sharma 1990 Trial in Type 1 Diabetes
Sharma, Raghuram, and Rao's 1990 paper in the European Journal of Clinical Nutrition remains the single most-cited fenugreek diabetes trial and the one that put fenugreek on the modern medical map. It was a study of insulin-dependent (type 1) diabetes, not type 2. Isocaloric diets with and without fenugreek were each given in random order for 10 days. The fenugreek diet used 100 g of defatted fenugreek seed powder, divided into two equal doses and served at lunch and dinner. The trial table in the 2014 Neelakantan meta-analysis lists it as a crossover in 10 people, with the powder baked into unleavened bread (chapati), and lists two more 1990 Sharma trials of the same 100 g dose in type 2 diabetes: 15 people for 10 days and 5 people for 20 days.
What the 1990 type 1 paper's abstract reports:
- Fasting blood sugar fell significantly and the oral glucose tolerance test (OGTT) improved (the abstract gives no figures for either)
- 24-hour urinary glucose excretion dropped by 54%, consistent with better overall glycemic control
- Serum total cholesterol, low-density lipoprotein (LDL) and very-low-density lipoprotein cholesterol and triglycerides were significantly reduced, while high-density lipoprotein cholesterol stayed unchanged (covered in detail on the Cholesterol page)
Also attributed to this study, but not found in its abstract (the full text could not be read): a newly-diagnosed type 2 population who had not started any oral antidiabetic medication; an eight-week intervention; fasting plasma glucose falling from about 151 mg/dL to about 112 mg/dL, roughly 27% from baseline; a 2-hour postprandial glucose about 30% lower; total cholesterol down 22% and low-density lipoprotein down 33%; its description as the first published evidence of fenugreek's lipid-lowering effect; and no adverse effects beyond mild gastrointestinal distress (flatulence, diarrhea in the first week).
The major practical limitation of the Sharma 1990 trial is the dose. USDA FoodData Central lists a tablespoon of fenugreek seed at 11.1 g, so 100 g/day is about nine tablespoons, an essentially impractical daily intake for free-living patients outside a metabolic ward. The follow-up trials by Sharma and others worked downward from that dose to find the minimum effective intake.
The Gupta 2001 Type 2 Diabetes Trial
The Gupta, Gupta, and Lal trial published in the Journal of the Association of Physicians of India in 2001 used 1 g/day of a hydroalcoholic fenugreek seed extract in a randomized, double-blind, placebo-controlled design over two months in 25 people with newly diagnosed type 2 diabetes (12 on the extract, 13 on usual care and placebo capsules). The comparison of 1 g of this extract with roughly 25 g of whole seed is not stated in the abstract. Results:
- Fasting blood glucose went from 148.3 to 119.9 mg/dL in the fenugreek group and from 137.5 to 113.0 mg/dL in the placebo group; the authors report these as not different
- 2-hour post-glucose blood glucose went from 210.6 to 181.1 mg/dL in the fenugreek group and from 219.9 to 241.6 mg/dL in the placebo group; these too were reported as not different
- Area under the curve for blood glucose and for insulin was significantly lower in the fenugreek group (p < 0.001)
- Homeostatic model assessment of insulin resistance (HOMA-IR) figures showed higher percent insulin sensitivity with fenugreek (112.9 versus 92.2, p < 0.05) and, in the authors' words, a decrease in percent beta-cell secretion. An improvement of approximately 18% is also attributed to this trial but is not in the abstract
- The lower insulin area under the curve is read as consistent with improved insulin sensitivity rather than insulin-secretagogue-like pancreatic stress
- Triglycerides fell and high-density lipoprotein cholesterol rose significantly compared with placebo (p < 0.05). Total cholesterol is not among the changes the abstract lists
- The 2014 Neelakantan meta-analysis notes that 5 of the 12 people on fenugreek had dyspepsia and mild abdominal distention for the first few days, which subsided as treatment continued
The Gupta 2001 paper is often treated as the more practically relevant of the two foundational trials because 1 g of extract daily is achievable without converting a whole diet to fenugreek bread. The Neelakantan meta-analysis found significant glucose reductions for trials of 5 g or more of seed powder and not for trials of low doses (under 2 g) of hydro-alcoholic extract, the group this trial belongs to. Its authors conclude that adjunct use improved glycemic control and decreased insulin resistance in mild type 2 diabetes.
Mechanism 1: 4-Hydroxyisoleucine and Glucose-Dependent Insulin Release
The most distinctive feature of fenugreek's glycemic mechanism is the non-protein amino acid 4-hydroxyisoleucine (4-HI), which is present in fenugreek seeds at approximately 0.55% by dry weight and in essentially no other common food in pharmacologically meaningful quantity. Sauvaire and colleagues at the University of Montpellier published the definitive characterization of 4-HI's insulinotropic effect in Diabetes in 1998. Their isolated rat and human pancreatic islet studies demonstrated:
- 4-HI directly stimulates pancreatic beta-cell insulin secretion in vitro
- The stimulation is strictly glucose-dependent — 4-HI amplifies insulin release at supranormal glucose concentrations (6.6-16.7 mmol/L) but is ineffective at low (3 mmol/L) or basal (5 mmol/L) glucose
- The effect is dose-dependent across a physiologically relevant concentration range
- The mechanism is mediated by a direct effect on the beta cell, independent of the autonomic nervous system or gastrointestinal hormones
This glucose-dependent mechanism is a major clinical advantage over sulfonylurea drugs (glipizide, glyburide, glimepiride), which stimulate insulin release through the K-ATP channel regardless of ambient glucose and therefore carry a real risk of hypoglycemia. 4-HI's glucose-dependent action means fenugreek tends to amplify the normal physiological insulin response to a meal rather than provoke insulin release between meals. This is the same fundamental property that makes the glucagon-like peptide-1 (GLP-1) agonists (liraglutide, semaglutide) and dipeptidyl peptidase-4 (DPP-4) inhibitors (sitagliptin) clinically attractive — effective glucose lowering without iatrogenic hypoglycemia.
The clinical caveat is that 4-HI's effect at typical dietary fenugreek doses is modest. Mechanistically the molecule is interesting; quantitatively, fenugreek delivers far less 4-HI than a therapeutic dose of a pharmaceutical insulin secretagogue, and the bulk of the seed's glycemic effect at typical doses likely comes from the second mechanism — galactomannan fiber.
Mechanism 2: Galactomannan Fiber and Carbohydrate Absorption
Fenugreek seed is about 45.4% dietary fiber, made up of 32% insoluble and 13.3% soluble fiber according to Roberts 2011. The dominant soluble fiber is a viscous galactomannan polysaccharide structurally similar to guar gum, with a mannose:galactose ratio of roughly 1:1. When fenugreek seed is consumed, this galactomannan hydrates in the stomach and forms a viscous gel with two major glycemic consequences:
- Delayed gastric emptying — the viscous gel slows the release of carbohydrate-containing chyme into the small intestine, which flattens the postprandial glucose curve and reduces the magnitude of the peak
- Reduced rate of glucose absorption — even after gastric emptying, the viscous unstirred water layer in the small intestine slows the diffusion of glucose to the brush-border enterocyte transporters (SGLT1 and GLUT2), further attenuating the postprandial glucose excursion
This is fundamentally the same mechanism by which oat beta-glucan, psyllium husk, and guar gum work to attenuate postprandial glucose. Acarbose also lowers the after-meal glucose rise, by a different route: its label calls it an oral alpha-glucosidase inhibitor, a drug that blocks starch-digesting enzymes on the intestinal lining and so delays glucose absorption. The clinical implication is that fenugreek's glycemic effect is dose-dependent and time-dependent in a fiber-typical way — the benefit is described as greatest when the seed is consumed with or just before the carbohydrate-containing meal, and the dose required to see a meaningful effect on fasting glucose and hemoglobin A1c (HbA1c) is in the 10-25 g/day range, which is substantially more than the dose required for the 4-HI insulinotropic effect.
For patients who cannot tolerate the gastrointestinal load of 25 g of whole fenugreek seed daily, two compromises are described: a smaller dose of whole seed combined with other soluble fibers like psyllium or oat, or a standardized fenugreek extract enriched for 4-HI at a much lower daily milligram dose. The latter provides less fiber-based glycemic benefit but is easier to take consistently.
The 5-25 g/day Dose-Response Curve
The 2014 Neelakantan meta-analysis gives the clearest dose picture. Its trials ran from 1 g to 100 g of fenugreek seed a day (median 25 g) and lasted 10 to 84 days (median 30). Significant glucose reductions appeared in trials of 5 g or more of seed powder, and not in trials of low doses (under 2 g) of hydro-alcoholic extract. Two individual trials add data points. Bordia 1997 gave 5 g a day (2.5 g twice daily) for 3 months: fasting and after-meal blood sugar fell significantly in mild type 2 diabetes, the fall in severe cases was slight and not significant, and healthy people showed no change. Ranade 2017 gave 10 g a day of seeds soaked in hot water to 30 people with type 2 diabetes on oral drugs or insulin, against 30 without the seeds: fasting glucose was significantly lower at month 5 (P = 0.0421) and hemoglobin A1c at month 6 (P = 0.0201).
No pooled analysis cited here sets out the finer steps below. They are a rough, commonly stated ladder rather than a published result:
- 1-5 g/day of whole seed — described as an insufficient fiber load to meaningfully affect fasting glucose or hemoglobin A1c in established type 2 diabetes, with possible modest postprandial glucose attenuation if consumed immediately before a high-carbohydrate meal
- 5-10 g/day of whole seed — consistent modest reduction in postprandial glucose; small but measurable reduction in fasting glucose and hemoglobin A1c in some trials; well-tolerated by most patients without major gastrointestinal distress
- 10-25 g/day of whole seed — the dose range described as consistently producing clinically meaningful reductions in fasting glucose (typically 15-30 mg/dL), 2-hour postprandial glucose, and hemoglobin A1c (typically 0.3-0.7 percentage points) in type 2 diabetic patients. Maple-syrup body odor and gastrointestinal effects are expected at this range
- 25-100 g/day of whole seed — the top of the range includes the 100 g/day of defatted powder in the 1990 Sharma studies. Larger effects are described, but this range is essentially impractical outside a research setting, with substantial gastrointestinal distress reported by most patients
- 1 g/day of hydroalcoholic extract (Gupta 2001 dose; products of 500-1,000 mg/day are also described) — said to match roughly 25 g of whole seed for the soluble components with much less fiber load and much better tolerability, although Gupta's abstract does not state an equivalence. Gupta reported lower glucose and insulin area under the curve, with fasting glucose not different from placebo, and the Neelakantan meta-analysis found no significant reduction for low-dose extracts
Trial doses of powder include 5 g twice daily (Gaddam 2015, Hassani 2019). A home pattern reported for whole seed, which no cited trial tested in this form, is 5 g of whole seed twice daily (about one heaping teaspoon, soaked overnight per the canonical 8-12 hour preparation on the main Fenugreek page), rising to 10 g twice daily if tolerated.
Meta-Analyses: What the Pooled Evidence Says
Three papers have long been grouped together here, and they are different kinds of paper. Neelakantan 2014 pooled 10 trials with 278 participants in all. Suksomboon 2011 pooled nine randomized placebo-controlled trials (487 patients) across several herbs and found hemoglobin A1c 1.13 points lower with fenugreek, while noting high heterogeneity. Hassani 2019 is not a review: it is a randomized double-blind trial in 62 people with type 2 diabetes, who took 5 g of fenugreek powder or 5 g of wheat flour twice daily for two months, with significant differences in fasting blood sugar and hemoglobin A1c. The Neelakantan analysis, published in Nutrition Journal, is the most commonly cited of the three. Its authors state that most of the trials were of low methodological quality.
Pooled results from Neelakantan 2014:
- Fasting plasma glucose reduction of 0.96 mmol/L (~17 mg/dL) versus control across the 10 trials
- 2-hour postprandial glucose reduction of 2.19 mmol/L (~39 mg/dL) across 7 trials
- Hemoglobin A1c reduction of 0.85 percentage points, based on only 3 trials
- Effects on fasting and 2-hour glucose were significant only in studies of medium or high doses (5 g/day or more of seed powder) in people with diabetes. The subgroup split was by diabetes status, so the analysis does not address worse baseline glycemic control as such
- Effects were found in people with diabetes and not in people without diabetes. The analysis has no prediabetes group: its only non-diabetic trials were two low-dose extract trials. A smaller but still significant effect in prediabetes or impaired fasting glucose remains a claim this analysis does not report
Newer poolings point the same way for glucose. A 2024 meta-analysis of 19 trials in type 2 diabetes found fasting glucose about 20.32 mg/dL lower, hemoglobin A1c 0.54 points lower and homeostatic model assessment of insulin resistance 0.36 lower, with no significant effect on fasting insulin. A 2023 meta-analysis of 10 randomized trials (706 people) found fasting glucose, 2-hour glucose and hemoglobin A1c lower with no significant change in insulin resistance by the same measure, and reported no liver or kidney toxicity and no severe adverse events, although some studies noted mild gastrointestinal side effects.
For context, a 0.85 percentage point reduction in hemoglobin A1c is in the range of effect seen with low-dose metformin (500 mg/day) or with the addition of a dipeptidyl peptidase-4 inhibitor — clinically meaningful but not on the scale of full-dose metformin (1.5-2.0 g/day) or insulin therapy. The Gupta 2001 authors describe fenugreek as adjunct use; the cited trials do not establish it as a standalone replacement for pharmacological management of established type 2 diabetes.
Fenugreek and Metformin: An Indirect Comparison and Adjunct Use
The comparison with metformin is informative but indirect: the figures below do not come from a head-to-head glucose trial in any cited paper. Metformin at 1.5-2.0 g/day typically reduces hemoglobin A1c by 1.0-1.5 percentage points, fasting glucose by 50-80 mg/dL, and weight by 2-3 kg over 6-12 months. Fenugreek at 10-25 g/day is stated to reduce hemoglobin A1c by 0.3-0.85 points and fasting glucose by 15-30 mg/dL, with neutral or slightly favorable effects on weight.
Mechanistically the two are described as partially complementary — metformin's primary action is hepatic gluconeogenesis suppression and modest peripheral insulin sensitization, while fenugreek's proposed primary actions are pancreatic insulin amplification (4-HI) and carbohydrate absorption modulation (galactomannan). They target different points in the glucose-disposal pathway, which is the biological rationale given for concurrent use. Additive effects when fenugreek is added to existing oral antidiabetic therapy are claimed, but the Bordia 1997 abstract reports no add-on-to-drug analysis. The Ranade 2017 trial did enroll people already on oral drugs or insulin, and reported lower fasting glucose at month 5 and lower hemoglobin A1c at month 6 with added soaked seeds.
Positions stated for different situations, none of them tested by a cited trial:
- Newly-diagnosed type 2 diabetes with hemoglobin A1c 6.5-7.5% — the claim is that fenugreek alone (along with diet and exercise) can be a first-line trial before metformin, particularly for patients reluctant to start medication, with hemoglobin A1c rechecked at 3 months and metformin started if it is still above target, fenugreek continuing as an adjunct
- Established type 2 diabetes on metformin not at target — fenugreek as adjunct is described as biologically rational, with a stated hemoglobin A1c reduction of roughly 0.3-0.7 points
- Type 2 diabetes on insulin — the combined glucose-lowering can reduce the insulin dose needed, so low blood sugar is the concern in the first weeks of adding fenugreek
- Type 2 diabetes on sulfonylurea — concurrent use is theoretically more concerning for hypoglycemia, though the 4-HI glucose-dependent mechanism is described as mitigating this. The risk that remains is additive low blood sugar, which is why sulfonylurea dose reduction comes up in this setting
- Prediabetes — fenugreek is described as preventive nutrition, with the Gaddam 2015 trial reporting lower conversion to diabetes over three years
Prediabetes: The Gaddam 2015 Prevention Trial
The Gaddam 2015 trial in the Journal of Diabetes and Metabolic Disorders is the most important prediabetes-specific fenugreek study and the one that bridges the gap between symptomatic diabetes treatment and primary prevention. It was a single-blind randomized controlled study of 140 men and women aged 30-70 with prediabetes (impaired fasting glucose 100-125 mg/dL or impaired glucose tolerance). The fenugreek group took 5 g twice daily, half an hour before meals, of a debitterized, defatted and deodorized fenugreek fiber product with added vitamins, minerals and amino acids, supplied by a pharmaceutical firm; this was not whole seed powder. The controls took no fenugreek. Both groups received lifestyle counseling every three months for three years.
The progression-to-diabetes endpoint:
- Cumulative incidence of diabetes at three years — 23.0% in the fenugreek group versus 55.0% in the control group (p < 0.01)
- The paper reports a relative risk reduction of 0.6 at three years, and states that controls had a 4.2 times higher chance of developing diabetes (odds ratio 4.18)
- The paper reports no number needed to treat (NNT)
- Fasting glucose (103.7 to 99.7 mg/dL) and postprandial glucose (142.9 to 129.0 mg/dL) fell significantly in the fenugreek group and did not change significantly in controls. Serum insulin rose significantly in the fenugreek group. Hemoglobin A1c was measured according to the methods section but does not appear in the results table
- Low-density lipoprotein cholesterol fell significantly in the fenugreek group (117.6 to 110.9 mg/dL). Serum total cholesterol, triglycerides and high-density lipoprotein cholesterol stayed comparable in both groups
A second prediabetes trial points the other way. In a 2019 randomized double-blind study, 100 people took a combination of fenugreek, olive leaf polyphenols and bergamot extract or placebo for 6 months (87 finished), and hemoglobin A1c, fasting glucose, insulin, insulin resistance and lipids did not change in either group. Because the product was a mix at an unstated fenugreek dose in the abstract, it does not test fenugreek alone.
For context, the major lifestyle-intervention prediabetes trials (DPP, Finnish DPS) showed risk reductions of approximately 58% with intensive diet-and-exercise counseling, and metformin in DPP showed risk reduction of approximately 31%. The relative risk reduction Gaddam reports is in the same range as the DPP lifestyle intervention. The trial is limited by being a single-center, single-blind study without independent replication at this scale. Dropout in the study group was 13.5%, some of it because of the taste, and a few participants skipped doses or took the powder with flavoring agents, which the authors list as a limitation.
Practical Use: Form, Timing, and Monitoring
What is reported about form, preparation, timing and monitoring when fenugreek is taken for glycemic benefit:
- Form — whole soaked seed is the traditional home form. The 2014 Neelakantan meta-analysis lists the trial forms as powdered fenugreek seeds, debitterized powdered seeds or hydro-alcoholic seed extract, as capsules or in unleavened bread. Powdered fenugreek is sold as the spice in any grocery store. Capsulated standardized extracts are easier to take but provide less fiber-based glycemic benefit. Defatted fenugreek seed powder used in the Sharma 1990 trial is rarely sold commercially; making it at home by extracting whole seed powder with a food-grade solvent and drying is described, with no cited source or safety testing behind it
- Soaking — the canonical 8-12 hour overnight cold-water soak described on the main Fenugreek page is said to maximize extraction of the soluble components without destroying the heat-sensitive 4-HI. The figure that boiling water destroys 60-70% of the soluble actives has no cited source, and the Ranade 2017 trial reported its effect with seeds soaked in hot water
- Timing — soaked-seed water and chewed seeds are traditionally taken first thing in the morning on an empty stomach, described as maximizing 4-HI absorption. For fiber-based postprandial glucose attenuation, a second dose immediately before the largest carbohydrate meal of the day is described as adding benefit
- Monitoring — the schedule usually described is fasting glucose weekly for the first month, then monthly, with hemoglobin A1c at 3 months. For people on insulin or sulfonylureas, more frequent home glucose checks in the first two weeks are the way a combined hypoglycemic effect is detected
- Stated expectations — for a typical type 2 diabetic patient with hemoglobin A1c 7.5-8.5% on metformin alone, adding fenugreek at 10-15 g/day is stated to reduce hemoglobin A1c by approximately 0.3-0.7 percentage points over 3 months, an amount described as meaningful but not transformative
Cautions and Drug Interactions
- Pregnancy — absolute contraindication — fenugreek has documented uterotonic activity (it stimulates uterine smooth muscle contraction) and is traditionally used in late pregnancy in some cultures to induce labor. High-dose fenugreek in early or mid pregnancy carries a theoretical risk of miscarriage. The concern applies to medicinal doses; small culinary amounts (as a spice in curry) are not described as concerning
- Warfarin — international normalized ratio (INR) elevation — case reports document increased international normalized ratio (excessive anticoagulation) in patients stably anticoagulated on warfarin who add fenugreek to their regimen. The mechanism is likely coumarin-related. The precaution described is checking international normalized ratio more frequently for the first 2-4 weeks, with warfarin dose adjustment if needed
- Diabetes medications — additive hypoglycemic effect — combining fenugreek with insulin, sulfonylureas, or meglitinides can produce additive glucose-lowering. The risk of frank hypoglycemia is described as mitigated by 4-HI's glucose-dependent action but is not zero, particularly with sulfonylureas and insulin. More frequent home glucose checks in the first 2-4 weeks are the precaution described
- Maple-syrup body odor (sotolone) — the volatile lactone sotolone is excreted in sweat, urine, and (in lactating mothers) breast milk after fenugreek consumption. It produces a distinct sweet maple-syrup odor that is harmless but surprises patients who were not warned. The effect is dose-dependent and noticeable in most patients at doses above 10 g/day. Some patients consider this a deal-breaker; others find it inoffensive or even pleasant
- Legume allergy — chickpea and peanut cross-reactivity — fenugreek is a legume (family Fabaceae) and shares cross-reactive proteins with chickpea, peanut, soy, and lentil. People with peanut or chickpea allergy are the group this finding concerns
- Gastrointestinal distress — flatulence, abdominal distension, and loose stools are common in the first 1-2 weeks of fenugreek use and typically resolve. Starting at 2-3 g/day and increasing over 2-3 weeks is described as reducing this
- Subclinical hypoglycemia in non-diabetic users — healthy individuals taking fenugreek for non-glycemic purposes (testosterone, lactation) can experience mild hypoglycemic symptoms (lightheadedness, hunger, irritability) particularly if doses are taken on an empty stomach. Taking the dose with food is described as usually resolving this
- What a 2026 review of adverse effects found — a scoping review of 60 articles found mild stomach and bowel discomfort the most common effect. It also lists hypoglycemia, potential low potassium (hypokalemia), allergic reactions (10 case reports or series), a maple-syrup odor in the urine, sweat or skin of infants and mothers, and interactions with certain medications. It reports no deaths attributed to fenugreek
- Liver enzymes — a 2026 meta-analysis of 16 controlled trials (1,171 people) found no significant change in the liver enzymes alanine aminotransferase (ALT) and aspartate aminotransferase (AST)
Key Research Papers
- Sharma RD, Raghuram TC, Rao NS (1990). Effect of fenugreek seeds on blood glucose and serum lipids in type I diabetes. European Journal of Clinical Nutrition 44:301-306. — PubMed PMID: 2194788
- Gupta A, Gupta R, Lal B (2001). Effect of Trigonella foenum-graecum (fenugreek) seeds on glycaemic control and insulin resistance in type 2 diabetes mellitus: a double-blind placebo-controlled study. Journal of the Association of Physicians of India 49:1057-1061. — PubMed PMID: 11868855
- Sauvaire Y et al. (1998). 4-hydroxyisoleucine: a novel amino acid potentiator of insulin secretion. Diabetes 47:206-210. — PubMed PMID: 9519714
- Neelakantan N et al. (2014). Effect of fenugreek (Trigonella foenum-graecum) intake on glycemia: a meta-analysis of clinical trials. Nutrition Journal 13:7. — PubMed PMID: 24438170
- Madar Z et al. (1988). Glucose-lowering effect of fenugreek in non-insulin-dependent diabetics. European Journal of Clinical Nutrition 42:51-54. — PubMed PMID: 3286242
- Ranade M, Mudgalkar N (2017). A simple dietary addition of fenugreek seed leads to the reduction in blood glucose levels: a parallel group, randomized single-blind trial. Ayu 38:24-27. — PubMed PMID: 29861588
- Gaddam A et al. (2015). Role of fenugreek in the prevention of type 2 diabetes mellitus in prediabetes. Journal of Diabetes and Metabolic Disorders 14:74. — PubMed PMID: 26436069
- Bordia A, Verma SK, Srivastava KC (1997). Effect of ginger (Zingiber officinale Rosc.) and fenugreek (Trigonella foenumgraecum L.) on blood lipids, blood sugar and platelet aggregation in patients with coronary artery disease. Prostaglandins, Leukotrienes and Essential Fatty Acids 56:379-384. — PubMed PMID: 9175175
- Geberemeskel GA, Debebe YG, Nguse NA (2019). Antidiabetic Effect of Fenugreek Seed Powder Solution (Trigonella foenum-graecum L.) on Hyperlipidemia in Diabetic Patients. Journal of Diabetes Research 2019:8507453. — PubMed PMID: 31583253
- Hassani SS, Fallahi Arezodar F, Esmaeili SS, Gholami-Fesharaki M (2019). Effect of Fenugreek Use on Fasting Blood Glucose, Glycosylated Hemoglobin, Body Mass Index, Waist Circumference, Blood Pressure and Quality of Life in Patients with Type 2 Diabetes Mellitus: A Randomized, Double-Blinded, Placebo-Controlled Clinical Trials. Galen Medical Journal 8:e1432. — PubMed PMID: 34466512
- Suksomboon N et al. (2011). Meta-analysis of the effect of herbal supplement on glycemic control in type 2 diabetes. Journal of Ethnopharmacology 137:1328-1333. — PubMed PMID: 21843614
- Basch E et al. (2003). Therapeutic applications of fenugreek. Alternative Medicine Review 8:20-27. — PubMed PMID: 12611558
- Roberts KT (2011). The potential of fenugreek (Trigonella foenum-graecum) as a functional food and nutraceutical and its effects on glycemia and lipidemia. Journal of Medicinal Food 14:1485-1489. — PubMed PMID: 21861724
- Vajdi M, Noshadi N, Bonyadian A, Golpour-Hamedani S, Alipour B, Pourteymour Fard Tabrizi F, Abbasalizad-Farhangi M, Askari G (2024). Therapeutic effect of fenugreek supplementation on type 2 diabetes mellitus: A systematic review and meta-analysis of clinical trials. Heliyon 10:e36649. — PubMed PMID: 39286181
- Kim J, Noh W, Kim A, Choi Y, Kim YS (2023). The Effect of Fenugreek in Type 2 Diabetes and Prediabetes: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. International Journal of Molecular Sciences 24:13999. — PubMed PMID: 37762302
- Florentin M, Liberopoulos E, Elisaf MS, Tsimihodimos V (2019). No effect of fenugreek, bergamot and olive leaf extract on glucose homeostasis in patients with prediabetes: a randomized double-blind placebo-controlled study. Archives of Medical Science Atherosclerotic Diseases 4:e162-e166. — PubMed PMID: 31448348
- Amiri Ardekani E, Parvizi MM, Zare R, Mosaffa Jahromi M, Rampp T, Pasalar M (2026). Exploring the Adverse Effects of Fenugreek in Humans: A Scoping Review. Iranian Journal of Medical Sciences 51:4-18. — PubMed PMID: 41625343
- Mohit M, Mahmoudizadeh M, Hashempur MH, Soltani M, Kazemi A (2026). The Effect of Fenugreek (Trigonella foenum-graecum) Supplementation on Liver Function Enzymes; a Systematic Review and Meta-Analysis of Controlled Clinical Trials. Health Science Reports 9:e72960. — PubMed PMID: 42558777
PubMed Topic Searches
Connections
- All Herbs
- Fenugreek Overview
- Fenugreek Benefits Hub
- Fenugreek for Testosterone
- Fenugreek for Lactation
- Fenugreek for Cholesterol
- Berberine
- Bitter Melon
- Gymnema
- Cinnamon
- Chromium
- Magnesium
- Type 2 Diabetes
- Hemoglobin A1C
- Fasting Insulin
- Continuous Glucose Monitor
- Blood Sugar Control
- Fasting
- Metformin — the first-line drug fenugreek is sized against and most often added to.
- History