⚠ Evidence warning: Clinical trials or other evidence do not support the claims that fenugreek modestly but really raises milk supply in mothers who need it, works best in the first weeks, and bridges supply dips such as growth spurts and return to work. This page keeps it as a report of what people, websites or other media say.
Fenugreek for Lactation (Galactagogue)
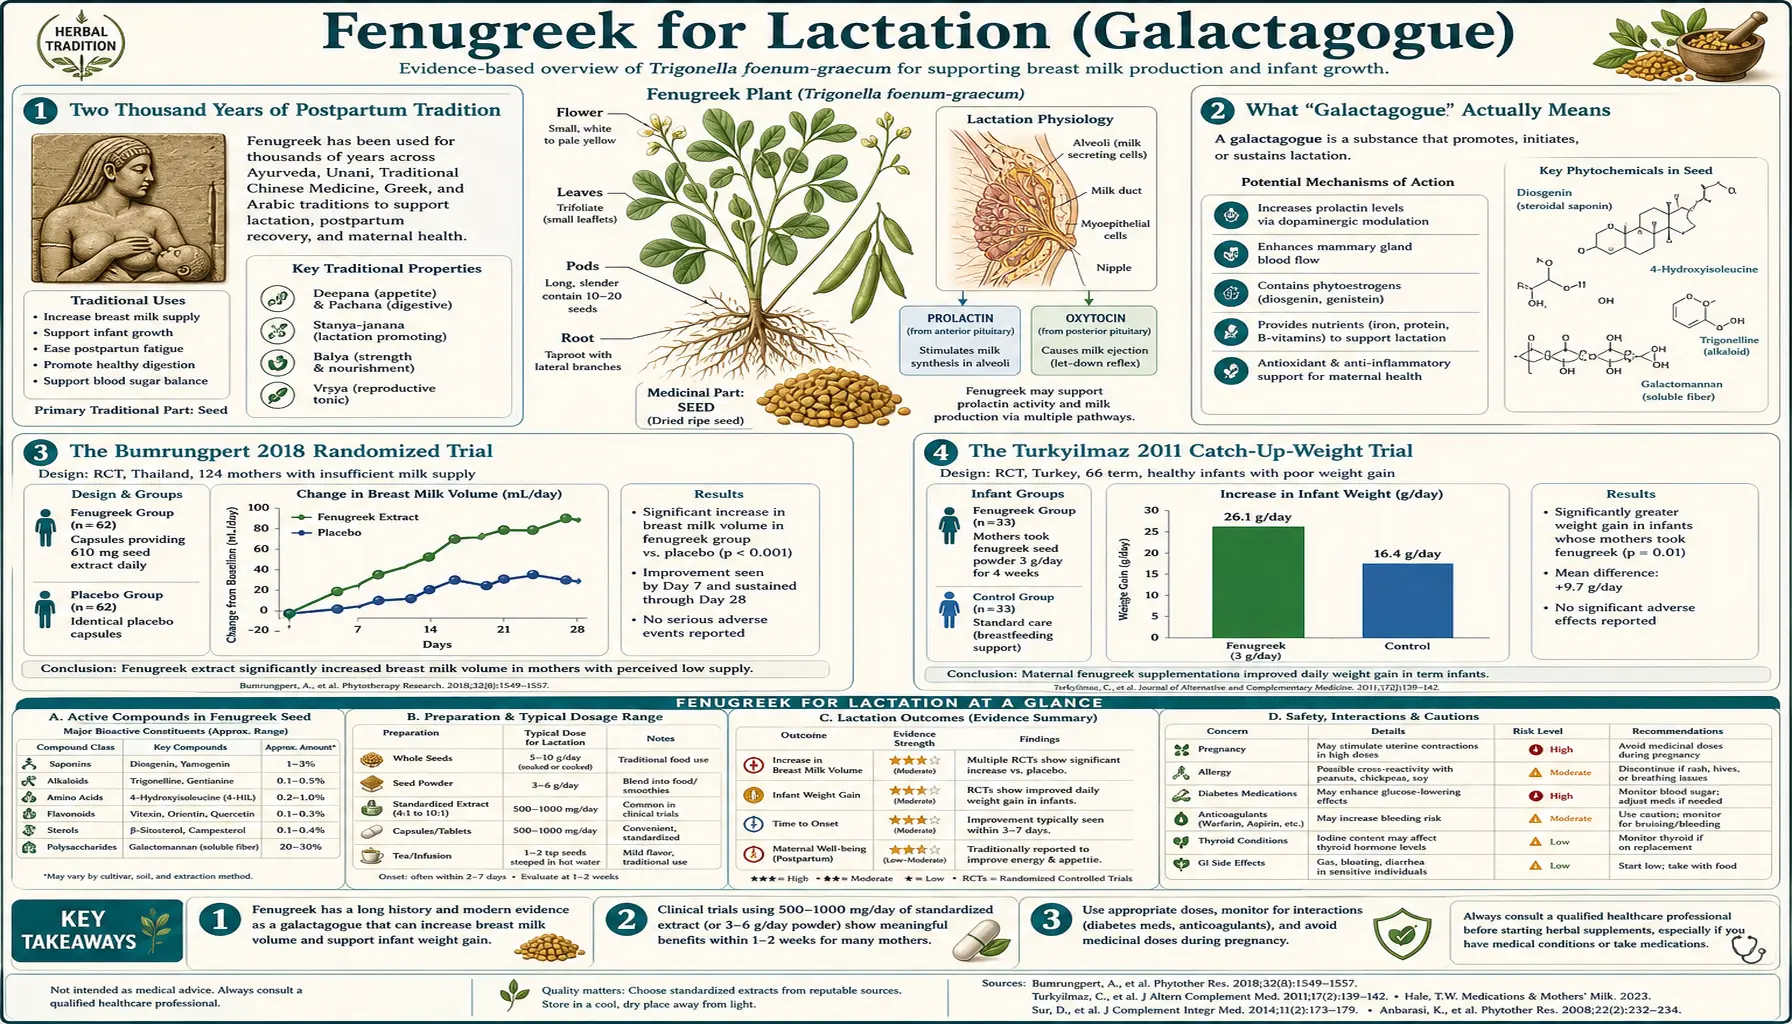
Fenugreek is the single most-used herbal galactagogue (milk-producing agent) on Earth. The tradition stretches back at least two thousand years across the Middle East, North Africa, South Asia, and the Mediterranean — postpartum mothers in Egypt, Iran, India, Greece, and Turkey have historically drunk fenugreek tea or eaten fenugreek-laden porridges in the first weeks after delivery, and the practice has migrated worldwide with the diaspora. The modern randomized trial literature is less voluminous than for fenugreek's diabetes effects, and its results are mixed: the Bumrungpert 2018 double-blind trial in Thai mothers found more milk by week four with a capsule mixing fenugreek, ginger and turmeric, the Turkyilmaz 2011 study found faster catch-up of birth weight in infants of mothers given a herbal tea containing fenugreek, the Khan 2018 network meta-analysis reports a pooled increase in milk, the Reeder 2013 trial found no difference, and the 2020 Cochrane review rates the evidence on natural galactagogues as very low certainty. The mechanism is incompletely understood but appears to involve diosgenin's phytoestrogenic activity on mammary tissue plus possible stimulation of sweat glands (the breast is a modified sweat gland evolutionarily). The most-discussed practical caveat is the maple-syrup body odor that the volatile sotolone metabolite produces in mother and infant sweat and urine — harmless but startling to a family that was not warned, and occasionally mistaken for the dangerous metabolic disorder maple syrup urine disease.
Table of Contents
- Two Thousand Years of Postpartum Tradition
- What "Galactagogue" Actually Means
- The Bumrungpert 2018 Randomized Trial
- The Turkyilmaz 2011 Catch-Up-Weight Trial
- Reeder 2013: Mothers of Preterm Infants
- The Khan 2018 Meta-Analysis
- Mechanism: Diosgenin, Phytoestrogens, and Sweat Glands
- Dose and Form: Tea, Capsule, or Whole Seed
- Timing: When in the Postpartum Course
- The Maple-Syrup Body Odor — Sotolone
- Cautions and Contraindications
- When Fenugreek Will Not Help
- Key Research Papers
- Connections
- Featured Videos
Two Thousand Years of Postpartum Tradition
The use of fenugreek as a postpartum galactagogue is among the most geographically widespread and temporally persistent traditional medical practices on record. Documented uses include:
- Egypt — fenugreek seed (Arabic hilba) tea is given to mothers in the first 40 days postpartum across most of the Nile valley, a practice that traces back at least to the medieval Islamic medical tradition and probably much earlier; charred fenugreek seeds have been found in pharaonic-era archaeological contexts associated with women's health
- India — methi laddu (sweet balls made with fenugreek seed, ghee, jaggery, and various nuts and spices) are a traditional postpartum food across most of North India and many parts of South India; specific formulations vary regionally, but the fenugreek base is consistent
- Turkey, Iran, and the Levant — fenugreek tea, alone or combined with anise and fennel, is a standard component of the postpartum diet, often prescribed by traditional midwives or older female relatives
- Greece and the Mediterranean — fenugreek (Greek moshositaro) appears in Hippocratic and Galenic texts as a women's remedy, with explicit reference to lactation support
- North Africa — fenugreek-spiced porridges and stews are standard postpartum nourishment across Morocco, Tunisia, Algeria, and the Sahel
- The Western diaspora — fenugreek became the dominant lay-recommended galactagogue in North American breastfeeding-support communities in the 1980s and 1990s, with peer-to-peer recommendation through La Leche League and similar networks driving widespread use
This extraordinarily consistent cross-cultural pattern of use is itself a kind of evidence — not in the same category as a randomized controlled trial, but the fact that postpartum mothers in eight different cultures independently arrived at the same plant suggests that the empirical observation of milk-supportive effect is reliable enough to be detected by ordinary mothers and the women supporting them. The modern trial literature has set out to test whether that consistent traditional observation holds up under controlled conditions.
What "Galactagogue" Actually Means
A galactagogue (from Greek gala, milk, plus agogos, leading) is any agent that supports milk production. The category includes pharmaceutical drugs (domperidone, metoclopramide), the various herbal preparations of which fenugreek is the most-used, and the most important and reliable galactagogue of all — effective milk removal by the infant or pump. No agent of any kind, herbal or pharmaceutical, will sustain milk supply in the absence of effective milk removal, because the primary regulation of milk production is local and feedback-based at the breast. Prolactin and oxytocin are the systemic hormones that initiate and let down milk, but the rate-limiting step in established lactation is the autocrine "Feedback Inhibitor of Lactation" (FIL) protein in milk — when the breast is emptied, FIL is removed and milk synthesis upregulates; when the breast stays full, FIL accumulates and milk synthesis downregulates.
The clinical implication is that fenugreek (or any other galactagogue) is most useful in two specific scenarios:
- Initiating or re-initiating milk supply — in the first days to weeks postpartum when supply is still being established, or in relactation after a feeding interruption
- Augmenting an established but inadequate supply — when good feeding/pumping technique is already in place and demand-side issues have been ruled out, but supply remains numerically insufficient
Fenugreek is unlikely to help when the limiting factor is poor latch, inadequate frequency of feeding, retained placental tissue causing high progesterone, or maternal anatomic issues (severe insufficient glandular tissue, prior breast surgery affecting milk ducts). These are demand-side or anatomic problems that pharmacology of any kind cannot easily fix. The Drugs and Lactation Database (LactMed), from the US National Institute of Child Health and Human Development, states that galactogogues "should never replace evaluation and counseling on modifiable factors that affect milk production"; the 2020 Cochrane review names infant suck, latch and feeding frequency among them.
The Bumrungpert 2018 Randomized Trial
The Bumrungpert et al. 2018 study published in Breastfeeding Medicine is a randomized double-blind controlled trial of a mixed herbal capsule; it had no fenugreek-alone group. The design enrolled 50 exclusively breastfeeding mothers and randomized them to two groups:
- Mixed capsule containing fenugreek, ginger and turmeric, three capsules three times daily (25 mothers)
- Placebo (25 mothers)
The intervention duration was four weeks, with milk volume measured using a manual breast pump and recorded for 2 days at baseline, week 2, and week 4.
Results:
- Mixed herbal group — milk volume increased by 49% at week 2 and by 103% at week 4
- Compared with placebo — these increases were greater than in the placebo group (p < 0.05)
- No difference in milk nutrient content between the groups
- No difference in adverse effects between the groups
- The published abstract gives no separate fenugreek, ginger or turmeric result and no infant weight result
The Bumrungpert trial is one of the positive trials cited in lactation reviews. Because the capsule mixed three herbs, the trial cannot show what fenugreek does alone, and its abstract gives no fenugreek dose. The idea that extract preparations may deliver a meaningful effect at a much lower mass intake than the older lay-recommended whole-seed dose (3-6 g/day or more) is not something this trial tested.
The Turkyilmaz 2011 Catch-Up-Weight Trial
The Turkyilmaz et al. 2011 study published in the Journal of Alternative and Complementary Medicine measured both infant weight and breast milk, with milk assessed on the third day after delivery. The design randomly assigned 66 mother-infant pairs to 3 groups of 22: mothers receiving a herbal tea containing fenugreek every day, placebo, and controls.
Results:
- Maximum weight loss after birth was smaller in the fenugreek-tea arm (less postnatal weight loss before milk supply established)
- Catch-up to birth weight happened earlier in the fenugreek-tea arm than in the control and placebo groups (p < 0.05); the figures of median day 7 versus day 11 sometimes given are not in the published abstract
- Measured breast milk volume was significantly higher in the fenugreek-tea arm than in the placebo and control groups (p < 0.05)
- Infants of mothers in the fenugreek-tea arm are said to have been more likely to have regained birth weight by the standard 10-14 day pediatric well-baby visit; the published abstract does not state this
- No adverse events of clinical significance
The trial is small and the tea formulation was not pure fenugreek (it included other traditional galactagogues), but the infant-outcome design is meaningful because faster catch-up to birth weight reduces the clinical pressure for supplementation with formula — which once started in the first week often sets a pattern that ends sustained breastfeeding earlier than the mother intended.
Reeder 2013: Mothers of Preterm Infants
The Reeder, Legrand, and O'Connor-Von 2013 study in Clinical Lactation addressed a more challenging population: mothers of preterm infants in the NICU, where milk supply is famously difficult to establish because the infant cannot directly nurse and the mother must rely on a breast pump. The design was a double-blind placebo-controlled trial in 26 mothers of infants born before 31 weeks. Starting on the fifth day after birth, each took 3 capsules of fenugreek or placebo 3 times a day for 21 days.
Results:
- Milk volume showed no statistical difference between fenugreek and placebo; a 2026 review gives the difference at day 10 as −63.0 mL (95% confidence interval −354.6 to 228.6), rated very low certainty
- Serum prolactin showed no statistical difference between groups
- Adverse effects — none were noted in the mothers or infants
- Statements that maximum daily milk volume was higher on fenugreek, or that the effect was most noticeable in mothers with low supply at baseline, do not appear in the published abstract
Reeder found no effect on prolactin and no effect on milk, so the trial cannot point to a non-prolactin mechanism behind a milk effect. The proposed phytoestrogen / mammary tissue direct effect mechanism discussed below, and the idea that fenugreek and pharmaceutical prolactin-elevating galactagogues (domperidone, metoclopramide) might be combined for additive effect, remain hypotheses this trial did not test.
A 2025 triple-blind trial in 68 mothers of babies born before 32 weeks used capsules of about 500 mg three times a day from the fifth to the fourteenth day after delivery. Milk volume was higher on fenugreek on day 7 (p = 0.017) but not on day 15 (p = 0.073), with no difference in prolactin (p = 0.324) or newborn weight (p = 0.172), and no side effects reported. A 2026 review of 10 trials of herbal galactagogues in mothers of preterm babies found a lack of high-quality trials in this group.
The Khan 2018 Meta-Analysis
The Khan et al. 2018 systematic review and network meta-analysis published in Phytotherapy Research identified five studies with 122 participants receiving fenugreek. Findings:
- Across 4 studies, the network estimate showed a significant increase in breast milk compared with placebo (11.11, 95% confidence interval 6.77 to 15.46)
- The pairwise comparison against placebo, control and reference groups gave a weighted mean difference of 17.79 (95% confidence interval 11.71 to 23.88), and the effect of fenugreek was substantially inferior to torbangun (Coleus amboinicus) and palm date; the 50-100 mL/day figure sometimes quoted is not in the abstract
- Lactation practice holds that the effect is most reliable in mothers in the first 2-4 weeks postpartum and in mothers with marginal baseline supply; the abstract gives no such subgroup result, and LactMed notes some evidence that fenugreek might be more effective in the first few days postpartum than after 2 weeks
- Mothers with adequate baseline supply are said to show a smaller and less consistent effect — consistent with the principle that you cannot easily increase supply beyond what infant demand is establishing
- Heterogeneity across trials was significant, primarily due to different fenugreek preparations, doses, and outcome measurement methods
- The abstract reports no safety results; the maple-syrup body odor, mild gastrointestinal complaints and the more serious reports from other sources are set out under Cautions below
"Modest but real" is how experienced lactation consultants have described the effect empirically for decades, and the Khan meta-analysis reports a pooled increase. Other summaries are more cautious. LactMed states that the effect "may be primarily psychological in humans" and notes that one meta-analysis found a mild effect and another found no good evidence. A 2013 systematic review of herbal galactogogues concluded that "no recommendation is made".
The 2020 Cochrane review of oral galactagogues covered 41 trials with 3005 mothers of healthy term infants. For natural products including fenugreek, milk-volume results from 13 studies could not be pooled because they differed too much (I² = 99%), and the certainty of the evidence was very low. The authors were "very uncertain whether fennel or fenugreek improves infant weight". The side effects reported were minor complaints, such as maple-syrup-smelling urine in mothers and hives (urticaria) in infants.
Mechanism: Diosgenin, Phytoestrogens, and Sweat Glands
The mechanism by which fenugreek supports milk production is incompletely understood, which is honestly typical of botanical lactation research — the basic-science underpinning is much thinner than the clinical-trial signal. Several mechanisms have been proposed:
- Diosgenin and steroidal-saponin phytoestrogen activity on mammary tissue — the steroidal sapogenin diosgenin is structurally similar to estrogen at the level of relevant receptor binding domains, and it appears to bind weakly to estrogen receptors on mammary tissue. Estrogen receptor activation during the lactation phase appears to support mammary tissue proliferation and alveolar function, though excessive estrogen suppresses milk production (which is why estrogen-containing oral contraceptives are usually avoided in the lactation period). The fenugreek effect appears to be a moderate, mammary-localized phytoestrogenic input rather than a systemic hormonal shift
- Modified-sweat-gland argument — embryologically and evolutionarily, the mammary gland is a modified apocrine sweat gland. Fenugreek demonstrably stimulates sweat-gland activity (witness the increased perspiration and the sotolone-driven body odor) and there is a hypothesis that some of the same signaling that increases eccrine and apocrine sweat-gland secretion also increases mammary-gland secretion. This is largely a heuristic argument, not a worked-out molecular mechanism, but it is consistent with the observation that fenugreek-using mothers report increased perspiration along with increased milk supply
- Mild oxytocin-modulating activity — some in-vitro work suggests fenugreek extracts can modulate oxytocin signaling in mammary tissue, which would support let-down and milk transfer rather than synthesis per se. The clinical relevance of this in-vitro signal is unclear
- Galactomannan fiber-mediated improvement in postpartum maternal blood glucose — in mothers with postpartum hyperglycemia (common after gestational diabetes), better glycemic control may support milk supply indirectly. This is a secondary mechanism rather than a primary one
- Sotolone as a chemical signal — sotolone is excreted in milk and may itself signal to the infant in some way that promotes more vigorous nursing, which then upregulates supply via the demand-side mechanism. Speculative
Rat studies add some detail. In nursing rats, fenugreek raised milk output by 16% and pup growth by 11% when the litter was enlarged to 12 pups, and had no effect when the mothers were on a low-protein diet. In rats nursing large litters, it raised plasma insulin by 77.1% and raised oxytocin gene expression in the pituitary gland. These are animal results; whether the same happens in women is not known.
The usual summary in lactation practice is that fenugreek modestly supports milk supply in the population that needs it, there are several plausible mechanism hypotheses, and the certainty of any one mechanism is low. For many mothers and providers, the lack of mechanistic clarity is acceptable given the long traditional record and the mixed modern trial literature.
Dose and Form: Tea, Capsule, or Whole Seed
Preparations across the published literature and lay use include:
- Fenugreek tea — 1-2 teaspoons of whole seed (approximately 3-6 g) steeped in 250 mL of just-off-boil water for 10-15 minutes, consumed three times daily. Total daily fenugreek seed exposure: approximately 10-18 g. This is the traditional preparation across most postpartum cultures
- Fenugreek capsules (powdered seed) — typically 600 mg per capsule; 2-3 capsules three times daily, for a daily dose of 3.5-5.4 g/day. This is the dose range most commonly used in lay practice in North America and Europe
- Fenugreek standardized extract — 200-500 mg three times daily of an extract standardized to a stated saponin or 4-HI content. The Bumrungpert 2018 capsule mixed fenugreek with ginger and turmeric, and its abstract gives no fenugreek dose
- Whole soaked seed — 1 teaspoon (approximately 5 g) of whole seed soaked overnight per the canonical 8-12 hour preparation on the main Fenugreek page, with the seeds chewed in the morning. This is the preparation most commonly used in South Asian postpartum tradition
- Methi laddu (Indian sweet balls) — traditional Indian preparation combining roasted fenugreek seed with ghee, jaggery, almonds, and various spices. Daily intake of 1-2 laddu provides 3-5 g of fenugreek seed plus supportive calories and nutrients during a critical metabolic period
The Academy of Breastfeeding Medicine Clinical Protocol #9 on galactogogues (2018) lists suggested fenugreek amounts of herbal tea, 200 mL three times a day, or 570-600 mg three times a day, for 1-3 weeks, and describes the studies as "most not of high quality; mixed results". Of herbal galactogogues in general it says there is "little or no scientific evidence for their effectiveness or safety". LactMed gives dosages typically used to increase milk supply as 1 to 6 grams daily. In lay practice, doses below 3 g/day are said to produce little noticeable effect, and doses above 8-10 g/day are said to push the maple-syrup body odor and gastrointestinal effects without proportionally more lactation benefit.
Timing: When in the Postpartum Course
Fenugreek is most useful in two specific windows:
- First 2-4 weeks postpartum — the supply-establishment window, when many mothers struggle with marginal supply that has not yet reached the demand-matched plateau. Fenugreek started early (day 3-7 postpartum) and continued through week 4 may help establish robust supply
- During acute supply challenges — e.g., during infant growth spurts, returning to work and pumping, illness affecting feeding frequency, or relactation after a feeding interruption. Fenugreek as short-term support during the challenge often helps bridge to recovery
Fenugreek is less useful as long-term ongoing supplementation in mothers with well-established adequate supply — the body has reached homeostatic regulation and additional pharmacological input adds little. It is also less useful as a "rescue" intervention for fundamentally inadequate milk transfer due to anatomical or latch issues — those are problems of technique and anatomy that lactation support addresses, not pharmacology.
The traditional postpartum-period framework (40 days in Middle Eastern tradition, three months in some South Asian traditions) maps reasonably onto the time when fenugreek is most likely to be useful. Sustained use beyond 3-4 months without clear ongoing benefit is generally described as unnecessary.
The Maple-Syrup Body Odor — Sotolone
The most-discussed and most-startling side effect of fenugreek use is the distinctive maple-syrup body odor that the volatile lactone sotolone (3-hydroxy-4,5-dimethyl-2(5H)-furanone) produces. Sotolone is the same molecule responsible for:
- The characteristic odor of genuine maple syrup
- The flavor of fenugreek-spiced curry
- The sweet aged flavor of certain wines (Sauternes, vin jaune)
- The diagnostic sweet odor in the rare metabolic disorder maple syrup urine disease (MSUD) — sotolone was identified in the urine of patients with the disease and is responsible for its odor; what differs is how it arises, since in that disorder the body cannot properly break down branched-chain amino acids
After fenugreek consumption, sotolone is excreted in:
- Maternal sweat — the mother smells of maple syrup, particularly after exercise
- Maternal urine
- Breast milk
- Infant urine and sweat (because the infant ingests sotolone in breast milk)
The implications:
- Cosmetic — the odor is harmless but startling. Many family members notice it before the mother does (people adapt quickly to their own odors)
- Diagnostic confusion with maple syrup urine disease — the most important clinical concern. A newborn whose mother is taking fenugreek who develops a sweet urine or breath odor may be misdiagnosed as having maple syrup urine disease — a life-threatening disorder that requires immediate dietary intervention. This has happened in published case reports: Korman 2001 describes mothers who took fenugreek during labor and whose newborns had a maple syrup-like odor, leading to a false suspicion of the disease. Knowing about a mother's fenugreek use gives clinicians another explanation to weigh before invasive testing
- Infant tolerance — lay sources describe the sotolone exposure in breast milk as well-tolerated by infants. LactMed states that "limited scientific data exist on the safety of fenugreek in nursing mothers or infants", and the 2020 Cochrane review lists hives (urticaria) in infants among the effects reported across natural galactagogues
- Forewarning the family — mothers describe telling the partner, parents, and pediatrician in advance: "I am taking fenugreek for milk supply. The baby and I may smell like maple syrup. This is expected and not harmful."
Cautions and Contraindications
- Late-pregnancy use — absolute contraindication except for labor induction — fenugreek has documented uterotonic activity. Traditional use for lactation begins after delivery; this activity is the concern with starting it in the third trimester for any other indication. (Specialist obstetric use for term-induction is a separate question)
- Maternal diabetes or hypoglycemia — fenugreek lowers blood glucose; LactMed states this for dosages of about 25 grams or more daily and urges caution with high dosages in diabetes. For postpartum mothers with gestational or pre-existing diabetes, the effect can lower glucose readings and add to the effect of insulin. This is also relevant for mothers with reactive hypoglycemia or those who skip meals while caring for a newborn
- Maternal warfarin or other anticoagulants — LactMed states that fenugreek can interact with warfarin to cause bleeding; the international normalized ratio (INR) is the blood test that tracks warfarin's effect
- Maternal asthma — there are scattered case reports of fenugreek triggering or worsening asthma in sensitive individuals, possibly related to legume cross-reactivity; LactMed lists exacerbation of asthma among reported reactions
- Peanut, chickpea, or other legume allergy — fenugreek is a legume; LactMed states that cross-reaction with chickpeas, peanuts and other legumes is possible, and the Academy of Breastfeeding Medicine protocol notes several reports of severe maternal allergic reactions to fenugreek
- The maple-syrup body odor — per the section above; the diagnostic confusion with maple syrup urine disease is the most consequential issue
- Maternal hypothyroidism — some clinicians note that fenugreek may mildly affect thyroid hormone levels in long-term high-dose use. For mothers on thyroid replacement therapy, those clinicians describe rechecking thyroid-stimulating hormone (TSH) 6-8 weeks after starting sustained fenugreek
- Mild gastrointestinal effects — gas, bloating, and loose stools in the first 1-2 weeks, typically resolving. May be more bothersome in mothers already managing postpartum digestive sensitivity
- Other reported harms — LactMed lists reports of liver toxicity, both with fenugreek alone and in herbal combinations, toxic epidermal necrolysis (a severe skin reaction) in a nursing mother thought to be caused by fenugreek, and a 14% fall in serum potassium. Diarrhea and liver swelling (hepatomegaly) occurred in a woman taking fennel, fenugreek and goat's rue together. In a survey of nursing mothers in the United States, 45% of 85 who had used fenugreek reported an adverse reaction
- Maternal anti-androgenic concerns — the same saponin-mediated effects discussed on the Testosterone page apply in reverse for the rare mother trying to maintain androgen levels. Most mothers do not need to think about this
When Fenugreek Will Not Help
It is just as important to know when fenugreek is unlikely to deliver. In the following situations the supply problem has its own underlying cause, which fenugreek alone is not expected to solve:
- Poor latch — if the infant is not effectively transferring milk at the breast, no galactagogue will sustain supply
- Inadequate feeding frequency — supply is demand-driven; feeding fewer than 8-10 times per 24 hours in the early postpartum period will not sustain robust supply regardless of pharmacology
- Retained placental tissue — high circulating progesterone from retained placental fragments aggressively suppresses milk synthesis. It is a recognized cause when supply suddenly drops in the early postpartum period without other explanation, and it is dealt with in obstetric care
- Severe insufficient glandular tissue (IGT) — some mothers have hypoplastic breast tissue with truly inadequate alveolar mass; no galactagogue will overcome this completely
- Prior breast surgery affecting milk ducts — reduction surgery in particular can sever milk ducts and limit supply ceiling
- Sheehan's syndrome or other postpartum pituitary disorders — rare, and a recognized cause when supply is suddenly absent after delivery, especially with concurrent menstrual or other endocrine signs
- Maternal severe stress, sleep deprivation, dehydration, undernutrition — these limit supply in their own right; fenugreek does not substitute for sleep and food
Key Research Papers
- Bumrungpert A et al. (2018). Effects of fenugreek, ginger, and turmeric supplementation on human milk volume and nutrient content in breastfeeding mothers: a randomized double-blind controlled trial. Breastfeeding Medicine 13:645-650. — PubMed PMID: 30411974
- Khan TM, Wu DB, Dolzhenko AV (2018). Effectiveness of fenugreek as a galactagogue: a network meta-analysis. Phytotherapy Research 32:402-412. — PubMed PMID: 29193352
- Turkyilmaz C et al. (2011). The effect of galactagogue herbal tea on breast milk production and short-term catch-up of birth weight in the first week of life. Journal of Alternative and Complementary Medicine 17:139-142. — PubMed PMID: 21261516
- Reeder C, Legrand A, O'Connor-Von SK (2013). The effect of fenugreek on milk production and prolactin levels in mothers of preterm infants. Clinical Lactation 4:159-165. — doi:10.1891/2158-0782.4.4.159
- Brodribb W; Academy of Breastfeeding Medicine (2018). ABM Clinical Protocol #9: Use of galactogogues in initiating or augmenting maternal milk production. Breastfeeding Medicine 13:307-314. — PubMed PMID: 29902083
- Damanik R, Wahlqvist ML, Wattanapenpaiboon N (2006). Lactagogue effects of Torbangun, a Bataknese traditional cuisine. Asia Pacific Journal of Clinical Nutrition 15:267-274. — PubMed PMID: 16672214
- Sevrin T et al. (2019). Impact of fenugreek on milk production in rodent models of lactation challenge. Nutrients 11:2571. — PubMed PMID: 31653107
- Mortel M, Mehta SD (2013). Systematic review of the efficacy of herbal galactogogues. Journal of Human Lactation 29:154-162. — PubMed PMID: 23468043
- Penagos Tabares F, Bedoya Jaramillo JV, Ruiz-Cortes ZT (2014). Pharmacological overview of galactogogues. Veterinary Medicine International 2014:602894. — PubMed PMID: 25254141
- Sevrin T et al. (2020). Fenugreek stimulates the expression of genes involved in milk synthesis and milk flow through modulation of insulin/GH/IGF-1 axis and oxytocin secretion. Genes (Basel) 11:1208. — PubMed PMID: 33081164
- Podebrad F, Heil M, Reichert S, Mosandl A, Sewell AC, Böhles H (1999). 4,5-dimethyl-3-hydroxy-2[5H]-furanone (sotolone): the odour of maple syrup urine disease. Journal of Inherited Metabolic Disease 22:107-114. — PubMed PMID: 10234605
- Korman SH, Cohen E, Preminger A (2001). Pseudo-maple syrup urine disease due to maternal prenatal ingestion of fenugreek. Journal of Paediatrics and Child Health 37:403-404. — PubMed PMID: 11532065
- Foong SC, Tan ML, Foong WC, Marasco LA, Ho JJ, Ong JH (2020). Oral galactagogues (natural therapies or drugs) for increasing breast milk production in mothers of non-hospitalised term infants. Cochrane Database of Systematic Reviews 5:CD011505. — PubMed PMID: 32421208
- Rouhi M, Hossieni MB, Khodaie L, Mohammad-Alizadeh-Charandabi S, Mirghafourvand M (2025). Investigating the effectiveness of fenugreek on the quantity of breast milk and the level of prolactin in mothers of preterm newborns: a randomized controlled clinical trial. Current Drug Research Reviews 17:471-480. — PubMed PMID: 41239794
- Cragg A, Levene I, Darabi S, Willcox M (2026). Herbal galactagogues to improve breastmilk production and lactation in mothers of preterm babies: a systematic review of clinical trials. European Journal of Clinical Nutrition 80:146-158. — PubMed PMID: 41350450
- Fenugreek. Drugs and Lactation Database (LactMed). Bethesda (MD): National Institute of Child Health and Human Development; 2006-. — PubMed PMID: 30000838
PubMed Topic Searches
Connections
- All Herbs
- Fenugreek Overview
- Fenugreek Benefits Hub
- Fenugreek for Blood Sugar
- Fenugreek for Testosterone
- Fenugreek for Cholesterol
- Fennel (Traditional Galactagogue)
- Anise
- Blessed Thistle
- Goat's Rue
- Turmeric
- Ginger
- Vitamin D3 (Postpartum)
- Iron (Postpartum)
- Iodine (Lactation)
- Bone Broth (Postpartum Nourishment)
- History