⚠ Evidence warning: Clinical trials or other evidence do not support the claims that fenugreek may allow lower statin doses and that fenugreek with fiber and diet can lower low-density lipoprotein cholesterol by 20-30 percent. This page keeps it as a report of what people, websites or other media say.
Fenugreek for Cholesterol & Lipid Profile
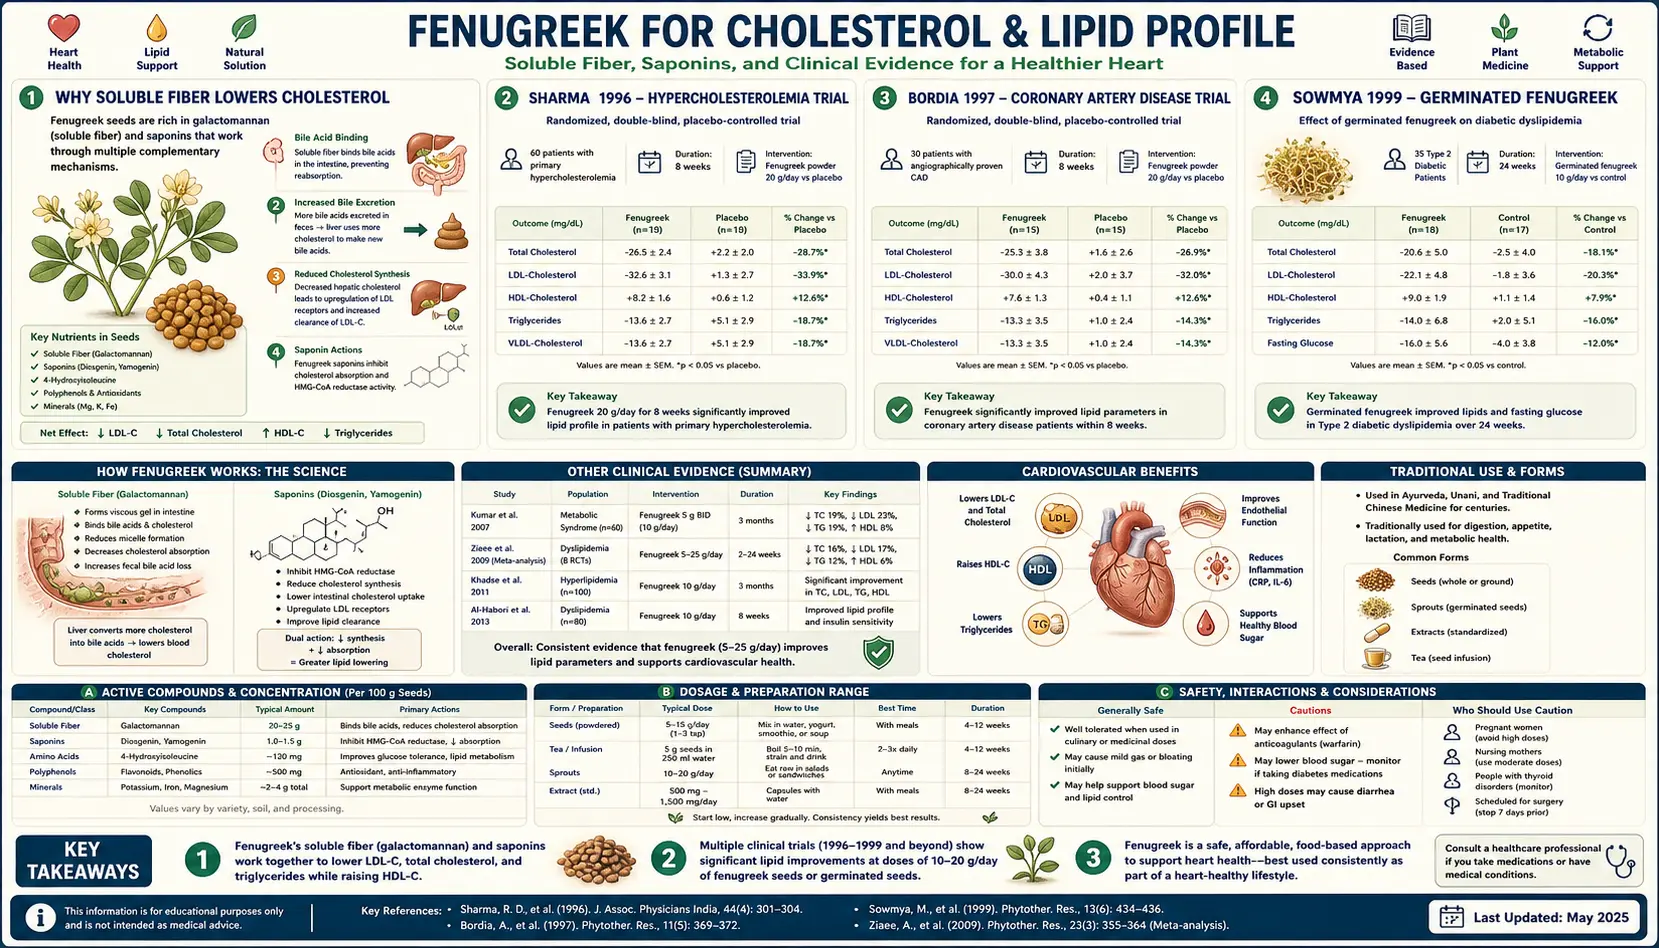
Fenugreek seed is described as lowering serum cholesterol primarily through its soluble galactomannan fiber, which physically binds bile acids in the intestinal lumen and forces the liver to draw down circulating low-density lipoprotein (LDL) cholesterol to synthesize replacement bile. This is mechanistically the same family of action as oat beta-glucan, psyllium husk, and the pharmaceutical bile-acid sequestrants (cholestyramine, colesevelam). A central clinical study is the Sharma 1996 trial in 60 people with non-insulin-dependent (type 2) diabetes, which added 25 g/day of fenugreek seed powder to the diet for 24 weeks and reported significant falls in total cholesterol, low-density lipoprotein and very-low-density lipoprotein cholesterol, and triglycerides. Other trials report lipid changes at 5 g/day in coronary patients with diabetes and at 18 g/day of germinated powder, and no change at 5 g/day in healthy people. The statement that a clear cholesterol effect takes at least 15-25 g/day of whole seed, more than the dose for glycemic benefit and more than most patients will sustain without significant gastrointestinal effects, has not been tested by a trial comparing those doses. Fenugreek is described as an adjunct to oat fiber, psyllium, statin therapy, or dietary cholesterol management, not a stand-alone solution for clinically significant hypercholesterolemia.
Table of Contents
- Why Soluble Fiber Lowers Cholesterol
- The Sharma 1996 Trial in Type 2 Diabetes
- The Bordia 1997 Trial in Coronary Artery Disease and Diabetes
- Sowmya 1999: Germinated Fenugreek
- Geberemeskel 2019: Lipids in Newly Diagnosed Type 2 Diabetes
- The Galactomannan Bile-Acid Binding Mechanism
- Low-Density Lipoprotein Reduction with Preserved High-Density Lipoprotein
- Fenugreek Galactomannan vs Oat Beta-Glucan vs Psyllium
- The Dose Required: What the Trials Used
- Fenugreek and Statin Therapy: An Indirect Comparison
- Practical Use: Combining With Diet and Other Fibers
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Why Soluble Fiber Lowers Cholesterol
Before examining fenugreek specifically, it helps to understand why any soluble fiber lowers serum cholesterol. The body uses cholesterol as the starting material for bile acid synthesis. Bile acids are secreted into the small intestine from the gallbladder after a fatty meal, where they emulsify fats for digestion and absorption. After the digestive task is complete, approximately 95% of the secreted bile acids are reabsorbed in the terminal ileum and returned to the liver via the portal vein — the so-called enterohepatic circulation. This recycling allows the liver to synthesize relatively little new bile acid each day, conserving cholesterol.
Soluble fibers like galactomannan, beta-glucan, and psyllium mucilage disrupt this elegant recycling system. They form a viscous gel in the small intestine that physically traps bile acids and carries them through to the colon and out of the body in stool. The liver, deprived of its recirculating bile acid pool, has no choice but to synthesize new bile acids from circulating low-density lipoprotein cholesterol, drawing down serum low-density lipoprotein concentrations in the process. This is the same mechanism by which the pharmaceutical bile acid sequestrants (cholestyramine, colesevelam, colestipol) lower serum low-density lipoprotein — they bind bile acids in the intestinal lumen with even higher affinity than soluble fibers do.
The mechanism implies certain predictions that the clinical trial data has borne out:
- The effect is dose-dependent and proportional to the amount of viscous soluble fiber consumed
- The effect is specific to low-density lipoprotein cholesterol (and apolipoprotein B-containing particles); high-density lipoprotein (HDL) is typically unaffected or modestly preserved
- The effect requires sustained consumption — bile-acid trapping is an ongoing process, and serum cholesterol returns to baseline within weeks of discontinuation
- The effect is additive with other low-density lipoprotein-lowering interventions (statins, dietary changes, other soluble fibers)
Fenugreek galactomannan fits into this framework alongside oat beta-glucan, psyllium husk, glucomannan (konjac), and the legume polysaccharides — all of which deliver this same mechanism with varying efficiency.
The Sharma 1996 Trial in Type 2 Diabetes
The Sharma et al. 1996 study published in Phytotherapy Research is the foundational clinical evidence for fenugreek's cholesterol-lowering effect. Its 60 participants had non-insulin-dependent (type 2) diabetes. Isocaloric diets without and with fenugreek were given for 7 days and then 24 weeks. The experimental diet contained 25 g of fenugreek seed powder a day. That is a quarter of the 100 g/day of defatted powder in Sharma's 1990 study of type 1 diabetes, and the abstract does not describe the 1996 powder as defatted or list high cholesterol as an entry requirement.
Results at 24 weeks, as the abstract gives them (it states no percentages):
- Total cholesterol — significant reduction
- Low-density lipoprotein cholesterol — significant reduction
- Very-low-density lipoprotein (VLDL) cholesterol — significant reduction
- Triglycerides — significant reduction
Also attributed to this study, but not found in its abstract (the full text could not be read): total cholesterol down approximately 18-30% with the largest effect at the highest baseline cholesterol; low-density lipoprotein down approximately 35%; very-low-density lipoprotein down approximately 27%; triglycerides down approximately 16-30%; high-density lipoprotein preserved or modestly increased; a substantially improved total cholesterol:high-density lipoprotein ratio, described as the most clinically relevant single metric for cardiovascular risk; concurrent improvements in fasting glucose; and no clinically significant adverse events beyond gastrointestinal complaints in the first 1-2 weeks.
A low-density lipoprotein reduction of 35%, if confirmed, would fall in the moderate-intensity statin range. The dose matters for how practical this is. USDA FoodData Central lists a tablespoon of fenugreek seed at 11.1 g, so 25 g/day is a little over two tablespoons and 100 g/day is about nine. The bulk and the maple-syrup body odor and the gastrointestinal effects are described as making the larger amounts difficult to sustain in real-world settings.
The 5-25 g/day range that is said to produce the bulk of the glycemic benefit is also said to produce a smaller but still detectable cholesterol effect — on the order of 5-15% low-density lipoprotein reduction.
The Bordia 1997 Trial in Coronary Artery Disease and Diabetes
The Bordia et al. 1997 placebo-controlled study in Prostaglandins, Leukotrienes and Essential Fatty Acids moved the question into the cardiovascular disease population. It covered healthy people, patients with coronary artery disease, and patients with non-insulin-dependent diabetes with or without coronary artery disease. Fenugreek was given at 2.5 g twice daily (5 g/day) for 3 months and ginger at 4 g daily for 3 months. A figure of 60 patients and random assignment are also attributed to this study; neither is in the abstract.
Findings for fenugreek:
- Healthy people — blood lipids and blood sugar (fasting and after meals) did not change
- Coronary artery disease patients who also had diabetes — total cholesterol and triglycerides fell significantly, with no effect on high-density lipoprotein cholesterol
- Mild non-insulin-dependent diabetes without coronary disease — fasting and after-meal blood sugar fell significantly; in severe cases the fall was slight and not significant
- Platelet aggregation — fenugreek did not affect platelet aggregation, fibrinolytic activity or fibrinogen
- Ginger did not affect blood lipids or blood sugar. At 4 g daily for 3 months it did not affect platelet aggregation in coronary patients; a single 10 g dose did reduce it
The Bordia trial is important because it reports a lipid effect at 5 g/day in a high-risk group while healthy people on the same dose showed none. The idea that fenugreek also has mild antiplatelet activity contributing to cardiovascular benefit is not supported by this trial, whose abstract reports no effect on platelets. The trial did not report hard clinical endpoints (myocardial infarction, stroke, cardiovascular mortality), so the hypothesis that fenugreek may have cardiovascular benefits beyond what serum lipid measurement alone captures remains untested by it.
Sowmya 1999: Germinated Fenugreek
The Sowmya and Rajyalakshmi 1999 study in Plant Foods for Human Nutrition introduced a useful preparation variation: germinated fenugreek seed (the seed sprouted for 48-72 hours before consumption). The hypothesis was that germination would increase bioavailability of certain components and possibly enhance the cholesterol-lowering effect. The design was a one-month trial in 20 adults aged 50-65, in two groups who added one packet a day of germinated powder to any dish of their choice: 12.5 g in one group and 18.0 g in the other.
Results:
- Germination brought distinct changes in the soluble fiber content of the seeds
- The authors describe a cholesterol-lowering effect at both levels; the fall in total cholesterol and low-density lipoprotein cholesterol was significant at 18.0 g
- High-density lipoprotein cholesterol, very-low-density lipoprotein and triglycerides showed no significant change
- The 18.0 g/day dose is below the 25 g/day of Sharma 1996
- Also attributed to this study, but not in its abstract: that participants found the germinated preparation easier to consume than dry-seed powder, with less gastrointestinal distress
The germination concept is practically interesting because it is described as making the higher fenugreek doses more palatable. Home germination is described as straightforward — the seeds are soaked overnight, drained, kept moist in a sprouting jar for 48-72 hours, and consumed when small white sprouts emerge. The sprouts have a milder flavor than dry seeds and can be added to salads, eggs, or soups.
Sprouts also carry a documented food-safety record. Fenugreek sprouts were identified as the common food behind the 2011 French and German outbreaks of Shiga toxin-producing Escherichia coli O104:H4. In the French outbreak, 24 cases followed one community event, 7 of them developed hemolytic uremic syndrome (a toxin-caused illness that damages the blood and kidneys), and fenugreek was the only sprout type independently linked to illness (relative risk 5.1). The German investigation identified sprouts as the most likely vehicle, although the outbreak strain could not be found on seeds from the implicated lot.
Geberemeskel 2019: Lipids in Newly Diagnosed Type 2 Diabetes
The Geberemeskel et al. 2019 trial in the Journal of Diabetes Research studied the lipid profile in 114 people with newly diagnosed type 2 diabetes. The 57 in the treatment group drank a solution of 25 g of fenugreek seed powder twice a day for one month; the 57 controls received metformin. Metformin was the comparator, and there was no placebo.
Results at one month in the fenugreek group, all significant against baseline and against the metformin group:
- Total cholesterol — 219.1 to 189.29 mg/dL, down 13.6%
- Low-density lipoprotein cholesterol — 137.9 to 105.6 mg/dL, down 23.4%
- Triglycerides — 256.1 to 195.8 mg/dL, down 23.53%
- High-density lipoprotein cholesterol — 37.8 to 48.3 mg/dL, up 21.7%
- Lipid levels in the metformin group did not change significantly
- The authors report no adverse effects
Also attributed to this study, but not found in the abstract, which reports lipids only: a significant reduction in fasting blood glucose and hemoglobin A1c (HbA1c), and a significantly improved atherogenic index (total cholesterol:high-density lipoprotein ratio). The paper is often read as a guide to what a typical patient will experience from a fenugreek seed regimen, with effect sizes described as cumulatively notable for a single inexpensive food intervention.
Pooled results are mixed for low-density lipoprotein. A 2024 meta-analysis of 19 trials in type 2 diabetes found total cholesterol about 33.10 mg/dL lower, low-density lipoprotein about 29.14 mg/dL lower and high-density lipoprotein about 5.68 mg/dL higher, with no significant change in triglycerides. A 2023 meta-analysis of 10 randomized trials (706 people) found total cholesterol, triglycerides and high-density lipoprotein improved, with no significant difference in low-density lipoprotein.
The Galactomannan Bile-Acid Binding Mechanism
The dominant soluble fiber in fenugreek seed is galactomannan, a polysaccharide with a backbone of (1-4)-linked beta-D-mannose units bearing single alpha-D-galactose side chains at a ratio of approximately 1:1 (mannose:galactose). This 1:1 ratio is unusually high among commercial galactomannans — guar gum has a 2:1 mannose:galactose ratio, locust bean gum has a 4:1 ratio. The higher galactose substitution in fenugreek galactomannan gives it greater water solubility and a different viscosity profile than its commercial cousins.
The bile-acid binding mechanism unfolds as follows:
- Fenugreek seed is consumed with or near a meal containing fat
- The galactomannan hydrates in the stomach and small intestine, forming a viscous gel
- Cholecystokinin from the duodenum stimulates gallbladder contraction and bile release into the small intestine
- The bile acids (primarily cholic acid and chenodeoxycholic acid and their glycine and taurine conjugates) emulsify dietary fat into micelles for digestion
- Normally, these bile acids would be reabsorbed in the terminal ileum via the sodium-dependent bile acid transporter (ASBT) and returned to the liver
- With galactomannan present, a fraction of the bile acids are physically trapped in the gel matrix and carried distally beyond the absorption window
- The trapped bile acids are excreted in stool, increasing fecal bile acid output by 20-40% in the typical fenugreek-fed individual
- The liver, sensing reduced returning bile acid pool, upregulates CYP7A1 (cholesterol 7-alpha-hydroxylase), the rate-limiting enzyme in bile acid synthesis from cholesterol
- The increased hepatic bile acid synthesis consumes hepatic cholesterol
- To replenish the cholesterol pool, the liver upregulates low-density lipoprotein receptor expression and pulls more low-density lipoprotein particles out of circulation
- Serum low-density lipoprotein cholesterol concentration falls
This is the same mechanism with only minor variations as for oat beta-glucan, psyllium mucilage, and pharmaceutical cholestyramine. The relative efficiency varies — psyllium and cholestyramine bind bile acids more efficiently per gram, while oat beta-glucan and fenugreek galactomannan have a milder taste and more palatable mouth feel.
Low-Density Lipoprotein Reduction with Preserved High-Density Lipoprotein
One of the favorable features of the bile-acid-binding mechanism is that it preferentially affects the atherogenic low-density lipoprotein particle pool while leaving high-density lipoprotein essentially unaffected. Across the fenugreek trials, the typical pattern is:
- Low-density lipoprotein cholesterol — stated as reduced by 10-35% depending on dose and baseline. The largest figure with an abstract behind it here is 23.4% (Geberemeskel 2019). Poolings from 2020 and 2024 found it lower; a 2023 pooling found no significant difference
- Total cholesterol — reduced by 10-30%
- Very-low-density lipoprotein cholesterol and triglycerides — reduced modestly (likely via a different mechanism, possibly involving the soluble-fiber-driven attenuation of postprandial hyperinsulinemia)
- High-density lipoprotein cholesterol — preserved, or in some trials modestly increased
- Total cholesterol:high-density lipoprotein ratio — improved (described as the most cardiovascular-risk-predictive single lipid metric)
- Apolipoprotein B — described as reduced (the underlying atherogenic particle concentration), although no human trial cited here measured it. In rats fed fenugreek galactomannan, liver cells made and secreted fewer apolipoprotein B-containing lipoproteins, mainly very-low-density lipoprotein (Boban 2006)
This is a more favorable lipid profile change than is achieved with some dietary interventions (e.g., low-fat diets, which can reduce both low-density lipoprotein and high-density lipoprotein and worsen the ratio). It is similar in pattern to the effect of moderate-intensity statin therapy, oat beta-glucan, or psyllium husk — all of which preserve high-density lipoprotein while reducing low-density lipoprotein.
Fenugreek Galactomannan vs Oat Beta-Glucan vs Psyllium
A practical question for any patient considering soluble fiber for cholesterol management is how fenugreek compares to its better-established competitors:
- Oat beta-glucan — perhaps the most-studied soluble fiber for cholesterol. The U.S. Food and Drug Administration (FDA) has granted a health claim for oat beta-glucan: 3 g/day reduces total cholesterol by approximately 4% and low-density lipoprotein by approximately 6-8%. Easy to consume as oatmeal or rolled oats; bland, well-tolerated, widely available. The clinical-trial-validated reference standard for botanical soluble-fiber cholesterol management
- Psyllium husk — the most efficient bile-acid binder per gram in the commercial botanical fiber category. 10 g/day reduces low-density lipoprotein by approximately 7-10%; 20 g/day reduces low-density lipoprotein by approximately 12-15%. Available as cheap generic powder. Some patients find the texture unpleasant; too little water when mixing it can cause esophageal obstruction
- Glucomannan (konjac) — very viscous polysaccharide from konjac root; 3-4 g/day reduces low-density lipoprotein by approximately 10%. Often sold as a weight-loss aid. Requires consumption with adequate water for safety
- Fenugreek galactomannan — less efficient per gram than psyllium or glucomannan, comparable to or modestly more effective than oat beta-glucan. Fenugreek seed is 13.3% soluble fiber by weight (Roberts 2011), and 15-25 g/day is stated to reduce low-density lipoprotein by approximately 8-15%. Has the advantage of concurrent glycemic and (in men) androgen-supportive effects from the other active compounds
Where the primary goal is low-density lipoprotein reduction with minimal complications, psyllium husk at 10-20 g/day is described as the most efficient and best-validated option. Where type 2 diabetes or pre-diabetes is also present, fenugreek is described as offering metabolic benefit beyond cholesterol alone. A combination is also described — 5 g of psyllium husk plus 10-15 g of fenugreek seed daily is said to deliver both mechanisms with less of either burden than the full effective dose of each alone.
The Dose Required: What the Trials Used
What the trials report: Bordia 1997 found lipid falls at 5 g/day in coronary patients with diabetes and none at 5 g/day in healthy people. Sowmya 1999 found a significant fall at 18.0 g/day of germinated powder in a small two-dose comparison with 12.5 g/day. Sharma 1996 reported falls at 25 g/day, and Geberemeskel 2019 at 25 g twice a day. No cited trial has compared doses across this range for cholesterol, so what the right dose is remains unknown.
It is also stated that the dose required for a meaningful cholesterol effect is substantially higher than the dose required for the glycemic effect, for this mechanistic reason:
- The glycemic effect is described as driven by 4-hydroxyisoleucine (active at relatively low milligram doses, present in standardized extracts) and to a secondary degree by the fiber-mediated slowing of carbohydrate absorption
- The cholesterol effect is described as driven almost entirely by the bulk fiber load and bile-acid binding, which requires a sustained gram-level intake of soluble fiber to be measurable
A rough dose-response for the cholesterol endpoint, stated without a source behind its steps:
- 1-5 g/day of whole seed — said to have no meaningful cholesterol effect, although Bordia 1997 reported one at 5 g/day in coronary patients with diabetes
- 5-10 g/day of whole seed — small effect, sometimes detectable in larger trials but not robustly meaningful in individual patients
- 10-25 g/day of whole seed — modest reliable cholesterol effect, typically 5-12% low-density lipoprotein reduction
- 25-50 g/day of whole seed — larger effect, on the order of 10-20% low-density lipoprotein reduction, but with significant gastrointestinal burden and substantial maple-syrup body odor
- 100 g/day (the dose of defatted powder in Sharma 1990, a 10-day study in type 1 diabetes) — said to give a 25-35% low-density lipoprotein reduction, but essentially impractical outside a research setting; that study's abstract states no percentage
The practical minimum effective dose is stated as approximately 15 g/day of whole seed — three heaping teaspoons, taken in divided doses with meals — and this is said to be more than most patients will sustain. Fenugreek's place in cholesterol management is therefore described as an adjunct to other measures (statins, oat-based diet, psyllium, dietary saturated-fat reduction), not as a standalone replacement for pharmacotherapy in patients with clinically significant hypercholesterolemia.
Fenugreek and Statin Therapy: An Indirect Comparison
No cited trial compares fenugreek with a statin directly. The statin figures below follow the standard intensity definitions as tabulated in a 2026 review (Minutolo 2026), set beside the figures given for fenugreek:
- Low-intensity statin (simvastatin 10 mg, fluvastatin 20-40 mg, pravastatin 10-20 mg, lovastatin 20 mg) — low-density lipoprotein reduction under 30%
- Moderate-intensity statin (rosuvastatin 5-10 mg, atorvastatin 10-20 mg, simvastatin 20-40 mg) — low-density lipoprotein reduction 30-49%
- High-intensity statin (rosuvastatin 20-40 mg, atorvastatin 40-80 mg) — low-density lipoprotein reduction 50% or more
- Fenugreek 15-25 g/day — low-density lipoprotein reduction stated as approximately 8-15%
- Sharma 1996 fenugreek 25 g/day — significant low-density lipoprotein reduction with no percentage in the abstract; the approximately 35% attributed to it would sit in the moderate-intensity range
A 2020 meta-analysis of 15 randomized trials gives the wider picture for fenugreek. Against controls, fenugreek lowered total cholesterol, low-density lipoprotein and triglycerides and raised high-density lipoprotein, with larger low-density lipoprotein and triglyceride effects in people with diabetes. The four studies with no control group showed no significant change in those three, but a significant rise in high-density lipoprotein.
Statins also do something that fenugreek does not — they reduce cardiovascular events through mechanisms beyond low-density lipoprotein reduction (plaque stabilization, anti-inflammatory effects, endothelial function improvement). The hard-outcome cardiovascular evidence base for statins is unmatched by any nutritional intervention. For people with established atherosclerotic cardiovascular disease, prior myocardial infarction (MI), or stroke, statin therapy is the first-line treatment in cardiology guidelines, and fenugreek is described as an adjunct, not a substitute.
For people with borderline-elevated low-density lipoprotein who do not meet criteria for statin therapy, fenugreek along with dietary modification and other soluble fibers is described as one non-pharmaceutical approach. The risk-benefit balance depends heavily on overall cardiovascular risk profile, family history, and other risk factors.
Practical Use: Combining With Diet and Other Fibers
- A reported fenugreek pattern — 5 g (about one heaping teaspoon) of soaked whole seed in the morning, plus 5-10 g additional with the largest meal of the day, totaling 10-15 g/day. This is described as delivering a modest cholesterol effect plus glycemic and metabolic benefits
- Oat-based breakfast — oatmeal or steel-cut oats with a tablespoon of ground flaxseed and chopped soaked fenugreek seed in the morning is described as a coordinated soluble-fiber load much greater than fenugreek alone
- Psyllium husk — 5 g of psyllium in water before the largest meal of the day plus fenugreek with the meal is described as delivering two complementary soluble fibers
- Dietary changes — reduction of saturated fat intake, replacement of refined carbohydrates with whole grains and legumes, and inclusion of nuts (almonds, walnuts) are described as a coordinated dietary approach with effects larger than any single intervention
- Lipid panel monitoring — the pattern described is a baseline lipid panel, then another at 8-12 weeks. The stated expected effect from fenugreek alone at sustainable doses is 5-15% low-density lipoprotein reduction, with larger effects attributed to concurrent dietary improvement
- People already on statin therapy — the claim is that fenugreek as an adjunct may allow lower statin doses in people who are statin-sensitive (myalgia, hepatic transaminase elevation). No cited trial tests this
- Strict non-pharmaceutical management — the claim is that fenugreek (15-25 g/day) plus oat or psyllium fiber (10-15 g/day) plus dietary saturated-fat reduction plus regular exercise can achieve low-density lipoprotein reductions on the order of 20-30%, comparable to a low-intensity statin and possibly sufficient with modest baseline elevation and an otherwise favorable risk profile. No cited trial tests this combination
Cautions and Drug Interactions
- Pregnancy — absolute contraindication for medicinal doses (uterotonic activity)
- Warfarin interaction — more frequent international normalized ratio (INR) checks for the first month after starting are the precaution described
- Diabetes medication interaction — same caveat as on the Blood Sugar page; combined glucose-lowering may require insulin or sulfonylurea dose reduction
- Reduced absorption of co-administered medications — this is the most under-appreciated soluble-fiber drug interaction. Viscous galactomannan can reduce the absorption of co-administered oral medications by trapping them in the intestinal gel. This is particularly relevant for narrow-therapeutic-index drugs (levothyroxine, warfarin, digoxin, lithium) and for drugs requiring rapid absorption. Spacing fenugreek and other oral medications by at least 2-4 hours is the mitigation described
- Reduced absorption of fat-soluble vitamins — sustained high-dose soluble fiber can modestly reduce absorption of vitamins A, D, E, and K. Not usually clinically meaningful at the doses typically used for cholesterol benefit, but worth noting for patients with established fat-soluble vitamin deficiency or fat malabsorption
- Maple-syrup body odor — per the other Fenugreek Benefits pages, this is the most-discussed cosmetic side effect, more pronounced at the higher doses used for cholesterol benefit
- Gastrointestinal effects — gas, bloating, cramping, and loose stools in the first 1-2 weeks; usually resolves with continued use. Increasing the dose gradually (starting at 5 g/day and rising over 2-3 weeks) is described as reducing this
- Hypoglycemia in non-diabetic patients — possible at the higher fiber doses used for cholesterol benefit, particularly if fenugreek is taken without food
- Legume allergy and cross-reactivity — documented cross-reactivity with peanut, chickpea, soy, and lentil
Key Research Papers
- Sharma RD, Sarkar A, Hazra DK, Misra B, Singh JB, Maheshwari BB, Sharma SK (1996). Hypolipidaemic effect of fenugreek seeds: a chronic study in non-insulin dependent diabetic patients. Phytotherapy Research 10:332-334. — doi:10.1002/(SICI)1099-1573(199606)10:4<332::AID-PTR827>3.0.CO;2-J
- Bordia A, Verma SK, Srivastava KC (1997). Effect of ginger (Zingiber officinale Rosc.) and fenugreek (Trigonella foenumgraecum L.) on blood lipids, blood sugar and platelet aggregation in patients with coronary artery disease. Prostaglandins, Leukotrienes and Essential Fatty Acids 56:379-384. — PubMed PMID: 9175175
- Sowmya P, Rajyalakshmi P (1999). Hypocholesterolemic effect of germinated fenugreek seeds in human subjects. Plant Foods for Human Nutrition 53:359-365. — PubMed PMID: 10540988
- Geberemeskel GA, Debebe YG, Nguse NA (2019). Antidiabetic Effect of Fenugreek Seed Powder Solution (Trigonella foenum-graecum L.) on Hyperlipidemia in Diabetic Patients. Journal of Diabetes Research 2019:8507453. — PubMed PMID: 31583253
- Sharma RD, Raghuram TC, Rao NS (1990). Effect of fenugreek seeds on blood glucose and serum lipids in type I diabetes. European Journal of Clinical Nutrition 44:301-306. — PubMed PMID: 2194788
- Khosla P, Gupta DD, Nagpal RK (1995). Effect of Trigonella foenum graecum (Fenugreek) on blood glucose in normal and diabetic rats. Indian Journal of Physiology and Pharmacology 39:173-174. — PubMed PMID: 7649611
- Belguith-Hadriche O, Bouaziz M, Jamoussi K, El Feki A, Sayadi S, Makni-Ayedi F (2010). Lipid-lowering and antioxidant effects of an ethyl acetate extract of fenugreek seeds in high-cholesterol-fed rats. Journal of Agricultural and Food Chemistry 58:2116-2122. — PubMed PMID: 20108903
- Boban PT, Nambisan B, Sudhakaran PR (2006). Hypolipidaemic effect of chemically different mucilages in rats: a comparative study. British Journal of Nutrition 96:1021-1029. — PubMed PMID: 17181876
- Roberts KT (2011). The potential of fenugreek (Trigonella foenum-graecum) as a functional food and nutraceutical and its effects on glycemia and lipidemia. Journal of Medicinal Food 14:1485-1489. — PubMed PMID: 21861724
- Ramulu P, Giridharan NV, Udayasekhararao P (2011). Hypolipidemic effect of soluble dietary fiber (galactomannan) isolated from fenugreek seeds in WNIN/Gr-Ob obese rats. Indian Journal of Medical Research. — PubMed
- Mukthamba P, Srinivasan K (2016). Hypolipidemic and antioxidant effects of dietary fenugreek (Trigonella foenum-graecum) seeds and garlic (Allium sativum) in high-fat fed rats. Food Bioscience 14:1-9. — doi:10.1016/j.fbio.2016.01.002
- Heshmat-Ghahdarijani K, Mashayekhiasl N, Amerizadeh A, Teimouri Jervekani Z, Sadeghi M (2020). Effect of fenugreek consumption on serum lipid profile: A systematic review and meta-analysis. Phytotherapy Research 34:2230-2245. — PubMed PMID: 32385866
- Vajdi M, Noshadi N, Bonyadian A, Golpour-Hamedani S, Alipour B, Pourteymour Fard Tabrizi F, Abbasalizad-Farhangi M, Askari G (2024). Therapeutic effect of fenugreek supplementation on type 2 diabetes mellitus: A systematic review and meta-analysis of clinical trials. Heliyon 10:e36649. — PubMed PMID: 39286181
- Kim J, Noh W, Kim A, Choi Y, Kim YS (2023). The Effect of Fenugreek in Type 2 Diabetes and Prediabetes: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. International Journal of Molecular Sciences 24:13999. — PubMed PMID: 37762302
- King LA, Nogareda F, Weill FX et al. (2012). Outbreak of Shiga toxin-producing Escherichia coli O104:H4 associated with organic fenugreek sprouts, France, June 2011. Clinical Infectious Diseases 54:1588-1594. — PubMed PMID: 22460976
- Buchholz U, Bernard H, Werber D et al. (2011). German outbreak of Escherichia coli O104:H4 associated with sprouts. New England Journal of Medicine 365:1763-1770. — PubMed PMID: 22029753
- Minutolo R, De Nicola L, Cesaro A et al. (2026). Targeting LDL Across the Whole Spectrum of Chronic Kidney Disease: From Pathophysiology to Novel Treatments. Current Atherosclerosis Reports 28:68. — PubMed PMID: 42400804