⚠ Evidence warning: Clinical trials or other evidence do not support the claims that fennel matches nonsteroidal anti-inflammatory drugs for period pain with better stomach tolerability, that it is a lower-risk alternative for women who tolerate those drugs poorly, that it combines well with a half dose of them and with other period-pain approaches, that the described tea and capsule regimen eases period pain, and that trans-anethole binds the estrogen receptor at the stated strength. This page keeps it as a report of what people, websites or other media say.
Fennel for Menstrual and Menopausal Symptoms
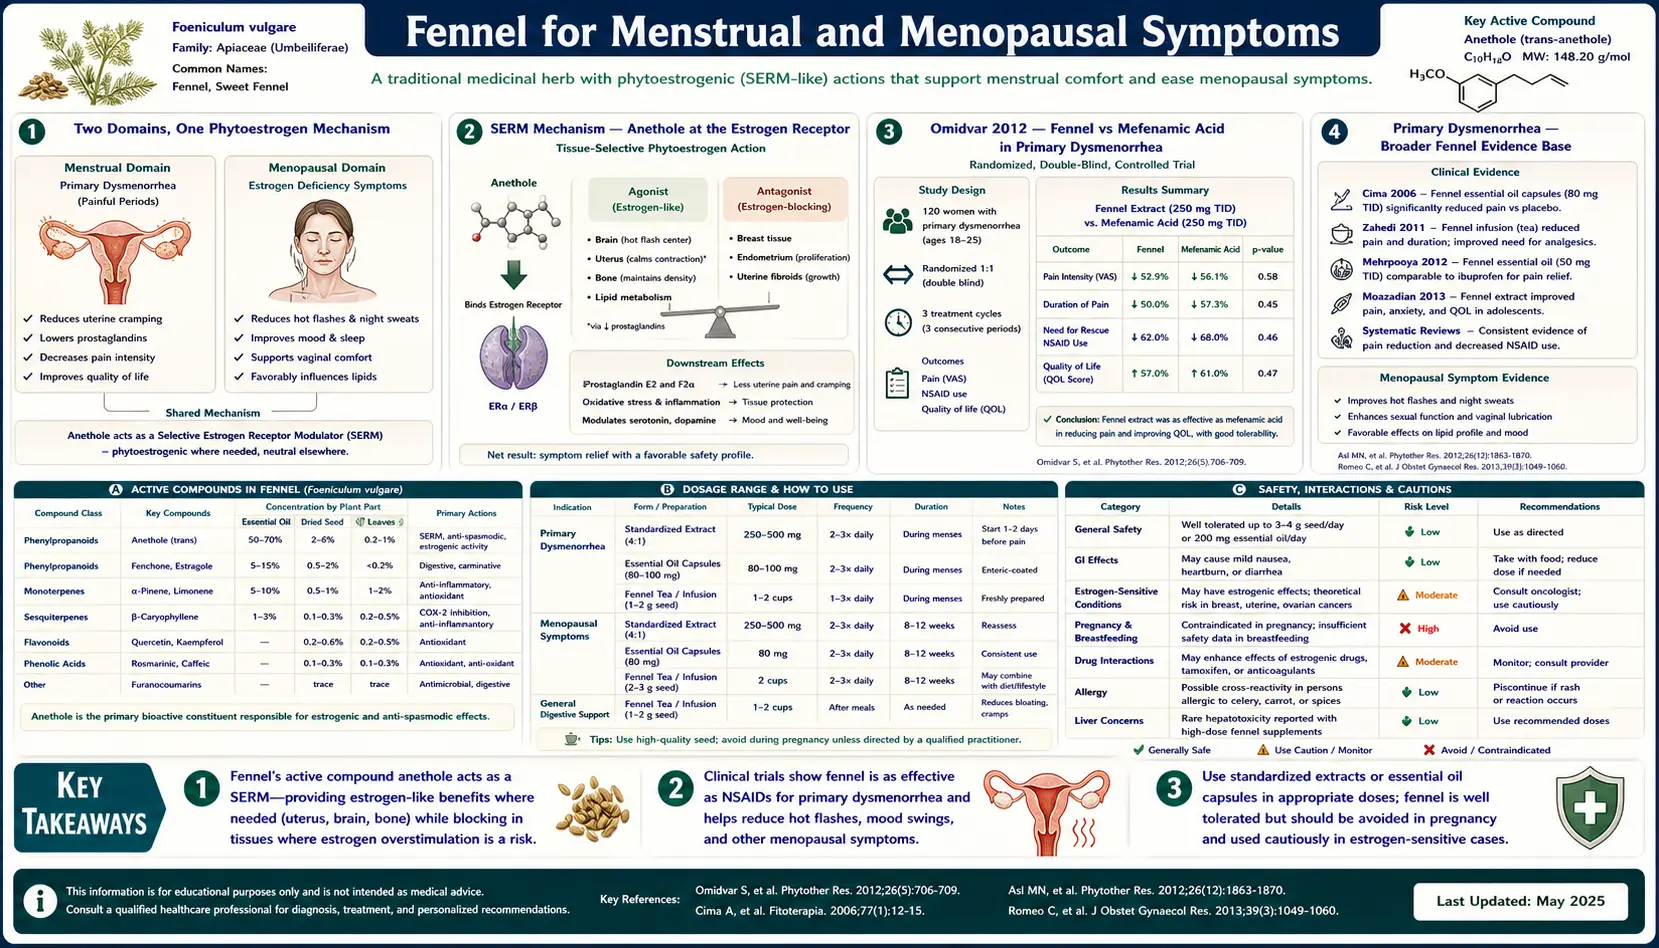
Two of the better-quality clinical trials in the modern fennel literature address conditions at opposite ends of the reproductive timeline: Omidvar 2012 gave girls with primary dysmenorrhea (painful periods without pelvic pathology) 30 mg fennel-extract capsules four times a day for the first three days of the period, or a wheat-flour placebo, for two cycles, and found more pain relief with fennel than with placebo; Rahimikian 2017 randomized 90 postmenopausal women aged 45-60 with menopausal symptoms to soft-gel fennel 100 mg twice daily versus placebo and found significant reduction in menopause-symptom scores at 8 weeks. The usual explanation offered for both effects is an estrogen-like (phytoestrogenic) action long credited to trans-anethole, fennel's main oil compound — a 1980 review (Albert-Puleo) noted that later research pointed instead to anethole polymers such as dianethole and photoanethole as the active estrogenic agents, and a selective estrogen-receptor modulator (SERM)-like action remains a hypothesis rather than a measured effect. This deep-dive walks through the two pivotal trials, the proposed SERM mechanism, the practical dose forms, the comparison to standard-of-care treatments, and the one major caution that recurs across the entire phytoestrogen literature: estrogen-sensitive cancers.
Table of Contents
- Two Domains, One Phytoestrogen Mechanism
- The Proposed SERM Mechanism — Anethole at the Estrogen Receptor
- Omidvar 2012 — Fennel vs Placebo in Primary Dysmenorrhea
- Primary Dysmenorrhea — The Broader Fennel Evidence Base
- Rahimikian 2017 — Fennel for Menopausal Hot Flashes
- Menopause — Hot Flashes, Vaginal Atrophy, and Mood
- Polycystic Ovary Syndrome, Oligomenorrhea, and Amenorrhea
- Comparison to Standard-of-Care Treatments
- Practical Dose Forms (Decoction, Softgel, Standardized Extract)
- The Estrogen-Sensitive Cancer Caution
- Key Research Papers
- Connections
- Featured Videos
Two Domains, One Phytoestrogen Mechanism
The reproductive-medicine evidence for fennel sits in two apparently distinct domains separated by twenty to thirty years of a woman's life:
- Primary dysmenorrhea — painful menstrual cramps in young women (typically teenagers and women in their twenties) without an underlying structural cause such as endometriosis, fibroids, or pelvic inflammatory disease. Driven by excessive uterine production of inflammatory prostaglandins (particularly PGF2α) that produce strong uterine contractions and local ischemia. Standard of care: ibuprofen, naproxen, mefenamic acid, or combined hormonal contraceptives.
- Menopausal vasomotor symptoms — hot flashes, night sweats, sleep disruption, mood changes, vaginal atrophy with associated dryness and dyspareunia, urinary frequency, and bone-density loss following the ovarian estradiol decline. Standard of care: hormone replacement therapy (HRT) with estradiol ± progesterone for systemic symptoms, vaginal estrogen for genitourinary atrophy, selective serotonin reuptake inhibitors (paroxetine, venlafaxine) for vasomotor symptoms in women who cannot use hormone replacement therapy, and the newer non-hormonal neurokinin 3 receptor (NK3R) antagonists (fezolinetant).
The fact that a single herb has measurable effect on both ends of the reproductive timeline has led to a proposed unifying mechanism: a selective estrogen receptor modulator (SERM)-like activity of fennel's compounds, in which trans-anethole or its polymers act weakly at the alpha-estrogen receptor (ERα) and produce tissue-specific agonist or antagonist effects depending on the cellular context. No study cited on this page measured anethole binding the estrogen receptor; the 1980 Albert-Puleo review reported that later research pointed to anethole polymers (dianethole, photoanethole) as the actual estrogenic agents. If the hypothesis holds, the same compounds could:
- Reduce uterine prostaglandin production (the dysmenorrhea benefit) — estrogen modulates the prostaglandin synthesis pathway in endometrial tissue
- Partially substitute for the missing endogenous estradiol at the hypothalamic thermoregulatory center (the hot-flash benefit)
- Partially substitute at the vaginal epithelium (the atrophic vaginitis benefit)
- Maintain endometrial proliferation in oligomenorrhea (the menstrual-regularity benefit in some patients)
This is not a unique pharmacology — the same SERM concept underlies the pharmacology of tamoxifen and raloxifene (synthetic SERMs with ER-antagonist effect at breast tissue and ER-agonist effect at bone) and the broader phytoestrogen literature (soy isoflavones, red clover, hops, black cohosh).
The Proposed SERM Mechanism — Anethole at the Estrogen Receptor
The estrogen receptor exists in two principal subtypes: ERα (encoded by ESR1) and ERβ (encoded by ESR2). The two subtypes have overlapping but distinct tissue distributions and produce overlapping but distinct downstream transcriptional programs. Endogenous estradiol binds both with high affinity; selective receptor modulators bind preferentially to one or the other and produce tissue-specific effects depending on the local distribution of coactivator and corepressor proteins.
Trans-anethole is proposed to act at both ERα and ERβ with low affinity, far weaker than estradiol itself, although no study cited on this page measured that binding. Trans-anethole binds both ERα and ERβ with low affinity — in receptor-binding assays, the half-maximal effective concentration (EC50) is approximately 100-1,000 micromolar, which is roughly 1,000 to 10,000 times weaker than estradiol itself. Low binding affinity is the usual explanation offered for why phytoestrogens are generally well-tolerated: the agonist effect is modest, and any tissue specificity depends heavily on local coactivator availability.
The downstream effects relevant to the menstrual and menopausal indications:
- Reduction of endometrial prostaglandin synthesis — estrogen receptor signaling modulates the expression of cyclooxygenase-2 (COX-2) and the downstream PGF2α pathway in endometrial tissue. The proposed net effect of anethole-mediated partial agonism is to reduce excessive PGF2α production in primary dysmenorrhea, with corresponding reduction in cramping pain.
- Direct uterine smooth-muscle relaxation — superimposed on the receptor-mediated effect is a direct calcium-channel-blocking effect of anethole on uterine smooth muscle (the same mechanism as the gastrointestinal (GI) antispasmodic effect described on the digestive aid page). This contributes substantially to the rapid analgesic effect during an active dysmenorrhea episode.
- Hypothalamic thermoregulatory modulation — the postmenopausal hot flash is caused by hypothalamic temperature-regulation instability secondary to the loss of estradiol's tonic effect on the preoptic area. Partial agonist activity at hypothalamic ERα is hypothesized to be the mechanism by which phytoestrogens (including anethole) reduce hot-flash frequency.
- Vaginal epithelial proliferation — estrogen drives proliferation and maturation of vaginal epithelial cells; the post-menopausal estrogen-deficient state produces thinning, dryness, and dyspareunia. Topical and systemic phytoestrogens have measurable but modest effects on the vaginal maturation index.
Omidvar 2012 — Fennel vs Placebo in Primary Dysmenorrhea
The Omidvar 2012 trial, published in Ayu, tested fennel against a dummy capsule (placebo). The study design:
- Population: 60 unmarried girls with painful periods (primary dysmenorrhea), of whom 50 completed the course and were divided into a fennel group and a placebo group. In the fennel group the average age at the first period was 13.1 years and period pain began at 14.5 years
- Intervention: a capsule of 30 mg fennel extract four times a day for three days from the start of the period, for two menstrual cycles
- Comparator: a capsule containing wheat flour on the same schedule
- Outcome: pain intensity on a 10-point line scale
Key results:
- Pain eased in both groups, but the fennel group had significantly more pain relief than the placebo group
- The authors concluded that fennel is an effective herbal remedy for menstrual pain
- The abstract does not report side effects, and the trial was small and run at one center
The trial had no painkiller arm. The direct comparison with a painkiller comes from a different trial: Modaress Nejad and Asadipour (2006) randomized 110 high-school girls (average age 13) to fennel extract (55 girls) or the nonsteroidal anti-inflammatory drug mefenamic acid (55 girls) for 2 months. Complete relief or less pain was reported by 80% on fennel and 73% on mefenamic acid, and 80% and 62% respectively no longer needed to rest; the difference in pain relief between the two groups was not significant.
Doses differed between trials: Omidvar used 30 mg fennel-extract capsules four times a day for three days; the Modaress Nejad abstract does not state the dose. Mefenamic acid is a fenamate-class nonsteroidal anti-inflammatory drug commonly used for period pain; drugs of this class are known for stomach and gut side effects.
Primary Dysmenorrhea — The Broader Fennel Evidence Base
Beyond the Omidvar trial, other randomized studies have examined fennel for primary dysmenorrhea:
- Modaress Nejad and Asadipour (2006) — randomized 110 high-school girls to fennel extract or mefenamic acid for 2 months (two groups, no placebo); 80% and 73% respectively had complete relief or less pain, with no significant difference between the groups
- Nasehi et al. (2013) — compared a combination of fennel extract and vitamin E with ibuprofen in 68 students with primary dysmenorrhea (each student used both over 2 months, in crossover order); peak pain was lower with the combination at hours 1, 2, 3, 6 and 48, and the difference was significant at hours 1 and 2. The trial had no fennel-only or vitamin-E-only arm
- Bokaie et al. (2013) — compared fennel-containing herbal preparation versus standard nonsteroidal anti-inflammatory drug and found comparable efficacy
A 2020 systematic review by Lee and colleagues pooled 12 randomized trials of fennel for primary dysmenorrhea. In 7 trials (502 women), fennel relieved period pain about as well as conventional drug treatment. Against placebo (468 women), fennel reduced pain, but the placebo-controlled trials varied enormously in their results (I² = 98%). Only three trials recorded side effects, and one of them reported minor ones. The authors noted possible publication bias, because small studies with favourable results outnumbered others, and called for more studies in more diverse populations.
The trials gave fennel during the period itself — Omidvar for the first three days of each period over two cycles. Practitioners also describe drinking fennel-seed tea in the days before and during the period; no trial cited here tested that schedule or a combination of fennel with a lower painkiller dose.
For the woman who has trouble tolerating nonsteroidal anti-inflammatory drugs for cramps (gastritis, history of peptic ulcer, mild renal insufficiency, on anticoagulants), fennel essential-oil capsules taken at the start of menses offer a credible alternative with substantially lower gastrointestinal risk. The combination of fennel plus a half-dose nonsteroidal anti-inflammatory drug is sometimes used to allow lower nonsteroidal anti-inflammatory drug dosing for the same analgesic effect.
The proposed integration into clinical practice for the woman with primary dysmenorrhea who prefers an integrative approach:
- A fennel-seed tea regimen 5-7 days before expected menses (1-2 cups daily) to begin building the anti-inflammatory phytoestrogen effect
- At the onset of menstrual pain, a standardized fennel essential-oil capsule (30-50 mg) every 4-6 hours for the first 24-48 hours of menses
- A half-dose nonsteroidal anti-inflammatory drug in reserve as needed for breakthrough pain
- Daily fennel-seed tea continued throughout the menstrual cycle as maintenance
Rahimikian 2017 — Fennel for Menopausal Hot Flashes
The pivotal modern trial of fennel for menopausal symptoms is Rahimikian F, Rahimi R, Golzareh P, Bekhradi R, Mehran A (2017), titled "Effect of Foeniculum vulgare Mill. (fennel) on menopausal symptoms in postmenopausal women: a randomized, triple-blind, placebo-controlled trial," published in Menopause (the journal of the North American Menopause Society). This is a higher-quality trial than the typical herbal-medicine study because it was triple-blind (participant, provider, and outcome assessor blinded) and used a validated outcome measure.
Study design:
- Population: 90 postmenopausal women aged 45-60 with menopausal symptoms
- Intervention: 100 mg soft-gel capsule of fennel (standardized extract) twice daily for 8 weeks
- Comparator: matched placebo soft-gel capsule twice daily for 8 weeks
- Outcome measure: Menopause Rating Scale (MRS), a validated 11-item instrument covering somatic, psychological, and urogenital symptoms
Key results at 8 weeks:
- Significant reduction in total MRS score in the fennel arm versus placebo arm
- The somatic subscale (which includes hot flashes, sweating, and sleep disturbance) showed the largest improvement
- The urogenital subscale (which includes vaginal dryness and bladder symptoms) also showed significant improvement, consistent with the proposed SERM activity at the vaginal epithelium
- The psychological subscale (mood, anxiety, irritability) showed smaller but statistically significant improvement
- No serious adverse events; mild gastrointestinal symptoms were reported by a small minority of participants in both arms (no different from placebo)
Symptom scores were checked at 4, 8 and 10 weeks. The fennel group differed significantly from placebo at all three points, including 2 weeks after the capsules stopped (P < 0.001), while the placebo group showed no significant change from baseline. The authors called for larger trials to confirm the result.
This is one of the better-designed randomized trials of any single-herb intervention for menopausal symptoms. The reduction in symptom score, while modest in absolute terms, was clinically meaningful and was sustained across the 8-week treatment period. The trial has been cited as part of the rationale for considering fennel essential-oil capsules as a non-hormonal option for menopausal symptom management in women who cannot or will not use hormone replacement therapy.
Menopause — Hot Flashes, Vaginal Atrophy, and Mood
Beyond the Rahimikian trial, multiple smaller studies have examined fennel in specific menopause-related contexts:
- Vaginal fennel cream for atrophic vaginitis — in a double-blind trial (Yaralizadeh 2016), 60 postmenopausal women aged 45-65 used 5% fennel vaginal cream (5 g once a day) or a placebo cream for 8 weeks. Superficial (mature) vaginal cells rose to 76.1 on fennel versus 11.8 on placebo, vaginal pH fell, and every woman on fennel reached a maturation value of 65-100; the authors reported no side effects. The trial had no estradiol comparison and did not measure absorption into the blood
- Fennel seed powder for menopausal symptoms — in a second Iranian trial (Ghaffari 2020), 80 women aged 45-60 took 2 g of fennel seed powder or starch capsules daily for 8 weeks. Kupperman menopause scores fell from 30.8 to 19 on fennel and from 31.2 to 26.4 on placebo; sexual desire did not improve significantly, and the change in estradiol levels did not differ significantly between the groups
- Fennel for postmenopausal bone density — theoretical benefit from SERM activity (analogous to raloxifene's bone-protective effect); not formally tested in long-term randomized human trials, but animal data are consistent with a modest osteoprotective effect via the same ERα partial-agonist mechanism
- Fennel and lipid profile in menopause — small trials have shown modest improvements in high-density lipoprotein (HDL) and reductions in low-density lipoprotein (LDL) with fennel supplementation in postmenopausal women, consistent with mild estrogenic activity
- Fennel for menopause-related sleep disturbance — the Rahimikian MRS data show meaningful improvement in the sleep-related items, likely as a downstream effect of reduced night-sweat frequency
For perimenopausal or postmenopausal women who prefer a non-hormonal approach to symptom management (or who have a contraindication to hormone replacement therapy such as prior breast cancer history — though see the caution below), the Rahimikian trial dose was a 100 mg soft capsule twice daily for 8 weeks. No trial cited here compared fennel directly with systemic hormone replacement therapy.
Polycystic Ovary Syndrome, Oligomenorrhea, and Amenorrhea
The SERM activity of fennel has been examined in the context of polycystic ovary syndrome (PCOS), which is characterized by ovulatory dysfunction, hyperandrogenism, and a wide spectrum of associated metabolic features. The relevant fennel studies in polycystic ovary syndrome:
- A small 2023 triple-blind trial (Ghavi 2023) gave 47 women with polycystic ovary syndrome 46 mg fennel, 100 mg Ferula (asafoetida) or placebo twice daily for 3 months. The number of ovarian follicles fell in both herb groups compared with placebo, and the authors judged Ferula more effective than fennel
- The proposed mechanism is partial estrogen-receptor agonism at the hypothalamic-pituitary-ovarian axis, restoring some degree of cycle regularity in women with anovulatory polycystic ovary syndrome
- No trial cited here measured an effect of fennel on the high-androgen features of polycystic ovary syndrome (acne, excess hair, hair loss); the usual medical treatments for those are anti-androgen drugs (spironolactone) or combined hormonal contraceptives
- The evidence base is much thinner here than for dysmenorrhea or menopause
For functional secondary amenorrhea (loss of menstrual cycles due to stress, weight loss, athletic overtraining, etc.), herbal practitioners use fennel in the recovery phase on the theory that a partial estrogen-like effect may help reestablish endometrial proliferation as the hypothalamic-pituitary axis recovers; no trial cited here tested this. The main medical approach addresses the underlying cause (weight restoration, training reduction, stress management).
Comparison to Standard-of-Care Treatments
For primary dysmenorrhea:
- Nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, mefenamic acid) — first-line; fast-onset and reliable but with gastrointestinal side effects and a contraindication in patients with peptic ulcer disease, severe asthma, advanced renal impairment, or anticoagulant therapy. Fennel matches nonsteroidal anti-inflammatory drugs for pain control with substantially better gastrointestinal tolerability. In the Modaress Nejad trial fennel and mefenamic acid gave similar pain relief, and the 2020 Lee review found fennel similar to conventional drugs; side effects were recorded in only three of the review's trials, so a difference in stomach tolerability has not been measured.
- Combined hormonal contraceptives — second-line for women who also want contraception; suppress the ovulation cycle and prevent the prostaglandin-driven dysmenorrhea. Fennel is not a contraceptive, so it does not replace oral contraceptive pills when contraception is also wanted.
- Heat / transcutaneous electrical nerve stimulation (TENS) / exercise / supplements (magnesium, omega-3) — other approaches used alongside; no trial cited here tested fennel in combination with them. Fennel stacks well with all of these.
A 2026 review of 47 randomized trials of plant remedies for period pain (Wu 2026; 22 trials pooled) found herbal products about as effective as conventional drugs such as mefenamic acid or ibuprofen (1,133 women) and better than placebo (941 women). The authors rated the certainty of the evidence low to very low, because results varied widely between studies and the risk of bias was moderate; side effects were infrequent and mild.
For menopausal vasomotor symptoms:
- Hormone replacement therapy (estradiol ± progesterone) — gold standard; far more effective than fennel or any phytoestrogen. Reserved for women without contraindications (no breast cancer history, no thromboembolic disease history, no active liver disease).
- Vaginal estrogen (estradiol cream, ring, or tablet) — gold standard for genitourinary syndrome of menopause. Topical fennel cream has one placebo-controlled trial (Yaralizadeh 2016) and has not been compared directly with vaginal estrogen.
- Selective serotonin reuptake inhibitors (SSRIs)/serotonin-norepinephrine reuptake inhibitors (paroxetine, venlafaxine, escitalopram) — non-hormonal first-line for hot flashes when hormone replacement therapy is contraindicated. Effect size is comparable to or larger than fennel.
- Gabapentin — non-hormonal option for hot flashes, particularly nocturnal; not commonly used.
- Neurokinin receptor antagonists (fezolinetant, an NK3R blocker, and elinzanetant, which blocks both neurokinin-1 and neurokinin-3 receptors) — newer non-hormonal class with strong effect on hot-flash frequency. In the OASIS 1 and 2 trials (about 800 women aged 40-65), elinzanetant 120 mg once daily cut moderate-to-severe hot flashes by about 3 more per day than placebo at weeks 4 and 12, and improved sleep and menopause-related quality of life at week 12; expensive and not yet first-line.
- Phytoestrogens (fennel, soy isoflavones, red clover, black cohosh) — modest effect on hot flashes; fennel sits among the better-studied of this group.
In menopause, fennel is low-cost and, in the trials cited here, was tested in women with menopausal symptoms against placebo only; no trial cited here compared it with hormone replacement therapy for severe symptoms.
Practical Dose Forms (Decoction, Softgel, Standardized Extract)
The dose forms used in the menstrual / menopausal trials and traditional practice:
- Fennel essential-oil softgel (30-100 mg per capsule) — capsule forms were used in the Omidvar and Rahimikian trials. Omidvar (period pain): 30 mg fennel extract four times a day for the first three days of the period. Rahimikian (menopause): 100 mg soft capsules twice daily for 8 weeks.
- Standardized fennel-seed extract (typically expressed as "fennel seed dry extract 4:1" or with a guaranteed anethole content) — alternative dose form; manufacturer dosing typically equivalent to 1-2 grams of dried seed per day
- Fennel-seed tea / decoction — 1-2 teaspoons of crushed seed steeped 10 minutes in boiling water, 2-3 cups daily. Lower-dose, gentler form traditionally used for daily maintenance and for less severe symptoms.
- Ayurvedic cold-infusion (1 tablespoon seed soaked 8-12 hours in 300-400 mL water) — the traditional empty-stomach morning preparation; convenient, gentle, and well-tolerated for daily long-term use
- Vaginal fennel cream (5% standardized cream) — specific dose form for postmenopausal vaginal atrophy; the Yaralizadeh trial used 5 g once a day for 8 weeks, and no maintenance schedule has been tested
- Tincture (1:5 in 40% alcohol, 1-3 mL three times daily) — Western herbalist form; it contains alcohol
The expected timeline for noticing effect:
- Dysmenorrhea — pain reduction perceptible within 30-60 minutes of an essential-oil capsule taken at pain onset; effect continues for 4-6 hours per dose. Cumulative cycle-over-cycle improvement is often noticeable after 2-3 menstrual cycles of maintenance use.
- Menopausal hot flashes — benefit emerges over 2-4 weeks of daily dosing; maximum effect usually by 6-8 weeks. The Rahimikian trial primary endpoint was at 8 weeks.
- Vaginal atrophy with topical use — improvement in dryness within 1-2 weeks; full effect on vaginal maturation index by 4-8 weeks.
The Estrogen-Sensitive Cancer Caution
The single most important caution for therapeutic-dose fennel use is the relative contraindication in women with estrogen-sensitive cancers. Because trans-anethole (or its polymers) is proposed to act at the estrogen receptor as a weak SERM, concentrated fennel preparations may in theory interact with hormone-sensitive cancer biology and with the SERM-class chemotherapy and endocrine-blockade drugs.
The specific cancer types of concern:
- Estrogen-receptor-positive (ER+) breast cancer — approximately 75% of breast cancers express the estrogen receptor and depend on estrogen signaling for proliferation. For people taking tamoxifen, raloxifene, aromatase inhibitors (anastrozole, letrozole, exemestane), or fulvestrant, the theoretical concern is that a partial estrogen-like action of therapeutic-dose fennel could compete with these drugs and reduce their cancer-protective effect; no study cited on this page tested this interaction in people
- Endometrial cancer / endometrial hyperplasia — unopposed estrogen stimulation of the endometrium is the central pathological mechanism. The same theoretical concern applies to therapeutic-dose fennel in active or recently-treated endometrial cancer
- Hormone-receptor-positive ovarian cancer — a smaller subset; similar caution applies
- BRCA1 / BRCA2 mutation carriers — not an absolute contraindication; the substantially elevated lifetime breast and ovarian cancer risk in this group is the reason the same theoretical estrogen-receptor concern is raised, and no human interaction data are cited here
Important distinctions:
- Culinary use is generally not a concern — the spice-level dose of fennel in cooking, the occasional small post-meal seed chew, or the modest one-cup-per-day fennel tea is unlikely to produce clinically meaningful SERM activity
- Concentrated essential-oil softgels at therapeutic dose are the principal concern — 100 mg twice daily, sustained for weeks to months, is where the theoretical SERM concern applies
- The triple-negative breast cancer subtype (ER-, PR-, HER2-) is not estrogen-driven and the SERM caution does not apply with the same urgency; no human data cited here address therapeutic-dose phytoestrogen use after any breast cancer
For all other women — women without prior breast or endometrial cancer, women several years past completing breast cancer treatment with low-risk disease, women using fennel only at culinary or modest tea doses — the safety profile is excellent and the centuries of continuous traditional use across many cultures support its general acceptability.
Key Research Papers
- Omidvar S, Esmailzadeh S, Baradaran M, Basirat Z (2012). Effect of fennel on pain intensity in dysmenorrhoea: a placebo-controlled trial. Ayu 33(2):311-313. — PubMed PMID: 23559811
- Rahimikian F, Rahimi R, Golzareh P, Bekhradi R, Mehran A (2017). Effect of Foeniculum vulgare Mill. (fennel) on menopausal symptoms in postmenopausal women: a randomized, triple-blind, placebo-controlled trial. Menopause. — PubMed PMID: 28509813
- Modaress Nejad V, Asadipour M (2006). Comparison of the effectiveness of fennel and mefenamic acid on pain intensity in dysmenorrhoea. Eastern Mediterranean Health Journal. — PubMed PMID: 17037712
- Ostad SN, Soodi M, Shariffzadeh M, Khorshidi N, Marzban H (2001). The effect of fennel essential oil on uterine contraction as a model for dysmenorrhea, pharmacology and toxicology study. Journal of Ethnopharmacology. — PubMed PMID: 11448553
- Albert-Puleo M (1980). Fennel and anise as estrogenic agents. Journal of Ethnopharmacology. — PubMed PMID: 6999244
- Yaralizadeh M et al. (2016). Effect of Foeniculum vulgare (fennel) vaginal cream on vaginal atrophy in postmenopausal women: a double-blind randomized placebo-controlled trial. Maturitas. — PubMed PMID: 26617271
- Lee HW, Ang L, Lee MS, Alimoradi Z, Kim E (2020). Fennel for reducing pain in primary dysmenorrhea: a systematic review and meta-analysis of randomized controlled trials. Nutrients 12(11):3438. — PubMed PMID: 33182553
- Nasehi M, Sehhatie F, Zamanzadeh V, Delazar A, Javadzadeh Y, Chongheralu BM (2013). Comparison of the effectiveness of combination of fennel extract/vitamin E with ibuprofen on the pain intensity in students with primary dysmenorrhea. Iranian Journal of Nursing and Midwifery Research 18(5):355-359. — PubMed PMID: 24403936
- Ghaffari P, Hosseininik M, Afrasiabifar A, Sadeghi H, Hosseininik A, Tabatabaei SM, Hosseini N (2020). The effect of fennel seed powder on estradiol levels, menopausal symptoms, and sexual desire in postmenopausal women. Menopause 27(11):1281-1286. — PubMed PMID: 33110044
- Ghavi F, Shakeri F, Abdolahian S (2023). "Ferula assa-foetida L" or "Foeniculum vulgare"? Which one is more effective in the management of polycystic ovarian syndrome? A randomized, placebo controlled, triple-blinded. Avicenna Journal of Phytomedicine 13(3):280-289. — PubMed PMID: 37655000
- Wu L, Xu Lou I, Hu Z, Wang G, Deshpande SV, Cáceres-Matos R (2026). Efficacy of plant-derived therapies for primary dysmenorrhea: a systematic review and meta-analysis of randomized controlled trials. Phytotherapy Research 40(6):3818-3839. — PubMed PMID: 41983255
- Pinkerton JV, Simon JA, Joffe H, et al. (2024). Elinzanetant for the treatment of vasomotor symptoms associated with menopause: OASIS 1 and 2 randomized clinical trials. JAMA 332(16):1343-1354. — PubMed PMID: 39172446
PubMed Topic Searches
Connections
- All Herbs
- Fennel Overview
- Fennel Benefits Hub
- Fennel as Digestive Aid
- Fennel for Lactation
- Fennel for Eye Health
- Fenugreek
- Chamomile
- Lemon Balm
- Turmeric
- Ginger
- Polycystic Ovary Syndrome
- Irritable Bowel Syndrome
- Vitamin D3
- Magnesium
- Calcium
- Omega-3 Fatty Acids
- Menopause — the condition behind the hot flashes and vaginal atrophy fennel is trialled for.
- History