⚠ Evidence warning: Clinical trials or other evidence do not support the claim that combining hypericum with vitamin B6 and magnesium is a well-tolerated protocol for PMS mood symptoms, or that hypericum with vitamin D3 and morning light is a well-tolerated combined approach to mild winter mood symptoms. This page keeps it as a report of what people, websites or other media say.
St. John's Wort for Mood and Seasonal Depression
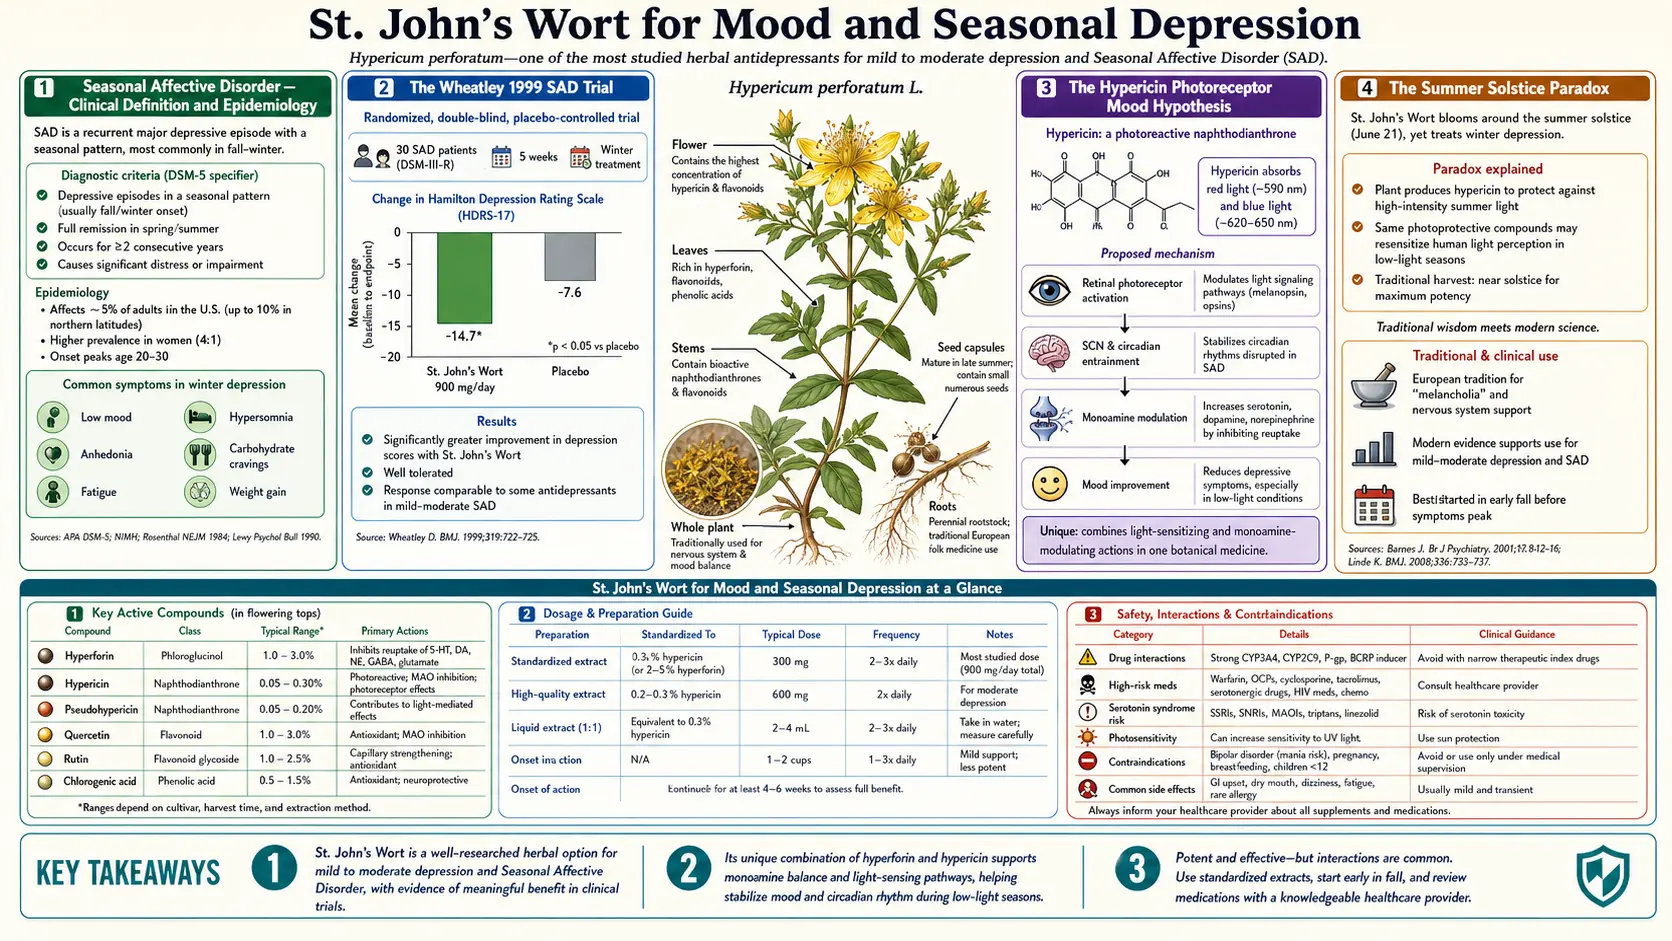
Of all medicinal herbs, St. John's Wort carries the most poetically appropriate connection to seasonal mood: its bright yellow flowers traditionally bloom around the summer solstice (the Feast of St. John the Baptist on June 24), and its red-pigmented hypericin compound — the same molecule that turns the traditional infused oil deep crimson — is a photoreceptor that requires visible light to exert its full activity. The first controlled study of hypericum specifically for Seasonal Affective Disorder (SAD) was a small randomized, single-blind trial by Martinez and colleagues in 1994, followed by Wheatley's 1999 postal survey of members of the SAD Association (Current Medical Research and Opinion), and later research has explored the herb's utility in the broader category of mild winter mood symptoms, sub-syndromal winter blues that fall short of full DSM SAD criteria, and the question of whether hypericum works synergistically with bright-light therapy (10,000 lux) or is best used as an alternative for patients who cannot tolerate or arrange for light therapy. This deep-dive walks through the SAD literature, the hypericin photoreceptor hypothesis, the curious therapeutic paradox of a midsummer-blooming herb being clinically useful for winter depression, and the autumn-start protocols that practitioners describe.
Table of Contents
- Seasonal Affective Disorder — Clinical Definition and Epidemiology
- The Wheatley 1999 SAD Survey and the Martinez 1994 Trial
- The Hypericin Photoreceptor Mood Hypothesis
- The Summer Solstice Paradox
- Hypericum vs Bright Light Therapy
- Combination Protocols: Hypericum + Light Therapy
- Sub-Syndromal SAD and Mild Winter Mood Symptoms
- Autumn-Initiation Prophylaxis Protocols
- Menopausal Mood Symptoms
- Premenstrual Syndrome (PMS) Applications
- Key Research Papers
- Connections
- Featured Videos
Seasonal Affective Disorder — Clinical Definition and Epidemiology
Seasonal Affective Disorder (SAD) is a recurrent form of major depressive disorder with a seasonal pattern, formally classified in the DSM-5 as "Major Depressive Disorder, Recurrent, with Seasonal Pattern." The full diagnostic criteria require:
- A regular temporal relationship between the onset of major depressive episodes and a specific time of year (typically autumn-onset, winter-pattern depression)
- Full remissions or shift to mania/hypomania at a characteristic time (typically spring)
- This seasonal pattern in the past two years with no non-seasonal episodes in the same period
- Seasonal episodes substantially outnumber non-seasonal episodes over the patient's lifetime
The most common SAD presentation is the autumn-winter pattern: depression onset in October-November, peak symptoms in December-February, remission in March-April. The atypical depression features distinguish SAD from non-seasonal major depression — SAD patients more often present with hypersomnia (oversleeping rather than insomnia), increased appetite with carbohydrate craving (rather than decreased appetite), weight gain (rather than weight loss), leaden paralysis (heavy-feeling limbs and fatigue), and social withdrawal.
Epidemiology: SAD prevalence varies strongly with latitude. In the northern United States and Canada, full SAD affects approximately 1-10% of the adult population, with sub-syndromal SAD (winter blues that fall short of full diagnostic criteria but cause meaningful impairment) affecting an additional 10-20%. Women are affected approximately 4 times more often than men. Onset is most common in young adulthood (20s-30s) with often a decades-long course of seasonal recurrence.
Standard treatments include bright light therapy (10,000 lux for 30 minutes daily, ideally morning), pharmaceutical antidepressants (selective serotonin reuptake inhibitors (SSRIs) are first-line in DSM-aligned American practice, bupropion-XL extended release has a U.S. Food and Drug Administration (FDA) indication specifically for SAD prevention with autumn initiation), cognitive behavioral therapy (CBT) adapted for SAD (CBT-SAD), and increasingly — in patients who decline or cannot tolerate pharmaceutical treatment — St. John's Wort.
The Wheatley 1999 SAD Survey and the Martinez 1994 Trial
David Wheatley's 1999 study (published in Current Medical Research and Opinion) is often called a trial, but its abstract describes a postal survey, with no randomization and no placebo group. Its design and findings:
- Population: volunteers from the membership of the SAD Association, who answered a postal survey before and after treatment
- Intervention: hypericum standardized extract 900 mg/day (300 mg three times daily, standardized to 0.3% hypericin)
- Groups: 168 people using hypericum alone and 133 people using hypericum plus light therapy; there was no dim-light or placebo group
- Duration: 8 weeks during the winter (November through February)
- Outcome: an 11-item rating scale with a maximum score of 44
Results: in the 168 people using hypericum alone, the mean score fell from 21.3 to 13 (p < 0.001); in the 133 using hypericum plus light therapy, it fell from 20.6 to 11.8 (p < 0.001). Both groups improved significantly in anxiety, loss of libido and insomnia. There were no significant differences between the groups on any measure, except that sleep improved more in the hypericum-plus-light group (p < 0.01). The author concluded that, on the results of this survey, hypericum would appear to be an effective treatment for SAD (PMID 10216809).
The earlier and smaller study by Martinez and colleagues (1994) was the controlled one: a randomized, single-blind trial in patients who met DSM-III-R criteria for major depression with seasonal pattern. Everyone took hypericum 900 mg/day for 4 weeks, combined with either bright light (3000 lux, n = 10) or dim light (< 300 lux, n = 10) for 2 hours daily. Hamilton Depression Scale scores fell significantly in both groups (P < .001), with no significant difference between the two groups (PMID 7857504). A 1997 review by Kasper summarised the same study: no significant difference when bright light therapy was combined with hypericum, and a need for further controlled studies (PMID 9342767).
Neither study had a hypericum-free placebo group, so neither can separate the herb's effect from improvement over time. In both, adding bright light to hypericum made no significant difference to mood scores; the only between-group difference was better sleep in the survey's hypericum-plus-light group.
The Hypericin Photoreceptor Mood Hypothesis
One of the more intriguing speculative hypotheses about hypericum's mechanism in SAD specifically (as opposed to its general antidepressant mechanism via hyperforin) is the hypericin photoreceptor hypothesis. The starting observation: hypericin is a powerful photoactive molecule. Its absorption spectrum peaks in the visible blue-green range (around 590-610 nm and 540-560 nm), and when activated by visible light, it generates singlet oxygen and reactive oxygen species through Type I and Type II photodynamic mechanisms.
The speculative hypothesis — first articulated in the 1990s and elaborated by several investigators — proposes that hypericin in skin, retinal tissue, or possibly even circulating in plasma could act as a supplementary photoreceptor, "amplifying" the effect of ambient light on circadian rhythms and mood-regulating neural circuits. The mechanism would parallel the established melanopsin photoreceptor system in retinal ganglion cells that drives circadian entrainment, but with hypericin providing additional photic input particularly in the low-light conditions of winter.
The hypericin photoreceptor hypothesis has supporting and undermining evidence:
- Supporting: hypericin clearly is photoactive in vitro and in skin (photosensitization is the dose-limiting side effect of high-dose hypericum). The seasonal pattern of SAD is unambiguously tied to ambient light deprivation. Hypericum's effect in SAD trials is at least as good as in non-seasonal depression trials, possibly suggesting some seasonal-specific mechanism in addition to general antidepressant action
- Undermining: the plasma concentrations of hypericin achieved with oral hypericum dosing are very low (nanomolar range), arguably below the threshold for meaningful photodynamic activity. The hyperforin TRPC6/monoamine mechanism is sufficient to explain general antidepressant effects without invoking a photoreceptor mechanism. No definitive in vivo demonstration of hypericin-mediated photic input to circadian or mood circuits has been published
The current consensus is that the hypericin photoreceptor hypothesis is intriguing but unproven, and that hypericum's efficacy in SAD is most parsimoniously explained by the same hyperforin-mediated monoamine mechanism that operates in non-seasonal depression. But the hypothesis persists in the literature because it would elegantly explain why a midsummer-blooming herb so traditionally tied to the solstice would be clinically useful for winter depression.
The Summer Solstice Paradox
Here is the cultural and pharmacological paradox worth contemplating: Hypericum perforatum is the medicinal plant most strongly tied to the summer solstice in European tradition. Its common name derives from St. John the Baptist (feast day June 24, three days after the solstice). It is harvested traditionally on Midsummer's Eve. Medieval herbalists associated it with sun-energy, light, and the protective power of bright midsummer brilliance. It blooms in the longest, sunniest days of the year. Its hypericin is photoactive. Its traditional infused oil requires sun-curing for weeks to develop its full red color and potency.
And yet, its most distinctive modern clinical indication is for winter seasonal affective disorder — the depression of the shortest, darkest days. The plant that captures and concentrates summer light is therapeutically deployed against the depression caused by winter light deprivation.
This is either pure poetic accident, a "doctrine of signatures" coincidence with no mechanistic underpinning, or it reflects something the medieval herbalists intuited about the relationship between the plant and seasonal light biology that modern pharmacology has not yet fully articulated. The hypericin photoreceptor hypothesis, if validated, would be the molecular mechanism behind the poetic appropriateness — the herb literally storing summer light in chemical form (hypericin biosynthesis is itself light-dependent during plant growth) and releasing it as supplementary photic input when administered during the dark winter months.
Whatever the mechanism, the human data are small. In the 1999 postal survey, average scores fell from 21.3 to 13 on hypericum alone; in the 1994 randomized study, with 10 patients in each light group, Hamilton scores fell with hypericum whether it was combined with bright or dim light. None of these studies reports a responder rate, and none had a placebo group.
Hypericum vs Bright Light Therapy
The gold-standard non-pharmaceutical treatment for SAD is bright light therapy: typically a 10,000 lux full-spectrum white light box positioned at eye level, used for 30 minutes each morning shortly after waking, throughout the symptomatic winter months. Bright light therapy has been studied since the 1980s and has strong evidence for efficacy in SAD, with response rates in the 60-80% range in well-designed trials.
No study cited on this page compares hypericum alone with light therapy alone: the 1999 survey compared hypericum alone with hypericum plus light therapy, and the 1994 trial gave hypericum to both groups, with bright or dim light. Both treatments require several weeks to reach full effect (4-6 weeks for hypericum, 2-4 weeks for light therapy).
Two recent network meta-analyses looked at light therapy itself. A 2024 analysis of 21 randomized controlled trials (1037 participants) found phototherapy significantly more effective than the other interventions or control therapies for SAD, while rating the quality of evidence as low (PMID 38220102). A 2025 analysis of 17 studies (773 patients) comparing light colours found white light most effective, followed by green, blue and red light (PMID 40629637).
Practical considerations for choosing between hypericum and light therapy:
- Light therapy advantages: no drug-interaction concerns, no systemic side effects, also useful for circadian rhythm disorders beyond SAD, can be combined with other treatments freely, evidence base is broader and more rigorous
- Light therapy disadvantages: requires daily 30-minute commitment that not all patients can accommodate (early morning schedules, light box needs to be in proper position, eyes open and facing roughly toward the light), one-time equipment cost of $100-300 for a quality medical-grade light box, needs consistent use throughout the winter season
- Hypericum advantages: simple oral dosing (three capsules daily with meals), can be used by patients who cannot accommodate light therapy schedule, no equipment required, also addresses non-seasonal depressive features, broader mood and anxiolytic effect
- Hypericum disadvantages: drug-interaction burden is significant (see Critical Drug Interactions deep-dive), 4-6 week onset window, photosensitivity risk at higher doses, contraindicated in many common clinical situations
Practitioners describe the choice as coming down to circumstances: light therapy for people who can commit to the daily routine and have no medication interaction concerns, hypericum for people who cannot use light therapy, prefer a tablet, or have non-seasonal mood symptoms alongside their seasonal pattern, and the two together for severe SAD.
Combination Protocols: Hypericum + Light Therapy
The 1999 survey included a hypericum-plus-light group: its scores fell from 20.6 to 11.8, against 21.3 to 13 with hypericum alone, with no significant difference between the groups except better sleep with light (PMID 10216809). In the 1994 randomized study, bright light added to hypericum made no significant difference compared with dim light (PMID 7857504).
A combination protocol described in naturopathic practice (autumn start):
- September-early October: hypericum standardized extract is started at 300 mg three times daily (900 mg/day total)
- Mid-October to November: the protocol assumes hypericum is now at therapeutic plasma levels; light therapy is added as symptoms begin to emerge, or in anticipation based on prior years' patterns, at 10,000 lux for 20-30 minutes within 1 hour of awakening, ideally between 7-9 AM
- December-February: both continue. Light timing is shifted if early-morning use disrupts sleep onset the following night. Some people tolerate brighter (20,000 lux for 10 minutes) or dimmer (5,000 lux for 60 minutes) regimens better than the standard
- March-April: as symptoms remit and daylight increases, light therapy is stopped first (typically late March), and hypericum is continued through April-May before tapering
- May-August: hypericum is paused during the summer months in people with a classic seasonal pattern and restarted in September the following year
Practitioners describe year-round hypericum maintenance, rather than seasonal start-stop, for some people with severe recurrent SAD, particularly with residual mood symptoms in spring/summer. The drug-interaction profile of hypericum does not change with seasonal versus continuous dosing — the same precautions apply whenever the herb is in use.
Sub-Syndromal SAD and Mild Winter Mood Symptoms
Full DSM SAD affects perhaps 1-10% of the population in northern latitudes, but a much larger group — perhaps 10-20% of adults in northern climates — experiences sub-syndromal SAD or "winter blues": mild but real winter mood symptoms that do not meet full diagnostic criteria for major depressive episode with seasonal pattern, but that still cause meaningful impairment in mood, energy, motivation, social engagement, and productivity during the December-February months.
Sub-syndromal winter blues is particularly common in:
- Adults living above 40 degrees North or below 40 degrees South (northern U.S., Canada, northern Europe, southern Australia/New Zealand)
- Adults with limited daytime outdoor exposure (office workers, night-shift workers, indoor-occupation workers)
- Adults with darker skin pigmentation in northern latitudes (the same melanin that reduces ultraviolet B-mediated Vitamin D synthesis may also affect circadian photic input)
- Women in their reproductive years (the female:male ratio for SAD is approximately 4:1, and the same ratio applies to sub-syndromal presentations)
- Adults with prior history of major depression, currently in remission
For sub-syndromal winter blues that does not meet full SAD criteria, practitioners describe hypericum as an option because the symptoms are by definition mild-to-moderate and the person may not need — or may not want — pharmaceutical antidepressant therapy. Other options described for mild winter mood symptoms include: Vitamin D3 supplementation (winter levels typically drop in northern climates and the relationship between low Vitamin D and mood is well-documented), morning bright light exposure (either via light box or via outdoor walking shortly after sunrise), and behavioral activation strategies (scheduled pleasant activities, exercise, social engagement).
Naturopathic practitioners describe a combined approach to mild winter mood symptoms: moderate-dose hypericum (300-600 mg/day rather than the full 900 mg/day antidepressant dose), 2000-5000 international units (IU)/day Vitamin D3, and morning outdoor light exposure or a bright light box, and report it as well-tolerated. The hypericum in this combination still carries its own drug-interaction burden (see the hypericum disadvantages above).
Autumn-Initiation Prophylaxis Protocols
A central idea in practitioners' use of hypericum for SAD is autumn initiation for prophylaxis. Because hypericum takes 4-6 weeks to reach full therapeutic effect, in this reasoning a start in December or January, when symptoms are already severe, comes too late — the herb cannot rescue an already-established winter depression as quickly as needed.
For people with established recurrent SAD, the protocol starts hypericum in early-to-mid September, before symptoms have begun, so that therapeutic plasma levels and full receptor effects are present by mid-October when daylight hours have noticeably shortened. This anticipatory dosing is analogous to the bupropion-XL FDA-approved SAD prophylaxis indication that uses the same autumn-initiation principle.
The autumn-initiation timeline practitioners describe:
- Late August - early September: prior years' pattern is reviewed. With reliable seasonal recurrence and a mid-October to mid-March symptomatic period, hypericum starts at 300 mg twice daily (600 mg/day)
- Mid-September: the dose rises to 300 mg three times daily (900 mg/day standard dose)
- October-March: 900 mg/day continues; the protocol raises it to 1,200 mg/day in late November/December if mood symptoms emerge despite prophylaxis
- April: as natural daylight returns and symptoms remit, the dose is tapered one dose at a time (e.g., 900 → 600 → 300 → off over 4-6 weeks)
- May-August: hypericum is typically paused during summer if the seasonal pattern is reliable
For people with year-round subclinical mood symptoms (e.g., persistent mild dysthymia that worsens seasonally), practitioners describe continuous low-dose hypericum (600 mg/day) year-round instead of the seasonal stop-start. Symptom pattern, drug interactions and personal preference are the factors weighed.
Menopausal Mood Symptoms
St. John's Wort has accumulated meaningful evidence for the mood symptoms of perimenopause and menopause — the irritability, mood lability, anxiety, depressed mood, and emotional reactivity that affect a substantial fraction of women through the menopausal transition. Several randomized trials have demonstrated significant improvement in menopausal mood measures with hypericum 900 mg/day over 8-12 weeks, with response rates comparable to those seen in non-menopausal depression trials.
The combination of hypericum with black cohosh (Actaea racemosa, formerly Cimicifuga racemosa) has been particularly well studied for menopausal symptoms, with the combination addressing both mood (hypericum) and vasomotor symptoms like hot flashes (black cohosh) more effectively than either herb alone. The Uebelhack et al. 2006 trial demonstrated that hypericum-plus-black-cohosh produced significantly greater improvement in both menopausal-specific mood symptoms and overall depression than placebo over 16 weeks in 301 women.
Practical considerations for menopausal mood use:
- Hypericum dose for menopausal mood is the standard 900 mg/day (300 mg three times daily of standardized extract)
- Black cohosh is typically dosed at 40 mg/day of a standardized black cohosh extract
- The combination is taken for 8-16 weeks and re-evaluated. Many women continue indefinitely through the perimenopausal years
- Drug-interaction concerns are the same as for non-menopausal hypericum use — menopausal women are often on multiple medications (cholesterol, blood pressure, osteoporosis, sometimes thyroid) and hypericum's interaction profile applies to each of them
- Hypericum can reduce the effectiveness of hormone replacement therapy (HRT) with estrogen + progesterone, which is why it is generally not combined with HRT in women taking black cohosh for vasomotor symptoms
Premenstrual Syndrome (PMS) Applications
Several small clinical trials and one larger randomized investigation have examined hypericum for the mood symptoms of premenstrual syndrome (PMS) and the more severe premenstrual dysphoric disorder (PMDD). The rationale: PMS/PMDD mood symptoms are believed to reflect cyclical serotonergic dysregulation in response to ovarian hormone fluctuations, and selective serotonin reuptake inhibitors (used either continuously or in the luteal phase only) are first-line pharmaceutical treatment for PMDD. Hypericum's monoamine reuptake inhibition could plausibly produce similar effects through similar mechanisms.
The results for PMS mood symptoms are mixed. A 2000 pilot study was open and uncontrolled: 19 women took 300 mg of hypericum extract a day for two menstrual cycles, and overall premenstrual syndrome scores improved by 51% (PMID 10901558). The 2010 randomized, double-blind, placebo-controlled crossover trial in 36 women with mild PMS, at 900 mg/day, found hypericum better than placebo for physical and behavioural symptoms, but found “no significant effects” compared with placebo for mood- and pain-related symptoms (PMID 20155996). A 2026 systematic review and meta-analysis of nine randomized controlled trials (1,020 participants) found that hypericum reduced anxiety (standardized mean difference, SMD = -0.21), depression (SMD = -0.45), mood disturbances (SMD = -0.36) and behavioural symptoms (SMD = -0.43) compared with placebo, while noting a lack of high-quality evidence for some outcomes (PMID 42920783). The effect is generally smaller than in major depression trials, possibly reflecting the inherently cyclical nature of PMS symptoms or the smaller effect size needed for clinically meaningful PMS improvement.
Practical considerations for PMS use:
- Standard dose 900 mg/day of standardized extract
- Practitioners describe continuous dosing (not luteal-phase only) for at least 3-4 menstrual cycles before response is judged
- The drug interaction with hormonal contraception is serious — in women on oral contraceptive pills, patches, rings or implants, breakthrough bleeding and unintended pregnancies have been documented with hypericum when no other contraception was used
- Naturopathic practitioners describe combining hypericum with pyridoxine (Vitamin B6, 50-100 mg/day) and magnesium (200-400 mg/day) for PMS mood symptoms, and report the combination as well-tolerated
Key Research Papers
- Wheatley D (1999). Hypericum in seasonal affective disorder (SAD). Current Medical Research and Opinion, 15(1):33-7. A postal survey of SAD Association members, before and after 8 weeks of hypericum. — PubMed PMID: 10216809
- Martinez B, Kasper S, Ruhrmann S, Möller HJ (1994). Hypericum in the treatment of seasonal affective disorders. Journal of Geriatric Psychiatry and Neurology, 7 Suppl 1:S29-33. Randomized, single-blind study of hypericum with bright or dim light. — PubMed PMID: 7857504
- Kasper S (1997). Treatment of seasonal affective disorder (SAD) with hypericum extract. Pharmacopsychiatry, 30 Suppl 2:89-93. Pharmacopsychiatry SAD review. — PubMed PMID: 9342767
- Wirz-Justice A, Bucheli C, Graw P, Kielholz P, Fisch HU, Woggon B (1986). Light treatment of seasonal affective disorder in Switzerland. Acta Psychiatrica Scandinavica, 74(2):193-204. The foundational European light therapy trial that established the SAD treatment framework into which hypericum was later added. — PubMed PMID: 3776666
- Lam RW et al. (2006). The Can-SAD study: a randomized controlled trial of the effectiveness of light therapy and fluoxetine in patients with winter seasonal affective disorder. American Journal of Psychiatry, 163(5):805-12. The pivotal head-to-head of light therapy vs SSRI in SAD that establishes the comparator framework. — PubMed PMID: 16648320
- Modell JG, Rosenthal NE, Harriett AE, Krishen A, Asgharian A, Foster VJ, Metz A, Rockett CB, Wightman DS (2005). Seasonal affective disorder and its prevention by anticipatory treatment with bupropion XL. Biological Psychiatry, 58(8):658-67. The bupropion-XL FDA-approved SAD prophylaxis trial that establishes the autumn-initiation framework. — PubMed PMID: 16271314
- Uebelhack R, Blohmer JU, Graubaum HJ, Busch R, Gruenwald J, Wernecke KD (2006). Black cohosh and St. John's wort for climacteric complaints: a randomized trial. Obstetrics & Gynecology, 107(2 Pt 1):247-55. Hypericum + black cohosh for menopausal mood. — PubMed PMID: 16449108
- Grube B, Walper A, Wheatley D (1999). St. John's Wort extract: efficacy for menopausal symptoms of psychological origin. Advances in Therapy, 16(4):177-86. An open drug-monitoring study of 111 women over 12 weeks. — PubMed PMID: 10623319
- Stevinson C, Ernst E (2000). A pilot study of Hypericum perforatum for the treatment of premenstrual syndrome. BJOG, 107(7):870-6. PMS pilot study. — PubMed PMID: 10901558
- Canning S et al. (2010). The efficacy of Hypericum perforatum (St John's Wort) for the treatment of premenstrual syndrome: a randomized, double-blind, placebo-controlled trial. CNS Drugs, 24(3):207-25. Larger randomized PMS trial. — PubMed PMID: 20155996
- Rosenthal NE et al. (1984). Seasonal affective disorder. A description of the syndrome and preliminary findings with light therapy. Archives of General Psychiatry, 41(1):72-80. The original Rosenthal description of SAD syndrome and light therapy. — PubMed PMID: 6581756
- Chen ZW, Zhang XF, Tu ZM (2024). Treatment measures for seasonal affective disorder: A network meta-analysis. Journal of Affective Disorders, 350:531-536. Light therapy across 21 randomized trials. — PubMed PMID: 38220102
- Wan Y, Ding J, Fan M, Huang H (2025). Effectiveness of visible light for seasonal affective disorder: A systematic review and network meta-analysis. Medicine (Baltimore), 104(27):e43107. Light colours compared across 17 studies. — PubMed PMID: 40629637
- Bozorgian L, Ghanbari S, Mottaghipisheh J, Abedi P, Mohammadi S, Zahedian M (2026). The efficacy of Hypericum perforatum L. for the treatment of premenstrual syndrome: A systematic review and meta-analysis. Avicenna Journal of Phytomedicine, 16(4):618-631. Nine randomized controlled trials in PMS. — PubMed PMID: 42920783