St. John's Wort — Critical Drug Interactions
⚠ CRITICAL SAFETY WARNING
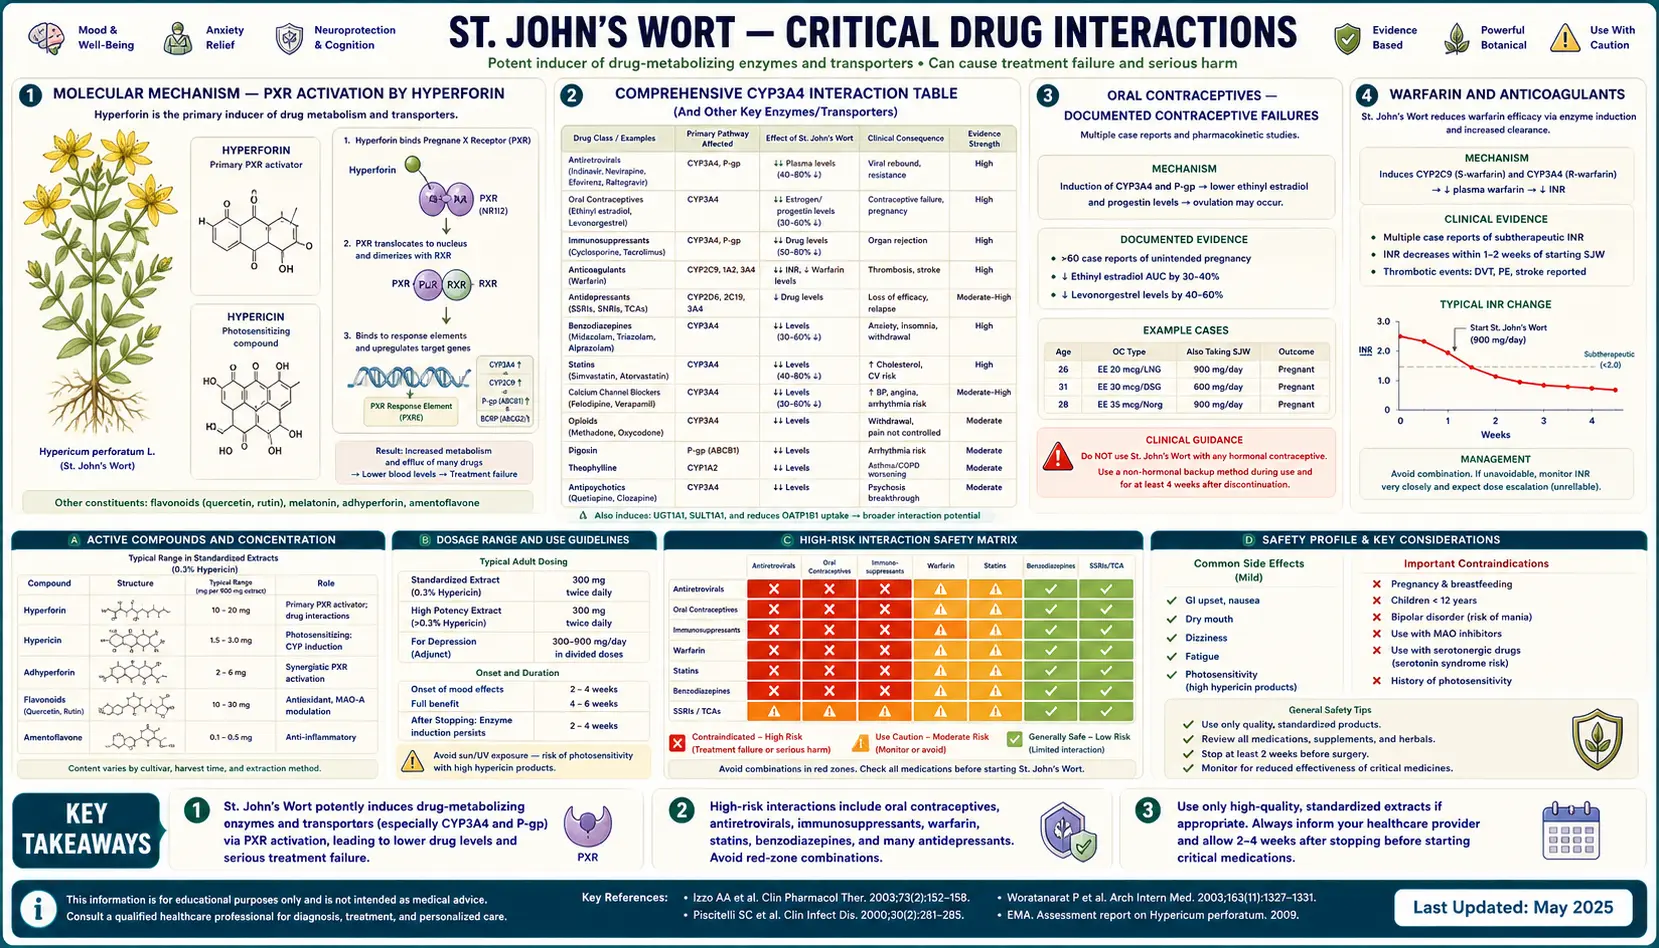
St. John's Wort has the most extensive and clinically significant drug-interaction profile of any commonly used medicinal herb. Documented cases include unintended pregnancies in women taking oral contraceptives, acute organ rejection in transplant patients, human immunodeficiency virus (HIV) antiretroviral treatment failure with viral resistance, warfarin anticoagulation failure with thrombotic events, and life-threatening serotonin syndrome from combination with selective serotonin reuptake inhibitors (SSRIs). The U.S. Food and Drug Administration (FDA), European Medicines Agency, Health Canada, the UK Medicines and Healthcare products Regulatory Agency, and Australia's Therapeutic Goods Administration have all issued formal regulatory warnings. The 2022 European Union (EU) herbal monograph states that St. John's Wort preparations supplying more than 1 mg of hyperforin a day speed up the drug-clearing enzymes CYP3A4, CYP2B6, CYP2C9 and CYP2C19 and the drug pump P-glycoprotein. It lists use with coumarin-type blood thinners (such as warfarin), cyclosporine, tacrolimus, sirolimus, everolimus, protease inhibitors and nucleoside reverse transcriptase inhibitors (HIV medicines), irinotecan, imatinib and similar cancer drugs as contraindicated, and states that hormonal contraceptives can become less reliable. The raised enzyme activity returns to normal within about 1 week of stopping, and the monograph notes that interactions with anaesthesia drugs are identified before planned surgery.
The same hyperforin molecule that drives St. John's Wort's antidepressant efficacy also produces its catastrophic drug-interaction profile. Hyperforin is a potent agonist of the pregnane X receptor (PXR), which is the master transcription factor controlling expression of the CYP3A4, CYP1A2, CYP2C9, and CYP2C19 cytochrome P450 enzymes and the P-glycoprotein drug efflux transporter. PXR activation by hyperforin upregulates these drug-metabolizing systems by 50-300% over baseline, dramatically accelerating the clearance of any drug that is a substrate. More than half of all prescription drugs in clinical use are metabolized by cytochrome P450 3A4 (CYP3A4) alone — including oral contraceptives, anticoagulants, immunosuppressants, human immunodeficiency virus antiretrovirals, cardiac drugs, chemotherapy, statins, anticonvulsants, and many psychiatric medications. The clinical consequences range from contraceptive failure (with documented unintended pregnancies) to organ-rejection cases in transplant patients to antiretroviral treatment failure with viral resistance to anticoagulation failure with thrombotic events. Separately, the herb's pharmacodynamic interaction with serotonergic drugs (selective serotonin reuptake inhibitors, serotonin-norepinephrine reuptake inhibitors (SNRIs), triptans, tramadol, monoamine oxidase inhibitors (MAOIs)) can produce potentially fatal serotonin syndrome. This deep-dive walks through the molecular mechanism, the comprehensive interaction tables, the U.S. Food and Drug Administration and international regulatory warning history, and the practical clinical-decision framework for any patient considering or already taking St. John's Wort.
Table of Contents
- Molecular Mechanism — PXR Activation by Hyperforin
- Comprehensive Cytochrome P450 3A4 Interaction Table
- Oral Contraceptives — Documented Contraceptive Failures
- Warfarin and Anticoagulants
- Immunosuppressants — Organ Rejection Cases
- Human Immunodeficiency Virus Antiretrovirals — Contraindicated or Not Recommended
- Serotonin Syndrome with Selective Serotonin Reuptake Inhibitors/Serotonin-Norepinephrine Reuptake Inhibitors/Triptans
- Cardiac Drugs (Digoxin, Statins, Antiarrhythmics)
- Chemotherapy and Targeted Cancer Therapies
- Anticonvulsants and Psychiatric Medications
- U.S. Food and Drug Administration, European Medicines Agency, and Health Canada Warning History
- Surgical and Anesthetic Considerations
- Clinical Decision Framework
- Key Research Papers
- Connections
- Featured Videos
Molecular Mechanism — PXR Activation by Hyperforin
The pharmacological root of St. John's Wort's drug-interaction profile is the activation of the pregnane X receptor (PXR) by hyperforin, the herb's principal antidepressant constituent. PXR (also known as NR1I2 or the steroid and xenobiotic receptor SXR) is a nuclear hormone receptor that functions as the master transcription factor controlling expression of the body's xenobiotic metabolism and elimination machinery.
When PXR is activated by an agonist (endogenous bile acids, hyperforin, the antibiotic rifampin, the antifungal clotrimazole, and various other xenobiotics), it translocates to the nucleus, heterodimerizes with the retinoid X receptor (RXR), and binds to PXR response elements (DR3 motifs) in the promoter regions of target genes including:
- Cytochrome P450 3A4 — the cytochrome P450 enzyme responsible for the metabolism of approximately 50% of all prescription drugs. Cytochrome P450 3A4 induction by hyperforin is the single most important driver of the herb's drug-interaction profile
- CYP1A2 — metabolizes caffeine, theophylline, clozapine, olanzapine, mirtazapine, and certain other drugs. Hyperforin induces CYP1A2 modestly
- CYP2C9 — metabolizes warfarin (S-enantiomer), phenytoin, several nonsteroidal anti-inflammatory drugs (NSAIDs), and other drugs. Hyperforin induces CYP2C9 partially
- CYP2C19 — metabolizes omeprazole, clopidogrel, certain anticonvulsants, voriconazole. Hyperforin has modest induction effect
- P-glycoprotein (P-gp, MDR1, ABCB1) — an adenosine triphosphate-driven drug efflux transporter located in intestinal epithelium (limiting drug absorption), hepatocytes (promoting drug elimination into bile), and the blood-brain barrier (limiting central nervous system (CNS) drug penetration). P-gp induction by hyperforin reduces oral bioavailability and central nervous system penetration of P-gp substrates
- UGT (UDP-glucuronosyltransferase) enzymes — Phase II conjugation enzymes that glucuronidate drugs for elimination. UGT1A1 and UGT2B7 are induced by hyperforin
The induction kinetics matter clinically:
- Cytochrome P450 3A4 induction begins within 3-7 days of starting hypericum at therapeutic dosing
- Maximum induction is reached at approximately 14 days, with cytochrome P450 3A4 activity increased by 100-300% over baseline (i.e., enzyme activity 2-4 times normal)
- P-glycoprotein induction follows a similar timeline
- After hypericum is stopped, the EU herbal monograph states that the raised enzyme activity returns to normal within about 1 week, as the induced enzyme protein is degraded
- The induction is dose-dependent — doses of hyperforin above approximately 1 mg/day (achieved with standardized extracts containing 1-5% hyperforin at 300-900 mg/day total dose) reliably produce clinically significant cytochrome P450 3A4 induction. Lower-hyperforin extracts produce less induction; the EU herbal monograph reports no clinically relevant interactions for traditional-use preparations supplying 1 mg of hyperforin a day or less, taken for no more than 2 weeks
The clinical consequence: any drug whose effective plasma concentration depends on CYP3A4, CYP1A2, CYP2C9, CYP2C19, P-gp, or UGT metabolism will have reduced plasma levels and reduced clinical effect when hypericum is co-administered. The magnitude of the interaction varies by drug (some have plasma level reductions of 25%, others of 75% or more), but the direction is consistent: hypericum reduces drug exposure.
Separately, hyperforin's monoamine reuptake inhibition (the mechanism behind its antidepressant effect) creates a pharmacodynamic interaction with other serotonergic, noradrenergic, and dopaminergic drugs — the effects of those drugs are additive or synergistic with hypericum's. The most clinically dangerous example is serotonin syndrome with selective serotonin reuptake inhibitor (SSRI)/serotonin-norepinephrine reuptake inhibitor (SNRI)/triptan/monoamine oxidase inhibitor (MAOI) combinations.
Comprehensive Cytochrome P450 3A4 Interaction Table
The following table summarizes the most clinically significant cytochrome P450 3A4-mediated and pharmacodynamic interactions with St. John's Wort. Categories of severity:
- ABSOLUTELY CONTRAINDICATED — the combination is listed as contraindicated (not to be used together)
- STRONGLY DISCOURAGED — the combination is used, if at all, only under specialist supervision with intensive monitoring
- SIGNIFICANT INTERACTION — dose adjustment and monitoring are needed; many clinicians do not co-prescribe
- MODERATE INTERACTION — reduced effect or breakthrough symptoms can occur; dose adjustment may be needed
Hormonal Contraceptives
- Combined oral contraceptive pills (ethinyl estradiol + progestin) — SIGNIFICANT INTERACTION. Reduced estrogen and progestin levels with documented contraceptive failure including unintended pregnancies. The EU herbal monograph states that lower hormone levels can cause bleeding between periods and less reliable birth control, and advises women using hormonal contraceptives to take additional contraceptive measures
- Progestin-only pills (norethindrone "mini-pill") — SIGNIFICANT INTERACTION, same interaction as combined pills
- Contraceptive patch — SIGNIFICANT INTERACTION, same interaction
- Vaginal contraceptive ring — SIGNIFICANT INTERACTION, same interaction
- Etonogestrel implant — SIGNIFICANT INTERACTION; the implant's contraceptive efficacy may be reduced
- Levonorgestrel emergency contraception — reduced efficacy; a copper IUD is the emergency option that enzyme induction does not affect
- Ulipristal acetate emergency contraception (a different drug from levonorgestrel) — its US label states that drugs or herbal products that induce CYP3A4 lower ulipristal levels and may decrease its effectiveness, and lists St. John's Wort among the products to avoid taking with it
- Levonorgestrel IUD — LOWER INTERACTION RISK because local hormone release does not depend on systemic cytochrome P450 3A4 metabolism, but breakthrough bleeding may occur. Generally considered acceptable with hypericum
- Copper IUD — NO INTERACTION; a non-hormonal method that enzyme induction does not affect
Anticoagulants and Antiplatelets
- Warfarin — ABSOLUTELY CONTRAINDICATED in the EU herbal monograph. Reduced anticoagulant effect, with documented thromboembolic events including stroke and pulmonary embolism. International normalized ratio (INR) can drop by 30-50%. The EU herbal monograph lists use with coumarin-type anticoagulants such as warfarin as contraindicated; when the two are combined anyway, clinicians check the international normalized ratio every 3-7 days and adjust the warfarin dose
- Direct oral anticoagulants (DOACs): apixaban, rivaroxaban, edoxaban are cytochrome P450 3A4 and P-gp substrates — SIGNIFICANT INTERACTION. Dabigatran is primarily P-gp substrate — MODERATE INTERACTION. All DOACs may have reduced anticoagulant effect; clinicians generally discourage co-administration
- Clopidogrel — MODERATE INTERACTION. Clopidogrel is a prodrug requiring CYP2C19 activation; the net effect of hypericum on active metabolite levels is complex and may either reduce or paradoxically increase antiplatelet effect, so it is followed clinically
Immunosuppressants (Organ Transplant)
- Cyclosporine — ABSOLUTELY CONTRAINDICATED. Cyclosporine levels drop by 50-70% with documented cases of acute kidney, liver, and heart allograft rejection
- Tacrolimus — ABSOLUTELY CONTRAINDICATED. Tacrolimus levels drop dramatically; rejection cases reported
- Sirolimus — ABSOLUTELY CONTRAINDICATED. Same mechanism, same rejection risk
- Mycophenolate — SIGNIFICANT INTERACTION via UGT induction
- Corticosteroids (prednisone, methylprednisolone, dexamethasone) — MODERATE INTERACTION; reduced efficacy possible but generally manageable
Human Immunodeficiency Virus Antiretrovirals
- Protease inhibitors (indinavir, ritonavir, atazanavir, darunavir, lopinavir, saquinavir, etc.) — ABSOLUTELY CONTRAINDICATED. Plasma levels reduced by 50-80% with treatment failure and emergence of viral resistance. The Piscitelli 2000 Lancet study of indinavir + hypericum showing 57% reduction in indinavir AUC was the trigger for U.S. Food and Drug Administration's first formal hypericum warning
- Non-nucleoside reverse transcriptase inhibitors (NNRTIs): efavirenz, nevirapine, etravirine, rilpivirine — CONTRAINDICATED on the rilpivirine label; the etravirine label states the two should not be co-administered, and the nevirapine label states the combination is not recommended. Same mechanism, same risk
- Integrase inhibitors: dolutegravir, elvitegravir, raltegravir, bictegravir — SIGNIFICANT INTERACTION; the US label wording differs by drug: the elvitegravir/cobicistat combination label lists St. John's Wort as contraindicated, the dolutegravir label says to avoid co-administration (there are insufficient data for dosing advice), the bictegravir label says co-administration is not recommended, and the raltegravir label does not list it
- Pharmacokinetic boosters: cobicistat, ritonavir as boosting agent — ABSOLUTELY CONTRAINDICATED
- Nucleoside reverse transcriptase inhibitors (tenofovir, emtricitabine, lamivudine, abacavir, zidovudine) — these are not mainly broken down by cytochrome P450 3A4, but the EU herbal monograph lists "nucleoside reverse transcriptase inhibitors" among the combinations it contraindicates for preparations supplying more than 1 mg of hyperforin a day, and US labels of tenofovir alafenamide-containing tablets list lower tenofovir alafenamide levels with St. John's Wort
Cardiovascular Medications
- Digoxin — SIGNIFICANT INTERACTION via P-gp induction. Reduced digoxin levels with risk of loss of rate control or heart failure decompensation
- Statins: simvastatin, atorvastatin, lovastatin — MODERATE INTERACTION via cytochrome P450 3A4. Pravastatin, rosuvastatin, fluvastatin, pitavastatin have lower cytochrome P450 3A4 dependence and lower interaction risk
- Calcium channel blockers: amlodipine, diltiazem, verapamil, nifedipine — MODERATE INTERACTION via cytochrome P450 3A4. Reduced antihypertensive effect possible
- Beta-blockers: metoprolol, propranolol — LOWER INTERACTION RISK
- Antiarrhythmics: amiodarone, quinidine, dronedarone — SIGNIFICANT INTERACTION via cytochrome P450 3A4
- Ivabradine — SIGNIFICANT INTERACTION via cytochrome P450 3A4
Psychiatric Medications (Pharmacodynamic Serotonin Syndrome Risk)
- Selective serotonin reuptake inhibitors: fluoxetine, sertraline, paroxetine, citalopram, escitalopram, fluvoxamine — STRONGLY DISCOURAGED. Serotonin syndrome risk (potentially fatal hyperthermic crisis with agitation, confusion, neuromuscular hyperactivity, autonomic instability). The EU herbal monograph states that St. John's Wort can add to the serotonergic effects of antidepressants such as sertraline and paroxetine and that serotonin syndrome can very rarely occur; in clinical practice the combination is not started, and a selective serotonin reuptake inhibitor is stopped and washed out before hypericum is begun
- Serotonin-norepinephrine reuptake inhibitors: venlafaxine, duloxetine, desvenlafaxine, levomilnacipran — STRONGLY DISCOURAGED. Same serotonin syndrome risk
- MAO Inhibitors: phenelzine, tranylcypromine, isocarboxazid, selegiline — ABSOLUTELY CONTRAINDICATED. Highest serotonin syndrome and hypertensive crisis risk
- Tricyclic antidepressants: amitriptyline, nortriptyline, imipramine, clomipramine — STRONGLY DISCOURAGED. Serotonin syndrome risk plus tricyclic levels may be reduced via CYP induction
- Triptans: sumatriptan, rizatriptan, zolmitriptan, eletriptan, etc. — SIGNIFICANT INTERACTION. Serotonin syndrome risk; the US sumatriptan label lists serotonin syndrome as a warning (not a boxed warning), particularly with selective serotonin reuptake inhibitors, serotonin-norepinephrine reuptake inhibitors, tricyclic antidepressants and MAO inhibitors
- Tramadol — SIGNIFICANT INTERACTION. Both serotonin syndrome risk and reduced tramadol active metabolite levels
- Dextromethorphan (in cough syrups) — SIGNIFICANT INTERACTION. Serotonin syndrome reports
- Lithium — MODERATE INTERACTION. Possible serotonergic potentiation
- Bupropion — MODERATE INTERACTION via CYP2B6. Reduced bupropion levels possible
- Antipsychotics: olanzapine, clozapine, quetiapine, aripiprazole, risperidone — SIGNIFICANT INTERACTION via cytochrome P450 3A4 and/or CYP1A2. Reduced antipsychotic levels with risk of psychotic decompensation
- Benzodiazepines: alprazolam, midazolam, triazolam — SIGNIFICANT INTERACTION via cytochrome P450 3A4. Reduced sedative effect. Diazepam, lorazepam, oxazepam have lower interaction risk
Chemotherapy and Targeted Cancer Therapies
- Tyrosine kinase inhibitors: imatinib, dasatinib, nilotinib, erlotinib, gefitinib, sorafenib, sunitinib — SIGNIFICANT INTERACTION via cytochrome P450 3A4. Reduced anticancer drug levels
- Irinotecan — SIGNIFICANT INTERACTION. Reduced active metabolite SN-38 levels
- Docetaxel, paclitaxel — SIGNIFICANT INTERACTION
- Etoposide, vinca alkaloids — SIGNIFICANT INTERACTION
- Tamoxifen — MODERATE INTERACTION. Tamoxifen requires cytochrome P450 2D6 (CYP2D6) activation; the net effect on the active endoxifen metabolite is complex
- General principle: the EU herbal monograph lists use with irinotecan, imatinib and other cancer drugs broken down by CYP3A4, CYP2B6, CYP2C9 or CYP2C19 or carried by P-glycoprotein as contraindicated
Anticonvulsants
- Carbamazepine — SIGNIFICANT INTERACTION via mutual cytochrome P450 3A4 induction (both drugs induce cytochrome P450 3A4). Carbamazepine levels may decrease with seizure breakthrough
- Phenytoin — SIGNIFICANT INTERACTION via CYP3A4 and CYP2C9 induction
- Phenobarbital — SIGNIFICANT INTERACTION (both drugs induce cytochrome P450 3A4)
- Lamotrigine — MODERATE INTERACTION via UGT induction
- Valproate — MODERATE INTERACTION
- Levetiracetam, topiramate, gabapentin, pregabalin — LOWER INTERACTION RISK (not primarily CYP metabolized)
Other Important Interactions
- Methadone — SIGNIFICANT INTERACTION via CYP3A4 and CYP2B6. Reduced methadone levels with risk of withdrawal and treatment failure in opioid use disorder management or pain management
- Oxycodone, fentanyl — SIGNIFICANT INTERACTION via cytochrome P450 3A4. Reduced analgesic effect
- Sildenafil, tadalafil, vardenafil — MODERATE INTERACTION via cytochrome P450 3A4
- Theophylline — SIGNIFICANT INTERACTION via CYP1A2
- Cyclophosphamide — SIGNIFICANT INTERACTION (complex effects on active metabolite formation)
- Voriconazole — SIGNIFICANT INTERACTION via CYP3A4 and CYP2C19
- Omeprazole, lansoprazole, esomeprazole, pantoprazole — MODERATE INTERACTION via CYP2C19; reduced acid suppression possible
- Atorvastatin/simvastatin + ezetimibe — the statin component has cytochrome P450 3A4 interaction as noted above
- Caffeine — MODERATE INTERACTION via CYP1A2 induction; caffeine clearance accelerated, may need higher doses for same effect
Oral Contraceptives — Documented Contraceptive Failures
The hypericum-contraceptive interaction is among the most consequential because the failure mode is a permanent life-altering event (unintended pregnancy) that often occurs without warning — the woman has no way to know contraceptive efficacy is reduced until breakthrough bleeding occurs or, worse, until pregnancy is confirmed.
The mechanism: combined oral contraceptive pills contain ethinyl estradiol (or in newer formulations, estetrol or estradiol valerate) plus a progestin (levonorgestrel, norethindrone, drospirenone, etc.). Both estrogen and progestin components undergo cytochrome P450 3A4 metabolism in the gut wall and liver, and both undergo intestinal P-glycoprotein efflux. Hyperforin's induction of cytochrome P450 3A4 and P-gp accelerates the metabolism and reduces the absorption of both components.
The clinical consequences:
- Faster breakdown of the pill's hormones: in a 2003 study of 12 women taking St. John's Wort 300 mg three times a day with a combined pill (Hall and colleagues), the clearance of norethindrone rose from 8.2 to 9.5 L/h and the half-life of ethinyl estradiol fell from 23.4 to 12.2 hours
- Ovulation: in the same study, follicle-stimulating hormone, luteinizing hormone and progesterone — hormones that signal ovulation — were not significantly affected over two cycles; the documented pregnancies come from case reports (below)
- Breakthrough bleeding and spotting (often the first clinical sign): in the same study it occurred in 7 of 12 women while taking St. John's Wort against 2 of 12 without it
- Contraceptive failure with unintended pregnancy
The literature includes multiple case reports and case series of pregnancies in women who became pregnant despite consistent oral contraceptive use after starting hypericum. The German pharmacovigilance database accumulated several documented cases in the late 1990s and early 2000s, which contributed to European Medicines Agency safety communications. The UK Medicines and Healthcare products Regulatory Agency issued a formal warning in 2000. The U.S. Food and Drug Administration followed in 2000 with its first formal hypericum-interaction advisory.
What the guidance and studies describe for women on hormonal contraception who are considering hypericum:
- Where pregnancy prevention is essential: the interaction applies to combined oral contraceptive pills, progestin-only pills, the patch, the ring and the etonogestrel implant, and the EU herbal monograph advises any woman using hormonal contraceptives to take additional contraceptive measures
- Methods not affected: a copper IUD is not hormonal and is unaffected by enzyme induction, and a levonorgestrel IUD releases its hormone locally, so its interaction risk is lower (breakthrough bleeding may still occur)
- Backup methods: the authors of the 2003 pharmacokinetic study concluded that women taking oral contraceptive pills should expect breakthrough bleeding and consider adding a barrier method of contraception (condoms) while taking St. John's Wort; emergency contraception may also be less effective (see the levonorgestrel and ulipristal entries above)
- After stopping: the EU herbal monograph states that the raised enzyme activity returns to normal within about 1 week after St. John's Wort is stopped
Warfarin and Anticoagulants
Warfarin is a vitamin-K-antagonist anticoagulant used for stroke prevention in atrial fibrillation, treatment of venous thromboembolism (deep vein thrombosis and pulmonary embolism), and prevention of clot formation in mechanical heart valves. Therapeutic warfarin dosing requires a delicate balance between adequate anticoagulation (typically targeting an international normalized ratio of 2.0-3.0, or 2.5-3.5 for mechanical valves) and excessive anticoagulation (with bleeding risk).
Hypericum interaction with warfarin:
- Mechanism: warfarin is metabolized primarily by CYP2C9 (S-warfarin enantiomer, the more potent form) and CYP1A2/cytochrome P450 3A4 (R-warfarin enantiomer). Hyperforin induces CYP2C9, CYP1A2, and CYP3A4, accelerating warfarin clearance
- Magnitude: international normalized ratio typically drops by 30-50% within 1-2 weeks of starting hypericum at therapeutic dosing
- Clinical consequences: documented cases of thromboembolic events (ischemic stroke, recurrent DVT/PE, mechanical valve thrombosis) in patients who became sub-therapeutic after starting hypericum
- Reverse effect after hypericum discontinuation: when hypericum is stopped, CYP induction wears off (the EU herbal monograph states that enzyme activity returns to normal within about 1 week) and warfarin clearance returns to baseline. The international normalized ratio may rise unpredictably during this transition, with bleeding risk if the warfarin dose was increased to compensate for the induction
Management:
- The EU herbal monograph lists hypericum with coumarin-type anticoagulants such as warfarin as contraindicated
- Where the two are combined anyway, the practice is weekly international normalized ratio checks while hypericum is started or its dose changed, and again weekly while it is stopped and washed out, with warfarin dose adjustment to keep the international normalized ratio on target
- Stopping hypericum abruptly without the anticoagulation clinic knowing can let the international normalized ratio rise as the induction wears off (see above)
Direct oral anticoagulants (DOACs):
- Apixaban, rivaroxaban, edoxaban are cytochrome P450 3A4 and P-glycoprotein substrates — substantial interaction with hypericum expected, with reduced anticoagulant effect
- Dabigatran is primarily P-glycoprotein substrate (minimal CYP metabolism) — modest interaction with hypericum, but still potentially clinically significant
- Unlike warfarin, DOACs do not have a routine monitoring parameter (no international normalized ratio equivalent), so detecting reduced anticoagulant effect is difficult clinically. Clinicians generally discourage co-administration of hypericum with DOACs
Immunosuppressants — Organ Rejection Cases
Solid organ transplant recipients (kidney, liver, heart, lung, pancreas, small bowel) require lifelong immunosuppression to prevent allograft rejection. Standard regimens typically include a calcineurin inhibitor (cyclosporine or tacrolimus), often combined with mycophenolate and corticosteroids, with maintenance dosing carefully titrated based on therapeutic drug monitoring to keep trough levels within narrow target ranges.
The hypericum-immunosuppressant interaction is among the most catastrophic:
- Cyclosporine: hyperforin induction of cytochrome P450 3A4 and P-gp reduces cyclosporine trough levels by 50-70%. Documented case series include acute kidney transplant rejection, liver transplant rejection requiring re-transplantation, and heart transplant rejection with hemodynamic compromise
- Tacrolimus: similar magnitude of reduction in trough levels with comparable rejection risk. Trough levels can drop from therapeutic 8-12 ng/mL to subtherapeutic 2-4 ng/mL within 1-2 weeks of hypericum initiation
- Sirolimus: same mechanism, same rejection risk
- Mycophenolate: less affected by CYP induction but UGT induction by hyperforin can modestly reduce active mycophenolic acid levels
- Reverse effect: when hypericum is discontinued, CYP induction wears off (within about 1 week, according to the EU herbal monograph) and calcineurin inhibitor levels rise. The post-hypericum-discontinuation period carries risk of supra-therapeutic levels with nephrotoxicity, neurotoxicity, or other immunosuppressant-specific toxicity
The EU herbal monograph lists use with cyclosporine, tacrolimus, sirolimus and everolimus as contraindicated: hypericum is ABSOLUTELY CONTRAINDICATED in solid organ transplant recipients on these drugs. The interaction has caused documented allograft loss and is not manageable with even intensive therapeutic drug monitoring. Depression after transplantation is usually treated with conventional pharmaceutical antidepressants with known interaction profiles (avoiding strong cytochrome P450 3A4 substrates or inhibitors) or non-pharmaceutical approaches (cognitive behavioral therapy (CBT), exercise, light therapy if seasonal).
Stem cell transplant and hematopoietic cell transplant recipients on immunosuppression for graft-versus-host disease prophylaxis or treatment face the same restrictions.
Patients on biologic immunomodulators (tumor necrosis factor (TNF) inhibitors, JAK inhibitors, IL-17 inhibitors, IL-23 inhibitors) for autoimmune disease generally have lower interaction risk because most biologics are not CYP-metabolized, though interactions differ from agent to agent.
Human Immunodeficiency Virus Antiretrovirals — Contraindicated or Not Recommended
The hypericum-HIV antiretroviral interaction was the trigger for the first formal U.S. Food and Drug Administration warning about hypericum in February 2000. The seminal study was Piscitelli et al. (Lancet, February 2000), which examined the effect of 14 days of hypericum administration on indinavir pharmacokinetics in healthy volunteers. The results were dramatic:
- Indinavir AUC (area under the plasma concentration curve) was reduced by 57%
- Indinavir trough plasma concentration was reduced by 81%
- The magnitude of interaction was more than sufficient to push indinavir levels below the minimum effective concentration for human immunodeficiency virus suppression
The clinical consequence: patients on indinavir who add hypericum will experience loss of viral suppression, viral load rebound, and emergence of human immunodeficiency virus protease resistance mutations that may compromise future treatment options. The same magnitude of interaction has been documented with other protease inhibitors and with non-nucleoside reverse transcriptase inhibitors (NNRTIs) including efavirenz and nevirapine.
Integrase strand transfer inhibitors (INSTIs) such as dolutegravir, elvitegravir/cobicistat, raltegravir, and bictegravir are increasingly the first-line antiretroviral class, but they are also significantly affected by hypericum (dolutegravir and bictegravir are UGT substrates that may be affected; cobicistat-boosted regimens lose pharmacokinetic boosting).
The EU herbal monograph lists protease inhibitors and nucleoside reverse transcriptase inhibitors among the combinations it contraindicates, and US drug labels warn against St. John's Wort for most antiretroviral classes — but the label wording differs from drug to drug:
- Protease inhibitors — CONTRAINDICATED (atazanavir, darunavir and lopinavir/ritonavir labels)
- NNRTIs — CONTRAINDICATED on the rilpivirine label; "should not be co-administered" on the etravirine label; "not recommended" on the nevirapine label
- INSTIs — CONTRAINDICATED with elvitegravir/cobicistat; the dolutegravir label says to avoid co-administration; "not recommended" on the bictegravir label (whose only listed contraindications are dofetilide and rifampin); not listed on the raltegravir label
- Pharmacokinetic boosters (cobicistat, ritonavir as booster) — CONTRAINDICATED
- Long-acting injectables (cabotegravir with rilpivirine) — CONTRAINDICATED
- Nucleoside RT inhibitors (tenofovir, emtricitabine, lamivudine, abacavir) — not mainly broken down by CYP3A4, but listed by the EU herbal monograph among contraindicated combinations; combination regimens also always include a third agent from one of the classes above
For human immunodeficiency virus-positive patients with depression, antidepressants chosen to fit the antiretroviral regimen commonly include bupropion, mirtazapine, or specific selective serotonin reuptake inhibitors known to have lower cytochrome P450 3A4 interaction (e.g., citalopram or escitalopram, with caution for QT prolongation when combined with certain antiretrovirals).
Serotonin Syndrome with Selective Serotonin Reuptake Inhibitors/Serotonin-Norepinephrine Reuptake Inhibitors/Triptans
Beyond the pharmacokinetic CYP-induction interactions discussed above, hypericum produces a clinically critical pharmacodynamic interaction with other serotonergic drugs. The mechanism: hyperforin's inhibition of serotonin reuptake (via the TRPC6/sodium-gradient mechanism) adds to the serotonergic effect of pharmaceutical selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors. When combined with other drugs that increase serotonergic signaling (triptans, tramadol, dextromethorphan, MAO inhibitors), the additive effect can produce serotonin syndrome — a potentially fatal hyperthermic crisis.
The clinical features of serotonin syndrome are classified into the Hunter Criteria (the modern diagnostic standard) and include:
- Mental status changes: agitation, confusion, restlessness, anxiety, hypomanic features
- Autonomic hyperactivity: tachycardia, hypertension (or sometimes hypotension), hyperthermia, diaphoresis (sweating), mydriasis (dilated pupils), tachypnea
- Neuromuscular hyperactivity: clonus (particularly inducible clonus in the lower extremities, or spontaneous clonus in severe cases), hyperreflexia, tremor, muscle rigidity, ocular clonus
- Severe cases: hyperthermia greater than 41 degrees C (106 degrees F), rhabdomyolysis, disseminated intravascular coagulation, seizures, multi-organ failure, death
Onset is typically within hours to days of adding a second serotonergic agent. The severity ranges from mild (agitation, mild tachycardia, modest tremor) to life-threatening (severe hyperthermia, rigidity, seizures).
Drugs that produce serotonin syndrome risk in combination with hypericum:
- All selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors
- MAO inhibitors (highest risk; combination is absolutely contraindicated)
- Tricyclic antidepressants (particularly clomipramine which is highly serotonergic)
- Triptans (sumatriptan, rizatriptan, etc.)
- Tramadol
- Tapentadol
- Meperidine
- Dextromethorphan (in cough syrups; both prescription and over-the-counter (OTC) formulations)
- Linezolid (a weak monoamine oxidase inhibitor antibiotic)
- Methylene blue (a potent reversible inhibitor of monoamine oxidase A, used in certain medical/surgical contexts)
- St. John's Wort + 5-HTP, L-tryptophan supplements, or SAM-e supplements
Hospital management of suspected serotonin syndrome:
- Stopping all serotonergic agents immediately
- Supportive care: intravenous (IV) fluids, cooling for hyperthermia, benzodiazepines (lorazepam) for agitation and tremor
- Severe cases: intensive care unit (ICU) admission, cyproheptadine (a serotonin 5-HT2A antagonist that may be used as antidote), aggressive cooling, intubation if needed
- Most cases resolve within 24-72 hours of stopping serotonergic agents
Serotonin syndrome comes from combining hypericum with another serotonergic medicine: the EU herbal monograph states that St. John's Wort can add to the serotonergic effects of antidepressants such as sertraline and paroxetine, or buspirone, and that serotonin syndrome can very rarely occur. Switches between hypericum and pharmaceutical selective serotonin reuptake inhibitors are usually made with a washout period of at least 2 weeks in either direction (longer for fluoxetine, which has a very long half-life). For more on the cluster of related conditions, see our Depression page.
Cardiac Drugs (Digoxin, Statins, Antiarrhythmics)
Digoxin: digoxin is a positive inotrope used in heart failure and rate control in atrial fibrillation. It has a narrow therapeutic index (target trough 0.5-2.0 ng/mL) and is primarily a P-glycoprotein substrate (not CYP-metabolized). Hypericum's P-gp induction can reduce digoxin levels by 25-30%, with risk of loss of rate control in atrial fibrillation or worsening heart failure. Co-administration generally avoided; if necessary, digoxin levels monitored closely.
Statins: cholesterol-lowering HMG-CoA reductase inhibitors. Susceptibility to hypericum interaction varies by specific statin:
- Simvastatin — predominantly cytochrome P450 3A4 metabolized; significant reduction in plasma levels with hypericum, with reduced low-density lipoprotein-lowering effect
- Atorvastatin — cytochrome P450 3A4 metabolized; moderate interaction
- Lovastatin — cytochrome P450 3A4 metabolized; similar to simvastatin
- Pravastatin, rosuvastatin, pitavastatin, fluvastatin — minimal cytochrome P450 3A4 dependence; lower interaction risk. These are the statins usually chosen for patients on hypericum
Calcium channel blockers: most CCBs (amlodipine, nifedipine, felodipine, diltiazem, verapamil) are cytochrome P450 3A4 substrates with reduced antihypertensive effect possible with hypericum co-administration. Blood pressure is monitored if the combination is used.
Antiarrhythmics: amiodarone, quinidine, and dronedarone are cytochrome P450 3A4 substrates with reduced antiarrhythmic effect possible. Amiodarone is particularly problematic because its long half-life means CYP induction effects persist for weeks after hypericum discontinuation.
Ivabradine: a sinus-node funny-current (If) inhibitor used in heart failure; significant cytochrome P450 3A4 substrate with reduced efficacy with hypericum co-administration; clinicians discourage the combination.
Beta-blockers: most beta-blockers have lower cytochrome P450 3A4 dependence and lower interaction risk with hypericum. Carvedilol has some cytochrome P450 2D6 metabolism but is less affected than cytochrome P450 3A4 substrates.
Aspirin and nonsteroidal anti-inflammatory drugs: low interaction risk pharmacokinetically, but combination with hypericum theoretically increases bleeding risk via additive antiplatelet and platelet-function effects (hypericum has weak antiplatelet effect via several mechanisms). Bleeding is watched for if the combination is used.
Chemotherapy and Targeted Cancer Therapies
Patients on active cancer treatment face particular risk from hypericum interactions because many chemotherapy agents and most targeted molecular therapies are cytochrome P450 3A4 substrates with narrow therapeutic indices. Reduced plasma levels of chemotherapy mean reduced anticancer effect, potentially compromising treatment success.
Specific concerns:
- Tyrosine kinase inhibitors (imatinib for CML, sunitinib for renal cell carcinoma, erlotinib for non-small-cell lung cancer, sorafenib, dasatinib, nilotinib, gefitinib, and many others) — nearly all are cytochrome P450 3A4 substrates with significant reduction in plasma levels expected with hypericum co-administration
- Irinotecan: hypericum reduces the AUC of the active metabolite SN-38 by approximately 40% with corresponding reduction in anticancer effect
- Cyclophosphamide: complex interaction; hypericum may either reduce or increase active metabolite formation depending on metabolic pathway dynamics
- Tamoxifen: complex interaction. Tamoxifen requires cytochrome P450 2D6 activation to the more potent endoxifen metabolite. Hypericum's effects on cytochrome P450 2D6 are weak, but the parallel cytochrome P450 3A4 induction affects tamoxifen disposition in complex ways. Net clinical effect on tamoxifen efficacy uncertain but caution warranted in breast cancer patients
- Docetaxel, paclitaxel: cytochrome P450 3A4 substrates with reduced plasma levels and reduced anticancer effect expected
- Etoposide: cytochrome P450 3A4 substrate with reduced levels
- Vinca alkaloids (vincristine, vinblastine, vinorelbine): cytochrome P450 3A4 substrates with reduced levels
- Immune checkpoint inhibitors (pembrolizumab, nivolumab, atezolizumab, etc.): low interaction risk pharmacokinetically (these are monoclonal antibodies not CYP-metabolized), but caution still warranted given the importance of cancer treatment efficacy
The general principle for cancer patients: the EU herbal monograph lists use with irinotecan, imatinib and other cancer drugs broken down by CYP3A4, CYP2B6, CYP2C9 or CYP2C19 or carried by P-glycoprotein as contraindicated, which covers much of active anticancer treatment. Depression in cancer patients is commonly treated with conventional antidepressants (citalopram, escitalopram, mirtazapine, bupropion) with known interaction profiles. For people in survivorship who are stable on adjuvant therapy, the interaction depends on which adjuvant drug they take (see the table above); people on surveillance alone take no anticancer drug for hypericum to affect.
Anticonvulsants and Psychiatric Medications
Anticonvulsants used both for seizure disorders and increasingly for mood stabilization (bipolar disorder), neuropathic pain, and migraine prophylaxis have complex interactions with hypericum:
- Carbamazepine and oxcarbazepine: both are cytochrome P450 3A4 inducers themselves; co-administration with hypericum produces mutual induction with reduced levels of both drugs and possibly seizure breakthrough
- Phenytoin: CYP3A4 and CYP2C9 substrate; reduced levels with hypericum and possibly seizure breakthrough
- Phenobarbital: itself a cytochrome P450 3A4 inducer; mutual induction with hypericum
- Lamotrigine: primarily UGT1A4 metabolized; UGT induction by hyperforin reduces lamotrigine levels modestly, with possible reduced mood stabilization or seizure breakthrough
- Valproate: complex interaction; reduced free valproate levels possible
- Levetiracetam: predominantly renal elimination; minimal interaction with hypericum. One of the safest anticonvulsant choices in a patient also on hypericum
- Topiramate: partial cytochrome P450 3A4 metabolism; modest interaction
- Gabapentin and pregabalin: renal elimination; minimal interaction with hypericum. Low-interaction combinations
The combination of hypericum with anticonvulsants used for mood stabilization in bipolar disorder is doubly problematic: (1) the pharmacokinetic interaction reduces mood stabilizer effectiveness, and (2) hypericum itself, like other antidepressants, can precipitate manic episodes in bipolar patients. Hypericum is generally contraindicated in bipolar disorder.
Antipsychotic medications:
- Clozapine: primarily CYP1A2 substrate; reduced levels with hypericum induction. Clozapine has a narrow therapeutic window and reduced levels may produce psychotic decompensation
- Olanzapine: CYP1A2 and CYP2D6 substrate; modest interaction
- Quetiapine, aripiprazole, risperidone, ziprasidone: predominantly cytochrome P450 3A4 metabolized; reduced levels with hypericum
- Lurasidone, iloperidone, brexpiprazole: cytochrome P450 3A4 substrates; reduced levels
For any patient on antipsychotic therapy for schizophrenia, schizoaffective disorder, or bipolar disorder, the risk of psychiatric decompensation from sub-therapeutic antipsychotic levels is high and not easily monitored clinically.
U.S. Food and Drug Administration, European Medicines Agency, and Health Canada Warning History
The international regulatory response to hypericum drug interactions provides important context:
- February 2000 — US FDA Public Health Advisory: triggered by Piscitelli et al. (Lancet, February 12, 2000) demonstrating 57% reduction in indinavir AUC with hypericum co-administration. The U.S. Food and Drug Administration issued a Public Health Advisory warning healthcare professionals and patients of the risk of significant drug interactions with St. John's Wort, particularly the contraindication with human immunodeficiency virus protease inhibitors. The U.S. Food and Drug Administration also recommended that healthcare providers ask all patients about St. John's Wort use, that pharmacists counsel patients about interactions, and that patients disclose use to all prescribers
- 2000 — UK MHRA Warning: the UK Medicines and Healthcare products Regulatory Agency (then known as MCA) issued warnings about St. John's Wort interactions with multiple drug classes including oral contraceptives, warfarin, cyclosporine, digoxin, and human immunodeficiency virus antiretrovirals
- 2002 — Health Canada Advisory: Health Canada issued an advisory on St. John's Wort drug interactions covering similar classes
- 2002 — Therapeutic Goods Administration (Australia) Bulletin: Australian TGA published guidance on hypericum interactions
- 2004 — European Medicines Agency Reflection Paper: European Medicines Agency (EMA) issued comprehensive guidance on hypericum interactions, recommending that any prescription medicine label include a warning about possible interactions with hypericum if the drug is metabolized by cytochrome P450 3A4 or transported by P-gp
- 2007 — UK Drug Safety Update: MHRA reiterated warnings and noted ongoing reports of contraceptive failure and other interactions in the Yellow Card pharmacovigilance database
- Current Status (2025): All major international drug regulators maintain ongoing warnings about hypericum interactions. In the EU, St. John's Wort is regulated as a herbal medicinal product with mandatory package-insert warnings about specific drug interactions. In the US, OTC St. John's Wort products typically carry voluntary warning labels but regulation is less strict than for prescription products
The regulatory warnings have been consistent in their message: St. John's Wort lowers the blood levels of many prescription medicines, and a medicine added while it is being taken can be affected the same way; the EU herbal monograph's list of contraindicated combinations is summarized in the warning box at the top of this page.
Surgical and Anesthetic Considerations
St. John's Wort interactions with anesthetic and surgical medications create specific perioperative concerns:
- Anesthetic agents: many inhaled and intravenous anesthetics are cytochrome P450 3A4 substrates; reduced plasma levels may produce inadequate anesthesia or unpredictable recovery profile
- Opioid analgesics: fentanyl, alfentanil, sufentanil, remifentanil, methadone, oxycodone are cytochrome P450 3A4 substrates with reduced analgesic effect possible
- Muscle relaxants: some neuromuscular blockers are P-gp substrates with altered duration of action
- Antiarrhythmic agents: used intraoperatively or in the intensive care unit (ICU); cytochrome P450 3A4 substrate interactions
- Bleeding risk: hypericum has weak antiplatelet activity that may increase surgical bleeding risk
- Postoperative drug-induced delirium: hypericum's effects on multiple neurotransmitter systems may interact unpredictably with anesthetic emergence and postoperative analgesia
- Postoperative wound healing: ironic concern given hypericum's topical wound-healing applications — oral hypericum may have systemic effects that affect wound healing differently than topical application
The standard recommendation from the American Society of Anesthesiologists and most surgical societies is to discontinue St. John's Wort at least 5 days, ideally 2 weeks, before any planned surgery. The 5-day minimum allows substantial reversal of hyperforin-mediated TRPC6/monoamine effects and partial reversal of cytochrome P450 3A4 induction. The EU herbal monograph states that before elective surgery, interactions with drugs used in general and regional anaesthesia are identified and the herbal product is stopped if necessary, and that the raised enzyme activity returns to normal within 1 week after stopping.
For emergency surgery, the surgical and anesthetic team can adjust drug doses and choices for hypericum only when they know the patient takes it.
Postoperative resumption of hypericum: can typically be resumed once the patient has stabilized postoperatively (1-2 weeks), is off most acute pain medications, and is not on any of the contraindicated postoperative drugs (e.g., warfarin for deep vein thrombosis (DVT) prophylaxis, certain antibiotics, certain analgesics).
Clinical Decision Framework
For any patient considering St. John's Wort, the following decision framework applies:
- Comprehensive medication review: the review covers every prescription medication, every over-the-counter medication, every herbal supplement, every vitamin, and every recreational substance the patient uses. The commercial drug-interaction databases used by pharmacists include hypericum and flag potential interactions
- Combinations listed as contraindicated: human immunodeficiency virus antiretrovirals (as detailed above), immunosuppressants in transplant patients, coumarin-type anticoagulants such as warfarin, MAO inhibitors, and much of active chemotherapy. When any of these is present, other depression treatments are used instead
- Strongly discouraged combinations: selective serotonin reuptake inhibitors, serotonin-norepinephrine reuptake inhibitors, tricyclics, triptans, tramadol, other anticoagulants (DOACs), hormonal contraception in women who depend on it for pregnancy prevention. With any of these, the choice is between moving off the problematic medication and using a different depression treatment
- Significant interactions: cardiac medications, statins, anticonvulsants, antipsychotics, calcium channel blockers, theophylline, methadone, sildenafil, etc. These are often manageable with awareness and monitoring
- What patients are told: the herb has more drug interactions than any other commonly used supplement; the interactions are real and clinically consequential, not theoretical; a healthcare provider, dentist or pharmacist can check for interactions only when they know it is being taken; any new medication added during hypericum use can be affected; planned surgery includes the interaction check described above; and the antidepressant effect takes about 2 weeks to begin
- Monitoring: for patients on warfarin, international normalized ratio every 1-2 weeks initially; for transplant patients (where the combination is contraindicated), trough drug levels; for human immunodeficiency virus patients, viral load monitoring
- Discontinuation planning: how long hypericum will be taken, which new medications might be needed in that time, and what happens if an acute illness needs antibiotics or other drug treatment are part of the plan from the start
In practice, the decision often comes down to one question: whether any of the contraindicated or strongly-discouraged medications are present. If they are, the drug-interaction risks described on this page apply in full; other depression options include conventional pharmaceuticals, other herbal antidepressants like saffron, lifestyle approaches, cognitive behavioral therapy and exercise.
For people on no other medications, the 2022 European Union herbal monograph recognizes standardized dry extracts of St. John's Wort (for example 900 mg once a day) as a well-established herbal medicine for the treatment of mild to moderate depressive episodes; people also use hypericum for mood symptoms, mild seasonal affective disorder and menopausal mood symptoms. The interaction profile becomes relevant only when other medications enter the picture.
Key Research Papers
- Piscitelli SC, Burstein AH, Chaitt D, Alfaro RM, Falloon J (2000). Indinavir concentrations and St John's wort. The Lancet, 355(9203):547-8. The pivotal indinavir interaction paper that triggered the FDA warning. — PubMed PMID: 10683007
- Moore LB, Goodwin B, Jones SA, Wisely GB, Serabjit-Singh CJ, Willson TM, Collins JL, Kliewer SA (2000). St. John's wort induces hepatic drug metabolism through activation of the pregnane X receptor. PNAS, 97(13):7500-2. The PXR/CYP3A4 mechanism paper. — PubMed: Moore PXR 2000
- Markowitz JS, Donovan JL, DeVane CL, Taylor RM, Ruan Y, Wang JS, Chavin KD (2003). Effect of St John's wort on drug metabolism by induction of cytochrome P450 3A4 enzyme. JAMA, 290(11):1500-4. JAMA mechanism paper. — PubMed PMID: 13129991
- Henderson L, Yue QY, Bergquist C, Gerden B, Arlett P (2002). St John's wort (Hypericum perforatum): drug interactions and clinical outcomes. British Journal of Clinical Pharmacology, 54(4):349-56. Comprehensive interaction review. — PubMed: Henderson BJCP review
- Mannel M (2004). Drug interactions with St John's wort: mechanisms and clinical implications. Drug Safety, 27(11):773-97. Drug Safety review. — PubMed PMID: 15350151
- Schwarz UI, Buschel B, Kirch W (2003). Unwanted pregnancy on self-medication with St John's wort despite hormonal contraception. British Journal of Clinical Pharmacology, 55(1):112-3. Documented contraceptive failure case. — PubMed: Schwarz contraceptive failure
- Ruschitzka F, Meier PJ, Turina M, Lüscher TF, Noll G (2000). Acute heart transplant rejection due to Saint John's wort. The Lancet, 355(9203):548-9. Documented heart transplant rejection. — PubMed PMID: 10683008
- Yue QY, Bergquist C, Gerden B (2000). Safety of St John's wort (Hypericum perforatum). The Lancet, 355(9203):576-7. Swedish pharmacovigilance experience with warfarin and other interactions. — PubMed PMID: 10683030
- Lantz MS, Buchalter E, Giambanco V (1999). St. John's wort and antidepressant drug interactions in the elderly. Journal of Geriatric Psychiatry and Neurology, 12(1):7-10. Serotonin syndrome case series. — PubMed: Lantz serotonin syndrome
- Hall SD, Wang Z, Huang SM, Hamman MA, Vasavada N, Adigun AQ, Hilligoss JK, Miller M, Gorski JC (2003). The interaction between St John's wort and an oral contraceptive. Clinical Pharmacology and Therapeutics, 74(6):525-35. Detailed pharmacokinetic study of OC interaction. — PubMed PMID: 14663455
- Johne A, Brockmöller J, Bauer S, Maurer A, Langheinrich M, Roots I (1999). Pharmacokinetic interaction of digoxin with an herbal extract from St John's wort (Hypericum perforatum). Clinical Pharmacology and Therapeutics, 66(4):338-45. Digoxin interaction characterization. — PubMed: Johne digoxin
- Mai I, Bauer S, Perloff ES, Johne A, Uehleke B, Frank B, Budde K, Roots I (2004). Hyperforin content determines the magnitude of the St John's wort-cyclosporine drug interaction. Clinical Pharmacology and Therapeutics, 76(4):330-40. Hyperforin dose-response in cyclosporine interaction. — PubMed PMID: 15470332
PubMed Topic Searches
Connections
- All Herbs
- St. John's Wort Benefits Hub
- St. John's Wort Overview
- St. John's Wort for Depression
- Mood & Seasonal Depression
- Antiviral & Wound Healing
- Depression
- Bipolar Disorder
- Atrial Fibrillation (Warfarin)
- Heart Failure (Digoxin)
- Endocrinology (Hormonal Contraception)
- Infectious Disease (Human Immunodeficiency Virus)
- International Normalized Ratio Monitoring
- Saffron (Alternative Antidepressant)
- Rhodiola Rosea (Alternative)
- Ashwagandha
- Stress Management
- History