⚠ Evidence warning: Clinical trials or other evidence do not support the claim that kava preserves sleep architecture and is an effective treatment for insomnia. This page keeps it as a report of what people, websites or other media say.
Kava for Sleep and Insomnia
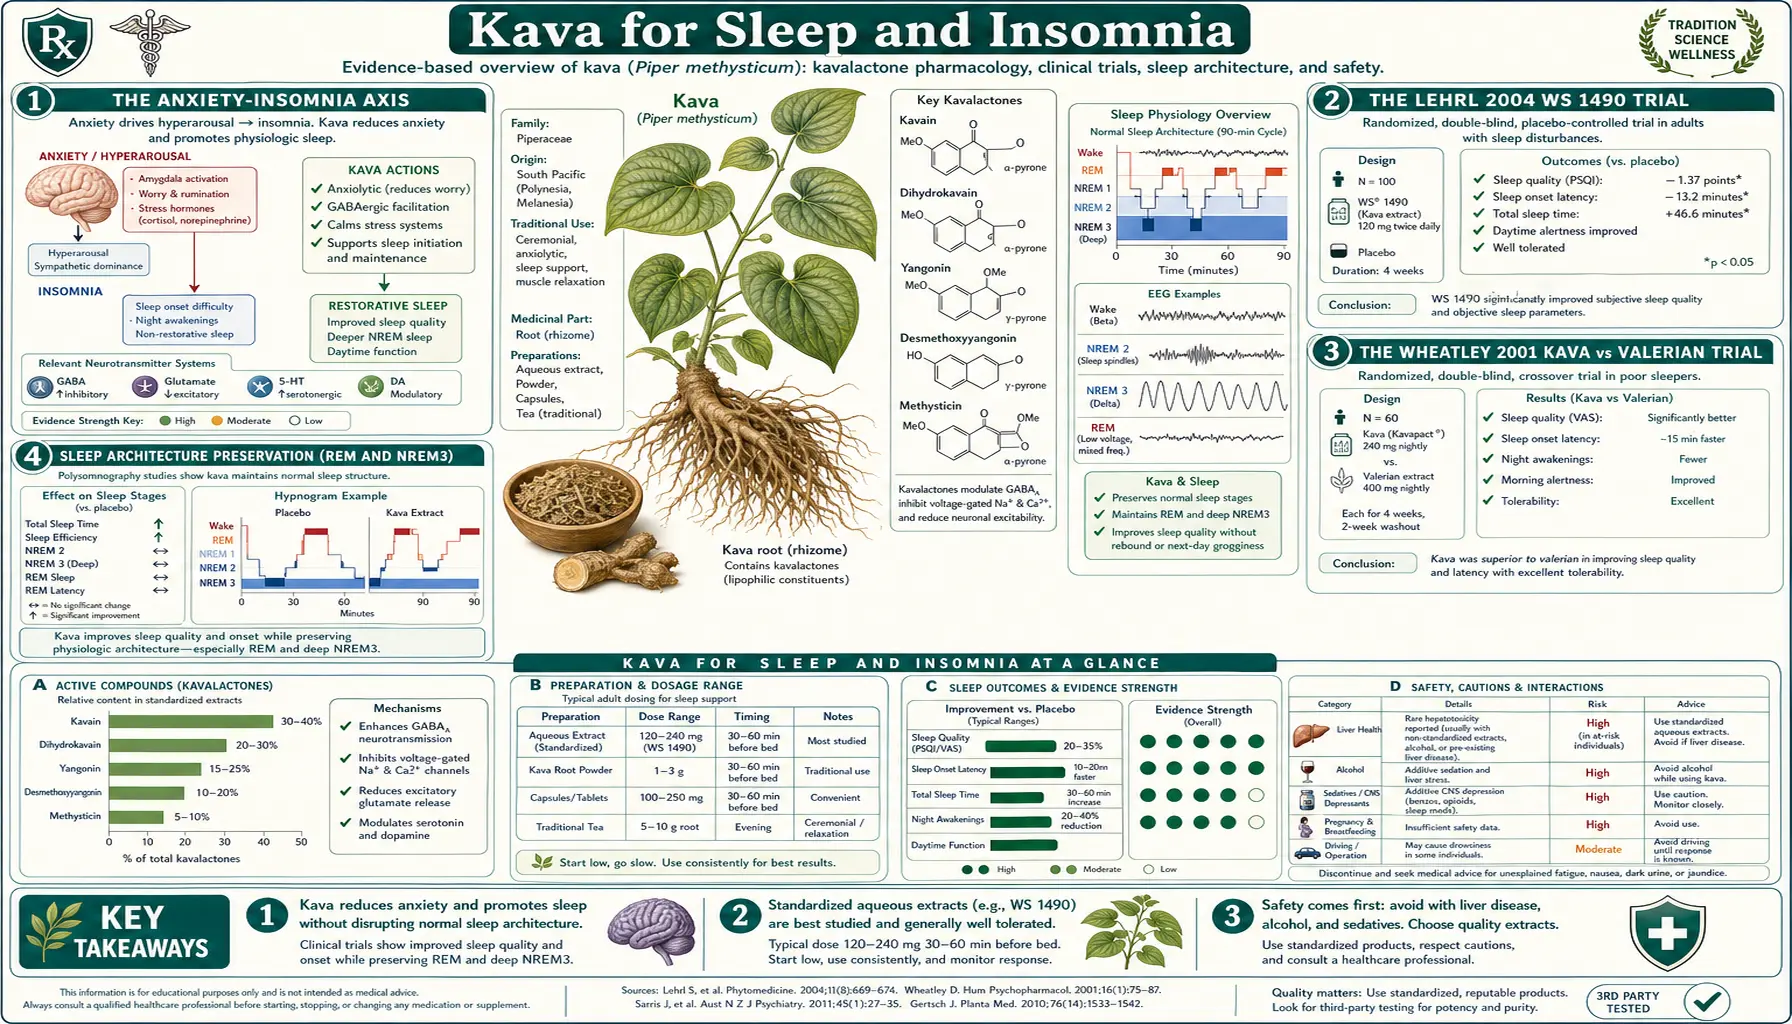
The use of kava for sleep is closely tied to its anxiolytic effect — for a large fraction of patients with chronic insomnia, the proximate cause is stress, anxiety, and ruminative cognition that prevent sleep onset and produce middle-night awakenings. Kava is described as addressing this anxiety-driven insomnia pathway through gamma-aminobutyric acid-A allosteric modulation, with two advantages claimed over the benzodiazepine, z-drug (zolpidem, eszopiclone), and antihistamine alternatives: that it preserves rapid eye movement (REM) sleep and slow-wave (non-REM stage 3) sleep architecture rather than suppressing them — a claim whose measured evidence comes from rats — and that it does not produce next-day cognitive impairment or amnesia. The main sleep-specific clinical studies are the Lehrl 2004 trial of a standardised kava extract in sleep disturbances linked to anxiety disorders and the Wheatley 2001 open pilot study, in which the same patients took kava and then valerian; a 2015 meta-analysis of 14 herbal insomnia trials found no herb, kava included, better than placebo. This deep-dive walks through the trial literature, the sleep architecture evidence, the comparison with conventional hypnotics, kava's liver-safety record, and how kava was used in the trials.
Table of Contents
- The Anxiety-Insomnia Axis
- The Lehrl 2004 Kava Extract Trial
- The Wheatley 2001 Kava and Valerian Pilot Study
- Sleep Architecture Preservation (REM and NREM3)
- Kava versus Benzodiazepines for Sleep
- Kava versus Z-Drugs (Zolpidem, Eszopiclone)
- Kava versus Antihistamines (Diphenhydramine, Doxylamine)
- Kava versus Melatonin, Valerian, and Other Natural Sleep Aids
- Menopausal and Perimenopausal Insomnia
- How Kava Was Used in the Trials
- Kava and the Liver: the Regulatory Record
- Key Research Papers
- Connections
- Featured Videos
The Anxiety-Insomnia Axis
Chronic insomnia is overwhelmingly anxiety-driven in adults. The clinical picture is familiar: difficulty falling asleep because of ruminative cognition (work concerns, financial worries, relationship stress), repeated middle-night awakenings with the same cognitive ruminations preventing return to sleep, and early-morning awakening with sustained autonomic arousal. The conventional sleep-medicine literature distinguishes "primary insomnia" from "anxiety-related insomnia" diagnostically but the underlying neurobiology is largely shared — both involve persistent hyperarousal of the limbic system and elevated sympathetic tone, both respond to the same pharmacological targets, and both share substantial epidemiological overlap with generalized anxiety disorder.
The implication for therapy is that any agent that effectively reduces anxiety will improve sleep, and any agent that effectively improves sleep needs to address the upstream arousal rather than just sedate the patient. Sedation without anxiolysis (the profile of antihistamines and to some extent z-drugs) tends to produce next-day grogginess without restorative sleep. Anxiolysis with mild sedation (the profile of benzodiazepines and kava) tends to produce more genuinely restorative sleep.
Kava's profile fits the anxiolysis-with-mild-sedation pattern. The kavalactones produce gamma-aminobutyric acid-A-mediated reduction in limbic arousal at clinical doses, with sedative effects emerging only at the higher end of the dose range or in combination with other central nervous system (CNS) depressants. The Sarris Kava Anxiety Depression Spectrum Study (KADSS) trial (discussed in the Anxiety Relief deep-dive) reported reductions on the Hamilton Anxiety Rating Scale (HAM-A), the Beck Anxiety Inventory and the Montgomery-Asberg Depression Rating Scale; its published abstract reports no sleep outcome.
The Lehrl 2004 Kava Extract Trial
The most cited sleep-specific kava trial is Lehrl 2004, published in the Journal of Affective Disorders. The multicenter study randomized 61 patients with sleep disturbances associated with non-psychotic anxiety disorders, double-blind, to either a standardized kava extract (200 mg of the extract per day) or placebo for 4 weeks, and measured outcomes with the SF-B sleep questionnaire (a German sleep questionnaire), the HAM-A, the Bf-S self-rating scale of well-being and the Clinical Global Impressions (CGI) scale.
Results:
- Sleep quality (SF-B "quality of sleep" sub-score) — significantly improved in the kava group versus placebo (P=0.007)
- Recovery from sleep (SF-B "recuperative effect after sleep" sub-score) — significantly improved in the kava group versus placebo (P=0.018)
- HAM-A psychic anxiety sub-score — superior effects in the kava group, matching the parallel anxiolytic effect
- Global clinical evaluation (CGI) — also indicated superior efficacy of the kava extract
- Subjective well-being — the well-being index (Bf-S) significantly improved in the kava group
- Safety — no significant changes in laboratory values, vital signs, or adverse event rate versus placebo over the 4-week trial
The Lehrl finding is consistent with the broader trial literature suggesting kava's sleep effect is mediated through anxiolysis rather than primary sedation — the patients who improved most on sleep also improved most on the anxiety measure, and the improvement in subjective well-being is incompatible with a heavy-sedation mechanism that would produce next-day fatigue.
The 4-week duration is a limitation; longer-term sleep efficacy and safety data are more limited. The choice of an acetonic extract (rather than aqueous noble-cultivar root extract) is another consideration that became prominent in the wake of the 2002 European hepatotoxicity controversy, but in this specific trial liver function tests showed no adverse signal.
A larger, longer 2020 trial (phase III, 16 weeks, 171 people with diagnosed generalised anxiety disorder, an aqueous extract of dried kava root standardised to 120 mg of kavalactones twice a day) found no significant difference in anxiety reduction between kava and placebo: at the end of the controlled phase 17.4% of the kava group were classified as remitted, compared with 23.8% of the placebo group (p = 0.46). Poorer memory and tremor or shakiness occurred more often in the kava group, and liver function test abnormalities were significantly more frequent in the kava group, although no participant met criteria for herb-induced liver injury. The authors concluded that this extract was not effective for diagnosed generalised anxiety disorder; the abstract reports no sleep outcome.
The Wheatley 2001 Kava and Valerian Pilot Study
The Wheatley 2001 study published in Phytotherapy Research was an open pilot study without a placebo group, in which the same patients took kava and then valerian in sequence; it was not a randomised comparison. 24 patients with stress-induced insomnia took kava 120 mg daily for 6 weeks. After 2 weeks off treatment, and with 5 having dropped out, 19 took valerian 600 mg daily for another 6 weeks. Stress was measured in three areas (social, personal and life-events), and insomnia in three areas (time to fall asleep, hours slept and waking mood):
- Stress — total stress severity was significantly relieved by both (p < 0.01), with no significant differences between them
- Insomnia — also significantly relieved by both (p < 0.01)
- Side effects — 58% of patients had no side effects with each; the commonest effects were vivid dreams with valerian (16%) and dizziness with kava (12%)
The author concluded that both may be useful in the treatment of stress and insomnia, but that further studies are required to determine their relative roles. Points of difference described between the two:
- Anxiety-predominant vs sleep-predominant complaint — kava's anxiolytic effect is generally stronger than valerian's
- Tolerance to side effects — some patients dislike valerian's characteristic earthy taste and vivid-dream effect; others dislike kava's numbing tongue effect
- Hepatotoxicity concern — valerian has a cleaner long-term hepatic safety profile in absolute terms; kava has a record of liver-injury reports (see Kava and the Liver below), and in the 2020 trial of an aqueous kava root extract, liver function test abnormalities were significantly more frequent on kava than on placebo, although no participant met criteria for herb-induced liver injury
- Combination — the two are sometimes combined; formal trials of the combination are limited
For broader context on natural sleep aids see our Valerian page, Passionflower page, and Lavender page.
Sleep Architecture Preservation (REM and NREM3)
One of the most important pharmacological distinctions between kava and conventional sleep medications concerns sleep architecture — the specific pattern of REM (rapid eye movement) and NREM (non-REM, divided into stages N1, N2, N3) sleep cycles through the night. Polysomnography is the technique used to map this architecture in laboratory studies.
Healthy human sleep alternates approximately every 90 minutes between NREM and REM phases. Each phase has distinctive electrical signatures, distinctive functional roles, and distinctive vulnerabilities to drug interference:
- NREM stage 3 (N3, also "slow-wave sleep") — characterized by high-amplitude delta waves on electroencephalogram (EEG). This is the physiologically restorative phase: growth hormone is released, glymphatic clearance of brain metabolites is active, and immune function is consolidated. Selective deprivation of N3 produces the subjective experience of "unrefreshing sleep" even when total sleep time is preserved.
- REM sleep — characterized by rapid eye movements, near-paralytic muscle atonia (except eye muscles), low-amplitude high-frequency electroencephalogram, and active dreaming. REM is essential for memory consolidation, particularly procedural and emotional memory. Selective deprivation of REM produces the experience of memory fragmentation and emotional dysregulation.
Most conventional sleep medications suppress one or both of these critical phases:
- Benzodiazepines — significantly suppress N3 (slow-wave sleep) and modestly suppress REM. The patient sleeps longer in stage N2 (light sleep), which the brain experiences as less restorative.
- Z-drugs (zolpidem, zaleplon) — similar pattern to benzodiazepines but typically less severe N3 suppression; eszopiclone is the most architecture-friendly of the z-drugs
- Antihistamines (diphenhydramine, doxylamine) — suppress REM sleep substantially; produce the characteristic "drugged sleep with vivid dreams during withdrawal" pattern
- Alcohol — suppresses REM in the first half of the night, then produces rebound REM in the second half (a major contributor to alcohol-related insomnia)
- Trazodone — less architecture disruption than benzodiazepines, often a preferred conventional choice for chronic insomnia
- Mirtazapine — relatively architecture-preserving
No human polysomnography study of kava is indexed in PubMed; the measured evidence on kava and sleep architecture comes from rats. In a 2005 study of sleep-disturbed rats, kava extract at 300 mg/kg shortened the time to fall asleep, had no effect on total waking or non-REM sleep time, and significantly increased delta (deep-sleep) activity during non-REM sleep, whereas the benzodiazepine flunitrazepam significantly decreased delta power; the kava effect was not blocked by the benzodiazepine-site blocker flumazenil. The kava sleep effect is described as primarily anxiolytic (reducing the limbic hyperarousal that prevents sleep onset) rather than direct sedative suppression of higher cortical states. This is the main theoretical advantage claimed for kava over conventional hypnotics; it has not been measured in human sleep studies.
One proposed explanation involves gamma-aminobutyric acid-A receptor subunits. Benzodiazepines act non-selectively across α1, α2, α3, and α5 containing gamma-aminobutyric acid-A receptors, with the α1 subtype mediating both sedation and the slow-wave sleep suppression effect. The measured data do not support the idea that kavalactones act preferentially at non-α1 subtypes. A 2016 laboratory study of kavain, the major anxiolytic kavalactone, on human gamma-aminobutyric acid-A receptors expressed in frog eggs (Xenopus oocytes) found that kavain boosted all the receptor types tested, regardless of subunit make-up, with greater enhancement at the α4β2δ type than at the α1β2γ2L type. Its effect was unaffected by flumazenil, indicating that kavain does not act through the classical benzodiazepine binding site.
Kava versus Benzodiazepines for Sleep
Benzodiazepines (temazepam, lorazepam, clonazepam used at bedtime, alprazolam less commonly) are still widely prescribed for insomnia despite well-established harms with chronic use. Kava's profile for sleep parallels its profile for anxiety, with several specific advantages and one disadvantage in the sleep-specific use case.
Where Kava Wins for Sleep
- Sleep architecture — in the rat study discussed above, kava extract increased deep-sleep delta activity while the benzodiazepine flunitrazepam decreased it; no human sleep-laboratory comparison has been published
- No next-day cognitive impairment — the morning-after grogginess characteristic of benzodiazepines (particularly longer-acting agents like clonazepam) is generally absent with kava at sleep-appropriate doses
- No memory impairment — the bedtime amnesia that benzodiazepines produce (forgetting events between taking the medication and falling asleep, occasional middle-night amnesia for sleepwalking or eating episodes) does not occur with kava
- No physical dependence or withdrawal — the rebound insomnia that complicates benzodiazepine discontinuation is much milder or absent with kava
- No respiratory depression risk — particularly relevant for patients with sleep apnea or chronic obstructive pulmonary disease (COPD), in whom benzodiazepine respiratory depression is a concern
- Less fall risk in older adults — benzodiazepines are a leading cause of falls and hip fractures in older patients
Where Benzodiazepines Win for Sleep
- Reliability of effect — a 1 mg lorazepam at bedtime will almost certainly produce sleep onset within 30 minutes in essentially every patient. Kava response varies meaningfully with product, individual pharmacogenomics, and current arousal level.
- Acute severe insomnia — benzodiazepines are appropriate for short-term use in acute crisis insomnia (post-bereavement, post-major-life-event, hospitalization). Kava is better suited to chronic mild-to-moderate sleep disturbance.
- Cleaner hepatic safety profile — in absolute terms benzodiazepines have a cleaner hepatic safety record (see Kava and the Liver below)
Herbal practitioners describe kava as an option tried for chronic stress-related insomnia not responsive to sleep hygiene measures, before benzodiazepine therapy. For acute severe insomnia, or where a rapid reliable effect is needed, benzodiazepines remain the established prescription option.
Kava versus Z-Drugs (Zolpidem, Eszopiclone)
The "z-drugs" (zolpidem, zaleplon, eszopiclone, zopiclone) are non-benzodiazepine gamma-aminobutyric acid-A modulators that selectively target the α1 subunit, producing more selective sedation with somewhat less of the anxiolytic effect of classic benzodiazepines. They have largely replaced benzodiazepines as first-line prescribed hypnotics in much of the developed world.
Important distinctions versus kava:
- Z-drug parasomnias — zolpidem is well-documented to produce sleepwalking, sleep-driving, sleep-eating, and middle-night amnestic episodes in a meaningful fraction of users. These complications are essentially absent with kava.
- Z-drug tolerance — though marketed as less tolerance-prone than benzodiazepines, the z-drugs do produce dose-escalation tolerance with chronic use. Kava's tolerance profile is less well-studied but appears modest based on traditional use evidence.
- Z-drug rebound insomnia — discontinuation of chronic z-drug use commonly produces 1–2 weeks of rebound insomnia. Kava discontinuation does not typically produce rebound.
- Z-drug U.S. Food and Drug Administration (FDA) boxed warning — in 2019 the U.S. Food and Drug Administration added a boxed warning to zolpidem, zaleplon, and eszopiclone regarding serious injuries and deaths from complex sleep behaviors. Kava is the subject of a different U.S. Food and Drug Administration warning: a March 2002 consumer advisory that kava-containing dietary supplements may be associated with severe liver injury (see Kava and the Liver below).
- Z-drug cognitive effects in older adults — zolpidem in particular is associated with worsened cognitive performance in older adults; the American Geriatrics Society Beers Criteria recommend against its use in this population
Proponents describe kava as an alternative for people who have had a poor experience with z-drugs (whether through parasomnias, tolerance, or persistent next-day grogginess), because its mechanism and side-effect profile differ.
Kava versus Antihistamines (Diphenhydramine, Doxylamine)
Over-the-counter night-time products — diphenhydramine combined with acetaminophen or ibuprofen, and stand-alone night-time sleep aids — rely on first-generation antihistamines — diphenhydramine or doxylamine — for their sleep effect. These are extremely widely used, easily available, and generally considered "safe" by the lay public despite a problematic profile for chronic use.
Antihistamine sleep aids have important limitations versus kava:
- Anticholinergic burden — diphenhydramine is a substantial muscarinic antagonist; chronic use is associated in observational studies with increased dementia risk in older adults (Gray et al. JAMA Internal Medicine 2015). Kava has no anticholinergic activity.
- Tolerance within 3–4 days — the sleep-promoting effect of diphenhydramine wanes within 3–4 nights of continued use, leaving residual side effects without continued benefit. Kava does not show this rapid tolerance pattern.
- REM suppression — antihistamines significantly suppress REM sleep, producing unrefreshing sleep and rebound REM with vivid dreams upon discontinuation. Kava's effect on human REM sleep has not been measured in a published sleep-laboratory study (see Sleep Architecture above).
- Next-day grogginess — the 8–10 hour half-life of diphenhydramine produces meaningful next-morning impairment, including impaired driving performance. Kava's 4–6 hour subjective duration produces less morning carryover.
- Constipation, urinary retention, dry mouth — anticholinergic side effects that bother many users. Kava does not produce these.
Kava lacks the anticholinergic side effects of these over-the-counter antihistamines, but it carries its own liver-safety record (see Kava and the Liver below).
Kava versus Melatonin, Valerian, and Other Natural Sleep Aids
Within the natural-medicine sleep aid category, kava competes with melatonin, valerian, passionflower, and several others. Each has a distinctive mechanism and use case.
A 2015 systematic review and meta-analysis of 14 randomised trials, involving a total of 1602 participants with insomnia, covered four single-herb preparations: valerian, chamomile, kava and wuling. It found no statistically significant difference between any herbal medicine and placebo, or any herbal medicine and active control, for any of the thirteen measures of clinical efficacy. A similar or smaller number of adverse events per person were reported with kava, chamomile and wuling than with placebo, and a greater number with valerian.
Melatonin
- Acts on the melatonin receptors MT1 and MT2 (melatonin receptors 1 and 2) to signal the onset of biological night; physiologically a circadian timing signal rather than a sedative
- Best for circadian-misalignment insomnia (jet lag, shift work, delayed sleep phase syndrome)
- Less effective for primary anxiety-related insomnia — the proximate problem in that case is limbic hyperarousal, not circadian timing
- Generally safe; minimal interactions; combined with kava by some practitioners (different mechanism, different time-course)
Valerian
- Acts through gamma-aminobutyric acid (GABA) reuptake inhibition (valerenic acid) plus weak gamma-aminobutyric acid-A modulation
- Effect emerges over 2–4 weeks of consistent use; less reliable for acute single-dose use than kava
- Distinctive earthy smell and taste limits patient adherence
- Cleaner long-term hepatic safety than kava (in absolute terms; see Kava and the Liver below)
- In the Wheatley 2001 open pilot, valerian and kava gave similar results for stress-related insomnia (discussed above)
Passionflower
- Also gamma-aminobutyric acid-A modulator but at different binding sites than kava or benzodiazepines
- Generally milder effect; useful for mild anxiety-related sleep disturbance
- Often combined with valerian, lemon balm, or kava in proprietary sleep formulas
Lavender (Oral Lavender Oil)
- Standardized oral lavender oil preparation; reduces anxiety in trials comparable to lorazepam
- Less direct sleep evidence than kava but shares the anxiolytic mechanism
- Generally well-tolerated; minimal interactions
Ashwagandha
- Adaptogen with hypothalamic-pituitary-adrenal-axis modulating effect
- Longer time course; works through stress hormone reduction rather than direct gamma-aminobutyric acid modulation
- Sleep improvement documented in trials but slower onset than kava
For primary anxiety-related insomnia, some practitioners describe combining melatonin 0.5–1 mg at bedtime for circadian signaling with kava 120 mg kavalactones at bedtime for anxiolysis, adding valerian or ashwagandha for chronic maintenance. No trial of this combination is cited on this page.
Menopausal and Perimenopausal Insomnia
Insomnia is one of the most distressing symptoms of perimenopause and early menopause, with up to 60% of perimenopausal women reporting clinically significant sleep disturbance. The biology is multi-factorial: declining progesterone (which has gamma-aminobutyric acid-A modulating activity through its allopregnanolone metabolite) reduces endogenous gamma-aminobutyric acid tone, hot flashes produce direct sleep disruption, mood disturbance contributes to ruminative cognition, and circadian shifts associated with hormonal change disturb sleep timing.
Limited evidence supports kava for perimenopausal anxiety; its effect on menopausal sleep has not been measured in the trial described below. The proposed mechanism is that kava restores gamma-aminobutyric acid-A tone that has dropped with declining progesterone, addresses anxiety component of the menopausal symptom complex, and does so without the cardiovascular concerns of hormone replacement therapy or the selective serotonin reuptake inhibitor (SSRI) side effects (sexual dysfunction, gastrointestinal (GI) upset, weight gain) that affect many menopausal women on conventional therapy.
The trial literature is small. A 2003 three-month randomized, open (unblinded) study by Cagnacci et al. gave perimenopausal women calcium alone (n=34), calcium plus kava 100 mg/day (n=15) or calcium plus kava 200 mg/day (n=19). Anxiety, depression and climacteric (menopausal) scores fell on kava, but only the decline of anxiety was significantly greater than the change in the calcium-only group (P<0.009). Sleep was not measured.
The hepatotoxicity caution is particularly relevant in perimenopausal women, who may have higher baseline transaminase elevations (non-alcoholic fatty liver disease (NAFLD) prevalence rises in this age range) and who often use kava in combination with other supplements including black cohosh (also with documented hepatotoxicity concerns). The liver-injury record, and the symptoms of serious liver disease the U.S. Food and Drug Administration lists, are set out in Kava and the Liver below.
How Kava Was Used in the Trials
Doses and Durations in the Trials
- Lehrl 2004 (sleep disturbances with anxiety disorders) — 200 mg a day of a standardized kava extract, or placebo, for 4 weeks
- Wheatley 2001 (open pilot, stress-induced insomnia) — kava 120 mg daily for 6 weeks
- Sarris 2009, KADSS (anxiety) — five tablets a day containing 250 mg of kavalactones a day, in 3-week placebo-controlled crossover phases
- Sarris 2020 (diagnosed generalised anxiety disorder) — an aqueous extract of dried kava root standardised to 120 mg of kavalactones twice a day, for 16 weeks; kava was not better than placebo, and liver function test abnormalities were more frequent on kava
- Cagnacci 2003 (perimenopausal women) — kava 100 mg/day or 200 mg/day with calcium, for 3 months
Product Types Practitioners Describe
- Noble cultivar aqueous root extract (instant kava, freeze-dried aqueous extract, or traditional cold-water preparation)
- Standardized to a known kavalactone content (typically 30–70 mg kavalactones per serving)
- Acetonic, ethanolic, or supercritical CO2 extracts are a stated concern unless flavokavain B and pipermethystine content is documented as low
- Root-only labeling, not aerial parts or whole plant
Sleep Dosing Described by Practitioners
- Practitioners describe starting with 60–120 mg kavalactones taken 45–60 minutes before bedtime, and going up to 180–240 mg kavalactones at bedtime if 60–120 mg is insufficient
- For mid-night awakening, a second 60 mg dose at the awakening is described, only in the first half of the night because of morning grogginess
- Combination with melatonin 0.5–1 mg at bedtime is described where circadian misalignment is also present
- These schedules come from practice; the trials above used the doses listed in the first list
What Users Describe
- Subjective relaxation within 20–45 minutes of ingestion
- Sleep onset within 30–60 minutes typically
- Sleep quality often improves more than sleep onset time per se — patients commonly report waking less often, returning to sleep faster after middle-night awakenings, and feeling more rested
- An effect that tends to build over the first 1–2 weeks of consistent use
- A numb mouth/tongue effect at higher traditional doses, described as harmless
Interactions and Hazards
- Alcohol the same evening — additive central nervous system depression and additive hepatic stress
- Acetaminophen the same evening, particularly > 1 g — a 2004 review of kava liver cases found 23 that also involved other compounds with potential liver toxicity
- Benzodiazepines or z-drugs the same evening — additive sedation
- Driving — practitioners describe caution until a person knows their own response to kava
Cycling
A cycling pattern described by practitioners for chronic nightly use is 4 weeks of nightly use followed by 1 week off, repeated; others describe intermittent use (3–4 nights per week, on the worst-sleep nights) to limit chronic exposure. These patterns come from practice, not from trials.
For broader sleep management see our Sleep Hygiene page and Insomnia page.
Kava and the Liver: the Regulatory Record
Before 1998, according to a 2004 review, kava extracts were considered very safe alternatives to anxiety drugs. By January 2003 kava extracts had been banned in the entire European Union and Canada, and were subject to cautions and advisories by the U.S. Food and Drug Administration, as a result of 11 cases of liver failure leading to liver transplants, including four deaths. The review counted 78 cases of liver toxicity reputedly linked to kava: four probably linked to kavalactones taken alone, and another 23 potentially linked to kava but also involving other compounds with potential liver toxicity. It described kava toxicity as appearing “idiosyncratic” and the potential for drug interactions as large.
The U.S. Food and Drug Administration's consumer advisory of March 25, 2002 states that kava-containing products had been associated with liver-related injuries — including hepatitis, cirrhosis, and liver failure — in over 25 reports of adverse events in other countries, and that four patients required liver transplants. In the U.S., the agency had received a report of a previously healthy young female who required liver transplantation, as well as several reports of liver-related injuries. The advisory lists jaundice (yellowing of the skin or whites of the eyes) and brown urine as symptoms of serious liver disease, and nausea, vomiting, light-colored stools, unusual tiredness, weakness, stomach or abdominal pain, and loss of appetite as non-specific symptoms of liver disease.
In the 2020 trial of an aqueous kava root extract (171 people, 16 weeks), liver function test abnormalities were significantly more frequent in the kava group than in the placebo group, although no participant met criteria for herb-induced liver injury.
Key Research Papers
- Lehrl S (2004). Clinical efficacy of kava extract WS 1490 in sleep disturbances associated with anxiety disorders. Journal of Affective Disorders. — PubMed PMID: 14706720
- Wheatley D (2001). Kava and valerian in the treatment of stress-induced insomnia. Phytotherapy Research. — PubMed PMID: 11536390
- Cagnacci A et al. (2003). Kava-Kava administration reduces anxiety in perimenopausal women. Maturitas. — PubMed PMID: 12590005
- Ernst E (2006). Herbal remedies for anxiety - a systematic review of controlled clinical trials. Phytomedicine. 13(3):205–208 — PubMed PMID: 16428031
- Sarris J, McIntyre E, Camfield DA (2013). Plant-based medicines for anxiety disorders, part 2: a review of clinical studies with supporting preclinical evidence. CNS Drugs. 27(4):301–319 — PubMed PMID: 23653088
- Geier FP, Konstantinowicz T (2004). Kava treatment in patients with anxiety. Phytotherapy Research. — PubMed PMID: 15162364
- Gray SL et al. (2015). Cumulative use of strong anticholinergics and incident dementia. JAMA Internal Medicine. — PubMed PMID: 25621434 (context for diphenhydramine comparison)
- Shinomiya K, Inoue T, Utsu Y, et al. (2005). Effects of kava-kava extract on the sleep-wake cycle in sleep-disturbed rats. Psychopharmacology. 180(3):564–569 — PubMed PMID: 15700178 (rat study; no human polysomnography study of kava is indexed in PubMed)
- Sarris J, Moylan S, Camfield DA, et al. (2012). Complementary medicine, exercise, meditation, diet, and lifestyle modification for anxiety disorders: a review of current evidence. Evidence-Based Complementary and Alternative Medicine. 2012:809653 — PubMed PMID: 22969831
- Chua HC, Christensen ET, Hoestgaard-Jensen K, et al. (2016). Kavain, the Major Constituent of the Anxiolytic Kava Extract, Potentiates GABAA Receptors: Functional Characteristics and Molecular Mechanism. PLoS One. 11(6):e0157700 — PubMed PMID: 27332705
- Leach MJ, Page AT (2015). Herbal medicine for insomnia: A systematic review and meta-analysis. Sleep Medicine Reviews. 24:1–12 — PubMed PMID: 25644982
- Sarris J, Kavanagh DJ, Byrne G, et al. (2009). The Kava Anxiety Depression Spectrum Study (KADSS): a randomized, placebo-controlled crossover trial using an aqueous extract of Piper methysticum. Psychopharmacology. 205(3):399–407 — PubMed PMID: 19430766
- Sarris J, Byrne GJ, Bousman CA, et al. (2020). Kava for generalised anxiety disorder: A 16-week double-blind, randomised, placebo-controlled study. Australian and New Zealand Journal of Psychiatry. 54(3):288–297 — PubMed PMID: 31813230
- Clouatre DL (2004). Kava kava: examining new reports of toxicity. Toxicology Letters. 150(1):85–96 — PubMed PMID: 15068826
- U.S. Food and Drug Administration (2002). Consumer Advisory: Kava-Containing Dietary Supplements May be Associated With Severe Liver Injury. March 25, 2002 — FDA consumer advisory (archived copy)