Kava for Anxiety Relief
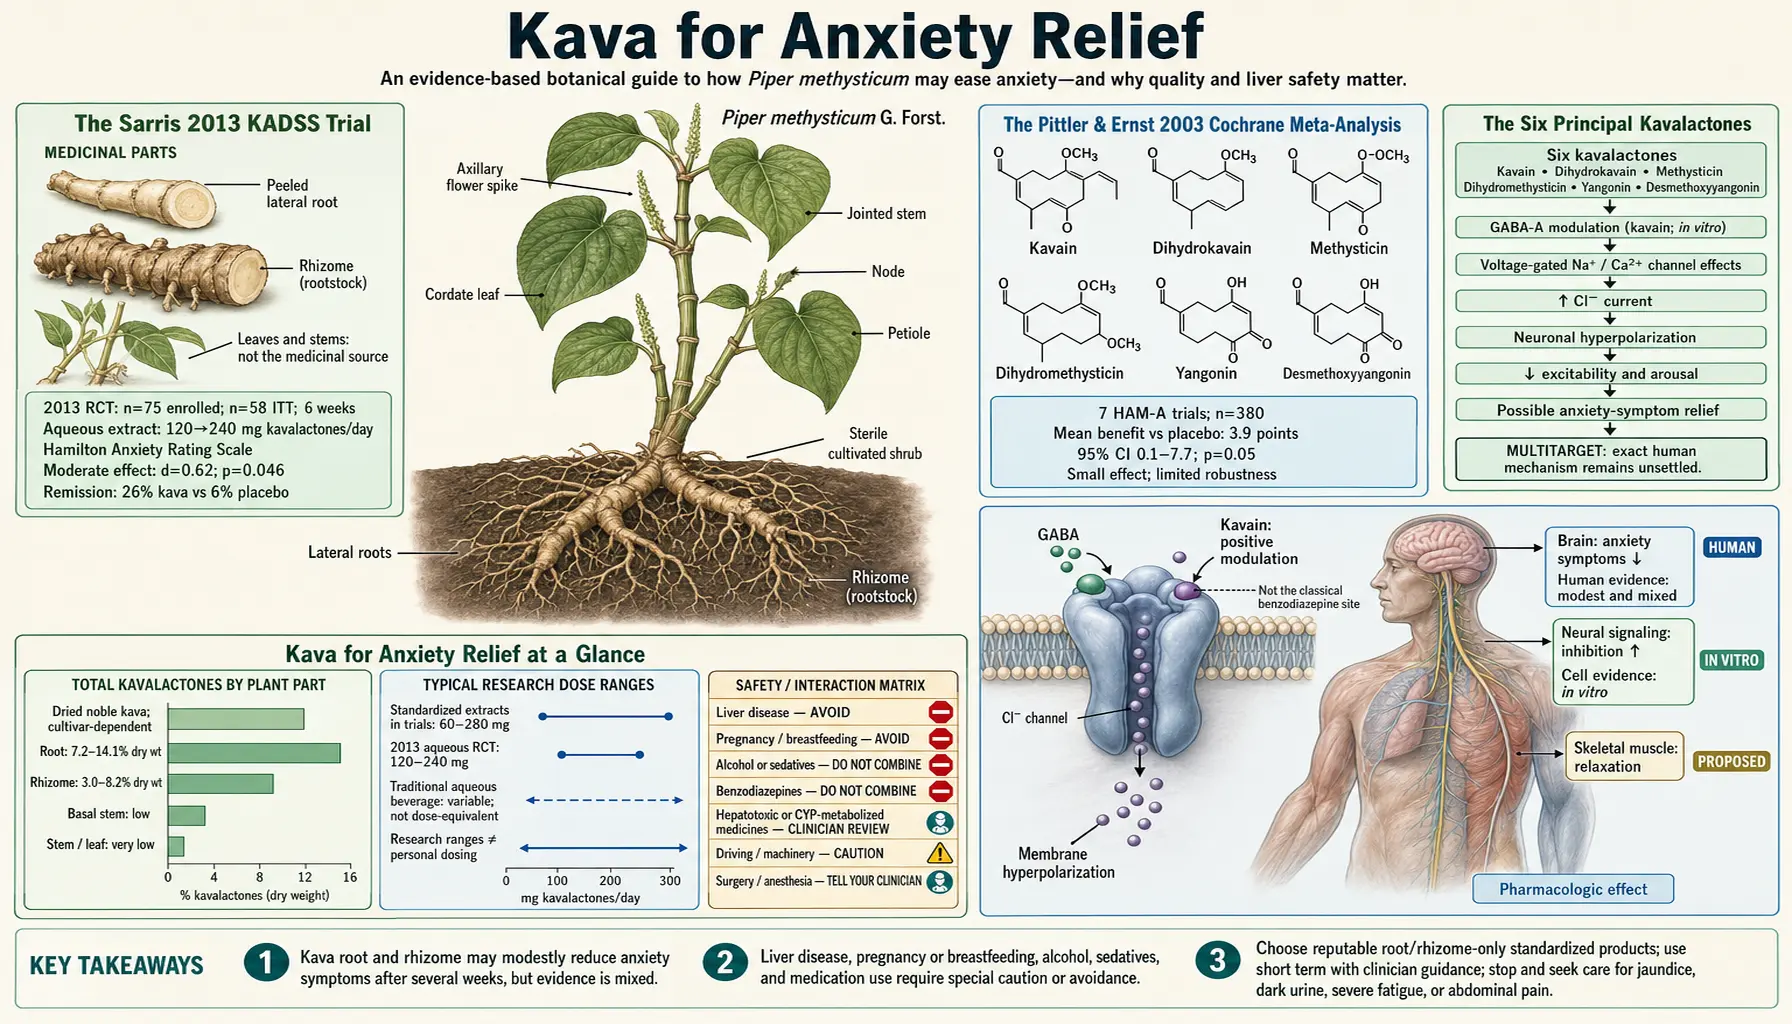
Kava (Piper methysticum) has been tested for anxiety in a series of randomized controlled trials (RCTs) with mixed results: the 2013 Sarris trial found a significant reduction in generalized anxiety disorder symptoms versus placebo, the Pittler & Ernst 2003 Cochrane review (11 trials, 645 participants) found a significant reduction in Hamilton anxiety scores in a meta-analysis of six of those trials, and the larger 16-week 2020 Sarris trial found no benefit over placebo. A 2022 guideline from the World Federation of Societies of Biological Psychiatry (WFSBP) and the Canadian Network for Mood and Anxiety Treatments (CANMAT) rated kava as not recommended for generalised anxiety disorder. The mechanism is positive allosteric modulation of gamma-aminobutyric acid-A receptors by the kavalactone class — principally kavain, methysticin, and yangonin — at sites distinct from the benzodiazepine binding pocket, producing anxiolysis without the tolerance, withdrawal, or amnestic effects characteristic of benzodiazepines. This deep-dive walks through the clinical trial evidence, the gamma-aminobutyric acid-A pharmacology, the comparison to benzodiazepines and selective serotonin reuptake inhibitors (SSRIs), and how kava has been used for mild to moderate generalized anxiety.
Table of Contents
- The Sarris 2013 Generalized Anxiety Disorder Trial
- The Pittler & Ernst 2003 Cochrane Meta-Analysis
- The Six Principal Kavalactones
- Gamma-Aminobutyric Acid-A Allosteric Modulation Mechanism
- Kava versus Benzodiazepines
- Kava versus Selective Serotonin Reuptake Inhibitors and Buspirone
- Trial History (Volz 1997 to Witte 2005)
- A 2018 Review and a 2022 Guideline Weigh the Kava Trials
- Dosing and Practical Use for Anxiety
- Social Anxiety and Performance Anxiety
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Sarris 2013 Generalized Anxiety Disorder Trial
One of the main pieces of modern evidence that kava reduces anxiety in clinically diagnosed anxiety disorder is the Sarris et al. 2013 trial, published in the Journal of Clinical Psychopharmacology. The study enrolled 75 adults with DSM-IV diagnosed generalized anxiety disorder and no comorbid mood disorder (Hamilton Anxiety Rating Scale (HAM-A) ≥ 20 at baseline), randomized them double-blind to either an aqueous extract of noble Vanuatu kava cultivar (titrated to 120 mg kavalactones per day for the first three weeks, escalated to 240 mg/day for an additional three weeks if needed) or matched placebo, and measured HAM-A change at 6 weeks.
The results:
- HAM-A reduction — in the intention-to-treat analysis of 58 participants, anxiety fell significantly more in the kava group than in the placebo group, with a moderate effect size (P = 0.046, Cohen d = 0.62); among participants with moderate to severe generalized anxiety disorder the effect was larger (P = 0.02; d = 0.82)
- Remission rate — 26% of the kava group versus 6% of the placebo group achieved full remission (HAM-A ≤ 7) by week 6
- No comorbid depression — the trial enrolled only people with no comorbid mood disorder; the improvement in Montgomery-Åsberg Depression Rating Scale (MADRS) scores reported for kava comes from the earlier 2009 Kava Anxiety Depression Spectrum Study (KADSS) crossover trial (see Trial History below)
- Liver function — serial liver function tests (alanine aminotransferase (ALT), aspartate aminotransferase (AST), gamma-glutamyl transferase (GGT), alkaline phosphatase, bilirubin) showed no significant change in the kava group versus placebo, supporting the safety of noble-cultivar aqueous root extracts
- Adverse events — the kava group reported more headaches (P = 0.05); no other adverse effect differed significantly between the groups. A companion analysis of the same trial found that kava significantly increased women's sexual drive compared with placebo (p = 0.040), with no negative sexual effects seen in men
The 2013 trial was important because it used a noble Vanuatu cultivar aqueous extract — the traditional preparation type — rather than the acetonic or ethanolic extracts implicated in the 2002 European hepatotoxicity controversy. The clean liver function results at clinical doses are themselves a contribution to the kava safety literature, beyond the primary efficacy finding.
A larger 2020 follow-up trial by Sarris and colleagues tested an aqueous extract of dried kava root (standardised to 120 mg of kavalactones twice a day) for 16 weeks in 171 people with diagnosed generalised anxiety disorder. It found no significant difference from placebo (a relative reduction favouring placebo of 1.37 points; p = 0.25), and 17.4% of the kava group were remitted versus 23.8% of the placebo group. Liver function test abnormalities were significantly more frequent in the kava group, although no participant met criteria for herb-induced liver injury. The authors concluded that this extract was not effective for diagnosed generalised anxiety disorder. Both the 2013 and the 2020 trials used aqueous root extracts.
The Pittler & Ernst 2003 Cochrane Meta-Analysis
The Pittler and Ernst 2003 Cochrane systematic review included 11 randomized double-blind placebo-controlled trials of kava extract for anxiety, with a total of 645 participants. Six of these studies (345 participants) used the Hamilton Anxiety Rating Scale (HAM-A) total score as a common outcome and were pooled in a meta-analysis, which found a significant reduction in patients receiving kava extract compared with patients receiving placebo (weighted mean difference 5.0 points, 95% confidence interval (CI) 1.1 to 8.8; p = 0.01). Adverse events reported in the reviewed trials were mild, transient and infrequent.
The Cochrane review noted several important caveats:
- Heterogeneity of extract type — the 11 included trials used different kava preparations (predominantly a standardised acetone extract, but also a methanolic extract and others). Effect sizes varied with extract type.
- Generally short duration — most trials were 4 to 12 weeks. Longer-term efficacy and safety were not addressed.
- Generally mild-to-moderate baseline anxiety — trials enrolled patients with anxiety symptoms (mostly tension, mixed anxiety/depression, generalized anxiety) but typically not severe panic disorder or specific phobia
- Safety signal — the meta-analysis reviewed adverse event reporting and found no significant difference in adverse event rate between kava and placebo. However, the pooled trials predated much of the 2002 hepatotoxicity reporting and could not address that issue directly.
The 2003 Cochrane review concluded that, compared with placebo, kava extract "appears to be an effective symptomatic treatment option for anxiety" and that the available data suggest it is relatively safe for short-term treatment (1 to 24 weeks), although more information is required; the reviewers called for further rigorous investigation, particularly into the long-term safety profile of kava.
The Pittler Cochrane review and the 2013 Sarris trial are the main positive evidence for kava in anxiety. Against them stand the negative 2002 Connor & Davidson trial and the larger negative 2020 Sarris trial. The 2022 WFSBP and CANMAT guideline rated kava as not recommended for generalised anxiety disorder, while rating ashwagandha and lavender as modestly supported in the treatment of anxiety disorders (see the section on reviews and guidelines below).
The Six Principal Kavalactones
Kava's bioactivity resides in the kavalactone class — styryl-2-pyranones (also called α-pyrones) concentrated in the root and rhizome of Piper methysticum. Six kavalactones together account for approximately 96% of the kavalactone content of a typical noble-cultivar root preparation:
- Kavain (also kawain) — the most extensively studied kavalactone; principal gamma-aminobutyric acid-A allosteric modulator; voltage-gated sodium channel blocker; weak dopamine reuptake inhibitor. Approximately 15–25% of total kavalactones in a typical noble cultivar.
- Methysticin — its rank varies by cultivar (in the noble Borogu chemotype 423561 it comes fifth, after kavain, dihydrokavain, yangonin and dihydromethysticin); gamma-aminobutyric acid-A modulator; neuromuscular effects; weak dopamine reuptake inhibitor. Approximately 10–20% of total kavalactones.
- Yangonin — pigmented kavalactone with characteristic yellow color; principal monoamine oxidase B (MAO-B) inhibitor among the kavalactone class; relevant to mood effects. Approximately 10–20% of total kavalactones.
- Desmethoxyyangonin — structural variant of yangonin with similar MAO-B inhibitory activity; weaker gamma-aminobutyric acid-A activity than kavain. Approximately 5–15% of total kavalactones.
- Dihydromethysticin — saturated version of methysticin; longer-acting at gamma-aminobutyric acid-A; implicated in the longer-duration sedative effect of some preparations. Approximately 5–15% of total kavalactones.
- Dihydrokavain — saturated kavain analog; significant skeletal muscle relaxant activity; less gamma-aminobutyric acid-A modulation than kavain. Approximately 5–15% of total kavalactones.
The relative proportions of these six kavalactones is highly cultivar-specific and is captured in the "chemotype" notation: a six-digit code (e.g. 462531) indicating the rank order of abundance from highest to lowest. The numbers follow the order in which the six kavalactones come off a high-performance liquid chromatography (HPLC) column: desmethoxyyangonin = 1, dihydrokavain = 2, yangonin = 3, kavain = 4, dihydromethysticin = 5, methysticin = 6. A chemotype 462531 cultivar therefore has kavain (#4) as the most abundant and methysticin (#6) as the second; most noble Borogu samples listed in a 2020 review carry the chemotype 423561 (Bian et al. 2020). Traditional Pacific kava cultivars have specific chemotypes that have been selected over millennia for their balanced anxiolytic-sedative-muscle-relaxant profile. Cultivars with high flavokavain B and pipermethystine content (the tudei cultivars) have historically been used only in restricted ritual contexts because of their less-tolerated psychoactive and toxicity profile.
The chemotype variability also explains why kava research is so methodologically difficult: a clinical trial of a single standardized extract (e.g. a standardised acetone extract titrated to 70% kavalactones) does not necessarily generalize to a different aqueous root preparation of a different cultivar.
Gamma-Aminobutyric Acid-A Allosteric Modulation Mechanism
The principal anxiolytic mechanism of the kavalactones is positive allosteric modulation of gamma-aminobutyric acid-A receptors — the same receptor class targeted by benzodiazepines, barbiturates, ethanol, neurosteroids, propofol, and zolpidem — but at distinct binding sites with distinct functional consequences.
The gamma-aminobutyric acid-A receptor is a pentameric ligand-gated chloride channel composed of various combinations of subunits (typically two α, two β, and one γ subunit). Gamma-aminobutyric acid (GABA) binding at the α-β interface opens the channel and allows chloride influx, hyperpolarizing the postsynaptic neuron and reducing its excitability. Various allosteric modulators bind at distinct sites on the receptor to enhance (positive modulation) or reduce (negative modulation) gamma-aminobutyric acid's effect:
- The benzodiazepine site at the α-γ interface (sensitive to flumazenil reversal)
- The barbiturate site on the β subunit
- The neurosteroid site on the membrane-facing α subunit
- The ethanol site (multiple proposed locations on α and δ subunits)
The kavalactones do not inhibit the binding of the benzodiazepine-site radioligand [3H]flunitrazepam in radioligand binding studies (Boonen et al. 1998, others), indicating their site of action is distinct from the benzodiazepine site. The exact molecular pocket has not been definitively identified, but pharmacological evidence suggests interaction at the β3 subunit or a novel allosteric site. Functional consequences differ from benzodiazepines in three important ways:
- No cross-tolerance with benzodiazepines — patients on chronic benzodiazepines do not show reduced response to kava, suggesting non-overlapping mechanism
- No flumazenil reversal — the benzodiazepine antagonist flumazenil does not reverse kava-induced anxiolysis, confirming separate sites
- Less amnestic effect — kava at clinical doses does not produce the anterograde amnesia characteristic of benzodiazepines, presumably because it does not act at the hippocampally-enriched α5-containing gamma-aminobutyric acid-A subtype that mediates benzodiazepine amnestic effects
The functional implication is that kava provides gamma-aminobutyric acid-A-mediated anxiolysis without the most problematic side effects of benzodiazepines: tolerance, withdrawal syndrome, amnesia, and abuse liability. This pharmacological profile is the reason kava has been proposed for situations where benzodiazepines are poorly tolerated or carry extra risk — including older patients, patients with substance use history, and patients requiring sustained daily use beyond a few weeks.
For broader context on gamma-aminobutyric acid pharmacology and other natural GABAergic modulators, see the Valerian page and the Passionflower page — both work through partially overlapping but distinct gamma-aminobutyric acid mechanisms.
Kava versus Benzodiazepines
The clinical comparison between kava and benzodiazepines is one of the most important practical questions in botanical anxiolytic medicine. The two classes target overlapping receptor populations but produce meaningfully different clinical profiles.
Where Kava Wins
- No physical dependence or withdrawal — kava does not produce a benzodiazepine-style withdrawal syndrome on discontinuation. There is no documented requirement for tapering. This is the single most important practical advantage in patients who would otherwise need chronic anxiolytic therapy.
- No anterograde amnesia — clinical doses of kava do not impair encoding of new memories, in contrast to benzodiazepines
- Less cognitive blunting — kava at clinical doses does not impair reaction time, working memory, or driving simulator performance (see the Mood and Cognitive Effects deep-dive)
- No respiratory depression — kava does not produce the respiratory depression risk that makes benzodiazepines dangerous in overdose or in combination with opioids
- No paradoxical disinhibition — benzodiazepines occasionally produce paradoxical agitation, aggression, or disinhibition, particularly in older adults and those with personality disorders. This is not a documented effect of kava.
Where Benzodiazepines Win
- Onset speed — sublingual or intravenous (IV) benzodiazepines act in minutes for acute panic or severe agitation. Oral kava onset is 20–45 minutes.
- Potency — benzodiazepines produce stronger anxiolysis in severe acute anxiety, panic, or pre-procedural sedation. Kava's clinical effect size in the trials is moderate, not large.
- Reliability across patients — benzodiazepine response is highly predictable. Kava response varies meaningfully with cultivar, extract type, and individual pharmacogenomics.
- Hepatic safety record — though kava-related hepatotoxicity is overwhelmingly associated with poor-quality extracts of aerial plant material (see the Hepatotoxicity Controversy section on the hub page), benzodiazepines have a cleaner hepatic safety profile in absolute terms.
In summary, benzodiazepines act faster and more strongly in acute severe anxiety and pre-procedural sedation, while kava's trial evidence concerns mild-to-moderate generalized anxiety, with mixed results (see Trial History below). Other factors that bear on the comparison are history of substance use disorder, age, and concurrent medications.
Kava versus Selective Serotonin Reuptake Inhibitors and Buspirone
Selective serotonin reuptake inhibitors (sertraline, escitalopram, paroxetine) are first-line pharmacological therapy for generalized anxiety disorder in most modern psychiatric guidelines. Buspirone (a 5-HT1A partial agonist) is a second-line oral agent specifically approved for generalized anxiety disorder (GAD). Kava's place in this hierarchy is not formally established; the 2022 WFSBP and CANMAT guideline rated it as not recommended for GAD. The situations in which kava has been proposed are listed below.
Onset and Time Course
- Selective serotonin reuptake inhibitors — 4–8 weeks to clinical effect; common early-treatment activation, gastrointestinal (GI) upset, sexual dysfunction; discontinuation syndrome possible especially with paroxetine
- Buspirone — 2–4 weeks to clinical effect; well-tolerated; no significant withdrawal; modest efficacy
- Kava — effect emerges within days to weeks; the 2013 Sarris trial showed measurable separation from placebo by week 2; no withdrawal syndrome; modest efficacy similar to buspirone
Clinical Niche for Kava
- Patients who have failed or cannot tolerate selective serotonin reuptake inhibitors (typically due to sexual dysfunction, gastrointestinal upset, or activation/agitation)
- Patients who refuse selective serotonin reuptake inhibitors based on preference or stigma concerns
- Patients requiring acute symptomatic relief while waiting for selective serotonin reuptake inhibitor (SSRI) onset
- Patients with anxiety that is primarily situational or stress-related rather than chronic
- Older patients in whom benzodiazepines are contraindicated and selective serotonin reuptake inhibitors may cause hyponatremia or fall risk
Combination Considerations
Combining kava with selective serotonin reuptake inhibitors is not absolutely contraindicated but warrants caution because the MAO-B inhibitory activity of yangonin and desmethoxyyangonin could theoretically interact with serotonergic medications. In practice, the in vivo MAO-B inhibition appears clinically modest and serotonin syndrome from this combination is not well-documented in case reports, but conservative clinicians avoid the combination. Combining kava with benzodiazepines raises a concern for additive central nervous system (CNS) depression, even though the receptor sites are distinct.
For broader context on natural anxiety remedies and stress management, see our Natural Anxiety Relief page and Stress Management page.
Trial History (Volz 1997 to Witte 2005)
The clinical trial literature on kava for anxiety spans nearly three decades and includes more than 20 randomized controlled trials. The principal milestones:
- Lehmann 1996 — one of the earliest controlled trials, 58 patients with anxiety of non-mental origin, demonstrated symptomatic improvement with a standardised kava extract versus placebo
- Volz & Kieser 1997 — the most cited European trial of kava for anxiety. 101 patients with various anxiety disorders, randomized to a standardised acetone kava extract (100 mg three times daily, providing 210 mg kavalactones/day) or placebo for 25 weeks. The HAM-A score reduction was significantly greater in the kava group, and the separation appeared as early as week 8.
- Watkins et al. 2001 — small mechanistic study (6 patients on kava, 7 on placebo) of kava's effect on vagal control of heart rate in generalized anxiety disorder; significantly more kava-treated patients showed improved baroreflex control of heart rate, and the size of that improvement tracked clinical improvement, while respiratory sinus arrhythmia did not respond
- Connor & Davidson 2002 — US trial in 37 adults with DSM-IV generalized anxiety disorder over 4 weeks; both groups improved, but kava was not superior to placebo in the principal analysis; published just as the European hepatotoxicity controversy was emerging and contributed to subsequent caution
- Pittler & Ernst 2003 Cochrane review — meta-analytic synthesis of available trials; the six pooled trials showed a significant reduction in Hamilton anxiety scores (weighted mean difference 5.0 points)
- Witte et al. 2005 — meta-analysis of six placebo-controlled randomized trials of one standardised acetone extract; mean improvement 5.94 points (95% CI -0.86 to 12.8) on the HAM-A scale better than placebo, and a success-rate odds ratio of 3.3 (95% CI 2.09–5.22)
- Sarris et al. 2009 (KADSS) — the Kava Anxiety Depression Spectrum Study, a 3-week placebo-controlled, double-blind crossover trial of an aqueous kava extract (250 mg of kavalactones a day) in 60 adults with 1 month or more of elevated generalized anxiety. Hamilton anxiety scores fell by 9.9 points on kava versus 0.8 points on placebo in the first controlled phase; the pooled effect across both phases was highly significant (p < 0.0001) with a large effect size (d = 2.24), Beck Anxiety Inventory and Montgomery-Åsberg Depression Rating Scale scores also fell significantly, and there were no serious adverse effects and no clinical liver toxicity
- Sarris et al. 2013 — the 6-week trial in 75 people with generalized anxiety disorder discussed in detail above; positive (P = 0.046, Cohen d = 0.62)
- Sarris et al. 2020 — larger 16-week trial in 171 people with diagnosed GAD, using an aqueous extract of dried kava root (120 mg of kavalactones twice a day); no significant difference from placebo (a relative reduction favouring placebo of 1.37 points; p = 0.25). Liver function test abnormalities were significantly more frequent on kava, although no participant met criteria for herb-induced liver injury. The authors wrote that research has generally supported kava in non-clinical populations (potentially for more situational anxiety, as a short-term anxiolytic), but that this extract was not effective for diagnosed generalised anxiety disorder.
The overall pattern across nearly three decades of trials is mixed. The 2009 crossover trial and the 2013 trial of aqueous root extracts were positive, but the larger and longer 2020 trial of an aqueous root extract was negative. Why the large 2009 result and the negative 2020 result differ so much is an open question.
A 2018 Review and a 2022 Guideline Weigh the Kava Trials
A 2018 systematic review by Smith and Leiras found 11 eligible articles, 7 of them comparing kava with placebo. Kava was more effective than placebo in 3 of those 7 trials. Pooling responder rates from 5 trials (330 people) gave a risk ratio of 1.50 (95% CI 1.12 to 2.01) in kava's favour, and adverse events were no different from placebo (P = 0.574). The authors concluded that kava "appears to be a short-term treatment for anxiety, but not a replacement for prolonged anti-anxiety use", and noted that, although not seen in their review, liver toxicity is "especially possible if taken longer than 8 weeks".
In 2022 an international taskforce of the World Federation of Societies of Biological Psychiatry (WFSBP) and the Canadian Network for Mood and Anxiety Treatments (CANMAT) — 31 academics and clinicians from 15 countries — graded nutrient and plant medicines for psychiatric disorders, looking mainly at meta-analyses and at two or more randomized trials. It rated kava "(-)", not recommended for generalised anxiety disorder. In the same guideline, ashwagandha and lavender were modestly supported in the treatment of anxiety disorders, and chamomile was not currently recommended for generalised anxiety disorder. The guideline also notes that single trials, open-label studies, case studies and traditional use were not assessed, and that an absence of data does not imply lack of efficacy.
Dosing and Practical Use for Anxiety
Effective anxiolytic dosing for kava is measured in milligrams of total kavalactones per day, not in grams of root or milliliters of preparation. Different products have different kavalactone concentrations, so reading the label for kavalactone content is essential.
Dose Ranges from the Trial Literature
- Minimum anxiolytic dose — approximately 60 mg kavalactones/day; below this, most trials fail to separate from placebo
- Standard anxiolytic dose — 120–240 mg kavalactones/day, typically divided into 2–3 doses; this is the range used in the 2013 Sarris trial
- Standardised acetone extract (used in much of the European trial literature) — 100 mg three times daily, providing ~210 mg kavalactones/day
- Traditional Pacific kava preparation — a single "shell" of traditional aqueous extract typically delivers 100–250 mg kavalactones; a social session might involve 4–8 shells over 2–3 hours
Onset and Duration
- Onset — 20–45 minutes after oral dosing; faster on empty stomach
- Peak effect — 1–2 hours after dosing
- Duration — 4–6 hours of subjective effect; longer-acting dihydromethysticin component may extend perceived effect to 8 hours
- Steady-state effect — full anxiolytic effect from regular daily dosing typically establishes by 2–4 weeks of consistent intake, similar to the time course of buspirone
Product Selection
- Products labeled "noble cultivar" carry cultivar names from the Vanuatu noble list (Borogu, Melomelo, Palarasul, others)
- Aqueous extract or instant kava ("water soluble") preparations are water-based, like the traditional drink; acetonic, ethanolic, and supercritical CO2 extracts are made with solvents
- Labels distinguish "root only" material from "aerial parts" or "whole plant"
- Third-party noble-cultivar certification schemes exist
- Traditional preparation of whole-root kava: 1–3 tablespoons of ground noble root in cold water, kneaded in a strainer bag for 5–10 minutes, strained, consumed
Cycling and Duration of Use
Traditional Pacific use is social and ceremonial, not daily medication. For modern anxiolytic use, some practitioners describe cycling the herb — for example, 4 weeks of daily use followed by a 1-week break. A liver monitoring schedule described for daily kava users is liver function testing (alanine aminotransferase, aspartate aminotransferase, gamma-glutamyl transferase, alkaline phosphatase, total bilirubin) before starting and after the first month, with repeats every 3–6 months. A 2018 systematic review notes that liver toxicity is "especially possible if taken longer than 8 weeks".
Social Anxiety and Performance Anxiety
While most randomized controlled trial evidence for kava concerns generalized anxiety disorder, traditional Pacific use is overwhelmingly in social and ceremonial contexts — a context that maps onto modern Western diagnostic categories of social anxiety disorder and situational performance anxiety. The subjective qualities reported by long-time kava users are precisely those one would want for these conditions: sociable but not euphoric, relaxed but mentally clear, fluent but not impulsive.
Pilot evidence for kava in social anxiety disorder is suggestive but limited. A small open-label study in social phobia patients found measurable improvement on Liebowitz Social Anxiety Scale scores. No large randomized controlled trial has specifically targeted social anxiety disorder as the primary diagnosis.
The use case for kava in performance anxiety (public speaking, stage performance, test-taking, athletic performance, situations where benzodiazepines are problematic because of their cognitive blunting) is supported by mechanistic arguments and by traditional use evidence but not by formal randomized controlled trial (RCT) data. The practical considerations:
- Onset of 20–45 minutes means the effect arrives 20–45 minutes after a dose, not at the moment of acute symptoms
- Effect on cognitive performance is neutral at clinical doses, in contrast to beta-blockers (which can cause fatigue) and benzodiazepines (which impair memory and reaction time) — an advantage for situations requiring cognitive performance
- The 4–6 hour duration matches a typical examination, presentation, or stage performance window
- Repeat dosing over several days (multi-day examinations, tournament play) is a use some people describe
For broader context on anxiety conditions, see our Anxiety page.
Cautions and Drug Interactions
- Hepatotoxicity from poor-quality extracts — the most important caution, covered comprehensively in the dedicated section on the Benefits hub page. Liver problems are not limited to poor-quality extracts: in the 2020 trial of an aqueous root extract (120 mg of kavalactones twice a day) over 16 weeks, liver function test abnormalities were significantly more frequent on kava than on placebo, although no participant met criteria for herb-induced liver injury. Monitoring schedules described for daily users include liver function tests before starting and periodically after.
- Concurrent alcohol — substantially increases hepatic risk and additive central nervous system depression. The 2002 European case reports of severe hepatotoxicity frequently involved concurrent alcohol consumption.
- Concurrent acetaminophen — both compete for hepatic glutathione conjugation. A cautious limit of less than 2 g/day of acetaminophen is described for kava users, and the concern is greatest with daily long-term kava use.
- Concurrent benzodiazepines, opioids, or alcohol — additive central nervous system depression and respiratory effects; the research raises a concern for anyone combining them.
- Concurrent selective serotonin reuptake inhibitors or monoamine oxidase inhibitors (MAOIs) — theoretical risk of serotonin syndrome from the MAO-B inhibitory activity of yangonin. The concern is strongest for monoamine oxidase inhibitors and smaller for selective serotonin reuptake inhibitors.
- Cytochrome P450 (CYP450) interactions — kavalactones inhibit CYP1A2, CYP2C9, CYP2C19, CYP2D6, and CYP3A4 in vitro. Clinical implications include possible elevated levels of warfarin, phenytoin, statins, and many other substrates. The concern is greatest for narrow-therapeutic-index medicines, where small changes in blood levels matter.
- Driving and operating machinery — though kava at clinical doses does not measurably impair driving simulator performance, individual response varies, so the trial averages do not predict how a given person will drive on kava.
- Pregnancy and breastfeeding — there is no good safety data on kava in pregnancy or breastfeeding
- Parkinson's disease — case reports of worsened parkinsonian symptoms with chronic high-dose kava use, possibly via dopaminergic interaction; these reports raise a concern for people with established Parkinson's.
- Pre-existing liver disease — absolute contraindication in active hepatitis, cirrhosis, or non-alcoholic fatty liver disease (NAFLD) with elevated transaminases
- Pre-surgical period — a stop of at least 2 weeks before elective surgery is commonly described, because of additive sedation with general anesthesia
- Dermopathy ("kava dermopathy") — chronic high-dose use (typical of daily Pacific consumers) can produce a reversible dry, scaly, yellowish skin rash. The mechanism may be interference with cholesterol metabolism. Resolves on discontinuation.
Key Research Papers
- Sarris J, Stough C, Bousman CA, et al. (2013). Kava in the treatment of generalized anxiety disorder: a double-blind, randomized, placebo-controlled study. Journal of Clinical Psychopharmacology. 33(5):643-8. — PubMed PMID: 23635869
- Sarris J, Stough C, Teschke R, et al. (2013). Kava for the treatment of generalized anxiety disorder RCT: analysis of adverse reactions, liver function, addiction, and sexual effects. Phytotherapy Research. 27(11):1723-8. — PubMed PMID: 23348842
- Sarris J, Kavanagh DJ, Byrne G, Bone KM, Adams J, Deed G (2009). The Kava Anxiety Depression Spectrum Study (KADSS): a randomized, placebo-controlled crossover trial using an aqueous extract of Piper methysticum. Psychopharmacology (Berl). 205(3):399-407. — PubMed PMID: 19430766
- Pittler MH, Ernst E (2003). Kava extract for treating anxiety. Cochrane Database of Systematic Reviews. — PubMed PMID: 12535473
- Volz HP, Kieser M (1997). Kava-kava extract [a standardised acetone extract] versus placebo in anxiety disorders — a randomized placebo-controlled 25-week outpatient trial. Pharmacopsychiatry. — PubMed PMID: 9065962
- Lehmann E et al. (1996). Efficacy of a special kava extract in patients with states of anxiety. Phytomedicine. — PubMed PMID: 23194958
- Connor KM, Davidson JR (2002). A placebo-controlled study of Kava kava in generalized anxiety disorder. International Clinical Psychopharmacology. 17(4):185-8. — PubMed PMID: 12131602
- Witte S, Loew D, Gaus W (2005). Meta-analysis of the efficacy of the acetonic kava-kava extract [a standardised extract] in patients with non-psychotic anxiety disorders. Phytotherapy Research. — PubMed PMID: 15934028
- Sarris J, Byrne GJ, Bousman CA, et al. (2020). Kava for generalised anxiety disorder: A 16-week double-blind, randomised, placebo-controlled study. Australian and New Zealand Journal of Psychiatry. 54(3):288-297. — PubMed PMID: 31813230
- Watkins LL, Connor KM, Davidson JR (2001). Effect of kava extract on vagal cardiac control in generalized anxiety disorder: preliminary findings. Journal of Psychopharmacology. 15(4):283-6. — PubMed PMID: 11769822
- Boonen G, Häberlein H (1998). Influence of genuine kavapyrone enantiomers on the GABA-A binding site. Planta Medica. 64(6):504-6. — PubMed PMID: 9776662
- Singh YN, Singh NN (2002). Therapeutic potential of kava in the treatment of anxiety disorders. CNS Drugs. — PubMed PMID: 12383029
- Sarris J, Kavanagh DJ (2009). Kava and St. John's wort: current evidence for use in mood and anxiety disorders. Journal of Alternative and Complementary Medicine. — PubMed PMID: 19614563
- Smith K, Leiras C (2018). The effectiveness and safety of Kava Kava for treating anxiety symptoms: systematic review and analysis of randomized clinical trials. Complementary Therapies in Clinical Practice. — PubMed PMID: 30396607
- Sarris J, Ravindran A, Yatham LN, et al. (2022). Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety Treatments (CANMAT) Taskforce. World Journal of Biological Psychiatry. 23(6):424-455. — PubMed PMID: 35311615
- Bian T, Corral P, Wang Y, et al. (2020). Kava as a Clinical Nutrient: Promises and Challenges. Nutrients. 12(10):3044. — PubMed PMID: 33027883
PubMed Topic Searches
Connections
- All Herbs
- Kava Overview
- Kava Benefits Hub
- Kava for Sleep
- Kava for Muscle Relaxation
- Kava for Mood
- Anxiety
- Depression
- Natural Anxiety Relief
- Stress Management
- Valerian (Gamma-Aminobutyric Acid Reuptake)
- Passionflower (Gamma-Aminobutyric Acid-A)
- Lavender
- Lemon Balm
- Ashwagandha (Hypothalamic-Pituitary-Adrenal Axis)
- History