Pau d'Arco — Benefits Deep Dive
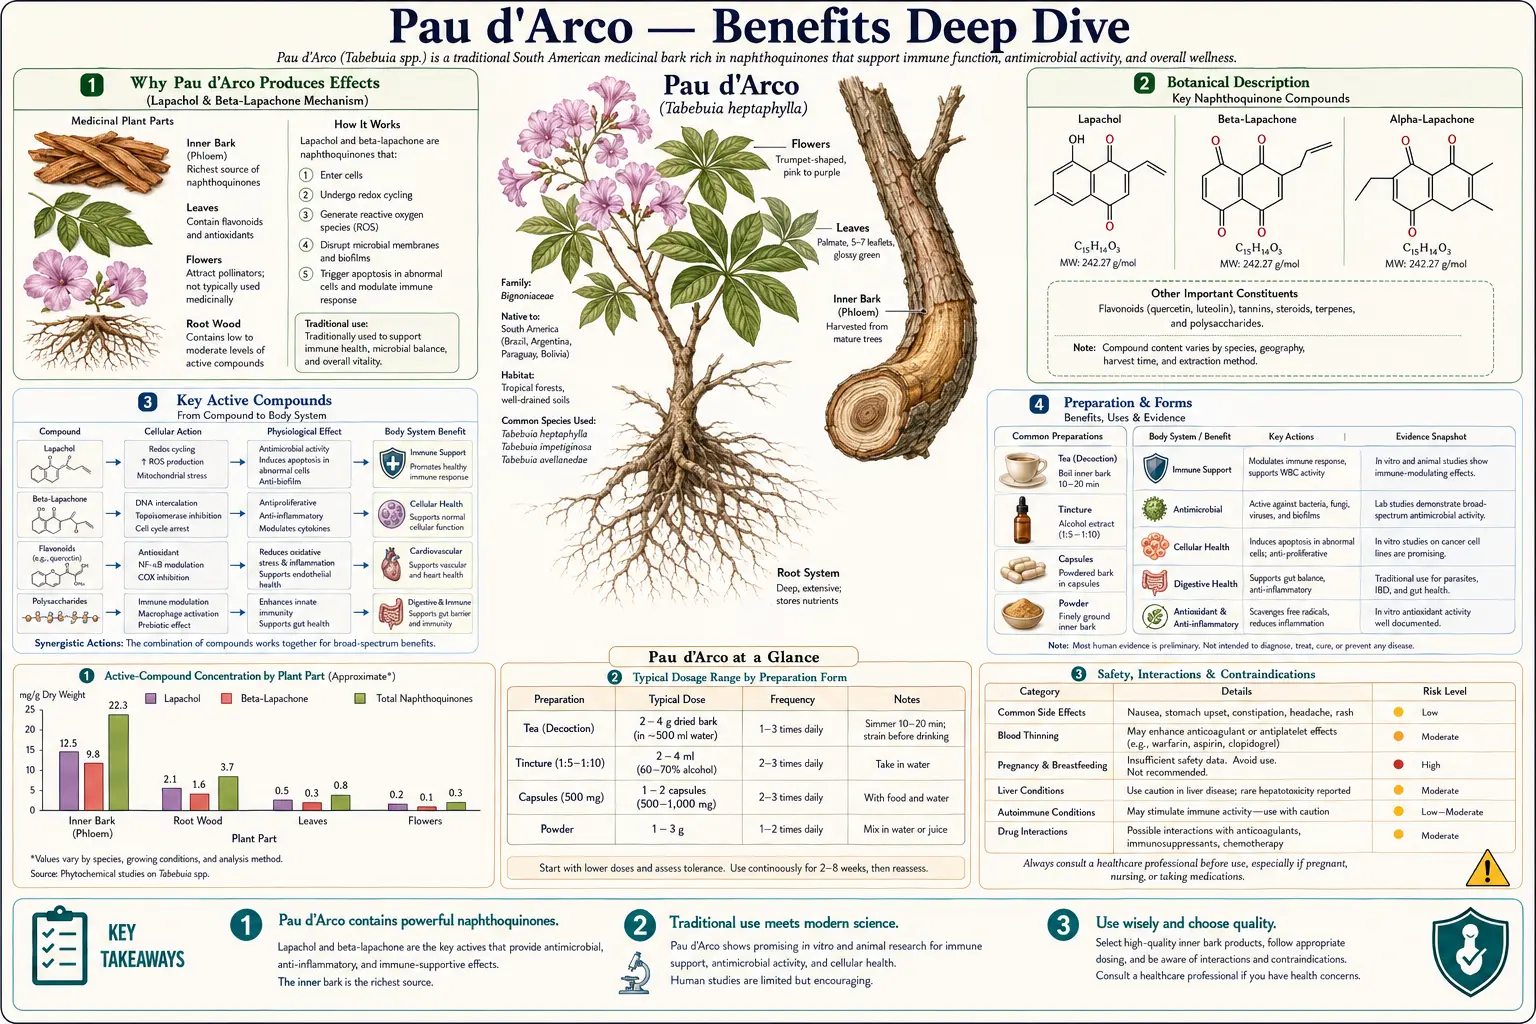
Pau d'Arco — the inner bark of Tabebuia impetiginosa (now reclassified as Handroanthus impetiginosus) — is the South American "lapacho" or "ipê-roxo," the famed "miracle tree" of Brazilian and Argentinian folk medicine. The Guaraní, the Andean Kallawaya healers of Bolivia, and other South American peoples have used its inner-bark decoctions for centuries as a "blood purifier" and broad-spectrum remedy for fungal infection, fever, wounds, dysentery, and chronic inflammation. The principal medicinal compounds are two naphthoquinones — lapachol and the more potent beta-lapachone — which generate intracellular reactive oxygen species, inhibit DNA topoisomerase I and II, suppress inflammation driven by nuclear factor kappa B (NF-κB), and exert direct activity against the yeast Candida albicans and against dermatophyte (skin-infecting) fungi. Four deep-dive pages below cover the four areas where the modern literature is strongest: antifungal action, immune modulation, anti-inflammatory mechanisms, and the cautions / cancer-research story that explains why Pau d'Arco has been treated with both reverence and serious concern by the National Cancer Institute since the 1970s.
Deep-Dive Articles
Antifungal
Lapachol and beta-lapachone naphthoquinone activity against Candida albicans, Aspergillus, and dermatophytes such as Trichophyton. Traditional Brazilian Indigenous use for skin yeast and "white tongue," topical bark decoctions for ringworm and athlete's foot, and the modern role of standardized Pau d'Arco extracts in "candida diet" anti-fungal supplement protocols (alongside caprylic acid, undecylenic acid, and oregano oil). Mechanism: redox cycling generates intracellular superoxide that fungi cannot detoxify as efficiently as mammalian cells.
Read the deep dive →Immune Modulation
Quinone-driven immunomodulation, natural killer (NK) cell activation, macrophage stimulation, and the traditional South American rainforest indication of "blood purification" (depurative). How the same redox-cycling that kills fungi also activates innate immune cells at lower doses, the cytokine profile shift documented in murine and in-vitro studies, and the role of Pau d'Arco in traditional Kallawaya and Guaraní medicine for fevers, wound healing, and recurrent infection.
Read the deep dive →Anti-Inflammatory
Beta-lapachone inhibition of NF-κB nuclear translocation, suppression of pro-inflammatory cytokines (tumor necrosis factor-α, interleukin-6, interleukin-1 beta (IL-1β)), cyclooxygenase (COX) inhibition, and the traditional Brazilian use of Pau d'Arco tea for joint pain and arthritis. Mechanistic overlap with curcumin and boswellia at the NF-κB node, with discussion of why the anti-inflammatory dose is generally lower than the antimicrobial dose.
Read the deep dive →Cautions & Cancer Research
The full story of the National Cancer Institute Phase I lapachol trials in the 1970s — terminated due to dose-limiting prothrombin prolongation and gastrointestinal toxicity at the doses needed for antitumor effect. Modern synthetic beta-lapachone and a beta-lapachone analogue in oncology Phase I/II trials. Critical safety warnings: the anticoagulant interaction (beta-lapachone is a vitamin K antagonist functional analog), high-dose hepatotoxicity, hemolytic anemia in glucose-6-phosphate dehydrogenase (G6PD) deficiency, and the absolute contraindication in pregnancy due to teratogenic potential.
Read the deep dive →Table of Contents
Why Pau d'Arco Produces Effects (Lapachol & Beta-Lapachone Mechanism)
The diverse clinical profile of Pau d'Arco — antifungal, immune-stimulating, anti-inflammatory, and historically antitumor — can be traced to a single molecular feature shared by its two principal naphthoquinones, lapachol (2-hydroxy-3-(3-methyl-2-butenyl)-1,4-naphthoquinone) and beta-lapachone (the cyclized ortho-naphthoquinone). Both molecules are redox-active quinones that undergo one-electron reduction inside cells to form unstable semiquinone radicals, which then react with molecular oxygen to regenerate the parent quinone and release a superoxide anion. This catalytic cycle, called redox cycling, deposits reactive oxygen species (ROS) inside the cell at a rate that often overwhelms the antioxidant defenses of fungi, parasites, and rapidly dividing tumor cells — while mammalian cells with intact glutathione, superoxide dismutase, and catalase systems tolerate the stress at lower doses.
- Redox cycling & reactive oxygen species (ROS) — the unifying mechanism. A 2002 review of beta-lapachone describes a futile redox cycle driven by the two-electron enzyme NAD(P)H:quinone oxidoreductase 1 (NQO1) as the proposed way it kills cells: cells that express NQO1 die, cells low in NQO1 are resistant, and at higher concentrations the reactive oxygen species produced appear to be responsible. That review describes tumour cells, not fungal cells; the same quinone redox chemistry is the proposed basis for the antifungal activity against Candida albicans, Aspergillus, and dermatophytes.
- DNA topoisomerase I and II inhibition — DNA topoisomerase I was the first biochemical target of beta-lapachone to be discovered, but the 2002 review notes that its role in cell death is not clear, and the NQO1 cycle described above is the proposed mechanism of cell death. Beta-lapachone itself was later developed as a synthetic drug for oncology Phase I trials, and a 2018 trial of a beta-lapachone analogue was designed around tumour NQO1 levels rather than topoisomerase — covered in detail on the Cautions & Cancer Research page.
- A phase 1 cancer trial of a beta-lapachone analogue (2018) — 42 people with advanced solid tumours received the analogue by 2-hour intravenous infusion. The most common treatment-related side effects were anaemia (79%), fatigue (45%) and low blood oxygen (hypoxia, 33%); short-lived severe hypoxia, which the authors linked to possible methaemoglobinaemia (a blood change that lowers oxygen delivery), occurred in 26%. Anaemia limited the dose. Among 32 patients whose response could be assessed, the best result was stable disease in 12, and 6 had some tumour shrinkage; the authors called this “modest single-agent activity”. This was an intravenous drug in cancer patients, not the bark tea.
- NF-κB nuclear translocation inhibition — at sub-cytotoxic concentrations, beta-lapachone blocks the IκB-kinase complex and prevents NF-κB p65 from translocating to the nucleus, suppressing transcription of tumor necrosis factor-α, interleukin-6 (IL-6), interleukin-1β, cyclooxygenase-2 (COX-2), and inducible nitric oxide synthase (iNOS). The evidence for this comes from cell experiments: a 1999 study in human myeloid (white-blood-cell) U937 cells found that beta-lapachone blocked tumor necrosis factor-triggered NF-κB activation, p65 translocation and the breakdown of its brake protein IκBα, and also abolished activation of activator protein-1 (AP-1); it was also inhibitory in T-cells and epithelial cells. No human anti-inflammatory trial has tested this. This is the proposed molecular basis for the anti-inflammatory effect and overlaps with the mechanism of curcumin, boswellic acids, and resveratrol.
- Innate immune activation — at intermediate doses, the same redox stress in macrophages and dendritic cells stimulates a measurable activation phenotype (upregulated major histocompatibility complex class II (MHC-II), increased phagocytic activity, natural killer cell cytotoxicity) without producing cell death. This biphasic dose-response is the molecular basis for the traditional "blood purifier" indication and the modern immune-modulating dosing range.
The therapeutic complication is that the same redox-cycling mechanism that drives all of these benefits also drives toxicity at higher doses. Lapachol at the doses required for measurable antitumor activity in the NCI Phase I trials (1.5-3.5 g/day orally) produced clinically significant prothrombin prolongation — beta-lapachone and lapachol are functional vitamin K antagonists, structurally similar to warfarin's 4-hydroxycoumarin pharmacophore. This is why herbal-safety references list warfarin, heparin, apixaban, rivaroxaban, and other anticoagulants as a contraindication with Pau d'Arco (the clotting effects add together), and why herbal-safety guidance commonly lists stopping Pau d'Arco at least 2 weeks before any planned surgery. The fourth deep-dive page covers the full caution profile and the NCI cancer-trial history, including the drug interactions and the doses at which bleeding problems appeared.
Key Research Papers
- de Almeida ER et al. (1990). Antiinflammatory action of lapachol. Journal of Ethnopharmacology. — PubMed PMID: 2374436
- Hartwell JL (1982). Plants Used Against Cancer (compilation including Tabebuia ethnobotany). — PubMed
- Block JB, Serpick AA, Miller W, Wiernik PH (1974). Early clinical studies with lapachol (NSC-11905). Cancer Chemotherapy Reports. — PubMed PMID: 4614904
- Pardee AB et al. (2002). Cancer therapy with beta-lapachone. Current Cancer Drug Targets. — PubMed PMID: 12188909
- Manna SK, Gad YP, Mukhopadhyay A, Aggarwal BB (1999). Suppression of tumor necrosis factor-activated nuclear transcription factor-kappaB, activator protein-1, c-Jun N-terminal kinase, and apoptosis by beta-lapachone. Biochemical Pharmacology. — PubMed PMID: 10075082
- Gerber DE et al. (2018). Phase 1 study of ARQ 761, a β-lapachone analogue that promotes NQO1-mediated programmed cancer cell necrosis. British Journal of Cancer. — PubMed PMID: 30318513
External Authoritative Resources
- NCI — Complementary & Alternative Medicine (background on the NCI lapachol Phase I program)
- U.S. National Center for Complementary and Integrative Health (NCCIH) — Herbs at a Glance (U.S. National Institutes of Health (NIH) National Center for Complementary and Integrative Health)
- MedlinePlus — Pau d'Arco (interactions, dosing cautions)
- Memorial Sloan Kettering — About Herbs: Pau d'Arco (oncology-focused clinical summary)
- PubMed — All research on Tabebuia impetiginosa / lapachol / beta-lapachone
Connections
- All Herbs
- Pau d'Arco (Main Page)
- Pau d'Arco — Antifungal
- Pau d'Arco — Immune Modulation
- Pau d'Arco — Anti-Inflammatory
- Pau d'Arco — Cautions & Cancer Research
- Oregano
- Neem
- Goldenseal
- Cat's Claw
- Olive Leaf
- Echinacea
- Fungal Infections
- Cancer
- Immune Boosting
- Oxidative Stress
- History