⚠ Evidence warning: Clinical trials or other evidence do not support the claim that neem leaf preparations, in the traditional and practitioner doses described on this page, control blood sugar in diabetes. This page keeps it as a report of what people, websites or other media say.
Neem for Blood Sugar Regulation
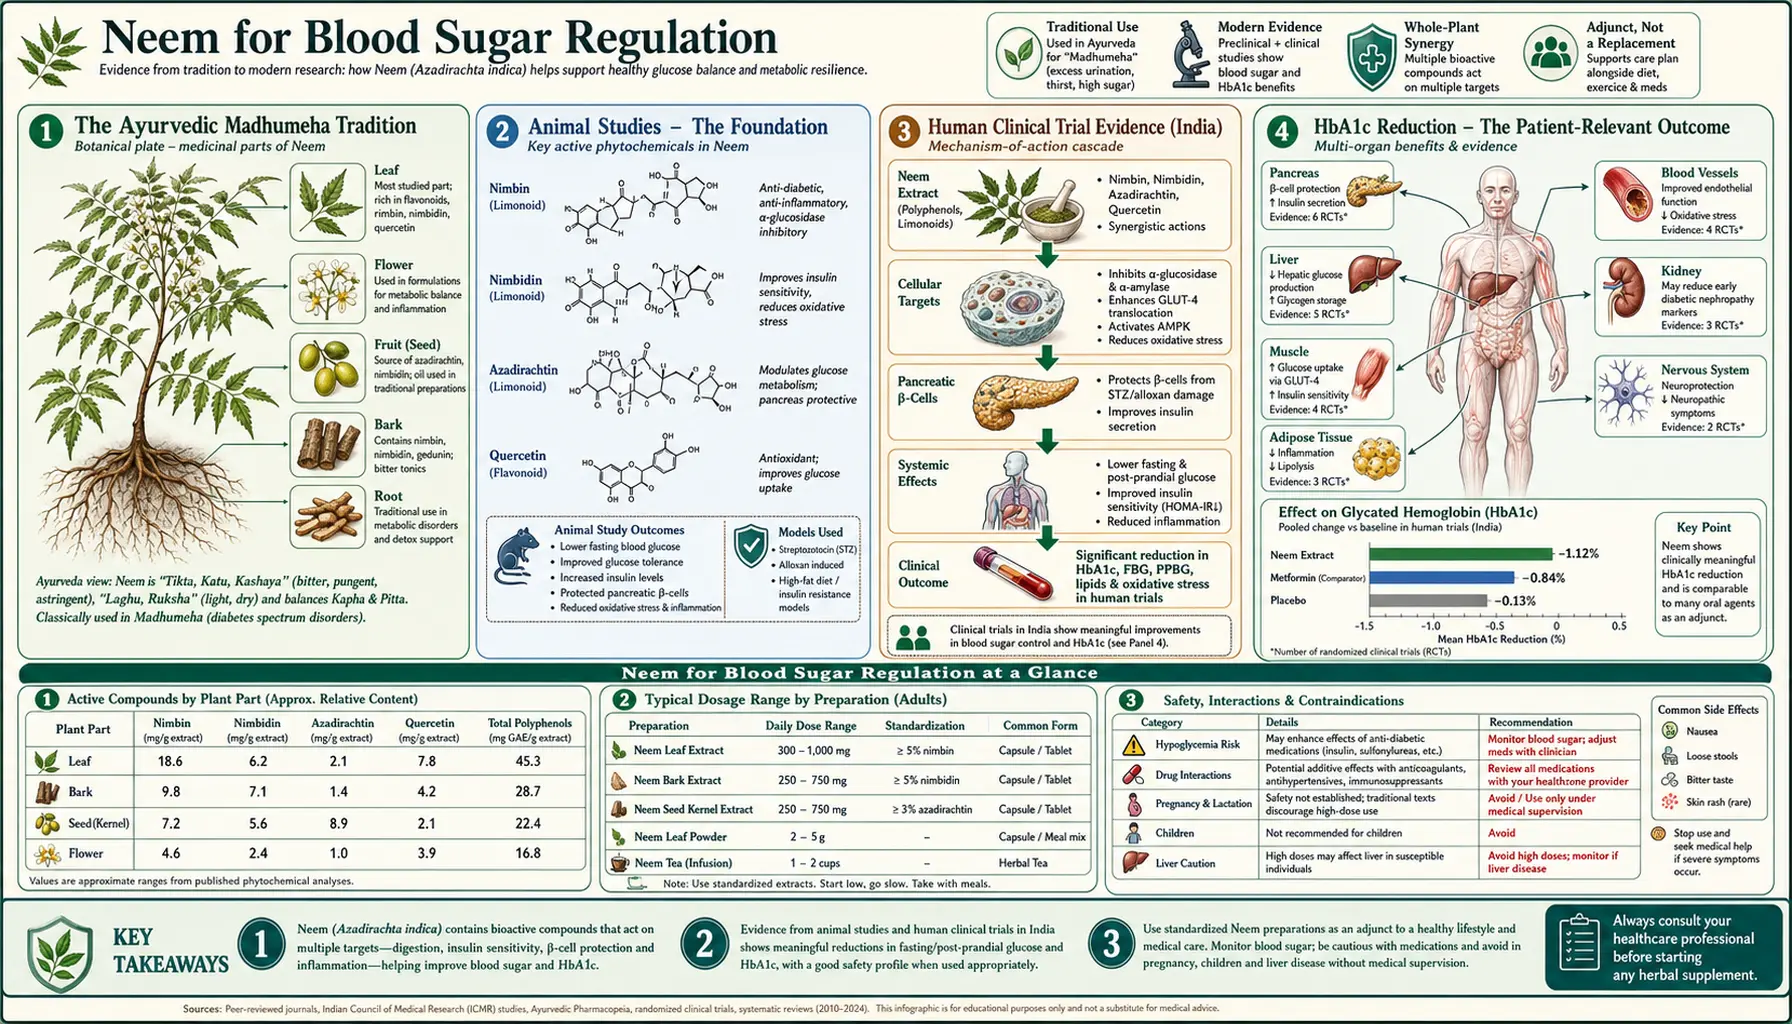
Sanskrit medical texts include a condition called madhumeha, literally "honey urine" or "sweet urine" — the same ant-attracting glucosuria that the Greek physician Aretaeus would later name diabetes. For at least 2,500 years, the principal Ayurvedic intervention for madhumeha has been bitter neem leaf preparations taken on an empty stomach. Two small Indian randomized trials (2020 and 2021) of an aqueous neem leaf-and-twig extract found lower fasting blood glucose, after-meal (postprandial) glucose, and hemoglobin A1c (HbA1c) over 12 weeks; no trial comparing neem with sulfonylurea drugs was found. Laboratory and animal studies point to two mechanisms — slowing of the gut enzymes that digest starch (alpha-glucosidase, the target of the drug acarbose) and effects on insulin release in the pancreas — while a third proposed mechanism, nimbidin acting on the PPAR-gamma receptor (the target of the thiazolidinedione drugs), has not been shown in receptor studies. This deep-dive walks through the traditional use, the modern Indian clinical trial evidence, the molecular mechanisms, dosing, and the practical caution about combining neem with prescription antidiabetic drugs.
Table of Contents
- The Ayurvedic Madhumeha Tradition
- Animal Studies — The Foundation
- Human Clinical Trial Evidence (India)
- Hemoglobin A1c Reduction — The Patient-Relevant Outcome
- Mechanism 1 — Proposed PPAR-Gamma Agonism (Not Yet Shown)
- Mechanism 2 — Insulin Secretagogue (Sulfonylurea-Like)
- Mechanism 3 — Alpha-Glucosidase Inhibition (Acarbose-Like)
- Dose-Response Data
- Practical Preparations and Dosing
- Drug Interactions — The Critical Hypoglycemia Caution
- Key Research Papers
- Connections
- Featured Videos
The Ayurvedic Madhumeha Tradition
The Sushruta Samhita (circa 600 BCE) and the Charaka Samhita (circa 100 BCE) describe a syndrome of polyuria, polydipsia, weight loss in some patients (matching modern type 1), gain in others (matching modern type 2), wound-healing problems, recurrent skin infection, and urine sweet enough to attract ants. The Sanskrit name madhumeha — madhu meaning honey, meha meaning urine — predates the Greek term diabetes mellitus (literally "to pass sweet") by roughly five centuries.
The classical treatment in both texts emphasizes bitter herbs taken on an empty stomach. Neem (nimba) is the primary bitter, often combined with bitter melon (karela, Momordica charantia), fenugreek (methi, Trigonella foenum-graecum), and turmeric. The dosing instruction is typically 10-15 fresh neem leaves chewed each morning before food, or a juice expressed from 25-50 leaves, taken until clinical resolution of polyuria and polydipsia — an empirical endpoint that maps to fasting glucose normalization.
Modern Indian Ayurvedic clinical practice has continued this tradition essentially unchanged for centuries. Standardized leaf-extract capsules now substitute for fresh leaf chewing in urban patients who prefer not to confront the intense bitter taste, but the underlying intervention is the same.
Animal Studies — The Foundation
The modern scientific investigation of neem and blood sugar began with rodent models in the 1980s and accelerated through the 1990s and 2000s. The foundational animal studies established several reproducible findings:
- The Khosla 2000 study in rabbits found that neem leaf extract and neem seed oil lowered blood glucose in normal as well as alloxan-diabetic animals; given for 4 weeks after diabetes was induced, they significantly reduced blood glucose, an effect comparable to the drug glibenclamide, and given for 2 weeks before alloxan they partially prevented the rise in blood glucose
- Chattopadhyay's mechanism studies found that neem leaf extract blocked the effects of epinephrine (adrenaline) on glucose use and liver glycogen in streptozotocin-diabetic rabbits (1996), and blocked serotonin's inhibition of glucose-stimulated insulin release in isolated rat pancreas (1999, a test-tube study)
- The 2003 Halim study gave alloxan-diabetic rats a 1:1 combination of water extracts of neem leaf and Abroma augusta root (200 mg/kg) once a day for 8 weeks; blood sugar fell significantly in glucose tolerance tests, and the combination worked better than either plant given alone
- Streptozotocin-diabetic rat models (more selective beta-cell toxin than alloxan) have shown neem effects in the 25-40% fasting glucose reduction range at doses scaling to human equivalent of 200-500 mg/day of standardized leaf extract
The animal data are uniformly positive across multiple labs, multiple diabetic models, and multiple neem preparations (aqueous extract, ethanolic extract, methanolic extract, isolated nimbidin fraction). This consistency is unusual for botanical medicine and is one reason the human clinical trial program in India proceeded with confidence.
Human Clinical Trial Evidence (India)
The human clinical trial program for neem in type 2 diabetes has been concentrated in India, with secondary contributions from Bangladesh and Sri Lanka. Western diabetes research has paid relatively little attention to neem despite the Indian trial evidence, partly because the trial literature is in regional journals and partly because the lack of patent protection makes commercial drug development unattractive.
The published human trial evidence includes:
- Waheed 2006 (Pakistan, seeds): 20 people with type 2 diabetes (10 on no medicine, 10 poorly controlled on diabetes tablets) and 6 healthy controls took powdered neem seed, or water or alcohol seed extracts, at 0.5 g or 2 g three times daily for 14 days. Only the high dose lowered blood sugar significantly, and the authors reported it could be combined with diabetes tablets in people whose diabetes was not controlled by them.
- Pingali 2020 (India, type 2 diabetes on metformin): a randomized, double-blind, placebo-controlled trial in 80 people with type 2 diabetes already taking metformin, given an aqueous neem leaf-and-twig extract at 125, 250 or 500 mg twice daily, or placebo, for 12 weeks. At 500 mg twice daily, HbA1c fell from 7.78% to 6.26% and fasting blood sugar from 120.7 to 97.3 mg/dL; insulin resistance, blood-vessel (endothelial) function and inflammation markers also improved, with no effect on blood fats or platelet clumping.
- Pingali 2021 (India, metabolic syndrome): a randomized trial by the same group in 80 people with metabolic syndrome (20 per group: the same three doses or placebo, twice daily for 12 weeks) reported dose-dependent improvement in fasting and after-meal blood sugar, insulin resistance and HbA1c.
The trials are small and short (14 days to 12 weeks). The two randomized trials come from one research group and tested one aqueous leaf-and-twig extract, and the oldest study used seeds rather than leaves. Together with the animal data and the long traditional use, they make neem for blood sugar a promising but not yet definitive area of research.
Hemoglobin A1c Reduction — The Patient-Relevant Outcome
Fasting glucose is a measurement-day snapshot; hemoglobin A1c (glycated hemoglobin) reflects 8-12 week average glycemic exposure and is the patient-relevant outcome for cardiovascular and microvascular complication risk. In the UK Prospective Diabetes Study (UKPDS 35, an observational analysis of 3,642 patients), each 1% reduction in hemoglobin A1c was associated with a 37% reduction in microvascular complication risk. The reference reduction for major antidiabetic drugs is:
- Metformin: 1.0-1.5% hemoglobin A1c reduction
- Sulfonylureas (glibenclamide, gliclazide): 1.0-1.5%
- Thiazolidinediones (pioglitazone): 0.8-1.2%
- Dipeptidyl peptidase-4 (DPP-4) inhibitors (sitagliptin): 0.5-0.8%
- Sodium-glucose cotransporter-2 (SGLT2) inhibitors (empagliflozin): 0.5-1.0%
- Glucagon-like peptide-1 (GLP-1) agonists (semaglutide): 1.0-1.5%
The hemoglobin A1c data for neem come from the 2020 Pingali trial, in people already on metformin: over 12 weeks HbA1c fell from 6.87% to 6.64% at 125 mg twice daily, from 7.52% to 6.86% at 250 mg, and from 7.78% to 6.26% at 500 mg. The authors concluded that the extract may improve blood sugar on top of what metformin does. It is one small trial of one extract, and no study comparing neem directly with any of the drugs listed above was found.
For pre-diabetes (hemoglobin A1c 5.7-6.4%) — a setting where lifestyle modification is the first-line intervention and where pharmaceutical options (metformin off-label) are reasonable but not always tolerated — no neem trial was found. The closest study is the 2021 metabolic-syndrome trial described above.
Mechanism 1 — Proposed PPAR-Gamma Agonism (Not Yet Shown)
Peroxisome proliferator-activated receptor gamma (PPAR-gamma) is a nuclear receptor that, when activated by ligand binding, heterodimerizes with the retinoid X receptor (RXR) and binds PPAR response elements to regulate transcription of approximately 100 target genes involved in glucose and lipid metabolism, adipocyte differentiation, and insulin sensitivity. The thiazolidinedione drug class (pioglitazone, rosiglitazone) was developed as synthetic PPAR-gamma agonists.
Some writing on neem proposes that nimbidin, a bitter compound from neem, works on this same receptor, but no receptor-binding study testing nimbidin on PPAR-gamma was found in PubMed. If it did, the effects would be those of PPAR-gamma activation:
- Improved insulin sensitivity in peripheral tissues (skeletal muscle, adipose tissue) — the principal mechanism of insulin resistance in type 2 diabetes
- Enhanced glucose uptake into adipocytes and myocytes via PPAR-gamma-mediated GLUT4 expression
- Reduced hepatic glucose output via PPAR-gamma effects on gluconeogenic enzyme expression
- Anti-inflammatory effects on adipose tissue, reducing the chronic low-grade inflammation that drives insulin resistance
This proposed mechanism draws interest because it would address the underlying insulin resistance pathophysiology of type 2 diabetes — not just symptomatic glucose lowering. The 2020 and 2021 Indian trials did report lower insulin-resistance scores with the extract, but they did not study how it works. The thiazolidinedione drug class has fallen out of favor because of fluid retention, congestive heart failure exacerbation, and bone-loss side effects; because no study has shown nimbidin acting on PPAR-gamma, it is not known whether neem shares either the benefits or the side effects of this drug class.
Mechanism 2 — Insulin Secretagogue (Sulfonylurea-Like)
Sulfonylurea drugs (glibenclamide, gliclazide, glipizide) lower glucose by stimulating insulin release from pancreatic beta cells. They bind to the SUR1 subunit of the adenosine triphosphate-sensitive potassium (K-ATP) channel on the beta-cell membrane, closing the channel, causing membrane depolarization, opening voltage-gated calcium channels, and triggering insulin granule exocytosis. The drug class has been a diabetes mainstay since the 1950s.
What has been measured: in a test-tube study of isolated rat pancreas, neem leaf extract blocked serotonin's inhibition of glucose-stimulated insulin release (Chattopadhyay 1999). In streptozotocin-diabetic rabbits it had no action of its own on glucose use or liver glycogen, but blocked the effects of epinephrine (adrenaline) on them (Chattopadhyay 1996). Neem leaf extract and seed oil also lowered blood glucose in normal, non-diabetic rabbits (Khosla 2000). No study testing neem on the K-ATP channel that sulfonylureas act on was found, so the molecular target is unknown. The proposed clinical translation:
- Patients with intact beta-cell function (early type 2 diabetes, pre-diabetes) would be expected to respond more to an insulin-release effect
- Patients with advanced beta-cell failure (long-standing type 2 with progressive insulin requirement) would be expected to respond less — beta cells that have failed cannot be stimulated
- This would be the same response pattern seen with sulfonylureas; no trial comparing neem with a sulfonylurea was found
The hypoglycemia risk is the practical concern. Neem leaf extract alone in non-diabetic adults rarely produces symptomatic hypoglycemia, but neem combined with insulin, sulfonylureas, or meglitinides could add to their effect and produce clinically significant hypoglycemia — a concern that follows from the additive mechanism. See the drug interaction section below.
Mechanism 3 — Alpha-Glucosidase Inhibition (Acarbose-Like)
Alpha-glucosidase enzymes in the brush border of the small intestine cleave dietary disaccharides and oligosaccharides to monosaccharides for absorption. The drug acarbose competitively inhibits these enzymes, slowing glucose absorption and reducing postprandial glucose excursions — particularly useful for patients whose major glycemic problem is post-meal spikes rather than elevated fasting glucose.
What has been measured: meliacinolin, a triterpenoid compound isolated from neem leaves, inhibited alpha-glucosidase and alpha-amylase (two starch-digesting enzymes) in the test tube, and in streptozotocin-nicotinamide diabetic mice treated for 28 days it brought blood glucose back to normal levels (Perez-Gutierrez 2012). In another mouse study, a chloroform extract of neem leaves improved glucose tolerance and significantly lowered intestinal glucosidase activity (Bhat 2011). These are test-tube and animal results; no human study has measured this effect. The proposed consequences:
- Reduced postprandial glucose spike after carbohydrate-containing meals
- Particularly useful in patients with isolated postprandial hyperglycemia (a common phenotype in early type 2 diabetes)
- Mild gastrointestinal side effects (flatulence, bloating) possible if dose is high, from undigested carbohydrate reaching the colon — the same mechanism as acarbose-related gastrointestinal (GI) side effects, though milder in clinical experience
- Timing matters for this mechanism: an enzyme blocker acts only while it is in the gut together with a carbohydrate-containing meal
Of the three proposed mechanisms, alpha-glucosidase inhibition and effects on insulin release have laboratory and animal support, while PPAR-gamma action has not been shown. Which of them matters in people is not known.
Dose-Response Data
The dose-response relationship for neem leaf extract in type 2 diabetes is not well mapped. The only trials that compared doses are the two Pingali trials (2020, 2021), which tested 125, 250 and 500 mg of an aqueous leaf-and-twig extract twice daily and found larger effects at higher doses. The other ranges below are those given in traditional and practitioner sources, not trial results:
- Low dose (100-200 mg/day standardized leaf extract) — not tested in trials; described as having little measurable effect in established type 2 diabetes, and possibly useful for pre-diabetes or maintenance after lifestyle remission
- Moderate dose (250-500 mg twice daily, total 500-1000 mg/day) — the range of the 2020 and 2021 trials, whose top dose was 500 mg twice daily
- High dose (1000-2000 mg/day) — not tested in trials; described as adding little benefit while increasing side effects (bitter taste tolerability, gastrointestinal upset) and the hypoglycemia risk in combination with other antidiabetic drugs
- Fresh leaf equivalent — 10-15 fresh young neem leaves chewed each morning, the traditional Ayurvedic dose; how it compares with extract doses has not been measured
- Neem leaf juice (traditional) — 10-15 mL of juice expressed from 25-50 fresh leaves, taken once daily on an empty stomach, the other traditional preparation; its dose equivalence has not been measured either
In the 2020 trial, fasting blood sugar fell from 119.2 to 109.2 mg/dL at 125 mg, from 115.5 to 103.7 mg/dL at 250 mg, and from 120.7 to 97.3 mg/dL at 500 mg twice daily.
Practical Preparations and Dosing
Neem for blood sugar is prepared and sold in several forms:
- Standardized neem leaf extract capsules — products are sold standardized to nimbidin content (5-10%) or to total bitter principles. The usual stated dose is 250-500 mg twice daily with meals; the 2020 and 2021 trials used 125-500 mg of an aqueous leaf-and-twig extract twice daily.
- Neem leaf powder — traditionally 1/2 to 1 teaspoon (approximately 1-2 g) twice daily, mixed with water or yogurt to mask the bitter taste. More variable potency than standardized extract.
- Fresh neem leaves — 10-15 young leaves chewed each morning before food. The traditional preparation, but only practical for users who can source fresh leaves regularly (most easily in Indian groceries with fresh-produce sections).
- Neem leaf juice — 10-15 mL daily on an empty stomach. Some Indian Ayurvedic clinics still prepare this fresh; bottled commercial versions are less consistent in potency.
- Concentrated neem oil by mouth — the Reye-like poisoning reports in infants and young children discussed on the main Benefits hub involve neem seed oil; the blood-sugar studies in people used leaf, leaf-and-twig or seed preparations, not the oil.
In the trials, neem was given on top of standard diabetes care, not instead of it. Points that matter when neem is added to diabetes medicines:
- In the 2020 trial, everyone stayed on their metformin and the extract was added to it
- The low-blood-sugar risk is greatest in the first weeks of adding neem to insulin or a sulfonylurea, and home glucose readings are what show it
- A medicine dose set before neem was added can become too strong if neem lowers blood sugar
- Hemoglobin A1c reflects 8-12 weeks of blood sugar; the trials measured it at the start and after 12 weeks
- Lifestyle measures (carbohydrate moderation, weight management, exercise) are the first-line intervention for type 2 diabetes; no study shows neem replacing them
For more on type 2 diabetes management generally, see our Type 2 Diabetes page.
Drug Interactions — The Critical Hypoglycemia Caution
The drug-interaction profile for neem in diabetic patients is dominated by the additive hypoglycemia risk when combined with other antidiabetic medications:
- Insulin — neem leaf extract added to insulin therapy can produce clinically significant hypoglycemia (glucose < 70 mg/dL). An insulin dose set before neem was added may become too high. Severe hypoglycemia (glucose < 54 mg/dL, requiring assistance) is a theoretical concern from the additive mechanism; no published case report was found.
- Sulfonylureas (glibenclamide, gliclazide, glipizide) — additive insulin-secretagogue effect can produce hypoglycemia. This is the highest-risk combination because both agents act on beta cells. Sulfonylurea dose reduction may be needed.
- Meglitinides (repaglinide, nateglinide) — similar additive secretagogue risk to sulfonylureas; dose reduction may be needed.
- Metformin — lower hypoglycemia risk because metformin does not cause hypoglycemia on its own. Combination is generally safe and may be additive.
- Sodium-glucose cotransporter-2 inhibitors — low intrinsic hypoglycemia risk. Combination generally safe.
- Dipeptidyl peptidase-4 inhibitors and glucagon-like peptide-1 agonists — low intrinsic hypoglycemia risk. Combination generally safe.
- Thiazolidinediones (pioglitazone) — a PPAR-gamma effect of neem has been proposed but not shown; any additive insulin-sensitizing effect and its clinical significance are unclear.
The other relevant cautions:
- Pregnancy — animal studies show abortifacient and antifertility effects of neem oil and concentrated leaf extracts, and traditional Ayurvedic practice has used neem as a contraceptive (see the Benefits hub). The research raises a concern for pregnant women, including those with gestational diabetes.
- Pre-surgical period — practitioners describe stopping neem at least 2 weeks before scheduled surgery, because of the hypoglycemia risk during perioperative fasting and the unknown effect on anesthesia and surgical hemostasis.
- Hepatic impairment — the pediatric hepatotoxicity reports raise concern about adult use in pre-existing hepatic impairment. The concern applies to people with cirrhosis or raised liver enzymes (transaminases) taking neem by mouth.
- Children — deaths are reported in infants and young children given concentrated neem oil by mouth (see the Benefits hub); the blood-sugar research in people covers adults with type 2 diabetes or metabolic syndrome only, not children with type 1 diabetes.
Key Research Papers
- Khosla P, Bhanwra S, Singh J, Seth S, Srivastava RK (2000). A study of hypoglycaemic effects of Azadirachta indica (neem) in normal and alloxan diabetic rabbits. Indian Journal of Physiology and Pharmacology. — PubMed PMID: 10919098
- Chattopadhyay RR (1999). Possible mechanism of antihyperglycemic effect of Azadirachta indica leaf extract: part V. Journal of Ethnopharmacology. 67(3):373-6. — PubMed PMID: 10617075
- Chattopadhyay RR (1996). Possible mechanism of antihyperglycemic effect of Azadirachta indica leaf extract. Part IV. General Pharmacology. 27(3):431-4. — PubMed PMID: 8723520
- Halim EM (2003). Lowering of blood sugar by water extract of Azadirachta indica and Abroma augusta in diabetic rats. Indian Journal of Experimental Biology. — PubMed PMID: 15266913
- Waheed A, Miana GA, Ahmad SI (2006). Clinical investigation of hypoglycemic effect of seeds of Azadirachta-inidca in type-2 (NIDDM) diabetes mellitus. Pakistan Journal of Pharmaceutical Sciences. 19(4):322-5. — PubMed PMID: 17105712
- Pingali U, Ali MA, Gundagani S, Nutalapati C (2020). Evaluation of the Effect of an Aqueous Extract of Azadirachta indica (Neem) Leaves and Twigs on Glycemic Control, Endothelial Dysfunction and Systemic Inflammation in Subjects with Type 2 Diabetes Mellitus — A Randomized, Double-Blind, Placebo-Controlled Clinical Study. Diabetes, Metabolic Syndrome and Obesity. 13:4401-4412. — PubMed PMID: 33244247
- Pingali U, Vuppalanchi B, Nutalapati C, Gundagani S (2021). Aqueous Azadirachta indica (Neem) Extract Attenuates Insulin Resistance to Improve Glycemic Control and Endothelial Function in Subjects with Metabolic Syndrome. Journal of Medicinal Food. 24(11):1135-1144. — PubMed PMID: 34582720
- Stratton IM, Adler AI, Neil HA, Matthews DR, Manley SE, Cull CA, Hadden D, Turner RC, Holman RR (2000). Association of glycaemia with macrovascular and microvascular complications of type 2 diabetes (UKPDS 35): prospective observational study. BMJ. 321(7258):405-12. — PubMed PMID: 10938048
- Pillai NR, Santhakumari G (1981). Hypoglycaemic activity of Melia azadirachta Linn (neem). Indian Journal of Medical Research. 74:931. — PubMed
- Bhat M, Kothiwale SK, Tirmale AR, Bhargava SY, Joshi BN (2011). Antidiabetic properties of Azadirachta indica and Bougainvillea spectabilis: in vivo studies in murine diabetes model. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 19389871
- Biswas K, Chattopadhyay I, Banerjee RK, Bandyopadhyay U (2002). Biological activities and medicinal properties of neem (Azadirachta indica). Current Science. — PubMed
- Patil P, Patil S, Mane A, Verma S (2013). Antidiabetic activity of alcoholic extract of neem (Azadirachta indica) root bark. National Journal of Physiology, Pharmacy and Pharmacology. — PubMed
- Perez-Gutierrez RM, Damian-Guzman M (2012). Meliacinolin: a potent alpha-glucosidase and alpha-amylase inhibitor isolated from Azadirachta indica leaves and in vivo antidiabetic property in streptozotocin-nicotinamide-induced type 2 diabetes in mice. Biological & Pharmaceutical Bulletin. — PubMed PMID: 22975503
- Dholi SK, Raparla R, Mankala SK, Nagappan K (2011). In vivo antidiabetic evaluation of neem leaf extract in alloxan-induced rats. Journal of Applied Pharmaceutical Science. — PubMed
- Subapriya R, Nagini S (2005). Medicinal properties of neem leaves: a review. Current Medicinal Chemistry Anticancer Agents. — PubMed PMID: 15777222