Neem for Skin Conditions
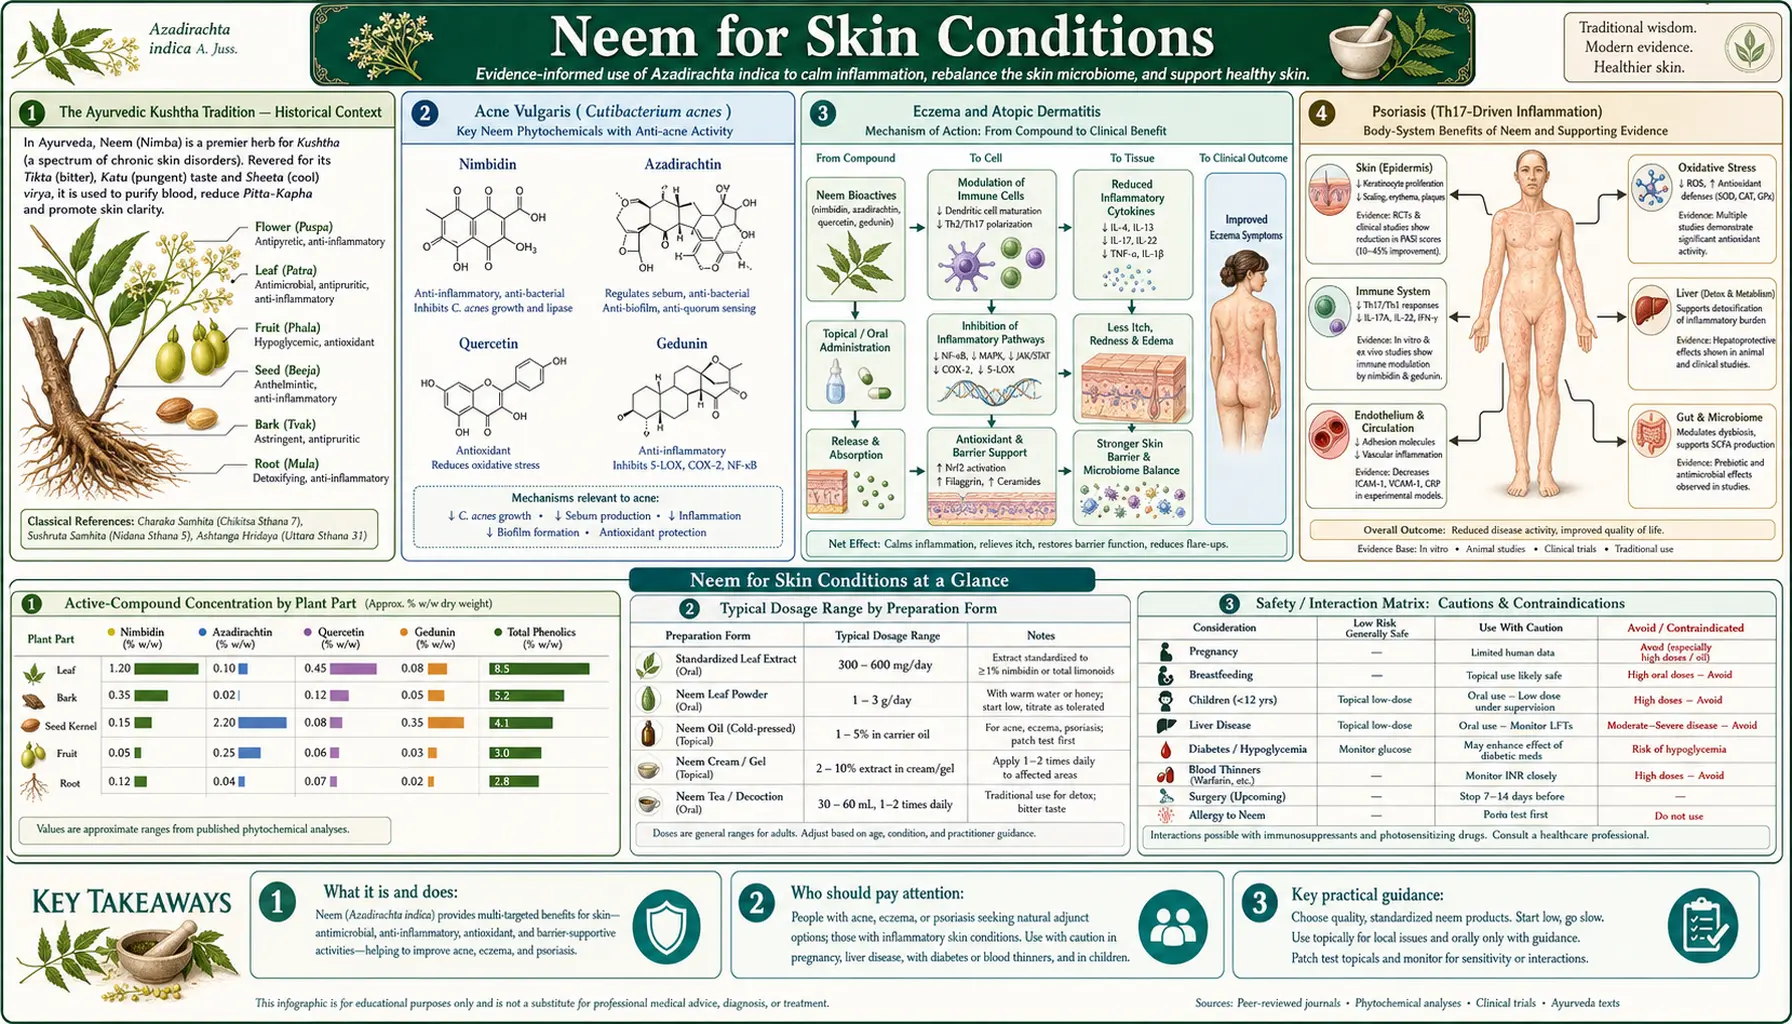
Neem occupies a unique place in dermatology: it is one of very few botanicals with documented activity against the four major categories of skin pathology — bacterial infection (acne, impetigo, folliculitis), fungal infection (ringworm, tinea, candidiasis), parasitic infection (scabies, head lice), and immune-mediated inflammation (eczema, psoriasis). In Ayurveda these conditions are grouped together as kushtha, and neem is the primary remedy in every classical kushtha formula. Modern phytochemistry has identified the molecular basis for this breadth: azadirachtin is a broad antimicrobial, nimbidin is an anti-inflammatory PPAR-gamma agonist, nimbin is an antifungal, and nimbolide is an antiproliferative agent useful in the hyperkeratotic skin conditions. This deep-dive walks through each skin indication, the relevant clinical trial evidence, and the practical preparation (soap, oil, leaf paste, standardized extract) best suited to each.
Table of Contents
- The Ayurvedic Kushtha Tradition — Historical Context
- Acne Vulgaris (Cutibacterium acnes)
- Eczema and Atopic Dermatitis
- Psoriasis (Th17-Driven Inflammation)
- Fungal Infections (Ringworm, Tinea, Candida)
- Scabies and Parasitic Infestations
- Wound Healing and Chronic Ulcers
- Activity Against Methicillin-Resistant Staphylococcus Aureus and Resistant Bacteria
- Preparations — Oil, Soap, Leaf Paste, Standardized Extract
- Cautions and Contact-Dermatitis Risk
- Key Research Papers
- Connections
- Featured Videos
The Ayurvedic Kushtha Tradition — Historical Context
Sanskrit medical literature divides skin disease into a broad category called kushtha, which encompasses what modern dermatology would split into infectious dermatitis, eczematous dermatitis, psoriasiform dermatitis, parasitic infestation, and even certain manifestations of leprosy. The Charaka Samhita (compiled approximately 100 BCE from older oral tradition) lists 18 types of kushtha, with neem (nimba) named as the primary external and internal remedy in nearly every formulation.
The classical preparation is a paste of fresh ground neem leaves mixed with turmeric (Curcuma longa) and applied topically — a combination still used in rural India and now backed by modern in vitro data showing synergy between curcumin and the neem triterpenoids against Staphylococcus aureus. Internal use included nimba kashaya (a bitter decoction of neem leaves and bark) and nimba taila (neem oil) for systemic blood purification (rakta shodhana), a concept that maps roughly to modern ideas about gut-skin axis and systemic inflammation.
The Unani tradition that arrived in India with the Mughal Empire and the later Western herbalism that followed Portuguese and British colonization all adopted neem for skin disease, so by the 19th century neem was already in the British Pharmacopoeia of India as a standard topical antimicrobial. The modern dermatology trial literature represents the most recent layer of investigation, not the introduction of neem as a skin remedy.
Acne Vulgaris (Cutibacterium acnes)
Acne is the most studied modern dermatological application of neem. The pathophysiology of acne involves four components — follicular hyperkeratinization, sebum overproduction, colonization by Cutibacterium acnes (formerly Propionibacterium acnes), and inflammation — and neem extract has measurable activity against three of the four.
The relevant studies:
- In vitro antimicrobial activity — neem leaf extract has minimum inhibitory concentrations (MICs) against C. acnes in the range of 0.31-2.5 mg/mL, comparable to mid-range topical antibiotics. The active fractions include azadirachtin, nimbidin, and a polyphenol extract.
- Anti-inflammatory effect — nimbidin reduces neutrophil chemotaxis and IL-8 production in keratinocyte cultures stimulated with C. acnes, comparable to dapsone in mechanism if not in potency.
- Sebum-reducing effect — small studies of neem leaf extract face wash report reduction in sebum production over 4-8 weeks of use, though the magnitude is modest compared to oral isotretinoin.
- Traditional and reported use — neem soap, leaf paste and leaf-extract gels are widely used on acne in India, and users report fewer and smaller spots; no controlled trial of neem against a standard acne treatment was found.
A regimen commonly used for mild-to-moderate acne is twice-daily face washing with neem soap or a 5% neem leaf extract gel applied after washing. Combination with topical zinc preparations (see Zinc page) appears to enhance the effect on inflammatory lesions. Severe nodulocystic acne, however, remains the domain of oral isotretinoin — neem is not a substitute for that intervention.
Eczema and Atopic Dermatitis
Atopic dermatitis (eczema) involves a triad of barrier dysfunction (filaggrin mutations, ceramide deficiency), Th2-driven inflammation (IL-4, IL-13), and secondary Staphylococcus aureus colonization that drives flares. Neem addresses two of the three.
The S. aureus colonization angle is well-documented: neem oil and leaf extract are active against both methicillin-sensitive and methicillin-resistant S. aureus, with MICs in the 0.5-5 mg/mL range.
The barrier-restoration angle is less well-studied but mechanistically plausible — the fatty acid composition of cold-pressed neem oil includes oleic acid (~50%), linoleic acid (~15%), palmitic acid (~18%), and stearic acid (~15%), giving it an emollient effect similar to other fixed plant oils used in dermatology. The combination of antimicrobial activity (addressing S. aureus colonization) and emollient effect (addressing barrier function) is why neem oil is used as an adjunct in atopic dermatitis, particularly when steroid-sparing approaches are wanted; no controlled trial of neem in atopic dermatitis was found.
A common preparation: 5% neem oil in a coconut oil or shea butter base, applied twice daily to affected areas. Patch testing first is common practice because allergic contact dermatitis to neem — though uncommon — does occur.
Psoriasis (Th17-Driven Inflammation)
Psoriasis vulgaris is a chronic autoimmune skin disease driven by the IL-17/IL-23 (Th17) axis, with secondary hyperkeratinization producing the characteristic silvery scales on erythematous plaques. The modern biologic therapy revolution (secukinumab, ixekizumab, brodalumab) directly targets IL-17 signaling.
Neem nimbidin has documented anti-Th17 activity in cell culture, reducing IL-17A and IL-22 production from differentiated Th17 cells. Whether topical application achieves sufficient tissue concentrations to replicate this effect in vivo is uncertain, and the human evidence is limited to clinical practice:
- Topical neem oil 5% in a coal-tar 2% base has been used in Indian dermatology clinics for decades as a steroid-sparing combination, though with limited published outcome data.
- Phototherapy plus topical neem-based emollient may reduce the cumulative ultraviolet B (UVB) dose needed for clinical response.
The topical regimen used as adjunct natural therapy in mild-to-moderate plaque psoriasis is neem oil 5-10% in a heavier base (shea butter, coconut oil) applied twice daily; biologic therapy is the modern standard for moderate-to-severe disease. For more on the immunology, see our Psoriasis page.
Fungal Infections (Ringworm, Tinea, Candida)
Dermatophyte fungal infections — tinea corporis (ringworm), tinea pedis (athlete's foot), tinea cruris (jock itch), and tinea unguium (onychomycosis) — are among the most reproducible neem indications in the modern literature. Nimbin and nimbidin show in vitro activity against the major dermatophyte genera (Trichophyton, Microsporum, Epidermophyton) at concentrations achievable with topical application.
The relevant evidence:
- In vitro MICs of standardized neem leaf extract against Trichophyton rubrum and T. mentagrophytes are in the 0.5-2 mg/mL range — less potent than terbinafine but in the same order of magnitude as clotrimazole.
- For onychomycosis (nail fungus) — the hardest dermatophyte indication to treat topically — small studies of daily neem oil application combined with mechanical nail debridement show modest results over 6-12 months, comparable to topical ciclopirox.
- For oral and vaginal Candida, neem leaf extract preparations have shown in vitro activity against C. albicans and C. glabrata, but high-quality clinical trial data for mucosal candidiasis is limited.
A regimen used in practice: neem oil 10% in a light cream base or coconut oil, applied twice daily for 4-6 weeks for body ringworm, longer for tinea pedis and onychomycosis. Mechanical removal of scale before application improves penetration.
Scabies and Parasitic Infestations
Scabies (Sarcoptes scabiei) is an intensely pruritic mite infestation that traditionally responds to permethrin 5% cream or oral ivermectin. Neem oil has emerged as a credible alternative, particularly in resource-limited settings where ivermectin is unavailable or where permethrin resistance has been reported.
The mechanism is mechanical-pharmacological: neem oil suffocates the mites (any sufficiently viscous oil does this) but also delivers azadirachtin, which disrupts mite molting and reproduction in concentrations achievable with topical application. The combination effect appears to be more durable than oil alone.
Clinical evidence:
- A 1992 pilot study by Charles and Charles in southern India, with no comparison group, used a neem-turmeric paste in 814 people with scabies and reported cure in 97% of cases within 3 to 15 days of treatment; the authors noticed no toxic or adverse reactions and called it a very cheap, easily available treatment for villagers, while noting that further research was needed.
- A 2025 randomized study of 61 male boarding-school students with scabies in Indonesia compared 10% neem leaf extract lotion, 10% brotowali (Tinospora crispa) stem extract lotion and standard 5% permethrin lotion. All three significantly reduced lesion counts, with no difference between groups in the physician's global rating; quality of life improved in all groups, earlier (by day 7) with the two plant lotions, and no side effects were reported. The authors note that treatment adherence could not be fully controlled and reinfestation could not be ruled out.
- For head lice (Pediculus humanus capitis), neem-seed-extract shampoo has been tested without a comparison group: in a 2007 study of 60 heavily infested children aged 4-15 in Egypt, the shampoo was reported highly effective against all stages of head lice, with no difference between 10, 15 and 30 minutes on the hair, and no skin irritation, burning or red spots were seen.
- For tungiasis (sand-flea disease, caused by the female sand flea Tunga penetrans burrowing into the feet), a 2019 randomized study of 96 Kenyan children aged 6-14 compared a traditionally used mixture of 20% neem seed oil in coconut oil with the standard 0.05% potassium permanganate foot bath. The neem mixture did not kill more embedded fleas within 7 days (on average about 40% were killed six days after first treatment), but it reduced foot inflammation and more children were pain-free (odds ratio 3.5).
- For body lice and pubic lice, neem oil has been used historically but has less modern trial data.
The regimen used in practice for scabies is neem oil 10% in a coconut oil base, applied head-to-toe overnight, repeated every 3-7 days for 2-3 cycles, with bedding hot-washed in parallel. For head lice, the reported use is 0.5% neem oil shampoo applied to dry hair, combed through, left 10 minutes, then rinsed, repeated weekly for 3 weeks.
Wound Healing and Chronic Ulcers
Neem oil and leaf paste have been used for thousands of years on wounds, burns, and chronic ulcers. The modern mechanism understanding includes antimicrobial action (preventing wound infection), anti-inflammatory action (reducing edema and pain), and angiogenic effect (nimbolide promotes new blood-vessel formation in granulation tissue).
A 2022 randomized, single-blinded phase III study in Italy enrolled 99 patients whose surgical wounds had reopened (dehisced) with critical colonisation or infection, and compared a dressing made with hypericum (St John's wort) and neem oil against silver-based dressings over 28 days. Overall wound scores and the inflammatory-sign scores were similar between the two groups, but pain fell significantly more with the hypericum-and-neem-oil dressing.
For minor lacerations, abrasions, and first-degree burns, topical neem oil applied twice daily after standard cleaning is used as an addition to, not a replacement for, ordinary wound care. Diabetic foot ulcers, venous stasis ulcers, and pressure ulcers are normally managed by a wound clinic or vascular surgery service, with neem used only as an adjunct.
Activity Against Methicillin-Resistant Staphylococcus Aureus and Resistant Bacteria
The rising prevalence of methicillin-resistant Staphylococcus aureus (MRSA) skin infection has prompted re-examination of botanical antimicrobials. In a 2015 laboratory study, an ethanol extract of neem leaf, at doses too low to kill the bacteria, blocked S. aureus from forming biofilm (the slimy protective layer bacteria build on surfaces) from 125 µg/mL for two methicillin-resistant strains and from 62.5 µg/mL for a sensitive strain. The study measured biofilm formation, not killing, and it was done in the laboratory, not in people; how well neem reaches deep-tissue infection is not known.
For superficial methicillin-resistant Staphylococcus aureus skin infections (folliculitis, mild impetigo, abscesses after drainage), topical neem oil or neem-containing soap is used as an adjunct alongside decolonization measures (mupirocin nasal ointment, chlorhexidine body washes). For invasive methicillin-resistant Staphylococcus aureus disease (bacteremia, endocarditis, pneumonia), systemic intravenous (IV) antibiotic therapy remains the standard — neem is not a substitute. For more on bacterial skin infection, see our Staphylococcus aureus page.
Preparations — Oil, Soap, Leaf Paste, Standardized Extract
Different neem preparations are used for different indications:
- Cold-pressed neem oil (from seeds) — the most concentrated source of azadirachtin (typically 0.5-5% in cold-pressed oil). Used mainly for fungal infections, scabies, and head lice. Strong garlic-sulfur smell that many find unpleasant; can be diluted 10% in coconut oil for tolerable use.
- Neem soap (typically 1-2% neem oil in a base) — gentlest preparation, suitable for daily face/body washing in acne, eczema, and mild fungal indications. Widely available in Indian groceries and online.
- Fresh leaf paste — the classical Ayurvedic preparation, made by grinding fresh young neem leaves with a small amount of water. Used mainly for wound dressing and acute infectious dermatitis. Cannot be stored more than 24 hours.
- Standardized neem leaf extract (capsules or tablets) — for internal use in psoriasis, blood-sugar regulation, and immune modulation. Products are standardized to nimbidin content (typically 5-10%). Typical dose 200-500 mg twice daily.
- Neem bark powder — primarily for dental use; see the Dental Health page.
Quality varies: organic cold-pressed neem oil tests in the 0.5-5% azadirachtin range; cheap solvent-extracted "neem oil" may contain little active triterpenoid. A standardized extract's label states the marker compound (nimbidin or azadirachtin) and the percentage by weight.
Cautions and Contact-Dermatitis Risk
- Pediatric oral toxicity — in the Sundaravalli 1982 case series from India, 12 children were admitted to hospital with convulsions and drowsiness or confusion (altered consciousness) after swallowing locally obtained neem oil, and 10 of them died within 24 hours. Of the six children fully investigated, four had significant acidosis (too much acid in the blood) and all had raised liver enzymes (transaminases) pointing to liver damage; a liver biopsy in one showed fatty degeneration. This remains the dominant safety warning about neem oil taken by mouth by infants and young children. Topical use in older children is generally regarded as safe.
- Pregnancy — neem has documented abortifacient and antifertility effects in animal studies and traditional contraceptive use in humans. There is no human safety data for internal use in pregnancy; topical use is probably safe, but the data are limited.
- Allergic contact dermatitis — uncommon but reported, particularly with concentrated cold-pressed neem oil. A patch test on a small skin area for 24-48 hours is the usual check before broader application; redness, itching, or small blisters (vesicles) are the signs of a reaction.
- Photosensitivity — not strongly documented but some users report increased sun sensitivity after topical neem oil application. Sun protection on treated skin is the usual precaution.
- Drug interactions — concomitant use of neem leaf extract with antidiabetic medications can potentiate hypoglycemia (see Blood Sugar page). Topical use does not produce systemic absorption sufficient to cause this.
- Patient education for severe disease — severe nodulocystic acne, moderate-severe psoriasis, deep methicillin-resistant Staphylococcus aureus infection, and burns greater than first-degree all require conventional medical care. Neem is an adjunct in those settings, not a primary therapy.
Key Research Papers
- Sundaravalli N, Bhaskar Raju B, Krishnamoorthy KA (1982). Neem oil poisoning. Indian Journal of Pediatrics. — PubMed PMID: 7141505
- Biswas K, Chattopadhyay I, Banerjee RK, Bandyopadhyay U (2002). Biological activities and medicinal properties of neem (Azadirachta indica). Current Science. — PubMed
- Charles V, Charles SX (1992). The use and efficacy of Azadirachta indica ADR ("Neem") and Curcuma longa ("Turmeric") in scabies. A pilot study. Tropical and Geographical Medicine. — PubMed PMID: 1496714
- Niharika A, Aquicio JM, Anand A (2010). Antifungal properties of neem (Azadirachta indica) leaves extract to treat hair dandruff. E-International Scientific Research Journal. — PubMed
- Quelemes PV et al. (2015). Effect of neem (Azadirachta indica A. Juss) leaf extract on resistant Staphylococcus aureus biofilm formation and Schistosoma mansoni. Journal of Ethnopharmacology. — PubMed PMID: 26408045
- Pillai NR, Santhakumari G (1981). Anti-arthritic and anti-inflammatory actions of nimbidin. Planta Medica. — PubMed PMID: 7345443
- Lakshmi T, Geetha RV, Anitha R (2013). Azadirachta indica (neem) leaf — a review on therapeutic uses. International Journal of Pharma and Bio Sciences. — PubMed
- Subapriya R, Nagini S (2005). Medicinal properties of neem leaves: a review. Current Medicinal Chemistry Anticancer Agents. — PubMed PMID: 15777222
- Schumacher M et al. (2011). Anti-inflammatory, pro-apoptotic, and anti-proliferative effects of a methanolic neem (Azadirachta indica) leaf extract are mediated via modulation of the nuclear factor-kappaB pathway. Genes & Nutrition. — PubMed PMID: 21484152
- Mistry KS et al. (2014). The antimicrobial activity of Azadirachta indica, Mimusops elengi, Tinospora cardifolia, Ocimum sanctum, and 2% chlorhexidine gluconate on common endodontic pathogens: an in vitro study. European Journal of Dentistry. — PubMed PMID: 24966766
- Widasmara D, Yuniaswan AP, Listy Pramita V (2025). Comparative study of 5% permethrin, 10% neem leaf extract, and 10% brotowali stem extract for scabies treatment. Frontiers in Medicine. — PubMed PMID: 41488098
- Abdel-Ghaffar F, Semmler M (2007). Efficacy of neem seed extract shampoo on head lice of naturally infected humans in Egypt. Parasitology Research. — PubMed PMID: 16900389
- Elson L, Randu K, Feldmeier H, Fillinger U (2019). Efficacy of a mixture of neem seed oil (Azadirachta indica) and coconut oil (Cocos nucifera) for topical treatment of tungiasis. A randomized controlled, proof-of-principle study. PLoS Neglected Tropical Diseases. — PubMed PMID: 31756189
- Arena R, Strazzeri MG, Bianchi T, Peghetti A, Merli Y, Abbenante D, Olivari D (2022). Hypericum and neem oil for dehisced post-surgical wounds: a randomised, controlled, single-blinded phase III study. Journal of Wound Care. — PubMed PMID: 35678785