⚠ Evidence warning: Clinical trials or other evidence do not support the claim that barberry bitters taken before meals improve digestion and relieve functional dyspepsia, low stomach acid, post-gallbladder-removal symptoms and IBS, and prevent SIBO coming back. This page keeps it as a report of what people, websites or other media say.
Barberry as a Digestive Aid
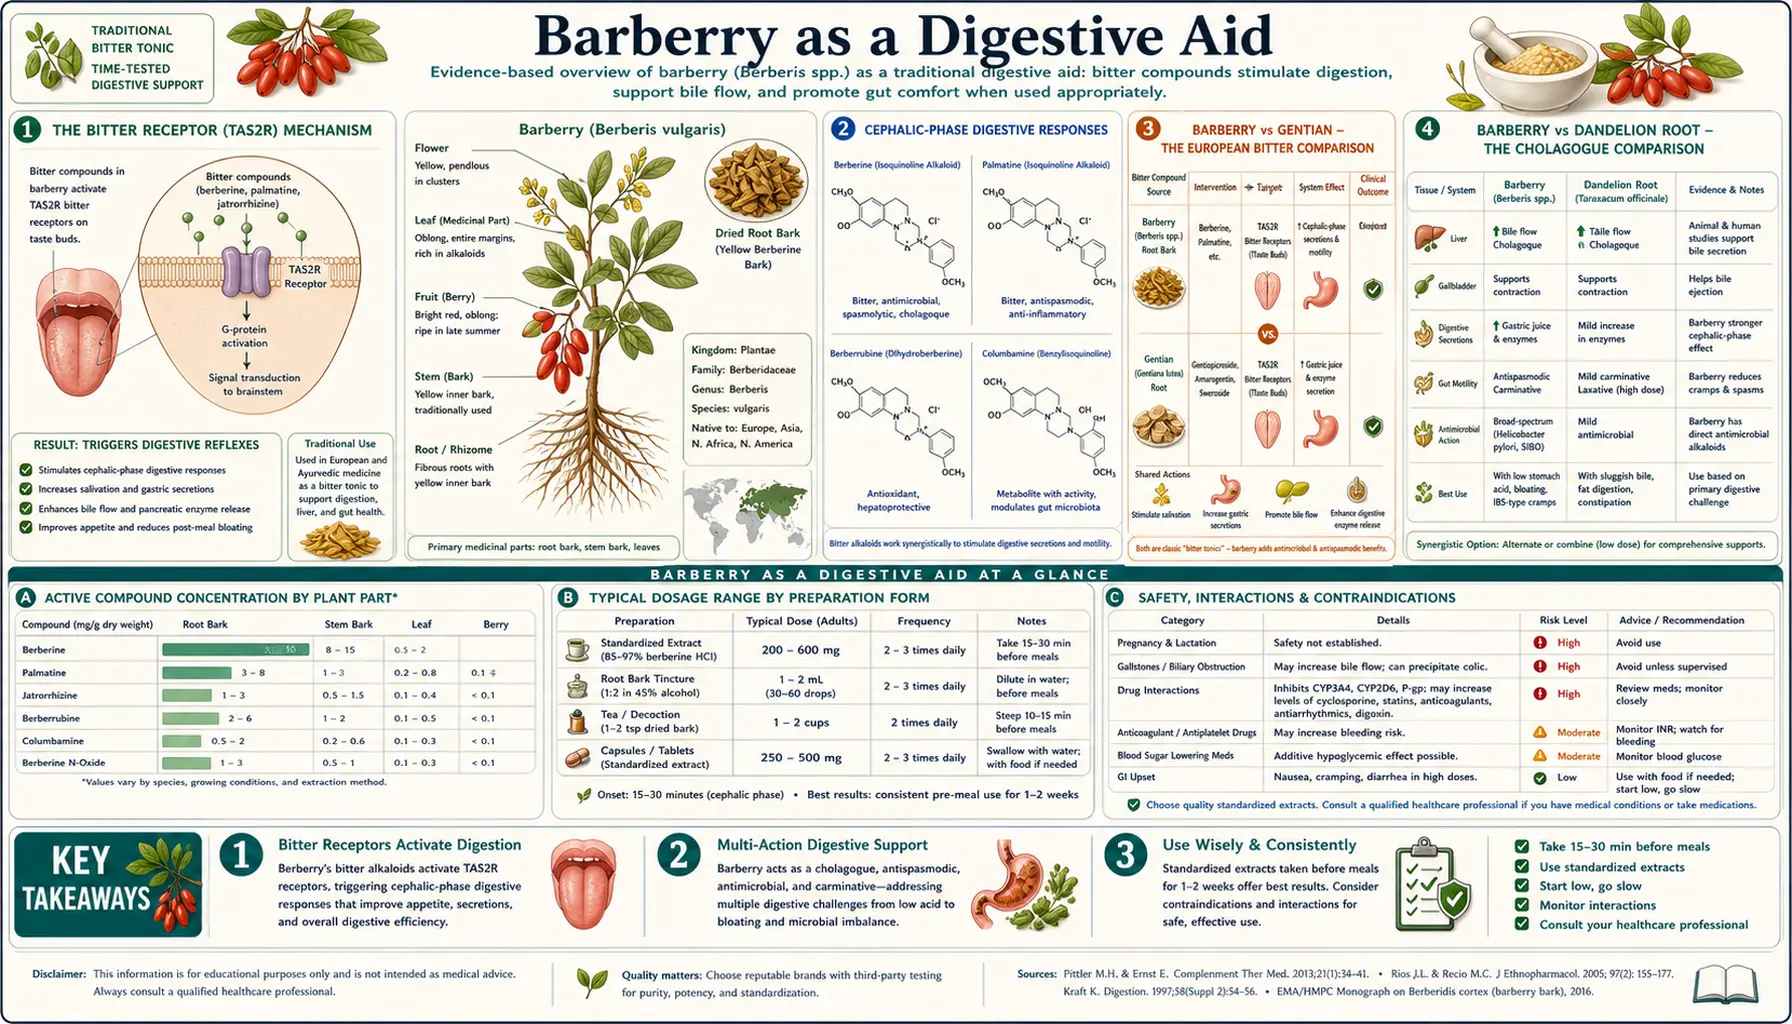
Barberry root is one of the classical European and Persian digestive bitters — alongside gentian (Gentiana lutea), dandelion root (Taraxacum officinale), wormwood (Artemisia absinthium), and angostura. The intense bitter taste of berberine on the tongue activates the bitter taste receptors (TAS2R family, expressed not only on the tongue but throughout the gastrointestinal (GI) tract), triggering a cascade of vagally mediated cephalic-phase digestive responses — increased salivation, gastric acid secretion, pepsinogen release, pancreatic enzyme secretion, bile flow stimulation, and gallbladder contraction — before the alkaloid is ever absorbed into the bloodstream. Herbalists explain that this taste-mediated cephalic-phase mechanism is why they give bitter herbs 10-20 minutes before meals, and why they hold that swallowing capsules without tasting the bitter does not produce the same digestive effect. Researchers are split between this explanation and a purely local action in the gut: a 2015 review by McMullen and colleagues reports that gentian and wormwood set off a blood-vessel reflex, evident after 5 minutes, that facilitates rather than stimulates digestive activity, and that the same herbs swallowed in capsules produced no such response during the stomach phase of digestion. This page covers the bitter-receptor mechanism, the comparison between barberry and other classical bitters (gentian, dandelion, wormwood), the clinical use of barberry for functional dyspepsia, biliary insufficiency, post-cholecystectomy syndrome, irritable bowel syndrome (IBS), hypochlorhydria, and the practical pre-meal dosing window.
Table of Contents
- The Bitter Receptor (TAS2R) Mechanism
- Cephalic-Phase Digestive Responses
- Barberry vs Gentian — the European Bitter Comparison
- Barberry vs Dandelion Root — the Cholagogue Comparison
- Functional Dyspepsia and Postprandial Distress Syndrome
- Hypochlorhydria and Age-Related Acid Decline
- Post-Cholecystectomy Syndrome
- Irritable Bowel Syndrome (IBS) Applications
- Fat-Meal Intolerance and Steatorrhea
- Small Intestinal Bacterial Overgrowth and Small-Intestinal Motility
- Practical Preparations — Tincture, Decoction, Bitter Blend
- The Pre-Meal Dosing Window (10-20 Minutes)
- Cautions and Contraindications
- Key Research Papers
- Connections
- Featured Videos
The Bitter Receptor (TAS2R) Mechanism
The TAS2R family of bitter taste receptors comprises approximately 25 different G-protein-coupled receptors in humans, each tuned to recognize a different range of bitter compounds. The evolutionary explanation for this redundant variety is defensive — bitter taste evolved as a warning system to identify toxic plant alkaloids before swallowing. Berberine is one of the most potent natural bitter compounds known, activating multiple TAS2R subtypes simultaneously (TAS2R8 and TAS2R43 in particular).
The discovery that bitter taste receptors are not confined to the tongue but are expressed throughout the gastrointestinal tract (in gastric chief cells, intestinal enteroendocrine cells, gallbladder smooth muscle, and elsewhere) and even in airway epithelium and other tissues has substantially expanded the modern understanding of bitter herb pharmacology. The receptors function as chemosensors that detect bitter compounds in the gastrointestinal lumen and trigger local responses including hormone release, motility changes, and protective reflexes.
When barberry tincture or decoction contacts the bitter receptors on the tongue, the signal travels via the chorda tympani nerve to the brainstem nucleus of the solitary tract and then to multiple cortical and subcortical areas, but critically also activates a vagally mediated efferent response back to the gut. This is the cephalic-phase digestive reflex: the bitter signal "warns" the gastrointestinal system that something potentially toxic is incoming, and the system responds with maximal preparation for digestion and detoxification.
When berberine reaches the gastrointestinal lumen (whether from the tincture or from food/decoction), it directly activates the gut-expressed TAS2R receptors on enteroendocrine cells (particularly the I cells, which release cholecystokinin (CCK), and the L cells, which release glucagon-like peptide-1 (GLP-1) and peptide YY (PYY)). The local intestinal release of CCK and glucagon-like peptide-1 amplifies the cephalic-phase signal and produces sustained digestive effects.
The functional consequence is that the bitter signal acts at multiple stages of digestion: oral tasting triggers cephalic-phase preparation, gastric contact triggers acid and pepsinogen release, intestinal contact triggers CCK / bile flow / pancreatic enzyme release. The whole cascade is set up by the bitter taste perception. In the herbal tradition, swallowing barberry as a capsule (so that no bitter is tasted on the tongue) is held to lose the cephalic-phase component and reduce the overall digestive effect.
Not every human study finds that bitterness speeds digestion. In a 2005 study of 16 healthy women, Wicks and colleagues found that chewing and spitting out (sham feeding) a bitter-tasting bar slowed stomach emptying compared with a pleasant strawberry-flavoured bar — the stomach took 24.7 minutes to empty halfway after the bitter bar versus 17.2 minutes after the pleasant one — while the muscular activity of the lower stomach was not significantly reduced.
Cephalic-Phase Digestive Responses
The cephalic phase of digestion is the preparation phase that begins before food is swallowed. It is initiated by sight, smell, thought of food, and especially by taste — bitter, sour, and umami tastes are particularly potent activators. The cephalic-phase response includes:
- Salivation — increased salivary flow, including increased salivary amylase content for carbohydrate predigestion
- Gastric acid secretion — parietal cell HCl release; the magnitude of cephalic-phase acid secretion can equal or exceed the post-meal gastric distention component
- Pepsinogen release — gastric chief cells release pepsinogen, which is converted to active pepsin by HCl, beginning protein digestion
- Gastric motility — baseline gastric tone and antral pumping activity increases in preparation for receiving and mixing food
- Pancreatic enzyme secretion — cephalic-phase pancreatic secretion is approximately 25% of total post-meal secretion; the rest follows from intestinal hormonal signals (CCK, secretin)
- Bile flow stimulation — sphincter of Oddi relaxation, gallbladder contraction, hepatic bile flow increase
- Insulin pre-secretion — pancreatic beta cells release a small bolus of "cephalic-phase insulin" in anticipation of the glucose load to follow, which substantially reduces the magnitude of the postprandial glucose excursion
The collective effect is that the gastrointestinal system is fully primed and ready when food arrives. The cephalic-phase response is impaired in many modern situations: distracted eating (television, phone), eating while standing or rushing, eating "on the go," chronic stress and sympathetic dominance, and the use of antacids/proton pump inhibitors that blunt the gastric acid response. Herbalists hold that bitter herbs taken pre-meal restore the cephalic-phase response in people whose innate response has been blunted by these factors.
In herbal practice, the reasoning is that pre-meal bitters improve digestion of subsequent food in ways that cannot be replicated by simply adding enzymes or HCl to the meal. The cephalic-phase response is coordinated and anticipatory; supplemental enzymes and HCl are reactive and uncoordinated. Both have a role, but bitters are said to work upstream where the regulation happens.
What is not known: the human bitter studies summarised by McMullen and colleagues in 2015 tested gentian, wormwood, coffee and caffeine, not barberry, and the responses they report are heart and blood-vessel changes (for gentian and wormwood, a sympathetic reflex evident after 5 minutes), not measured stomach acid or enzyme output. No study measuring barberry's effect on stomach acid in people was found for this page.
Barberry vs Gentian — the European Bitter Comparison
Gentian root (Gentiana lutea) is the European prototype of a digestive bitter and is the active ingredient in many traditional digestif liqueurs and bitters formulations (commercial aperitif and cocktail bitters, gentian-based amari, classic gentian tinctures). The bitter compounds in gentian are the secoiridoid glycosides amarogentin and gentiopicroside, with amarogentin being one of the most intensely bitter substances known — detectable by human taste at concentrations of approximately 1 part in 50,000.
Comparing barberry and gentian as digestive bitters:
- Bitterness intensity — gentian (amarogentin) is more intensely bitter on the tongue than barberry (berberine). On bitterness alone, gentian is the stronger of the two.
- Cholagogue effect — both stimulate bile flow, with comparable effects in animal cannulation studies. Barberry has a modest edge for direct gallbladder smooth muscle stimulation.
- Gastric acid stimulation — both promote HCl secretion through the cephalic-phase mechanism. Roughly equivalent.
- Antimicrobial effect — barberry has substantial antimicrobial activity from berberine; gentian has essentially none. Herbalists therefore use barberry when they want a digestive and an antimicrobial action together (e.g., post-traveler's-diarrhea recovery).
- Metabolic effect — barberry has AMP-activated protein kinase (AMPK) / glycemic / lipid effects from berberine; gentian does not. Herbalists use barberry where a metabolic effect is also wanted.
- Tolerability — gentian is generally well tolerated; barberry occasionally causes gastrointestinal symptoms at higher doses (the same constipation/diarrhea profile seen with concentrated berberine).
- Cost and availability — both are widely available as tinctures from herbal pharmacies; cost is roughly equivalent.
In herbal practice, gentian is the traditional and more intensely bitter choice when only a digestive bitter is wanted; barberry is used as the multi-purpose option when practitioners also want an effect on metabolic markers or are concerned about lurking enteric pathogens.
Many traditional bitter blends combine both — the "Swedish bitters" formulation includes gentian root, angelica root, zedoary, theriac venetian, manna, senna leaves, myrrh, camphor, and saffron, with regional variations sometimes adding barberry root. The combination approach takes advantage of multiple bitter receptors and a range of supportive actions.
Barberry vs Dandelion Root — the Cholagogue Comparison
Dandelion root (Taraxacum officinale) is the classical Western herbal cholagogue and was traditionally roasted as a "dandelion coffee" substitute for its bitter, mildly tonic, and bile-stimulating effect. The active constituents are the sesquiterpene lactones (taraxacin, taraxasterol) and the bitter principles, plus a substantial inulin content in the root that has prebiotic effects on the gut microbiome.
Comparing barberry and dandelion as cholagogues:
- Bitterness — dandelion is moderately bitter, less intense than barberry or gentian. The cephalic-phase effect is real but less pronounced.
- Cholagogue / choleretic effect — dandelion has a long traditional reputation for stimulating bile flow, supported by some animal data. Barberry is at least comparable, with some studies suggesting greater direct gallbladder smooth muscle effect.
- Gentleness — dandelion is markedly milder than barberry. Herbalists often start sensitive people, or those wanting gentle long-term daily use, on dandelion.
- Diuretic effect — dandelion leaf (not root) has substantial mild diuretic effect; barberry has essentially none.
- Prebiotic effect — dandelion root contains inulin (10-40% by weight depending on harvest time), which provides substantial prebiotic effect on gut microbiome. Barberry has indirect microbiome effects through the antimicrobial mechanism (see the Antimicrobial deep-dive) but no prebiotic content.
- Metabolic / antimicrobial effects — barberry has the berberine-mediated metabolic and antimicrobial actions; dandelion does not.
Dandelion root is the gentler and more accessible of the two (it can even be foraged from untreated lawns and parks, where the root is the medicinal part), while barberry gives the stronger bitter effect plus the broader berberine pharmacology. Herbalists also combine them in a tincture blend — equal parts barberry root, dandelion root, and (optionally) artichoke leaf, taken 40-60 drops in water 15-20 minutes before meals, is a classical multi-cholagogue digestive formulation.
See our Dandelion page for more on dandelion root and leaf as separate medicinal preparations.
Functional Dyspepsia and Postprandial Distress Syndrome
Functional dyspepsia (FD) is defined by the Rome IV criteria as bothersome postprandial fullness, early satiety, epigastric pain, or epigastric burning, occurring at least three days per week for at least three months, in the absence of an organic explanation. It is subdivided into two major subtypes: postprandial distress syndrome (PDS, dominated by fullness and early satiety) and epigastric pain syndrome (EPS, dominated by pain and burning). FD affects approximately 10-30% of adults in Western populations.
Conventional medical management of FD includes proton pump inhibitors (more effective for EPS than PDS), prokinetics (metoclopramide, domperidone, more effective for PDS), tricyclic antidepressants in low dose (visceral hypersensitivity modulation), and reassurance plus dietary adjustment. Outcomes are modest.
Herbalists give several reasons for using bitter herbs in FD, particularly the PDS subtype:
- Improved cephalic-phase preparation — many FD patients have blunted cephalic-phase digestive response from chronic stress, distracted eating, or previous extended antacid use
- Gastric emptying — bitters have been described as speeding stomach emptying for the "food sitting in my stomach" complaint that dominates PDS, but the studies point the other way: a bitter taste slowed stomach emptying in 16 healthy women (Wicks and colleagues, 2005), and in mice bitter compounds placed in the stomach slowed emptying through a direct effect on stomach muscle that was not mediated by CCK or GLP-1 (Janssen and colleagues, 2011)
- Increased gastric acid secretion — many FD patients have unsuspected hypochlorhydria (often secondary to age, H. pylori, or proton pump inhibitor (PPI) overuse). Restoring cephalic-phase acid secretion improves protein digestion and reduces fermentation-driven bloating
- Improved bile delivery — the cholagogue effect addresses the fat-meal intolerance component
- Anti-H. pylori effect — berberine has documented activity against H. pylori, the most common identifiable cause of dyspeptic symptoms (covered on the Antimicrobial deep-dive)
The best-studied human use of berberine for the stomach is alongside antibiotics against H. pylori. A 2019 meta-analysis by Hu and colleagues pooled 13 randomized trials from China and found that adding berberine to standard triple therapy raised the eradication rate (relative risk, RR, 1.22), improved peptic ulcer healing (RR 1.15) and symptom relief (RR 1.11), and lowered side effects (RR 0.65), compared with triple therapy alone. These regimens used berberine together with antibiotics, not berberine or barberry tincture on its own.
The FD protocol herbal practitioners describe with barberry is 40-60 drops of 1:5 tincture in water, taken 15-20 minutes before each meal; practitioners report that people who benefit tend to notice it within 1-2 weeks of consistent use. Where H. pylori is suspected or confirmed, some practitioners add higher-dose berberine (500 mg three times daily) for the antimicrobial effect.
Hypochlorhydria and Age-Related Acid Decline
Hypochlorhydria (reduced gastric acid secretion) is increasingly recognized as a frequently overlooked clinical entity. Causes include:
- Age — gastric acid output declines with age; by age 70, approximately 30% of adults have measurably reduced HCl secretion
- Chronic proton pump inhibitor use
- Chronic H. pylori infection, particularly atrophic gastritis stage
- Autoimmune atrophic gastritis (often with pernicious anemia)
- Hypothyroidism
- Chronic stress and sympathetic dominance
- Bariatric surgery (gastric bypass, sleeve gastrectomy)
Hypochlorhydria produces a constellation of symptoms: postprandial bloating and fullness, belching, fermentation-driven flatulence within 30-60 minutes of eating, sense of food "sitting" in the stomach, undigested food in stool, increased susceptibility to enteric infection (since gastric acid is a major innate antimicrobial barrier), and a series of nutritional deficiencies (B12, iron, magnesium, zinc, calcium) due to impaired protein digestion and reduced ionization of mineral nutrients.
Conventional management of hypochlorhydria is poorly supported by guidelines. Functional medicine commonly uses betaine HCl supplementation (typically 1-3 capsules of 500-650 mg betaine HCl with protein-containing meals, titrated to symptom resolution without epigastric burning). Pre-meal bitter herbs are an alternative or adjunct that work through restoration of the cephalic-phase HCl response rather than direct HCl replacement.
The barberry protocol practitioners describe for hypochlorhydria is 40-60 drops of 1:5 tincture in water, 15-20 minutes before meals. Many people prefer the bitter-herb approach because it restores the body's own acid-secretion response rather than substituting it, and because it avoids the small but real risk of betaine HCl causing gastritis or ulceration in patients with unsuspected mucosal compromise.
Some practitioners combine bitters with a modest dose of betaine HCl, reasoning that the bitter restores the regulatory response while the betaine provides supplemental capacity as the body's own response recovers.
Post-Cholecystectomy Syndrome
Post-cholecystectomy syndrome refers to the constellation of digestive symptoms that persist or develop after surgical removal of the gallbladder (cholecystectomy). Affects approximately 10-40% of cholecystectomy patients, depending on the criteria used. Common symptoms:
- Postprandial bloating, particularly after fat-containing meals
- Bile-acid diarrhea (chronic loose stools 1-3 times per day, often shortly after meals)
- Fat malabsorption with steatorrhea in severe cases
- Epigastric or right upper quadrant pain
- Nausea, particularly after fat-rich meals
- Sphincter of Oddi dysfunction (less common but more severe; can require sphincterotomy)
The pathophysiology is that without the gallbladder reservoir, bile drips continuously from the liver into the duodenum at a low baseline rate rather than being concentrated and released in a coordinated postprandial bolus. This produces three downstream problems: (1) the constant low-level bile flow into the duodenum and beyond reaches the colon and causes bile-acid diarrhea; (2) the absence of postprandial bile bolus means inadequate bile delivery to emulsify fats consumed in a large fat-rich meal; (3) the loss of the gallbladder's volumetric reservoir means no buffering of bile flow against changes in hepatic bile production.
Barberry tincture pre-meals is used for the second component (inadequate postprandial bile delivery), with the reasoning resting on the CCK / sphincter of Oddi mechanism: by stimulating CCK release before food arrives and promoting sphincter of Oddi relaxation, the small bolus of bile that has accumulated in the common bile duct is released into the duodenum precisely when fat enters — partially restoring the lost gallbladder-mediated coordination.
The first component (bile-acid diarrhea) is conventionally treated with bile acid sequestrants (cholestyramine, colesevelam) or with smaller, more frequent meals to reduce the postprandial bile-flow spike. Berberine itself has some effect on bile acid metabolism via farnesoid X receptor (FXR) signaling that may modestly help, but barberry tincture is not the primary tool for this component.
For more on gallbladder disease, see our Gallbladder Disease page.
Irritable Bowel Syndrome (IBS) Applications
Irritable bowel syndrome (IBS) is the most common functional gastrointestinal disorder, affecting approximately 10-15% of adults. The Rome IV criteria require recurrent abdominal pain on average at least one day per week in the last three months, associated with two or more of: relation to defecation, change in stool frequency, or change in stool form. IBS is subtyped as diarrhea-predominant (IBS-D), constipation-predominant (IBS-C), mixed (IBS-M) or unsubtyped (IBS-U).
Barberry has potential utility in several irritable bowel syndrome subtypes through different mechanisms:
- Diarrhea-predominant irritable bowel syndrome with post-prandial trigger — if the diarrhea is largely postprandial and bile-acid diarrhea is suspected, barberry tincture pre-meal may modestly help through bile acid metabolism modulation. More importantly, if a small intestinal bacterial overgrowth (SIBO) component is present (covered below), the antimicrobial berberine effect addresses the upstream cause.
- Constipation-predominant irritable bowel syndrome with bloating and fermentation — the digestive bitter + cholagogue effect improves upstream digestion, reducing the substrate available for colonic bacterial fermentation that produces gas and bloating. May also help motility through cephalic-phase preparation.
- Mixed-type irritable bowel syndrome (IBS-M) with postprandial distress — bitter herbs improve cephalic-phase preparation; the antimicrobial effect addresses any pathobiont overgrowth.
- Irritable bowel syndrome with small intestinal bacterial overgrowth — in herbal practice berberine is one of the first-line botanical options for small intestinal bacterial overgrowth treatment, often used in 4-week protocols at 500 mg three times daily (often combined with neem, oregano oil, or rifaximin for the more difficult cases). See our small intestinal bacterial overgrowth page.
A randomized trial has tested the berberine alkaloid in IBS. In a 2015 double-blind, placebo-controlled trial by Chen and colleagues, 132 people with diarrhea-predominant IBS took berberine hydrochloride 400 mg a day (given in two doses) or placebo for 8 weeks; diarrhea, abdominal pain and urgent need to pass stool all became less frequent in the berberine group than in the placebo group, and berberine was well tolerated. The trial tested the purified alkaloid, not barberry tincture.
The irritable bowel syndrome protocols practitioners describe with barberry depend on the dominant features. For mild irritable bowel syndrome with prominent dyspepsia: 40-60 drops of 1:5 tincture in water, pre-meals. For irritable bowel syndrome with confirmed or suspected small intestinal bacterial overgrowth: standardized berberine 500 mg three times daily for 4 weeks, often combined with neem or oregano oil by clinicians familiar with small intestinal bacterial overgrowth botanical protocols. For more on irritable bowel syndrome generally, see our Irritable Bowel Syndrome page.
Fat-Meal Intolerance and Steatorrhea
Fat-meal intolerance (postprandial bloating, nausea, abdominal cramping after fat-rich meals) and steatorrhea (visible fat in stools, floating greasy stools, oily anal leakage) reflect inadequate fat digestion. Causes include:
- Biliary insufficiency from gallbladder disease, post-cholecystectomy syndrome, or intrahepatic cholestasis
- Pancreatic exocrine insufficiency (chronic pancreatitis, cystic fibrosis, post-pancreatic surgery, severe diabetes)
- Small intestinal disease (celiac disease, Crohn's disease, small intestinal bacterial overgrowth, post-radiation enteritis)
- Reduced bile acid pool from ileal resection or extensive bile acid sequestrant use
The barberry / cholagogue intervention is most useful for the biliary insufficiency component. By stimulating bile flow, sphincter of Oddi relaxation, and gallbladder contraction (in patients with intact gallbladder), the pre-meal bitter improves bile delivery to the duodenum coincident with the arrival of fat — restoring proper fat emulsification and reducing the malabsorption signal.
For pancreatic exocrine insufficiency, pancreatic enzyme replacement therapy (PERT) with pancrelipase is the primary intervention; bitters may modestly help through CCK-mediated stimulation of any residual pancreatic enzyme secretion but cannot replace PERT.
For small intestinal disease, treatment is aimed at the underlying disease. Bitters may help symptomatically but cannot substitute for treatment of celiac, Crohn's, or other primary intestinal pathology.
Small Intestinal Bacterial Overgrowth and Small-Intestinal Motility
Small intestinal bacterial overgrowth (SIBO) is a clinical syndrome of excessive bacterial colonization of the small intestine, typically associated with bloating, postprandial distention, abdominal pain, altered bowel habits, and sometimes malabsorption with secondary nutritional deficiencies. Small intestinal bacterial overgrowth can be diagnosed by breath testing (lactulose or glucose hydrogen breath test) or aspirate culture of the proximal jejunum.
Berberine has emerged as one of the better-evidence-supported botanical options for small intestinal bacterial overgrowth treatment. A 2014 retrospective chart review by Chedid and colleagues at a hospital gastroenterology referral practice (not a randomized trial: patients chose their own treatment) followed 104 people with newly diagnosed SIBO on the lactulose breath test. Of 37 who took commercial herbal blends for 4 weeks, 17 (46%) had a negative follow-up breath test, compared with 23 of 67 (34%) who took the antibiotic rifaximin (P=.24, a difference that was not statistically significant). The blends contained berberine-containing herbs (Indian barberry root and Coptis root) and berberine sulfate, with oregano oil and thyme oil among other herbs. Of 14 people for whom rifaximin had not worked and who were then given the herbal blends, 8 (57.1%) had a negative breath test afterwards. Reported side effects were 1 case of anaphylaxis, 2 of hives, 2 of diarrhea and 1 Clostridium difficile infection with rifaximin, against 1 case of diarrhea with the herbs. Botanical small intestinal bacterial overgrowth protocols used by practitioners typically give berberine 500 mg three times daily for 4-6 weeks; that dosing comes from practice, not from this study.
The mechanism of berberine in small intestinal bacterial overgrowth involves both direct antimicrobial action (covered in the Antimicrobial deep-dive) and pro-motility effects that help clear the small intestine of stagnant content. The migrating motor complex (MMC) is the "housekeeper" wave of gastrointestinal motility that sweeps the small intestine between meals; impaired MMC is a key contributing factor to small intestinal bacterial overgrowth. Berberine's cholinergic / vagal effects support normal MMC function.
The relevance to the digestive-aid use of barberry is that even low-dose barberry tincture pre-meals may have a modest preventive effect against small intestinal bacterial overgrowth recurrence by supporting motility and biliary clearance. For active small intestinal bacterial overgrowth, practitioners use higher-dose standardized berberine. For small intestinal bacterial overgrowth prevention after successful eradication, the long-term strategy practitioners describe is pre-meal bitters plus attention to meal spacing (4-5 hours between meals to allow MMC waves) and addressing root causes (hypothyroidism, abdominal adhesions, structural issues).
For more on small intestinal bacterial overgrowth, see our small intestinal bacterial overgrowth page with its extensive deep-dive sub-articles on testing, root causes, treatment protocols, and prokinetics.
Practical Preparations — Tincture, Decoction, Bitter Blend
Barberry tincture (the most practical digestive bitter form).
- Standard preparation: 1:5 ratio dried root in 40-50% alcohol (vodka or grain alcohol diluted with water to target percent)
- Macerate for 6 weeks with daily shaking, then press and strain
- Dosing: 40-60 drops (2-4 mL) diluted in 1-2 ounces of water, taken 15-20 minutes before meals
- Shelf life: indefinite when stored in dark glass with intact alcohol content
- Commercial options: commercial tinctures are widely available from herbal pharmacies
Barberry root decoction.
- 1-2 teaspoons (2-4 g) of dried, crushed barberry root bark in 250-300 mL water
- Simmer 15-20 minutes, strain
- Traditionally sipped slowly so the bitter taste registers on the tongue, rather than swallowed in one gulp like medicine, since the cephalic-phase effect is held to depend on actual tasting
- Sometimes sweetened with a small amount of honey for palatability; herbalists keep some bitterness for the cephalic-phase effect
Classical bitter blend tincture (multi-herb).
- Equal parts (1 part each): barberry root, dandelion root, gentian root, and orange peel
- 1:5 in 50% alcohol, macerated 6 weeks
- Dosing: 40-60 drops in water 15-20 minutes before meals
- The orange peel contributes additional bitter compounds plus a more palatable aromatic profile
Swedish bitters or similar traditional formulations.
- Commercial Swedish bitters (Maria Treben's formula and variants) are widely available and contain barberry root alongside other classical bitters
- Label directions typically give 1 teaspoon in water before meals
Barberry capsules (traditionally not used for the digestive-bitter effect).
- Capsules bypass the oral bitter receptor and lose the cephalic-phase effect entirely
- Used for the higher-dose antimicrobial or metabolic purposes rather than as a digestive bitter
- Some practitioners describe opening the capsule and dissolving the contents in a small amount of water before swallowing (e.g., when capsules are used for portability), so the bitter at least partly touches the tongue
The Pre-Meal Dosing Window (10-20 Minutes)
The dosing window herbalists give for digestive bitters is 10-20 minutes before the meal. Their rationale:
- The cephalic-phase response begins within seconds of bitter taste contact and peaks at approximately 10-20 minutes
- By the time food arrives, gastric acid secretion is fully primed, gastric tone is increased, and intestinal hormonal preparation is established
- Dosing immediately before eating (less than 5 minutes) does not allow full cephalic-phase preparation; the food arrives before the system has fully primed
- Dosing more than 30 minutes before eating allows the cephalic-phase response to wane before the food arrives
- Dosing during or after the meal can still produce some intestinal effects from the swallowed bitter compounds but loses most of the oral / cephalic-phase benefit
The common practice is to take the bitter tincture or decoction about 15 minutes before sitting down to eat, while preparing the food or setting the table. Practitioners describe a secondary benefit of this timing: a brief mindful pause before eating, which improves the broader digestive context (slower, more attentive eating, better chewing, reduced sympathetic activation).
Frequency: typically 2-3 times daily before main meals. Some practitioners recommend even a small dose before snacks if dyspeptic symptoms occur with snacks. Long-term daily use is well tolerated and many traditional cultures consume bitter aperitifs daily (the Italian amaro tradition, French digestifs, German Magenbitter) without apparent adverse effects.
Cautions and Contraindications
- Pregnancy and breastfeeding (contraindicated) — berberine crosses the placenta and displaces bilirubin from albumin binding, risking kernicterus in newborns. For this reason herbal references list pregnancy and breastfeeding as contraindications for barberry preparations. Ginger and chamomile are the gentler herbs traditionally used for digestive upset in pregnancy.
- Active peptic ulcer disease — the bitter-stimulated increase in gastric acid secretion can aggravate active peptic ulcer. Herbal practice is to heal the ulcer with conventional therapy first and to bring bitters in only afterwards, cautiously, if acid secretion needs restoring.
- Hyperchlorhydria / acid reflux (use caution) — in some patients with gastroesophageal reflux disease (GERD) or excessive acid secretion, additional bitter-stimulated acid can worsen symptoms. The clinical picture matters: gastroesophageal reflux disease with a weak lower esophageal sphincter (LES) and normal acid may improve with bitters (better cephalic-phase preparation reduces fermentation pressure on LES); GERD with hyperchlorhydria may worsen. Practitioners describe trying bitters cautiously and stopping them if symptoms worsen.
- Bile duct obstruction — in mechanical biliary obstruction (gallstone in the common bile duct, cholangiocarcinoma, pancreatic head mass), the cholagogue effect of bitters cannot empty against the obstruction and may cause biliary colic. Herbal references treat bile duct obstruction as a contraindication.
- Severe inflammatory bowel disease flare — the increased gastrointestinal motility and secretion stimulated by bitters can theoretically aggravate active inflammatory bowel disease (IBD). Practitioners generally hold off bitters during active severe flares.
- Children — berberine is contraindicated in infants because of the bilirubin / kernicterus concern. In herbal practice, diluted barberry tincture is used as a digestive bitter in older children.
- Drug interactions — berberine inhibits several liver enzymes that clear many drugs: in a human study, repeated berberine lowered cytochrome P450 2D6 (CYP2D6) activity (the test ratio rose ninefold), CYP2C9 activity (the test ratio doubled) and CYP3A4 activity (blood exposure to the test drug midazolam rose 40%), so it can raise blood levels of drugs cleared these ways; the concern is greatest with chronic high-dose use and smaller, though not absent, with lower-dose pre-meal tincture use, which matters most for people taking several medicines.
Key Research Papers
- McMullen MK et al. (2015). Bitters: time for a new paradigm. Evidence-Based Complementary and Alternative Medicine. — comprehensive review of the bitter-receptor / cephalic-phase mechanism. PubMed PMID: 26074998
- Wicks D, Wright J, Rayment P, Spiller R (2005). Impact of bitter taste on gastric motility. European Journal of Gastroenterology and Hepatology. — in 16 healthy women, a bitter taste delayed gastric emptying. PubMed PMID: 16093874
- Behrens M, Meyerhof W (2011). Gustatory and extragustatory functions of mammalian taste receptors. Physiology and Behavior. — the extra-oral TAS2R distribution paper. PubMed PMID: 21324331
- Janssen S et al. (2011). Bitter taste receptors and alpha-gustducin regulate the secretion of ghrelin with functional effects on food intake and gastric emptying. PNAS. — bitter-receptor / gastric emptying axis. PubMed PMID: 21245306
- Imanshahidi M, Hosseinzadeh H (2008). Pharmacological and therapeutic effects of Berberis vulgaris and its active constituent, berberine. Phytotherapy Research. — comprehensive Berberis vulgaris review covering digestive indications. PubMed PMID: 18618524
- Chedid V, Dhalla S, Clarke JO, Roland BC, Dunbar KB, Koh J, Justino E, Tomakin E, Mullin GE (2014). Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine. — a retrospective chart review of berberine-containing herbal blends versus rifaximin. PubMed PMID: 24891990
- Moayyedi P, Lacy BE, Andrews CN, Enns RA, Howden CW, Vakil N (2017). ACG and CAG Clinical Guideline: Management of Dyspepsia. American Journal of Gastroenterology. — conventional context for functional dyspepsia. PubMed PMID: 28631728
- Chen C, Tao C, Liu Z, Lu M, Pan Q, Zheng L, Li Q, Song Z, Fichna J (2015). A Randomized Clinical Trial of Berberine Hydrochloride in Patients with Diarrhea-Predominant Irritable Bowel Syndrome. Phytotherapy Research. — 132 people with IBS-D, berberine hydrochloride 400 mg a day versus placebo for 8 weeks. PubMed PMID: 26400188
- Hu Q, Peng Z, Li L, Zou X, Xu L, Gong J, Yi P (2019). The Efficacy of Berberine-Containing Quadruple Therapy on Helicobacter Pylori Eradication in China: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Frontiers in Pharmacology. — berberine added to standard triple therapy for H. pylori. PubMed PMID: 32116685
- Guo Y, Chen Y, Tan ZR, Klaassen CD, Zhou HH (2012). Repeated administration of berberine inhibits cytochromes P450 in humans. European Journal of Clinical Pharmacology 68(2):213-217. — PubMed PMID: 21870106
PubMed Topic Searches
Connections
- All Herbs
- Barberry Overview
- Barberry Benefits Hub
- Barberry for Antimicrobial Action
- Barberry for Blood Sugar
- Barberry for Liver Health
- Berberine (Standardized Supplement)
- Berberine Benefits Deep Dive
- Dandelion Root
- Goldenseal
- Turmeric
- Ginger
- Gallbladder Disease
- Irritable Bowel Syndrome
- Small Intestinal Bacterial Overgrowth
- Small Intestinal Bacterial Overgrowth — Root Causes
- Small Intestinal Bacterial Overgrowth — Prokinetics and Relapse Prevention
- Gut Healing
- Gut-Brain Axis
- History