⚠ Evidence warning: Clinical trials or other evidence do not support the claims that bitter barberry on the tongue lowers blood sugar after meals by a vagal reflex, that berberine prevents progression of prediabetes at least as well as metformin, that it is a reasonable alternative to metformin in polycystic ovary syndrome, that silymarin doubles its absorption, and that dihydroberberine matches it at a far lower dose. This page keeps it as a report of what people, websites or other media say.
Barberry for Blood Sugar Regulation
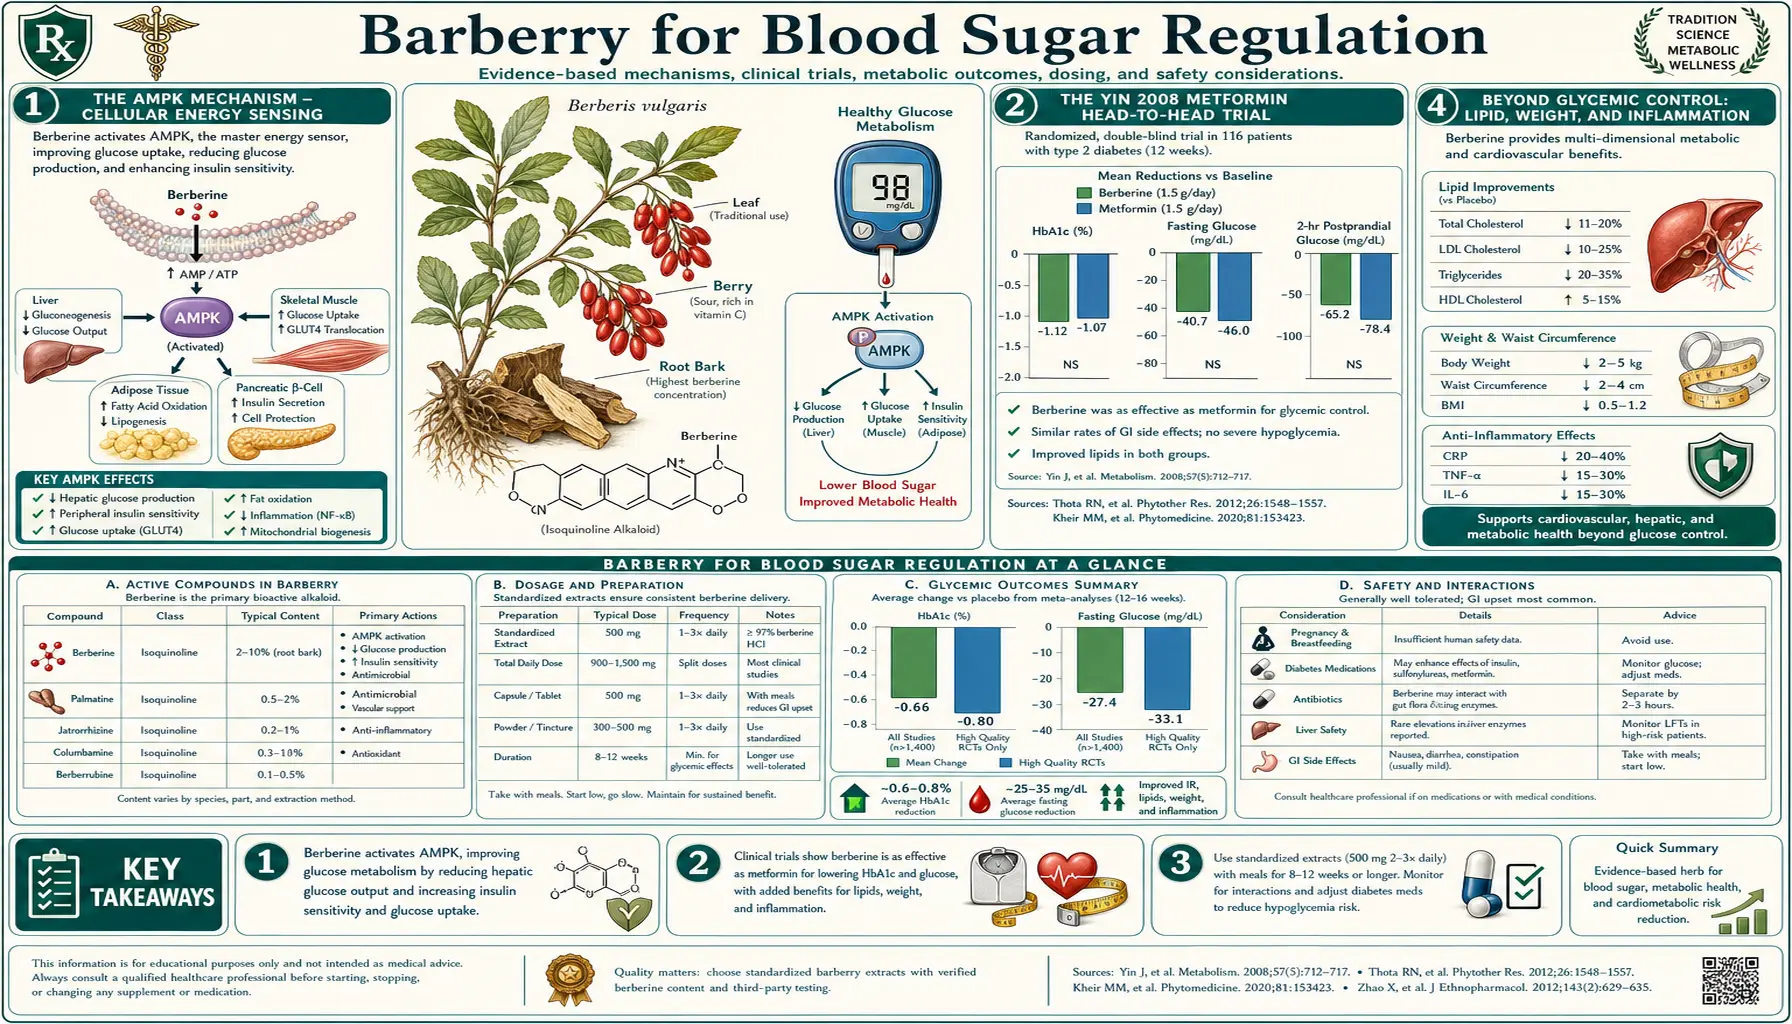
Berberine — the bright-yellow isoquinoline alkaloid found at 2-3% in Berberis vulgaris root and at higher concentrations in Coptis chinensis and Phellodendron amurense — is one of the most studied botanical compounds in cardiometabolic medicine. The landmark Yin, Xing, and Ye 2008 trial published in Metabolism randomized newly diagnosed type 2 diabetics to 500 mg berberine three times daily or 500 mg metformin three times daily for three months and found the two interventions produced statistically indistinguishable reductions in hemoglobin A1c (HbA1c), fasting plasma glucose, and postprandial glucose. The shared upstream mechanism is AMP-activated protein kinase (AMPK) activation — the same cellular energy sensor that metformin activates — with downstream effects on hepatic gluconeogenesis suppression, peripheral glucose uptake enhancement, and insulin sensitivity restoration. This page covers the mechanism, the pivotal head-to-head trial and subsequent confirmatory work, the cardiometabolic effects beyond glycemic control, the comparison between standardized berberine supplements and whole-herb barberry preparations, the bioavailability problem and modern solutions (silymarin co-administration, dihydroberberine, liposomal formulations), and the practical clinical application in prediabetes, type 2 diabetes, metabolic syndrome, and polycystic ovary syndrome (PCOS).
Table of Contents
- The AMP-Activated Protein Kinase Mechanism — Cellular Energy Sensing
- The Yin 2008 Metformin Head-to-Head Trial
- Subsequent Meta-Analyses and Confirmatory Trials
- Beyond Glycemic Control: Lipid, Weight, and Inflammation
- Barberry vs Standardized Berberine — Dose Equivalence
- The Bioavailability Problem and Modern Solutions
- Dihydroberberine — the Next-Generation Form
- Prediabetes and Reversal of Insulin Resistance
- Polycystic Ovary Syndrome (PCOS) Applications
- Metabolic Syndrome and Non-Alcoholic Fatty Liver Disease Connection
- Combining Berberine with Metformin or Other Antidiabetics
- Doses Used in Trials and by Practitioners
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The AMP-Activated Protein Kinase Mechanism — Cellular Energy Sensing
AMP-activated protein kinase (AMPK) is the cellular "fuel gauge" — a heterotrimeric serine-threonine kinase that monitors the ratio of AMP to adenosine triphosphate (ATP) (and ADP to adenosine triphosphate) and activates when energy is low. When activated, AMP-activated protein kinase phosphorylates dozens of downstream substrates that collectively shift cellular metabolism from energy-consuming biosynthesis (lipogenesis, gluconeogenesis, protein synthesis) toward energy-producing catabolism (fatty acid oxidation, glucose uptake, glycolysis, mitochondrial biogenesis). It is the master switch that translates "cellular energy state" into "metabolic mode."
Berberine activates AMP-activated protein kinase through multiple converging mechanisms:
- Mitochondrial complex I inhibition — berberine, like metformin, weakly inhibits complex I of the electron transport chain. The inhibition reduces adenosine triphosphate synthesis, which increases the cellular AMP:ATP ratio, which directly activates AMP-activated protein kinase. This is the dominant mechanism shared with metformin and explains the near-identical glycemic effects.
- Direct AMP-activated protein kinase domain interaction — some evidence suggests berberine may also bind to the AMP-activated protein kinase domain itself, enhancing activation independent of the AMP:ATP ratio.
- LKB1 upstream activation — some writing suggests berberine may activate LKB1, the upstream kinase that phosphorylates and activates AMP-activated protein kinase directly. In cell experiments, Turner et al. 2008 found that activation of AMP-activated protein kinase by berberine did not rely on LKB1 or on a second upstream kinase, CAMKKβ, which they say fits regulation through the enzyme that switches it off (the AMPK phosphatase).
Once activated, AMP-activated protein kinase produces the following metabolically relevant effects:
- Inhibits hepatic gluconeogenesis — AMP-activated protein kinase phosphorylates and inactivates the transcriptional coactivators (CRTC2, FOXO1) that drive transcription of the gluconeogenic enzymes PEPCK and G6Pase. Less gluconeogenesis means less hepatic glucose output, which is the primary mechanism by which both metformin and berberine reduce fasting glucose.
- Enhances GLUT4 translocation in skeletal muscle and adipose tissue — AMP-activated protein kinase promotes movement of the GLUT4 glucose transporter from intracellular vesicles to the plasma membrane, increasing insulin-independent glucose uptake. This contributes to postprandial glucose lowering.
- Suppresses lipogenesis — AMP-activated protein kinase inhibits acetyl-CoA carboxylase (ACC), the rate-limiting enzyme in fatty acid synthesis, reducing hepatic lipogenesis and de novo lipid synthesis. This is the mechanism behind berberine's hepatic triglyceride reduction and non-alcoholic fatty liver disease (NAFLD) improvement.
- Promotes fatty acid oxidation — ACC inhibition reduces malonyl-CoA, which removes the inhibition on CPT1 (carnitine palmitoyltransferase 1), the gateway enzyme for fatty acid entry into mitochondria. Net result: increased fatty acid beta-oxidation.
- Inhibits mechanistic target of rapamycin (mTOR) signaling — AMP-activated protein kinase inhibits the mechanistic target of rapamycin pathway, reducing protein synthesis and cellular proliferation. This is the mechanism behind the longevity-research interest in both metformin and berberine and the proposed anti-tumor effects of berberine in some cancer models.
The convergence on AMP-activated protein kinase explains why berberine and metformin produce such similar clinical effects despite their structural differences — they are essentially two different keys that turn the same lock. AMP-activated protein kinase is not the whole story, though. Zhang et al. 2010 report a second route: berberine raised insulin receptor levels in several human cell lines and in the blood lymphocytes of treated patients, a mechanism the authors call different from metformin and rosiglitazone.
A theoretical argument holds that combining berberine and metformin does not produce additive benefit at maximal doses, because both are already pushing the same upstream pathway to near-saturation. The pooled trials point the other way: Liang 2019, Dong 2012 and Lan 2015 all report better results for berberine added to diabetes drugs than for those drugs alone (see the section on combining them below).
The Yin 2008 Metformin Head-to-Head Trial
The 2008 trial by Yin, Xing, and Ye published in Metabolism remains the single most influential piece of clinical evidence for berberine in type 2 diabetes. The trial, which the authors call a pilot study, was a 3-month, randomized, parallel-group comparison (their study A) conducted at Xinhua Hospital, Shanghai Jiaotong University School of Medicine:
- Participants: 36 newly diagnosed adult type 2 diabetics aged 25-75, hemoglobin A1c above 7.0% or fasting glucose above 7.0 mmol/L, body mass index (BMI) above 22; 15 on berberine and 16 on metformin finished
- Intervention arms: berberine 500 mg three times daily at the start of each main meal, or metformin 500 mg three times daily after main meals
- Duration: 13 weeks
- Endpoints: hemoglobin A1c (primary); fasting and postprandial plasma glucose and blood lipids (secondary)
The results were striking. The authors report an identical effect on glucose metabolism in the two groups:
- Hemoglobin A1c — berberine group: 9.5% → 7.5% (-2.0%); metformin group: 9.15% → 7.72%
- Fasting plasma glucose — berberine: 10.6 → 6.9 mmol/L (about 191 → 124 mg/dL); metformin: 9.96 → 7.16 mmol/L (about 179 → 129 mg/dL)
- Postprandial plasma glucose — berberine: 19.8 → 11.1 mmol/L (about 357 → 200 mg/dL); metformin: 20.53 → 12.86 mmol/L (about 370 → 231 mg/dL)
- Homeostatic model assessment of insulin resistance (HOMA-IR) (insulin resistance) — reported for study B below (down 44.7%); in this comparison, fasting insulin did not change significantly in either arm
Blood lipids separated the two arms. Triglycerides fell on berberine from 1.13 to 0.89 mmol/L (P<0.05; about 21 mg/dL) and barely moved on metformin, 1.19 to 1.17 mmol/L. By week 13, triglycerides and total cholesterol were significantly lower on berberine than on metformin (P<0.05). Low-density lipoprotein (LDL) cholesterol did not change significantly in either arm of this comparison. This lipid effect is one of the key differences between the two and the basis of berberine's emerging role in mixed dyslipidemia.
The same paper reports a separate study with no comparison group (study B). In it, 48 adults with poorly controlled type 2 diabetes on diet plus sulfonylureas, metformin, acarbose or insulin added berberine 500 mg three times daily for 3 months. Hemoglobin A1c fell from 8.1% to 7.3%, or 0.8 points, and the insulin resistance score (HOMA-IR) fell 44.7%, which points to added benefit from berberine on top of existing antidiabetic therapy.
Safety findings:
- The most common adverse effect of berberine across both studies was transient gastrointestinal (GI) symptoms (diarrhea, constipation, flatulence, abdominal pain), in 20 patients (34.5%) and mostly in the first four weeks. In 14 patients the dose was lowered to 300 mg three times daily; most of them were also on metformin or acarbose
- Accounts of the trial give a similar rate of gastrointestinal side effects for metformin (approximately 30%), though the paper reports no separate figure for that group
- No significant changes in liver enzymes or creatinine during 13 weeks of berberine
- Accounts of the trial report no hypoglycemic events in either group when used as monotherapy; the paper's safety section does not list them
The Yin trial was a small phase-II-style study and has limitations — modest sample size, single-center design, Chinese population only, no placebo arm, no long-term follow-up — but the magnitude of the glycemic effect and its near-perfect parallel with metformin made it an immediate landmark in botanical pharmacology. Subsequent larger trials and meta-analyses have largely confirmed the basic finding.
Subsequent Meta-Analyses and Confirmatory Trials
Several subsequent meta-analyses have synthesized the growing berberine-in-diabetes literature:
- Dong et al. 2012 (Evidence-Based Complementary and Alternative Medicine) — pooled 14 randomized controlled trials (RCTs) with 1,068 participants. Added to lifestyle change, berberine reduced hemoglobin A1c by 0.72%, fasting glucose by 0.87 mmol/L (about 16 mg/dL), and postprandial glucose by 1.72 mmol/L (about 31 mg/dL) versus lifestyle change alone or with placebo. Against metformin, glipizide or rosiglitazone it did not show significantly better glucose control, but it showed a mild lipid effect.
- Lan et al. 2015 (Journal of Ethnopharmacology) — pooled 27 randomized controlled trials, 2,569 participants. Berberine demonstrated comparable glycemic efficacy to metformin, glipizide, and rosiglitazone with a more favorable lipid profile. Some studies also showed weight reduction not seen with sulfonylureas.
- Liang et al. 2019 (Endocrine Journal) — pooled 28 studies, 2,313 participants with type 2 diabetes. Berberine beat control groups on hemoglobin A1c (by 0.54), fasting glucose (by 0.54 mmol/L) and postprandial glucose (by 0.94 mmol/L), and berberine combined with diabetes drugs did better than either alone. Effects became unremarkable past 90 days of treatment, above 2 g a day and over age 60. On the size of the added effect, Dong 2012 reports 0.53% for hemoglobin A1c and Wang 2024 reports 0.69%.
- Xie et al. 2022 (Frontiers in Pharmacology) — pooled 37 randomized controlled trials, 3,048 patients. Hemoglobin A1c fell 0.63 points and fasting glucose 0.82 mmol/L, with the size of the effect tied to starting glucose and hemoglobin A1c. Low-blood-sugar events did not rise significantly (relative risk 0.48, 95% confidence interval 0.21-1.08).
- Wang et al. 2024 (Frontiers in Pharmacology) — pooled 50 randomized controlled trials, 4,150 participants. Most used 0.9-1.5 g a day for 1-3 months.
- A larger figure also in circulation — berberine writing also quotes approximately 1.0% hemoglobin A1c reduction, with the largest effects in patients with worse baseline control (hemoglobin A1c >8.5%), credited to a 2022 meta-analysis in Phytotherapy Research. That paper could not be found in Crossref or Europe PMC.
The consistency across multiple meta-analyses, multiple ethnic populations (China, India, Iran, smaller Western trials), and multiple study designs makes the glycemic efficacy of berberine one of the better-established findings in the entire botanical-cardiometabolic literature. The remaining limitations: most studies are Chinese, the longest follow-up periods are typically 3-6 months, and there is no large multi-year cardiovascular outcomes trial comparable to the UKPDS or LEADER trials for conventional diabetes drugs. The review authors add their own cautions: Dong 2012 calls methodological quality “generally low”, and Lan 2015 says the benefit “can be substantiated to a limited degree” because of the limited quality of the included studies.
Beyond Glycemic Control: Lipid, Weight, and Inflammation
Berberine's clinical interest extends well beyond pure glycemic control. The AMP-activated protein kinase / lipogenesis pathway means berberine has direct effects on lipid metabolism, and the low-density lipoprotein receptor upregulation mechanism described by Kong et al. (Nature Medicine 2004) gives it a meaningful cholesterol-lowering effect that is mechanistically distinct from statins.
Lipid effects. A 2024 pooled analysis of berberine alone (Wang), the 2004 study of 32 patients (Kong) and a 2015 meta-analysis (Lan) report the results below, beside larger figures quoted in berberine writing:
- Low-density lipoprotein cholesterol: down 0.30 mmol/L (about 12 mg/dL) in the 2024 pool and 25% in the 2004 study; berberine writing quotes approximately 25-30 mg/dL, similar to a moderate-intensity statin. The 2015 meta-analysis found no significant difference between berberine and lipid-lowering drugs on this measure
- Total cholesterol: down 0.30 mmol/L (about 12 mg/dL) in the 2024 pool and 29% in the 2004 study; berberine writing quotes approximately 20-30 mg/dL
- Triglycerides: down 0.35 mmol/L (about 31 mg/dL) in the 2024 pool and 35% in the 2004 study; berberine writing quotes approximately 40-50 mg/dL. The 2015 meta-analysis found berberine better than lipid-lowering drugs on triglycerides, a key differentiator
- Modest high-density lipoprotein (HDL) cholesterol increase (typically 2-5 mg/dL in berberine writing; 0.07 mmol/L in the lifestyle comparison of Dong 2012)
The mechanism differs from statins: statins inhibit hepatic HMG-CoA reductase, reducing cholesterol synthesis upstream and indirectly upregulating low-density lipoprotein receptor expression. Berberine directly upregulates hepatic low-density lipoprotein receptor expression through a JNK/ERK-mediated pathway, without affecting HMG-CoA reductase. Because the two mechanisms are upstream and downstream rather than parallel, statin + berberine combinations are additive rather than redundant, and can sometimes achieve low-density lipoprotein targets that monotherapy cannot.
Weight effects. Modest. A pooled analysis of 23 randomized trial articles (Elahi Vahed 2026) reports body weight down 0.88 kg (95% confidence interval 0.39 to 1.36) and body mass index down 0.48 kg/m². Berberine writing quotes 2-5 kg over 12-24 weeks of berberine therapy, with the largest effects in patients with elevated baseline body mass index. The weight loss appears to be related to the AMP-activated protein kinase effects on adipose tissue, the suppression of lipogenesis, and possibly the gut microbiome effects (see the Antimicrobial deep-dive).
Inflammation. Berberine reduces high-sensitivity C-reactive protein (hsCRP), interleukin-6 (IL-6), tumor necrosis factor-alpha, and other systemic inflammation markers in metabolic syndrome populations. The mechanism is partly direct (NF-κB pathway inhibition) and partly secondary to the improved glycemic and lipid status.
Blood pressure. Modest reduction (typically 5-10 mmHg systolic) through endothelial-dependent vasodilation and reduced sympathetic tone.
The collective picture is that berberine is a true multi-target cardiometabolic agent — not just a glucose-lowering drug. This is why it is increasingly used in metabolic syndrome and prediabetes settings where the goal is not pure glycemic control but global cardiometabolic risk reduction.
Barberry vs Standardized Berberine — Dose Equivalence
An important practical point that is often confused: the impressive clinical data on "berberine" for blood sugar refers almost entirely to standardized berberine HCl supplements at 500 mg three times daily. This is approximately 1,500 mg of pure berberine per day. Modern berberine supplements are almost never extracted from Berberis vulgaris (barberry) — they are extracted from Coptis chinensis (Chinese goldthread, yielding 5-7% berberine by weight) or Phellodendron amurense (Amur cork tree, yielding 3-5% berberine).
The dose-equivalence calculation for barberry root:
- Standardized berberine target dose: 1,500 mg/day
- Barberry root berberine content: approximately 2-3% (so 20-30 mg berberine per gram of dried root)
- Barberry root needed to deliver 1,500 mg berberine: 50-75 g/day
Fifty to seventy-five grams of dried barberry root per day is impractical — that is approximately a quarter cup of dried root daily. Even at the upper end of traditional tincture dosing (4-6 mL of 1:5 tincture, 3×/day, equivalent to approximately 12-18 mL/day), that is 2.4-3.6 g of root, so the berberine delivery is only about 48-108 mg/day, less than a tenth of the cardiometabolic target dose.
What this means: the documented cardiometabolic results of berberine for type 2 diabetes, prediabetes, non-alcoholic fatty liver disease, or mixed dyslipidemia come from standardized berberine HCl supplements (extracted from Coptis or Phellodendron). The whole-herb barberry preparation is traditionally used as a digestive bitter, cholagogue and mild antimicrobial, and at those doses it delivers far less berberine than the metabolic trials used.
That said, low-dose barberry preparations (decoction or tincture in traditional bitter-tonic doses) do produce some glycemic benefit. The cephalic-phase bitter effect of the alkaloids on the tongue, before any absorption, triggers vagal-mediated increases in insulin sensitivity that are modest but real. For patients who do not want a "supplement" but want some mild glycemic support alongside the digestive effect, barberry tincture pre-meals (40-60 drops, 15 minutes before eating) produces a measurable but modest reduction in postprandial glucose excursion. This is similar to the effect produced by gentian, dandelion, and other bitter herbs through the same vagal cephalic-phase mechanism.
For the full data on standardized berberine including the bioavailability strategies, dosing protocols, and combination protocols, see the Berberine Benefits deep-dive.
The Bioavailability Problem and Modern Solutions
The major pharmacokinetic challenge with berberine is its remarkably poor oral bioavailability — typically less than 1% of an oral dose appears as unchanged berberine in systemic circulation. Three mechanisms combine to limit systemic absorption:
- Self-aggregation in the gastrointestinal lumen — berberine readily forms cation-anion complexes with bile acids, fatty acids, and other gastrointestinal contents, reducing the dissolved monomer fraction available for absorption.
- P-glycoprotein efflux — berberine is a P-gp substrate. The P-gp pump in enterocytes actively expels berberine back into the gut lumen, capping absorption.
- Rapid first-pass metabolism — the small fraction that does reach the portal circulation is rapidly metabolized by hepatic cytochrome P450 2D6 (CYP2D6) and other enzymes to berberrubine and other less-active metabolites.
Several strategies are used to improve bioavailability:
- Silymarin co-administration — silymarin (the standardized extract of milk thistle, see our Milk Thistle page) inhibits P-gp efflux. Berberine writing says that combining berberine with silymarin (approximately 100-200 mg silymarin per 500 mg berberine) approximately doubles berberine systemic exposure and produces clinically meaningful improvement in efficacy; no human pharmacokinetic trial with that figure was found. The pilot by Di Pierro et al. 2012 measured results, not exposure: 22 people with type 2 diabetes on oral drugs took two tablets a day of Berberis aristata extract plus milk thistle extract for 90 days, and hemoglobin A1c went from 8.0% to 7.15%.
- Piperine co-administration — piperine from black pepper inhibits cytochrome P450 3A4 (CYP3A4) first-pass metabolism. Less well-studied than silymarin in the berberine context but used in some commercial formulations.
- Phytosome / liposomal formulations — encapsulating berberine in phospholipid carriers improves absorption by 2-5× in pharmacokinetic studies. Several commercial products use this approach.
- Dihydroberberine — the reduced form of berberine (see next section).
Dihydroberberine — the Next-Generation Form
Dihydroberberine is the reduced (di-hydrogen-added) form of berberine. The reduction is reversible and occurs naturally in vivo by gut bacterial nitroreductase activity — dihydroberberine is actually one of the bacterially generated berberine metabolites in the human gut. Supplementing the reduced form directly has several pharmacokinetic advantages:
- Better intestinal absorption — dihydroberberine is often described as approximately 5× more bioavailable than berberine HCl. In a pilot crossover trial in five men (Moon 2021), plasma berberine exposure (area under the curve over 120 minutes) was 284.4 ng/mL after 100 mg of dihydroberberine and 42.3 ng/mL after 500 mg of berberine; Turner 2008 reported better results in high-fat-fed rodents. The added hydrogens reduce the quaternary nitrogen's interaction with P-gp efflux pumps.
- Re-oxidation to berberine in vivo — once absorbed, dihydroberberine is partly re-oxidized back to active berberine, providing sustained delivery.
- Lower dose requirement — the dihydroberberine dose described by sellers is 100-150 mg twice daily (versus 500 mg three times daily for standard berberine HCl), said to give similar clinical efficacy.
- Better gastrointestinal tolerability — the lower total dose reduces gastrointestinal side effects (constipation, abdominal cramping).
Dihydroberberine is now available as a commercial supplement (sold under trade names). Cost is somewhat higher per dose than standard berberine HCl; sellers point to the lower dose and better tolerability for people with sensitive gastrointestinal tracts. The clinical efficacy data for dihydroberberine is far smaller than for standard berberine HCl: in the five-man pilot above, glucose (p = 0.97) and insulin (p = 0.24) did not differ across conditions, which the authors put down to the short duration and the insulin-responsive volunteers, and they say efficacy studies are still to be done.
Prediabetes and Reversal of Insulin Resistance
Prediabetes — defined as hemoglobin A1c 5.7-6.4% or fasting glucose 100-125 mg/dL or 2-hour OGTT glucose 140-199 mg/dL — affects approximately 100 million American adults. Approximately 30% of prediabetics progress to overt type 2 diabetes within 5 years without intervention. The Diabetes Prevention Program established that intensive lifestyle change (7% weight loss + 150 minutes/week moderate exercise) reduces progression risk by approximately 58%, and metformin 850 mg twice daily reduces progression risk by approximately 31%.
Berberine has not been formally tested in a DPP-equivalent prediabetes prevention trial, but multiple smaller studies suggest it is at least as effective as metformin for progression prevention. The Yin trial enrolled people with diagnosed type 2 diabetes, not prediabetes; hemoglobin A1c ended at 7.5% and 7.3% in its two studies. Several Chinese studies in prediabetic populations have shown improved insulin sensitivity, reduced fasting glucose, and normalization of postprandial glucose excursions.
Practitioner protocols for prediabetes typically combine:
- Berberine HCl 500 mg three times daily with meals (or dihydroberberine 150 mg twice daily) — the cardiometabolic core
- Lifestyle modification including reduced refined carbohydrate, increased physical activity, and weight optimization
- Continuous glucose monitor (CGM) use to identify which foods and meals cause the largest individual glucose excursions and to confirm the intervention is working — see our CGM page
- Periodic hemoglobin A1c monitoring (every 3-6 months) and fasting insulin / homeostatic model assessment of insulin resistance (every 6-12 months)
For more on insulin resistance specifically, see our Insulin Resistance page.
Polycystic Ovary Syndrome (PCOS) Applications
Polycystic ovary syndrome affects 5-10% of reproductive-age women and is fundamentally an insulin-resistance disorder with downstream hyperandrogenic and ovulatory consequences. Metformin has been a mainstay of polycystic ovary syndrome therapy for decades, with documented benefit for menstrual regularity, ovulation, hirsutism, and metabolic parameters. Berberine has been studied as a metformin-equivalent in polycystic ovary syndrome with results that broadly parallel the type 2 diabetes findings.
The most informative polycystic ovary syndrome-specific trial is Wei et al. 2012 (European Journal of Endocrinology), which randomized 89 women with polycystic ovary syndrome and insulin resistance to one of three arms for 3 months: berberine 500 mg three times daily, metformin 1500 mg/day, or placebo. Every arm also took compound cyproterone acetate, a hormonal drug. The abstract reports:
- Homeostatic model assessment of insulin resistance and insulin levels: berberine lower than placebo (P<0.05); no metformin-versus-placebo result is given
- Waist-to-hip ratio: berberine outperformed metformin (greater reduction), P<0.01
- Lipid profile: berberine outperformed metformin (greater total cholesterol, triglyceride and low-density lipoprotein reduction, greater high-density lipoprotein increase; P<0.05)
- Total testosterone and free androgen index: the abstract gives no result for these; accounts of the trial say both active arms reduced them versus placebo
- SHBG (sex hormone binding globulin): higher on berberine than on metformin (P<0.05) and placebo (P<0.01), a change linked to reduced bioavailable androgen. The authors call for further controlled studies
A 2024 meta-analysis (Ha and Song) of 10 trials and 713 women found that berberine added to standard care raised ovulation rates (relative risk 1.41) and clinical pregnancy rates (relative risk 1.96), and the authors ask for further trials. Some practitioners now consider berberine a reasonable alternative to metformin for polycystic ovary syndrome, particularly for patients who do not tolerate metformin's gastrointestinal side effects or for whom the lipid benefit is clinically important.
Metabolic Syndrome and Non-Alcoholic Fatty Liver Disease Connection
Under the 2009 harmonized definition, metabolic syndrome is the simultaneous presence of three or more of five findings: central obesity, raised blood pressure, raised triglycerides, lowered high-density lipoprotein, and raised fasting glucose. Non-alcoholic fatty liver disease (NAFLD) is the hepatic manifestation of metabolic syndrome and is now the most common chronic liver disease in the developed world.
A 2025 pool of placebo-controlled trials (Liu) reports berberine lowering triglycerides by 0.367 mmol/L, waist circumference by 3.27 cm and 2-hour glucose by 1.606 mmol/L, with no significant effect on high-density lipoprotein or blood pressure, and no significant safety difference from placebo. Berberine's multi-target cardiometabolic profile touches several of the diagnostic components:
- Insulin resistance: AMP-activated protein kinase activation, homeostatic model assessment of insulin resistance improvement
- Glycemic control: hemoglobin A1c, fasting glucose, postprandial glucose
- Dyslipidemia: low-density lipoprotein receptor upregulation, triglyceride reduction
- Central obesity: modest but consistent weight reduction
- Non-alcoholic fatty liver disease: hepatic steatosis reduction (covered in detail on the Liver Health deep-dive)
- Inflammation: high-sensitivity C-reactive protein, interleukin-6, tumor necrosis factor-alpha reduction
Practitioner protocols for metabolic syndrome combine berberine (500 mg three times daily, or dihydroberberine 150 mg twice daily) with comprehensive lifestyle modification — carbohydrate restriction, increased physical activity, weight optimization, sleep optimization, and stress management. These practitioners describe berberine as a metabolic accelerant rather than a stand-alone therapy, used with lifestyle change rather than as a substitute for it.
Combining Berberine with Metformin or Other Antidiabetics
A common clinical question is whether berberine adds benefit when combined with metformin. The Yin paper's study B, which had no comparison group, showed a 0.8-point hemoglobin A1c reduction with berberine added to existing antidiabetic regimens. Subsequent meta-analyses confirm modest but real additive benefit when berberine is combined with metformin, sulfonylureas, or insulin.
The mechanism for the additive effect is not entirely clear — given that both berberine and metformin activate AMP-activated protein kinase through the same upstream mitochondrial complex I mechanism, one might predict redundancy rather than additivity. Possible explanations include:
- Berberine has AMP-activated protein kinase-independent glucose-lowering mechanisms (low-density lipoprotein receptor upregulation does not affect glucose, but the same berberine molecule may have other distinct effects, such as the insulin receptor route reported by Zhang et al. 2010)
- The dosing of metformin and berberine in real clinical practice often leaves AMP-activated protein kinase below saturation, leaving room for additional pharmacologic push
- The lipid effects of berberine are largely independent of metformin and add cardiovascular benefit even when glycemic effects are saturated
Some practitioners describe adding berberine 500 mg three times daily as a next step for people on metformin who have not reached hemoglobin A1c goal, often cheaper and better tolerated than escalating to a sulfonylurea or dipeptidyl peptidase-4 (DPP-4) inhibitor. Lan 2015 notes its relatively low cost compared with first-line medicines. Blood sugar can fall too low during the first 2-4 weeks of the combination, and insulin or sulfonylurea doses are sometimes lowered as the combination's full effect emerges.
Doses Used in Trials and by Practitioners
Standardized berberine HCl (the cardiometabolic protocol). The Yin trial used 500 mg three times daily, lowered to 300 mg three times daily when gut symptoms were heavy; the 2024 pooled analysis found 0.9-1.5 g a day for 1-3 months most common. Practitioner schedules build up to that dose:
- Starting dose: 500 mg with the largest meal of the day, for 1 week (allows gastrointestinal adaptation)
- Week 2: 500 mg twice daily with meals
- Week 3 onward: 500 mg three times daily with meals (total 1,500 mg/day)
- Practitioners give it with food, describing fewer gastrointestinal side effects and a cephalic-phase digestive bitter effect
- Practitioners describe onset of glycemic improvement within 2-4 weeks and full effect by 12 weeks; in the Yin trial, fasting and postprandial glucose fell from the first week
- These schedules include hemoglobin A1c tests every 3 months and fasting insulin every 6 months
Dihydroberberine.
- Sellers describe 100-150 mg twice daily with meals
- Said to match the glycemic effect of standard berberine HCl at much lower total dose; the five-man pilot above found no difference in glucose or insulin
- Described as better tolerated gastrointestinal-wise by people who could not tolerate standard berberine
Barberry tincture (mild adjunct dose).
- Herbalists describe 40-60 drops (2-3 mL) of 1:5 tincture in water, 15 minutes before each meal
- Provides bitter cephalic-phase effect plus modest berberine systemic delivery
- This delivers far less berberine than the diabetes trials used; herbalists use it as a prediabetes adjunct or for digestive symptoms
Combination considerations.
- Berberine + silymarin (200 mg silymarin per 500 mg berberine) — described as doubling bioavailability
- Berberine + alpha-lipoic acid (300-600 mg alpha-lipoic acid, ALA) — additive insulin-sensitizing effect
- Berberine + cinnamon (1-2 g Ceylon cinnamon) — complementary mechanisms (cinnamon affects insulin receptor activation)
- Berberine + magnesium (200-400 mg, glycinate or malate) — magnesium is depleted in insulin resistance and synergizes glycemic improvement
Cautions and Drug Interactions
- Pregnancy and breastfeeding (contraindicated) — berberine crosses the placenta and displaces bilirubin from albumin, risking kernicterus in newborns. The concern applies to both pregnancy and breastfeeding.
- Hypoglycemia in patients on multiple antidiabetics — berberine added to insulin, sulfonylureas, or meglitinides can produce hypoglycemia, and the doses of the existing antidiabetics are often lowered.
- Cytochrome P450 and P-gp inhibition — berberine inhibits cytochrome P450 3A4 and P-glycoprotein, with potential for significant interaction with cyclosporine, tacrolimus, statins (atorvastatin, simvastatin, lovastatin), and many other prescription drugs. In a crossover study in healthy men, 2 weeks of berberine 300 mg three times daily slowed three liver enzyme systems: CYP2D6 (urinary dextromethorphan ratio up ninefold), CYP2C9 (losartan ratio doubled) and CYP3A4 (midazolam exposure up about 40%). Many common drugs use these routes, and the authors state that drug interactions need to be considered.
- Gastrointestinal side effects — the most common adverse effect. Constipation in some patients, diarrhea in others, occasionally bitter or metallic taste. Practitioners describe splitting the dose, taking it with food, or stepping down the dose as typically resolving the symptom; in the Yin paper, symptoms in combination therapy disappeared within a week of lowering the dose. Dihydroberberine is described as an option for persistent intolerance.
- Anticoagulants — potential for warfarin potentiation, which shows up as a rising International Normalized Ratio (INR), the blood-thinning test.
- Hypotension — mild blood pressure reduction may augment antihypertensives.
- Long-term use — safety data on continuous berberine use beyond 12-24 months in humans is limited. Some practitioners describe periodic 2-4 week "drug holidays" every 6 months, which is empirical rather than evidence-based. The largest long trial gave 1,108 people berberine 0.3 g twice daily or placebo for up to 2 years after removal of bowel polyps, a lower dose than the 1,500 mg above. Adenomas came back in 36% versus 47%, no colorectal cancers were found, no serious adverse events were reported, and constipation was the most common side effect (1% versus under 0.5%). In follow-up lasting 6 years after treatment ended, recurrence stayed lower (34.7% versus 52.1%).
Key Research Papers
- Yin J, Xing H, Ye J (2008). Efficacy of berberine in patients with type 2 diabetes mellitus. Metabolism. — PubMed PMID: 18442638
- Kong W et al. (2004). Berberine is a novel cholesterol-lowering drug working through a unique mechanism distinct from statins. Nature Medicine. — PubMed PMID: 15531889
- Lee YS et al. (2006). Berberine, a natural plant product, activates AMP-activated protein kinase with beneficial metabolic effects in diabetic and insulin-resistant states. Diabetes. — the foundational AMPK mechanism paper. PubMed PMID: 16873688
- Dong H et al. (2012). Berberine in the treatment of type 2 diabetes mellitus: A systemic review and meta-analysis. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 23118793
- Lan J et al. (2015). Meta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension. Journal of Ethnopharmacology. — PubMed PMID: 25498346
- Liang Y et al. (2019). Effects of berberine on blood glucose in patients with type 2 diabetes mellitus: a systematic literature review and a meta-analysis. Endocrine Journal. — PubMed PMID: 30393248
- Wei W et al. (2012). A clinical study on the short-term effect of berberine in comparison to metformin on the metabolic characteristics of women with polycystic ovary syndrome. European Journal of Endocrinology. — PubMed PMID: 22019891
- Pirillo A, Catapano AL (2015). Berberine, a plant alkaloid with lipid- and glucose-lowering properties: From in vitro evidence to clinical studies. Atherosclerosis. — comprehensive lipid mechanism review. PubMed PMID: 26520899
- Cicero AFG, Baggioni A (2016). Berberine and its role in chronic disease. Advances in Experimental Medicine and Biology. — comprehensive cardiometabolic review. PubMed PMID: 27671811
- Zhang H et al. (2010). Berberine lowers blood glucose in type 2 diabetes mellitus patients through increasing insulin receptor expression. Metabolism. — insulin receptor mechanism. PubMed PMID: 19800084
- Di Pierro F et al. (2012). Pilot study on the additive effects of berberine and oral type 2 diabetes agents for patients with suboptimal glycemic control. Diabetes, Metabolic Syndrome and Obesity. — the silymarin co-administration / add-on study. PubMed PMID: 22924000
- Turner N et al. (2008). Berberine and its more biologically available derivative, dihydroberberine, inhibit mitochondrial respiratory complex I. Diabetes. — the dihydroberberine bioavailability foundation. PubMed PMID: 18285556
- Xie W, Su F, Wang G, Peng Z, Xu Y, Zhang Y, Xu N, Hou K, Hu Z, Chen Y, Chen R (2022). Glucose-lowering effect of berberine on type 2 diabetes: A systematic review and meta-analysis. Frontiers in Pharmacology. — PubMed PMID: 36467075
- Wang J, Bi C, Xi H, Wei F (2024). Effects of administering berberine alone or in combination on type 2 diabetes mellitus: a systematic review and meta-analysis. Frontiers in Pharmacology. — PubMed PMID: 39640489
- Elahi Vahed I et al. (2026). The effect of berberine on obesity indices: a systematic review and meta-analysis. International Journal of Obesity. — PubMed PMID: 41310257
- Moon JM, Ratliff KM, Hagele AM, Stecker RA, Mumford PW, Kerksick CM (2021). Absorption Kinetics of Berberine and Dihydroberberine and Their Impact on Glycemia: A Randomized, Controlled, Crossover Pilot Trial. Nutrients. — PubMed PMID: 35010998
- Ha S, Song X (2024). Berberine as adjuvant therapy for treating reduced fertility potential in women with polycystic ovary syndrome: A meta-analysis of randomized controlled trials. Explore. — PubMed PMID: 39236662
- Alberti KG et al. (2009). Harmonizing the metabolic syndrome: a joint interim statement of the International Diabetes Federation Task Force on Epidemiology and Prevention; National Heart, Lung, and Blood Institute; American Heart Association; World Heart Federation; International Atherosclerosis Society; and International Association for the Study of Obesity. Circulation. — PubMed PMID: 19805654
- Liu D, Zhao H, Zhang Y, Hu J, Xu H (2025). Efficacy and safety of berberine on the components of metabolic syndrome: a systematic review and meta-analysis of randomized placebo-controlled trials. Frontiers in Pharmacology. — PubMed PMID: 40740996
- Guo Y, Chen Y, Tan ZR, Klaassen CD, Zhou HH (2012). Repeated administration of berberine inhibits cytochromes P450 in humans. European Journal of Clinical Pharmacology. — PubMed PMID: 21870106
- Chen YX et al. (2020). Berberine versus placebo for the prevention of recurrence of colorectal adenoma: a multicentre, double-blinded, randomised controlled study. The Lancet Gastroenterology & Hepatology. — PubMed PMID: 31926918
- Tan YJ et al. (2025). Berberine for preventing colorectal adenoma recurrence and neoplasm occurrence: 6-Year follow-up of a randomized clinical trial. Cell Reports Medicine. — PubMed PMID: 40795846
PubMed Topic Searches
Connections
- All Herbs
- Barberry Overview
- Barberry Benefits Hub
- Barberry for Antimicrobial Action
- Barberry for Liver Health
- Barberry as a Digestive Aid
- Berberine (Standardized Supplement)
- Berberine Benefits Deep Dive
- Milk Thistle (Silymarin Bioavailability Booster)
- Diabetes
- Insulin Resistance
- Metformin, Berberine, and Glucagon-Like Peptide-1 Receptor Agonists
- Polycystic Ovary Syndrome
- Blood Sugar
- Continuous Glucose Monitor (CGM)
- Hemoglobin A1C
- Magnesium
- Metformin — the biguanide that shares the same complex I and AMP-activated protein kinase mechanism as berberine and served as the comparator arm in the Yin 2008 trial.
- History