⚠ Evidence warning: Clinical trials or other evidence do not support the claims that standard berberine usually achieves the target effect and that lower-dose dihydroberberine is a reasonable second-line trial. This page keeps it as a report of what people, websites or other media say.
Berberine — Benefits Deep Dive
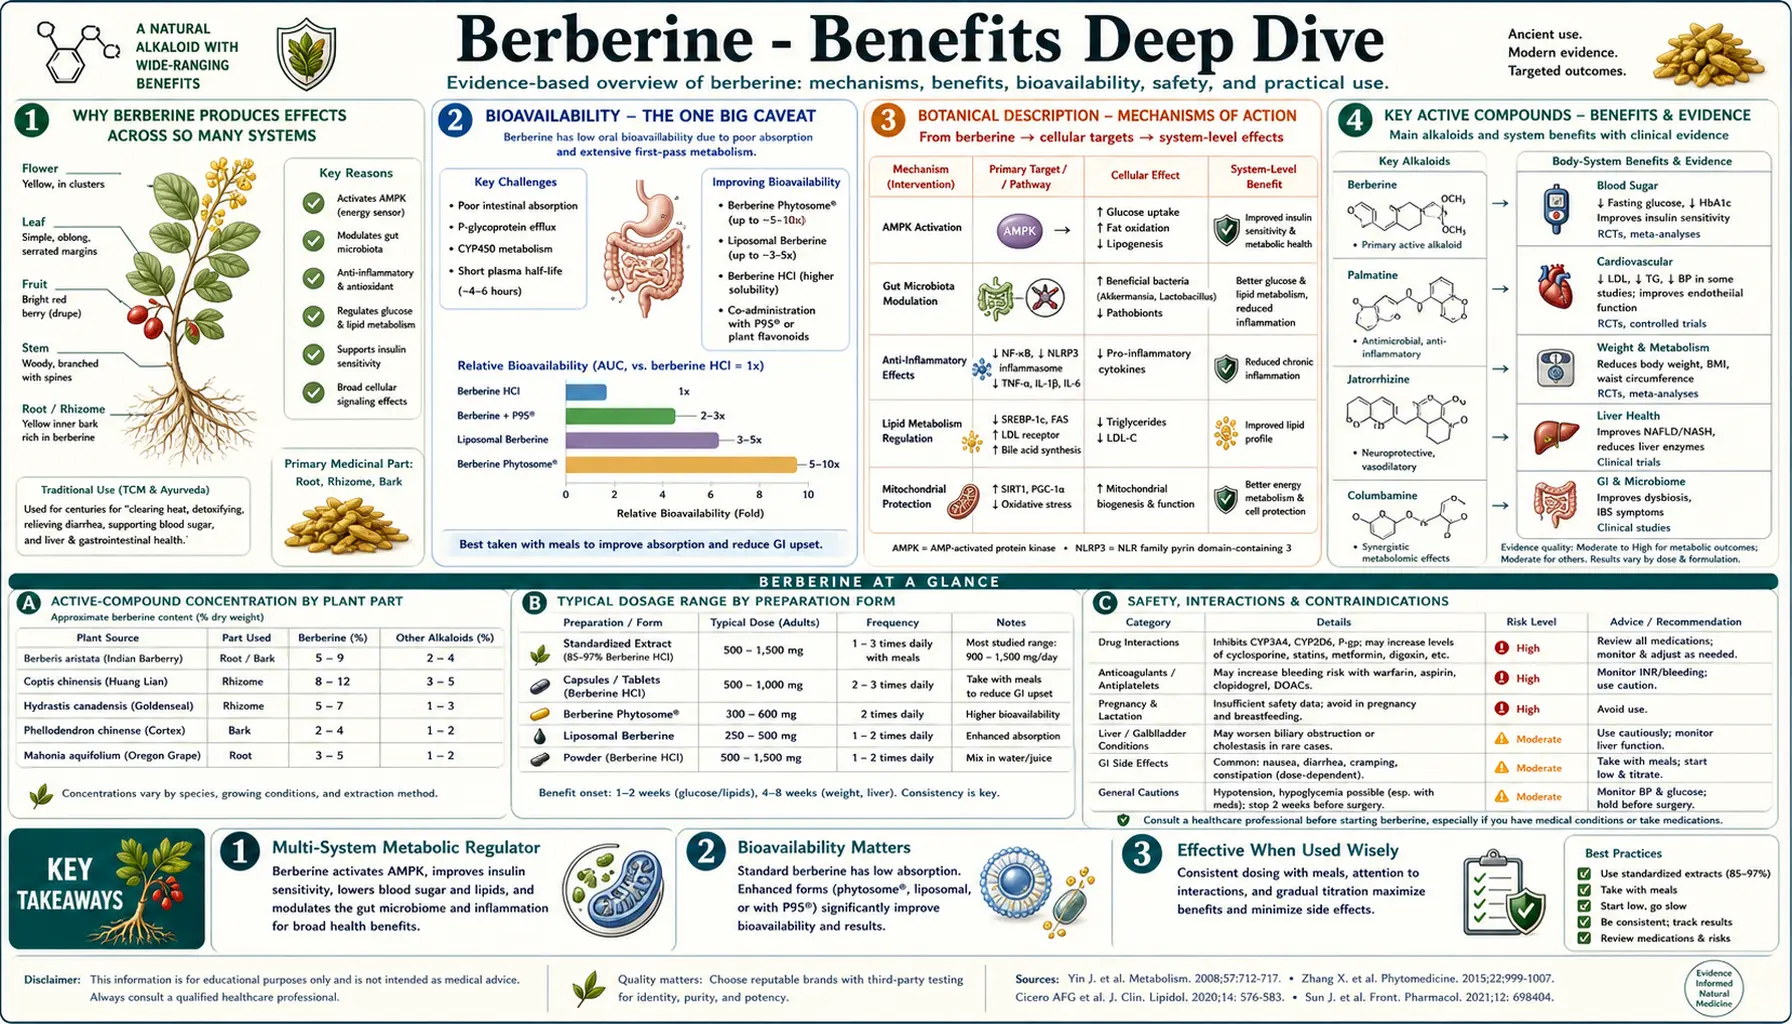
Berberine is a yellow isoquinoline alkaloid extracted from the roots, rhizomes, and bark of several botanically unrelated plants — Coptis chinensis (Chinese goldthread), Phellodendron amurense (Amur cork tree), Berberis species (barberry, Oregon grape), and the rhizomes of Hydrastis canadensis (goldenseal). It has been used for two millennia in Traditional Chinese Medicine and Ayurveda, and over the last two decades laboratory and clinical research has studied how it works, although the 2012 and 2015 meta-analyses of its diabetes trials rated the quality of most of those trials as low or limited (Dong 2012, Lan 2015). The mechanistic story converges on a single molecular target: AMP-activated protein kinase (AMPK), the cellular "metabolic master switch" that also happens to be the principal target of the diabetes drug metformin. In the 2008 Yin pilot trial (36 adults with newly diagnosed type 2 diabetes, 3 months), berberine 500 mg three times daily lowered hemoglobin A1c (HbA1c) from 9.5% to 7.5%, and the authors described its blood-sugar effect as similar to that of metformin at the same dose — one source of berberine the popular name "nature's metformin." Four benefit pages below explore the clinical domains where berberine produces its largest, best-documented effects: glycemic control, lipid metabolism, gastrointestinal infection and dysbiosis, and the broader metabolic syndrome cluster that ties them all together through AMP-activated protein kinase activation.
Deep-Dive Articles
Blood Sugar & Glycemic Control
The Yin 2008 head-to-head pilot trial vs metformin (hemoglobin A1c fell from 9.5% to 7.5% on berberine, an effect the authors called similar to metformin's), the Lan 2015 and Dong 2012 meta-analyses pooling over 25 trials, AMP-activated protein kinase activation as the shared mechanism with metformin, the "nature's metformin" framing, the dosing used in trials (500 mg three times daily with meals), gastrointestinal (GI) side effects (transient diarrhea, cramping; 34.5% of patients in Yin 2008 had transient digestive effects) and what is reported to reduce them, and how berberine has been studied both on its own and added to other diabetes treatment.
Read the deep dive →Cholesterol & Lipid Metabolism
The Kong 2004 Nature Medicine paper that established low-density lipoprotein-receptor upregulation as the lipid mechanism (in 32 patients treated for 3 months, low-density lipoprotein (LDL) cholesterol fell 25% and total cholesterol 29%), the dual AMPK + LDLR pathway that differs from the HMG-CoA-reductase inhibition of statins, the favorable effect on triglycerides and high-density lipoprotein (HDL), comparative efficacy data vs statins, research on berberine in people who cannot take statins, and studies of berberine combined with a low-dose statin.
Read the deep dive →Gut Health, Small Intestinal Bacterial Overgrowth & Dysbiosis
The Chedid 2014 clinic study in which patients with small intestinal bacterial overgrowth (SIBO) were offered either rifaximin or herbal antimicrobials (including berberine) — the follow-up breath test was negative in 46% on herbs vs 34% on rifaximin (P=.24), which the authors read as herbs being at least as effective, while calling for prospective studies — the broad-spectrum antimicrobial activity against bacteria, yeast, and protozoa, the C. difficile pilot data, dysbiosis-rotation protocols, the historical use for bacterial diarrhea and dysentery, and the practical microbial-modulation framework that distinguishes berberine from antibiotic monotherapy.
Read the deep dive →AMP-Activated Protein Kinase & Metabolic Syndrome
AMP-activated protein kinase as the cellular "master switch" sensing low energy (high AMP:ATP ratio) and orchestrating glucose uptake, fatty acid oxidation, mitochondrial biogenesis, and autophagy. The Wei 2012 polycystic ovary syndrome (PCOS) trial (89 women, 3 months) showing lower insulin resistance, waist-to-hip ratio and blood lipids (it reported metabolic and hormonal results, not ovulation or pregnancy), application to non-alcoholic fatty liver disease (NAFLD), waist circumference and visceral adiposity, the unifying mechanism behind berberine's simultaneous effect on glucose, lipids, weight, and inflammation.
Read the deep dive →Table of Contents
- Deep-Dive Articles
- Why Berberine Produces Effects Across So Many Systems
- Bioavailability — The One Big Caveat
- Berberine and Colorectal Polyp Recurrence
- Research Papers: Glycemic Control
- Research Papers: Lipids & Cardiovascular
- Research Papers: Gut, Small Intestinal Bacterial Overgrowth & Antimicrobial
- Research Papers: AMP-Activated Protein Kinase & Metabolic Syndrome
- Research Papers: Cross-Cutting (Mechanism, Safety, Forms)
- External Authoritative Resources
- Connections
- Featured Videos
Why Berberine Produces Effects Across So Many Systems
Berberine is unusual among natural products because its diverse clinical effects — on blood sugar, lipids, gut microbes, body weight, blood pressure, hepatic steatosis, and polycystic ovary syndrome — all trace back to a small number of molecular targets that happen to sit at metabolic chokepoints. Five mechanisms account for essentially the entire pharmacology:
- AMP-activated protein kinase activation — berberine activates AMP-activated protein kinase, the cellular fuel sensor that turns on when energy is low. AMP-activated protein kinase in turn increases glucose uptake, switches mitochondria from fatty-acid synthesis to fatty-acid oxidation, stimulates mitochondrial biogenesis, and triggers autophagy. This is the same target as the diabetes drug metformin, which is one explanation offered for the similar hemoglobin A1c results of berberine and metformin in the 2008 Yin trial. AMP-activated protein kinase activation explains the glycemic effect and most of the broader metabolic-syndrome cluster.
- Low-density lipoprotein-receptor upregulation — the 2004 Kong paper in Nature Medicine showed that berberine stabilizes hepatic low-density lipoprotein-receptor mRNA, dramatically increasing the number of low-density lipoprotein receptors on the surface of hepatocytes and pulling low-density lipoprotein particles out of circulation. This mechanism is different from statins (which inhibit HMG-CoA reductase to reduce hepatic cholesterol synthesis) and explains the additive lipid-lowering when the two are combined — see the cholesterol deep-dive.
- Broad-spectrum antimicrobial activity — berberine has direct activity against many bacteria (Gram-positive and Gram-negative), yeasts (particularly Candida), and protozoa (Giardia, Entamoeba). The mechanism appears to involve DNA intercalation, FtsZ ring inhibition (preventing bacterial cell division), and efflux-pump inhibition. This explains the historical use for bacterial diarrhea and dysentery and the modern role in small intestinal bacterial overgrowth and dysbiosis management.
- GLUT4 translocation — independent of AMP-activated protein kinase, berberine appears to directly increase translocation of the insulin-responsive glucose transporter GLUT4 from intracellular vesicles to the plasma membrane of muscle and adipose cells. This is the same translocation event that insulin triggers, and it explains why berberine improves insulin sensitivity in the absence of significant changes in fasting insulin levels.
- Dipeptidyl peptidase-4 (DPP-4) inhibition — berberine has measurable inhibitory activity against dipeptidyl peptidase-4, the enzyme that degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and GIP. This is the same target as the gliptin class of diabetes drugs (sitagliptin, linagliptin, saxagliptin). The dipeptidyl peptidase-4 inhibition is modest compared to prescription gliptins but contributes additively to the post-prandial glucose-lowering effect.
The convergence of five mechanisms on overlapping pathways — glucose uptake, lipid metabolism, microbial ecology, energy sensing — explains why berberine is one of the most-studied herbal compounds of the past two decades. A PubMed search for "berberine" returned 10,457 records on 31 October 2026, 4,879 of them dated 2020 or later.
Bioavailability — The One Big Caveat
The single most important practical limitation of berberine is its extraordinarily poor oral bioavailability — the most widely quoted figure comes from rats, in which a 2011 study measured an absolute oral bioavailability of 0.68% (Chen 2011). The molecule is poorly absorbed across the intestinal epithelium, and what does get absorbed is rapidly subject to P-glycoprotein efflux back into the gut lumen, then hepatic first-pass metabolism through cytochrome P450 enzymes (especially cytochrome P450 2D6 (CYP2D6) and cytochrome P450 3A4 (CYP3A4)) into a variety of demethylated metabolites.
The paradox is that despite such low absorption, oral berberine produces clinically meaningful systemic effects on blood glucose, lipids, and inflammation. Three explanations have emerged:
- Active metabolites — the demethylated metabolites (berberrubine, demethyleneberberine, jatrorrhizine, thalifendine) retain significant pharmacologic activity and circulate at higher concentrations than the parent compound.
- Gut-luminal effect — the large share that is not absorbed remains in the gut at locally pharmacologic concentrations, where it exerts antimicrobial effects on the gut microbiome and directly stimulates the gut epithelium (including L-cells that secrete glucagon-like peptide-1). The gut-microbiome modulation alone is now thought to account for a meaningful fraction of berberine's metabolic effects, even before any systemic absorption.
- Enterohepatic recirculation — the small fraction that is absorbed is excreted in bile back into the gut and partially re-absorbed, extending the effective duration of action.
Two formulation approaches address bioavailability directly:
- Dihydroberberine — a reduced form of berberine. In high-fat-fed rodents it countered increased body fat, fat build-up in tissues and insulin resistance better than berberine itself, which the researchers put down to better absorption (Turner 2008). The human data so far come from one small pilot: five young men took four doses each of placebo, 500 mg berberine, 100 mg dihydroberberine and 200 mg dihydroberberine in turn (randomized, double-blind crossover). Blood berberine over two hours (area under the curve) was 284.4 ng/mL × 120 min after 100 mg dihydroberberine against 42.3 after 500 mg berberine, but glucose and insulin did not differ between the doses; the authors call for longer efficacy studies in overweight, glucose-intolerant people, and one author disclosed being a paid advisor to a supplement-industry company (Moon 2021). Commercial dihydroberberine ingredients are marketed as allowing lower per-dose amounts than standard berberine 500 mg.
- Sodium caprate / piperine combinations — absorption enhancers that inhibit P-glycoprotein efflux and increase tight-junction permeability. Several commercial products combine berberine with sodium caprate or with piperine (the black-pepper alkaloid used in turmeric formulations for the same purpose).
The blood-sugar trials described here, such as Yin 2008, used standard berberine, 500 mg three times daily with meals. The enhanced forms cost more, and their human evidence so far is the five-person pilot above, which measured blood levels rather than a lasting effect on blood sugar. The clinical guidance is straightforward: if standard berberine 500 mg three times daily with meals achieves the target effect (which it usually does, based on the trial evidence), there is no need for the more expensive enhanced forms. If the response is inadequate or gastrointestinal tolerance is poor at the standard dose, dihydroberberine at a lower per-dose amount is a reasonable second-line trial. For more on dosing, see the main Berberine page.
Berberine and Colorectal Polyp Recurrence
Colorectal adenomas are growths (polyps) in the large bowel that can turn into cancer, and they often come back after they are removed. A Chinese randomized trial gave berberine or a comparison treatment for 2 years to people who had had adenomas removed. A 2025 follow-up study tracked the people who finished that trial for up to 6 years after the pills were stopped: 648 of them had at least one more colonoscopy. Adenomas came back in 34.7% of the berberine group against 52.1% of the comparison group, and any new growth (neoplasm) was found in 63.4% against 71.0%. The authors conclude that the protective effect lasted at least 6 years after treatment ended and that berberine may serve as a long-term preventive agent after polyp removal. The follow-up was a retrospective cohort study, and its authors declared no competing interests (Tan 2025).
Research Papers: Glycemic Control
- Yin J, Xing H, Ye J (2008). Efficacy of berberine in patients with type 2 diabetes mellitus. Metabolism;57(5):712-717. — PubMed PMID: 18442638
- Lan J, Zhao Y, Dong F, Yan Z, Zheng W, Fan J, Sun G (2015). Meta-analysis of the effect and safety of berberine in the treatment of type 2 diabetes mellitus, hyperlipemia and hypertension. Journal of Ethnopharmacology;161:69-81. — PubMed PMID: 25498346
- Dong H, Wang N, Zhao L, Lu F (2012). Berberine in the treatment of type 2 diabetes mellitus: a systemic review and meta-analysis. Evidence-Based Complementary and Alternative Medicine;2012:591654. — PubMed PMID: 23118793
- Zhang Y, Li X, Zou D, et al. (2008). Treatment of type 2 diabetes and dyslipidemia with the natural plant alkaloid berberine. Journal of Clinical Endocrinology and Metabolism;93(7):2559-2565. — PubMed PMID: 18397984
- Berberine AMPK activation mechanism — PubMed: Berberine AMPK
- Berberine GLUT4 translocation mechanism — PubMed: Berberine GLUT4
- Berberine vs metformin head-to-head comparisons — PubMed: Berberine vs metformin
- Berberine for prediabetes / impaired glucose tolerance — PubMed: Berberine prediabetes
- Berberine DPP-4 inhibition activity — PubMed: Berberine DPP-4
- Berberine and insulin sensitivity in skeletal muscle — PubMed: Berberine insulin sensitivity
Research Papers: Lipids & Cardiovascular
- Kong W, Wei J, Abidi P, et al. (2004). Berberine is a novel cholesterol-lowering drug working through a unique mechanism distinct from statins. Nature Medicine;10(12):1344-1351. — PubMed PMID: 15531889
- Berberine LDL-receptor upregulation hepatocyte mechanism — PubMed: Berberine LDLR mRNA
- Berberine plus statin combination therapy — PubMed: Berberine plus statin
- Berberine for statin-intolerant patients — PubMed: Berberine for statin-intolerant
- Berberine effect on triglycerides — PubMed: Berberine triglycerides
- Berberine effect on HDL cholesterol — PubMed: Berberine HDL
- Berberine and atherosclerosis progression — PubMed: Berberine atherosclerosis
- Berberine and PCSK9 / LDL clearance pathway — PubMed: Berberine PCSK9
- Berberine blood pressure modulation — PubMed: Berberine blood pressure
- Berberine meta-analysis lipid endpoints — PubMed: Berberine lipid meta-analysis
Research Papers: Gut, Small Intestinal Bacterial Overgrowth & Antimicrobial
- Chedid V, Dhalla S, Clarke JO, et al. (2014). Herbal therapy is equivalent to rifaximin for the treatment of small intestinal bacterial overgrowth. Global Advances in Health and Medicine;3(3):16-24. — PubMed PMID: 24891990
- Tan YJ, Zou TH, Yu K, et al. (2025). Berberine for preventing colorectal adenoma recurrence and neoplasm occurrence: 6-Year follow-up of a randomized clinical trial. Cell Reports Medicine;6(9):102293. — PubMed PMID: 40795846
- Berberine for Clostridium difficile infection — PubMed: Berberine C. difficile
- Berberine antimicrobial spectrum Gram-positive Gram-negative — PubMed: Berberine antimicrobial spectrum
- Berberine for bacterial diarrhea historical clinical trials — PubMed: Berberine bacterial diarrhea
- Berberine and the gut microbiome / dysbiosis modulation — PubMed: Berberine gut microbiome
- Berberine FtsZ inhibition bacterial cell division — PubMed: Berberine FtsZ
- Berberine efflux pump inhibition resistance reversal — PubMed: Berberine efflux pump
- Berberine for Helicobacter pylori — PubMed: Berberine H. pylori
- Berberine for Candida and antifungal activity — PubMed: Berberine antifungal
- Berberine for Giardia and protozoal diarrhea — PubMed: Berberine protozoal
Research Papers: AMP-Activated Protein Kinase & Metabolic Syndrome
- Wei W, Zhao H, Wang A, et al. (2012). A clinical study on the short-term effect of berberine in comparison to metformin on the metabolic characteristics of women with polycystic ovary syndrome. European Journal of Endocrinology;166(1):99-105. — PubMed PMID: 22019891
- Berberine AMPK master switch energy sensor mechanism — PubMed: Berberine AMPK master switch
- Berberine for non-alcoholic fatty liver disease (NAFLD) — PubMed: Berberine NAFLD
- Berberine for PCOS ovulation and reproductive outcomes — PubMed: Berberine PCOS reproductive
- Berberine and visceral adipose / waist circumference — PubMed: Berberine visceral fat
- Berberine and metabolic syndrome cluster outcomes — PubMed: Berberine metabolic syndrome
- AMPK mitochondrial biogenesis fatty acid oxidation — PubMed: AMPK mitochondrial biogenesis
- Berberine autophagy mTOR pathway — PubMed: Berberine autophagy mTOR
- Berberine and inflammation NF-kappaB pathway — PubMed: Berberine NF-kB
- Berberine weight loss / body composition trials — PubMed: Berberine weight loss
Research Papers: Cross-Cutting (Mechanism, Safety, Forms)
- Chen W, Miao YQ, Fan DJ, et al. (2011). Bioavailability study of berberine and the enhancing effects of TPGS on intestinal absorption in rats. AAPS PharmSciTech;12(2):705-711. — PubMed PMID: 21637946
- Turner N, Li JY, Gosby A, et al. (2008). Berberine and its more biologically available derivative, dihydroberberine, inhibit mitochondrial respiratory complex I: a mechanism for the action of berberine to activate AMP-activated protein kinase and improve insulin action. Diabetes;57(5):1414-1418. — PubMed PMID: 18285556
- Moon JM, Ratliff KM, Hagele AM, et al. (2021). Absorption Kinetics of Berberine and Dihydroberberine and Their Impact on Glycemia: A Randomized, Controlled, Crossover Pilot Trial. Nutrients;14(1):124. — PubMed PMID: 35010998
- Berberine bioavailability oral absorption pharmacokinetics — PubMed: Berberine bioavailability
- Dihydroberberine enhanced bioavailability — PubMed: Dihydroberberine
- Berberine plus sodium caprate absorption enhancer — PubMed: Berberine + sodium caprate
- Berberine CYP3A4 CYP2D6 drug interactions — PubMed: Berberine CYP interactions
- Berberine safety profile and adverse effects review — PubMed: Berberine safety
- Berberine pregnancy contraindication kernicterus risk — PubMed: Berberine pregnancy caution
- Berberine source plants Coptis Phellodendron Berberis — PubMed: Berberine source plants
- Berberrubine and active metabolites pharmacology — PubMed: Berberine metabolites
- Berberine isoquinoline alkaloid chemistry — PubMed: Berberine chemistry
- Berberine network pharmacology multi-target review — PubMed: Berberine multi-target
External Authoritative Resources
- U.S. National Center for Complementary and Integrative Health (NCCIH) (U.S. National Institutes of Health, NIH) — Berberine and Weight Loss: What You Need To Know — the U.S. government's consumer-facing summary of evidence and safety
- MedlinePlus — Berberine — National Library of Medicine drug-and-supplement information
- Examine.com — Berberine
- Linus Pauling Institute — Micronutrient Information Center — for related metabolic-syndrome and antioxidant micronutrient context
- PubMed — All berberine research (10,457 records on 31 October 2026)
Connections
- All Herbs
- Berberine Benefits Deep Dive (Remedies) — a parallel benefits hub for the same compound in the Remedies tree, with its own four sub-articles on blood sugar and insulin sensitivity, cholesterol, the gut microbiome, and dosing, forms and cautions.
- Berberine (Main Page)
- Berberine for Blood Sugar
- Berberine for Cholesterol
- Berberine for Gut Health & Small Intestinal Bacterial Overgrowth
- Berberine, AMP-Activated Protein Kinase & Metabolic Syndrome
- Barberry (Berberine Source)
- Goldenseal (Berberine Source)
- Bitter Melon
- Gymnema
- Cinnamon
- Hemoglobin A1C
- Fasting Insulin
- Lipid Panel
- Diabetes
- Insulin Resistance
- Metabolic Syndrome
- Polycystic Ovary Syndrome
- Small Intestinal Bacterial Overgrowth
- Non-Alcoholic Fatty Liver Disease
- Atherosclerosis
- Blood Sugar
- Gut Healing
- Inositol
- History