Ginseng for Immune and Antiviral Function
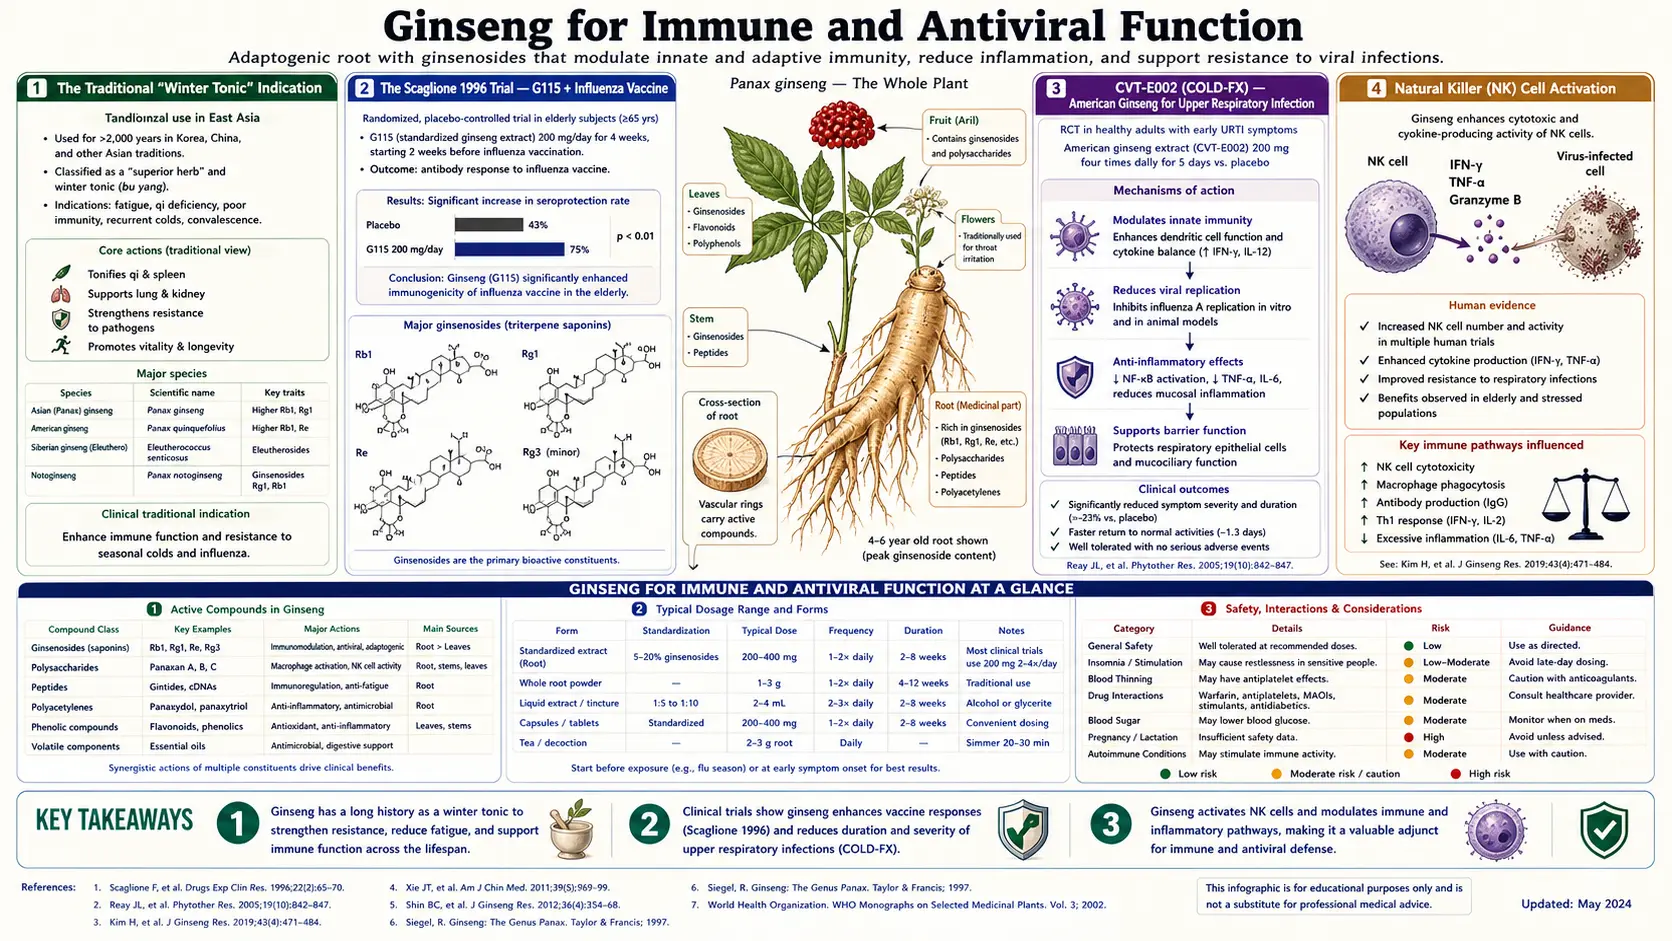
Ginseng's immune-supporting reputation in traditional medicine has been confirmed by an unusually well-designed clinical trial. The Scaglione 1996 study randomized 227 volunteers to either a standardized Asian ginseng (Panax ginseng) extract (100 mg daily for 12 weeks) or matching placebo, with all subjects receiving a polyvalent influenza vaccine at week 4. Between weeks 4 and 12 there were 15 cases of influenza or common cold among the 114 people taking ginseng versus 42 cases among the 113 taking placebo, and average antibody titers at week 8 were 272 units versus 171 units. A separate line of research on a standardized North American ginseng extract (CVT-E002), begun at the University of Alberta, found fewer respiratory infections in older adults in long-term care and in community-dwelling adults, although later trials found no difference on their main outcomes (see below). The mechanism centers on enhanced natural killer (NK) cell cytotoxicity, increased macrophage and dendritic cell activation, and an adjuvant-like effect on antibody-class switching in B cells — the same broad immune-modulating effects that explain ginseng's traditional use as a "winter tonic" in cold climates.
Table of Contents
- The Traditional "Winter Tonic" Indication
- The Scaglione 1996 Trial — a Standardized Asian Ginseng Extract and Influenza Vaccine
- CVT-E002, a Standardized North American Ginseng Extract, for Upper Respiratory Infection
- Natural Killer (NK) Cell Activation
- Macrophage and Dendritic Cell Activation
- Antibody Class-Switching and Vaccine Adjuvant Effect
- Polysaccharides vs Ginsenosides — Two Active Fractions
- Elderly Immune Decline (Immunosenescence)
- Dosing and Timing for Immune Use
- Cautions, Limitations, and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
The Traditional "Winter Tonic" Indication
The traditional Chinese and Korean medical use of ginseng for "preventing colds" and "supporting recovery from prolonged illness" predates any concept of viruses or immune cells by roughly two thousand years. The empirical observation was that people who took ginseng regularly tended to get fewer respiratory illnesses each winter, recovered faster from those they did catch, and convalesced from major illness with more vigor. The classical Chinese pharmacology categorized this as ginseng's effect of "tonifying lung qi and protecting wei qi" (defensive qi, roughly equivalent to the modern concept of innate immunity).
Modern immunology has largely vindicated the traditional claim, though with the caveat that "regularly" is doing important work in the description — ginseng's immune effects accumulate over weeks of dosing and are not particularly impressive in single-dose form. The classical "winter tonic" use, where someone begins taking ginseng in early autumn and continues through winter, maps closely to the most successful modern clinical trials, which use 4-12 weeks of pre-exposure dosing before evaluating infection rates.
The relevance of ginseng to acute infectious disease (taking ginseng once a cold has already started) is less well-supported by the literature. Like vitamin C, ginseng appears more useful for prevention than for treatment of established viral illness.
The Scaglione 1996 Trial — a Standardized Asian Ginseng Extract and Influenza Vaccine
The single most important clinical demonstration of ginseng's immune effect is the Scaglione 1996 trial, led from the University of Milan’s Department of Pharmacology, run in 3 private practices in Milan and published in the journal Drugs Under Experimental and Clinical Research. The trial enrolled 227 healthy adults (mean age 49) during the autumn influenza season and randomized them to either:
- A standardized Asian ginseng (Panax ginseng) extract, 100 mg daily for 12 weeks
- Identical-appearing placebo
All subjects received a polyvalent (3-strain) influenza vaccine at week 4. The trial measured (1) confirmed influenza or common-cold incidence over the 12-week period, (2) post-vaccination antibody titers to the included influenza strains, and (3) natural killer cell activity in a subset.
Results:
- Influenza/cold incidence: between weeks 4 and 12, 15 cases among the 114 people in the ginseng arm vs 42 cases among the 113 people on placebo (statistically significant, p < 0.001)
- Antibody titers: by week 8, average antibody titers rose to 272 units in the ginseng arm vs 171 units on placebo (p < 0.0001)
- Natural killer cell activity: nearly twice as high in the ginseng arm as on placebo at weeks 8 and 12 (p < 0.0001)
- Tolerability: 24 laboratory safety values showed no significant change in either group; there were only 9 adverse events in the whole study, the main one being insomnia
The Scaglione trial is widely cited as the strongest single demonstration of an herbal supplement potentiating vaccine response in healthy adults. This single 1996 trial has not been independently repeated at this size, but the consistent direction of effect across the various downstream measures (clinical infection rate, antibody titer, natural killer cell activity) gives the result internal coherence beyond a single endpoint.
The standardized Asian ginseng extract used in the trial is a Panax ginseng (Korean / Asian) extract standardized to 4% total ginsenosides — specifically, a defined ratio of Rg1, Rb1, and other ginsenosides developed and patented in the 1970s. It is the same extract used in the Reay cognitive trials, in the Caso Marasco 1996 trial (625 people, which compared a multivitamin plus the ginseng extract with the multivitamin alone for 12 weeks and found a larger gain on an 11-item quality-of-life questionnaire, 11.9 vs 6.4 points), and in many other modern ginseng studies.
CVT-E002, a Standardized North American Ginseng Extract, for Upper Respiratory Infection
A parallel line of research on American ginseng (Panax quinquefolius) was conducted at the University of Alberta starting in the late 1990s. The team isolated a poly-saccharide-rich fraction of American ginseng root, designated CVT-E002, which was later sold commercially. Multiple randomized trials evaluated this preparation in different populations:
- McElhaney 2004 (institutionalized elderly): two trials in long-term care (nursing home and assisted living, at three sites) with 89 and 109 residents (average age 81 and 83.5), randomized to CVT-E002 200 mg twice daily or placebo for 8 or 12 weeks. Laboratory-confirmed influenza: 7 of 101 on placebo vs 1 of 97 on CVT-E002 (P = .033); influenza plus respiratory syncytial virus illness: 9 of 101 vs 1 of 97 (P = .009), which the authors describe as an 89% relative risk reduction.
- Predy 2005 (community-dwelling adults): 323 adults (mean age 43) randomized to CVT-E002 400 mg/day or placebo for 4 months during influenza season. Of the 279 who started treatment (130 vs 149), the CVT-E002 arm had 0.68 colds per person vs 0.93 on placebo; 10.0% vs 22.8% had 2 or more colds, and cold symptoms lasted 10.8 vs 16.5 days in total.
- McElhaney 2011 (influenza-vaccinated community-dwelling adults): a larger trial of 783 adults randomized to placebo, 400 mg or 800 mg a day for 6 months. Laboratory-confirmed upper respiratory infections, the main outcome, did not differ (5.5%, 5.2% and 4.6%; P = 0.89); infections defined by symptom criteria (Jackson criteria) were fewer, milder and shorter in the treated groups, and the authors call for a larger trial.
The CVT-E002 (American ginseng polysaccharide) and standardized Asian ginseng extract (Korean ginseng, standardized for ginsenosides) lines of research suggest that two distinct fractions of ginseng can each independently support immune function: the polysaccharide fraction (more prominent in American ginseng, particularly the CVT-E002 preparation) and the ginsenoside fraction (more prominent in Korean Panax ginseng standardized extracts). This is biologically reasonable since polysaccharides and triterpene saponins activate different innate immune pathways — polysaccharides predominantly through pattern-recognition receptors on macrophages and dendritic cells, ginsenosides through more diverse downstream signaling.
In the US, CVT-E002 is sold as a dietary supplement; in Canada it is a Natural Health Product with a Health Canada license number authorizing claims about cold/flu prevention.
Pooled reviews give a more cautious picture than single trials. A 2011 systematic review of five North American ginseng trials (747 people) concluded there is “insufficient evidence to conclude that ginseng reduces the incidence or severity of common colds”; fewer people had at least one cold on ginseng, but not significantly (relative risk 0.70, 95% CI 0.48–1.02), while in two trials colds were 6.2 days shorter in people taking it preventively for 8–16 weeks. A 2020 meta-analysis of ten trials of Asian or North American ginseng found about 30% fewer seasonal upper respiratory infections (relative risk 0.69, 95% CI 0.52–0.90), but judged the risk of bias high-to-unclear for most trials and could not exclude publication bias; its authors state that the evidence does not allow conclusions.
Natural Killer (NK) Cell Activation
Natural killer (NK) cells are innate-immune lymphocytes specialized to kill virus-infected cells and certain tumor cells without requiring prior antigen exposure or major histocompatibility complex (MHC) restriction. They are first-line responders to viral infection, killing infected cells before adaptive immunity (T cells, antibody) has time to organize. Natural killer cell activity declines with age and chronic stress, contributing to elderly susceptibility to viral infection and reactivation of latent herpesviruses.
Multiple ginseng preparations have demonstrated natural killer cell enhancement in human studies:
- Scaglione 1996 found natural killer activity nearly twice as high at weeks 8 and 12 in vaccinated subjects taking the standardized Asian ginseng extract as on placebo
- Korean red ginseng polysaccharide preparations have shown natural killer enhancement in cancer patient populations
- CVT-E002 (American ginseng polysaccharide) has shown natural killer enhancement in vitro and in elderly subjects
- Ginsenoside Rh1 (a deglycosylated ginsenoside metabolite generated by gut microbial action on Rg1) has been shown to enhance natural killer cytotoxicity against tumor cell lines in vitro
The natural killer-enhancing effect is particularly relevant for elderly populations (where immunosenescence has reduced baseline natural killer function), cancer patients (where chemotherapy and disease have depressed natural killer function), and chronically stressed individuals (where elevated cortisol suppresses natural killer activity).
Macrophage and Dendritic Cell Activation
Macrophages and dendritic cells are the principal antigen-presenting cells of the innate immune system. They phagocytize pathogens, process antigens, and present them to T cells in the context of MHC class II to initiate adaptive immune responses. Ginsenosides modulate both cell types:
- Macrophage activation — ginsenoside Rg1 increases macrophage phagocytic activity, increases tumor necrosis factor-alpha and interleukin-1-beta production at appropriate doses (an effect that is paradoxically anti-inflammatory in the context of chronic low-grade inflammation, because it shifts macrophages from a stuck M2 phenotype to a more flexible M1 capability), and increases nitric oxide production from inducible nitric oxide synthase (iNOS) as part of pathogen-killing capacity.
- Dendritic cell maturation — ginsenoside Rb1 promotes dendritic cell maturation from immature precursors, upregulates surface MHC class II and co-stimulatory molecules (CD80, CD86), and enhances T-cell priming capacity. The net effect is improved antigen presentation to naive T cells, contributing to the vaccine adjuvant effect seen in the Scaglione trial.
- Toll-like receptor (TLR) signaling — ginseng polysaccharides act as agonists of TLR4 on macrophages and dendritic cells, mimicking some aspects of pathogen-associated molecular patterns (PAMPs) without the actual pathogenic risk. This is a common mechanism for plant-derived polysaccharide immunomodulators.
The macrophage / dendritic cell mechanism explains why ginseng is more useful for general immune resilience than for acute treatment of established infection — it primes the innate immune system to respond more robustly to future challenges, rather than substituting for antiviral or antibacterial therapy in active infection.
Antibody Class-Switching and Vaccine Adjuvant Effect
The Scaglione 1996 finding of higher antibody titers (an average of 272 vs 171 units at week 8) in vaccinated subjects taking the standardized Asian ginseng extract is proposed to be explained by ginseng's adjuvant-like effects on B-cell biology. B cells require help from T-helper cells to class-switch from initial immunoglobulin M (IgM) production to higher-affinity immunoglobulin G (IgG) (the dominant protective antibody class for influenza). The factors that enhance this T-cell help and B-cell maturation include:
- Improved dendritic cell antigen presentation to naive T cells (ginseng effect, discussed above)
- Enhanced interleukin-4 (IL-4) and interleukin-21 (IL-21) production from T-follicular helper (Tfh) cells
- Improved germinal center reaction in lymph nodes, where B cells undergo somatic hypermutation and affinity maturation
- Improved follicular dendritic cell function holding antigen on display for affinity selection
Several preclinical studies in mice have shown that ginsenosides act on each of these steps, with the net effect of higher-titer and higher-affinity antibody responses to co-administered antigens. The clinical translation in the Scaglione trial — higher average antibody titers to the influenza vaccine (272 vs 171 units) — is consistent with this mechanism.
The adjuvant effect has practical relevance beyond seasonal influenza vaccination. Elderly patients, immunosuppressed patients (post-organ-transplant, on chronic prednisone, on biologic immunomodulators for autoimmune disease), and patients with hypogammaglobulinemia all mount weaker antibody responses to vaccines. Ginseng pre-vaccination has been investigated as a strategy to improve vaccine responsiveness in these populations, with promising but preliminary results.
The U.S. Food and Drug Administration (FDA) does not recommend any over-the-counter supplement specifically as a vaccine adjuvant. For more on vaccination, see Immune Boosting.
Polysaccharides vs Ginsenosides — Two Active Fractions
One of the more interesting aspects of ginseng pharmacology is that the root contains two largely independent classes of bioactive molecules, both with immune-modulating activity:
- Ginsenosides — triterpene saponins, the better-studied class. ~30 individual ginsenosides have been characterized. Variable lipid-solubility; ginsenosides are absorbed (in part) intact through the gut wall and circulate systemically.
- Polysaccharides — complex sugar polymers, including beta-glucans, pectins, and arabinogalactans. Not absorbed intact (too large to cross the gut epithelium) but act locally on gut-associated lymphoid tissue (GALT) and through pattern-recognition receptor signaling. CVT-E002 is a polysaccharide-enriched preparation.
The two fractions activate different aspects of immune function and are likely additive in whole-root preparations. Most traditional ginseng preparations (decoctions, teas, whole-root powder) contain both. Modern standardized extracts vary: the standardized Asian ginseng extract used by Scaglione is standardized for ginsenoside content but contains some polysaccharide; CVT-E002 is enriched for polysaccharide but contains some ginsenoside; ginsenoside-only purified preparations exist primarily in research settings.
Whole-root powder or extract contains both fractions, so both immune mechanisms can contribute; the practical clinical benefit of selecting one fraction over the other has not been demonstrated.
Elderly Immune Decline (Immunosenescence)
Immune function declines with age in stereotyped ways: thymic involution reduces naive T-cell output, natural killer cell function declines, B-cell antibody response to vaccination weakens, and the cytokine environment shifts toward chronic low-grade inflammation ("inflammaging"). The net effect is increased susceptibility to viral infection (influenza, respiratory syncytial virus (RSV), herpes zoster reactivation), reduced vaccine effectiveness, and slower recovery from infectious illness. The U.S. Centers for Disease Control and Prevention (CDC) and World Health Organization (WHO) data on influenza mortality concentrate the majority of deaths in adults over 65 for this reason.
Ginseng has been studied as an intervention for immunosenescence in multiple trials:
- McElhaney 2004 (CVT-E002 in long-term-care residents) found fewer laboratory-confirmed influenza and respiratory syncytial virus illnesses (9 of 101 on placebo vs 1 of 97)
- McElhaney 2011 (CVT-E002 in 783 influenza-vaccinated community-dwelling adults) found no difference in laboratory-confirmed upper respiratory infections (5.5%, 5.2% and 4.6%), though symptom-defined infections were fewer and shorter
- High 2012 (CVT-E002 in 293 people with early, untreated chronic lymphocytic leukemia, a blood cancer whose patients are at high risk of respiratory illness, January–March 2009) found no reduction in days of acute respiratory illness (8.5 days on CVT-E002 vs 6.8 on placebo) or in antibiotic use; moderate-to-severe sore throat was less common on CVT-E002
- Several small Korean red ginseng trials in elderly populations have shown improved natural killer cell function and fewer upper respiratory infections
- Pre-vaccination ginseng dosing in elderly subjects has shown trends toward improved antibody response, though the elderly studies are smaller than the Scaglione 1996 trial in middle-aged adults
For older adults in institutional settings, the strongest single result is the McElhaney 2004 trial; the larger trial in community-dwelling adults and the trial in chronic lymphocytic leukemia found no difference on their main outcomes. The Canadian regulatory acceptance of CVT-E002 is partly based on this evidence base in elderly populations.
For more on healthy aging strategies, see Healthy Aging, Vitamin D3, and Zinc — all three of which have substantial evidence for supporting elderly immune function as well.
Dosing and Timing for Immune Use
Doses used in trials and in traditional practice vary by preparation:
- Standardized Asian ginseng (Panax ginseng) extract — 100 mg daily, the Scaglione trial dose. The trials started dosing 4-12 weeks before peak respiratory infection season (typically late October in the temperate Northern Hemisphere) and continued through the season.
- CVT-E002 American ginseng polysaccharide — 200 mg twice daily in the McElhaney 2004 trials; many sources describe doubling to 400 mg twice daily at the first sign of cold symptoms ("rescue" dosing) for 3 days. The trial evidence concerns routine preventive use rather than the rescue dose.
- Whole-root Korean red ginseng powder — 1-3 g/day, traditionally taken in the morning, continuously through the cold/flu season.
- Whole-root American ginseng powder — 1-3 g/day, morning. Practitioners describe it as the gentler choice compared with Korean red ginseng for evening-shift workers and people with significant anxiety or insomnia.
Timing relative to vaccination: if the goal is to enhance the antibody response to an influenza vaccine, the Scaglione protocol started ginseng 4 weeks before vaccination and continued for 8 weeks after.
For acute use at the onset of cold symptoms, the evidence is weaker. The CVT-E002 rescue protocol (400 mg twice daily for 3 days at the first cold symptom) is described in product marketing but has limited rigorous clinical evidence. The trials tested ginseng for prevention rather than for treating a cold already under way.
Cautions, Limitations, and Drug Interactions
- Immunosuppressant interaction — patients on cyclosporine, tacrolimus, methotrexate, biologic immunomodulators (anti-tumor necrosis factor (TNF) agents, Janus kinase (JAK) inhibitors), or chronic prednisone face a theoretical interaction with ginseng's immune-activating effects. Most patients tolerate moderate doses without measurable interference with the immunosuppressant's effect; drugs with a narrow gap between an effective and a toxic blood level, such as cyclosporine and tacrolimus, are the ones where a small change matters most.
- Autoimmune disease — theoretical concern that immune-activating herbs may worsen autoimmune conditions (lupus, rheumatoid arthritis, multiple sclerosis, type 1 diabetes). Clinical observation does not consistently support this concern with ginseng specifically; the theoretical concern applies most to people with active autoimmune disease.
- Active infection (bacterial) — ginseng is not a substitute for antibiotics in confirmed bacterial infection. The trials tested it for prevention and supportive care, not as primary therapy for streptococcal pharyngitis, pneumonia, urinary tract infection, or other bacterial conditions.
- Warfarin interaction — a case report and then a randomized, placebo-controlled trial of 20 healthy volunteers found that American ginseng reduces warfarin's anticoagulant (blood-thinning) effect: after 2 weeks of ginseng the peak international normalized ratio (INR) was lower than on placebo (difference −0.19; P = 0.0012), and warfarin blood levels were lower too.
- Pregnancy — safety in pregnancy has not been established. Postpartum use is sometimes considered for fatigue and immune support.
- Insomnia — Korean red ginseng particularly can disrupt sleep if taken in the evening, which is why it is traditionally taken in the morning; insomnia was the main adverse event in the Scaglione trial.
- Children — CVT-E002 has been studied at lower doses in children for cold prevention, with reasonable safety but limited efficacy data.
Key Research Papers
- Scaglione F et al. (1996). Efficacy and safety of the standardised ginseng extract G115 for potentiating vaccination against the influenza syndrome and protection against the common cold. Drugs Under Experimental and Clinical Research. — PubMed PMID: 8879982
- Predy GN et al. (2005). Efficacy of an extract of North American ginseng containing poly-furanosyl-pyranosyl-saccharides for preventing upper respiratory tract infections: a randomized controlled trial. Canadian Medical Association Journal. — PubMed PMID: 16247099
- McElhaney JE et al. (2004). A placebo-controlled trial of a proprietary extract of North American ginseng (CVT-E002) to prevent acute respiratory illness in institutionalized older adults. Journal of the American Geriatrics Society. — PubMed PMID: 14687309
- McElhaney JE et al. (2011). Efficacy and safety of CVT-E002, a proprietary extract of Panax quinquefolius in the prevention of respiratory infections in influenza-vaccinated community-dwelling adults. Influenza Research and Treatment. — PubMed PMID: 23074661
- High KP et al. (2012). A randomized, controlled trial of Panax quinquefolius extract (CVT-E002) to reduce respiratory infection in patients with chronic lymphocytic leukemia. Journal of Supportive Oncology. — PubMed PMID: 22266154
- Lee CS et al. (2014). Effects of Korean red ginseng on respiratory infections. Journal of Ginseng Research. — PubMed
- Yoo DG et al. (2012). Protective effect of ginseng polysaccharides on influenza viral infection. PLoS One. — PubMed PMID: 22442708
- Wang Y et al. (2010). Immunomodulatory effects of polysaccharides from Panax ginseng. International Immunopharmacology. — PubMed
- Kang S, Min H (2012). Ginseng, the immunity boost: the effects of Panax ginseng on immune system. Journal of Ginseng Research. — PubMed
- Lee JS et al. (2014). Salutary effect of Korean red ginseng on systemic inflammation. Journal of Ethnopharmacology. — PubMed
- Block KI, Mead MN (2003). Immune system effects of echinacea, ginseng, and astragalus: a review. Integrative Cancer Therapies. — PubMed PMID: 15035888
- Caso Marasco A et al. (1996). Double-blind study of a multivitamin complex supplemented with ginseng extract. Drugs Under Experimental and Clinical Research. — PubMed PMID: 9034759
- Yuan CS et al. (2004). Brief communication: American ginseng reduces warfarin's effect in healthy patients: a randomized, controlled Trial. Annals of Internal Medicine. — PubMed PMID: 15238367
- Seida JK, Durec T, Kuhle S (2011). North American (Panax quinquefolius) and Asian Ginseng (Panax ginseng) Preparations for Prevention of the Common Cold in Healthy Adults: A Systematic Review. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 19592479
- Antonelli M, Donelli D, Firenzuoli F (2020). Ginseng integrative supplementation for seasonal acute upper respiratory infections: A systematic review and meta-analysis. Complementary Therapies in Medicine. — PubMed PMID: 32951718
- Lim TS et al. (2002). Polysaccharide isolated from Panax ginseng induces apoptosis of human melanoma cells. Acta Pharmacologica Sinica. — PubMed