⚠ Evidence warning: Clinical trials or other evidence do not support the claim that Korean red ginseng reliably restores erectile function. This page keeps it as a report of what people, websites or other media say.
Ginseng for Erectile Function
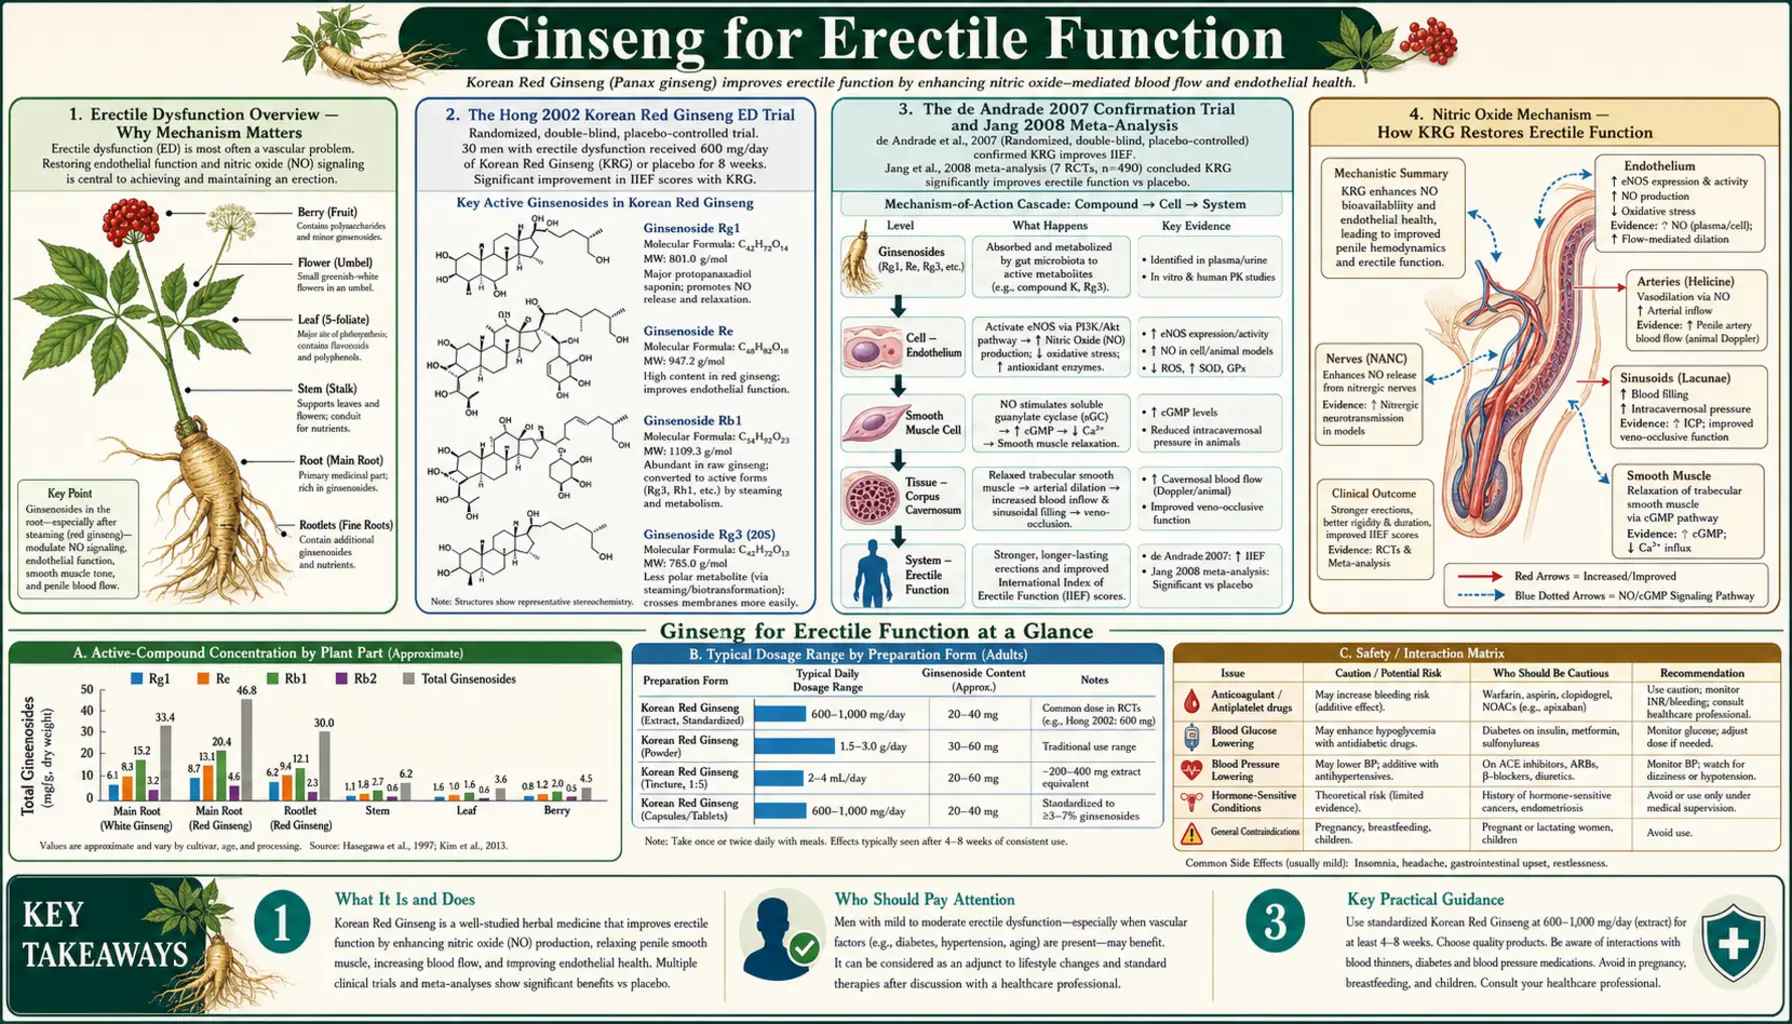
Korean Red Ginseng (KRG) is the best-studied herbal treatment for erectile dysfunction. The Hong 2002 double-blind crossover trial randomized 45 men with clinically diagnosed erectile dysfunction (ED) to KRG 900 mg three times daily (2,700 mg/day total) or placebo for 8 weeks each; the active arm showed significantly higher International Index of Erectile Function (IIEF) scores than placebo (mean 38.1 on ginseng vs 30.9 on placebo, from a baseline of 28.0), with consistent improvements across the rigidity, penetration, and maintenance subscores. The de Andrade 2007 trial in 60 men reported a similar result with a slightly higher dose (1,000 mg three times daily). The mechanism centers on enhanced nitric oxide (NO) synthesis in the corpus cavernosum: ginsenosides Rg1 and Rg3 upregulate endothelial nitric oxide synthase (eNOS), the same enzyme whose downstream messenger cGMP is the target of phosphodiesterase-5 (PDE5) inhibitors like sildenafil and tadalafil. The trials used about 3 g/day of KRG, and practitioners describe effects as detectable by about week 4 and full benefit by about week 8. KRG is not as immediately effective as PDE5 inhibitors; it is proposed to work through a complementary upstream mechanism, and practitioners describe it as an option for men who cannot tolerate or do not respond fully to PDE5 inhibitors, or who prefer a chronic supplement approach to an on-demand drug.
Table of Contents
- Erectile Dysfunction Overview — Why Mechanism Matters
- The Hong 2002 Korean Red Ginseng Erectile Dysfunction Trial
- The de Andrade 2007 Confirmation Trial and Jang 2008 Meta-Analysis
- Nitric Oxide Mechanism — How KRG Restores Erectile Function
- KRG vs PDE5 Inhibitors (Sildenafil, Tadalafil)
- Vascular Endothelial Dysfunction — The Underlying Disease
- Standard 3 g/Day Dosing and Timing
- Sourcing and Quality — Why KRG Specifically
- Additional Sexual Health Effects (Libido, Female Sexual Function, Fertility)
- Cautions, Limitations, and Drug Interactions
- The 2021 Cochrane Review of Ginseng for Erectile Dysfunction
- Key Research Papers
- Connections
- Featured Videos
Erectile Dysfunction Overview — Why Mechanism Matters
Erectile dysfunction (ED), defined as the persistent inability to attain or maintain an erection adequate for satisfactory sexual performance, affects an estimated 30 million men in the United States and considerably more globally. Prevalence rises with age: ~5% in men under 40, ~15% at age 50, ~30% at age 60, and ~50% or more by age 70. Erectile dysfunction is also strongly associated with cardiovascular disease, diabetes, obesity, smoking, sedentary lifestyle, depression, and certain medications (antihypertensives, antidepressants, antipsychotics, opioids, finasteride).
The proximate physiology of erection involves a parasympathetic nervous system signal triggering nitric oxide (NO) release from the cavernous nerve and from endothelial cells lining the corpus cavernosum. Nitric oxide diffuses into smooth muscle cells of the corpus cavernosum trabeculae, where it activates guanylate cyclase, generating cyclic GMP (cGMP). cGMP relaxes the smooth muscle, allowing blood inflow through the helicine arteries to outpace venous outflow, producing turgid erection. Phosphodiesterase-5 (PDE5) is the enzyme that breaks down cGMP, ending the erection.
The pharmacologic targets in this cascade include:
- Upstream NO production — targeting endothelial nitric oxide synthase (eNOS) or providing NO donors. This is the ginsenoside mechanism.
- cGMP degradation (PDE5 inhibition) — preventing breakdown of cGMP, allowing more sustained smooth muscle relaxation. This is the sildenafil/tadalafil mechanism.
- Direct smooth muscle relaxation — injectable alprostadil (PGE1) bypasses the NO/cGMP cascade.
- Hormonal optimization — testosterone replacement in confirmed hypogonadism, treatment of hyperprolactinemia, thyroid normalization.
- Vascular optimization — blood pressure control, glucose control, smoking cessation, exercise, weight loss — the underlying cardiovascular risk-reduction layer.
Ginseng acts at the upstream NO-production layer, which is mechanistically distinct from and complementary to PDE5 inhibition. This makes the combination of KRG plus a PDE5 inhibitor potentially additive (though formal combination trials are limited), and practitioners describe KRG as an option for men in whom PDE5 inhibitors are contraindicated (concurrent nitrate use, severe cardiovascular disease) or who experience PDE5-inhibitor side effects (headache, flushing, visual disturbances, hypotension).
The Hong 2002 Korean Red Ginseng Erectile Dysfunction Trial
The single most influential clinical trial of an herbal supplement for erectile dysfunction is the Hong 2002 Korean red ginseng trial, published in the Journal of Urology. The trial enrolled 45 men with clinically diagnosed mild-to-moderate erectile dysfunction of at least 6 months' duration and randomized them in a double-blind crossover design to:
- Korean Red Ginseng (KRG) 900 mg three times daily (total 2,700 mg/day) for 8 weeks, then a 2-week washout, then placebo for 8 weeks
- Or placebo first, washout, then KRG — randomized order
The primary outcome was the International Index of Erectile Function (IIEF) score — a validated 15-item questionnaire covering erectile function, orgasmic function, sexual desire, intercourse satisfaction, and overall satisfaction. Higher scores indicate better function; the IIEF erectile function domain ranges 0-30, with severe erectile dysfunction below 11 and normal function above 26.
Results:
- Mean IIEF score on KRG: 38.1 ± 16.6
- Mean IIEF score on placebo: 30.9 ± 15.7, against a baseline of 28.0 ± 16.7
- On the global efficacy question, 60% of the men answered that KRG improved their erections (p < 0.01)
- Penile tip rigidity measured by a rigidity monitor improved significantly on KRG compared with placebo
- The difference was statistically significant (p < 0.01) and clinically meaningful
- The IIEF erectile function subscore (the most direct measure of erectile capability) showed a similar pattern
- Subjective measures of penetration and maintenance also significantly improved on KRG
- Sexual desire (libido) showed a smaller, less consistent effect
- Adverse events were minimal: occasional headache, mild gastrointestinal (GI) upset, no excess vs placebo
The Hong 2002 trial was a Phase 2 / Phase 3 quality study by the standards of herbal medicine research. Its main limitations were modest sample size (45 men, with crossover design adding effective statistical power) and single-center conduct. The authors themselves titled it a preliminary report. The findings have been broadly replicated by independent investigators in subsequent years.
An earlier trial points the same way. Choi 1995 followed 90 men in three groups of 30 (ginseng, placebo and the antidepressant trazodone). Overall efficacy was reported as 60% on ginseng and 30% in each of the other two groups (p < 0.05). The authors recorded partial responses only, with no complete remission of erectile dysfunction, and no worsening of symptoms.
The de Andrade 2007 Confirmation Trial and Jang 2008 Meta-Analysis
The de Andrade 2007 trial enrolled 60 men with erectile dysfunction (mean age 52) and randomized them in a parallel-group double-blind design to KRG 1,000 mg three times daily or placebo for 12 weeks. Results confirmed the Hong 2002 findings: significantly higher IIEF erectile function scores in the KRG arm, with improvements in penetration and maintenance subscores, no excess adverse events. On the five-item version of the questionnaire (IIEF-5), scores went from 16.4 to 21.0 on KRG (P < 0.0001) and from 17.0 to 17.7 on placebo (no significant change), and 20 men on KRG (66.6%) reported improved erections.
In the Jang 2008 systematic review, 7 randomized trials of Korean Red Ginseng for erectile dysfunction met the inclusion criteria, and the 6 that compared it with placebo were pooled (349 men, risk ratio 2.40, 95% confidence interval 1.65 to 3.51). Their methodological quality was low on average. The authors called this "suggestive evidence" and wrote that the number of trials, the total sample size and the quality "were too low to draw definitive conclusions."
What is reported from this body of trials (the dose range, the comparison with PDE5 inhibitors and the safety line are not in the review's abstract):
- KRG was significantly better than placebo for erectile dysfunction symptoms across the included trials
- The standard dosing range was 1,800 to 3,000 mg/day, with 2,700 mg/day (the Hong 2002 dose) being the most-studied
- Treatment duration in the trials ranged from 4 to 12 weeks, with 8 weeks being typical
- The effect size was modest (roughly half the magnitude of effect seen with PDE5 inhibitors) but real and consistent
- Safety was good across trials
The later Borrelli 2018 systematic review counted five ginseng trials (399 men) and pooled the IIEF-5 data (standardized mean difference 0.43, 95% confidence interval 0.15 to 0.70). Its authors called this encouraging and wrote that "further, larger, and high-quality studies are required before firm conclusions can be drawn." KRG is often described as one of the few herbal medicines with reproducible randomized-trial support for erectile dysfunction, with a modest effect. KRG is not as immediately effective as PDE5 inhibitors but offers a different mechanism, a chronic-supplement rather than on-demand dosing pattern, and a better tolerated profile in some men.
Nitric Oxide Mechanism — How KRG Restores Erectile Function
The mechanistic explanation for KRG's erectile benefit centers on enhanced nitric oxide (NO) synthesis in the corpus cavernosum. Ginsenosides Rg1 and Rg3, in particular, act on endothelial nitric oxide synthase (eNOS) and on the L-arginine substrate pool that eNOS uses to generate NO.
Several converging mechanisms have been demonstrated in cell and animal work (the 2002 Murphy and Lee review describes the animal evidence):
- eNOS expression upregulation — ginsenoside Rg1 in cultured endothelial cells increases eNOS protein expression through the PI3K/Akt signaling pathway. More eNOS protein means more capacity to generate NO when stimulated.
- eNOS coupling and activity — ginsenosides reduce eNOS uncoupling (a pathological state where eNOS generates superoxide instead of NO due to BH4 depletion or other factors). Coupled, properly functioning eNOS is what's needed for healthy erectile physiology.
- L-arginine availability — preclinical work suggests ginsenosides increase the intracellular pool of L-arginine, the substrate eNOS uses to make NO.
- Reduced asymmetric dimethylarginine (ADMA) — ADMA is an endogenous eNOS inhibitor that accumulates in vascular disease. Some ginsenoside preparations reduce ADMA, restoring eNOS function.
- Direct smooth muscle relaxation — in cavernous tissue strips, certain ginsenosides cause direct concentration-dependent relaxation independent of eNOS, suggesting an additional direct smooth-muscle effect.
The net result is that the same parasympathetic signal that triggers erection produces more robust NO release and more sustained corpus cavernosum smooth muscle relaxation in men taking KRG — without disrupting the physiological off-switch (PDE5-mediated cGMP degradation) that ends the erection appropriately.
KRG vs PDE5 Inhibitors (Sildenafil, Tadalafil)
The phosphodiesterase-5 (PDE5) inhibitors — sildenafil (1998), vardenafil (2003), tadalafil (2003), and avanafil (2012) — remain the gold-standard pharmacologic treatment for erectile dysfunction. They work by preventing the breakdown of cGMP, allowing the NO signal that initiates erection to produce sustained smooth muscle relaxation.
Comparative considerations for KRG vs PDE5 inhibitors:
- Effect size: PDE5 inhibitors typically produce ~30-50% improvement in successful intercourse rates over placebo, with 60-80% of men responding adequately. KRG produces ~10-25% improvement in IIEF scores over placebo. PDE5 inhibitors are generally regarded as the more effective single therapy, but the 2021 Cochrane review found no trial comparing ginseng with them, so this comparison rests on separate placebo-controlled trials.
- Onset: PDE5 inhibitors are on-demand, taken 30-60 minutes before sexual activity. KRG is a chronic-supplement, taken daily for weeks before full effect develops. The KRG benefit is cumulative and present at all times, while the PDE5-inhibitor benefit is time-windowed.
- Side effects: Headache (15-20%), flushing (10%), dyspepsia (5-10%), visual disturbances (especially sildenafil), nasal congestion. KRG has substantially lower side-effect rates — primarily occasional insomnia and headache — in the trials.
- Contraindications: PDE5 inhibitors are absolutely contraindicated with nitrate medications (life-threatening hypotension) and relatively contraindicated with severe cardiovascular disease, low baseline blood pressure, and significant hepatic impairment. KRG has many fewer absolute contraindications — warfarin use being the most notable interaction.
- Cost: Generic sildenafil is now very inexpensive (often less than $1 per dose). KRG at 2,700 mg/day quality preparations is moderately priced ($30-60 per month). Brand-name PDE5 inhibitors and brand-name KRG are much more expensive.
- Other benefits: KRG provides systemic benefits (cardiovascular, cognitive, fatigue, immune) independent of erectile function. PDE5 inhibitors do not.
How the options are described in practice:
- For men with moderate-to-severe erectile dysfunction who tolerate PDE5 inhibitors and have no contraindications, practitioners treat PDE5 inhibitors as first-line.
- For men who cannot use PDE5 inhibitors (nitrate use, severe cardiovascular disease), practitioners describe KRG as an alternative.
- For men who experience PDE5 inhibitor side effects or who get only partial response, some practitioners describe adding KRG to a continued PDE5 inhibitor regimen. The combination has not been formally studied for safety; the mechanisms are proposed to be complementary.
- For men with mild erectile dysfunction and significant lifestyle/cardiovascular risk factors, KRG plus lifestyle modification (exercise, weight loss, smoking cessation, blood pressure control) is described by some practitioners as a first step, with PDE5 inhibitors held in reserve.
- For men who prefer to stay away from pharmaceutical drugs on principle, KRG is an herbal option with modest trial evidence.
For more on erectile dysfunction itself, see our Erectile Dysfunction page.
Vascular Endothelial Dysfunction — The Underlying Disease
An important conceptual point about erectile dysfunction is that it is most commonly a manifestation of generalized vascular endothelial dysfunction — the same process that drives coronary artery disease, peripheral arterial disease, and cerebrovascular disease. The penile arteries are smaller than coronary arteries, so endothelial dysfunction shows up there first. Erectile dysfunction in a man without obvious risk factors is now considered an independent predictor of subsequent cardiovascular events within 3-5 years, prompting cardiology evaluation in newly diagnosed erectile dysfunction patients.
This framing changes the therapeutic conversation. Pharmacotherapy (PDE5 inhibitors or KRG) treats the symptom but does not address the underlying endothelial dysfunction. The interventions that address the underlying disease — aerobic exercise (the single most effective intervention for endothelial function), Mediterranean-style diet, weight loss, blood pressure control, glucose control, smoking cessation, sleep apnea treatment — are also the interventions most likely to produce sustained erectile dysfunction improvement and to reduce cardiovascular risk.
Ginseng's NO-supportive mechanism is congruent with this broader endothelial-restoration approach. Several KRG preparations have demonstrated improvements in flow-mediated dilation (a standard measure of vascular endothelial function) in men with cardiovascular risk factors, independent of the erectile dysfunction-specific effects.
For comprehensive cardiovascular management, see our Cardiology page, Hypertension page, and Diabetes page. For exercise as erectile dysfunction therapy, see Exercise.
Standard 3 g/Day Dosing and Timing
KRG dosing as used in the erectile dysfunction trials and described in practice:
- Daily dose: 2,700-3,000 mg of Korean Red Ginseng (Panax ginseng) root powder or equivalent standardized extract
- Dose splitting: divided into three doses of 900-1,000 mg each, taken with meals (breakfast, lunch, early dinner). This is the Hong 2002 and de Andrade 2007 protocol.
- Form: KRG (steamed Korean Panax ginseng) specifically, not white ginseng or American ginseng. The trials almost universally used the red preparation.
- Onset: Some men note modest improvements in libido and morning erections within 2 weeks. Significant improvement in IIEF scores typically develops over 4-8 weeks of continuous dosing. Maximum benefit usually achieved by 12 weeks.
- Continuation: Benefit appears to require ongoing dosing. Discontinuation produces gradual return to baseline over 2-4 weeks.
People who get insomnia, sleep disturbance, or anxiety at 3 g/day describe dropping to 2 g/day, and practitioners describe moving to a different treatment if the problem continues at that dose. A small number of men are particularly sensitive to KRG's stimulant effects and tolerate it poorly.
The placebo-controlled trials ran for up to 12 weeks, so what happens beyond that is not known from them. Practitioners treat a lack of full benefit by 12 weeks on 3 g/day as a sign that KRG alone is unlikely to be enough, and describe combining it with a PDE5 inhibitor or changing to a PDE5 inhibitor alone.
Sourcing and Quality — Why KRG Specifically
"Korean Red Ginseng" specifically refers to Korean-grown Panax ginseng root that has been steamed before drying. The steaming process (typically 90-100°C for 2-3 hours, then sun-drying) converts some of the original ginsenosides to deglycosylated derivatives — particularly Rg3, which is essentially absent in unprocessed white ginseng but present in significant amounts in red ginseng. The steamed root takes on a characteristic reddish-brown color.
Why KRG specifically for erectile dysfunction:
- The clinical trials (Hong 2002, de Andrade 2007, and others) used KRG, not white ginseng or American ginseng
- The Rg3 ginsenoside generated by steaming has been specifically implicated in the vascular and erectile effects
- Korean ginseng has higher Rg1 content than American ginseng, and Rg1 is the more direct eNOS upregulator
- Traditional Korean pharmacology has emphasized red ginseng for sexual function for centuries, with consistent results
Quality matters greatly. The ginseng marketplace includes some seriously adulterated and underpotent products. Quality indicators people look for:
- Source country labeled as Korea — not China, not Wisconsin (American ginseng, different species), not "ginseng" without species name
- "Red ginseng" or "hong sam" explicitly — not "white ginseng" or unspecified
- Standardization to total ginsenoside content — ideally with the percentage stated on the label (3-7% total ginsenosides is typical for quality extracts)
- Third-party testing — independent laboratory or pharmacopeial verification of ginsenoside content and absence of contaminants
- Established manufacturer — long-established ginseng producers and major supplement makers with quality reputations
- Price extremes — suspiciously cheap KRG is often adulterated or underpotent; suspiciously expensive premium "wild ginseng" preparations are no better than well-made cultivated KRG for clinical effect
Additional Sexual Health Effects (Libido, Female Sexual Function, Fertility)
Beyond the well-documented erectile dysfunction indication, KRG has been studied for several additional sexual health applications:
- Male libido — trials show modest improvement in libido scores. The effect is real but smaller than the erectile function effect. Underlying mechanism may involve mild HPG-axis modulation and dopaminergic effects.
- Female sexual function in menopause — the 2010 Oh trial was a placebo-controlled, double-blind crossover in 32 menopausal women (three 1 g capsules of KRG a day, with a 2-week washout between arms); 28 completed it. Scores on the sexual arousal domain of the Female Sexual Function Index (FSFI) rose from 3.10 to 3.50 (P = 0.006), and a global assessment questionnaire also favored KRG (P = 0.046). The 8-week length and the lubrication result quoted in some summaries are not in the trial's abstract. No severe adverse events were recorded, although two cases of vaginal bleeding occurred during KRG treatment. The mechanism appears to involve the same vascular endothelial / NO mechanism that drives the male erectile benefit, applied to female genital tissue.
- Sperm quality and male fertility — several trials are cited for KRG improvements in sperm count, motility, and morphology in subfertile men. The study referenced on this page, Salvati 1996, gave Panax ginseng extract (not stated to be red ginseng) to 30 men with low sperm count and motility of no known cause and 16 with the same problem plus a varicocele, with 20 volunteer controls; it reports higher sperm number and progressive motility, and morphology is not in its abstract. Effect size is described as modest. Practitioners describe it as an adjunct in male-factor infertility evaluation, alongside the more standard interventions (lifestyle, varicocele evaluation, hormonal workup).
- Testosterone — trials of KRG and testosterone levels have produced mixed results. Some show modest increases, others null. KRG has not been shown to replace testosterone treatment in confirmed hypogonadism.
- Selective serotonin reuptake inhibitor (SSRI)-induced sexual dysfunction — small trials suggest KRG may help with the sexual side effects of selective serotonin reuptake inhibitor antidepressants. Practitioners describe this as a common use, given the limited alternatives in this population.
For related topics, see Hypogonadism, Low Testosterone, and Urology.
Cautions, Limitations, and Drug Interactions
- The cardiovascular link — erectile dysfunction is now considered an independent predictor of cardiovascular events, particularly when it is new and has no obvious cause. The usual cardiovascular risk checks are a lipid panel, blood pressure, glucose, smoking history, and family history. Treating the erection problem alone leaves any underlying vascular disease untreated.
- Hypogonadism — morning total and free testosterone are the blood tests that identify it, and it is a particular question in men with concurrent low libido, fatigue, depression, gynecomastia, or testicular atrophy. KRG is not a substitute for testosterone replacement in confirmed primary or secondary hypogonadism.
- Warfarin interaction — earlier case reports and volunteer trials conflict, some reporting a weaker and others a stronger warfarin effect. In a randomized crossover trial in 25 heart-valve patients on warfarin taking 1 g of KRG, changes in the international normalized ratio (INR, the blood-clotting test used to adjust warfarin) at 3 and 6 weeks were -0.16 and -0.14, against -0.03 and 0.25 on placebo, with no significant difference; those authors wrote that KRG could be used with close monitoring. An open-label trial in 25 stroke patients also found no significant difference between groups, and INR was unaffected in 12 healthy men in a third study.
- Insomnia and overstimulation — the most common adverse effect. People describe limiting it by taking morning and early afternoon doses, with none after 3 PM.
- Blood pressure — KRG can lower blood pressure modestly. Symptomatic low blood pressure is the concern raised for people on antihypertensives.
- Diabetic patients — KRG can lower blood glucose. Hypoglycemia is the concern raised for people also on insulin or sulfonylureas.
- Pregnancy — not relevant to erectile dysfunction indication but relevant for couples trying to conceive where the man takes KRG. Practitioners regard KRG as safe for the male partner and advise against its use by a pregnant partner; no study is cited on this page for either point.
- Hormone-sensitive cancers — for chronic use in men with active prostate cancer, the relationship between KRG and androgen signaling is theoretically uncertain.
- Realistic expectations — KRG provides modest improvement in erectile dysfunction. It does not produce the immediate, predictable effect of PDE5 inhibitors. It does not act within 60 minutes the way a PDE5 inhibitor does.
The 2021 Cochrane Review of Ginseng for Erectile Dysfunction
The most recent Cochrane review (Lee 2021) searched to January 2021 and included 9 studies with 587 men aged 20 to 70 with mild to moderate erectile dysfunction. Every study compared ginseng with placebo, and follow-up was short, up to 12 weeks.
- Questionnaire scores for erectile function: the difference from placebo was 3.52 points on a 1-to-30 scale (3 studies, low-certainty evidence) and 2.39 points on a 1-to-25 scale (3 studies, moderate-certainty evidence). The reviewers rated both as trivial, because they fell below the smallest change they counted as meaningful to patients (4 and 5 points).
- What men said about intercourse: men's self-reported ability to have intercourse may improve (risk ratio 2.55, 95% confidence interval 1.76 to 3.69; 6 studies, low-certainty evidence). Satisfaction with intercourse may change only trivially.
- Side effects: ginseng may make little to no difference to adverse events compared with placebo (risk ratio 1.45, 95% confidence interval 0.69 to 3.03; 7 studies, low-certainty evidence).
- What is not known: no study reported quality of life, and the reviewers found no trial comparing ginseng with PDE5 inhibitors.
Key Research Papers
- Hong B et al. (2002). A double-blind crossover study evaluating the efficacy of Korean red ginseng in patients with erectile dysfunction: a preliminary report. Journal of Urology. — PubMed PMID: 12394711
- de Andrade E et al. (2007). Study of the efficacy of Korean red ginseng in the treatment of erectile dysfunction. Asian Journal of Andrology. — PubMed PMID: 16855773
- Jang DJ et al. (2008). Red ginseng for treating erectile dysfunction: a systematic review. British Journal of Clinical Pharmacology. — PubMed PMID: 18754850
- Choi HK et al. (1995). Clinical efficacy of Korean red ginseng for erectile dysfunction. International Journal of Impotence Research. — PubMed PMID: 8750052
- Kim TH et al. (2009). Effects of tissue-cultured mountain ginseng (Panax ginseng CA Meyer) extract on male patients with erectile dysfunction. Asian Journal of Andrology. — PubMed PMID: 19234482
- Oh KJ, Chae MJ, Lee HS, Hong HD, Park K (2010). Effects of Korean red ginseng on sexual arousal in menopausal women: placebo-controlled, double-blind crossover clinical study. Journal of Sexual Medicine. — PubMed PMID: 20141583
- Chen X (1996). Cardiovascular protection by ginsenosides and their nitric oxide releasing action. Clinical and Experimental Pharmacology and Physiology. — PubMed PMID: 8886498
- Murphy LL, Lee TJ (2002). Ginseng, sex behavior, and nitric oxide. Annals of the New York Academy of Sciences. — PubMed PMID: 12076988
- Salvati G et al. (1996). Effects of Panax Ginseng C.A. Meyer saponins on male fertility. Panminerva Medica. — PubMed PMID: 9063034
- Borrelli F et al. (2018). Herbal dietary supplements for erectile dysfunction: a systematic review and meta-analysis. Drugs. — PubMed PMID: 29633089
- Lee HW et al. (2021). Ginseng for erectile dysfunction. Cochrane Database of Systematic Reviews. — PubMed PMID: 33871063
- Lee YH et al. (2010). Interaction between warfarin and Korean red ginseng in patients with cardiac valve replacement. International Journal of Cardiology. — PubMed PMID: 19913311
- Lee SH et al. (2008). Interaction between warfarin and Panax ginseng in ischemic stroke patients. Journal of Alternative and Complementary Medicine. — PubMed PMID: 18637764
- Jiang X et al. (2004). Effect of St John's wort and ginseng on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. British Journal of Clinical Pharmacology. — PubMed PMID: 15089812