Probiotic Strains and Selection
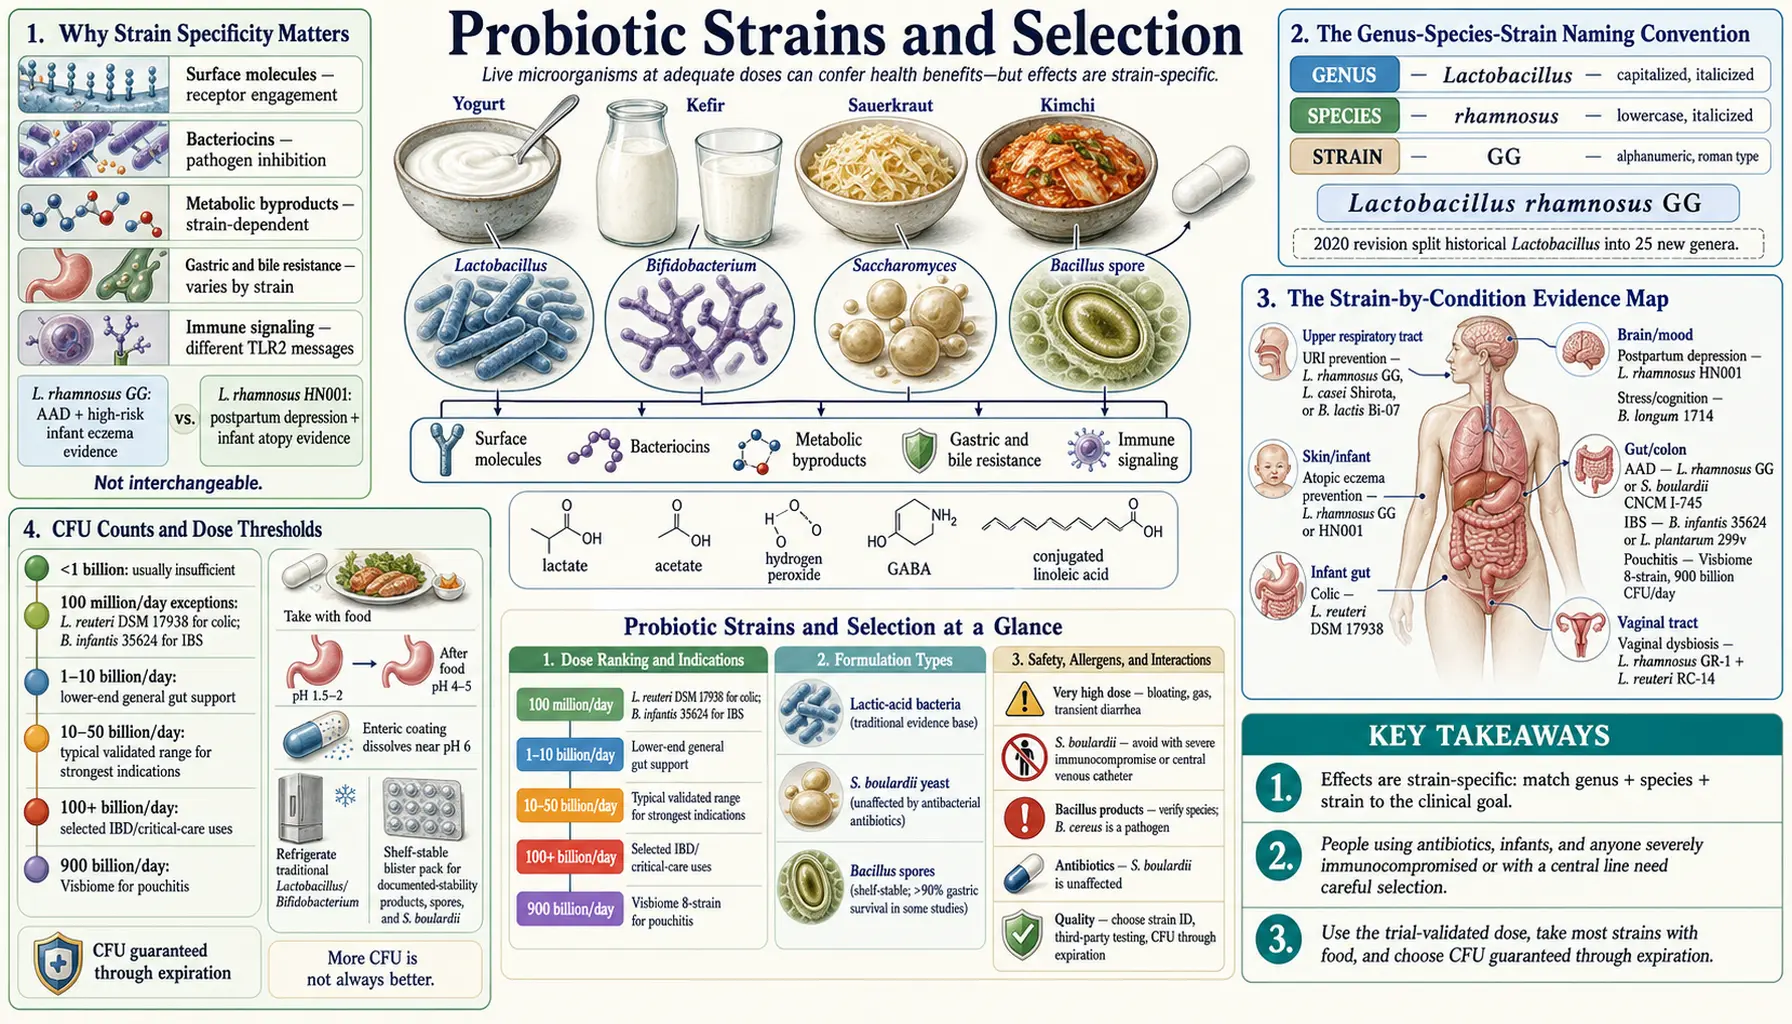
Walking into a health-food store probiotic aisle is one of the more confusing experiences in modern supplement shopping. Dozens of brands, billions of CFU advertised, claims ranging from "immune support" to "complete digestive wellness" — and almost no information on what specific strain at what dose was tested for which condition. The actual science is much more precise than the marketing implies. The 2014 ISAPP consensus statement (Hill et al.) established that a probiotic is "live microorganisms that, when administered in adequate amounts, confer a health benefit on the host," and that the relevant biology is strain-specific: Lactobacillus rhamnosus GG is not interchangeable with Lactobacillus rhamnosus HN001 just because they share a species name. This deep-dive walks through the genus-species-strain naming convention, the strain-by-condition evidence map, CFU dose thresholds, refrigerated vs shelf-stable formulations, the rise of spore-based probiotics, why Saccharomyces boulardii is uniquely useful, and the strains and doses that trials studied for each common clinical goal.
Table of Contents
- Why Strain Specificity Matters
- The Genus-Species-Strain Naming Convention
- The Strain-by-Condition Evidence Map
- CFU Counts and Dose Thresholds
- Refrigerated vs Shelf-Stable Formulations
- Enteric Coating and Gastric Survival
- Single-Strain vs Multi-Strain Formulas
- Spore-Based Probiotics (Bacillus coagulans, B. subtilis)
- Saccharomyces boulardii — The Only Yeast Probiotic
- The Zmora Personalized Response Finding
- Regulatory Wild-West and Quality Control
- Strains and Doses Studied by Clinical Goal
- Key Research Papers
- Connections
- Featured Videos
Why Strain Specificity Matters
The single most important concept for probiotic supplementation is that strains matter, not just species or genera. Lactobacillus rhamnosus GG (also called LGG) and Lactobacillus rhamnosus HN001 belong to the same species but are different organisms with different genome content, different surface molecules, different metabolic profiles, and different clinical effects.
The mechanism for strain-level differences includes:
- Surface molecules — lipoteichoic acid structure, exopolysaccharide composition, surface protein expression, and adhesin diversity all vary at the strain level and determine which host receptors the probiotic engages and how strongly
- Bacteriocin production — the specific antimicrobial peptides produced, and the spectrum of pathogens they inhibit, are strain-determined
- Metabolic byproducts — the relative production of lactate vs acetate vs hydrogen peroxide, the production of GABA or other neuroactive metabolites, the production of conjugated linoleic acid, all vary at the strain level
- Gastric and bile acid resistance — survival rates through the upper GI tract vary several orders of magnitude across strains within the same species
- Immune signaling profile — the same TLR2 receptor receives different "messages" from different strains, biasing the local immune response in different directions
The clinical consequence is that Lactobacillus rhamnosus GG has solid evidence for antibiotic-associated diarrhea prevention and atopic eczema prevention in high-risk infants, while Lactobacillus rhamnosus HN001 has solid evidence for postpartum depression reduction and infant atopic prevention. The two are not interchangeable; picking the wrong one for the wrong indication is likely to produce no effect at all.
This is the inverse of how most consumers think about probiotics. The marketing language and the supplement aisle layout encourage you to think of "probiotics" as a category — like "vitamins" — where the specific product doesn't matter much. The science says the opposite: probiotic effects are strain-specific in the way that drug effects are molecule-specific.
The Genus-Species-Strain Naming Convention
The proper naming of a probiotic strain has three components, in order:
- Genus — the broader taxonomic group, capitalized and italicized. Examples: Lactobacillus, Bifidobacterium, Saccharomyces, Bacillus, Streptococcus, Lactococcus, Escherichia
- Species — the narrower group within the genus, lowercase and italicized. Examples: rhamnosus, plantarum, infantis, boulardii, coagulans, thermophilus
- Strain — the specific isolate, usually an alphanumeric identifier in roman type. Examples: GG, HN001, 35624, CNCM I-745, DSM 17938, NCC3001, BB-12, La-5
A complete proper name therefore looks like: Lactobacillus rhamnosus GG, or Bifidobacterium animalis subsp. lactis BB-12, or Saccharomyces boulardii CNCM I-745. A product label that says only "Lactobacillus acidophilus" without a strain identifier is providing roughly the same level of information as a drug label that says "antibiotic" without specifying which one.
One complication is that taxonomic revisions in 2020 split the historical Lactobacillus genus into 25 new genera. The probiotic strains formerly called Lactobacillus casei, L. paracasei, L. rhamnosus, L. plantarum, and L. reuteri are now technically Lacticaseibacillus casei, Lacticaseibacillus paracasei, Lacticaseibacillus rhamnosus, Lactiplantibacillus plantarum, and Limosilactobacillus reuteri. The literature and the supplement industry have lagged the renaming — most product labels still use the historical Lactobacillus names. This deep-dive uses the traditional names because they are what consumers will see on labels, but be aware that scientific literature increasingly uses the new genus names.
The Strain-by-Condition Evidence Map
The following table summarizes the strain-by-condition evidence in clinical use. For each indication, the strains with the strongest randomized-trial evidence are listed.
- Antibiotic-associated diarrhea (AAD) prevention: Lactobacillus rhamnosus GG, Saccharomyces boulardii CNCM I-745
- Clostridioides difficile infection (CDI) prevention: S. boulardii CNCM I-745, L. rhamnosus GG, a three-strain formula (L. acidophilus CL1285 + L. casei LBC80R + L. rhamnosus CLR2)
- Irritable bowel syndrome (IBS): Bifidobacterium longum subsp. infantis 35624, Lactobacillus plantarum 299v, S. boulardii
- Pouchitis (maintenance of remission): a high-dose 8-strain mixture at 900 billion CFU/day
- Ulcerative colitis (mild-moderate, maintenance): Escherichia coli Nissle 1917
- Atopic eczema prevention (high-risk infants): L. rhamnosus GG, L. rhamnosus HN001
- Infant colic (breastfed infants): Lactobacillus reuteri DSM 17938
- Upper respiratory infection prevention: L. rhamnosus GG, L. casei Shirota, Bifidobacterium animalis subsp. lactis Bi-07
- Vaginal dysbiosis and bacterial vaginosis: L. rhamnosus GR-1 + L. reuteri RC-14
- Helicobacter pylori eradication adjunct: L. reuteri DSM 17938, S. boulardii
- Traveler's diarrhea prevention: S. boulardii
- Postpartum depression reduction: L. rhamnosus HN001
- Depression / anxiety adjunct: L. helveticus R0052 + B. longum R0175, B. longum NCC3001
- Stress / cognition: B. longum 1714
For each entry, the strain (not just the species) is what matters. L. rhamnosus GG is not L. rhamnosus HN001. B. infantis 35624 is not interchangeable with other "B. infantis" preparations. L. reuteri DSM 17938 is the strain that has the colic and the H. pylori evidence; other L. reuteri strains may or may not produce the same effects.
CFU Counts and Dose Thresholds
Probiotic doses are expressed in colony-forming units (CFU), a measure of the number of viable organisms in the dose. Modern probiotic products typically range from 1 billion to 200 billion CFU per dose, with some megadose products advertising 1 trillion CFU. The dose-response relationship is real but nonlinear and condition-specific.
General principles from the clinical trial literature:
- Less than 1 billion CFU: typically insufficient for measurable clinical effect, with rare exceptions like L. reuteri DSM 17938 in infant colic (100 million CFU/day is the trial-validated dose) and B. infantis 35624 in IBS (100 million CFU/day)
- 1-10 billion CFU/day: a reasonable lower-end dose for general gut-health support; insufficient for most specific clinical indications based on trial doses
- 10-50 billion CFU/day: the typical dose range for the strongest probiotic indications — AAD prevention, atopic eczema prevention, IBS treatment, upper respiratory infection prevention. Most validated indications use doses in this range.
- 100+ billion CFU/day: used for the high-dose 8-strain mixture in pouchitis (900 billion CFU/day) and for some critical-care / IBD indications; not necessary for most outpatient applications
"More CFU is better" is not generally true. Higher doses do not produce proportionally larger effects in most indications, and very high doses may produce side effects (bloating, gas, transient diarrhea) without additional benefit. Match the dose to the trial-validated dose for the specific indication being targeted.
A critical caveat: the CFU count on the label is typically the count at the time of manufacture, not at the time of consumption. Live organism count drops over time due to ambient temperature exposure, especially if the product is not refrigerated. A bottle labeled "10 billion CFU" may contain 1-3 billion CFU by the time the consumer takes the last capsule near the end of the bottle's shelf life. The AGA recommends labeling that guarantees the CFU count "through expiration" rather than just at manufacture.
Refrigerated vs Shelf-Stable Formulations
Refrigerated probiotic products were historically considered superior because cold storage extends the viability of most Lactobacillus and Bifidobacterium strains. Many refrigerated product lines promote refrigeration as a quality differentiator.
The newer shelf-stable formulations use one or more of the following strategies to maintain viability without refrigeration:
- Lyophilization with cryoprotectants — freeze-drying with trehalose, skim milk, or other protective excipients that preserve the freeze-dried cell wall during ambient storage
- Moisture-impermeable blister packs — aluminum/plastic foil packaging that prevents humidity exposure (the proximate cause of most ambient-temperature viability loss)
- Spore-forming organisms — Bacillus coagulans, Bacillus subtilis, and other spore-formers are intrinsically heat- and humidity-stable in their spore form, germinating in the gut
- Yeast probiotics — S. boulardii as a yeast is more robust than most lactic acid bacteria for ambient storage
What the stability picture shows: refrigeration still gives the most margin for traditional Lactobacillus and Bifidobacterium formulations, especially where a product has no extensive stability testing. Shelf-stable products with documented stability testing through expiration hold their labeled counts, which matters most for travel. Shelf-stable products with no strain-level disclosure and no documented stability testing give no way to know what survives to the expiration date.
Enteric Coating and Gastric Survival
Gastric acid is the first major challenge facing an ingested probiotic. Gastric pH in the fasting state is around 1.5-2; in the postprandial state it rises to around 4-5. Most Lactobacillus and Bifidobacterium strains have limited acid tolerance — survival through the stomach is typically estimated at 1-10%, with substantial strain variation. Bile acid exposure in the duodenum kills additional organisms.
Strategies that improve gastric survival include:
- Taking with food — food buffers gastric acid and the probiotic gets through more easily. Most trials of L. rhamnosus GG and similar strains used dosing with meals.
- Enteric coating — capsules with a pH-sensitive polymer (typically acrylic-based) that resists gastric acid and dissolves at duodenal pH (~6). Several probiotic products use enteric-coated capsules with documented improved survival.
- Acid-resistant strains — some strains have intrinsic acid tolerance (L. rhamnosus GG, L. acidophilus, S. boulardii, all Bacillus spore-formers). Choosing these strains can be as effective as enteric coating.
The transient-passage paradigm developed by Sonnenburg, Knight, Zmora, and others reframes the survival question. Most probiotic strains do not permanently colonize the gut even when delivered in high numbers. They pass through over a few days, exerting effects during transit, and then leave. Whether 1% or 10% of dosed organisms survive the stomach matters less than whether the surviving fraction is high enough (and stays present for long enough) to deliver the intended signaling effect. For most indications, the trial-validated dose has been picked to deliver adequate live organisms past the stomach in the typical patient; you do not need to over-engineer the delivery further.
Single-Strain vs Multi-Strain Formulas
The supplement industry has moved heavily toward multi-strain formulations, often listing 10-20 different strains in a single product with marketing language about "broad-spectrum support" or "comprehensive microbiome diversity." The clinical evidence is more nuanced.
Arguments for multi-strain formulas:
- Different strains have different mechanisms and target different conditions; a multi-strain formula provides more functional coverage
- The colonic microbiome naturally contains hundreds of species; restoring complexity may require multi-component intervention
- Some specific multi-strain formulations (the high-dose 8-strain mixture for pouchitis; the three-strain L. acidophilus CL1285 + L. casei LBC80R + L. rhamnosus CLR2 formula for CDI prevention) have positive trial evidence that no single-strain alternative can match
Arguments for single-strain formulas:
- The strongest clinical evidence in most indications is for specific single strains, not for multi-strain blends
- Manufacturer-blended multi-strain products often lack any clinical trial validation of the specific combination at the specific doses used
- Different strains may compete with each other in the gut, reducing the dose of each strain that actually engages with the host
- The CFU count of a multi-strain product is typically divided across the strains, so the dose of any one trial-validated strain may be subtherapeutic
Where the evidence sits: for a specific clinical indication, the trial evidence is for single strains or for particular multi-strain products tested in that indication. For general "gut support" or "microbiome diversity" maintenance in healthy adults, multi-strain formulas are widely used but the evidence base is weaker than for targeted use.
Spore-Based Probiotics (Bacillus coagulans, B. subtilis)
Spore-forming probiotics — Bacillus coagulans GBI-30 6086, Bacillus subtilis DE111, Bacillus clausii — have grown rapidly in market share over the past decade. The spore form is a dormant, environmentally resistant cell that survives heat, humidity, and gastric acid much better than vegetative Lactobacillus cells. Spores germinate in the small intestine, becoming metabolically active vegetative cells that exert probiotic effects for the duration of transit, then sporulate again or die in the colon.
Advantages of spore-based probiotics:
- Excellent shelf stability at ambient temperature without refrigeration
- Very high gastric survival rates (>90% in some studies) compared to Lactobacillus/Bifidobacterium
- Can be added to food products (baked goods, beverages, protein bars) and survive processing
- Long expiration dates and consistent dosing throughout the bottle
The clinical evidence is growing but generally smaller than for traditional Lactobacillus/Bifidobacterium strains. Bacillus coagulans GBI-30 has trial evidence in IBS, post-exercise recovery, and immune support; B. subtilis DE111 in functional bowel symptoms and athletic performance; B. clausii as a long-standing pediatric diarrhea treatment in Europe. For most validated indications (AAD prevention, CDI prevention, IBS first-line probiotic, atopic eczema), the traditional Lactobacillus/Bifidobacterium/S. boulardii strains still have the strongest evidence base.
A caution: not all Bacillus species are safe as probiotics. Bacillus cereus in particular is a known foodborne pathogen producing emetic and diarrheal toxins, and contamination of probiotic products with B. cereus has been documented. Species-identification testing of the finished product is the check that detects this kind of contamination.
Saccharomyces boulardii — The Only Yeast Probiotic
Saccharomyces boulardii CNCM I-745 is uniquely useful in the probiotic toolkit because it is a yeast, not a bacterium. This single biological fact produces several practical consequences that distinguish it from all other probiotics.
The key consequences:
- Unaffected by antibiotics — antibacterial antibiotics do not kill yeasts. This means S. boulardii can be taken concurrently with antibiotic therapy without any 2-hour-apart timing concern that applies to Lactobacillus/Bifidobacterium. This is the key advantage for AAD and CDI prevention.
- Cannot permanently colonize — as a non-native organism that does not establish in the gut, S. boulardii always clears within 3-5 days after the last dose. This is a feature for indications where you want a defined intervention period.
- Directly cleaves C. difficile toxin A — S. boulardii produces a 54-kDa protease that cleaves both C. difficile toxin A and the toxin's epithelial receptor, providing dual protection against the most severe CDI complication
- Trophic effect on enterocytes — S. boulardii produces a 120-kDa protein that increases brush-border enzyme expression and accelerates enterocyte renewal, with measurable effects on intestinal villous height and absorptive surface area
- Trial evidence in CDI, AAD, traveler's diarrhea, H. pylori adjunct, IBS, and acute infectious diarrhea — the broadest evidence base of any single probiotic strain
The standard dose is 250 mg twice daily (each 250 mg capsule contains approximately 5 billion CFU), for the duration of antibiotic exposure plus 1-2 weeks afterward in AAD/CDI prevention, or for 4 weeks in IBS, or for the duration of travel plus 1-2 days in traveler's diarrhea prevention.
The contraindications are specific: severely immunocompromised patients and patients with central venous catheters in place have a small risk of S. boulardii fungemia, which has been documented in case reports. The Yelin 2019 study found probiotic-derived bloodstream infections in ICU patients, including S. boulardii cases. The risk is low but not zero, and the strain should be avoided in these populations.
The Zmora Personalized Response Finding
The 2018 Zmora N et al. Cell paper from the Elinav lab in Israel reframed how researchers think about probiotic colonization. The investigators gave a standard 11-strain multi-strain probiotic to healthy volunteers and then directly sampled the mucosal microbiome via colonoscopy and upper endoscopy — not stool, which is just the lumen contents.
The findings were striking. Volunteers fell into two clear groups:
- "Permissive" hosts (about half of subjects) — the probiotic strains successfully colonized the gut mucosa, persisted for weeks, and produced measurable changes in gene expression and metabolite production
- "Resistant" hosts (about half of subjects) — the probiotic strains were excluded by the host's existing microbiome; the strains transited through the lumen but did not colonize the mucosa
The host features that predicted resistance vs permissiveness included baseline microbiome composition, baseline immune gene expression in the gut mucosa, and host genetic factors. Stool sampling completely missed the difference — probiotic strains showed up in stool from both groups, even though only one group had actual mucosal colonization.
The implication is that probiotic response is highly individual, and that "trying a strain for a few weeks and seeing if it helps" is the rational empirical approach for many indications. A strain with good population-level trial evidence may not work for any individual patient if they happen to be in the resistant phenotype. Conversely, an individual patient may have a strong response to a strain that has only modest population-level evidence.
A second Zmora-lab finding from the same 2018 issue of Cell: in patients given a course of antibiotics followed by probiotic supplementation, the probiotic supplementation actually delayed the recovery of the native microbiome compared to no intervention or autologous fecal microbiota transplant. This is a counterintuitive result and is part of the reason for continued caution around routine probiotic use after antibiotic courses without a specific indication beyond AAD prevention.
Regulatory Wild-West and Quality Control
In the United States, probiotics are regulated as dietary supplements under the 1994 Dietary Supplement Health and Education Act (DSHEA), which means the FDA does not require pre-market approval of efficacy or safety for the specific product. Manufacturers are required to follow Good Manufacturing Practices (GMP), to make truthful and non-misleading label claims, and to ensure the product is safe — but the enforcement model is largely reactive (FDA acts on reports of harm) rather than proactive.
The consequence is real quality variability. Independent testing organizations have repeatedly documented probiotic products that:
- Contain fewer CFU than labeled (sometimes orders of magnitude fewer)
- Contain different strains than labeled
- Contain undeclared contaminating organisms
- Have lost most viability before reaching the consumer due to shipping or storage conditions
- Use generic strain names ("Lactobacillus acidophilus") without disclosing the actual strain identifier, making it impossible to know if the product is the trial-validated strain or a different strain marketed under the species name
The quality markers that testing and label review look at:
- Strain-level labeling — a label that discloses the specific strain identifier (e.g., "Lactobacillus rhamnosus GG", not just "Lactobacillus rhamnosus") is the only way to match a product to the trial-validated strain
- Third-party certification — NSF certification, USP verification, or published independent testing
- "Guaranteed CFU through expiration" — rather than only "at time of manufacture"
- Single-purpose versus generic blends — for specific clinical indications, the trial evidence is for specific strains rather than generic multi-strain blends
Strains and Doses Studied by Clinical Goal
The following summarizes the strains, doses and durations described in the research for common clinical goals. A product is matched to this evidence by the strain identifier on its label, whoever makes it. Decisions about probiotics, especially for infants, pregnancy and hospital patients, belong with a clinician.
- Preventing AAD during an antibiotic course → Saccharomyces boulardii 250 mg twice daily, started on day 1 of antibiotics and continued 1 week after antibiotics finish. S. boulardii is favored over Lactobacillus in this setting because it is a yeast and is unaffected by the antibiotic.
- Preventing CDI in hospitalized patients on antibiotics → S. boulardii 250 mg twice daily, or a high-dose Lactobacillus/Bifidobacterium multi-strain formula at >10 billion CFU/day, started within 48 hours of the first antibiotic dose
- IBS with bloating and abdominal pain → Bifidobacterium longum subsp. infantis 35624, one daily dose over a 4-week trial period; when it clearly helps it is continued, and when it does not, other strains or other interventions come into consideration.
- Frequent URIs in a child (preschool or early school age) → Lactobacillus rhamnosus GG 10 billion CFU/day during URI season (October-March in most temperate climates)
- Eczema prevention in a high-risk infant (family history of atopy) → maternal L. rhamnosus GG 10 billion CFU/day during third trimester and breastfeeding; or direct infant L. rhamnosus GG 10 billion CFU/day for first 6 months
- Colic in a breastfed infant → L. reuteri DSM 17938, 5 drops daily, with benefit reported at 2-3 weeks
- Bacterial vaginosis recurrence prevention → L. rhamnosus GR-1 + L. reuteri RC-14, 1-2 capsules daily, orally; this colonizes the vagina via the gut-vaginal axis
- Low mood / mild depression, as adjunct support → L. helveticus R0052 + B. longum R0175, 1 dose daily for 8 weeks; see the mental-health deep-dive for the broader psychobiotic discussion
- Traveler's diarrhea on a trip to a high-risk destination → S. boulardii 250 mg twice daily, starting 5 days before travel and continuing through the trip plus 2 days after
- General "support" with no specific indication → this is the weakest use case for probiotics. Fermented foods (yogurt, kefir, sauerkraut, kimchi) are a richer source of live organisms; see the Fermented Foods Benefits hub.
Key Research Papers
- Hill C et al. (2014). Expert consensus document: The International Scientific Association for Probiotics and Prebiotics consensus statement on the scope and appropriate use of the term probiotic. Nature Reviews Gastroenterology & Hepatology. — PubMed
- Sniffen JC et al. (2018). Choosing an appropriate probiotic product for your patient: an evidence-based practical guide. PLOS ONE. — PubMed PMID: 30586435
- Zmora N et al. (2018). Personalized gut mucosal colonization resistance to empiric probiotics is associated with unique host and microbiome features. Cell. — PubMed PMID: 30193112
- Suez J et al. (2018). Post-antibiotic gut mucosal microbiome reconstitution is impaired by probiotics and improved by autologous FMT. Cell. — PubMed PMID: 30193113
- Sanders ME (2008). Probiotics: definition, sources, selection, and uses. Clinical Infectious Diseases. — PubMed PMID: 18181724
- Whorwell PJ et al. (2006). Efficacy of an encapsulated probiotic Bifidobacterium infantis 35624 in women with irritable bowel syndrome. American Journal of Gastroenterology. — PubMed PMID: 16863564
- Capurso L (2019). Thirty years of Lactobacillus rhamnosus GG: a review. Journal of Clinical Gastroenterology. — PubMed PMID: 30741841
- McFarland LV, Bernasconi P (1993). Saccharomyces boulardii: a review of an innovative biotherapeutic agent. Microbial Ecology in Health and Disease. — PubMed
- Konuray G, Erginkaya Z (2018). Potential use of Bacillus coagulans in the food industry. Foods. — PubMed PMID: 29899254
- Salminen S et al. (2021). The International Scientific Association of Probiotics and Prebiotics (ISAPP) consensus statement on the definition and scope of postbiotics. Nature Reviews Gastroenterology & Hepatology. — PubMed
- Zheng J et al. (2020). A taxonomic note on the genus Lactobacillus: description of 23 novel genera. International Journal of Systematic and Evolutionary Microbiology. — PubMed PMID: 32293557
- Yelin I et al. (2019). Genomic and epidemiological evidence of bacterial transmission from probiotic capsule to blood in ICU patients. Nature Medicine. — PubMed PMID: 31700189
PubMed Topic Searches
Connections
- All Food
- Probiotics Overview
- Probiotics Benefits Hub
- Probiotics for Gut Health
- Probiotics for Immune Function
- Mental Health and Gut-Brain Axis
- Fermented Foods
- Probiotic Strains in Fermented Foods
- Resistant Starches (Prebiotic Substrate)
- Gut Healing
- Irritable Bowel Syndrome
- SIBO
- Crohn's Disease
- Ulcerative Colitis
- Eczema
- Yogurt
- Kefir
- Kimchi
- History