⚠ Evidence warning: Clinical trials or other evidence do not support the claims that resistant starch brings modest but consistent decreases in visceral fat and that long-term use is associated with reduced colorectal cancer risk in multiple populations. This page keeps it as a report of what people, websites or other media say.
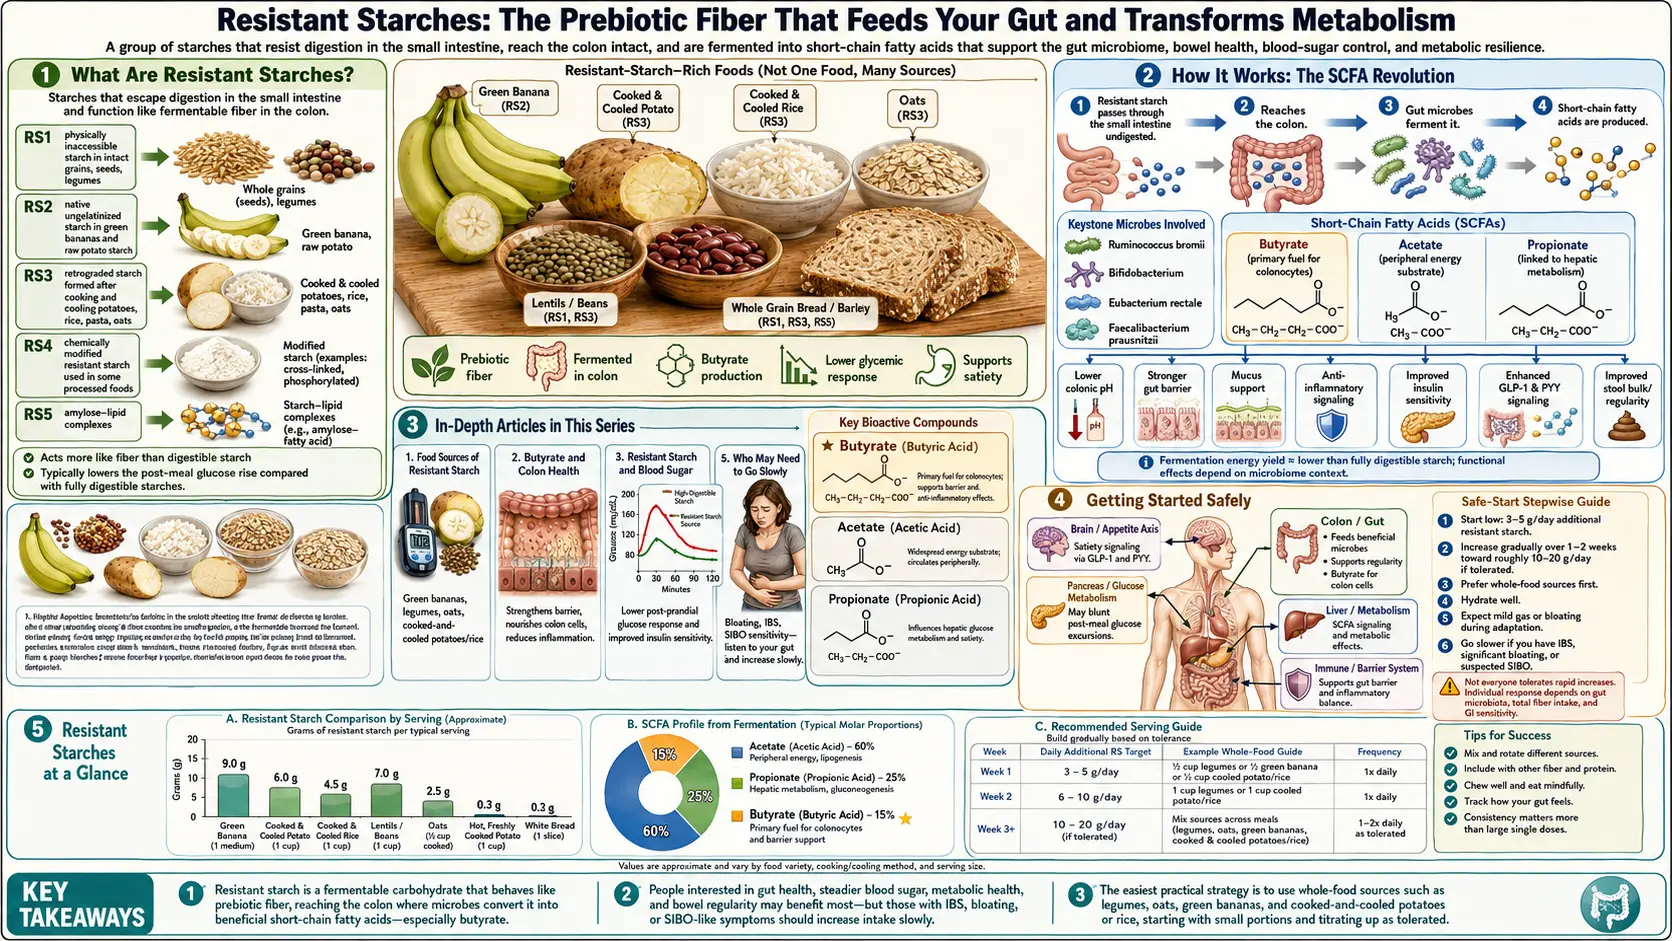
Resistant Starches: The Prebiotic Fiber That Feeds Your Gut and Transforms Metabolism

Resistant starch is the carbohydrate nutrition science forgot and is now frantically rediscovering. Unlike the starches in white bread or mashed potatoes that are rapidly broken down into glucose in your small intestine, resistant starch does exactly what its name suggests: it resists digestion. It passes through the stomach and small intestine untouched, arriving intact in the colon, where trillions of bacteria ferment it into short-chain fatty acids (SCFAs) — butyrate, acetate, and propionate — that feed the gut lining, quiet systemic inflammation, reshape insulin sensitivity, and silently reconfigure metabolism from the bottom up. The average Western diet supplies only about 3–5 grams of resistant starch per day. Human ancestors likely consumed 30–50 grams. Closing that gap may be one of the highest-leverage, lowest-cost interventions available for gut health, liver health, metabolic disease, and long-term weight regulation.
Table of Contents
1. What Resistant Starches Are
A resistant starch is any starch — or starch-degradation product — that escapes digestion in the small intestine of healthy people and reaches the colon, where it becomes fermentable substrate for gut microbes. Functionally, resistant starch behaves like a soluble, fermentable dietary fiber, even though chemically it is still a starch (a polymer of glucose). The concept was formalized by Hans Englyst and John Cummings in the 1980s when they noticed that laboratory starch-digestion assays consistently underestimated how much starch actually reached the terminal ileum in humans. That "missing" starch was the resistant fraction, and it turned out to be the most metabolically interesting part of the carbohydrate on your plate.
Resistant starch is not a single molecule but a structural category. Whether a starch is resistant depends on the physical architecture of the food, the ratio of amylose to amylopectin, the presence of intact cell walls, and crucially the temperature history of the food (whether it has been cooked, cooled, reheated, or eaten raw).
2. The Five Types of Resistant Starch
Researchers classify resistant starch into five subtypes, each formed by a different mechanism:
- RS1 — Physically inaccessible. Starch trapped inside intact plant cell walls, as in whole or coarsely milled grains, seeds, and legumes. Chewing and milling release it; fine flour destroys it.
- RS2 — Native granular. Raw starch granules with a crystalline structure that digestive enzymes cannot penetrate. Found in raw potatoes, raw potato starch, green (unripe) bananas, banana flour, and high-amylose maize starch.
- RS3 — Retrograded. Starch that was gelatinized by cooking and then recrystallized upon cooling. This is why a cold potato salad contains substantially more resistant starch than a fresh baked potato, and why yesterday's rice, reheated, still carries more RS than rice freshly cooked.
- RS4 — Chemically modified. Starches altered by cross-linking or esterification in food manufacturing. Found in many processed foods as an added fiber ingredient.
- RS5 — Amylose-lipid complex. Starch molecules bound to fatty acids, forming helical structures that resist digestion. Formed naturally during cooking of high-amylose grains in the presence of oils.
RS1, RS2, and RS3 are the forms most people can meaningfully increase through ordinary food choices — which is the focus of this series.
3. How It Works: The Short-Chain Fatty Acid Revolution
When resistant starch reaches the colon, fermentation by bacteria — particularly Ruminococcus bromii, Bifidobacterium adolescentis, Faecalibacterium prausnitzii, and Eubacterium rectale — produces short-chain fatty acids in roughly this proportion: 60% acetate, 20% propionate, 20% butyrate. Resistant starch is an unusually efficient butyrogenic substrate, meaning it drives butyrate production higher than almost any other fiber.
Butyrate is the primary energy source for the cells lining your colon (colonocytes), supplying roughly 70% of their energy needs. Well-fed colonocytes maintain a tight epithelial barrier, suppress inflammatory signaling, and starve pathogenic bacteria of the oxygen they need to overgrow. Butyrate also acts as a histone deacetylase (HDAC) inhibitor, influencing gene expression throughout the body, and activates AMP-activated protein kinase (AMPK), the master metabolic switch that shifts cells toward fat oxidation and away from lipid storage. Propionate travels through the portal vein to the liver, where it suppresses hepatic de novo lipogenesis. Acetate enters systemic circulation and helps regulate appetite via central signaling.
Through these pathways, a simple prebiotic carbohydrate ends up touching the liver, the pancreas, adipose tissue, the immune system, and the brain.
4. Key Health Benefits at a Glance
- Improved insulin sensitivity. In a 4-week trial in 10 healthy people, 30 g/day raised insulin sensitivity (Robertson 2005). In insulin-resistant adults, 40 g/day improved insulin sensitivity over 12 weeks (Johnston 2010, 20 people) and improved insulin resistance in muscle and fat tissue but not in the liver over 8 weeks (Robertson 2012, 15 people).
- Lower fasting glucose and post-meal glucose. A "second-meal effect": resistant starch eaten at breakfast reduces glucose response to lunch.
- Reduced liver fat. In a 4-month randomized trial in people with non-alcoholic fatty liver disease (99 on resistant starch, 97 controls), liver fat fell by 9.08 percentage points more than in the control group, or 5.89 points after allowing for weight loss (Ni 2023). In the 12-week Johnston 2010 trial, 40 g/day did not significantly change liver fat.
- Visceral fat. Modest but consistent decreases in visceral adipose tissue. The Keenan 2015 review describes reduced abdominal fat in rodent studies. In the Johnston 2010 human trial, 40 g/day for 12 weeks did not significantly change body weight or visceral fat.
- Stronger gut barrier and reduced inflammation. Increased tight-junction integrity, lower systemic lipopolysaccharide (LPS).
- Enhanced satiety. Higher glucagon-like peptide-1 (GLP-1) and peptide YY (PYY) release is the proposed route to reduced appetite and calorie intake. The Keenan 2015 review reports raised GLP-1 in rodent studies, but only 1 of several human studies found an increase in serum GLP-1.
- Cancer prevention research. The butyrate story is strongest here — long-term adherence is associated with reduced colorectal cancer risk in multiple populations. Butyrate is the proposed protective route. In the long-term CAPP2 randomized trial in people with Lynch syndrome (an inherited high cancer risk), 30 g/day for up to 4 years made no difference to colorectal cancer incidence over up to 20 years of follow-up, but fewer people developed other Lynch-syndrome cancers (27 vs 48), most clearly cancers of the upper digestive tract (Mathers 2022).
- Bifidogenic effect. Selectively feeds beneficial gut species; tends to reduce pathobiont abundance.
5. In-Depth Articles in This Series
This hub links to four focused deep-dives. Each is self-contained and citation-heavy; start with whichever topic matters most to you.
- Resistant Starches and the Gut Microbiome — How RS reshapes the microbial ecosystem, why Ruminococcus bromii is the keystone degrader, and what short-chain fatty acid (SCFA) production means for gut barrier function, inflammation, and the gut-brain axis.
- Resistant Starches for Fatty Liver Disease — Non-alcoholic fatty liver disease (NAFLD), also called metabolic dysfunction-associated steatotic liver disease (MASLD): the gut-liver axis, how short-chain fatty acids reach the liver via the portal vein, and what human trials tell us about alanine aminotransferase (ALT)/aspartate aminotransferase (AST), liver fat fraction, and insulin sensitivity.
- Resistant Starches and Visceral Fat Reduction — Why visceral adipose is the dangerous kind, how short-chain fatty acids drive glucagon-like peptide-1 / peptide YY satiety signaling, and what realistic expectations look like for body composition.
- Foods Highest in Resistant Starch — A practical, table-driven guide to reaching 30 g/day from whole foods: green bananas, cooked-and-cooled potatoes and rice, lentils, oats, and more.
6. How Much Resistant Starch Is Used
The modern Western intake averages 3–5 grams per day. The dose used in most clinical trials to produce metabolic benefits is 15–40 grams per day. Practitioners commonly describe 20–30 grams per day as a gut-health target, reachable from whole foods with modest reorganization of meals: a daily serving of lentils or beans, cooled potatoes or rice folded into at least one meal, a green banana or a tablespoon of green banana flour in a smoothie, and steel-cut oats. See the food list for exact numbers and serving sizes.
7. Tolerance and Safety
Resistant starch is generally very well tolerated, but the microbiome takes time to adapt. Sudden large doses in a gut that has been eating low-fiber for years will usually produce bloating, gas, and cramping — the common reason people dismiss prebiotics after a single experiment. Practitioners describe ramping up gradually over 2–4 weeks, starting at 5 g/day and adding 5 g every 3–5 days as tolerated. In people with small intestinal bacterial overgrowth (SIBO), active irritable bowel syndrome (IBS) flare-ups, or advanced cirrhosis, resistant starch and other fermentable fiber can transiently worsen symptoms when fermentation occurs in the wrong location or at the wrong rate.
IMPORTANT: This information is educational: it reports what studies, practitioners and food data describe. The main known side effects are the bloating, gas and cramping described above.
Key Research Papers
- Englyst HN, Kingman SM, Cummings JH. Classification and measurement of nutritionally important starch fractions. Eur J Clin Nutr. 1992;46 Suppl 2:S33-50. — PubMed PMID: 1330528
- Birt DF, Boylston T, Hendrich S, et al. Resistant starch: promise for improving human health. Adv Nutr. 2013;4(6):587-601. — PubMed PMID: 24228189
- Topping DL, Clifton PM. Short-chain fatty acids and human colonic function: roles of resistant starch and nonstarch polysaccharides. Physiol Rev. 2001;81(3):1031-64. — PubMed PMID: 11427691
- Robertson MD, Bickerton AS, Dennis AL, Vidal H, Frayn KN. Insulin-sensitizing effects of dietary resistant starch and effects on skeletal muscle and adipose tissue metabolism. Am J Clin Nutr. 2005;82(3):559-67. — PubMed PMID: 16155268
- Ze X, Duncan SH, Louis P, Flint HJ. Ruminococcus bromii is a keystone species for the degradation of resistant starch in the human colon. ISME J. 2012;6(8):1535-43. — PubMed PMID: 22343308
- Bindels LB, Walter J, Ramer-Tait AE. Resistant starches for the management of metabolic diseases. Curr Opin Clin Nutr Metab Care. 2015;18(6):559-65. — PubMed PMID: 26406392
- Keenan MJ, Zhou J, Hegsted M, et al. Role of resistant starch in improving gut health, adiposity, and insulin resistance. Adv Nutr. 2015;6(2):198-205. — PubMed PMID: 25770258
- Johnston KL, Thomas EL, Bell JD, Frost GS, Robertson MD. Resistant starch improves insulin sensitivity in metabolic syndrome. Diabet Med. 2010;27(4):391-7. — PubMed PMID: 20536509
- Robertson MD, Wright JW, Loizon E, et al. Insulin-sensitizing effects on muscle and adipose tissue after dietary fiber intake in men and women with metabolic syndrome. J Clin Endocrinol Metab. 2012;97(9):3326-32. — PubMed PMID: 22745235
- Mathers JC, Elliott F, Macrae F, et al. Cancer Prevention with Resistant Starch in Lynch Syndrome Patients in the CAPP2-Randomized Placebo Controlled Trial: Planned 10-Year Follow-up. Cancer Prev Res (Phila). 2022;15(9):623-634. — PubMed PMID: 35878732
- Ni Y, Qian L, Siliceo SL, et al. Resistant starch decreases intrahepatic triglycerides in patients with NAFLD via gut microbiome alterations. Cell Metab. 2023;35(9):1530-1547.e8. — PubMed PMID: 37673036
- Further reading: PubMed search: resistant starch microbiome
Connections
- All Food
- Prebiotics — where resistant starch fits among the prebiotic families
- Visceral Fat
- Fatty Liver Disease
- High Resistant Starch Foods
- High Resistant Starch Foods — food rankings by RS grams per serving, the cook-and-cool RS3 protocol, daily targets, and a sample meal plan hitting ~20g RS.
- Gut Microbiome
- Small Intestinal Bacterial Overgrowth
- Fermented Foods
- Probiotics
- Gut Healing
- Irritable Bowel Syndrome
- Bananas
- Lentils
- Oats
- Glucagon-Like Peptide-1 Receptor Agonists
- Gut-Brain Axis
- Fasting
- Insulin Resistance
- Nattokinase
- Dietary Fiber
Featured Videos