⚠ Evidence warning: Clinical trials or other evidence do not support the claim that sardine calcium avoids the absorption drop seen with calcium carbonate in older people and low stomach acid, and that food-matrix cofactors keep calcium out of arteries. This page keeps it as a report of what people, websites or other media say.
Sardines for Calcium & Bones from Whole Fish
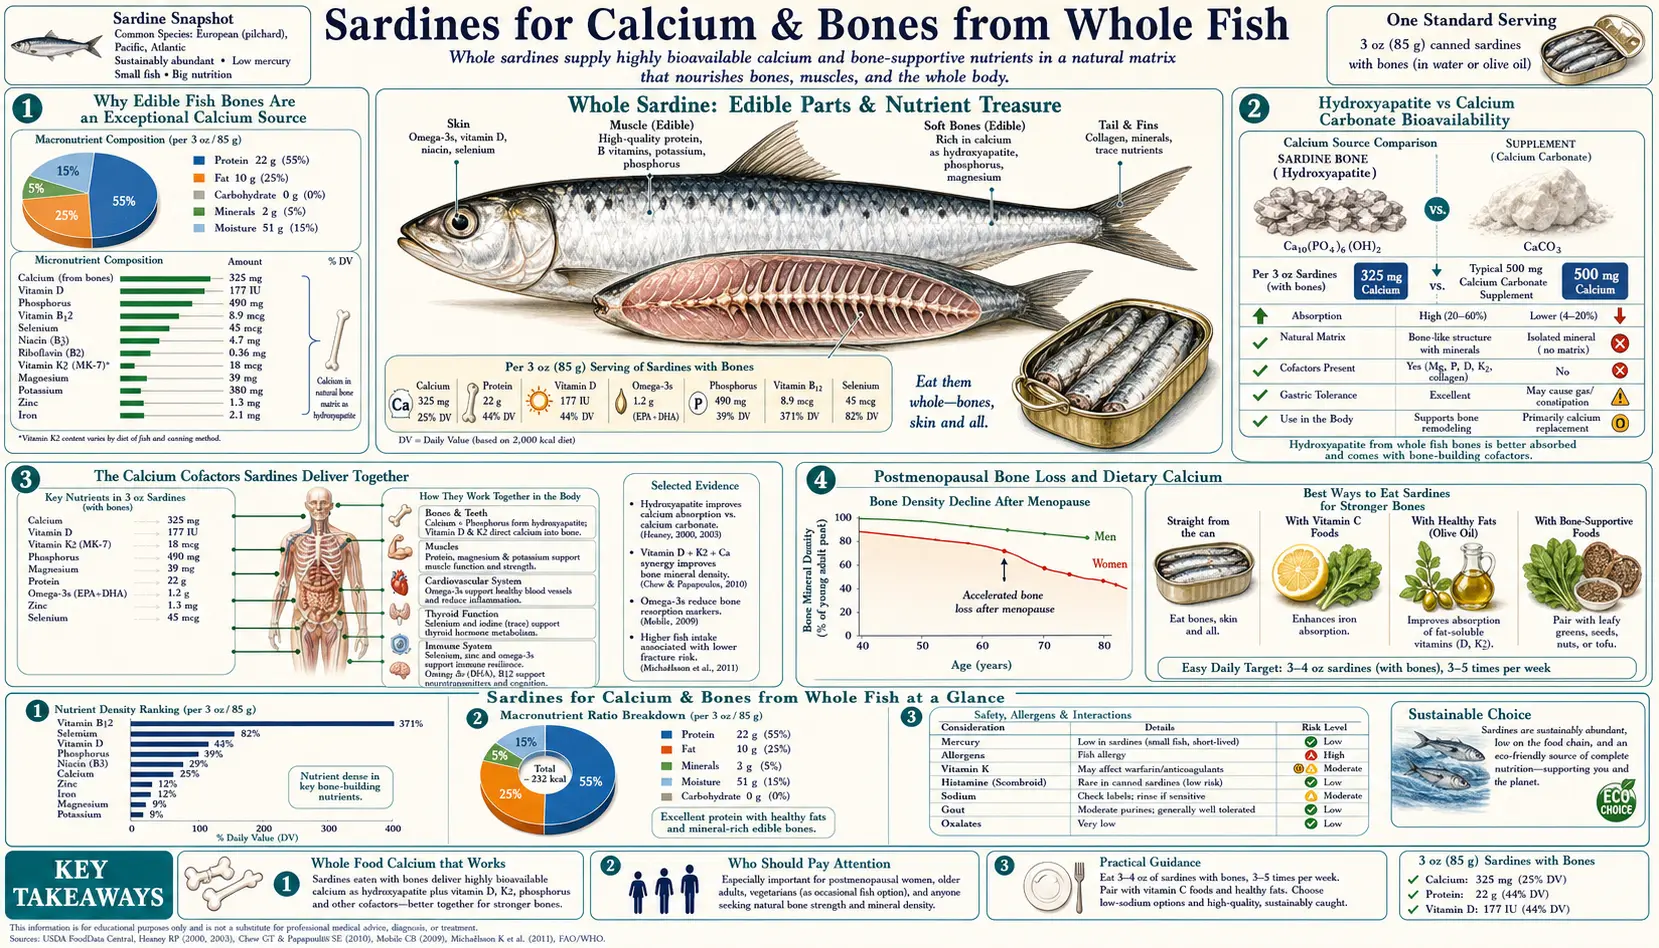
Sardines are unique among commonly consumed animal foods because their soft, fully-edible vertebrae and ribs deliver hydroxyapatite calcium — the same biological mineral matrix as human bone — in a form the digestive tract recognizes and absorbs efficiently. A single 3.75-ounce tin provides 351 mg of calcium (27% of the 1,300 mg FDA Daily Value), more than a cup of milk, alongside the Vitamin D3, magnesium, phosphorus, and Vitamin K2 cofactors that determine whether dietary calcium ends up mineralizing bone or calcifying arteries. For postmenopausal women, men over 70, patients with lactose intolerance, and anyone who cannot tolerate dairy, sardines are arguably the most efficient single-food strategy for meeting calcium needs without the cardiovascular risk signal associated with high-dose isolated calcium carbonate supplements.
Table of Contents
- Why Edible Fish Bones Are an Exceptional Calcium Source
- Hydroxyapatite vs Calcium Carbonate Bioavailability
- The Calcium Cofactors Sardines Deliver Together
- Postmenopausal Bone Loss and Dietary Calcium
- A Dairy-Free Calcium Strategy
- The Calcium Supplement Cardiovascular Controversy
- The Sardinian Blue Zone Pattern
- Practical Intake — How Many Tins per Week
- Cautions (Kidney Stones, Hyperparathyroidism)
- Key Research Papers
- Connections
- Featured Videos
Why Edible Fish Bones Are an Exceptional Calcium Source
The canning process for sardines — typically pressure-cooked at 115-121 °C for 60-90 minutes in sealed cans — thoroughly softens the vertebrae and ribs of the fish to the point where they become indistinguishable in texture from the surrounding flesh. The bones do not need to be removed, and most consumers do not even notice them in the final product. What they are eating is biological hydroxyapatite — the same calcium-phosphate mineral lattice that constitutes their own skeleton.
Hydroxyapatite (chemical formula Ca10(PO4)6(OH)2) is the dominant inorganic component of vertebrate bone. It is laid down on a collagen scaffold during ossification, providing the compressive strength of bone while collagen provides the tensile strength. When sardine bone is dissolved in gastric acid, the released calcium and phosphate ions enter the duodenum together, in roughly the correct stoichiometric ratio for bone mineralization, alongside intact collagen-derived peptides and bone-matrix proteins.
This is different from drinking milk (where calcium is bound to casein protein), eating dark leafy greens (where calcium is partially bound to oxalate and fiber), or taking a calcium carbonate or citrate supplement (where calcium is isolated and chemically defined). Each form has different absorption characteristics, and each interacts with different cofactor requirements. The fish-bone form is the closest dietary match to the body's actual bone-mineral chemistry.
Hydroxyapatite vs Calcium Carbonate Bioavailability
Calcium carbonate (the most common over-the-counter calcium supplement) requires significant gastric acid to dissolve. In healthy young adults with normal stomach acid, calcium carbonate absorption is roughly 25-30% when taken with food. In adults over 65 with reduced gastric acid (atrophic gastritis affects 25-30% of this population), or in patients on chronic proton pump inhibitor therapy (omeprazole, esomeprazole, pantoprazole, lansoprazole), calcium carbonate absorption can drop to 5-10% meaning most of the calcium passes through unabsorbed.
Calcium citrate (the second common supplement form) does not require gastric acid for dissolution and maintains 30-35% absorption regardless of stomach acid status. It is the supplement of choice for elderly patients and those on acid-suppression therapy.
In the Malde 2010 study, 10 healthy young men absorbed 22.5% of the calcium from enzyme-rinsed salmon bone and 21.9% from cod bone, against 27.4% from a calcium carbonate control. That study did not test sardines and had no older or low-stomach-acid group. Health writers also describe fish-bone calcium as better absorbed than calcium carbonate in older people, because the bone matrix appears to release calcium more gradually as it is digested, and as free of the absorption falloff at low stomach acid that supplemental calcium carbonate shows.
A second direct human test used small soft-boned Bengali fish eaten with their bones. In 19 healthy men and women aged 21 to 28, calcium absorption was 23.8% from the fish meal and 21.8% from a skimmed-milk meal, and the difference was not statistically significant (Hansen 1998).
More importantly, the calcium from sardines comes embedded in a complete bone-mineralization toolkit, which the next section addresses.
The Calcium Cofactors Sardines Deliver Together
Calcium absorption is only the first step. The body needs additional micronutrients to direct absorbed calcium to bone tissue rather than to arterial walls, kidney stones, or soft-tissue calcification. The four key cofactors are Vitamin D3 (calcium absorption and transport), magnesium (bone matrix formation), phosphorus (the other half of hydroxyapatite), and Vitamin K2 menaquinone (activates osteocalcin, which deposits calcium into bone, and activates matrix Gla protein, which removes calcium from arteries).
A single sardine tin delivers all four together:
- Vitamin D3 (cholecalciferol) — approximately 175 international units (IU) per tin, roughly 22% of the adult Recommended Dietary Allowance
- Magnesium — about 36 mg per tin (USDA lists 39 mg per 100 g, and a tin is 92 g), approximately 10% of adult Recommended Dietary Allowance
- Phosphorus — 451 mg per tin, approximately 36% of the 1,250 mg FDA Daily Value; by USDA's figures a tin holds more phosphorus than calcium (451 mg against 351 mg)
- Vitamin K2 menaquinone — small but non-zero amounts (K2 is produced by gut bacteria in the fish and concentrated in fatty tissues)
For Vitamin K2 specifically, fermented foods (natto, hard cheeses) and pasture-raised dairy and eggs are the dietary leaders, but oily fish does contribute. The combination of calcium, phosphorus, magnesium, and Vitamin D3 in sardines (alongside high-quality protein for the bone collagen matrix) is essentially a complete bone-formation package in a single shelf-stable food.
Contrast this with a calcium carbonate supplement: it provides calcium alone, with none of the cofactors. The Auckland Calcium Study (reported in 2008) and the 2010 Bolland et al. meta-analysis raised concerns that isolated calcium supplementation (1,000 mg/day in the Auckland trial, 500 mg/day or more in the meta-analysis) was associated with increased risk of myocardial infarction — possibly because the calcium pulse without K2 activation of matrix Gla protein contributed to arterial calcification rather than bone deposition. This concern, addressed in detail below, does not apply to food-source calcium because food sources deliver the calcium with its cofactors.
Postmenopausal Bone Loss and Dietary Calcium
Postmenopausal women lose approximately 1-2% of bone mineral density per year for the first 5-10 years after menopause, driven by the loss of estrogen's protective effect on osteoclast activity. Over a lifetime, this translates to a hip fracture risk of approximately 17-20% for a 50-year-old white woman.
Adequate dietary calcium does not stop this loss but slows it. The IOM recommends 1,200 mg/day of calcium for women over 50 and men over 70. The average American adult consumes 800-1,000 mg/day, leaving a 200-400 mg gap that needs to be closed through food or supplementation.
Two sardine tins per week deliver 700 mg of calcium — about 100 mg/day averaged across the week. Combined with the calcium already in a typical diet (dairy, leafy greens, beans, almonds, fortified plant milks), this can close the gap entirely for many adults without resorting to high-dose calcium supplements. The strategy of "food first, supplement only the gap" is the current expert consensus from the IOM and from clinical bone-density guidelines.
Combined with the omega-3, Vitamin D, and protein in the same food, sardines may provide additional bone-protective effects beyond calcium alone. Omega-3 fatty acids have been shown in observational studies to modestly reduce bone resorption markers. High-quality protein intake supports the collagen matrix of bone. The Mediterranean diet pattern, which features small oily fish prominently, is associated with reduced hip fracture risk: a 2025 meta-analysis of 8 studies (15 cohorts, 503,174 people) found a relative risk of 0.71 (95% confidence interval 0.55-0.91) with high adherence. It looked at the whole diet, and its abstract does not attribute the result to fish.
A Dairy-Free Calcium Strategy
For patients who cannot tolerate dairy — lactose intolerance (affecting roughly 65% of the global adult population), casein or whey allergy, A1-beta-casein sensitivity, or simple personal preference — obtaining adequate dietary calcium without dairy can be difficult. The major dairy-free calcium sources are:
- Canned sardines with bones — 351 mg per 3.75 oz tin
- Canned salmon with bones — 232 mg per 3 oz serving
- Tofu set with calcium sulfate — 253 mg per 1/2 cup (check the label; tofu set with magnesium chloride is much lower)
- Collard greens (cooked) — 268 mg per cup, but with oxalate that reduces absorption to ~5-15%
- Kale (cooked) — 94 mg per cup, low oxalate, ~50% absorbed
- Almonds — 76 mg per ounce
- Fortified plant milks — typically 300-450 mg per cup, similar absorption to dairy
- Sesame seeds / tahini — 88 mg per tablespoon of unhulled sesame
Sardines and canned salmon are the only dairy-free animal-source foods with substantial bioavailable calcium — both depend on the edible bones. For a lacto-free patient targeting 1,200 mg/day, a typical strategy is three sardine tins per week (averaging 150 mg/day), fortified plant milk in coffee and cereals (300 mg/day), kale or bok choy in regular meals (100 mg/day), and almonds or tahini as snacks (100 mg/day) — totaling 650 mg/day from food, with the remaining 550 mg closed by a 500 mg calcium citrate supplement split into two doses (calcium absorption peaks at single doses around 500 mg).
The Calcium Supplement Cardiovascular Controversy
The dispute has a clear timeline. In 2008, the Auckland Calcium Study (Bolland et al., BMJ) reported on 1,471 postmenopausal women, mean age 74, randomized to 1,000 mg/day calcium citrate or placebo for 5 years. The trial was primarily designed to assess bone density and fracture. Self-reported myocardial infarction (heart attack) was more common with calcium (45 events in 31 women vs 19 events in 14 women, p=0.01). After the events were checked against records, the count was 24 events vs 10 (relative risk 2.12, 95% confidence interval 1.01-4.47). When unreported events from the national hospital database were added, the relative risk was 1.49 (0.86-2.57), which is not statistically significant. The authors concluded there were “upward trends” in cardiovascular event rates.
In 2010 a meta-analysis by the same group pooled 15 trials of calcium supplements of at least 500 mg/day. The relative risk of myocardial infarction was 1.27 (1.01-1.59) across trials, and the hazard ratio was 1.31 (1.02-1.67) in the trials with patient-level data. Its conclusion applied to calcium supplements “without coadministered vitamin D”.
The mechanism is a proposed explanation, not a measured result. It holds that a large bolus of isolated calcium (1,000 mg taken at once as a tablet) produces a sudden serum calcium spike that the body's regulatory systems struggle to clear. Without simultaneous Vitamin K2 to activate matrix Gla protein (the molecular sponge that removes calcium from arterial walls), some of the excess calcium may deposit in atherosclerotic plaques and contribute to plaque instability.
The Women's Health Initiative reanalysis and several subsequent trials have produced more equivocal results, and the cardiovascular signal remains debated. Health writers often describe a conservative pattern: dietary calcium first, supplements only to close the gap to 1,200 mg/day, no more than 500 mg per single dose, and Vitamin K2 (90-180 mcg/day menaquinone-7, MK-7) for people on calcium supplements. They also say food-source calcium has not shown the cardiovascular signal and that the concern applies specifically to high-dose isolated supplements taken between meals.
Later reviews moved away from the alarm. In 2016 a guideline from the National Osteoporosis Foundation and the American Society for Preventive Cardiology took the position, on moderate-quality evidence, that calcium with or without vitamin D, from food or supplements, “has no relationship (beneficial or harmful)” to cardiovascular risk in generally healthy adults, and that intake not above the upper level of 2,000 to 2,500 mg/day “should be considered safe from a cardiovascular standpoint”. A 2023 meta-analysis of 12 randomized trials found calcium supplements were not associated with myocardial infarction, total stroke, heart failure admission, or death from heart disease or any cause, and its authors called for further study.
Sardines deliver calcium in food-matrix form alongside its cofactors, and they are described as a way to meet calcium needs without engaging the supplement-related cardiovascular concern. What is not known: no trial comparing sardine calcium with supplements on heart events was found for this page. For more on the bone-cardiovascular calcium routing problem, see our Vitamin K2 page and Morley Robbins protocol pages.
The Sardinian Blue Zone Pattern
Sardinia, the Italian island, is one of the five recognized Blue Zones — geographic regions with unusually high concentrations of centenarians (people living to 100+ years). The Ogliastra and Barbagia regions of central Sardinia have the highest documented density of male centenarians in the world (approximately 30 per 100,000 vs the European average of 5 per 100,000).
Popular accounts describe the traditional Sardinian diet as plant-based with regular small oily fish, and sardines share their name with the island. The researchers who study its long-lived mountain population describe something different. A 2015 review says this population “depended mostly upon livestock rearing”, ate relatively more animal-derived foods than the rest of the island, and kept a traditional diet “based on cereal-derived foods and dairy products”. A 2020 survey of 150 very old people in Ogliastra found a plant-based diet with dairy, and reported that fish “was very scarce”. Local diet patterns also feature pecorino sheep cheese (rich in calcium and Vitamin K2 from grass-fed sheep), grass-fed lamb and goat, fava beans, whole-grain sourdough bread, garden tomatoes, and Cannonau wine. The intake pattern is pastoral, with a Sardinian emphasis on cereals and dairy.
Researchers have proposed multiple hypotheses for the Sardinian centenarian phenomenon — founder genetic effects, social cohesion, physical activity from shepherding, lower stress, the wine pattern — but the consistent micronutrient density of the food pattern, including calcium-rich grass-fed sheep dairy, is plausibly one contributor. The 2004 study that mapped the zone says the mechanism “remains unknown” and offers a genetic hypothesis: frequent marriage between relatives and low immigration may have favored protective genes. Sardinian women, who do not typically participate in shepherding labor, have a less dramatic centenarian density than men, which has been interpreted as evidence that activity and social factors contribute alongside diet.
Popular writing treats small oily fish as a signature feature of populations with favorable longevity outcomes. The Sardinian surveys above do not show this, because fish was scarce in the people studied, and the 2020 authors say prospective studies are still needed to test cause and effect.
Practical Intake — How Many Tins per Week
Health writers commonly describe 2-4 tins of sardines per week for adults interested in bone health. The U.S. Food and Drug Administration (FDA) lists sardine as a "Best Choice" fish (its lowest-mercury tier), and its advice for pregnancy and breastfeeding gives 2-3 servings per week from that list, with one serving being 4 ounces. There is no widely-recognized upper limit other than overall caloric and sodium considerations.
Patterns health writers describe (not trial-tested regimens):
- Postmenopausal women on bone-density follow-up — 3 tins per week as part of an overall calcium-adequate diet, alongside resistance training and Vitamin D3 supplementation
- Lactose-intolerant adults targeting 1,200 mg/day calcium — 3 tins per week plus fortified plant milk and dark leafy greens
- Pregnant women — 2 tins per week, well within the U.S. Food and Drug Administration pregnancy advisory; sardines contribute calcium for fetal bone, DHA for fetal brain, without the mercury concerns of larger fish
- Patients on metformin or proton pump inhibitors (B12 depletion risk) — 3 tins per week as a strategy to maintain B12 status without injections
- Endurance athletes — 4 tins per week for the combination of protein, omega-3, sodium, and coenzyme Q10 (CoQ10)
Canned sardines vary in oil content (olive oil, sunflower oil, water, tomato sauce), salt content (most are 200-300 mg sodium per tin; "no salt added" versions are widely available), and bone density. Many products are widely distributed in supermarkets. Smaller imports from Portugal, Spain, and France are positioned as premium products with somewhat better oil quality but at significantly higher prices.
Cautions (Kidney Stones, Hyperparathyroidism)
- Calcium oxalate kidney stone history — counterintuitively, low dietary calcium increases kidney stone risk by allowing more dietary oxalate to be absorbed (calcium binds oxalate in the gut and reduces its absorption). Adequate calcium from food (not high-dose supplements) is now recognized as protective against recurrent calcium oxalate stones. In a cohort of 91,731 women followed for 12 years, the highest fifth of dietary calcium intake carried a relative risk of first kidney stones of 0.65 against the lowest fifth, while taking supplemental calcium carried 1.20 (Curhan 1997). No study testing sardines themselves in people with a stone history was read for this page.
- Primary hyperparathyroidism — elevated parathyroid hormone (PTH) with elevated serum calcium points to a possible parathyroid adenoma, and in this disease blood calcium is already high. Food amounts of calcium from sardines are not expected to cause hypercalcemia in a normal endocrine system.
- Hyperuricemia and gout — sardines are moderately high in purines (210 mg/100 g, comparable to organ meats). For people with established gout or hyperuricemia (serum uric acid >7 mg/dL), practitioners commonly describe 1-2 tins per week or lower-purine alternatives like canned salmon.
- Sodium-restricted diets — standard sardines provide 200-350 mg sodium per tin. Against a strict cardiac sodium restriction (<2,000 mg/day), no-salt-added versions and fresh sardines contribute less.
- BPA in can linings — older can linings used bisphenol A. Many producers now list BPA-free linings as a standard. Glass-jarred sardines eliminate the can-lining concern entirely.
- Fish allergy — finned fish allergy is relatively rare in adults (approximately 0.4% prevalence in the US) but can be severe. Sardines are a finned fish and can trigger that allergy; non-fish calcium sources include calcium citrate plus K2 and dietary leafy greens.
- Histamine intolerance — canned fish contains higher histamine than fresh fish, and rare scombroid poisoning has occurred with improperly stored sardines. People with histamine intolerance or mast cell activation syndrome may react to canned fish.
Key Research Papers
- Malde MK et al. (2010). Calcium from salmon and cod bone is well absorbed in young healthy men: a double-blinded randomised crossover design. Nutrition & Metabolism. — PubMed PMID: 20646299
- Heaney RP, Dowell MS, Hale CA, Bendich A (2003). Calcium absorption varies within the reference range for serum 25-hydroxyvitamin D. Journal of the American College of Nutrition. — PubMed PMID: 12672710
- Bolland MJ et al. (2010). Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ. — PubMed PMID: 20671013
- Reid IR, Bolland MJ, Grey A (2014). Effects of vitamin D supplements on bone mineral density: a systematic review and meta-analysis. The Lancet. — PubMed PMID: 24119980
- Trichopoulou A et al. (2003). Adherence to a Mediterranean diet and survival in a Greek population. NEJM. — PubMed PMID: 12826634
- Schurgers LJ et al. (2007). Vitamin K-containing dietary supplements: comparison of synthetic vitamin K1 and natto-derived menaquinone-7. Blood. — PubMed PMID: 17158229
- Weaver CM, Heaney RP (2006). Calcium in Human Health (book/chapter overview). — PubMed
- Curhan GC et al. (1997). Comparison of dietary calcium with supplemental calcium and other nutrients as factors affecting the risk for kidney stones in women. Annals of Internal Medicine. — PubMed PMID: 9092314
- Beasley JM, LaCroix AZ, Larson JC, et al. (2014). Biomarker-calibrated protein intake and bone health in the Women's Health Initiative clinical trials and observational study. American Journal of Clinical Nutrition. — PubMed PMID: 24552750
- Ross AC, Manson JE, Abrams SA, et al. (2011). The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. Journal of Clinical Endocrinology and Metabolism. — PubMed PMID: 21118827
- Larsson SC, Bergkvist L, Wolk A (2009). Long-term dietary calcium intake and breast cancer risk in a prospective cohort of women. American Journal of Clinical Nutrition. — PubMed PMID: 19056569
- Bolland MJ, Barber PA, Doughty RN, et al. (2008). Vascular events in healthy older women receiving calcium supplementation: randomised controlled trial. BMJ. — PubMed PMID: 18198394
- Kopecky SL, Bauer DC, Gulati M, et al. (2016). Lack of Evidence Linking Calcium With or Without Vitamin D Supplementation to Cardiovascular Disease in Generally Healthy Adults: A Clinical Guideline From the National Osteoporosis Foundation and the American Society for Preventive Cardiology. Annals of Internal Medicine. — PubMed PMID: 27776362
- Sim MG, Teo YN, Teo YH, et al. (2023). Association Between Calcium Supplementation and the Risk of Cardiovascular Disease and Stroke: A Systematic Review and Meta-Analysis. Heart, Lung & Circulation. — PubMed PMID: 37743221
- Hansen M, Thilsted SH, Sandström B, et al. (1998). Calcium absorption from small soft-boned fish. Journal of Trace Elements in Medicine and Biology. — PubMed PMID: 9857327
- Fa-Binefa M, Clara A, Lamas C, Elosua R (2025). Mediterranean Diet and Risk of Hip Fracture: A Systematic Review and Dose-Response Meta-Analysis. Nutrition Reviews. — PubMed PMID: 39441714
- Pes GM, Tolu F, Dore MP, et al. (2015). Male longevity in Sardinia, a review of historical sources supporting a causal link with dietary factors. European Journal of Clinical Nutrition. — PubMed PMID: 25369832
- Nieddu A, Vindas L, Errigo A, et al. (2020). Dietary Habits, Anthropometric Features and Daily Performance in Two Independent Long-Lived Populations from Nicoya peninsula (Costa Rica) and Ogliastra (Sardinia). Nutrients. — PubMed PMID: 32492804
- Poulain M, Pes GM, Grasland C, et al. (2004). Identification of a geographic area characterized by extreme longevity in the Sardinia island: the AKEA study. Experimental Gerontology. — PubMed PMID: 15489066