Sardines — Omega-3 Density
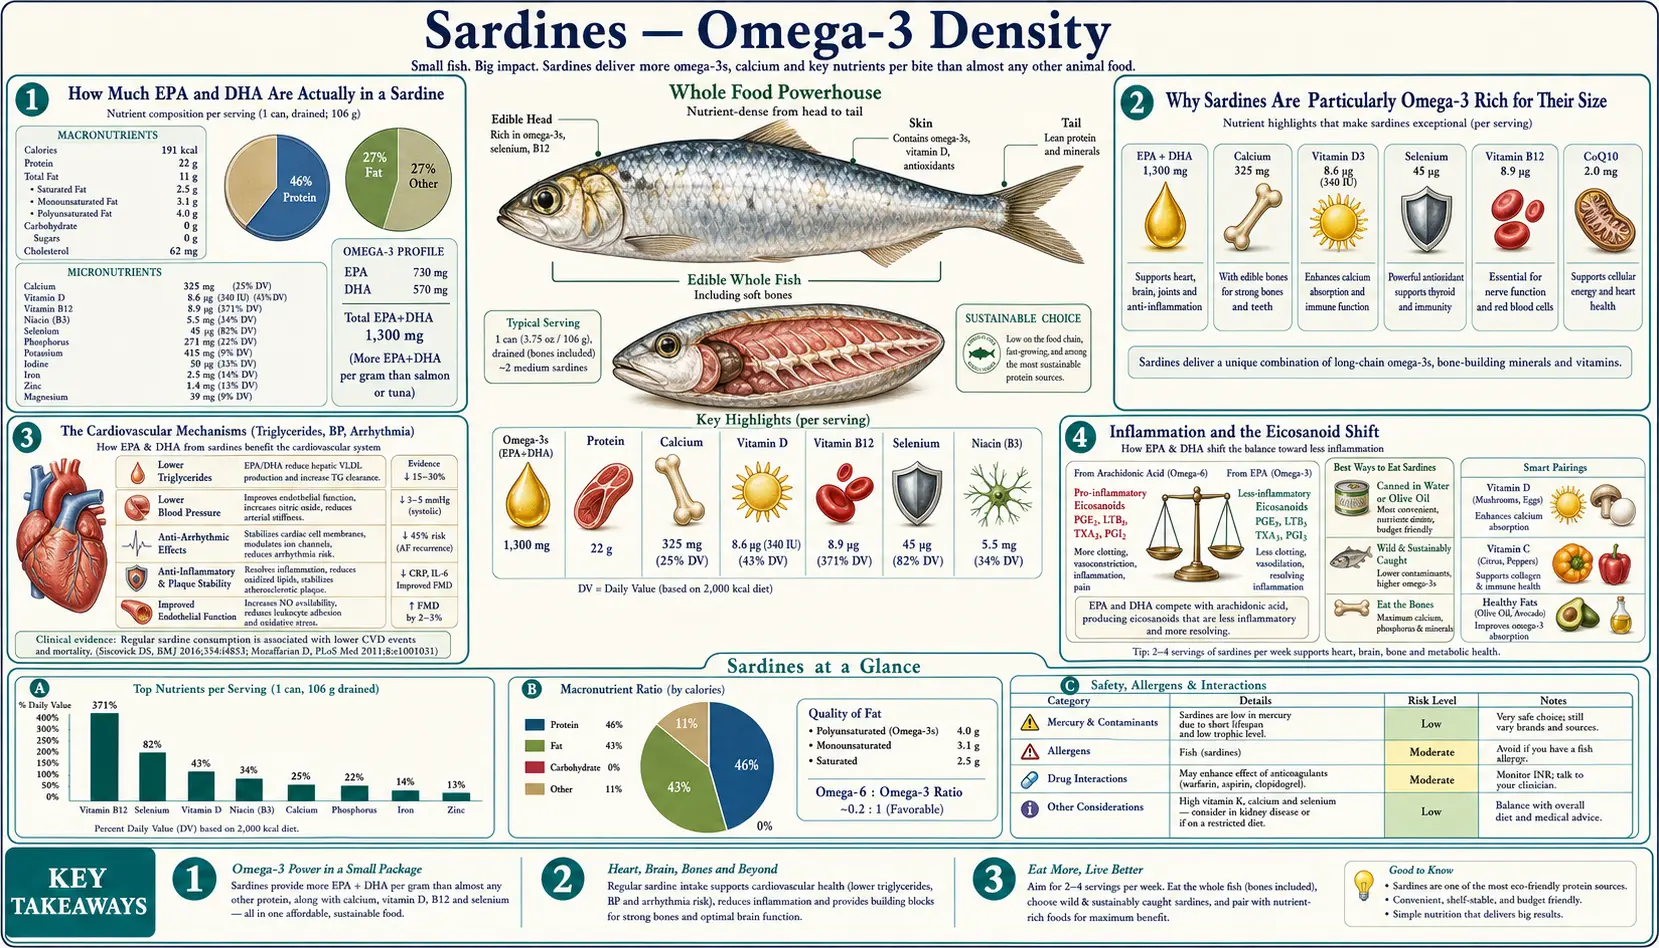
Sardines deliver approximately 980-1,360 mg of combined eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA) per 100-gram serving — a density that rivals wild Alaskan salmon and exceeds nearly every other food source per dollar spent. The combined intake from two sardine tins per week comfortably meets the American Heart Association's 2 servings/week fatty-fish recommendation that has been the cornerstone of cardiovascular dietary guidance for two decades. The mechanisms behind omega-3's effects on triglycerides, blood pressure, inflammatory eicosanoid production, sudden cardiac death risk, and cognitive decline are now well-characterized at the molecular level — this page walks through how that biochemistry translates into clinical outcomes, why many practitioners and readers favour a food-source strategy (sardines, mackerel, herring, salmon, anchovies) over fish-oil capsules, and what the omega-3 index blood test measures.
Table of Contents
- How Much Eicosapentaenoic Acid and Docosahexaenoic Acid Are Actually in a Sardine
- Why Sardines Are Particularly Omega-3 Rich for Their Size
- The Cardiovascular Mechanisms (Triglycerides, Blood Pressure, Arrhythmia)
- Inflammation and the Eicosanoid Shift
- Cognitive Protection and Docosahexaenoic Acid in Brain Phospholipids
- Sudden Cardiac Death Reduction
- Food Source vs Fish-Oil Capsules
- The Omega-3 Index and Practical Targets
- Cautions (Bleeding Risk, AFib Signal)
- Key Research Papers
- Connections
- Featured Videos
How Much Eicosapentaenoic Acid and Docosahexaenoic Acid Are Actually in a Sardine
The U.S. Department of Agriculture (USDA) FoodData Central database lists canned Atlantic sardines (packed in oil, drained, with bones) as containing approximately 982 mg total long-chain omega-3 fatty acids per 100 g, broken down as roughly 473 mg eicosapentaenoic acid (EPA, 20:5n-3) and 509 mg docosahexaenoic acid (DHA, 22:6n-3). Pacific sardines and Mediterranean sardines from cold-water seasonal catch can run somewhat higher (up to 1,360 mg/100 g for fish caught at peak feeding season).
A standard 3.75-ounce tin (92 g of drained fish, per USDA) therefore provides roughly 900 mg of eicosapentaenoic acid + docosahexaenoic acid combined — close to the 1 g/day target the American Heart Association recommends for adults with established coronary heart disease and more than twice the 400 mg/day general-prevention threshold.
For comparison, on a per-100-g basis (USDA FoodData Central figures where marked):
- Atlantic mackerel — 898 mg eicosapentaenoic acid + 1,400 mg docosahexaenoic acid (USDA, raw; the highest figure in this list)
- Atlantic herring — 709 mg eicosapentaenoic acid + 862 mg docosahexaenoic acid (USDA, raw)
- Wild Atlantic salmon — 1,840 mg
- Farmed Atlantic salmon — 862 mg eicosapentaenoic acid + 1,100 mg docosahexaenoic acid (USDA, raw; high due to fish-oil enriched feed, but with PCB and contaminant concerns)
- Pacific sardines — 1,360 mg
- Atlantic canned sardines — 982 mg
- Albacore tuna — 870 mg (with significant mercury concern)
- Skipjack/light canned tuna — 270 mg
- Cod (Atlantic) — 158 mg
- Tilapia — 5 mg eicosapentaenoic acid + 86 mg docosahexaenoic acid (USDA, raw)
Sardines outperform tilapia, cod, and most farmed fish, and are competitive with wild salmon at roughly one-quarter the price. The omega-3-per-dollar ratio is unmatched.
Why Sardines Are Particularly Omega-3 Rich for Their Size
Cold-water fish accumulate omega-3 polyunsaturated fatty acids in their cell membranes and fat depots as a metabolic adaptation. Eicosapentaenoic acid and docosahexaenoic acid have multiple double bonds that maintain membrane fluidity at low temperatures — without them, the fish's cell membranes would solidify at North Atlantic or Pacific water temperatures. Saturated and monounsaturated fats solidify at higher temperatures and would not preserve enzyme function in cold-water species.
Sardines are particularly omega-3 dense for several reasons:
- They feed on phytoplankton and zooplankton — the primary biosynthetic source of eicosapentaenoic acid and docosahexaenoic acid in the marine food chain. Larger predator fish accumulate omega-3 by consuming sardines, anchovies, and other forage fish. Sardines are the first link — they get their omega-3 directly from the phytoplankton.
- They are an oily fish — total fat content is roughly 11% of body weight (vs ~1% for cod or tilapia). USDA lists 11.4 g of fat per 100 g of canned Atlantic sardines — 1.53 g saturated, 3.87 g monounsaturated and 5.15 g polyunsaturated — of which 473 mg is eicosapentaenoic acid and 509 mg is docosahexaenoic acid. Omega-3 is a minority of the fat, but a large amount for a food.
- Whole-body consumption — canned sardines include the skin, bones, and viscera (in some preparations), all of which concentrate omega-3 in addition to the muscle tissue. Filleted fish loses the skin-associated omega-3.
- Cold-water habitat — sardines from cold Mediterranean, Pacific, and Atlantic waters have higher omega-3 than warm-water sardines.
- Wild-caught only — commercial sardine fisheries are not aquaculture. Wild diet maintains the natural omega-3 profile, unlike farmed salmon (whose omega-3 content depends on the fish-meal/fish-oil percentage of the commercial feed).
The processing matters too. Canning in olive oil preserves the omega-3 better than canning in water, which can leach fatty acids into the packing medium. Sardines packed in soybean or sunflower oil dilute the omega-3 with omega-6, reducing the favorable omega-3-to-omega-6 ratio. This is why sardines packed in olive oil or in their own juices are often preferred.
The Cardiovascular Mechanisms (Triglycerides, Blood Pressure, Arrhythmia)
Long-chain omega-3 fatty acids exert several distinct effects on cardiovascular physiology, each with a separate molecular mechanism:
- Triglyceride reduction — eicosapentaenoic acid and docosahexaenoic acid suppress hepatic very-low-density lipoprotein (VLDL) synthesis by inhibiting the SREBP-1c transcription factor and by direct competition with omega-6 fatty acids for triglyceride esterification. The effect is dose-dependent: 1 g/day produces minimal reduction, 2-4 g/day produces 20-50% triglyceride reduction in patients with baseline TG >200 mg/dL. This is the mechanism behind prescription icosapent ethyl and prescription omega-3-acid ethyl esters, both U.S. Food and Drug Administration-approved for severe hypertriglyceridemia.
- Blood pressure reduction — meta-analysis of 70 trials (Miller et al. 2014) found that 2 g/day omega-3 reduces systolic blood pressure (BP) by approximately 4.5 mmHg and diastolic by 3.0 mmHg in patients with hypertension. The mechanism involves enhanced endothelial nitric oxide production, reduced sympathetic tone, and modulation of the renin-angiotensin system.
- Antiarrhythmic effect — eicosapentaenoic acid and docosahexaenoic acid stabilize cardiac myocyte membranes by modulating sodium channel inactivation kinetics and reducing intracellular calcium overload during ischemia. This is the proposed mechanism behind the dramatic sudden-cardiac-death reductions observed in GISSI-Prevenzione and other trials.
- Reduced platelet aggregation — eicosapentaenoic acid competes with arachidonic acid for cyclooxygenase, producing thromboxane A3 (weak platelet aggregator) instead of thromboxane A2 (strong aggregator). The net effect is mild antiplatelet activity.
- Anti-inflammatory eicosanoid shift — covered in the next section.
The cumulative effect across these mechanisms is meaningful but not as dramatic as some early trials suggested. The 2018 ASCEND trial and 2019 VITAL trial, both of 1 g/day omega-3 versus placebo in low-risk primary prevention populations, found no significant reduction in their main cardiovascular outcomes (ASCEND rate ratio 0.97, P=0.55; VITAL hazard ratio 0.92, P=0.24). The benefit appears to be larger in patients with established disease, elevated triglycerides, or other high-risk features — which is the population that the REDUCE-IT trial targeted (and where icosapent ethyl produced a 25% relative risk reduction in major adverse cardiovascular events).
Inflammation and the Eicosanoid Shift
The omega-6 arachidonic acid (AA, 20:4n-6) is the precursor for the "inflammatory" eicosanoid family: prostaglandins of the 2-series (PGE2, PGI2, TXA2), leukotrienes of the 4-series (LTB4), and lipoxins. These molecules drive vasoconstriction, platelet aggregation, neutrophil chemotaxis, and the classical inflammatory cascade.
Eicosapentaenoic acid (20:5n-3) competes with AA for the same enzymes (cyclooxygenase, lipoxygenase) and produces the 3-series prostaglandins (PGE3, PGI3, TXA3) and 5-series leukotrienes (LTB5), which are 10-100x less inflammatory than their omega-6 counterparts. Higher tissue eicosapentaenoic acid content shifts eicosanoid production toward the less-inflammatory species.
Beyond the original "competitive enzyme inhibition" model, the past decade has identified a separate family of pro-resolving lipid mediators derived from eicosapentaenoic acid and docosahexaenoic acid: resolvins (E-series from eicosapentaenoic acid, D-series from docosahexaenoic acid), protectins (from docosahexaenoic acid), and maresins (from docosahexaenoic acid). These are not anti-inflammatory in the classical sense — they actively promote the resolution phase of inflammation by enhancing neutrophil clearance by macrophages (efferocytosis), reducing pro-inflammatory cytokine production, and promoting tissue repair. The discovery of these pathways by Charles Serhan and colleagues fundamentally reshaped the conceptual model of inflammation from "on-off" to "initiation followed by active resolution."
The clinical translation is that adequate dietary eicosapentaenoic acid and docosahexaenoic acid provide the substrate for resolvin synthesis. Patients with chronic low-grade inflammation (rheumatoid arthritis, inflammatory bowel disease, metabolic syndrome, autoimmune conditions, post-surgical recovery) may benefit from sustained dietary omega-3 intake at levels of 1-2 g/day. Sardines, mackerel, herring, salmon, and anchovies are the practical food-source strategy.
Cognitive Protection and Docosahexaenoic Acid in Brain Phospholipids
Docosahexaenoic acid is the dominant omega-3 in the brain — approximately 10-15% of total brain phospholipid fatty acid is docosahexaenoic acid, concentrated in synaptic membranes and the photoreceptor outer segments of the retina. Docosahexaenoic acid is structurally critical for neuronal membrane fluidity, neurotransmitter receptor function, and synaptic vesicle trafficking. The brain accumulates docosahexaenoic acid preferentially from the bloodstream via the MFSD2A transporter expressed at the blood-brain barrier.
Adequate dietary docosahexaenoic acid is most clearly important in two developmental windows: fetal brain development (third trimester, when fetal brain docosahexaenoic acid accumulation peaks) and infant brain development (first 18 months of life, supported by breast milk docosahexaenoic acid content which directly reflects maternal intake). Beyond these developmental windows, the question is whether dietary docosahexaenoic acid influences cognitive decline in older adults.
The observational evidence is suggestive. The Rotterdam Study (5,386 Dutch participants aged 55 or older, free of dementia at the start) found that fish consumption was associated with approximately 60% lower risk of incident dementia (relative risk 0.4) after an average of 2.1 years of follow-up. Multiple other observational cohorts (Framingham, Chicago Health and Aging Project, EPIC) have reproduced this association.
The randomized trial evidence is more equivocal. Large randomized trials of docosahexaenoic acid or fish-oil supplementation in older adults have failed to show significant cognitive benefit; one example is the Multidomain Alzheimer Preventive Trial (MAPT), in 1,680 adults aged 70 or older without dementia who had a memory complaint, a limitation in one everyday activity, or slow walking speed. The most likely interpretation is that docosahexaenoic acid supplementation late in the disease course, after substantial neurodegeneration has occurred, cannot reverse the damage — while sustained lifelong intake of dietary omega-3 from fish may modestly delay or prevent cognitive decline through mechanisms operating decades earlier.
The practical takeaway: regular sardine, salmon, and small-oily-fish consumption from middle age onward is consistent with the best available observational evidence for cognitive protection. Pure docosahexaenoic acid supplementation as a cognitive intervention in already-impaired patients is not supported by current trial data.
Sudden Cardiac Death Reduction
Sudden cardiac death (SCD) accounts for roughly half of all cardiovascular deaths in the developed world — an estimated 350,000 deaths per year in the United States alone. Most occur in patients with established but unrecognized coronary disease, triggered by acute ischemia precipitating a fatal arrhythmia (typically ventricular fibrillation).
The first large observational signal came from the Physicians' Health Study: a nested case-control analysis of 94 men who died suddenly and 184 matched controls found that men whose blood long-chain omega-3 levels were in the highest quartile had approximately 81% lower risk of sudden death than those in the lowest quartile (adjusted relative risk 0.19). The signal was for SCD specifically, not for overall coronary mortality — suggesting an antiarrhythmic mechanism distinct from atherosclerosis-modifying effects.
The GISSI-Prevenzione trial (n=11,324 post-MI patients in Italy) was open-label: patients were randomly assigned to 1 g/day omega-3, vitamin E, both, or no supplement (the control group) for 3.5 years. Omega-3 lowered the risk of death by 14% and of cardiovascular death by 17% in the main two-way analysis (20% and 30% in the four-way analysis). The effect appeared within 4 months of starting supplementation, faster than would be expected for atherosclerosis modification.
The proposed mechanism is membrane stabilization. Eicosapentaenoic acid and docosahexaenoic acid incorporated into cardiac myocyte phospholipid membranes modulate the sodium and L-type calcium channels that determine cellular electrical excitability. Patients with adequate tissue omega-3 levels have higher arrhythmia threshold — the same ischemic insult that triggers VF in a depleted patient may not in an omega-3-replete patient.
The Omega-3 Index (red blood cell eicosapentaenoic acid+docosahexaenoic acid as a percentage of total fatty acids) is the validated biomarker. Levels >8% are associated with the lowest SCD risk; levels <4% carry the highest risk. The average American falls between 4-6%; the average Japanese person (sustained high fish intake) falls around 9-10%. Regular sardine consumption can move an American adult from 5% to 7-8% within 3-6 months without supplementation.
Food Source vs Fish-Oil Capsules
Multiple lines of evidence suggest that food-source omega-3 (oily fish 2-4x/week) outperforms equivalent doses of fish-oil capsule supplementation:
- The capsule trials are mostly null or modest — ASCEND (n=15,480 diabetics, 1 g/day omega-3) and VITAL (n=25,871 general population, 1 g/day omega-3) both reported essentially null primary cardiovascular endpoints, while observational data on dietary fish intake consistently shows benefit.
- Capsule omega-3 may be oxidized — independent testing (Albert et al. 2015) found that a substantial fraction of commercial fish-oil capsules exceed industry oxidation standards, potentially delivering lipid peroxides rather than intact eicosapentaenoic acid/docosahexaenoic acid. Refrigeration extends shelf life. Triglyceride-form supplements are more stable than ethyl-ester form.
- Food sources include cofactors — oily fish provides selenium (cofactor for glutathione peroxidase, which protects PUFAs from oxidation), Vitamin E (antioxidant for membrane PUFAs), and other antioxidant micronutrients. Isolated fish-oil capsules do not.
- The REDUCE-IT trial used a different molecule — the cardiovascular benefit seen in REDUCE-IT (icosapent ethyl, a purified eicosapentaenoic acid ethyl ester at 4 g/day) is not directly translatable to other omega-3 products. The negative STRENGTH trial used a different eicosapentaenoic acid+docosahexaenoic acid mixture and showed no benefit at similar dosing.
- Fish also contains other beneficial nutrients — protein, Vitamin D, B12, calcium (in sardines specifically), selenium, taurine, coenzyme Q10 (CoQ10). The benefit of "eating fish" is not reducible to the omega-3 content alone.
The American Heart Association and European Society of Cardiology advice puts oily fish (about 2 servings per week) first as the source of omega-3 for heart health. Prescription omega-3 is a separate category: prescription icosapent ethyl is approved for severe hypertriglyceridemia (triglycerides of 500 mg/dL or more, per its label), and the REDUCE-IT trial gave it to statin-treated patients with heart disease, or with diabetes plus other risk factors, whose fasting triglycerides were 135-499 mg/dL. Fish-oil capsules are also used by people who cannot eat fish for allergy, ethical, or accessibility reasons.
The Omega-3 Index and Practical Targets
The Omega-3 Index, developed by William Harris and Clemens von Schacky, measures red blood cell membrane eicosapentaenoic acid+docosahexaenoic acid as a percentage of total fatty acids. Because RBCs have a 120-day lifespan, the index reflects 3-4 months of average dietary omega-3 intake — a more reliable biomarker than serum levels, which fluctuate with the most recent meal.
Validated risk strata:
- <4% — high cardiovascular risk; typical of populations with minimal fish intake
- 4-8% — intermediate risk; typical of most Americans
- >8% — low risk; typical of populations with regular fatty-fish consumption (Norway, Japan, Mediterranean coast)
Two sardine tins per week (delivering approximately 2 g eicosapentaenoic acid+docosahexaenoic acid averaged across the week) can raise an Omega-3 Index from approximately 5% to 7-8% over 3-6 months of consistent intake. Three tins per week reliably moves most patients above 8%.
The omega-3 index is offered as a blood test by several commercial laboratories. It measures the share of eicosapentaenoic acid and docosahexaenoic acid in red blood cell membranes; because the result reflects the previous 3-4 months of intake, a repeat test 3-6 months after a change in diet shows how far the level has moved. For more on the broader role of omega-3 in cardiometabolic health, see our Omega-3 Fatty Acids page.
Cautions (Bleeding Risk, AFib Signal)
- Bleeding risk at high doses — omega-3 supplementation at >3 g/day combined with warfarin, direct oral anticoagulants, or dual antiplatelet therapy can produce a mild additive antiplatelet effect. Surgical guidance has historically called for stopping fish oil 7-10 days before elective surgery; practice on this varies. Food-source omega-3 at typical dietary doses does not pose meaningful bleeding risk.
- Atrial fibrillation signal — the STRENGTH and REDUCE-IT trials, both of high-dose omega-3 (4 g/day), reported a small but statistically significant increase in atrial fibrillation (in REDUCE-IT, hospitalization for atrial fibrillation or flutter in 3.1% vs 2.1%, P=0.004). The OMEMI trial (1.8 g/day in heart-attack survivors aged 70-82) found new atrial fibrillation in 7.2% on omega-3 vs 4.0% on placebo, a difference that was not statistically significant (hazard ratio 1.84, P=0.06). The mechanism is unclear and the absolute risk is small. The icosapent ethyl label warns of this risk and states it was greater in people who had already had atrial fibrillation or flutter; food-source intake at typical levels does not raise this concern.
- Fishy aftertaste / belching — the most common subjective complaint with fish-oil capsules. Less of an issue with food-source intake. Higher-quality (lower-oxidation) products and refrigerated capsules are reported to help.
- Pregnancy considerations — sardines are a U.S. Food and Drug Administration (FDA) "Best Choices" fish, safe for pregnancy at 2-3 servings per week. The docosahexaenoic acid in sardines actively supports fetal brain development. The FDA/EPA fish advice places the high-mercury fish (king mackerel, marlin, swordfish, shark, tilefish, bigeye tuna) in its "Choices to Avoid" group for pregnancy.
- Drug interactions — omega-3 can mildly potentiate the blood pressure-lowering effect of antihypertensives, the glucose-lowering effect of some diabetes medications, and the antiplatelet effect of aspirin or nonsteroidal anti-inflammatory drugs (NSAIDs). None of these are typically problematic but warrant awareness.
- Cost-effectiveness — pure observation, not safety: sardines deliver omega-3 at roughly $1-2 per gram, while pharmaceutical-grade icosapent ethyl runs $300-400/month for 4 g/day. For most patients targeting general cardiovascular omega-3 adequacy, sardines are dramatically more cost-effective.
Key Research Papers
- GISSI-Prevenzione Investigators (1999). Dietary supplementation with n-3 polyunsaturated fatty acids and vitamin E after myocardial infarction. The Lancet. — PubMed PMID: 10465168
- Yokoyama M et al. (2007). Effects of eicosapentaenoic acid on major coronary events in hypercholesterolaemic patients (JELIS). The Lancet. — PubMed PMID: 17398308
- Bhatt DL et al. (2019). Cardiovascular Risk Reduction with Icosapent Ethyl for Hypertriglyceridemia (REDUCE-IT). NEJM. — PubMed PMID: 30415628
- Miller PE et al. (2014). Long-chain omega-3 fatty acids EPA and DHA and blood pressure: a meta-analysis of randomized controlled trials. American Journal of Hypertension. — PubMed PMID: 24610882
- Albert CM et al. (2002). Blood levels of long-chain n-3 fatty acids and the risk of sudden death. NEJM. — PubMed PMID: 11948270
- Harris WS, von Schacky C (2004). The Omega-3 Index: a new risk factor for death from coronary heart disease? Preventive Medicine. — PubMed PMID: 15208005
- Serhan CN (2014). Pro-resolving lipid mediators are leads for resolution physiology. Nature. — PubMed PMID: 24899309
- Kalmijn S et al. (1997). Dietary fat intake and the risk of incident dementia in the Rotterdam Study. Annals of Neurology. — PubMed PMID: 9392577
- Manson JE et al. (2019). Marine n-3 Fatty Acids and Prevention of Cardiovascular Disease and Cancer (VITAL). NEJM. — PubMed PMID: 30415637
- Mozaffarian D, Wu JH (2011). Omega-3 fatty acids and cardiovascular disease: effects on risk factors, molecular pathways, and clinical events. Journal of the American College of Cardiology. — PubMed PMID: 22051327
- Calder PC (2017). Omega-3 fatty acids and inflammatory processes: from molecules to man. Biochemical Society Transactions. — PubMed PMID: 28900017
- Nicholls SJ et al. (2020). Effect of High-Dose Omega-3 Fatty Acids vs Corn Oil on Major Adverse Cardiovascular Events in Patients at High Cardiovascular Risk (STRENGTH). JAMA. — PubMed PMID: 33190147
PubMed Topic Searches
Connections
- All Food
- Sardines Overview
- Sardines Benefits Hub
- Sardines — Calcium & Bones
- Sardines — Vitamin D & B12
- Sardines — Low Mercury
- Omega-3 Fatty Acids
- Salmon
- Herring
- Cod
- Tuna
- Cardiology
- Atrial Fibrillation
- Hypertension
- Neurology
- Rheumatology
- Lipid Panel
- History
- Nutrients